Clostridium difficile infection (CDI) presents a considerable clinical challenge. Between 2000 and 2010, the number of hospitalizations related to CDI in the United States doubled, and predictions for 2011 and 2012 suggest rapidly increasing growth. 1 Beyond this increase in the total burden of this disease, its associated mortality doubled between 2000 and 2005, and doubled yet again between 2007 and 2011, a phenomenon most likely related to the emergence in the early 2000s of the hypervirulent NAP1 strain of C. difficile.Reference Lessa, Mu and Bamberg 2 – Reference Hall, Curns, McDonald, Parashar and Lopman 4
The implications of CDI are particularly pronounced among the elderly, whose risk of contracting this disease is a staggering 26-fold higher than that for 1–17-year-olds, 13 times that among 18–44-year-olds, and 4 times that among 45–64-year-olds.Reference Lessa, Mu and Bamberg 2 People who are 65 years old or older, in fact, represent more than 50% of all CDI cases in the United States, or nearly 260,000 cases annually.Reference Lessa, Mu and Bamberg 2 This number is expected to continue growing not only because of the steady rise in CDI incidence, but also because of changing demographic characteristics, with this age group likely to double in size in the United States from 40 million in year 2010 to 83 million in 2050. 5
Such combined growth will certainly present a formidable burden to our already strained healthcare financing system in general, and to Medicare in particular because it represents the primary payer for services in the elderly. The current estimate of the total financial burden of CDI in the United States is up to nearly $6 billion annually, and this represents only expenses associated with hospitalization.Reference Kwon, Olsen and Dubberke 6
As the Centers for Medicare and Medicaid Services continue to work toward reducing healthcare expenditures while at the same time improving the quality of healthcare delivery, one key step is to attempt to fully understand the complex range of clinical and economic outcomes associated with CDI in the elderly. To address this gap in needed evidence, we conducted a population-based cohort study among Medicare fee-for-service patients to quantify the full annual burden of CDI the United States and focused on costs related to both inpatient and outpatient care.
METHODS
We conducted a population-based retrospective cohort study among elderly adults in the United States, age 65 years or older, enrolled in Medicare fee-for-service, to calculate the clinical and economic burden of CDI. Because this study used already existing fully deidentified data, the study was exempt from institutional review board consideration.
Data Source
We examined the Medicare 5% random sample of data from Centers for Medicare and Medicaid Services for years 2008 through 2010. This includes hospital insurance (Part A—payment for hospital, skilled nursing facility [SNF], home health and hospice care), supplementary medical insurance (Part B—optional coverage; pays for physician, outpatient hospital, home health and laboratory tests, and durable medical equipment), and prescription medications (Part D—optional coverage) for eligible enrollees. Because some Medicare enrollees may also be covered by Medicaid, we linked the Medicare 5% sample with 100% of the Medicaid Claims data.
Cohort and Outcome Definitions
Patients were included if they were aged 65 years or older as of January 1, 2009, and covered continuously by Medicare fee-for-service (Parts A and B) from January 1, 2008, through December 31, 2009. The primary outcome of interest was mortality at 30, 60, and 180 days and at 1 year following the onset of the index CDI episode. Secondary outcomes were costs attributable to CDI within 2 months and 1 year following the incident episode. We defined an incident CDI episode by at least 1 appearance of the International Classification of Diseases, Ninth Revision, Clinical Modification (ICD-9-CM) code 008.45 in the Medicare or Medicaid claims with no other occurrences within the preceding 12 months. All other appearances of the corresponding ICD-9-CM code were deemed repeat episodes. The location of the onset (eg, community, hospital) of the incident CDI case was examined. CDI was further subdivided into healthcare-associated (HA) and community-associated. The disease was classified as HA if there was evidence of an acute or a SNF hospitalization within 12 weeks preceding the incident CDI episode, or if the ICD-9-CM code for CDI was not the principal hospitalization diagnosis. In the absence of such exposure or if the CDI code appeared as the principal diagnosis for a hospitalization, the infection was considered community-associated.
The first date of CDI claim was used as the index date for the CDI cohort. The eligible Medicare enrollees without a CDI diagnosis from January 1, 2008, through December 31, 2010, served as the control group and were randomly assigned an index date in 2009. The 12 months prior to this index date was used as an observation period for baseline demographic and clinical characteristics and healthcare utilization parameters. Patients were followed up for 12 months after their index date or until death for the outcomes of interest.
Statistical Analyses
We compared the baseline characteristics of patients with CDI and those without. The χ2 test evaluated differences in categorical variables and the t test in continuous variables. In addition to P values, standardized differences were calculated for each variable. Standardized difference is defined as an absolute difference in sample means between the groups divided by the estimate of pooled standard deviation; they are used to distinguish clinical versus statistical significance in large samples, where the risk of type 1 error is high and the threshold of 10% or greater is recognized as a clinically important difference.Reference Normand, Landrum and Guadagnoli 7
To compute attributable mortality and costs, we used a greedy match method to develop a CDI propensity model, and matched CDI-positive with CDI-negative patients on their propensity scores (PS) at a 1:1 ratio to within 0.001 unit of PS.Reference Baser 8 The PS was calculated via a logistic regression model of factors associated with the risk of CDI, including patient age, gender, race, census region, and comorbidities using Charlson comorbidity score.Reference Deyo, Cherkin and Ciol 9 Because inflammatory bowel disease is known to predispose to CDI, we included the presence of inflammatory bowel disease, defined as evidence of either ulcerative colitis and/or Crohn disease ICD-9-CM codes.Reference Berg, Kelly and Farraye 10 Such other known CDI risk factors as prior hospitalizations, nursing home stays, antibiotic exposure, and gastric acid suppressant use within 90 days and within 1 year prior to the incident CDI were also included in the regression model. Healthcare utilization parameters examined in the observation period were claims ($US amount) per month stratified by the location of the encounter (eg, inpatient, outpatient, SNF), as well as total healthcare costs. To assess how well the PS matching was able to control for the various confounding factors, we compared baseline characteristics between CDI-positive and matched CDI-negative groups. We derived CDI-attributable costs and mortality by computing the differences in these values between the propensity-matched CDI-positive and CDI-negative groups.
Statistical significance was set a priori at the alpha <.05. All analyses were performed with SAS, version 9.3 (SAS Institute).
RESULTS
Among the 1,165,165 patients meeting the inclusion criteria, 6,838 (0.6%) had at least 1 episode of CDI during the study period (82.5% HA CDI). Of these CDI cases we were able to PS match 6,761 (98.9%; 82.3% HA CDI) to 6,761 patients without CDI. Online Supplementary Table 1 shows baseline characteristics of the comparator groups before and after the matching procedure.
Before matching, there were many differences between those with and those without a CDI episode (Online Supplementary Table 1). Age, the proportion of women, the burden of comorbidities, prior hospitalization, antibiotic use, nursing home admissions, and healthcare utilization were all considerably higher in the CDI-positive than the CDI-negative group. After PS matching, most of the previously observed differences between the groups attenuated substantially or disappeared altogether (Online Supplementary Table 1). Although some of the differences retained statistical significance at P<.05 even after PS matching, most likely due to the large sample size, the only parameters to retain the standard difference with a threshold of 10% or greater were the number of days spent in a hospital both over the 12 months prior to the index CDI episode (mean [±SD], 20.1±20.3 CDI-positive vs 18.0±22.8 CDI-negative) and over the 90 days prior to it (14.4±13.0 CDI-positive vs 10.8±10.6 CDI-negative).
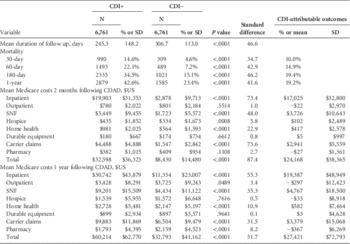
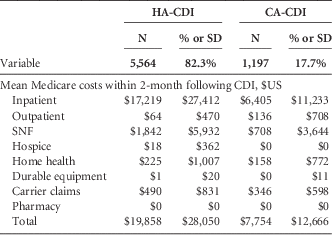
The outcomes of interest in the PS-matched groups exhibited striking differences, however (Table 1). At each time point examined (30, 60, and 180 days and 1 year), mortality among patients with a CDI episode was 2-3 times that observed in the CDI-negative group (eg, 42.6% CDI-positive vs 23.4% CDI-negative, P<.001, or 19.2% CDI-attributable 1-year mortality). As for healthcare costs over the ensuing year, inpatient stays represented the highest Medicare expenses in both CDI-positive (mean [±SD], $30,742±$43,879) and CDI-negative ($11,354±$23,007) groups, P<.001, with the CDI-attributable inpatient cost of $19,387±$48,949 to Medicare. Though several other cost centers differed between the groups, the most striking differences were detected in the SNF costs ($9,201±$15,509 CDI-positive vs $4,434±$11,122, P<.001, CDI-negative attributable cost of $4,767±$18,500), and carrier claims (claims made by clinicians not affiliated with hospitals), ($9,883±$11,869 CDI-positive vs $6,504±$9,479 CDI-negative, P<.001, CDI-attributable cost of $3,379±$15,068). Adding all of these separate costs together produced the annual CDI-attributable Medicare cost of $27,421±$72,793 per patient (Table 1). The cost differences exhibited a similar pattern at 2 months following the incident CDI (Table 1), with CDI-specific costs for an HA-CDI episode ($19,858±$28,050) nearly triple those for a community-associated-CDI case ($7,754±$12,666) (Table 2). The corresponding individual cost centers followed a pattern similar to the itemized costs in the overall CDI group (Table 2). Total Medicaid costs were in the range of $1,000 and $5,000 at 2 months and 1 year, respectively, and did not differ between the 2 groups at either time point (data not shown).
CDI Attributable Mortality and Costs

NOTE. CDAD, Clostridium difficile–associated diarrhea; CDI, C. difficile infection; SNF, skilled nursing facility.
CDI-Specific Medicare Costs Over 2 Months Following Incident Episode, Stratified by HA vs CA Disease

NOTE. CA, community-associated; CDI, Clostridium difficile infection; HA, healthcare-associated; SNF, skilled nursing facility.
DISCUSSION
In the current study we demonstrate that in the Medicare population, CDI is associated with a substantial rise in the risk of mortality and a major impact on total Medicare costs over the year following the index event. That is, CDI nearly doubles the risk of death and increases total Medicare spending by almost $30,000 per patient. Though most of this expenditure is concentrated in the hospital, other settings contribute substantially as well, particularly SNF (nearly $5,000) and unaffiliated physician claims (>$3,000). Extrapolating these values to the national CDI burden translates to 46,000 potential deaths, and more than $6 billion (2009 $US) in attributable healthcare costs among 240,000 Medicare patients with CDI.
Several prior studies have addressed both mortality and costs associated with CDI. Kwon and colleaguesReference Kwon, Olsen and Dubberke 6 reviewed studies published between 1997 and 2008, thus straddling the periods before and after the emergence of the NAP1 strain. They identified 8 studies reporting CDI-attributable mortality, 3 of which occurred in the epidemic setting. In these reports mortality ranged from 1.5% in-hospital to 16.7% at 1 year.Reference Miller, Hyland, Ofner-Agostini, Gourdeau and Ishak 11 – Reference Loo, Poirier and Miller 18 Our estimates of all-cause mortality among CDI patients (at 30 days: 15%; at 180 days: 35%; at 1 year: 43%) are similar to those reported by others (at 30 days: 16.3%-17.5%; at 180 days: 38%; at 1 year: 37.3%), regardless of the interval of observation.Reference Dubberke, Butler and Reske 14 , Reference Gravel, Miller and Simor 15 , Reference Pepin, Valiquette and Cossette 17 , Reference Loo, Poirier and Miller 18 Therefore, the difference in the corresponding attributable mortality between those studies and ours lies clearly in the comparator groups. That is, all studies reviewed by Kwon et alReference Kwon, Olsen and Dubberke 6 focused on hospitalized cohorts of patients, both with and without CDI. Because our study was not limited to inpatient population, most of our CDI-negative patients were not identified while in the hospital, putting them at a much lower risk for death.
In addition to studies reporting mortality, Kwon and colleaguesReference Kwon, Olsen and Dubberke 6 also examined studies reporting CDI-attributable costs.Reference Kyne, Hamel, Polavaram and Kelly 13 , Reference Dubberke, Butler and Reske 14 , Reference Tabak, Zilberberg, Johannes, Sun and McDonald 16 , Reference Song, Bartlett, Speck, Naegeli, Carroll and Perl 19 – Reference Pakyz, Carroll and Harpe 23 The range of costs associated with CDI in the reviewed studies was vast, spanning from $6,000 to more than $33,000 in 2012 $US. Each of the 8 studies included, however, focused solely on hospital costs associated with CDI, and most limited cost estimates to a single index CDI hospitalization. The authors of the review noted that those studies utilizing propensity scoring adjusted for the highest number of covariates and hence were associated with the lowest estimates for attributable costs.Reference Kwon, Olsen and Dubberke 6 They explained this phenomenon at least in part by invoking a high degree of residual confounding in studies with fewer covariates. Our findings, however, contradict this hypothesis. We propensity-adjusted for fully 77 covariates, a number comparable with those used by Dubberke et alReference Dubberke, Butler and Reske 14 and Tabak and colleagues,Reference Tabak, Zilberberg, Johannes, Sun and McDonald 16 and, nonetheless, arrived at a substantially higher cost estimate. More likely, the differences between our cost estimates and theirs lie in the patient mix. That is, Tabak et alReference Tabak, Zilberberg, Johannes, Sun and McDonald 16 in a 2008 multicenter study quantified only the costs of index CDI hospitalization and calculated those to be $6,117. On the other hand, Dubberke and colleaguesReference Dubberke, Butler and Reske 14 in a single-center study in 2003 computed CDI-attributable hospitalization costs over 180 days following the initial hospitalization with a CDI episode to be $2,454. The design of each of these earlier studies, therefore, severely limits the generalizability of their findings. In contrast, our study is unique in that it represents the entire Medicare population in the United States and does not limit the cohort to only those whose CDI occurred in the hospital. In this way, we help to expand the understanding of costs associated with CDI in this large and growing population, including interactions with the healthcare system at multiple levels across its spectrum.
To the best of our knowledge, ours is the first study to quantify the totality and scope of the cost burden attributable to CDI. Indeed, more than 70% of the attributable cost lies in the inpatient domain. This is accounted for in large part by the fact that most of the initial CDI occurred in the inpatient setting. However, the financial implications of CDI are clearly more complex than the implications of the first hospitalization complicated by this infection. Specifically, many with CDI survive to discharge and more than one-quarter may require a readmission within 30 days.Reference Zilberberg, Shorr, Micek and Kollef 24 Our $17,000 estimate of the CDI-attributable 2-month inpatient costs includes the cost of these early readmissions, just as the $19,000 CDI-attributable 1-year inpatient costs very likely include the 45% prevalence of 180-day readmissions.Reference Olsen, Yan, Reske, Zilberberg and Dubberke 25 More than 80% of the annual CDI per-patient direct healthcare costs accrue within the first 2 months following the index episode. Also, although the cost trajectories in both of the groups rose following those 2 months, their rates of rise were similar. This implies that the first 2 months following a CDI episode present an opportunity to examine healthcare delivery practices in this population and to focus on prevention of high-cost and high-morbidity events such as rehospitalization.
Our study has a number of limitations. As a retrospective study it is subject to a number of biases, most notably selection bias. To mitigate this we developed a priori inclusion criteria. Because we used administrative coding to identify the main outcome (no methods or results of clinical CDI testing available in the database), there is a threat of misclassification. Although this method of identifying CDI is well validated in the hospitalized population, it may not be as accurate in a mixed population of in- and outpatients.Reference Dubberke, Reske, McDonald and Fraser 26 We tried to reduce its impact by establishing a 1-year disease-free interval among patients who develop CDI. In general, misclassification would reduce the magnitude of the differences between the comparator groups, thus biasing our results toward the null. Confounding is an issue in observational studies. Because the aim of our study was to calculate costs and mortality attributable specifically to CDI, we dealt with confounding by deriving a PS for the risk of CDI and then analyzing a PS-matched cohort. Recent evidence suggests that this methodology generally produces results similar to those generated in randomized controlled trials.Reference Kitsios, Dahabreh, Callahan, Paulus, Campagna and Dargin 27 Although we used a highly generalizable dataset, several factors are potentially limiting to it. For risk factor analysis, we defined incident CDI as an episode occurring following at least 12 months disease-free period. This definition diverges from that in the guidelines.Reference Cohen, Gerding and Johnson 28 However, including patients who might have had an episode of CDI within the year prior to the incident episode would have reduced our ability to clearly differentiate the study groups on the basis of their risk factors. This definition, however, limits the generalizability of our findings to only those patients who have not had an episode of CDI within the prior year. Despite these potential limitations, the overall generalizability of our data makes this study a useful contribution to the literature on the outcomes attributable to this disease.
In summary, in this large and generalizable study of the elderly population, we have demonstrated that CDI results in a considerable increase in the risk of death and costs to Medicare within the year following the incident episode. Although mortality increases linearly over time, most of the cost burden appears to accrue early in the aftermath period, and is mostly due to inpatient care. These high clinical and economic costs suggest that there is a strong need to employ aggressively such existing CDI preventive strategies as antibiotic stewardship, in addition to developing new interventions specifically geared at this large and growing population of patients.
ACKNOWLEDGMENTS
Financial support. Pfizer.
Potential conflicts of interest. M.D.Z. reports that she is a consultant to and has received research grant support from Pfizer and Merck and has served as a consultant to ViroPharma and ReBiotix. A.F.S. reports that he is a consultant to and has received research grant support from Pfizer and Merck. L.W. reports that she is an employee of STATinMED who received grant support from Pfizer for conducting this study. O.B. reports that she is an employee of STATinMED who received grant support from Pfizer for conducting this study. H.Y. reports that she is an employee of and stockholder in Pfizer.
SUPPLEMENTARY MATERIAL
To view supplementary material for this article, please visit http://dx.doi.org/doi:10.1017/ice.2016.188