1. Introduction
Social cognitive impairments in schizophrenia manifest as difficulties with emotion recognition, the theory of mind, and emotion management (Green & Horan, Reference Green and Horan2010). Emotion management can be defined as the ability to be open to feelings and to modulate them in oneself as well as in others (Mayer, Salovey, & Caruso, Reference Mayer, Salovey and Caruso2002). Emotion management is an important aspect of social cognition for independent living, work ability and social functioning (Eack et al., Reference Eack, Greeno, Pogue-Geile, Newhill, Hogarty and Keshavan2010; Kee et al., Reference Kee, Horan, Salovey, Kern, Sergi, Fiske and Green2009). Emotion management is also suggested to mediate the effects of cognitive remediation therapy on functional outcomes in schizophrenia (Eack, Pogue-Geile, Greenwald, Hogarty, & Keshavan, Reference Eack, Pogue-Geile, Greenwald, Hogarty and Keshavan2011). Therefore, improving the ability to manage emotions is a critical treatment target in the schizophrenia population.
An early meta-analysis showed moderate benefits of cognitive remediation therapy at improving social cognition in schizophrenia (Wykes, Huddy, Cellard, McGurk, & Czobor, Reference Wykes, Huddy, Cellard, McGurk and Czobor2011), while more modest benefits were observed in a more recent meta-analysis (Kambeitz-Ilankovic et al., Reference Kambeitz-Ilankovic, Betz, Dominke, Haas, Subramaniam, Fisher and Kambeitz2019). Cognitive remediation therapies that focus on social cognitive skills demonstrated significant improvement in various social cognitive domains, such as facial affect identification and theory-of-mind (Grynszpan et al., Reference Grynszpan, Perbal, Pelissolo, Fossati, Jouvent, Dubal and Perez-Diaz2011; Kurtz & Richardson, Reference Kurtz and Richardson2012; Kurtz, Gagen, Rocha, Machado, & Penn, Reference Kurtz, Gagen, Rocha, Machado and Penn2016), as well as emotion management (Gohar, Hamdi, El Ray, Horan, & Green, Reference Gohar, Hamdi, El Ray, Horan and Green2013; Horan et al., Reference Horan, Kern, Tripp, Hellemann, Wynn, Bell and Green2011). A better understanding of the neural underpinnings of such behavioral changes may help improve and optimize the effect of cognitive remediation treatments on specific social cognitive domains in schizophrenia.
Cognitive enhancement therapy (CET; Hogarty et al., Reference Hogarty, Flesher, Ulrich, Carter, Greenwald, Pogue-Geile and Zoretich2004) is a form of cognitive remediation that specifically treats both neurocognition and social cognition (Eack, Hogarty, Greenwald, Hogarty, & Keshavan, Reference Eack, Hogarty, Greenwald, Hogarty and Keshavan2007; Hogarty et al., Reference Hogarty, Flesher, Ulrich, Carter, Greenwald, Pogue-Geile and Zoretich2004; Wojtalik et al., Reference Wojtalik, Hogarty, Cornelius, Phillips, Keshavan, Newhill and Eack2016). It is a comprehensive, step-wise approach to remediation that seeks to facilitate the development of both neurocognitive and social cognitive milestones in schizophrenia. Youth within the early course of schizophrenia who received CET have been noted to show improved neurocognition and social cognition, as well as functional gains in employment, social functioning, and daily activities (Eack et al., Reference Eack, Greenwald, Hogarty, Cooley, DiBarry, Montrose and Keshavan2009). In a recent study, individuals with schizophrenia who received CET showed increased right dorsolateral prefrontal cortex (dlPFC) activity during an executive function task that was associated with improved neurocognitive performance, but not with social cognitive performance (Keshavan, Eack, Prasad, Haller, & Cho, Reference Keshavan, Eack, Prasad, Haller and Cho2017). This finding is in line with observations from several studies showing an association between neurocognitive improvements after cognitive remediation and increased activity in the dlPFC in schizophrenia (Guimond et al., Reference Guimond, Béland and Lepage2018a, Reference Guimond, Padani, Lutz, Eack, Thermenos and Keshavan2018b; Mothersill & Donohoe, Reference Mothersill and Donohoe2019; Penadés et al., Reference Penadés, González-Rodríguez, Catalán, Segura, Bernardo and Junqué2017; Ramsay, Nienow, Marggraf, & MacDonald, Reference Ramsay, Nienow, Marggraf and MacDonald2017). While several studies implicate the dlPFC in cognitive remediation-related improvements in executive function in schizophrenia (Keshavan et al., Reference Keshavan, Eack, Prasad, Haller and Cho2017; Ramsay & MacDonald, Reference Ramsay and MacDonald2015; Wei et al., Reference Wei, Wang, Yan, Li, Pan, Cui and Tang2016), the neural basis of cognitive remediation-related improvements in social cognitive domains, including emotion management, remains unclear (Campos et al., Reference Campos, Santos, Gagen, Machado, Rocha, Kurtz and Rocha2016).
The relationship between activity in brain regions subserving executive function and limbic regions could play an important role in emotion management. Functional connectivity between the amygdala and both the ventrolateral prefrontal cortex (vlPFC) and the dlPFC is associated with the ability to manage emotions, which is an important component of social cognition in neurotypical individuals (Banks, Eddy, Angstadt, Nathan, & Luan Phan, Reference Banks, Eddy, Angstadt, Nathan and Luan Phan2007; Ochsner, Silvers, & Buhle, Reference Ochsner, Silvers and Buhle2012; Morawetz, Bode, Baudewig, & Heekeren, Reference Morawetz, Bode, Baudewig and Heekeren2017). Individuals with schizophrenia also show abnormal functional connectivity among these regions (Cole, Anticevic, Repovs, & Barch, Reference Cole, Anticevic, Repovs and Barch2011; Liu et al., Reference Liu, Zhang, Chen, Tian, Li, Qu and Zhuo2017; Yoon et al., Reference Yoon, Minzenberg, Ursu, Ryan Walter, Walters, Wendelken and Yoon2008). Evidence has shown that abnormalities of the amygdala-prefrontal cortex pathway underlie emotion management dysfunctions in schizophrenia (Anticevic, Repovs, & Barch, Reference Anticevic, Repovs and Barch2012; Morris, Sparks, Mitchell, Weickert, & Green, Reference Morris, Sparks, Mitchell, Weickert and Green2012). More specifically, reduced functional connectivity between the amygdala, vlPFC, and dlPFC is related to impaired emotion management abilities in schizophrenia (Park, Chun, Park, Kim, & Kim, Reference Park, Chun, Park, Kim and Kim2018; Szabó et al., Reference Szabó, Farkas, Marosi, Kozák, Rudas, Réthelyi and Csukly2017). It is, therefore, possible that treatments that target and modulate this network could enhance the ability to manage emotions.
In this study, we sought to characterize changes in amygdala-vlPFC and amygdala-dlPFC connectivity in a sample of people within the early course of schizophrenia who were randomized to 18 months of either CET or active control intervention. The active control intervention was an enriched supportive therapy (EST) that fosters illness management by teaching how to apply coping strategies and providing psychoeducation (Hogarty et al., Reference Hogarty, Flesher, Ulrich, Carter, Greenwald, Pogue-Geile and Zoretich2004). We hypothesized that CET would enhance emotion management capacity, as well as amygdala-vlPFC and amygdala-dlPFC resting-state functional connectivity, while this would not be the case for EST. We also hypothesized that increased connectivity in these neural circuits would be related to improved emotion management ability observed after CET but not EST.
2. Methods
2.1 Participants
A total of 106 participants with schizophrenia or schizoaffective disorder within the early course of the illness were enrolled as part of the longitudinal, randomized-controlled clinical trial ‘Brain Imaging, Cognitive Enhancement and Early Schizophrenia’ (BICEPS), at Beth Israel Deaconess Medical Center, Boston, MA and the University of Pittsburgh, Pittsburgh, PA (Wojtalik, et al., Reference Wojtalik, Mesholam-Gately, Hogarty, Greenwald, Litschge, Sandoval and Eacksubmitted). The Institutional Review Boards of both sites approved the study, and all the participants gave written informed consent before participating.
The structured clinical interview for the DSM-IV (SCID) was used to confirm the diagnosis by trained raters. Inclusion criteria were: (1) 18–55 years of age; (2) IQ ⩾ 80 as assessed using the two-subtest form of the Wechsler Abbreviated Scale Intelligence 2nd Edition (WASI-II); (3) a sixth-grade reading level as assessed by the reading subtest of the Wide Range Achievement Test 4th Edition and fluent spoken English; (4) diagnosis of schizophrenia, schizophreniform, or schizoaffective disorder by the SCID; (5) illness duration ⩽10 years; (6) on antipsychotic medication or otherwise clinically stabilized for at least 2 months prior to study enrollment; and (7) displaying significant social and cognitive disability as assessed using the cognitive style and social cognition eligibility interview as used in previous CET studies (Eack et al., Reference Eack, Greenwald, Hogarty, Cooley, DiBarry, Montrose and Keshavan2009, Reference Eack, Hogarty, Greenwald, Litschge, Mcknight, Bangalore and Cornelius2015; Hogarty et al., Reference Hogarty, Flesher, Ulrich, Carter, Greenwald, Pogue-Geile and Zoretich2004). Participants were excluded if they had: (1) other medical conditions associated with cognitive impairment; (2) persistent suicidal or homicidal behavior; (3) substance abuse or dependence within 3 months; or (4) contraindications for magnetic resonance imaging (MRI; e.g. claustrophobia; MRI-incompatible implants or medical devices or history of injury involving metal fragments).
2.2 Treatments
The participants were randomly assigned to either CET or EST (control treatment) and treated for 18 months. The CET protocol is an integrated neurocognitive and social cognitive approach that begins with 60 h in participant-pairs of computer-based neurocognitive training in attention, memory, and problem solving, followed by integration into 45 weekly in-person group sessions of 6–8 participants. These structured weekly sessions focused on a wide range of social-cognitive abilities, such as perspective-taking, emotion management, reading non-verbal cues, and social context appraisal (see Hogarty et al., Reference Hogarty, Greenwald and Eack2006). The EST protocol consisted of weekly 30–60-min personal therapy (Hogarty, Reference Hogarty2002) focused on psychoeducation, stress, and illness management. The sessions were reduced to biweekly as the treatment progressed. The same clinicians provided both treatments, thereby avoiding potential clinician effects. The possibility of treatment contamination was minimized by the fact that both interventions were manual-driven, and were supervised by experts in both therapeutic conditions (Susan S. Hogarty, Deborah P. Greenwald, Shaun M. Eack). Both treatments have been described in detail in previous publications (Hogarty et al., Reference Hogarty, Flesher, Ulrich, Carter, Greenwald, Pogue-Geile and Zoretich2004; Keshavan et al., Reference Keshavan, Eack, Prasad, Haller and Cho2017).
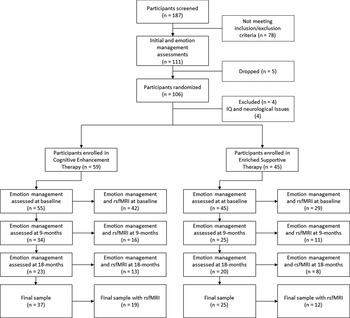
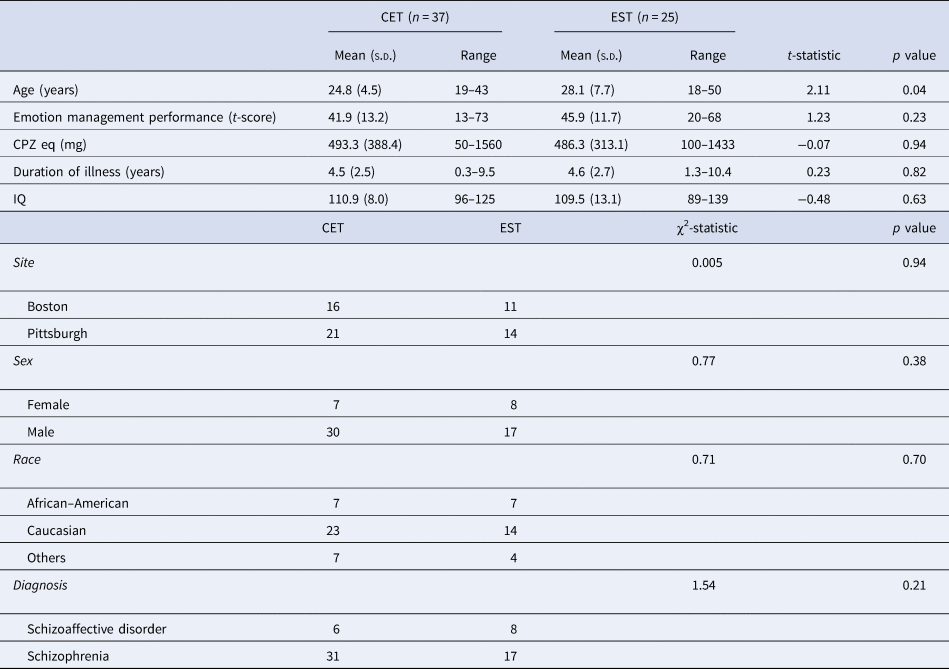
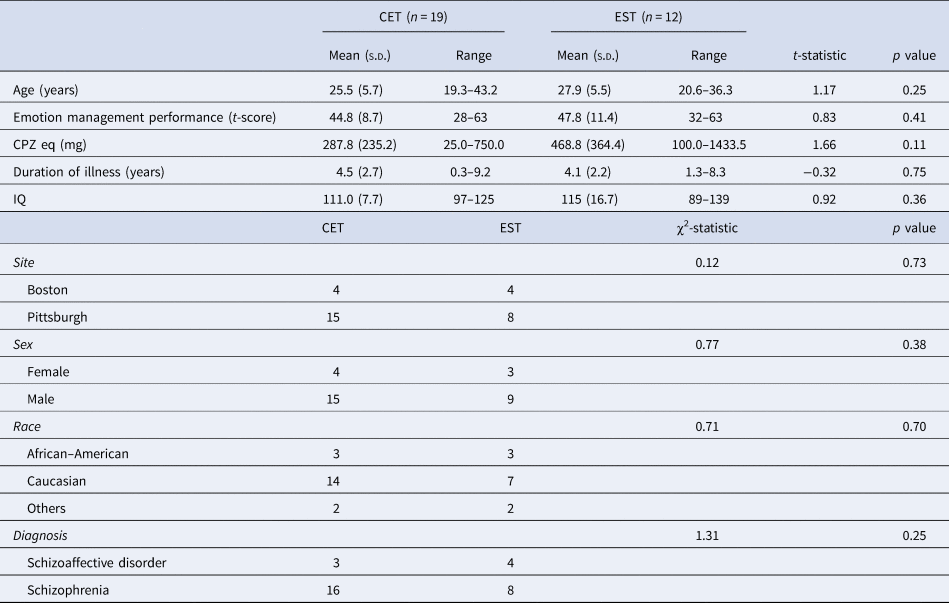
Neuroimaging and emotion management measurements were acquired at baseline and 9 and 18 months follow-up. Figure 1 shows the treatment group and data collection flowchart. Demographic, clinical, and cognitive information comparing the two groups included in our analysis at baseline is shown in Table 1. Age significantly differed between the groups, with the CET group being younger (p = 0.04). No significant differences were observed between the groups in terms of race, diagnosis, chlorpromazine equivalent medication dosage, or duration of illness. Table 2 shows that no significant demographic differences were found between treatment groups in the imaging sample. No significant demographic differences were found between the analysis sample and the randomization sample (all p > 0.18; Supplementary Table 2).
Randomization and data collection flowchart. Note: The flowchart represents how many participants were screened, have completed initial assessments, were randomized, and then were enrolled in both treatment conditions. It also delineates the number of participants with good quality data that were included in our analyses at baseline, 9, and 18 months. The final sample consists of participants who have been assessed at least twice during the study period. rsfMRI, resting-state functional magnetic resonance imaging.

Baseline demographic, clinical and cognitive data for the final sample

Note: CPZ eq, chlorpromazine equivalence; IQ, Intelligence Quotient estimate based on two-subtest form of the Wechsler Abbreviated Scale Intelligence, 2nd Edition (WASI-II).
Baseline demographic, clinical and cognitive data for the final sample with imaging data
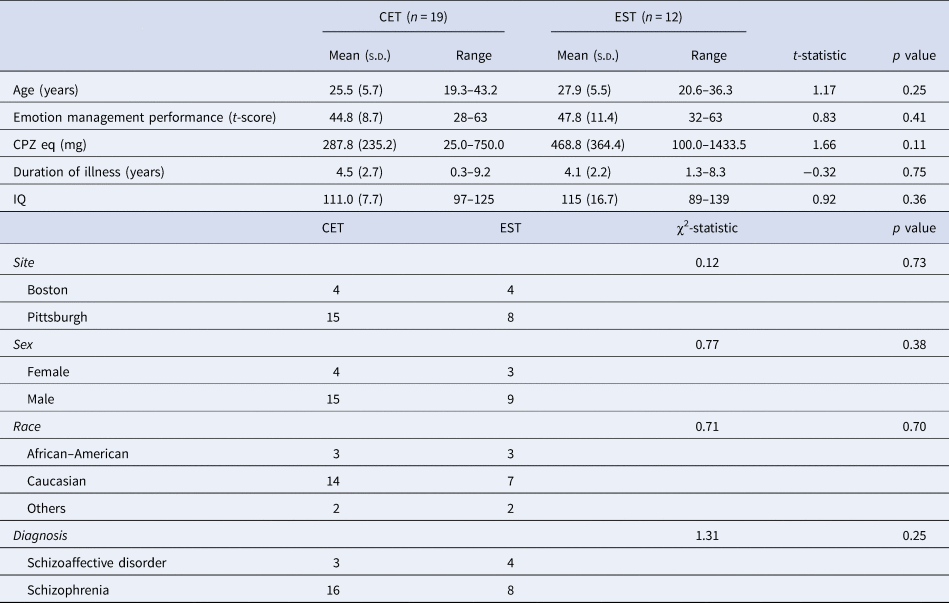
Note: CPZ eq, chlorpromazine equivalence; IQ, Intelligence quotient estimate based on two-subtest form of the Wechsler Abbreviated Scale Intelligence 2nd Edition (WASI-II).
2.3 Measures
2.3.1 Emotion management
We chose to use the managing emotions branch of the Mayer–Salovey–Caruso Emotional Intelligence Test (MSCEIT; Mayer, Salovey, Caruso, and Sitarenios, Reference Mayer, Salovey, Caruso and Sitarenios2003) as it is strongly correlated with functional outcome (Eack et al., Reference Eack, Greeno, Pogue-Geile, Newhill, Hogarty and Keshavan2010; Kee et al., Reference Kee, Horan, Salovey, Kern, Sergi, Fiske and Green2009), and hence it is used as part of the measurement and treatment research to improve cognition in schizophrenia consensus cognitive battery (Nuechterlein et al., Reference Nuechterlein, Green, Kern, Baade, Barch, Cohen and Marder2008). This measure also performed well on test–retest reliability, repeated measure utility, response to pharmacological intervention, as well as practicality and tolerability (Mayer, Salovey & Caruso, Reference Mayer, Salovey and Caruso2012; Nuechterlein et al., Reference Nuechterlein, Green, Kern, Baade, Barch, Cohen and Marder2008). Furthermore, this measure assesses how people manage their emotions, which is of particular interest when investigating brain functional networks that are known to be important for regulating and managing emotions (Banks et al., Reference Banks, Eddy, Angstadt, Nathan and Luan Phan2007; Morawetz et al., Reference Morawetz, Bode, Baudewig and Heekeren2017; Ochsner et al., Reference Ochsner, Silvers and Buhle2012). Uncorrected t-scores were used in all analyses.
2.3.2 Resting-state functional MRI
A 3T Siemens Trio (TIM upgrade) scanner was used at the Boston site to acquire resting-state functional magnetic resonance imaging (fMRI) data, while a 3T Siemens Verio scanner was used at the Pittsburgh site. The imaging parameters at both sites consisted of 3000-ms repetition time, 30-ms echo time, 85° flip angle, and 3 × 3 × 3-mm3 voxels. Forty-seven axial sections were collected at Boston while 45 were collected at Pittsburgh, both with interleaved acquisition and no gap. All participants were instructed to ‘remain still, stay awake, and keep their eyes open’ during the resting-state fMRI run of 6.2 min (124 time points). A high-resolution T1 image was also taken for pre-processing purposes.
Resting-state fMRI data were preprocessed using data processing assistant for resting-state (DPABI) image processing software (Version 4.0 190305; Yan, Wang, Zuo, and Zang, Reference Yan, Wang, Zuo and Zang2016) for a total of 186 scans including all time points (CET, n = 105; EST, n = 81). The first four volumes were removed from every scan to minimize the effects of the scanner signal stabilization. The scans with head motion exceeding 4-mm maximum translation or 4° maximum rotation were discarded (CET, n = 19; EST, n = 20). Functional and structural images were co-registered. Structural images were normalized and segmented into gray matter, white matter, and cerebral spinal fluid (CSF) partitions using the Diffeomorphic Anatomical Registration Through Exponentiated Lie Algebra (DARTEL) method (Ashburner, Reference Ashburner2007). The Friston 24-parameter model was used to regress out head motion effects from the data (Friston, Williams, Howard, Frackowiak, & Turner, Reference Friston, Williams, Howard, Frackowiak and Turner1996). CSF, WM and global signals were regressed out (Yan et al., Reference Yan, Cheung, Kelly, Colcombe, Craddock, Di Martino and Milham2013). The images were realigned and corrected for slice timing. Framewise displacement was calculated and all volumes exceeding the threshold of 0.5-mm were censored. Scans with more than 50% of volumes requiring censoring were discarded (CET, n = 9; EST, n = 8). There was no significant treatment group difference in terms of volumes that were censored (p = 0.55). The data had nuisance covariates regressed out and were band-pass filtered for 0.01–0.08-Hz signals. Normalization was then performed via DARTEL in Montreal Neurological Institute space and smoothing was performed using an 8-mm Gaussian kernel full-width-at-maximum-height. A total of 96 participants had at least one scan collected during the study. From these 96 participants, a total of 87 participants (91%) remained after quality control and filtering as described above. Of these 87 participants, 71 (82%) had a baseline scan, but only 31 of those 71 participants (44%) also had a scan obtained at a second-time point. Therefore, a total of 31 participants (19 CET and 12 EST) were included in the longitudinal resting-state fMRI analysis.
Our a priori hypothesis was to determine the strength of correlation of the pathway between the amygdala and the lateral prefrontal cortex using anatomical selected seeds that relate to emotion management (Anticevic et al., Reference Anticevic, Repovs and Barch2012; Hoptman et al., Reference Hoptman, D'Angelo, Catalano, Mauro, Shehzad, Kelly and Milham2010; Wager, Davidson, Hughes, Lindquist, & Ochsner, Reference Wager, Davidson, Hughes, Lindquist and Ochsner2008) and that have previously been used in the literature (Morawetz et al., Reference Morawetz, Bode, Baudewig and Heekeren2017). Therefore, bilateral amygdala, dlPFC, and vlPFC were selected as a priori regions-of-interest (ROIs) for our analyses using the automated anatomical labeling atlas (Tzourio-Mazoyer et al., Reference Tzourio-Mazoyer, Landeau, Papathanassiou, Crivello, Etard, Delcroix and Joliot2002; see details in Supplementary Table 1).
2.4 Statistical analyses
1All statistical analyses were performed in R. linear mixed-effects models were performed with the lmerTest package (Kuznetsova, Brockhoff, & Christensen, Reference Kuznetsova, Brockhoff and Christensen2017) and adjusted for random intercept for each participant. All analyses were corrected for sites to account for possible differences between assessors and scanners. Age and sex were entered as covariates in the models as these variables are known to affect the MSCEIT scores as well as the brain functional connectivity measures (Cabello, Sorrel, Fernández-Pinto, Extremera, & Fernández-Berrocal, Reference Cabello, Sorrel, Fernández-Pinto, Extremera and Fernández-Berrocal2016; Zhang et al., Reference Zhang, Cahill, Arbabshirani, White, Baum and Michael2016). Post-hoc within-group effects were also examined. Multiple comparison correction for Type 1 error was applied using the false discovery rate Benjamin–Hochberg procedure and q values are reported.
First, a linear mixed-effect model was used to analyze the effect of treatment groups on emotion management performance over time.
Next, functional connectivity was assessed using a seed-based analysis. ROI-to-ROI functional connectivity values were extracted and z-transformed values were calculated using the DPABI toolbox (Yan et al., Reference Yan, Wang, Zuo and Zang2016). A series of linear mixed-effects models were then used to analyze the effect of the treatment group on these z-transformed connectivity values over time between our ROIs.
Finally, linear mixed-effects models were used to explore the association between change over time in functional connectivity and change over time in emotion management performance, and the interaction of treatment groups on this longitudinal relationship. When the between-group interactions were significant, post-hoc linear mixed-effects models were then performed in each group separately.
3. Results
3.1 Effect of treatment on emotion management performance
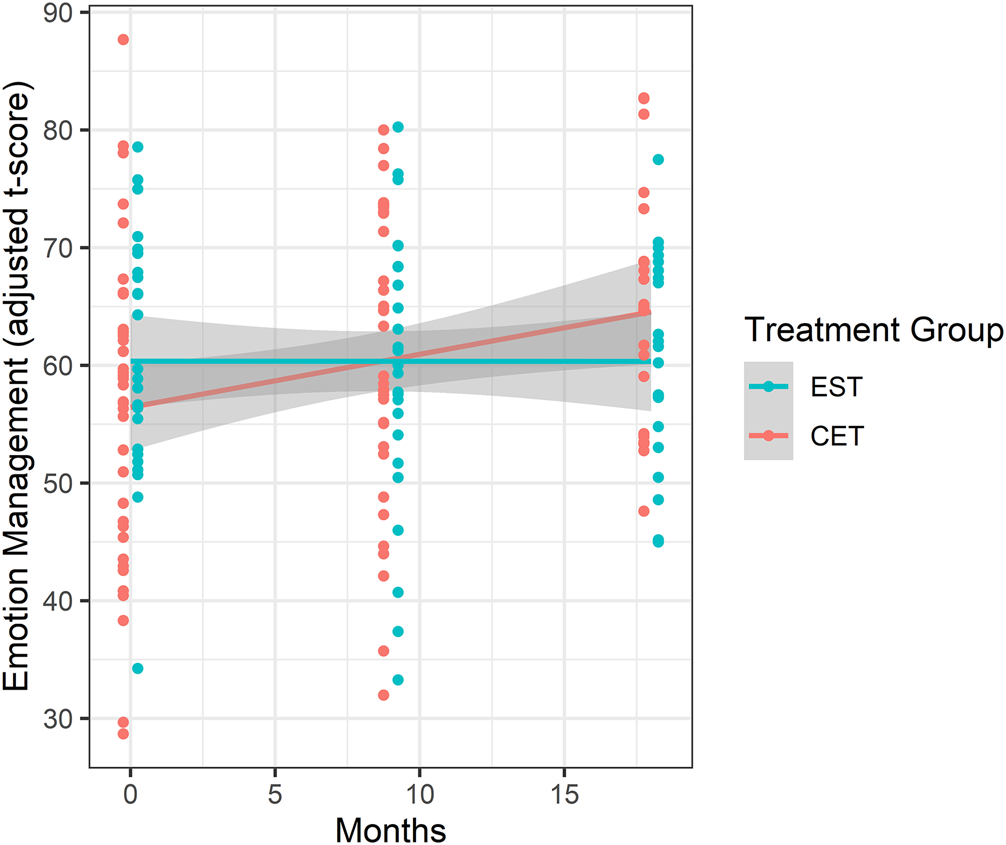
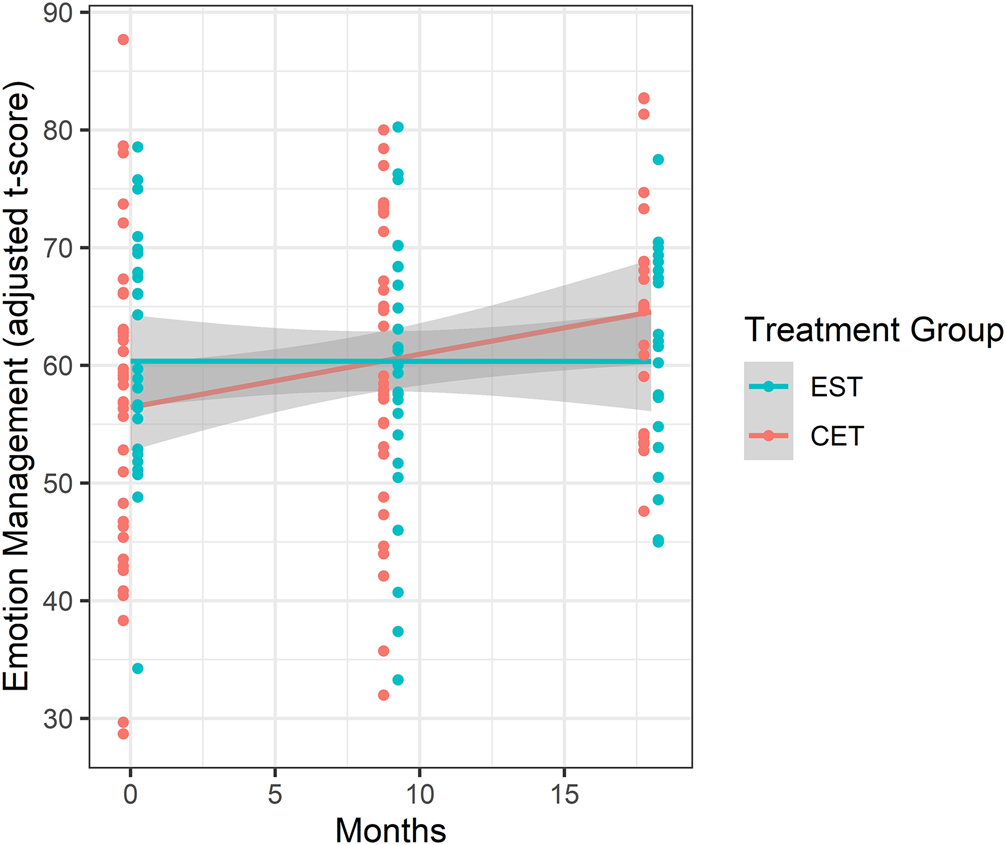
We observed a significant time by group interaction on emotion management performance (B = −0.215, t = −2.34, p = 0.021; see Fig. 2). Post-hoc within-group analysis revealed that only participants in the CET group displayed a significant improvement in emotion management over time (CET: B = 0.213, t = 2.95, p = 0.0043; EST: B = 0.0147, t = 0.85, p = 0.183). The interaction term was also significant in the subsample of participants included in the rsfMRI analysis (B = −0.269, t = −2.47, p = 0.018; see Supplementary Figure 1).
Patients enrolled in CET significantly improved their emotion management performance over time compared to patients enrolled in EST. Note: emotion management t-scores are adjusted for age, sex and site. EST, enriched supportive therapy; CET, cognitive enhancement therapy.
3.2 Effect of treatment on functional connectivity
Neither significant longitudinal change over time nor group differences in functional connectivity were observed between any of our ROIs (all p > 0.300; see Supplementary Table 3).
3.3 Relationship between change in emotion management performance and functional connectivity
Significant between-group interactions were observed in terms of the association between change in emotion management abilities and change in functional connectivity between the left amygdala and bilateral dlPFC (left amygdala-to-left dlPFC, B = −0.703, t = −3.44, p = 0.002, q = 0.009; left amygdala-to-right dlPFC, B = −0.760, t = −3.51, p = 0.002, q = 0.009), as well as between right amygdala and right dlPFC (right amygdala-to-right, B = −0.638, t = −2.75, p = 0.01, q = 0.03).
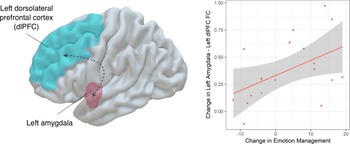
As demonstrated in Fig. 3, post-hoc within-group analysis revealed that the more the participants in the CET group improved their emotion management performance over time, the more they tend to show an increase in functional connectivity between the left amygdala and the left dlPFC (B = 0.466, t = 2.47, p = 0.027), while this relationship was not observed in the EST group (B = −0.498, t = −1.60, p = 0.154).
Emotion management improvement over time in people enrolled in CET was associated with increased functional connectivity between the left amygdala and the left dlPFC. Note: Graphical representation of the two regions of interest (left panel); scatter plot showing association between change in emotion management performance and change in functional connectivity following cognitive enhancement therapy (CET) (right panel). Change in functional connectivity z-scores are adjusted for age, sex and site. dlPFC, dorsolateral prefrontal cortex; FC, functional connectivity; EST, enriched supportive therapy; CET, cognitive enhancement therapy.

Post-hoc within-group analysis showed that significant group interactions related to functional connectivity between the bilateral amygdala and the right dlPFC were instead driven by reduced connectivity between these brain regions being related to better emotion management performances in patients enrolled in EST (left amygdala-to-right dlPFC, B = −0.955, t = −3.62, p = 0.008; right amygdala-to-right dlPFC, B = −1.23, t = −12, p < 0.001), while such a negative relationship was not observed in patients enrolled in CET (left amygdala-to-right dlPFC, B = 0.300, t = 1.19, p = 0.254; right amygdala-to-right dlPFC, B = 0.292, t = 1.29, p = 0.217).
There was neither significant overall relationship between change in emotion management abilities and change in functional connectivity observed across treatment groups (see Supplementary Tables 4) nor group differences for any of the measures of functional connectivity at baseline (see Supplementary Tables 5).
4. Discussion
In this study, we investigated changes in emotion management performance and amygdala-vlPFC/dlPFC connectivity in individuals within the early course of schizophrenia receiving CET. Our results show that emotion management ability in patients with schizophrenia improves significantly after undergoing CET as compared to EST. Our findings also denote that individuals who showed greater improvements in emotion management performance over the course of CET were more likely to show increased connectivity between the left amygdala and the left dlPFC. These findings suggest that increased functional connectivity between these two brain regions could be an underlying mechanism involved in the amelioration of emotion management impairments in individuals with schizophrenia receiving CET.
Our current results support previous findings that indicate that CET is an effective approach for improving various aspects of social cognition in individuals with schizophrenia (Hogarty et al., Reference Hogarty, Flesher, Ulrich, Carter, Greenwald, Pogue-Geile and Zoretich2004; Reference Hogarty, Greenwald and Eack2006; Lee et al., Reference Lee, Redoblado-Hodge, Naismith, Hermens, Porter and Hickie2013; Wojtalik et al., Reference Wojtalik, Hogarty, Cornelius, Phillips, Keshavan, Newhill and Eack2016). More specifically, our findings suggest that improvements in emotion management performance in individuals who receive CET are related to increased functional connectivity between the left amygdala and left dlPFC, two important regions for emotion management in neurotypical individuals (Banks et al., Reference Banks, Eddy, Angstadt, Nathan and Luan Phan2007; Lee, Heller, van Reekum, Nelson, & Davidson, Reference Lee, Heller, van Reekum, Nelson and Davidson2012) and in schizophrenia (Ursu et al., Reference Ursu, Kring, Gard, Minzenberg, Yoon, Ragland and Carter2011). In line with these results, Wojtalik et al., in an independent sample, found CET treatment to increase activity in prefrontal and limbic regions while participants performed an emotion regulation task (Wojtalik et al., Reference Wojtalik, Hogarty, Cornelius, Phillips, Keshavan, Newhill and Eack2016). Taken together, these findings show that activity changes in fronto-limbic networks are associated with performance improvements in managing emotions following CET in patients with schizophrenia.
While we observed an association between increased emotion management ability and increased functional connectivity over time between the left amygdala and left dlPFC in the CET group and not in the EST group, we found no main effect of groups on functional connectivity. Furthermore, no significant changes were detected between the amygdala and vlPFC, which was surprising given that both regions are implicated in emotion processing in neurotypical individuals (Banks et al., Reference Banks, Eddy, Angstadt, Nathan and Luan Phan2007; Lee et al., Reference Lee, Heller, van Reekum, Nelson and Davidson2012; Morawetz et al., Reference Morawetz, Bode, Baudewig and Heekeren2017). However, it is possible that the vlPFC is less involved in individuals in whom this ability is impaired, and more research is needed to investigate this further. Moreover, as we performed a longitudinal fMRI study and follow-up scans were sparse, our study was limited in sample size, which may have reduced our power to detect group differences in these measures.
Our findings also revealed an unexpected negative relationship between change in the bilateral amygdala and right dlPFC connectivity and emotion management performance in our active control group receiving EST. More specifically, individuals who received EST showed lower emotion management performance at follow-up, but increased functional connectivity between the bilateral amygdala and right dlPFC. This surprising finding may be a result of our control condition or relate to individual differences in declining emotion management abilities throughout the current study. This also raises the possibility that increased functional connectivity between the bilateral amygdala and right dlPFC may occur in the natural course of schizophrenia. This could be an inefficient neural response, since it is associated with reduced emotional management abilities, suggesting a maladaptive compensatory effect. Nonetheless, it is important to note that our final EST control group sample was small. Subsequently, additional research in a larger sample is needed to elucidate this intriguing result.
Previous reports suggest that both right and left dlPFC play a differential role in the top–down regulation of emotions (Ligeza, Wyczesany, Tymorek, & Kamiński, Reference Ligeza, Wyczesany, Tymorek and Kamiński2016; MacDonald, Cohen, Stenger, & Carter, Reference MacDonald, Cohen, Stenger and Carter2000; Sanchez-Lopez, Vanderhasselt, Allaert, Baeken, & De Raedt, Reference Sanchez-Lopez, Vanderhasselt, Allaert, Baeken and De Raedt2018). Brain stimulation studies showed that increased activity of the left dlPFC may help reduce attention toward negative emotions, while stimulation of the right dlPFC would result in impaired disengagement toward these negative emotions in neurotypical individuals (De Raedt et al., Reference De Raedt, Leyman, Baeken, Van Schuerbeek, Luypaert, Vanderhasselt and Dannlowski2010; Sanchez-Lopez et al., Reference Sanchez-Lopez, Vanderhasselt, Allaert, Baeken and De Raedt2018). While increased activity in the left dlPFC would be critical for improving emotion regulation, this may not be the case for the right dlPFC in neurotypical individuals (Sanchez-Lopez et al., Reference Sanchez-Lopez, Vanderhasselt, Allaert, Baeken and De Raedt2018) as well as in people with depression (De Raedt & Koster, Reference De Raedt and Koster2010; Disner, Beevers, Haigh, & Beck, Reference Disner, Beevers, Haigh and Beck2011). This could explain the differential lateralized effect in functional connectivity we observed between CET and EST across both hemispheres of the dlPFC.
This study is the first to investigate resting-state functional connectivity underlying changes in emotion management performances after CET in individuals within the early course of schizophrenia. Our results provide evidence that the functional corticolimbic connectivity between the left amygdala and left dlPFC may be a potential mechanism underlying emotion management outcomes following CET in schizophrenia. Nonetheless, the findings from our study should be interpreted considering its limitations. First, the current sample consists of individuals with unusually high baseline IQ and may not be a representative of most people within the early course of schizophrenia. Hence, future studies are needed to confirm our current findings in people within the early course of schizophrenia with lower IQ as well as in individuals in more advanced stages of the illness. It is important to note that the current findings related to emotion management are limited by the use of the MSCEIT as our measure of social cognitive outcome. This aspect of social cognition depends on cognitive processes including verbal memory, comprehension, and more general cognitive processing. Further research is required to investigate the cognitive components of CET that may contribute to emotion management task improvement. Many other domains of social cognition are impaired in schizophrenia and should be investigated in future studies (e.g. emotion recognition, attention bias, theory of mind) (Mike et al., Reference Mike, Guimond, Kelly, Thermenos, Mesholam-Gately, Eack and Keshavan2019). These domains of social cognition are likely to be supported by different brain networks (Laillier et al., Reference Laillier, Viard, Caillaud, Duclos, Bejanin, de La Sayette and Laisney2019; Lee & Siegle, Reference Lee and Siegle2012; Sanchez-Lopez et al., Reference Sanchez-Lopez, Vanderhasselt, Allaert, Baeken and De Raedt2018). Hence, more research is needed to investigate the brain correlates of improvement in other aspects of social cognition following CET.
Furthermore, since we excluded brain imaging data containing excessive motion and many participants did not have a brain scan post-baseline, the final sample size of participants included in our functional connectivity analysis was relatively small. This may reduce the generalizability of our results. Nonetheless, the demographics from the initial sample (n = 100) were similar to those of our final sample (see Supplementary Table 2). The small sample size for the fMRI analysis also reduced our power and as such, may have increased the risk of false-negative results. This lack of power also limits our ability to further investigate whole-brain functional changes over time. Future studies should explore the link between improvements in emotion management and other resting-state networks, such as the default mode network (Mars et al., Reference Mars, Neubert, Noonan, Sallet, Toni and Rushworth2012). In addition, CET is an extended cognitive remediation program and we observed high levels of attrition over time (55% from baseline to 18 months). While the attrition was similar in both CET and EST groups (see Fig. 1), the current results may be biased by the type of individuals who remain in the study over the 18-month period, as it is likely that those who dropped out experienced fewer benefits from treatment. In the future, a larger longitudinal sample should be used to account for these limitations and replicate our current findings. This also highlights the importance of closer monitoring of quality control during imaging data collection for further similar clinical trials to avoid such attrition. This study was conducted at two different sites with two different scanners. While we harmonized data acquisition procedures between both sites and included site as a covariate in all our analyses, this is an additional limitation to our study. Finally, more efforts are needed to increase the retention of participants in CET trials and to further develop shorter-duration cognitive interventions that may similarly improve emotion management performance and social cognition in schizophrenia.
In summary, this study suggests that functional connectivity between the left amygdala and left dlPFC is a possible underlying brain mechanism of emotion management improvement following CET in early course schizophrenia. A better understanding of the role of functional connectivity between the amygdala and the dlPFC in these social cognitive outcomes may guide the development of more targeted treatment approaches. In the future, studies may try to target this specific brain circuit with neuromodulation techniques to enhance plasticity and thereby maximize the efficacy of CET in improving emotion management ability. Furthermore, additional neuroimaging research is required to unravel the complex influence of CET on resting-state functional connectivity. The association of neurocognitive and social-cognitive aspects of CET treatment, and their interaction, on improved functional connectivity, will be an important concept to subsequent investigations.
Supplementary material
The supplementary material for this article can be found at https://doi.org/10.1017/S0033291720004110
Acknowledgements
The authors thank all the participants who took part in the study, as well as Annaliese Lausberg, Josh Golt, Summer McKnight, Scott Barb, and Taylor Nichols for their help with data collection, as well as Rachel Templeton for her help with the preliminary analyses.
Financial support
This work was funded by an operating grant from NIMH MH 92440; MSK, PI, Clinicatrials.gov #NCT01561859). SG was supported by a postdoctoral training fellowship from the Fonds de recherche du Québec – Santé (FRQS) and by an Emerging Research Innovators in Mental Health (eRIMh) award. GC was supported by the European Union's research and innovation programme under the Marie Sklodowska-Curie grant agreement no. 749201. RB was supported by NIH grant R01 MH116170.
Conflicts of interest
None.
Ethical standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008.