Acute respiratory infections such as pneumonia and bronchiolitis are common for both healthy infants and those with congenital heart disease (CHD). Previous studies showed children with CHD and viral bronchiolitis stay hospitalised 3 times longer, Reference Doucette, Jiang, Fryzek, Coalson, McLaurin and Ambrose1 have up to 37 times the mortality rate, Reference Doucette, Jiang, Fryzek, Coalson, McLaurin and Ambrose1,Reference Welliver, Checchia, Bauman, Fernandes, Mahadevia and Hall2 and have hospitalisations that cost 3 times more Reference Doucette, Jiang, Fryzek, Coalson, McLaurin and Ambrose1 when compared to children with bronchiolitis without CHD. While most research on respiratory infections hospitalisations in infants with CHD focuses on viral bronchiolitis, studies that examine non-bronchiolitis respiratory infections in children with CHD suggest high incidence rates and poor outcomes. A multi-centre study in Italy showed that non-bronchiolitis respiratory infections accounted for two-thirds of respiratory infections-related hospitalisations in children under 2 years of age with CHD. Reference Pongiglione, Possidoni and di Luzio Paparatti3 A population study in Sweden showed higher relative risks for hospitalisation for children with CHD who have non-Respiratory Syncytial Virus (RSV) infections including non-RSV pneumonia (8.87–10.26), compared to those with RSV infection (5.99–7.23). Reference Granbom, Fernlund, Sunnegårdh, Lundell and Naumburg4 Despite the high prevalence of non-bronchiolitis respiratory infections in children with CHD, to our knowledge no studies in the United States have published on this broader population. Due to global differences in demographics, models of care, and practice standards, the findings in European studies are unlikely to be generalisable to a United States cohort.
The objectives of this study are (1) to quantify the burden of all acute respiratory infections in paediatric inpatients with CHD in the United States, and (2) to compare length of stay, cost, and mortality for those with acute respiratory infections versus those without.
Material and methods
Data source and sample
We conducted a multi-centre, retrospective cross-sectional study using data from Kids’ Inpatient Database from 2012, a national administrative dataset of inpatients from age 0 to 20 discharged in 2012 from all non-rehabilitation hospitals in 44 participating states in the United States. 5 Our sample included patients under the age of 1 year with International Classification of Diseases, Ninth Revision, Clinical Modification (ICD-9-CM) codes consistent with CHD (745–747.49). We excluded neonates ≤28 days old to exclude birth hospitalisations.
Acute respiratory infections
Acute respiratory infection was defined as having a qualifying Clinical Classifications Software category as defined by the Kids’ Inpatient Database for Respiratory Infections, 7 which includes ICD-9-CM codes for pneumonia, influenza, bronchitis/bronchiolitis, and other upper respiratory infections (e.g., tonsillitis, croup), in any of the patient’s 25 discharge diagnoses.
Critical versus non-critical congenital heart disease
Using ICD-9-CM codes, we stratified our sample into those with critical CHD, defined as conditions that require surgical or cardiac catheterisation intervention within the first year of life Reference Oster, Lee, Honein, Riehle-Colarusso, Shin and Correa6 (e.g., hypo-plastic left heart syndrome) and those without critical CHD (e.g., ventricular septal defects; supplementary Table 1).
Patient demographics and clinical characteristics
Demographics include sex, race (categorised as non-Hispanic White, non-Hispanic Black, Hispanic, and other), and payer (categorised as Medicaid/Medicare, private insurance/Health maintenance organisation, and other). Clinical characteristics include complex chronic conditions using Feudtner et al’s classification system, Reference Feudtner, Feinstein, Zhong, Hall and Dai8 severity of illness defined by Hospitalisation Resource Intensity Score for Kids (calculated using cost and All Patient Refined Diagnosis Related Group Severity of Illness score), Reference Richardson, Rodean, Harris, Berry, Gay and Hall9 whether the admission was for cardiac surgery (defined as cardiac surgery occurring on day 0 or 1 of hospitalisation, identified by using Clinical Classification Software procedure category for “Operations on the Cardiovascular System” as well as a database defined variable for number of days from admission to procedure.
Outcome variables
Primary outcomes of interest studied include in-hospital mortality rate, length of stay (in days), and estimated cost (in dollars). Cost was estimated from charge data provided for each discharge, using hospital specific cost-to-charge ratios provided by the database. 10
Statistical analyses
All analyses reflected the Kids’ Inpatient Database complex sampling design; the stratification, hospital-level clustering, and sampling weight variables from the database, as well as definition of the specified study group (infants with CHD) as a study subpopulation, were used to obtain national estimates as well as standard errors and 95% confidence intervals. We conducted one set of bivariate analyses to assess the relationships between respiratory infections and all other variables for all infants with CHD, and another set to assess the relationships between non-critical and critical CHD for all infants with respiratory infections (specifying the survey subpopulation as infants with CHD and respiratory infections). Descriptive statistics generated national estimates of numbers and proportions (with 95% confidence interval) of patients by patient demographics and patient clinical characteristics. Differences in proportions on each characteristic between respiratory infections and no respiratory infections, followed by non-critical and critical CHD were statistically tested with a Pearson’s chi-square test statistic that was corrected for the survey design effects and reported as an F-statistic.
A multi-variable logistic regression model was used to estimate the association between presence of respiratory infections and mortality, and generalised linear models were used to estimate the association between presence of respiratory infections and the dependent outcome variables of length of stay and cost. Length of stay used a negative binomial regression (negative binomial random variable, log link function); cost used a gamma regression (gamma random variable, log link function). The stratification, clustering, and sampling weight variables were incorporated into the analysis to provide appropriate estimates of standard errors. Associations for the generalised linear models are presented as exponentiated regression estimates, with 95% confidence intervals; exponentiated regression coefficients for these models represent the fold-difference (i.e., ratio) in the covariate-adjusted mean length of stay (or cost) in discharges from respiratory infections compared to non-respiratory infections discharges. Covariates used in the adjusted mortality, length of stay, and cost models included sex, race, payer, critical CHD, admitted for cardiac surgery, Hospitalization Resource Intensity score (in quartiles), presence of complex chronic condition, and type of complex chronic condition.
All analyses used two-tailed tests with a significance level of 0.05. Statistical analysis was carried out using Stata (Version 15, StataCorp, College Station TX) software for survey data analysis.
Results
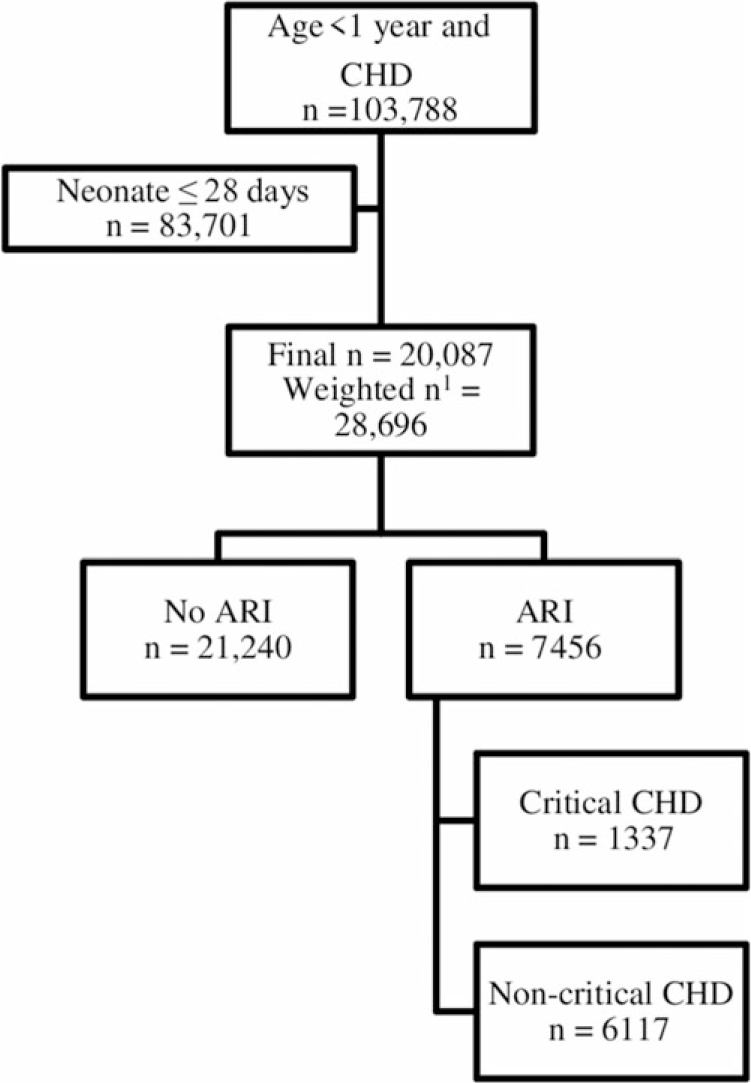
There were 28,696 discharges (including deaths) that met inclusion criteria (Fig 1). Of these, 73% had non-critical CHD and 26% had an acute respiratory infection. The most common non-critical congenital heart lesions were ostium secundum atrial septal defect, ventricular septal defect, and patent ductus arteriosus. The most common critical congenital heart lesion was Tetralogy of Fallot, hypoplastic left heart syndrome, and coarctation of the aorta. Acute respiratory infections accounted for 32% of the hospital days (121, 686 days) and costs ($438 million) for all hospitalisations in children with CHD. The overall mortality rate was 2%.
Flow-chart depicting sample selection, inclusion and exclusion criteria, and subgroups for children with congenital heart disease (CHD) admitted with and without acute respiratory infection (ARI). 1The sample was weighted using a weighting variable provided in the KID 2012 database, to obtain national estimates from the raw data.

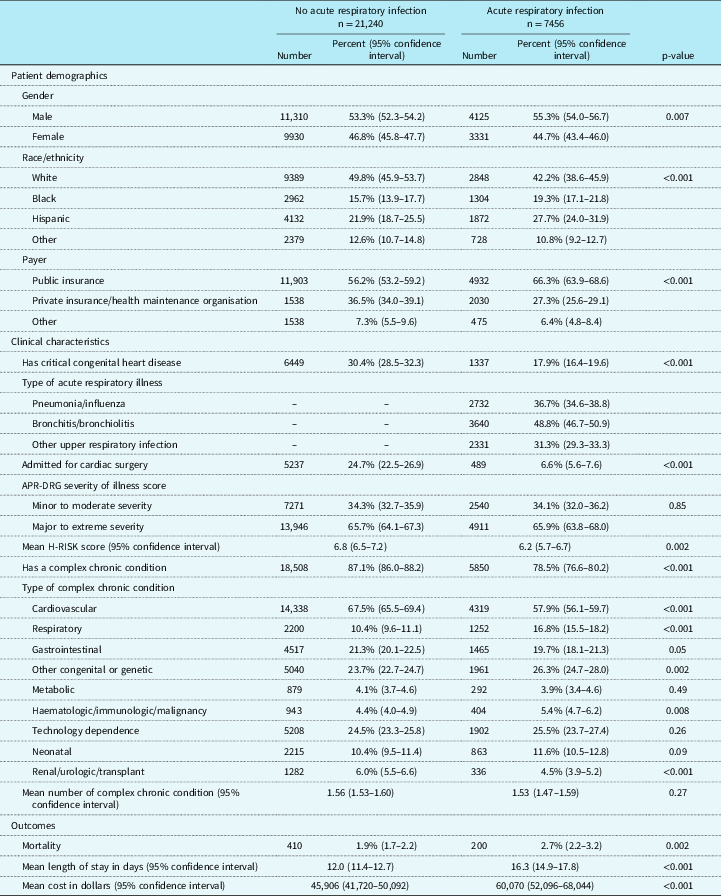
Table 1 compares patient characteristics and outcomes for those without respiratory infections versus with respiratory infections. Patient demographics varied between the two groups: for those with a respiratory infection, a higher proportion of discharges were male, non-white, and had public insurance. Clinical characteristics also varied; a higher proportion of discharges with a respiratory infection had non-critical CHD, was not admitted for cardiac surgery, had a lower mean Hospitalisation Resource Intensity score, and had a respiratory complex chronic condition. Mortality rate was higher in discharges with a respiratory infection, as was mean length of stay and cost.
Patient characteristics and outcomes for infant inpatients with congenital heart disease (CHD) with acute respiratory infection versus without acute respiratory infection.

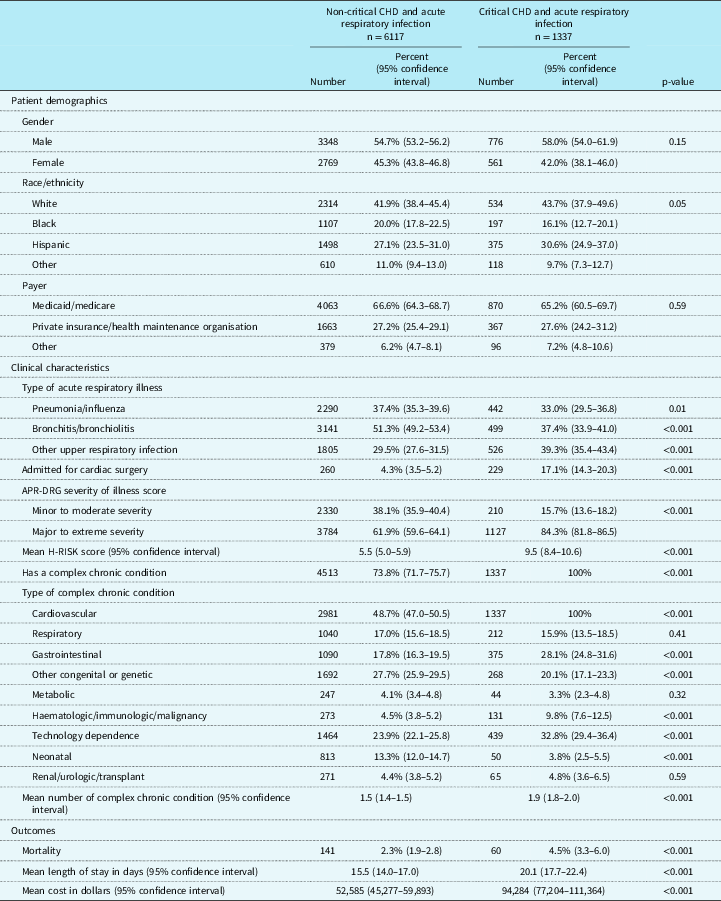
Table 2 shows the differences in characteristics and outcomes for infants with respiratory infections between those with non-critical CHD versus critical CHD. There were no significant differences in patient demographics between groups. The distribution of types of respiratory infections differed between groups, with a higher proportion of those with non-critical CHD with pneumonia and bronchiolitis. The vast majority of children in the ‘Other upper respiratory infection’ group had non-tonsillitis illnesses (with only 55 with tonsillitis). A higher proportion of those with critical CHD had other upper respiratory infections, was admitted for cardiac surgery, and had a gastrointestinal complex chronic condition, technology dependence, or haematologic/immunologic/malignancy complex chronic condition, and had higher mean Hospitalisation Resource Intensity scores. Proportions with respiratory complex chronic condition were similar in both groups. Outcomes were worse in discharges with critical CHD, with more than double the mortality, longer mean length of stay, and higher mean cost.
Patient characteristics and outcomes for infant in patients with acute respiratory infection, with non-critical congenital heart disease (CHD) versus critical CHD.

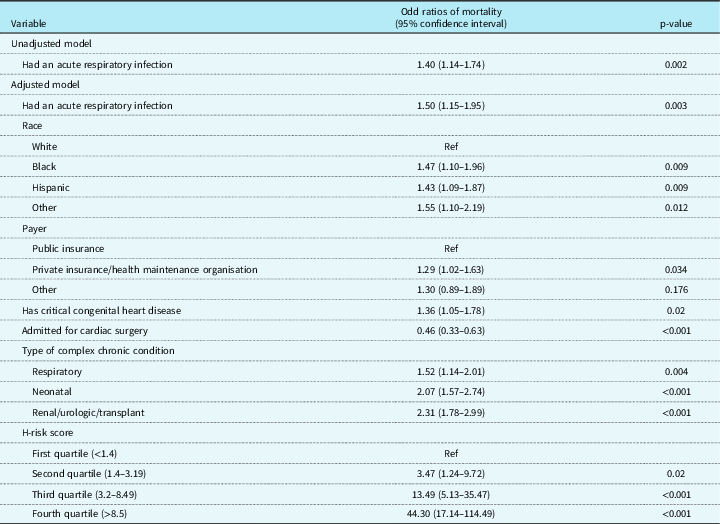
Table 3 displays results of our multi-variable logistic regression model, which shows associations between respiratory infections and mortality, adjusting for demographic and clinical covariates that were significantly different between those with and without respiratory infections. Respiratory, neonatal, and renal/urologic/transplant complex chronic condition; and increasing H-RISK score were all independent risk factors for increased odds of mortality. Non-White race (Black, Hispanic, and Other) was independently associated with increased odds of mortality. Admission for cardiac surgery was independently associated with decreased odds of mortality. Discharges with a respiratory infection continued to have higher odds of mortality (1.50 (95% CI 1.15–1.95)) despite adjustments for covariates.
Logistic regression model for acute respiratory infection and other demographic and clinical covariates versus mortality.

Variables included in model without statistically significant odds ratios: sex, has a complex chronic condition, congenital or genetic complex chronic condition, haematologic/immunologic/malignancy complex chronic condition
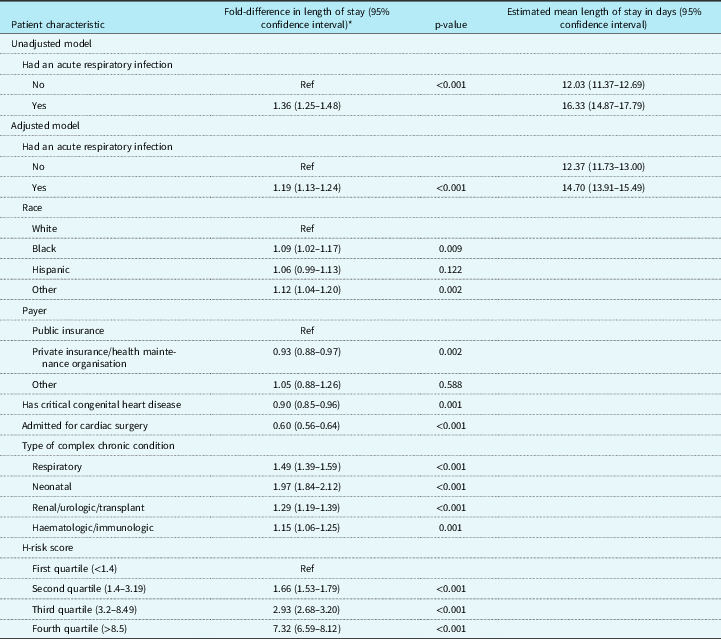
Table 4 displays results of our multi-variable negative binomial regression model which shows associations between respiratory infections and length of stay. Respiratory, neonatal, and renal/urologic/transplant complex chronic condition; and increasing H-Risk score were all independent risk factors for increased fold-difference in length of stay. Black and Other race were independently associated with increased fold-difference in length of stay. Private insurance and admission for cardiac surgery were independently associated with decreased fold-difference in length of stay. Discharges with respiratory infections continued to have higher fold-difference in length of stay (1.19 (95% CI 1.13–1.24)), despite adjustments for covariates.
Unadjusted and multi-variable-adjusted negative binomial regression model of association between acute respiratory infection and length of stay.

Variables included in model without statistically significant fold-different in length of stay: sex, has a complex chronic condition, congenital or genetic complex chronic condition
* Exponentiated Poisson regression estimates (95% confidence interval) estimating fold-difference in mean length of stay (acute respiratory infection/no acute respiratory infection)
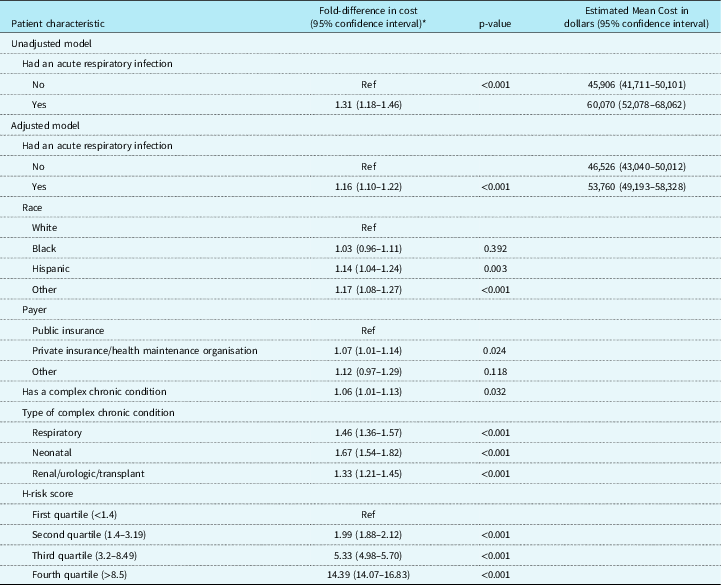
Table 5 displays our multi-variable gamma regression model which shows associations between respiratory infections and cost. Hispanic and other race; respiratory, neonatal, and renal/urologic/transplant complex chronic condition; private insurance; and increasing Hospitalisation Resource Intensity score were all independent risk factors for increased fold-difference in cost. Discharges with respiratory infections continued to have higher fold-difference in cost (1.16 (95% CI 1.10–1.22)) despite adjustments for covariates.
Unadjusted and multi-variable-adjusted gamma regression model of association between presence of acute respiratory infection and cost.

Variables included in model without statistically significant fold-different in cost: sex, has a critical congenital heart disease, admitted for cardiac surgery, congenital or genetic complex chronic condition, haematologic or immunologic complex chronic condition
* Exponentiated gamma regression estimates (95% confidence interval) estimating fold-difference in mean cost (acute respiratory infection/no acute respiratory infection)
Discussion
In this cross-sectional retrospective cohort study of over 28,000 infant discharges with CHD, acute respiratory infections accounted for over 25% of hospitalisations, 33% hospital days, and 33% of costs for all hospitalisations in infants with CHD. Having a respiratory infection during hospitalisation was associated with a higher mortality, longer length of stay, and higher cost compared to those without respiratory infection, particularly in those with critical CHD. The differences in outcomes persisted even after accounting for demographic and clinical differences between those with and without a respiratory infection.
The poor outcomes of infants with CHD with respiratory infections are likely due to a combination of factors. This includes baseline deleterious effects on the lungs by CHD such as lung injury from over or under-perfusion, alterations in the composition of surfactant, and differences in lower airway resistance. Reference Simonato, Baritussio and Carnielli11 Additionally for those with certain types of heart lesions, respiratory infections can precipitate pulmonary hypertensive crisis and/or heart failure. As a result of these factors, infants with CHD and respiratory infections may be more likely to have more severe illness with higher morbidity and mortality. In our study children with critical CHD and respiratory infections had longer mean length of stay, almost double the mean cost, and almost double the mortality rate compared to those with non-critical CHD and respiratory infections, demonstrating that children with critical CHD are particularly susceptible to poor sequelae from respiratory infections. Our study also demonstrated that some co-morbidities such as respiratory complex chronic conditions are independent risk factors for worse outcomes. Respiratory complex chronic conditions were more prevalent in those with acute respiratory infections and were associated with higher odds of mortality, longer length of stay, and higher cost. This supports that the added insult of acute respiratory infections in a child with both cardiac disease and a respiratory co-morbidity can lead to significantly worse outcomes.
The mortality rate in our study of infants with CHD and acute respiratory infections is similar to a that of a study of infants with Respiratory Syncytial Virus and CHD conducted outside the United States, Reference Lee, Chang and Wang12 but higher than one conducted in the United States. Reference Doucette, Jiang, Fryzek, Coalson, McLaurin and Ambrose1 Our mean lengths of stay are longer and our costs higher than the same United States study. These differences can be likely explained by our broader definition for respiratory infections which included illnesses other than bronchiolitis, as well as differences in how we defined critical CHD versus how the United States’ study defined high risk CHD.
Of note, our study demonstrated minority race as an independent risk factor for differential outcomes. All non-White races (i.e., Black, Hispanic, and Other) had significantly higher odds of mortality. Black and “Other” children additionally had significantly increased length of stay, even after controlling for other co-variates, whereas Hispanic and “Other” children had significantly increased costs. Future studies should further investigate the reasons for these differences, including the potential role of systemic differences in the way we care for children of different races, leading to worse outcomes for minority children.
There are several limitations to the current study. CHD can have varying degrees of severity based on the underlying lesion as well as stage of repair which can affect outcomes, and these can be challenging to classify using ICD-9-CM codes. We used non-critical versus critical CHD for our classification system, but there are instances where non-critical CHD such as large ventricular septal defects can lead to significant sequelae from respiratory infections. Due to the cross-sectional nature of the database, we were unable to examine when a respiratory infection occurred during a hospitalisation. Our study relied on the use of ICD-9-CM codes to identify patients who were billed for CHD, and respiratory infections which may not have been accurately coded by the medical coders; therefore, our study may have underestimated the true prevalence of these conditions. These limitations are balanced by some important strengths of our study. The large sample size in the Kids’ Inpatient Database provided adequate power to look at our relatively rare population of paediatric inpatients with CHD and respiratory infections, and the rare outcome of mortality. Additionally, Kids’ Inpatient Database 2012 represents discharges from most states, and from both children’s and non-children’s hospitals which makes our findings more generalisable.
There are several strategies that could potentially decrease the burden of children with CHD with respiratory infections, including measures to decrease the incidence of respiratory infections prior to hospitalisation such as vaccination and measures to decrease hospital-acquired respiratory infections. Palivizumab prophylaxis has demonstrated great efficacy in reducing the morbidity of respiratory syncytial viral infections in infants with haemodynamically significant CHD, Reference Chu, Hornik and Li13–Reference Yount and Mahle15 yet studies suggest sub-optimal rates of administration to eligible infants, Reference Mansbach, Kunz, Acholonu, Clark and Camargo16–Reference Stewart, Ryan, Seare, Pinsky, Becker and Frogel19 and several studies highlight interventions to increase compliance. Reference Afghani, Ngo and Leu20–Reference Golombek, Berning and Lagamma23 Similarly, influenza vaccination reduces mortality in children with CHD, Reference Flannery, Reynolds and Blanton24 yet only about half of children with high risk conditions such as cardiac disease receive it. Reference Santibanez, Lu, O’Halloran, Meghani, Grabowsky and Singleton25 Measures to reduce hospital-acquired respiratory infection include hand hygiene, personal protective equipment when appropriate, patient cohorting in facilities with shared rooms, and judicious hospital visitor restrictions. Reference French, McKenzie and Coope26
New infection prevention protocols will be in effect during respiratory viral season this year in the United States due to the SARS-CoV-2 (COVID-19) pandemic including universal masking of workers in healthcare settings, as well as increased masking and social-distancing in the general populace. Future studies should evaluate the impact of these measures on the overall incidence and morbidity and mortality of acute respiratory illnesses in children with CHD this season.
Lastly, for those paediatric inpatients with CHD who develop respiratory infections despite preventative measures, there is little literature to guide their clinical care. Future studies should assess interventions and care guidelines that may improve the overall clinical course and outcomes of this population, with a particular focus on improving the care of children who are racial minorities and demonstrate some of the worst outcomes.
Supplementary material
To view supplementary material for this article, please visit https://doi.org/10.1017/S1047951120004333.
Acknowledgements
We would like to acknowledge Amir Hassan, BA, Clinical Research Assistant, for his help in creating and formatting the tables for this manuscript.
Financial support
This work was supported by grants UL1TR001855 and UL1TR000130 from the National Center for Advancing Translational Science (NCATS) of the United States National Institutes of Health. The content is solely the responsibility of the authors and does not necessarily represent the official views of the National Institutes of Health.
Conflict of interest
All authors have no potential conflicts of interest to disclose.