Introduction
This paper reviews recent literature on involuntary relocation between nursing homes. It updates Smith and Crome's review of over 40 years of studies of different types of relocation published before 1999, focusing particularly on the relocation of groups of older people when care homes close.Reference Smith and Crome1
Despite finding ambiguous and sometimes contradictory research about effects on mortality and morbidity, Smith and Crome concluded that older people most at risk of adverse outcomes are those with existing physical and/or mental impairments. Moves without preparation carry higher risk.Reference Smith and Crome1 These conclusions had been identified in the literature over the last four decades, following research linking better outcomes to planned and carefully conducted moves and highlighting of high mortality associated with ill-prepared moves. They went on to argue that ‘despite the inherent methodological challenges, review of this literature suggests that the transfer process, preparation for transfer, the degree of change and the health of the population to be moved are important determinants of outcome in terms of mortality and functional mental health status’ (p. 92).
The importance of focusing on process and the conditions before and after moves has also been highlighted in relation to the increased mortality associated with first admissions.Reference Aneshensel, Pearlin, Levy-Storms and Schuler2 If the social causation theory (deaths are caused by the move) co-exists with the social selection theory (people who move into care homes are in worse health and so more likely to die), efforts to improve the process of admission or relocation and the quality of receiver homes will be rewarded by improved survival.
Currently, the rate of closures in England is low compared with the peak in 2000: 114 homes with 2775 places closed in the year to March 2011 compared with 17,000 places in 2000.Reference Laing3 This is attributed to smaller, less viable homes having already closed, and reduced opportunities to sell homes for alternative uses because of the economic down-turn.Reference Laing3 Closures during 2000–2001 resulted in loss of 6% of nursing homes and 4.9% of nursing places, the majority of which were reported to have been good quality.Reference Netten, Darton and Williams4 In the last 3 years the number of new places created has outnumbered those lost by closure to the order of double.Reference Laing3 This reverses the trend of the previous 15 years and suggests that a new balance is being achieved between pressures of need from the ageing population and efforts to reduce admissions to care for reasons of economy and the wish to provide better alternative modes of care. It also means that the number of people experiencing enforced relocation annually has been dramatically reduced.
Why revisit the evidence?
Many of the current clinical, social, economic and political reasons to revisit the research echo those highlighted in 2000.Reference Smith and Crome1 In the UK, families’ fear and anger at closures has led to frequent legal challenges.Reference Jolley, Jefferys, Katona and Lennon5 Recent events have prompted renewed policy interest in the possibility that financial failure of one large care home provider might damage the health, well-being and survival of large numbers of vulnerable people.6, 7 In 2011, the largest UK independent care home provider, Southern Cross, ceased to operate due to financial difficulties linked to public fee levels, reduced occupancy, debt problems and leaseback arrangements. There was intense and emotive media interest, including reports of crisis in care, a political storm, the sudden closure of several hundred homes, concerns that older people would be thrown on to the streets and left homeless or die if forced to move.Reference Shipman8–Reference Riddell11 After it failed to secure lower rents, Southern Cross negotiated the transfer of its homes to other providers, and it seems that ‘no more than a handful of non-viable homes were subject to (such) a threat’ of closure.Reference Laing3 An intention to improve service continuity and provide seamless services more broadly has been highlighted by the coalition government and a discussion paper on the adequacy of and options for market oversight has been followed by a consultation due to be reported in the Autumn of 2012.12–14
Long-term care (LTC) continues to play an important role in the spectrum of health, housing and social care for large numbers of older people: in England around 208,000 places are provided by 4600 nursing homes, and some 261,000 places in around 13,400 care homes without nursing.15 These attract revenue estimated at almost twice that of public spending on community servicesReference Bäumker, Netten, Dening and Milne16 and public expenditure is predicted to grow substantially.Reference Comas-Herrera, Wittenberg, Pickard and Knapp17 In the United States there are around 1.8 million nursing home residents;Reference Harrington, Carrillo, Dowdell, Tang and Woleslagle Blank18 about 238,000 older people live in 4850 residential care facilities in Canada;19 219,500 live in aged care facilities in Australia where the government is encouraging expansion through initiatives such as interest free loans.20 The UK market is increasingly characterized by larger operators, running larger homes, and although there has been a shift from nursing homes (now termed ‘care homes with nursing’) to residential homes (now termed ‘care homes without nursing’) the biggest increase in care home capacity in the last 3 years has been in private nursing homes.Reference Laing3
Increasing proportions of nursing home residents are likely to have characteristics that mean they are at most risk of adverse outcomes if relocated. Levels of dependency are higher than 10–15 years ago, and the proportion of residents with dementia is estimated to be as high as two-thirds.Reference Laing3, Reference Lievesley, Crosby, Bowman and Midwinter21, 22 People with dementia have increased mortality following first admission to a care home, compared with older people with dementia who remain in the community.Reference Aneshensel, Pearlin, Levy-Storms and Schuler2 They are likely to be especially vulnerable to adverse outcomes when relocated. Research in the 1980s and 1990s found increased mortality among older people who moved to institutional care compared with those that did not. Those with cognitive or functional impairment, physical dependence, urinary incontinence, need for intense nursing or psychosocial factors (apathy, lack of social support and social isolation) being particularly vulnerable.Reference Aneshensel, Pearlin, Levy-Storms and Schuler2, Reference Thorson and Davis23 A recent longitudinal cohort study found more than 50% of older people who moved into Icelandic nursing homes over an 11-year period (1996–2006) died within 3 years, and almost one-third of newly admitted residents were likely to need palliative care within 1 year.Reference Hjaltadóttir, Hallbert, Ekwall and Nyberg24 Length of stay (time from admission to death) has declined since the mid-1990s.Reference Bebbington, Darton and Netten25, Reference Forder and Fernandez26
Admissions of older people to LTC may carry the risk of fragmentation of care, and recently transitional care has increasingly been the focus of research and calls for improvement.Reference Boockvar, Fridman and Marturano27, Reference Chhabra, Rattinger, Dutcher, Hare, Parsons and Zuckerman28 Residents and relatives’ reports of routine admission to LTC have long highlighted that these moves are experienced as stressful, unwanted, disruptive, as well as life-threatening events, which are characterized by a lack of time, control over the decision, support and choice of home.Reference Aminzadeh, Dalziel, Molnar and Garcia29–Reference Dohrenwend and Dohrenwend40 If routine transfers are potentially hazardous and need better systems in place, how do similar and sometimes identical systems hold up during care home closures? In the USA and Australia attention has focused on medication errors when older people move to nursing facilities or between hospitals and nursing homes.Reference Boockvar, Fridman and Marturano27, Reference Boockvar, Fishman, Kyriacou, Monias, Gavi and Cortes41–Reference Desai, Williams, Greene, Pierson and Hansen43 Errors of communication, order transcription, pharmacy issues and name confusion, have been associated with patient harm.Reference Boockvar, Fishman, Kyriacou, Monias, Gavi and Cortes41, Reference Desai, Williams, Greene, Pierson and Hansen43
Aims and method
This review had two main aims: to identify and evaluate empirical evidence on the consequences and impact of relocation on individual nursing home residents, and to identify any interventions or recommendations for the management and process of forced relocation to maximize the wellbeing and safety of residents. The review focuses specifically on involuntary collective relocations between nursing homes due to closure.
The Cochrane Database, Medline, Cumulative Index to Nursing and Allied Health Literature (CINAHL), Social Science Citation Index, and PsychINFO were searched for English language articles published between 2000 and Spring 2012. No design criteria were applied. The search used medical subheading terms (MeSH) and synonymous terms for relocation, nursing home, older people, consequences, including mortality, morbidity, stress and preparation and adjustment. Titles were screened by both authors for relevance before articles were retrieved, the nature of the evidence mapped by topic, and data reviewed and synthesized. The review also drew on some articles already known by the authors. Heterogeneity in study design precluded met-analysis. Fuller details of the search methods are available from the corresponding author.
Results of searches
Search of the databases generated over 3500 results and 250 articles of broad interest. These were grouped by general topic area, including empirical studies of forced collective relocation of older people, articles on initial moves to LTC, or nursing home to hospital transfers. When titles were reviewed, 133 were not relevant, or of only background interest. Forty-one were meeting abstracts or letters. Ten recent quantitative studies were found that investigated the effects of involuntary relocation from nursing homes. Only a few articles report research into the closure process.Reference Williams and Netten31, Reference Williams, Netten and Ware44 Papers were excluded from the findings section when reading revealed that they provided only background information about topics, or were beyond the scope of the review, for example articles on end of life care transfers and individual moves from LTC to the community.
While our focus is the relocation of groups of people when care homes close, such relocations are the sum of the experiences of individuals compounded by the mass effects of a group move. Some help in understanding mass relocations may come from a consideration of individual transfers to LTC and between settings. Thus articles on individual relocation, transfer or transition of nursing home residents between different settings were kept and reviewed to reflect the focus of recent relocation research and identify findings or recommendations of relevance to nursing home closure relocation.
Outcomes of forced relocation
Castle's review of empirical studies (1970–1999), which also included studies of different types of relocation, found, like Smith and Crome, inconsistent results, including reports of positive, negative, and, most typically, no changes in outcomes.Reference Smith and Crome1, Reference Castle45 Mortality rates following relocation ranged from 0 to 43% (the latter rate occurred amongst residents moved to a radically different environment within 6 months compared with 21% in a comparison group).Reference Bourestom and Tars46 Positive psychological effects were found when psychiatric patients were moved within a hospital to units with more specialized care,Reference Haddad47 but other studies established statistically significant negative impacts for depression and falls.Reference Castle45 Castle categorized potentially important moderators of adjustment to relocation into four main groups, which are similar to the determinants of outcome identified by Smith and Crome:
(1) characteristics of the people relocated (demographic, physiological, psychological, personality and situational factors);
(2) planning/preparation programmes;
(3) the nature of the relocation (e.g. voluntary or involuntary, inter- or intra-institutional);
(4) the new setting (quality, similarity, wider community setting, population density).Reference Smith and Crome1, Reference Castle45, Reference Castle48
Castle went on to encourage developments in good practice to minimize adverse outcomes. Thorson and Davis similarly conclude that ‘We think that it is honest to conclude that change, and the threat of change, are disruptive to people who are near the end of their lives. Attempting to prepare for and minimise the impact of that change probably is a good idea’ (p. 137).Reference Thorson and Davis23
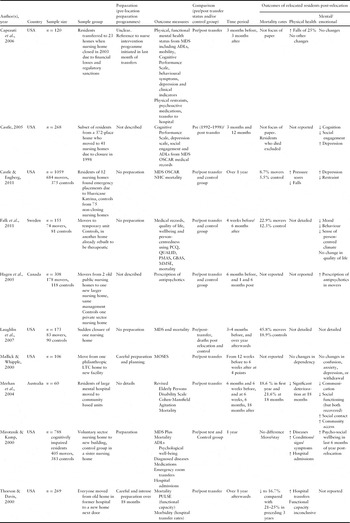
A 2004 study that examined raised cortisol levels as a biological marker of stress showed that the first 3 weeks after relocation are the most stressful for residents.Reference Hodgson, Freedman, Granger and Erno49Table 1 shows the study characteristics and changes found in mortality, physical health and mental/emotional health of relocated older people in the ten empirical studies found. None was conducted in the UK. Seven are from the United States, and one from Canada, Australia and Sweden. Four studies explored the impact of inter-institutional relocations between nursing homes due to closure. Reference Castle48, Reference Capezuti, Boltz, Renz, Hoffman and Norman50–Reference Laughlin, Parsons, Kosloski and Bergman-Evans52 Studies of other types of forced mass relocation found include nursing home to nursing home relocation involving mass moves to new replacement facilities,Reference Thorson and Davis23, Reference Hagen, Esther, Ikuta, Williams, Le Navenec and Aho53, Reference Mirotznik and Kamp54 of which two concerned moves to a new building under the same management,Reference Hagen, Esther, Ikuta, Williams, Le Navenec and Aho53, Reference Mirotznik and Kamp54 an evacuation due to natural disaster,Reference Castle and Engberg51 a temporary mass move,Reference Falk, Wijk and Persson55 and relocation from a large mental hospital to extended care units.Reference Meehan, Robertson, Stedman and Byrne56
Summary of relocation study characteristics and changes in physical and mental function published since 2000, showing which studies found increases (↑) and/or decreases (↓), and/or no change post-relocation

Overall, 2258 relocated residents’ outcomes are reported across the studies, with the samples of movers ranging from 60 to 684 older people. Study design varied. Half used a control group as well as baseline pre-transfer measures. Reference Castle45, Reference Laughlin, Parsons, Kosloski and Bergman-Evans52–Reference Falk, Wijk and Persson55 Half used before and after measures only.Reference Thorson and Davis23, Reference Castle48, Reference Capezuti, Boltz, Renz, Hoffman and Norman50, Reference Meehan, Robertson, Stedman and Byrne56, Reference Mallick and Whipple57 Several were retrospective.Reference Castle48, Reference Laughlin, Parsons, Kosloski and Bergman-Evans52 Time periods of follow-up ranged from 6 weeks to 18 months post-relocation. Preparation programmes were provided in three cases, each of which concerned planned moves, with longer lead-in times involving relocation to new facilities.Reference Thorson and Davis23, Reference Mirotznik and Kamp54, Reference Mallick and Whipple57
Of the ten studies presented in Table 1, six reported mortality, four physical health changes, and eight psychological changes. Three found deaths increased amongst relocated residents compared with those in control groups, with rates ranging from 8.7 to 45.8% of relocated residents,Reference Castle and Engberg51, Reference Laughlin, Parsons, Kosloski and Bergman-Evans52, Reference Falk, Wijk and Persson55 and another found that 21.6% of relocated patients died within 18 months but considered this to be within the usual mortality range of such patients.Reference Meehan, Robertson, Stedman and Byrne56 One study found no difference in death rates between relocated and control groups,Reference Mirotznik and Kamp54 and another that death rates fell compared with those in the preceding 3 years.Reference Thorson and Davis23
The clinical outcomes of residents forced to move in 2002–2003 from a Philadelphia nursing home, primarily funded by Medicaid, which closed due to financial failure and inability to correct regulatory deficiencies, were tracked using secondary analysis of data collected to evaluate an advanced practice nurse intervention put in place to reduce stress during the final months of the discharge period.Reference Capezuti, Boltz, Renz, Hoffman and Norman50 The paper reports secondary analyses. Results of the primary intervention study were not found. Relocation was associated with a significant increase in the number of residents who fell, compared with before the move. The increased likelihood of falling applied to both those with and without a falls history, was higher for those with a falls history, and was associated with mobility. The increase in falls in those without a history of falls suggests there is a need for extra falls precautions and preventions in homes receiving older people from home closures.
Twelve nursing homes in southern Louisiana closed as a matter of urgency when Hurricane Katrina caused widespread flooding and damage in 2005, and 684 residents found alternative accommodation wherever a suitable bed could be found. This unique natural experiment was used by Castle and EngbergReference Castle and Engberg51 to report on the outcomes for these residents compared with matched residents of similar homes that were not closed: as near as anyone has come to a controlled trial of emergency relocation. This study is one of several that have taken advantage of high-quality routine data, including the Minimum Data Set (MDS),Reference Rahman and Applebaum58 and facility level data (Nursing Home Compare, NHC)59 and On-line-Survey Certification and Recording (OSCAR)60 in the USA. The MDS describes individual residents in detail at the time of admission, annually and at times of special events. Relocated residents showed more depression, more pressure sores and more deaths (8.7 vs. 5.4%, P < 0.01). Relocated residents were approximately twice as likely to die during a 4-month period but less likely to be restrained or to fall. Castle and Engberg concluded that since decline in resident health status is possible after a forced relocation, facilities should dedicate additional resources to residents who are admitted following such relocation.Reference Castle and Engberg51
Laughlin and colleagues remind us that death and disability can follow relocations ushered by less dramatic forces than Katrina:Reference Laughlin, Parsons, Kosloski and Bergman-Evans52 in a secondary analysis of data from the PhD theses of LaughlinReference Laughlin61 and ParsonsReference Parsons62 they report on the relocation of 83 people. These residents were informed 6 weeks before the move. There were no subsequent preparation discussions or meetings; placements were determined by the availability of a bed. The only outcome reported was mortality within a year: 38/83 of those relocated died compared with 17/90 of controls. Half the deaths amongst movers occurred within 3 months. People over 85 years had the highest mortality. The authors conclude that relocation produced excess deaths and go on to suggest ways in which such deaths might be minimized: providing choices, creating predictability and maximizing residents’ strengths. These are intuitive and echo similar suggestions established in the literature.
Castle reported an additional analysis using MDS and OSCAR data, supplemented by review of medical records to explore changes in health status through measures of cognition, mood, engagement and activities of daily living (ADL) from the MDS, but not mortality, when a large nursing home closed in 1998.Reference Castle48 Cognition and engagement fell in the 12 months post-relocation and depression scores were higher (all at P > 0.05% significance). These effects were more marked at 3 months. There is no control group in this study, so it could be argued that time and ageing contributed to the declines, the peak of change at 3 months and drift back toward previous scores argue for a relocation effect.
Turning to moves between facilities, Thorson and Davis describe the careful relocation of 269 people from an old county home for the aged to a new building.Reference Thorson and Davis23 Preparation began 18 months in advance. Residents were assessed using the PULSES (Physical Upper limb, Lower limb, Sensory, Excretory, Social/Emotion) scale.Reference Moskowitz and McCann63 PULSE scores appeared to predict likelihood of death. However, the authors decided that little could be concluded from this because those with the greatest level of disability were also the most likely to die irrespective of relocation. The annual rate of deaths after relocation was lower than the previous 3 years and the number and rate of deaths was actually highest in the year pre-relocation. Suggested interpretations are that while the preparation programme may have minimized mortality after relocation, it may also have hastened deaths in the year before.
Hagen et al.Reference Hagen, Esther, Ikuta, Williams, Le Navenec and Aho53 monitored changes in the prescription of antipsychotic medication in a Canadian relocation: the setting was two ‘low-grade’ homes, the residents of which were transferred to a new 190-bed unit ‘designed to provide a more social and less institutional atmosphere’. Data were collected 6 months pre-move, and 1 month and 6 months post-move. Prescription of antipsychotics rose from 21.5 to 32.6% and then to 36.9%. Comparative figures from a 118-bed unit in the same area that was not involved with relocation remained stable: 30.3, 30.5 and 33.1%. There is useful reference to studies of antipsychotic prescribing in Europe, Australia, Japan, the USA and Canada and the impact of the Omnibus Budget Reconciliation Act (OBRA)64 on such prescriptions in the USA. The rates described in these Canadian homes are high. Prescription rates were lowest in the two ‘low-grade’ homes which it was deemed should be replaced. Whether the change in prescription rate resulted from altered behaviour of residents is unclear, for there is no report of behaviour, health or death rate.
Mallick and WhippleReference Mallick and Whipple57 question the phenomenon of relocation stress syndrome when they found no significant changes in rates of dependency, confusion, anxiety, depression or withdrawal (the five elements associated with the diagnosis) after a long planned relocation of 106 residents from an old facility to a larger facility with more specialized care. They used the Multidimensional Observation Scale for Elderly Subjects (MOSES).Reference Helmes, Sapo and Short65 The findings may reflect the long length of notice, availability of a patient advocate and social worker, resident involvement in room allocations, careful planning of moves over 5 days, and the move to a better environment with more care. The sample included some younger adults.
Mirotznik and Kamp explore whether people with cognitive impairment are more vulnerable to relocation effects at three relocation periods: pre-relocation, and short- and long-term post-relocation.Reference Mirotznik and Kamp54 Using eight outcome measures for physical and psychological morbidity and mortality, they found that movers experienced negative health outcomes: accruing more conditions, signs and symptoms, diagnosed diseases, and hospital admissions. These effects spanned all three relocation periods. Inexplicably they found that compared with non-movers, relocated residents were less likely to die and more likely to have improved psychological health in the last 6 months of the 12-month post-relocation time period. No evidence, however, suggested that people with severe cognitive impairment were more at risk than other relocated older people. In a study (776 residents) of single-person intra-building room transfers, Mirotznik again found older people with cognitive impairment were at no greater risk than cognitively intact residents.Reference Mirotznik66
A Swedish study of the effects of a temporary mass move to a facility 7 miles away for 1 year while a new facility was built focused on the quality of life, wellbeing and perceived person-centredness of the environment of residents.Reference Falk, Wijk and Persson55 A mixture of self-reported and proxy measures were used: Person-centred Climate Questionnaire (PCQ, self reported);Reference Edvardsson, Sandman and Rasmussen67 Quality of Life in Late-Stage Dementia Questionnaire (QUALID, a proxy measure);Reference Weiner, Martin-Cook, Svetlik, Saine, Foster and Fontaine68, Reference Falk, Persson and Wijk69 Patient Mood Assessment Scale (PMAS, a proxy measure);Reference Edberg70 and General Behaviour Assessment Scale (GBAS, a proxy measure).Reference Edberg70 Proxy measures were used for individuals with MMSEReference Folstein, Folstein and McHugh71 less than 21; self report was used where Mini Mental State Examination (MMSE) was 21 or greater. MMSE scores fell in both groups. QUALID did not change in either group. PCQ, PMAS and GBAS all deteriorated in movers. Mortality was greater amongst movers: 17/74 moved, 10/81 controls (chi-square: P = 0.08). Interviews at 10–12 weeks post-relocation revealed that residents felt the move, carried out over 1 day, had been poorly organized, the temporary accommodation cold, institutional, confusing and not liked. Staff reported discontent. Thus a poorly organized relocation was associated with adverse effects on the people it was intending to help in the longer term.
Meehan et al.Reference Meehan, Robertson, Stedman and Byrne56 provide positive perspectives of outcomes for older patients with mental illness relocated from a psychiatric hospital to community-based extended care units in Australia. Sixty patients moved from the hospital to units with 8–22 beds. Patients were elderly with diagnoses of schizophrenia (50%), dementia, mood disorder or Korsakov Psychosis. One person died in the 6 months before the relocation, 11 died within a year and a further two by 18 months. Four patients moved on to a nursing home, three to hostels and one returned to their home of origin. Measures from the Revised Elderly Persons Disability ScaleReference Fleming72 and Cohen-Mansfield Scale for AgitationReference Cohen-Mansfield73 demonstrated significant deterioration in communication, general health and sociability following relocation. Deterioration in general health persisted, but communication and sociability returned to previous levels after falling in the period from 6 weeks before to 6 weeks after relocation. The death rate within the first year, which is five times that within the cohort in the previous 6 months and 2.5 times the rate in the following 6 months, is said not to be significant because: ‘the majority died of medical conditions’ and ‘it is similar to the mortality rate for patients in the wards from which the patients were discharged’.
Some research has sought to highlight other types of negative and positive outcomes that may be associated with relocation and nursing homes. A small qualitative Swedish study reports the outcomes of one nursing home closure from the perspective of 11 staff.Reference Flackman, Hansebo and Kihlgren74 It found that staff reported negative effects, including less control over their work, and a loss of their spirit of comradeship. Staff of closing homes have also reported feeling stress, grief and bereavement, concern about the welfare of relocated residents and an intention to stop working in the sector.Reference Holder75 Possible positive resident outcomes include improvements in quality of care, frequency of visits from relatives and geographical locations.Reference Holder75
White and Seagrave report an interesting analysis of patient outcomes when Hospital Based Skilled Nursing Facilities (HBSNF) closed between 1997 and 2001.Reference White and Seagrave76 The closures occurred because Medicare withdrew additional funding for patients moved into such facilities. At the same time the provision for home care was reduced. They found that closures were associated with patients staying in acute hospital beds for longer, increases in the costs of each admission episode, and increased use of free-standing nursing facilities where funding was still available. Mortality in the patients admitted to hospitals without HBSNFs was lower at 30, 120 and 360 days than in ‘controls’ that still provided them. Messages here may be that loss of this in-house nursing facility was found to be compensated by increased use of acute beds (the delayed discharge scenario), perhaps in part because of the lack of funds for alternative care at home. This change had a sustained benefit in reduced mortality, perhaps because of the non-availability of relocation to the ‘step-down’ type of wards.
The care home closure process
Little has been published on the process of care home closure, or evaluations of efforts to improve outcomes. While relocation teams, assessment tools, the promotion of involvement and a sense of control, as well as familiarity with the new setting have all been recommended to promote successful relocation,Reference Castle45, Reference Holder75 there has, and continues to be, a gap in knowledge about what elements of planning and preparation programmes work. Studies of independent sector closures in England 2000–2001 highlighted the need to clarify the role and responsibilities of the national regulator, and the legal responsibilities and powers of local government.Reference Williams and Netten31 Local government guidance on voluntary closures was patchy and arrangements, procedures and recommendations varied between councils: some reviewed only those whose needs were thought to have changed, some only publicly funded residents, and some self-funded residents only if they had no relatives or were unable to make arrangements themselves.Reference Williams and Netten31 In contrast, the Welsh Assembly Government (WAG) has produced statutory guidance on the responsibilities of local authorities, local health boards and NHS trusts during closures.77 It states that commissioning agencies should intervene to improve the quality of services and where possible prevent avoidable closures. Case studies conducted in England found that providers’ notice could be as short as 3 weeks, and choice of home was restricted by lack of information, lack of homes, lack of time and delays in assessments.Reference Holder75, Reference Darton, Williams and Netten78, Reference Darton, Williams and Netten79
Findings from this research have been incorporated with other good practice recommendations in recent guidance for councils from the Association of Adult Social Services (ADASS) and Social Care Institute for Excellence (SCIE).Reference Glasby, Robinson and Allen80 Relatives and residents should be listened to, given no less than 2 months notice by providers, told the reasons for closure, what will happen, how they will be helped and by whom, informed of any changes, contacted promptly by local government care managers, preferably organized into small teams offering continuity of care, vacancy information, support to find appropriate new homes, and access to an independent advocate. Other good practice guides for England have also been published or updated in the last decade offering detailed suggestions about managing information, and practicalities as well as issues for providers to consider in relation to their employees’ concerns, rights and potential loss to the sector.81
In his commentary on the issues raised by closures for local authorities, Scourfield argues that social work contains the professional skills and approach required by individual and group needs during closures but doubted ‘care management,’ focused on instrumental practices, can provide these.Reference Scourfield82 Williams et al. (2007)44 suggest that care managers find a way. Dubin suggests that Coleman's concept of ‘transition coaches’, proposed in relation to community care, might be applied here and that nurse practitioners are well placed to fulfil the role.Reference Dubin83, Reference Coleman, Parry and Chalmers84
A recent Welsh study recommended the guidance in Wales be strengthened further: the regulator should collect and distribute detailed information about routes to closure, successful prevention, and the processes involved to identify and share good practice; financial health of independent providers should be a prerequisite of registration, it should be monitored by the regulator and concerns shared with local authorities.Reference Burholt, Beech and Winter85
Initial moves to LTC and moves between care homes and hospitals
Older people and their relatives rarely feel involved or in control of the decision to move to LTC and would value advice and support on how to compare homes.Reference Davies and Nolan30, Reference Nolan and Dellasega36, Reference Ryan and Scullion39, Reference Davies, Sandberg, Lundh, Warnes, Warren and Nolan86, Reference Tanner87 Factors identified as important span the activities of health and social care professionals and care home providers: effective communication between care providers and agencies including hospitals and LTC facilities, provision of accessible, useful and timely information, involvement of family members and the older person in the decision-making process. People seek a sense of control, holistic streamlined interdisciplinary assessments, help during the search and selection process, standardization of application forms, sufficient time to visit homes and make a decision, and improved advocacy services.Reference Cheek, Ballantyne, Byers and Quan88–Reference Cheek and Ballantyne90 Patient-centred care teams rather than institution-centred care teams are recommended,Reference Parry, Coleman, Smith, Frank and Kramer91 as is the education of relatives and older people's representatives about the importance of respecting older people's decision-making autonomy.Reference Johnson, Popejoy and Radina92 Cox describes a pilot scheme where a ‘LTC ombudsman’ helped people deal with any difficulties associated with the transition process between hospital and care homes.Reference Cox, Bylina, Krogmann and Krambeck93
Chabbra reviewed studies of medication reconciliation interventions to overcome difficulties and failures of communication that result in older people receiving the wrong medication on transfer to and from LTC.Reference Chhabra, Rattinger, Dutcher, Hare, Parsons and Zuckerman28 The appointment of pharmacy transition co-ordinators with specific responsibilities for managing medication when older people move between settings have been shown to improve prescribing practice, although evidence is limited by study design flaws.Reference Chhabra, Rattinger, Dutcher, Hare, Parsons and Zuckerman28, Reference Crotty, Rowett, Spurling, Giles and Phillips42
Recommendations to support adaptation after a move include the use of story sharing, close monitoring of residents’ adaptation for up to 3 months, and the creation of a transitional care team, to include the resident, their representative(s), a nurse, care assistant, activities director, social worker, physician, dietician and chaplain,Reference Heliker and Scholler-Jaquish94 the use of introduction and orientation programmes for resident and family and monitoring of residents to identify signs of relocation stress syndrome.Reference Kao, Travis and Acton95
Turning to later transfers, it is likely that most movement of individuals between homes is from care homes without nursing to care homes with nursing. The frequency and nature of such moves in the UK is under-explored, but a small scale study found 33% of 225 residents experienced one relocation and 4% two or more moves.Reference Cook, Reed, Sullivan and Burridge96 Lewis pointed to the dynamics of nursing home life in the USA: only 37% of 197 people admitted to 24 nursing homes died in their first home, 54% going on to be ‘transferred frequently between hospitals and other nursing homes’.Reference Lewis, Cretin and Krane97
Hertz and colleagues in the USA propose a framework for use in planning and focusing practice before an individual is relocated and monitoring outcomes afterwards.Reference Hertz, Rossetti, Koren and Robertson98 Five outcome measures are proposed: the older person will be satisfied, social networks and activities will be maintained, health status will be stable or have improved, their needs will be met and they will remain at the new home for at least 6 months. Interventions should support autonomy, control, social activities, personal interests, social contacts, coping with loss and continuity of care.Reference Hertz, Rossetti, Koren and Robertson98 The 15-item Care Transitions Measure may be adaptable to care home closure.Reference Coleman, Mahoney and Parry99 There is a short 3-question version, which focuses on preparation to participate in post-hospital self-care and on what staff actually did rather than on what they may have asked the patient.
For people with dementia (PWD), there remains a paucity of evidence about what supportive strategies might involve and what works. Recent recommendations include taking time to identify preferences and needs and develop appropriate strategies; education of staff in strategies that can be used to cope with change, such as ‘reframing’ of identity and experience, ‘obeying’, and ‘normalizing’ of losses associated with old age. The use of attentive and empathic listening techniques helps gain understanding of a resident's preferences and concerns.Reference Aminzadeh, Dalziel, Molnar and Garcia29, Reference Aminzadeh, Dalziel, Molnar and Garcia100
Discussion
The view that a poorly managed transfer could have a negative impact on life expectancy, and that adverse effects can be moderated by careful planning, has already been accepted by the European Court of Human Rights ruling based on the case of Louisa Watts.Reference Jolley, Jefferys, Katona and Lennon5 While evidence on the impact of forced relocation continues to be mixed, the evidence suggests that there is a link between organized relocations and better outcomes and equally between disorderly relocations and negative health outcomes. Recent evidence continues to suggest that preparation is an important moderator.
The majority of the studies that found adverse outcomes involved situations where there was little or poor preparation for the group transfers, or where information about preparation was unavailable. Negative health outcomes associated with relocation include increased falls, pressure sores, diseases and conditions/signs/symptoms, and hospital admissions. Negative psychological outcomes associated with relocation include deterioration in depression, cognition, social engagement, mood, and behaviour. Death rates ranged from 0 to 45.8%, which is similar to the range identified in the review published in 2000. The highest rate occurred in relation to a sudden relocation with no preparation. The White and Seagrave paper found sustained reduction in mortality where moves in hospitals were curtailed.Reference White and Seagrave76
The one study that reported no adverse consequences involved careful preparation and planning.Reference Mallick and Whipple57 The two other studies of relocation that included careful preparation also found no increase in mortality, although other negative outcomes were found in relation to physical health.Reference Thorson and Davis23, Reference Mirotznik and Kamp54 Thorson and David's suggestion that their finding of a reduced death rate following a rise during the year prior to the move may indicate that preparation programmes may hasten death, is thought-provoking.Reference Thorson and Davis23
As in the past, where improved outcomes were reported they were associated with relocations of people to better quality settings, such as from an old psychiatric hospital to community-based units, or from an old nursing home to a new building. It would be unwise to discard the good practice recommendations for supporting people with dementia and similar conditions based on the suggestion of one study that cognitive impairment does not dispose to greater risk when people are to be relocated.Reference Mirotznik and Kamp54 It is at odds with previous findings, experience and intuition, and future studies and audits should check and report their own findings on this issue.
A worrying increase of 25.7% in fall ratesReference Capezuti, Boltz, Renz, Hoffman and Norman50 is counter-balanced by a finding of less falls in a later study.Reference Castle and Engberg51 However, the authors suggest that this may be because providers are aware of this potential hazard and put in place practices to counter-act it. Increased prescription of antipsychotics was found amongst older people moved to a new building compared with non-movers,Reference Hagen, Esther, Ikuta, Williams, Le Navenec and Aho53 and less restraint use was found amongst people evacuated due to Hurricane Katrina.Reference Castle and Engberg51 Both scenarios could simply reflect the practices of the receiving facilities, rather than the behaviour of residents. Others have found deterioration in behaviour,Reference Falk, Wijk and Persson55 increased depression, and worsening cognition, social functioning and communication particularly in the first 6 months.Reference Castle48, Reference Castle and Engberg51, Reference Meehan, Robertson, Stedman and Byrne56 However, others found no change in physical or psychological health,Reference Mirotznik and Kamp54, Reference Mallick and Whipple57 or concluded that where deterioration (or death) was found it resulted from age rather than relocation.Reference Meehan, Robertson, Stedman and Byrne56
It would seem sensible for professionals involved in managing care home closures to consider the challenges and recommendations for good practice during initial moves to LTC and subsequent transfers to and from LTC. There is considerable consensus about what hinders and what is likely to promote a ‘positive’ experience when older people move to a care home for the first time, and on the need for staff in receiving facilities to plan ways in which they can support individuals.
Much of the literature highlights older people and their relatives’ experiences of poor practice. It would be useful to find out the impact of ‘good’ quality transitions on people's experiences and outcomes. The information available to the public about care homes in the UK has increased, mostly in the form of web directories. It remains to be seen how helpful this information is in supporting choice of home when residents and families have to find vacancies in a hurry. Some progress has been made in identifying ways in which people with dementia might be supported when moving to LTC, but more detailed practice development and evaluation is still needed in this area. Research on the measurement of the quality of care transitions from hospital is an area that has potential to be adapted for use during nursing home relocation.
Hertz's broad outcome framework for preparation before relocation focused on outcomes for people without cognitive impairment.Reference Hertz, Rossetti, Koren and Robertson98 They may be considered ambitious given what is written about people's experiences of relocation. The proposed outcome areas are similar to other quality-of-life-based outcome indicators for social care (e.g. ASCOT)Reference Netten, Forder and Beadle-Brown101 and so suggest that normal good practice goals should apply to relocations as well as everyday service provision.
Smith and Crome highlighted the many methodological and analytical challenges to conducting ‘scientifically’ robust research in this field, and the limited or contestable nature of the evidence.Reference Smith and Crome1 Conducting randomized controlled trials is impractical and inappropriate. Studies are, therefore, usually naturalistic or opportunistic. The validity and generalizability of relocation research prior to 2000 was limited. Much of the recent evidence has the same limitations, including lack of control groups, reliance on pre/post test measures, relatively small sample sizes, variation in measurement tests, variation in time periods, variation in the types of potential outcome explored, and failure to consider factors that might influence outcome. Such limitations are generally acknowledged. Potential confounding factors that could be explored include the impact of falling standards of care during closure periods, of anticipation of relocation, of preparation programmes on residents’ health before a move, the nature of the transfer process including planning and preparation, and the potential impact of the admission practices, quality of care and setting of receiving homes.
There have been some positive methodological developments linked to data developments in the USA. More recent studies have taken advantage of the ability to analyse national data resulting from the rigorous requirement to monitor residents and the facilities of care homes in the USA. From a research standpoint, it would be useful to have a similar requirement in other countries.
Nevertheless, it remains the case that only a small number of relocations are reported in the literature and these often take a particular perspective. Within the recent papers summarized here, texts sometimes present a more reassuring picture than the statistics. The subtleties of relocation such as the emergence of delirium as a complicating factor, or the impact of new social care or medication regimes will require greater detail of observation than is likely to be gleaned from routine data. Similarly, the gain in statistical power of larger studies is offset by a lack of information and understanding of the nature of the transfer process, preparation and mechanisms. These combined with information about the context and conditions may help identify what works for whom. The advantage of fieldwork studies remains to be fully realized, though the papers from Sweden and elsewhere that consider the experiences of staff and residents are illuminating and thought provoking.
In the USA, there have been calls for a protocol for tracking residents after relocation and for the information to be held in a national database to help identify best practices.Reference Capezuti, Boltz, Renz, Hoffman and Norman50 In the UK, absence of routine national reporting of the number and type of care home closures, the number and reason for individual transfers between facilities, and of the health of individual residents means it is impossible to conduct the sort of studies now possible in the USA. It would be useful to have the ability to track residents in the UK and other countries.
Currently, plans to reduce the burden of data collection on local authorities suggest that tracking of older people in their care journeys will be introduced but restricted to short-term preventative services.102 Lack of monitoring may affect accountability, which in turn may have negative consequences for practice and opportunity for research. It would be useful to know the number of closures by home type, location, whether closures were voluntary, if providers perhaps ‘jumped before they were pushed’, the length of notification given to the regulator and to residents/relatives/local authorities, the main reasons for closure, the existence and content of any resident preparation prior to the move, the overall quality of the care home, whether the home had any deficiencies, and if so the number and severity.
The ADASS and Social Care Association guidance on managing care home closure are positive developments that bring together recommendations for practice.Reference Glasby, Robinson and Allen80, 81 Many of the recommendations are drawn from opinions, supplemented by research findings from the perspectives of people with recent experience. There is a need for more practice-based research and explorations of whether recommendations are being put into practice, whether closures are orderly, and what outcomes are achieved.
Issues that remain include how care homes might be encouraged or obliged to follow good practice during closures and who should have responsibility for ensuring that they do so. Should some good practice be made obligatory, and if so, how can it be enforced and by whom? The Welsh Assembly Government has clarified its approach to closures. In England, however, there is still no legislation or central government guidance specifically defining the roles, powers and responsibilities of councils, NHS bodies, or the regulator during planned care home closures, or ownership transfers. The Care Quality Commission (CQC) does not appear to have a policy relating to their role during care home closure periods or ownership transfers. This would be useful for such periods are times of potential risk.
Lack of on-going monitoring of the financial viability of care homes is a key concern. The CQC's approach is similar to that of the previous social care regulator; it is not a financial specialist. They provide only non-technical oversight of the financial position of providers when they register, and financial viability is not subject to routine monitoring.Reference Malley, Holder, Dodgson, Booth, Mor, Leone and Maresso103 The current legal requirement for providers to notify the regulator within 6 months if they cease to be financially viable, or will close, is unlikely to guarantee that closures due to financial failure are identified and managed in a timely way.Reference Malley, Holder, Dodgson, Booth, Mor, Leone and Maresso103 Notification within 6 months would be too late to act as a ‘warning’ system. While councils also place requirements around viability and notification of closure on providers when they commission care, it is unlikely that they have the expertise and resources to conduct on-going assessment of financial stability.
The UK coalition government is introducing major national policy changes that should address some of these issues. The recent White Paper on Social Care highlights a consultation on possible steps to ensure service continuity should a provider fail.14 This consultation, the collection of more information about the market by ADASS and the CQC, and meetings with major providers to discuss their financial situation all suggests a firm commitment to ensuring earlier identification of provider failure. It has been made clear that any changes will need to be in keeping with the priorities and principles of minimizing burden on providers and local government, of cost effectiveness and proportionate response, and that the government will not protect private care home providers from risk or insure them against failure.14 The exact role of the regulator remains unclear, but it is likely that any oversight provided by councils would be limited to those care homes from which they commission.
The lack of a clear legal framework for the provision of adult social care services in the UK underpins the lack of clarity around local authorities’ responsibilities when a private provider fails.Reference Williams and Netten31 The legislative changes proposed in the Care and Support Bill should go some way to clarifying councils’ roles during closure situations.104 The way in which the reform of social work, and introduction of independent social worker led organizations to augment and complement the work of local authorities, affects older people's experiences of relocation to and between LTC settings is an issue that warrants evaluation; particularly in terms of influence on lines of accountability and responsibility. The impact of new commissioning arrangements is another uncertainty.
The British Geriatrics Society has recently called for more professional collaboration, multi-agency and multi-professional leadership to improve the healthcare support provided to older people living in care homes.105 The Royal Pharmaceutical Society (2011) has published guidance on keeping patients safe when they transfer between care providers.Reference Picton106 A Charter of Rights for people with dementia and their carers has been launched in Scotland.107 In the USA, the National Patient Safety Goal (NPSG) for ensuring medication reconciliation is maintained and communicated across the continuum of care, includes goals for hospitals and LTC providers.108
Conclusion
Nursing homes and residential homes continue to provide an important component within the spectrum of care services for older people, but their place and functions are changing. This means that there will always be the prospect that some will close to give way to new versions of care. Happily the rate of closures in the UK and other countries has fallen since the peak in the millennium. Although the literature appeared to be moving away from trying to establish whether the relocation of older people causes negative outcomes as far back as the 1980s, the question about whether forced moves causes unnecessary deaths continues to be asked. It is an important question, but establishing valid and generalizable causal links and explanations between a life event and health outcome is challenging.
It may be time to acknowledge that the question of whether forced relocation between nursing homes causes negative outcomes cannot be established in a way that involves randomized controlled trials, the method given priority in the hierarchy of evidence. The recent evidence suggests that ill-planned or casually implemented closure and relocation is stressful and linked to adverse outcomes in terms of symptoms, health and survival, and that careful, respectful, person-centred planning and implementation of closure and relocation moderates the likelihood of adverse outcomes.
Castle's observation that the elements of planning and preparation that are most effective are largely unknown remains true. There is a lack of research into outcomes tied to residents’ and relatives’ preferences, the effects of relocation on social networks, social support (size and level and nature of contact), including family, former informal caregivers, friends living in the closed home, care home staff, and in turn social life and social well-being, and more widely effects on social capital and social participation in the community, as well as the new home. The extent to which mass moves from care homes involve short-term moves while places in preferred homes become available, or are followed by additional moves due to dissatisfaction or inappropriate care is another unexplored area. Further studies would also benefit from a more comprehensive idea of what a good relocation and transfer process should look like from the perspectives of all stakeholders (including health and social care professionals), and just what management practices and interventions should be trying to achieve in terms of process and outcome.
Residents and families should be made aware that closure and relocation are a real possibility when they move to long-term care, just as they should be made aware that they may need to move to a new facility to receive nursing or dementia care. A Residents’ Charter including information about what to expect if they find themselves involved in such events would help.
Conflict of interest
The authors declared no conflicts of interest related to this paper.