Despite coronary artery fistula being a rare congenital malformation, it is the most common congenital coronary artery anomaly with haemodynamic significance.Reference Armsby, Keane, Sherwood, Forbess, Perry and Lock1, Reference Latson2 Closure is indicated for the large coronary artery fistula to prevent complications. Transcatheter closure of the coronary artery fistula is possible by using coils, detachable balloons, umbrellas, polyvinyl alcohol foam, and a duct occluder.Reference Armsby, Keane, Sherwood, Forbess, Perry and Lock1, Reference Latson2 We describe the cases of two children whose large coronary fistulas were closed through a retrograde approach with an Amplatzer vascular plug (AGA Medical Corporation, Golden Valley, Minnesota, United States of America). The Amplatzer vascular plug is a self-expandable cylindrical device made from a nitinol wire mesh. The device is secured on both ends with platinum marker bands. The devices are made in various sizes ranging from 4 to 16 millimetres in 2 millimetres increments.
Case 1
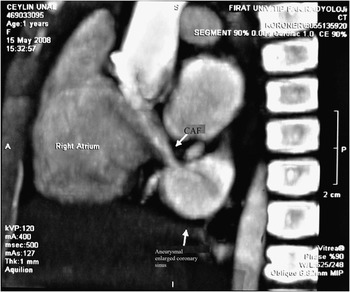
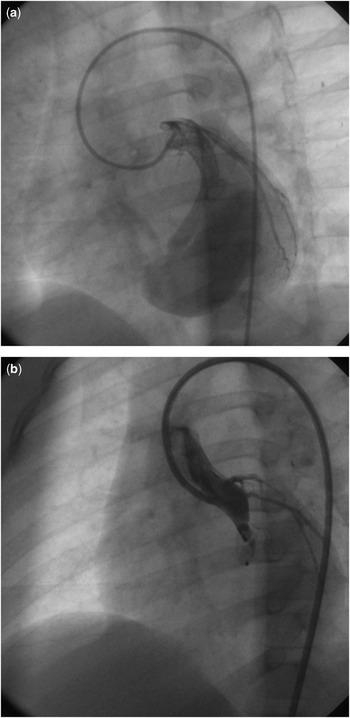
A 19-month-old asymptomatic girl was referred for cardiac systolic–diastolic murmurs audible over the left sternal border. General examination was unremarkable. Her electrocardiography showed a right-axis deviation and right bundle branch block. Chest X-ray only revealed mildly increased pulmonary vascularity. Transthoracic echocardiography suggested the presence of a large left coronary artery and a fistulised connection with the right atrium. Multi-slice computerised tomography clearly showed a dilated anomalous fistulous connection between the left coronary artery and abnormal large coronary sinus (Fig 1). Cardiac catheterisation and coronary angiography revealed a significant 1.5:1 left-to-right shunt and a large coronary fistula that arose from the ostium of the left coronary artery and drained into the coronary sinus near the right atrium opening (Fig 2a). The proximal fistula dimension was 6 millimetres, the middle part 4.5 millimetres, and distal the narrowest part 1.5 millimetres. The coronary sinus was aneurysmally enlarged; its dimension was 11 millimetres. Heparin (75 units per kilogram) was administered. At the risk of blocking the main coronary during embolisation, the guiding catheter was placed in the middle part of the fistula. The fistula was occluded by using the Amplatzer vascular plug through a guiding catheter with a retrograde approach. We chose a device that was nearly 50% bigger than the diameter of the middle segment of the fistula, and thus a 6-millimetre device was placed. Control coronary angiograms showed complete occlusion without residual flow (Fig 2b). Low-dose aspirin therapy was begun after the procedure because of proximal coronary artery dilatation. At the 21-month follow-up, the patient remained free from any cardiovascular symptoms.
Multi-slice tomography shows an enlarged left coronary artery fistula and aneurysmal dilatation of the coronary sinus.

(a) Selective coronary angiography shows a large coronary cameral fistula originating from the left coronary artery and draining into the aneurysmal enlarged coronary sinus. (b) Control angiography shows no residual flow through the fistula with occlusion with the Amplatzer vascular plug. The device is still attached to its delivery cable.

Case 2
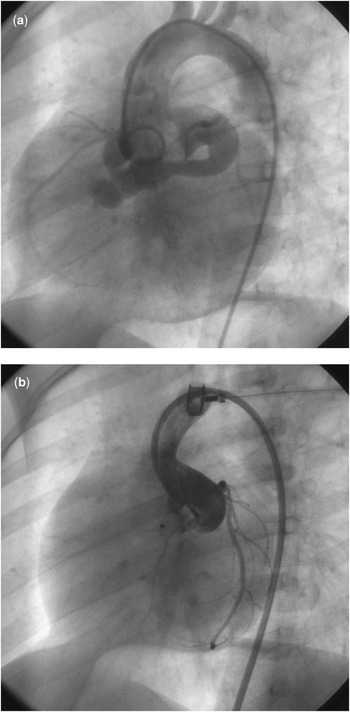
A 4-year-old asymptomatic girl was referred for cardiac systolic–diastolic murmurs over the left sternal border. General examination was unremarkable. Her electrocardiography was normal. Chest X-ray only revealed mildly increased pulmonary vascularity. Transthoracic echocardiography suggested the presence of a large left coronary artery and fistulas both of the right atrium and right ventricle, and a small secundum atrial septal defect. Cardiac catheterisation and coronary angiography revealed a significant 1.9:1 left-to-right shunt and a large coronary fistula that arose from the ostium of the left coronary artery and drained into the right atrium, and into the right ventricle (Fig 3a). The narrowest part of the fistula was the middle segment measuring 6.2 millimetres, with the dimension of the distal part increasing to 15.1 millimetres. Heparin (75 units per kilogram) was administered. The guiding catheter was placed in the middle part of the fistula. The fistula was occluded by using the Amplatzer vascular plug through a guiding catheter with a retrograde approach. We were placed at the 14-millimetre device; the proximal part of the device was placed at the distal enlarged part of the fistula. Control selective coronary angiograms showed complete occlusion without residual flow (Fig 3b). Low-dose aspirin therapy was begun after the procedure because of proximal coronary artery dilatation. At the 13-month follow-up, the patient remained free from any cardiovascular symptoms.
(a) Aortic root angiography shows a fistula between a left coronary artery with multiple connections, the right atrium, and the right ventricle. (b) Selective left coronary angiography is showing that the fistula is occluded after deployment with the Amplatzer vascular plug.

Discussion
The coronary artery fistula constitutes the most common haemodynamic significant congenital coronary abnormality in children.Reference Armsby, Keane, Sherwood, Forbess, Perry and Lock1, Reference Latson2 Most authors have recommended closure of these fistulas during childhood even in the absence of symptoms. Drainage into the coronary sinus is especially associated with coronary sinus rupture.Reference Ferhandes, Kadivar, Hallman, Reul, Ott and Cooley3 Transcatheter closure of these lesions is increasingly being utilised as an alternative to surgical closure. More recently, a vascular embolic device to close the fistula percutaneously has been used.Reference Armsby, Keane, Sherwood, Forbess, Perry and Lock1, Reference Latson2 The choice of the device and technique is determined by the cost, familiarity of the operator with the different approaches, and the anatomical characteristics of the fistula. There are a few reports addressing the use of the Amplatzer vascular plug for this purpose.Reference Balaguru, Joseph and Kimmelstiel4–Reference Wiegand, Sieverding, Kaulitz and Hofbeck7 The device is user-friendly, and comes pre-loaded and attached to the delivery cable. The Amplatzer vascular plug appears to track easily with good pushability using a coronary guide catheter. Transcatheter closure needs the embolic device to be placed in the most suitable location. To place it more proximally or distally can be dangerous due to thrombus formation and myocardial infarctions, or due to device migration to a cardiac chamber. The device has the ability to recapture or reposition, thus decreasing the risk of obstruction and migration.
Retrograde or antegrade arterial approaches are used to close coronary artery fistula. Our experience shows that closing a large coronary artery fistula through the retrograde arterial approach using an Amplatzer vascular plug is a simple and quick method. The antegrade arterial approach lengthens the procedure. In addition, it may be difficult to advance the delivery catheter to the ideal point for its placement, especially in patients with a tortuous fistula. In our cases, the fistula originated from the proximal part of the left coronary artery. Thus, it was possible to cannulate the fistula deeply without causing any major distortion or damage to the vessels.
These case reports show that to apply a retrograde approach when placing an Amplatzer vascular plug for transcatheter occlusion of a large coronary artery fistula is feasible and safe in children. Therefore, it has advantages compared to other devices for selected patients.