An icy wind blows through your cotton shirt while you sit outside the hospital door, waiting for your wife to bring up the car. The warm August day, when you entered the emergency room, has transformed into a gray November one. Your mind returns to Dr. Snipe.
Your company introduced a new health insurance program last spring and you were invited to select a physician from a list of doctors in your area. You did your homework and asked friends and several healthcare workers for the most competent primary care physician. The name that kept coming up was Dr. Snipe, and so you made an appointment.
It took a while to get in, but on your initial visit, he seemed pleasant enough. He spent a lot of time talking to you and, when he examined you, he made you feel confident that you had chosen a physician that you could count on in the worst of illness. Dr. Snipe would be able to guide you through your next 20 years. When you mentioned to him the tight feeling you get in your neck and arm sometimes, his ears seemed to perk up.
When you left the office you were told to return in the morning for a treadmill test. The next day, you met Dr. Able, who introduced herself as your cardiologist. After the treadmill she told you that it showed signs of poor blood flow in the heart and recommended that you undergo a cardiac catheterization in a few days, by her colleague, Dr. Burns. The next morning the tightness returned and you called the emergency number on your insurance card. The on-call physician, Dr. Chan, told you to go to the hospital immediately. There, you were met by Dr. Davis and his emergency room team. Dr. Evans, the admitting cardiology resident, let it be known that he would be responsible for writing all the orders that directed your medical care when you were transferred to the coronary care unit. Dr. Fudd, the hospital's intensivist, introduced himself and his team, Drs. Gavin, Hubbard, and Iota. After your heart was catheterized and Dr. Juster was unable to place numerous necessary stents, further catheterization was ruled out after consultation with the attending cardiologist, Dr. Kite. Therefore, you were referred to the Medical Center's leading cardiac surgeon, Dr. Luce. He seemed totally competent and reassuring. Surgery was scheduled for the following morning.
There are several weeks when names and events float like leaves in the wind. Doctors like Nevermore, Potter, and Travis seem to be in there somewhere, along with vague memories of respirators, IV tubes, and innumerable smiling, unrecognizable faces. The next thing you clearly remember is the surgical ward with Dr. Weber as the resident managing your wound. As you got stronger, Dr. Xavier assumed your care in order to manage the multiple medical complications that had developed during your ICU stay. For the past 4 weeks you have gotten to know Dr. Yoste quite well as she took care of you in the Skilled Nursing Facility. And now, as you are leaving, the nurse hands you a card listing your first posthospital visit with your new cardiologist, Dr. Zulka.
The car door opens and you stand to get in. The icy wind returns, along with the thought, “What ever happened to Dr. Snipe?”
Does it matter?
Many of my medical colleagues would ask if there are any data to show that your cardiac output and blood flow would be any different 1 year later, whether or not Dr. Snipe participated in your hospital care.
If it does matter, however; the model of having a physician who knows you in more facets that just the disease process that is active at the time may soon be eliminated in the process of healthcare commodification that marks our effort to gain economic control in medical care.
Medicine Acquires the Skills of Commerce
In the early 1980s, when hospital administrators were learning that their jobs now required them to control expenses, it became apparent that many of them had no reliable way to determine what any particular item or procedure actually cost. The prices on each activity depended more on a billing structure than the true labor and material that comprised the activity. The profit margins had previously been so high that there was no need to micro-account the revenues. Hospitals had been paid a global fee for each patient and what was received easily paid for the staff and supplies, plus a decent extra for maintenance and new equipment. This relaxed attitude to inventory and accounting practices was one of the first mind-sets to disappear when managed care got serious. Now hospitals, and ultimately all providers, are required to structure each service they provide in a measurable and defined manner that allows a specific cost to be assigned to the service. Nursing units have supply carts that look like an automat in Manhattan, stocked with medications, IV bottles, and compresses, all obtained by keying in the patient's ID. By packaging hospital services into definable price units, administrators turned to a standard commercial practice—commodification.
The word “commodification” is derived from the verb “commodify”—to turn into a commodity. The traditional sense of “commodity” is “anything movable that can be bought and sold.”1
Webster's New International Dictionary, 2nd ed. Commodity. Springfield, Mass.: G&C Merriam; 1947:539.
Random House Dictionary of the English Language, 2nd ed. Commodity. New York: Random House; 1987:412.
One essential ingredient of a commodity is its ability to be measured and quantified. The business mind of the mid-1980s introduced the idea that a medical service could be commodified, as long as it could be specifically defined, quantitatively measured, and numerically recorded. One way in which the commodified physician unit can be recognized is in the changing way in which physicians are paid. Traditionally, doctors have been paid in a method identified as fee-for-service. This is the term used to describe a patient paying for a doctor's office or hospital visit. Initially these fees were very flexible and reflected the doctor's rough approximation of the time and complexity involved in the case, as well as the patient's ability to pay. The first step toward commodification was to place a number on the visit and break it into four possible categories (problem-focused, detailed, comprehensive, and complex3
CPT 2007: Current Procedural Terminology, std. ed. Chicago: American Medical Association; 2006:10.
Physicians entering the profession in the 21st century do not expect to practice fee-for-service medicine. They are looking at salary options. When established practices try to recruit young colleagues the negotiation is about a fixed salary or even an hourly rate. Doctors by the hour and patients by the time slot; now we have a model that can be programmed to maximal financial efficiency. Their techniques just need to be subject to the precision of Cartesian analysis.
Evidence-Based Medicine: Quantifying the Outcome
If the essential feature of the commodified product is its ability to be counted and measured, the only personality the commodity has is quantification. It is important to compare the shift toward medical commodification with another developing trend in medicine—the effort to define the efficacy of all medical treatment in terms of the evidence that demonstrates their measurable outcomes. The effort is to subject every medical treatment and diagnostic measure to statistical scrutiny. Only those actions that can be objectively validated as effective for achieving a specific endpoint are considered medically appropriate. Those that do not stand up to rigorous analysis are rejected. This seems totally appropriate at first pass. But what about the myriad of procedures and tests performed for years but never studied with the techniques of evidence-based measurement? The proponents of the new medicine consider them all suspect.
A few years ago a resident turned to me on rounds and said, “Hasn't only about 20 to 30% of what we do been proven to work?” I did not have a ready answer, but I understood his point. There is a great deal of medicine handed down from teacher to student without the security of a p value. Medical care, as opposed to medical science, is the ability to extrapolate the scientific fact to the imperfectly understood human situation. Certainly, the scientist in me wants to continue to pursue the effectiveness of every test and therapy in order to eliminate those that are ineffective. However, to reject most of what we are doing as invalid based on lack of statistically demonstrable results, even if there is general consensus on the value of a particular treatment, would leave medicine with no approach to many patient ills.
The commercial world seems to have endorsed evidence-based medicine even more enthusiastically than the medical one. Patients now enter into a health insurance plan that is a contract for services. Inherent in that contract is a definition of “medical necessity.” This means that each health plan states what medical services are, and what are not, covered for any individual enrolled in that insurance plan. Insurance companies are free to deny, by contract, uncovered medical services. Insurers are happy to deny treatments that are proven to be ineffective, and they are well justified in doing so. But recently I have seen a new, more aggressive stance. Some programs are now touting their willingness to cover therapies that have passed the test of scientific scrutiny, but what goes unsaid is a willingness to deny anything that has not yet been recognized as valid using evidence-based analysis. The bar has been moved from denying those treatments that have been shown not to work to including the myriad of things we have done for years and not yet studied rigorously. Formerly, insurance denials were for treatments and tests that had been proven ineffective. Soon, insurers could be demanding proof of efficacy before paying for a treatment or test. The standard will shift to the financial benefit of the insurance company. Commercial interests can now use physicians' desire to measure the effects of treatment as their excuse to increase profits.
Precise outcome measurement, salaried doctors to provide specific treatments for numbered diagnoses, and patients contracted to receive the product: We are now beginning to define commodified healthcare. All that is missing is to make the parts interchangeable.
Fungibility
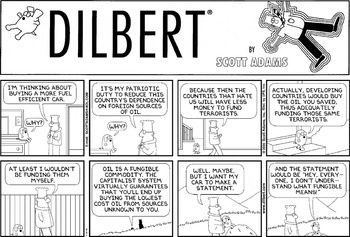
As a child in Tennessee, I used to listen to the farm report on the radio as I ate breakfast. One portion of the program always dealt with the commodities market—corn, soybeans, and hog bellies. I would listen to the announcer talk about the price of September cotton and marvel at the fact that the cotton had not even been planted yet. This lack of individual distinction for the commodified article of commerce, to the point of nonexistence in terms of cotton, is the second essential element of the term “commodity.” A commodity is an article that can be defined and measured in such a way that any particular article of the same type is interchangeable with another. The current buzzword is fungibility (see Figure 1).

Dilbert, 19 February 2006. (Reproduced with permission.)
The Merriam-Webster Online Dictionary defines “fungible” as “being of such a nature that one part or quantity may be replaced by another equal part or quantity in the satisfaction of an obligation.”4
Merriam-Webster Online Dictionary. Fungible. http://www.merriam-webster.com (2 Jan 2007).
Another childhood memory is Sunday morning after church, eating with my family in the first branch of a new motel called Holiday Inn. I recall my father telling us that this was just the first motel of its kind, but the idea was to build many more of them around the South so that a traveler would know what type of room and furnishings to expect, whether they were staying at a Holiday Inn in Greenville, Mississippi, or Mobile, Alabama. The consistency of the product was valued as highly as the particular quality of any individual hotel. Holiday Inn commodified hotel service. Commercial forces are capable of doing the same in medicine. The doctor–patient visit as a fungible commodity? Why not?
A Fungus among Us
A good example of the fungibility of the modern physician can be found in my own hospital's experience. About 20 years ago, many of the doctors in one of the major community hospitals in San Francisco came together to form a large physician-owned and -managed corporation to begin contracting with major insurance companies to provide care to large groups of patients. The patients received their health insurance coverage through their work, and the rapidly rising cost of healthcare in the 1990s was forcing many employers to look to new methods of healthcare delivery to keep costs manageable. The delivery model of the time was the Health Maintenance Organization (HMO). The hallmark of this delivery system is that the physician group is paid a fixed sum of money to care for a defined group of patients. This is called capitation, or payment per head. The amount of reimbursement does not change, regardless of the number of medical services needed by the patient group. In theory, this system encourages the rational use of medical treatments and discourages waste and inefficiency. The physician group at my institution decided to transfer this incentive down to each of its member physicians by paying each primary care physician a set amount based on the number of patients assigned to each individual physician (individual capitation). The amount per patient, called a “cap rate,” was distributed monthly and the physician was expected to provide his or her patients with the medical care they needed while covering overhead and other expenses from this fixed payment. At the time, most physicians in San Francisco saw their patients in the office and, when the patient became sicker, they followed them in the hospital as well. This dual role of outpatient and inpatient care provided continuity of care, but was perceived as inefficient by the managers of the medical group. As a result, the medical group, in 1994, decided to hire young physicians, specialists in internal medicine, just like the members of the medical group. These doctors would work exclusively in the hospital, providing only inpatient care. Subsequently, this form of medical provider was called a “hospitalist”5
Wachter RM, Flanders S. The hospitalist movement and the future of academic general internal medicine. Journal of General Internal Medicine 1998;13:783–5.
Recognizing their physician members' resistance, the medical group had an idea. Old habits would be hard to change unless there was a change in the incentives as well. And so they told their members something like this: “We recognize that all of you are excellent physicians and that good patient care is what motivates many of you to follow your own patients when they are hospitalized. We would never want to interfere with the continuity of the doctor/patient relationship if you, the doctor, feel it is so important. Nevertheless, we have hired some new physicians who will be working full time in the hospital to care for patients who some of you may wish to turn over for hospital care. Those of you continuing to see their own hospital patients can do so. However, there is one more thing. The ‘cap rate’ for doctors covering their own patients will be the same as the rate for doctors delegating their patients to the hospitalists.”
In other words, doctors who continued to see their own hospital patients would now be doing so on their own time and for no additional reimbursement. Overnight, the vast majority of doctors in the group, who had previously provided medical care to their hospitalized patients, stopped doing so and turned them over to the hospitalist service. These same doctors now talk about how much better their lives have become since they no longer have to go over to the hospital and deal with the sickest patients and their families. It is now uncommon to find any patient in my hospital who is being cared for by a doctor who knew them before they arrived in the emergency room. The new “arrangement” is not clearly described to patient's choosing a doctor from the health plan booklet who will care for them “in sickness and in health.” We find fungibility in action. Now we know what happened to Dr. Snipe.
Depersonalization
The depersonalization of the patient in the process of medical care is something that has been discussed at length in the literature, beginning with Paul Ramsey's groundbreaking work, The Patient As Person.6
Ramsey P. The Patient as Person: Explorations in Medical Ethics. New Haven, Conn.: Yale University Press; 1970.
The impersonal doctor or health plan can be compared to the machine: cold, calculating, and efficient. Our country has a long tradition of resisting such developments. Why else do we always pull for John Henry over the pile driver, Paul Bunyan over the chain saw, or Garry Kasparov over Big Blue? It is not simply that we are pulling for the underdog, it just seems more important to root for the human in the face of an impersonal technology. If we are to demonstrate the root problem with commodified healthcare, however, more than sentiment will be required.
To Market, to Market …
Last November, I went to the market to buy a turkey for my family's Thanksgiving dinner. I imagined the noble bird of our forefathers' time, standing proud, tail fanned, head held high, red waddle flapping defiantly. What I found on the shelf bore no resemblance to the creature I was seeking. Wrapped in plastic, on a yellow Styrofoam board was a very large, pale, glob of flesh. The neatly printed label advertised two large breasts, six wings and four legs, complete with drumsticks that would make a hog proud. I had found the commodified turkey. The turkey no longer contained the gizzard and giblets I had loved as a youth, and certainly there was no heart. The turkey had become something else in its journey from the farmyard in Kansas to the meat counter at Albertson's. Some essential features had been left behind on the slaughterhouse floor. The key to the dangers of commodified medicine was realized. It is not what the product is; it is what has been removed.
Commodification depends on the Cartesian assumption that the whole can be broken down completely into the sum of its individual parts, which can themselves be precisely defined. Confining the doctor–patient relationship to measurable, definable, and recordable variables limits it to the world of the definition and eliminates the possibility of healing occurring in ways that are not measured. Have we left something behind in the processing plant?
No Role for Beneficence
The defining characteristic of the normative good in a commodified activity (service or product) is what is actually measured. For medicine, that fits with the current fascination with evidence-based medicine and outcome analysis. Results that can be measured are all that count: utilitarianism in action. The purposes, goals, or character of the actor are insignificant. There is no need to consider intentionality, virtue, principle, or misfortune. Miscalculation is the only sin.
By stripping the intentionality of an action away and concentrating only on the observable qualities of that action, commodification negates one of the positive attributes of medicine, the affirmation of a duty to put a patient's benefit above self-interest, the duty to beneficence that has previously been considered an ethical pillar of medicine. Beneficence is an attitude that is much more difficult to measure than the actions that it motivates. The ability to eliminate it from the interaction between doctor and patient helps to deliver the commodified product.
Commodification is an economic concept and is designed for economic means. Its principles and values are derived from the values of the marketplace. The marketplace takes no count of good or benevolent intention. Results count. Everyone is to look after him- or herself in the end, preserving his or her own interests ahead of others. Dr. Jonsen aptly quotes Adam Smith's terse comment on benevolence: “Nobody but a beggar chuses to depend chiefly upon the benevolence of his fellow-citizens.”7
Jonsen AR. Guest Editorial: A note on the notion of commercialism. Cambridge Quarterly of Healthcare Ethics 2007;16:368–73.
“Trust Me; I'm a Doctor”
And so we come to what is missing in the turkey of commercialized healthcare: trust. Trust is a human quality that is essential for a good relationship. It requires knowledge of the individual with whom one is interacting. It includes an awareness of the measurable actions that have come before, but also encompasses a belief in the nature of what will happen in the future. It is more than a scientific prediction of future outcomes based on past occurrences. It includes a belief in the intentions of the trusted party. It does not develop instantly, but can be shattered suddenly.
As in my institution, it is not uncommon for patients in the modern American hospital to have no one caring for them whom they have met before they arrived in the emergency room. There is no relationship that has not been forged in the immediate crisis of illness. The most common reason for ethics consultation for our ethics committee is when patients, or their surrogates, demand treatments that will provide no measurable benefit. Requests for futile care have many etiologies, but one of the most common is that family members do not trust us when we say that there is no more that can be done. The measurable outcomes of the persistent vegetative state mean nothing to many people when their loved one is lying in the ICU. A trust in God, the tale of a friend, or even a TV talk show host is stronger than believing a new doctor or nurse. It is easier to wait until another doctor rotates on the service to see if there is a better prognosis.
Conclusion
The essential components of a commodity are quantifiability and fungibility. In an effort to control the rising costs of medical care, economic concepts such as commodification have been introduced. Earlier definitions of a commodity as a “physical article of commerce” have been modified to include services such as medical care. Continued emphasis on cost containment will hasten the transformation.
Diseases and physician–patient encounters have been reduced to numbers. Doctors and patients are being viewed as interchangeable units of service. The validity of the entire medical process is becoming dependent exclusively on measurable data. Evidenced-based medicine is one manifestation of this way of thinking. Changing physician reimbursement from a fee-for-service model to a salary model is another example. The hospitalist movement represents a third form of commodification.
None of these newer methods of healthcare delivery are bad in themselves. Grouping symptom categories (diseases) into recognizable formats will improve our ability to contrast and compare various therapies. Evidence-based medicine has the potential to greatly improve the efficacy of the medical treatment. For many uncomplicated and straightforward illnesses, convenience of provider may be as important to a busy patient as long-term continuity.
The problem with commodified healthcare is not with the elements that it contains, but those that are not in evidence. By removing an emphasis on beneficence as a crucial component of the medical encounter, there is no longer a basis for trust, which can be considered essential for the healing process in its most basic sense. Commodification preserves the objective elements of medicine, but, like my Thanksgiving turkey, it removes the heart.