Introduction
Administration of interferon-α (IFN-α) for the treatment of hepatitis C is associated with a significant incidence of depressive symptomatology, with up to 40% of patients developing major depression over 3 months of IFN-α therapy (Hauser et al. Reference Hauser, Khosla, Aurora, Laurin, Kling, Hill, Gulati, Thornton, Schultz, Valentine, Meyers and Howell2002; Raison et al. Reference Raison, Borisov, Broadwell, Capuron, Woolwine, Jacobson, Nemeroff and Miller2005; Leutscher et al. Reference Leutscher, Lagging, Buhl, Pedersen, Norkrans, Langeland, Morch, Farkkila, Hjerrild, Hellstrand and Bech2010). This observation has been taken as evidence of the possible role of inflammatory mechanisms in the pathophysiology of major depression more generally (Raison et al. Reference Raison, Capuron and Miller2006), and is consistent with reports of elevated plasma levels of pro-inflammatory mediators such as tumour necrosis factor (TNF) and interleukin-6 (IL-6) in depressed patients (Dowlati et al. Reference Dowlati, Herrmann, Swardfager, Liu, Sham, Reim and Lanctot2010).
The mechanism by which IFN-α might produce depression has been explored in several previous studies. One potential mechanism involves induction of indoleamine 2,3-dioxygenase (IDO) with consequent alterations in the metabolism of the serotonin precursor tryptophan. Central tryptophan depletion was originally suggested as a cause of IFN-α-induced depression (Bonaccorso et al. Reference Bonaccorso, Meltzer and Maes2000; Capuron et al. Reference Capuron, Ravaud, Neveu, Miller, Maes and Dantzer2002), but more recent formulations have implicated increased production of tryptophan metabolites, such as quinolinic and kynurenic acids, which have the potential to alter central glutamatergic neurotransmission (Wichers & Maes, Reference Wichers and Maes2004; Miller et al. Reference Miller, Maletic and Raison2009; Raison et al. Reference Raison, Dantzer, Kelley, Lawson, Woolwine, Vogt, Spivey, Saito and Miller2010). It has also been suggested that the response to inflammatory mediators such as IFN-α might include impairment of the ability of astrocytes to take up synaptic glutamate, thus predisposing to glutamate toxicity (Tavares et al. Reference Tavares, Tasca, Santos, Alves, Porciuncula, Emanuelli and Souza2002; McNally et al. Reference McNally, Bhagwagar and Hannestad2008). This is of interest in view of the postulated role of glutamate abnormalities (Sanacora et al. Reference Sanacora, Zarate, Krystal and Manji2008) and glial cell deficits (Rajkowska & Miguel-Hidalgo, Reference Rajkowska and Miguel-Hidalgo2007) in major depression.
Magnetic resonance spectroscopy (MRS) provides a safe and non-invasive method for the measurement of cortical glutamate. A growing number of studies have demonstrated MRS abnormalities in glutamine and glutamate in brain regions such as the anterior cingulate cortex in mood disorders (Yüksel & Öngür, Reference Yüksel and Öngür2010). Typically, reliable differentiation of glutamate from glutamine with MRS is highly challenging so the combined total glutamate with glutamine, often termed Glx, is reported. Recent technical advances allow for more confident estimation of glutamate and glutamine individually (Mekle et al. Reference Mekle, Mlynárik, Gambarota, Hergt, Krueger and Gruetter2009). This is an important development because, although Glx reflects a total glutamatergic pool, the ratio of glutamine to glutamate is thought to more closely reflect glutamatergic function (Théberge et al. Reference Théberge, Bartha, Drost, Menon, Malla, Takhar, Neufeld, Rogers, Pavlosky, Schaefer, Densmore, Al-Semaan and Williamson2002; Yüksel & Öngür, Reference Yüksel and Öngür2010).
The aim of the present study was to use proton MRS to assess the effect of IFN-α on cerebral glutamate and glutamine levels in patients receiving IFN-α treatment for the management of hepatitis C. We also investigated whether changes in these brain neurochemicals correlated with emergent depressive symptomatology.
Method
Participants
We recruited 17 participants, aged between 18 and 65 years, who had chronic hepatitis C viral infection without evidence of cirrhosis, and were scheduled to receive treatment with pegylated IFN-α and ribavirin (IFN) as part of their routine clinical care. Participants were recruited from National Health Service (NHS) hepatology clinics at two centres (Oxford and Bristol, UK). They were scanned at baseline, prior to starting treatment, and again after 4–6 weeks of treatment with IFN. Those with current DSM-IV Axis I disorders by the SCID (First et al. Reference First, Spitzer, Gibbon and Williams2002), taking a non-stable dose of psychotropic medication or with any contraindication to MR scanning were excluded. Clinical or biochemical evidence of cirrhosis was an exclusion criterion and all participants had had a liver biopsy or fibroscan. Past psychiatric history such as a history of opiate dependence was not an exclusion criterion. Concomitant medication was continued at the same dose throughout the study. The majority of participants (16 out of 17) were taking no psychotropic medication; the remaining participant was taking a low-dose antidepressant but does not contribute to the glutamine analyses presented here. We included patients who were taking vitamin supplements, erythromycin, thyroxine, the oral contraceptive pill and regular inhalers. The study was approved by the Oxfordshire Research Ethics Committee A and all participants gave written informed consent. Participants were reimbursed for their time and any other expenses.
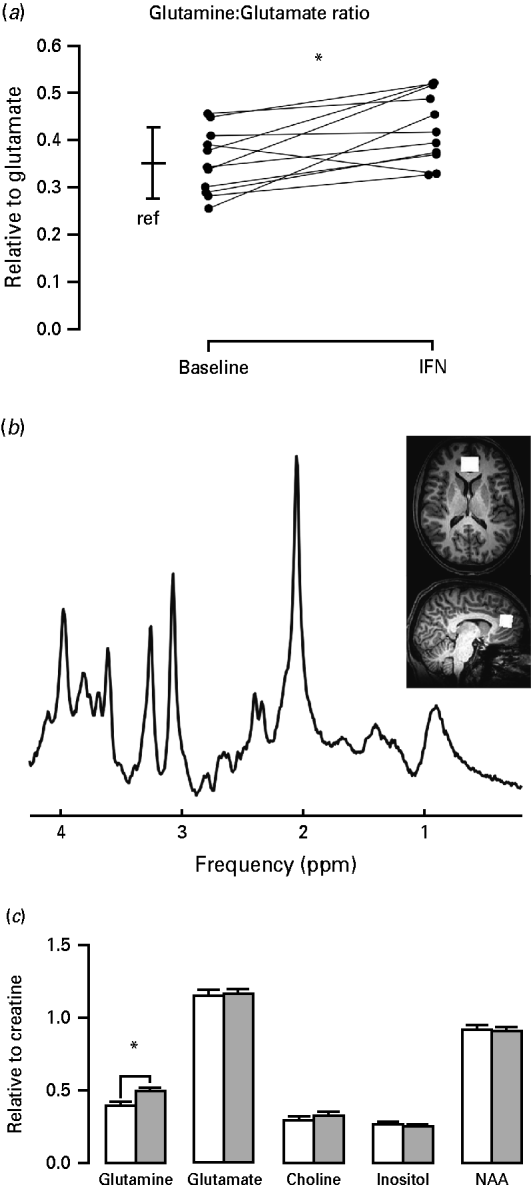
Imaging was performed on a 3-T Siemens TIM Trio scanner (Siemens, Germany) with a body coil transmitter and a 12-channel head receiver array. MRS measurements were obtained from a 25 × 20 × 20 mm voxel of the medial prefrontal cortex including the pregenual anterior cingulate cortex (Fig. 1 b) using spin-echo full-intensity acquired localized (SPECIAL) spectroscopy (Mekle et al. Reference Mekle, Mlynárik, Gambarota, Hergt, Krueger and Gruetter2009) with repetition time (TR) = 3000 ms and echo time (TE) = 8.5 ms. Water-suppressed (192 averages) and water-unsuppressed data (eight averages) were obtained. The voxel was positioned manually by reference to an axial T1-weighted gradient-echo image. Prior to spectral analysis, motion-corrupted averages were discarded, and the effects of scanner drift were removed by performing a frequency and phase alignment of the averages. Spectra were analysed with LCModel version 6.2 (Provencher, Reference Provencher1993) using a set of simulated metabolite basis spectra. Eddy current correction was used. Metabolite estimates with Cramér–Rao lower bounds (CRLBs) > 20% were excluded. One baseline glutamine estimate was excluded for this reason. Concentrations were expressed relative to creatine (Cr), and the ratio of glutamate to glutamine was calculated. In a secondary analysis, concentrations relative to tissue water were calculated. T1-weighted structural images of whole brain were acquired with 1 mm3 voxel resolution. FSL FAST was used to segment the structural brain images into grey matter, white matter and cerebrospinal fluid (CSF) to allow estimation of voxel composition.
(a) Glutamine:glutamate ratio at baseline and during treatment with interferon-α (IFN-α). Bar: reference values (mean and standard deviation) for healthy controls with this method. (b) Sample spin-echo full-intensity acquired localized (SPECIAL) spectrum and voxel position in the anterior cingulate cortex. (c) Magnetic resonance spectroscopy (MRS) measures at baseline (white) and during interferon treatment (grey). NAA, N-acetylaspartate. * p < 0.05.

Ratings
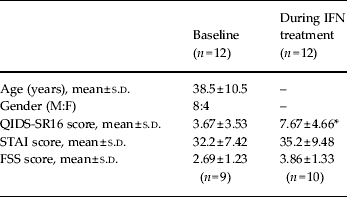
Self-report measures of mental state were obtained at baseline and at the time of second scan using the 16-item self-report Quick Inventory of Depressive Symptomatology (QIDS-SR16; Rush et al. Reference Rush, Trivedi, Ibrahim, Carmody, Arnow, Klein, Markowitz, Ninan, Kornstein, Manber, Thase, Kocsis and Keller2003), the State–Trait Anxiety Inventory (STAI; Spielberger et al. Reference Spielberger, Gorsuch and Lushene1970) and the Fatigue Severity Scale (FSS; Krupp et al. Reference Krupp, LaRocca, Muir-Nash and Steinberg1989). FSS ratings were not available for three participants (Table 1).
Participant characteristics

IFN, Interferon; M, male; F, female; QIDS-SR16, 16-item Quick Inventory of Depressive Symptomatology – Self-Report; STAI, State–Trait Anxiety Inventory; FSS, Fatigue Severity Scale; s.d., standard deviation.
* p < 0.05 difference between baseline and treatment.
Statistics
Group comparisons were performed using the general linear model in PASW Statistics version 18 (SPSS Inc., USA). MRS measures were tested for correlation with age and voxel composition. No significant effects were seen so these were not included as covariates in the model. Correlations were tested using Pearson's r. All statistical tests were two-tailed with 0.05 significance level.
Results
Imaging data were obtained at baseline and during IFN treatment from 12 patients with chronic hepatitis C. Of the 17 patients recruited, one did not tolerate baseline scanning, two withdrew before completing the protocol, and for two the MRS acquisition failed for technical reasons. Six of the 12 patients demonstrated a rapid virological response (RVR) with undetectable serum viral load at week 4 of treatment. Treatment was associated with a statistically significant increase in depression symptoms (p = 0.01, Table 1) but not in anxiety or fatigue ratings (p > 0.15 both cases).
IFN treatment was associated with a significant increase in anterior cingulate cortex glutamine levels (glutamine/Cr baseline 0.40 ± 0.10, IFN 0.50 ± 0.12, p = 0.02; Fig. 1 c). No effect on glutamate was observed (p > 0.7, Fig. 1 c). A significant increase in glutamine:glutamate ratio was also seen (baseline 0.35 ± 0.07, IFN 0.43 ± 0.08, p < 0.01, Fig. 1 a). Estimates of concentrations for both metabolites were obtained with low estimated errors (CRLB glutamate 4.8 ± 0.7%, glutamine 11.3 ± 3.0%). The majority (eight) of these participants were taking no concomitant medication; the others were taking vitamin supplements, erythromycin, oral contraceptive and an antihistamine respectively.
No significant effect of IFN was observed on other MRS measures relative to Cr [choline, N-acetylaspartate (NAA), inositol, p > 0.2 all cases]. No significant correlation was observed between change in viral load and any MRS measure. A secondary analysis of concentrations relative to tissue water showed the same pattern of effect, with a significant effect of IFN on glutamine (p = 0.03) but not on other measures (p > 0.3 in all cases).
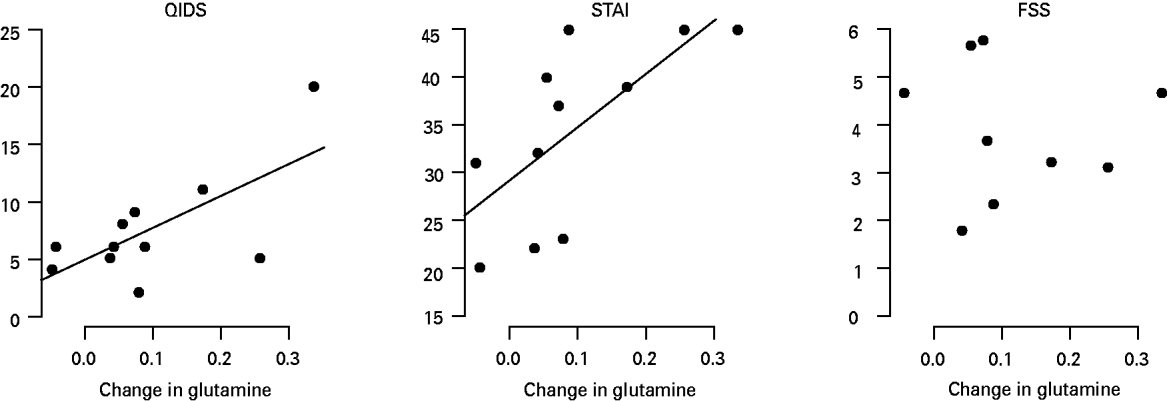
The observed change in cortical glutamine concentration correlated with symptom ratings at the time of the second scan (Fig. 2) for depression (QIDS: r = 0.68, p = 0.02) and anxiety (STAI: r = 0.69, p = 0.02) but not fatigue (FSS: p > 0.8). Anxiety scores also correlated with change in the glutamine:glutamate ratio (r = 0.68, p = 0.02).
Change in glutamine with mental state during treatment. QIDS, Quick Inventory of Depressive Symptomatology; STAI, State–Trait Anxiety Inventory; FSS, Fatigue Severity Scale. Significant correlations with QIDS (r = 0.68, p = 0.02) and STAI (r = 0.69, p = 0.02).

Discussion
Our findings suggest that treatment with IFN-α over 4–6 weeks leads to an increase in glutamine levels in the anterior cingulate cortex. However, levels of glutamate were unchanged. Of note, this increase in glutamine showed some correlation with measures of depression and anxiety. To our knowledge, this effect on cortical glutamine has not been described previously.
The cycling of glutamine and glutamate is a key process in the control of glutamate neurotransmission. Glutamate released from synaptic terminals is taken up into astrocytes, where it is converted to glutamine by the enzyme glutamine synthetase. Glutamine is subsequently released by astrocytes and accumulates in glutamatergic neurones, where it is converted back to glutamate by glutaminase. Our data suggest that IFN-α treatment is associated with an increase in glutamine relative to glutamate. This might be consistent with increased turnover of glutamate because, with elevated glutamate levels, we would expect more glutamate to be made available for astrocytes for conversion to glutamine (Yüksel & Öngür, Reference Yüksel and Öngür2010). Because glutamate itself can be neurotoxic, there are several mechanisms that prevent glutamate levels becoming excessive, particularly uptake into astrocytes (Danbolt, Reference Danbolt2001). Functional interpretation of changes in spectroscopic measures is not always straightforward; however, there is growing evidence that increased glutamine relative to glutamate is consistent with glutamatergic overactivity (Ongür et al. Reference Ongür, Jensen, Prescot, Stork, Lundy, Cohen and Renshaw2008) and thus altered resting-state activity (Alcaro et al. Reference Alcaro, Panksepp, Witczak, Hayes and Northoff2010). Given the well-established role of the medial prefrontal cortex, including the anterior cingulate cortex, in emotional processing and mood disorders (Kupfer et al. Reference Kupfer, Frank and Phillips2012; Strakowski et al. Reference Strakowski, Adler, Almeida, Altshuler, Blumberg, Chang, DelBello, Frangou, McIntosh, Phillips, Sussman and Townsend2012), such changes are well placed to influence the risk of developing depression.
As noted earlier, accurately differentiating glutamine from glutamate with MRS is often challenging. Methods such as those used here with very short echo times assist in precise glutamate quantitation (Wijtenburg & Knight-Scott, Reference Wijtenburg and Knight-Scott2011). In this study, as in previous reports with this particular technique (Mekle et al. Reference Mekle, Mlynárik, Gambarota, Hergt, Krueger and Gruetter2009), both glutamine and glutamate were measured with low errors, lending confidence to the finding that glutamine increases relative to glutamate during IFN-α treatment.
There are several processes by which IFN-α might increase glutamate release. IFN-α has been shown to elevate CSF levels of quinolinic acid, which can increase glutamate release from synaptosomes (Raison et al. Reference Raison, Dantzer, Kelley, Lawson, Woolwine, Vogt, Spivey, Saito and Miller2010). Inflammatory mediators can also lead to decreased uptake of glutamate into astrocytes, which could result in increased synaptic glutamate levels (McNally et al. Reference McNally, Bhagwagar and Hannestad2008). However, diminished glutamate uptake into astrocytes would not be expected to lead to increased glutamine as observed here because of reduced access of glutamate to the astrocytic enzyme glutamine synthetase.
It is possible to elevate central glutamine concentrations in people with hepatic cirrhosis by inducing hyperammonaemia (Mardini et al. Reference Mardini, Smith, Record and Blamire2011). This effect is associated with compensatory reductions in myo-inositol concentrations (Mardini et al. Reference Mardini, Smith, Record and Blamire2011). A similar pattern can be observed when cirrhosis is accompanied by hepatic encephalopathy (Häussinger et al. Reference Häussinger, Laubenberger, vom Dahl, Ernst, Bayer, Langer, Gerok and Hennig1994; Weissenborn et al. Reference Wijtenburg and Knight-Scott2007). In this study we excluded patients with evidence of cirrhosis a priori to avoid this potential confound. The absence of any decrease in myo-inositol levels makes it less likely that the effect on glutamine seen here can be explained by alterations in circulating ammonia, but it could be of interest in future studies to measure this directly. Whereas participants in this study were recruited from a general clinic population, replication in other samples would increase confidence further that the effect seen is generalizable.
In a previous IFN study, increased CSF levels of quinolinic acid were reported to correlate with scores on the Montgomery–Åsberg Depression Rating Scale (MADRS) during IFN-α treatment (Raison et al. Reference Raison, Dantzer, Kelley, Lawson, Woolwine, Vogt, Spivey, Saito and Miller2010). We also saw a correlation between increases in cortical glutamine and the depression and anxiety ratings. It clearly would be of interest to measure both glutamine and quinolinic acid in patients receiving IFN-α to see whether the concentrations of these two neurochemicals correlate with each other and with depression scores.
It is known that chronic hepatitis C viral infection can affect mental state in the absence of IFN-α treatment, and indeed that it can be associated with MRS abnormalities, such as elevated levels of choline (Forton et al. Reference Forton, Allsop, Main, Foster, Thomas and Taylor-Robinson2001). A recent study found that elevated basal ganglia choline and inositol reduced in people with sustained response to antiviral treatment (Byrnes et al. Reference Byrnes, Miller, Lowry, Hill, Weinstein, Alsop, Lenkinski and Afdhal2012). The current study lacks the statistical power to investigate such subgroup effects robustly. Previous studies have not used MRS techniques optimized to specifically identify alterations in glutamine levels such as those described here. The pretreatment glutamine:glutamate ratios found here are similar to those in healthy volunteers at our centre with this combination of MRS acquisition and analysis (Fig. 1 a), suggesting that IFN-α treatment is causing a change rather than normalizing a baseline abnormality, but clearly further investigation of baseline effects of viral infection on such measures would be of interest. Potential participants with current Axis I disorders were excluded from taking part in this study. If participants with existing depression at baseline had been included, this might have affected the magnitude of the neurochemical effects seen and could be investigated in future studies.
There have been several studies using MRS to examine cortical glutamate levels in patients experiencing major depressive episodes. In general, in patients with current unipolar depression, MRS levels of total glutamate and glutamine are reported to be lower than controls whereas elevated levels are associated with bipolar depression (Yüksel & Öngür, Reference Yüksel and Öngür2010). Unipolar depression also tends to be associated with a reduction of the ratio of glutamine to glutamate (Yüksel & Öngür, Reference Yüksel and Öngür2010). If this is the case, the neurochemical changes produced by IFN-α as measured by MRS may be distinct from those seen in unipolar depression. This raises the possibility that depression associated with inflammation may have a profile of glutamatergic changes similar to that seen in bipolar depression.
A similarity in the emergent neurochemical profile in this model and that seen in bipolar depression may be of particular interest given recent reports of emergent manic or mixed affective episodes during IFN treatment (Constant et al. Reference Constant, Castera, Dantzer, Couzigou, de Ledinghen, Demotes-Mainard and Henry2005) and the association of the presence of trait markers of vulnerability to bipolar disorder with higher rates of psychiatric complications of IFN treatment (Lim et al. Reference Lim, Olson, Zaman, Phelps and Ingram2010). The changes seen in glutamate activity in major depression and bipolar disorder seem relatively independent of concomitant psychotropic medication. In the present study the effect observed cannot be secondary to psychotropic medication, which would have the greatest potential to influence MRS results; however, some participants were taking medication for physical reasons. We tried to deal with this by only recruiting patients whose drug treatment was stable. We suspect that it might be impracticable to recruit a group of hepatitis C patients receiving IFN who are otherwise medication free.
Here we have observed that treatment with IFN-α over 4–6 weeks leads to an increase in glutamine levels in the anterior cingulate cortex. This effect correlates with depressive symptoms but the neurochemical effect seen differs from that observed in unipolar depression. This may have implications for the management and prevention of IFN-induced depression. Our study requires replication in a larger group of IFN-treated participants, where it would also be desirable to have a direct comparison group of patients with major depression.
Acknowledgements
We thank the nurses D. O'Donnell, J. Phillips and E. Sims and the patients for their participation in this study. This study was supported by the Medical Research Council, the Academy of Medical Sciences and Wellcome Trust, and the John Fell Oxford University Press (OUP) Research Fund. Dr Taylor was a National Institute for Health Research (NIHR) Clinical Lecturer through the Oxford University Clinical Academic Graduate School. Additional support was received from the Oxford NIHR Biomedical Research Centre.
Declaration of Interest
Professor Cowen has been a member of advisory boards of Eli Lilly, Servier and Lundbeck and has been a paid lecturer for Eli Lilly, Servier, Lundbeck and GlaxoSmithKline. Dr Taylor has been a paid lecturer for Bristol-Myers Squibb and his spouse is an employee of GlaxoSmithKline.