Introduction
Cystic echinococcosis (CE) is a chronic infection caused by the tapeworm Echinococcus granulosus. In humans, the larval stage of the parasite can develop and form cysts in almost any organ, but particularly in the liver and lungs (Brunetti et al., Reference Brunetti, Kern and Vuitton2010). Echinococcus granulosus in humans triggers a humoral and cellular response characterized by elevated serum antibodies and by concurrent intervention of T-helper cell 1 (Th1) and T-helper cell 2 (Th2) cytokines (Rigano et al., Reference Rigano, Profumo, Di Felice, Ortona, Teggi and Siracusano1995a). The variability and severity of the clinical expression of the disease probably also reflect the variety of human immunological responses to the parasite. Therapy of CE is primarily surgical, even though pharmacological treatment with benzimidazole carbamates is nowadays an effective alternative (Horton, Reference Horton1989; Todorov et al., Reference Todorov, Vutova, Mechkov, Petkov, Nedelkov and Tonchev1990; Teggi et al., Reference Teggi, Lastilla and De Rosa1993; Wen et al., Reference Wen, New and Craig1993; WHO-IWGE, 1996). Clinical evaluation of the outcome of disease is difficult and relies on combined imaging methods and serological techniques. Because specific antibodies persist in patients' sera for several years after recovery, a long-term clinical and serological follow-up is required to evaluate the success or failure of therapy. New and interesting research in the immunosurveillance of CE includes the study of cytokines, possibly associated with the outcome of the disease. Most studies on CE cytokines are mainly based on in vitro experiments, i.e. determination of cytokine production following stimulation of peripheral blood mononuclear cells or T-helper cells of patients with crude and B hydatid antigen (Fauser & Kern, Reference Fauser and Kern1997; Hernandez-Pomi et al., Reference Hernandez-Pomi, Borras-Salvador and Mir-Gisbert1997; Rigano et al., Reference Rigano, Profumo, Eruschi, Carulli, Azzara, Ioppolo, Buttari, Ortona, Margutti, Teggi and Siracusano2001). These studies demonstrated an increase in the production of some cytokines, such as interferon-gamma (IFN-γ), interleukin (IL)-4 and IL-5. Others demonstrated simultaneous involvement of Th1 and Th2 cells in CE patients (Haralabidis et al., Reference Haralabidis, Karagouni, Frydas and Dotsika1995; Rogan & Craig, Reference Rogan and Craig1997; Ortona et al., Reference Ortona, Rıgano, Buttarı, Delunardo, Ioppolo, Marguttı, Profumo, Teggı, Vaccarı and Sıracusano2003). Although two studies have reported the presence of cytokines in sera from surgically treated CE patients, neither of them evaluated the association between cytokines and the clinical outcome of the disease (Torcal et al., Reference Torcal, Navarro-Zorraquino, Lozano, Larrad, Salinas, Ferrer, Roman and Pastor1996; Touil-Boukoffa et al., Reference Touil-Boukoffa, Sanceau, Tayebi and Wietzerbin1997). In particular, Torcal et al. (Reference Torcal, Navarro-Zorraquino, Lozano, Larrad, Salinas, Ferrer, Roman and Pastor1996) reported a close relationship of IL-1, IL-2 and IL-4 with the number, characteristics and location of cysts within the liver; Touil-Boukoffa et al., (Reference Touil-Boukoffa, Sanceau, Tayebi and Wietzerbin1997) postulated that after surgical removal of hydatid cysts, measurement of serum cytokine levels might allow early detection of relapse. Continuing our research programme into the identification of immunological markers indicating the effectiveness of pharmacological and surgical treatment, in the present study we have monitored serum IL-4, IL-10 and IFN-γ concentrations in 50 pharmacologically and surgically treated CE patients, to evaluate in vivo the association of cytokine production with the outcome of disease.
Materials and methods
Collection of blood samples
Blood samples were obtained from 50 patients (16 males and 34 females; mean age ± SD was 31.1 ± 11.2 years, range 9–69 years) with clinically/radiologically diagnosed hydatidosis, and ten sex- and age-matched healthy controls. Healthy adults had no past history of dog contact, travelling to highly endemic areas or treatment for previous parasitic infections. Samples from all subjects were centrifuged at 2000 × g for 10 min at 4°C to obtain the serum. Lipaemic or haemolysed sera were discarded. Sera were divided into three tubes for each subject and stored immediately at − 70°C until cytokine analysis.
Diagnosis, treatment and surgical procedures
A detailed clinical history of all hydatid patients was recorded, e.g. clinical complications, demographic details, results of radiological investigations, anatomical location of cysts, anthelmintic treatment and histopathology of surgically resected specimens, on pre-tested proforma. No patient received any antiparasitic treatment before his/her inclusion in the study or showed serious concomitant disease. CE definitive diagnosis was assessed on the basis of imaging techniques (ultrasonography (USG) and computed tomography (CT) scan) and confirmed by histopathological examination on biopsy samples taken at surgery. The classification of CE relied on ultrasound examination and CT scan, according to the WHO Informal Working Group on Echinococcosis (WHO-IWGE) classification revised criteria (Junghanss et al., Reference Junghanss, da Silva, Horton, Chiodini and Brunetti2008). Hydatid cysts were classified into five types: type CE1 (unilocular, simple cysts), type CE2 (multivescicular, multiseptated cysts), type CE3 (unilocular cyst which may contain daughter cysts with detachment of laminated membrane), type CE4 (heterogeneous or hyperechoic degenerative contents) and type CE5 (calcified cysts). Fifteen patients had type CE1 cysts; 23, type CE2; 4, type CE3; 6, type CE4; and 2, type CE5. Patients received anthelmintic treatment with albendazole, 400 mg twice a day for 3 months, plus praziquantel, 40 mg/kg per day for 2 weeks prior to surgical intervention and 3- to 6-month cycles of albendazole (10–12 mg/kg per day) after surgery, as per standard guidelines (WHO-IWGE, 1996). The most common surgical procedure performed was cystectomy using a freezing cone to prevent intra-operative spillage of cyst contents. The effectiveness of pharmacological and surgical treatment was evaluated by objective criteria, mainly based on imaging techniques (USG, CT scan and magnetic resonance imaging (MRI)) and cytokine determination at 6 months, 1 year and 2 years following pharmacological and surgical treatment. The long-term outcome of therapy was assessed by the presence or the lack of relapse 3 years after the pharmacological and surgical treatment.
Cytokine assays
Serum cytokine concentration of IL-4, IL-10 and IFN-γ were determined by enzyme-linked immunosorbent assay (ELISA) commercial kits (human IL-4, IL-10 and IFN-γ high-sensitivity ELISA kits, Gen-Probe Diaclone, France), according to the manufacturer's instructions. Ranges of the sensitivity standard curve of ELISA kits were 1–35 pg/ml for IL-4, 12.5-400 pg/ml for IL-10 and 0.78–25 pg/ml for IFN-γ. All serum samples were tested in duplicate. Cytokine concentrations were calculated using the mean optical density of two wells and comparison with a standard curve.
Data analysis
Results of cytokine detection were expressed as arithmetic means and ranges. Results were compared as healthy control group vs. pre-operative group; and also between pre-operative vs. post-operative groups. Results were evaluated using Student's t-test. A P value of less than 0.05 was considered to be statistically significant.
Results
In the present study the age of patients varied between 9 and 69 years. The mean age of the patients ( ± SD) was 31.12 ± 11.24 years. The highest number of cases (41) of disease was recorded among patients aged 20–49 years. Hydatidosis was found to be predominant in females (68%; 32% in males). Seventy-six per cent of patients were from rural areas and 24% from urban areas. Thirty-four of the radiologically and surgically confirmed cases had hepatic cysts, while 16 had extra-hepatic cysts (12 lung cysts, 3 liver and lung, and 1 thigh cyst). All patients responded to pharmacological and surgical treatment except for two women (aged 32 and 36 years) in whom multiple cysts (12 and 7 cysts, respectively) were detected in liver and lung 2 years after the first operation.
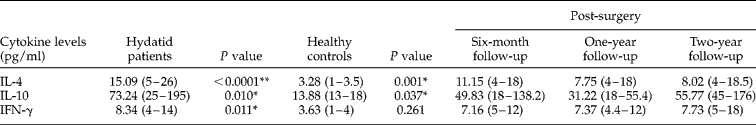
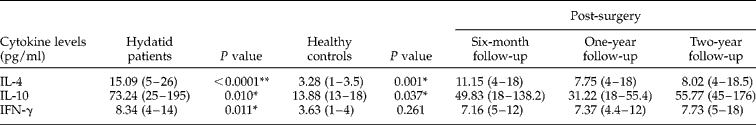
Serum cytokine levels of IL-4, IL-10 and IFN-γ were detected in patient sera at the time of surgery (pre-surgery) and post-surgery, i.e. 6, 12 and 24 months. The present data for IL-4 levels (table 1) clearly showed a significant increase in pre-operative patients compared with healthy controls (P< 0.0001), whereas at post-surgery up to 6, 12 and 24 months later there was a significant decrease in IL-4 compared with pre-operative levels (P= 0.001). This suggests that IL-4 can serve as a reliable marker for the success of such surgery.
Mean concentrations, with ranges given in brackets, of serum cytokine levels in 50 patients with CE and ten healthy controls before and after treatment.
*P< 0.05; **P< 0.0001.
IL-10 measurements also showed a significant increase in pre-surgery compared with healthy controls (P= 0.010). A substantial decrease in IL-10 was observed during post-surgery (P= 0.037), but this was not as marked as in the case of IL-4 levels (P= 0.001). High concentrations of IL-4 and IL-10 2 years later were likely to be due to relapses of the disease in two patients, although this was significantly less than at pre-surgery (P= 0.037). Nevertheless this cytokine does decrease during successful post-surgery and may serve as an additional adjunct marker (table 1).
The IFN-γ measurements were clearly elevated in patients before treatment (P= 0.011) but, as no significant changes occurred following pharmacological and surgical treatment, this cytokine is unlikely to serve as a marker for a relapse in cystic echinococcosis. The success of therapy was evident through clinical and imaging assessment at 2 years after the end of albendazole therapy, which showed that 96% of patients responded clinically.
Discussion
One of the most immediate needs in the post-surgical or post-pharmacological treatment immunosurveillance of CE patients is to identify markers indicating the effectiveness of treatment. The frequent relapse of disease (25%) after an initial therapeutic success is a serious problem in the pharmacological treatment of CE (Teggi et al., Reference Teggi, Lastilla and De Rosa1993). Results of the present study revealed that there is a considerable increase in both Th1 (IFN-γ) and Th2 (IL-4, IL-10) cytokines in CE patients. Cytokine levels of IL-4, IL-10 and IFN-γ were detected in 82%, 74% and 50% of hydatid patients at the time of diagnosis. These results are well supported by previous investigations (Rigano et al., Reference Rigano, Profumo, Di Felice, Ortona, Teggi and Siracusano1995a, Reference Rigano, Profumo, Ioppolo, Notargiacomo, Ortona, Teggi and Siracusanob; Zhang et al., Reference Zhang, Ross and McManus2008). Elevated cytokine levels were also observed in sera of hydatid disease patients with lung and liver involvement (Touil-Boukoffa et al., Reference Touil-Boukoffa, Sanceau, Tayebi and Wietzerbin1997). The coexpression of both Th1 and Th2 cytokines is in agreement with most of the previous studies (McManus & Bryant, Reference McManus, Bryant, Thompson and Lymbery1995; Vuitton, Reference Vuitton2003; Rigano et al., Reference Rigano, Buttari, De Falco, Profumo, Ortona, Margutti, Scotta, Teggi and Siracusano2004; Mezioug & Touil-Boukoffa, Reference Mezioug and Touil-Boukoffa2009). The coexistence of significantly high IL-4 production with high IL-10 concentrations observed in most of the hydatid patients supports Th2-cell activation in human hydatidosis. Despite producing IL-10, a known inhibitor of Thl cytokine production (Mosmann & Moore, Reference Mosmann and Moore1991; Sher et al., Reference Sher, Fiorentino, Caspar, Pearce and Mosmann1991), the patients also produced IFN-γ, suggesting that the immune response to E. granulosus infection is also regulated by the Thl (or Th0) cell subset. In human hydatidosis Thl- and Th2-type cytokine patterns probably coexist, each T-cell subset recognizing distinct epitopes on the parasite antigen.
The assessment of changes in serum cytokine levels of IL-4, IL-10 and IFN-γ in 6-month, 1-year and 2-year follow-up samples clearly demonstrates that IL-4 and IL-10 levels were considerably decreased in patients who responded to treatment. Results showed a clear association between IL-4 and IL-10 cytokine levels in patients with cystic echinococcosis and outcome of pharmacological and surgical treatment. High levels of IFN-γ and low levels of IL-4 and IL-10 (Th2) in patients who responded successfully to treatment are confirmed by many studies (Rigano et al., Reference Rigano, Profumo, Ioppolo, Notargiacomo, Ortona, Teggi and Siracusano1995b, Reference Rigano, Profumo, Buttari, Teggi and Siracusano1999a, Reference Rigano, Profumo, Ioppolo, Notargiacomo, Teggi and Siracusanob). Ortona et al. (Reference Ortona, Rıgano, Buttarı, Delunardo, Ioppolo, Marguttı, Profumo, Teggı, Vaccarı and Sıracusano2003) observed the decrease in IL-4 and IL-10 (Th2) and increase in IFN-γ (Th1) response in patients who responded successfully to treatment, and concluded that high IFN-γ (Th1) levels and low IL-4 and IL-10 (Th2) are the markers for successful treatment. Mezioug & Touil-Boukoffa (Reference Mezioug and Touil-Boukoffa2009) reported that Th1 response is more related to resistance, protective immunity and killing the cyst, whereas Th2 response is associated with susceptibility to disease and escapes immunity. Zhang & McManus (Reference Zhang and McManus2006) stated that when a cyst dies naturally, is killed by chemotherapy treatment or is removed by surgery, Th2 responses drop rapidly and Th1 responses become dominant. This can be interpreted as Th1 lymphocytes contributing significantly to the inactive stage of hydatid disease, with Th2 lymphocytes being more important in the active and transitional stages. Our results are well supported by the recent studies, which also observed significantly high levels of IL-4 and IL-10 cytokines in patients during the active stage of disease and considerably decreased levels of these cytokines after surgical treatment in combination with albendazole (Shan et al., Reference Shan, Ji, Li, Tuxun, Lin and Wen2011; Tuxun et al., Reference Tuxun, Wang, Lin, Shan, Tai, Li, Zhang, Zhao and Wen2012; Pang et al., Reference Pang, Zhang, Ma, Zhang, Zhao, Xin, Wang, Zhu, Wen and Ding2014).
In conclusion, the results point to the presence of both a Th1 and Th2 cytokine profile in CE, with Th2 predominance at the active stage of disease and significant decrease of Th2 (IL-4, IL-10) cytokines in patients who responded to treatment. Thus, the results, overall, indicated the usefulness of cytokine monitoring in the clinical follow-up of patients after treatment, and underline the need to search for more sensitive techniques to identify patients at risk of relapse.
Financial support
This research received no specific grant from any funding agency, commercial or not-for-profit sectors.
Conflict of interest
None.
Ethical standards
All procedures were approved by the Institutional Ethics Committee of MVM Bhopal and all subjects gave their informed consent to the study.