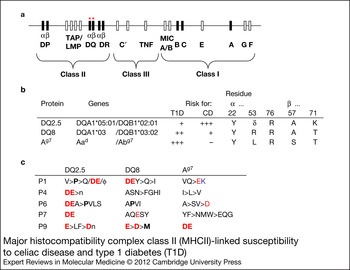
Major histocompatibility complex (MHC) genes were the first genes found to be associated with diseases that involve T-cell-mediated pathology (reviewed by Ref. Reference Carpenter1). These strong associations account for a substantial proportion of genetic risk. The MHC is a multi-locus region of the genome, which comprises several sub-regions containing clustered genes involved in immune function, as illustrated for the HLA (human leukocyte antigen) region, the human MHC, in Fig. 1a (Ref. Reference Klein2). The class II sub-region, which carries many of the strongest disease associations, encodes the α- and β-chains of several heterodimeric MHC class II (MHCII) glycoproteins, called HLA-DR, HLA-DP and HLA-DQ in humans. MHCII proteins are expressed constitutively on B cells, dendritic cells (DCs), thymic epithelial cells (TECs) and monocytes or macrophages [collectively, antigen-presenting cells (APCs)] and are inducible on other cell types (Ref. Reference Ting and Trowsdale3).
Major histocompatibility complex class II (MHCII)-linked susceptibility to celiac disease and type 1 diabetes (T1D). (a) Schematic map of the human MHC [human leukocyte antigen (HLA)] on human chromosome 6q23; polymorphic ‘classical’ class I and II genes are shown as black boxes, with DQ genes indicated by red asterisks. (b) Polymorphisms discussed in the text, which are implicated in the differential associations of HLA-DQ and H2-A subtypes with CD and T1D. These alleles differ in other respects, but the key polymorphisms are identified by comparison with nonsusceptibility alleles (not shown) and shown in single-letter code. δ, deletion. Residue numbering for DQ α-chain sequences in this figure, as throughout this manuscript, follows that for H2-A and HLA-DR (Ref. Reference Cucca90) to facilitate identification of homologous residues; native residue numbers for DQα would be higher by 3 (α25, α56, α79). (c) Anchor motifs for peptide binding to these risk alleles. Single-letter code is used. Charged residues are red (−) or blue (+). Groupings: ϕ, hydrophobic; n, neutral aliphatic; p, polar. Preferences discussed in the text are highlighted in bold.

MHCII genes show extensive structural polymorphism, with many alleles existing in human populations at most loci (except for the α-chain of DR), all of which differ from one another at several positions. Most individuals are heterozygous at most MHCII loci and express both alleles (termed codominance). In the international HLA gene nomenclature (Ref. Reference Marsh4), each allele is identified by its locus name followed by two pairs of digits, which identify structural variants (e.g. DRB1*04:01 for one of the structural variants of the gene coding for the HLA-DR β-chain). Different MHCII alleles are overrepresented in patients with different immune-related disorders, particularly in autoimmune diseases with a significant contribution of T cells to pathogenesis. In murine models of these conditions, genetic studies also indicate a marked effect on disease susceptibility of genotype at the two MHCII loci (called H2-A and H2-E, with alleles designated by superscripts, e.g. H2-Ed).
Structure and normal function of MHCII proteins
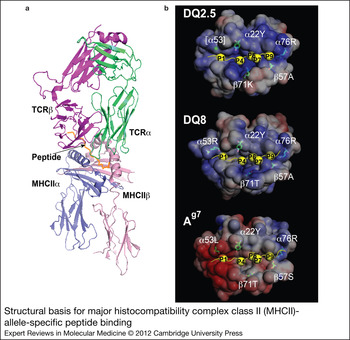
The normal function of MHCII glycoproteins is to capture peptides in endocytic compartments of APCs and to present them at the surface of these cells, where they can engage clonally variable antigen receptors (T-cell receptors, TCRs) on T cells expressing the CD4 molecule (CD4+ T cells), a coreceptor for MHCII (Ref. Reference Neefjes5) (Fig. 2a). Crystal structures of MHCII proteins reveal a single, groove-shaped peptide-binding site, which accommodates peptides with a nine residue binding ‘core’, usually with N- and C-terminal overhangs of varying length (reviewed in Ref. Reference Suri, Lovitch and Unanue6). Certain amino acid side chains are preferentially found at critical positions within the core (‘anchor residues’ at relative positions 1, 4, 6, 7 and 9), where they make complementary contacts with specificity pockets lining the groove. The complex also is stabilised by several hydrogen bonds between the peptide backbone and the groove. These mechanisms enable MHCII molecules to bind tens of thousands of peptides that satisfy the binding preferences at anchor residues (Refs. Reference Velazquez, DiPaolo and Unanue7, Reference Rammensee, Friede and Stevanoviic8). There is no discrimination between peptides derived from endosomal proteolysis of self-proteins or from invading pathogens. Much MHCII polymorphism involves short, recombined sequence cassettes that diversify the peptide-binding groove with remarkably little impact on the overall tertiary structure (examples are shown in Fig. 2b, with relevant polymorphisms listed in Fig. 1b). Thus, each MHCII allelic variant presents a distinct peptide repertoire (Ref. Reference Rammensee, Friede and Stevanoviic8), albeit with some overlap (Fig. 1c).
Structural basis for major histocompatibility complex class II (MHCII)-allele-specific peptide binding. (a) Ribbon diagram of a crystal structure showing T-cell receptor (TCR) engagement by peptide–MHCII complex on antigen-presenting cells. The 21.30 TCR (magenta and green) is shown engaging the murine MHCII molecule I-Ag7 (blue and pink), with the HEL11–27 peptide (orange) bound to it. Image was generated from Protein Data Bank (PDB) coordinates 3MBE (Ref. Reference Yoshida147) using PyMol software (Ref. Reference Schrodinger155). (b) Mapping of key polymorphic residues in Fig. 1b onto the binding grooves of the disease-associated human MHCII alleles DQ2.5, DQ8 and murine alleles Ag7. Crystal structures are shown of DQ2.5 complex with P6-deamidated αI-gliadin peptide (residues 57–68) [PDB code: 1S9 V (Ref. Reference Kim70); top], DQ8 complex with αII-gliadin peptide (residues 223–240) deamidated at P1 and P9 [PDB code: 2NNA (Ref. Reference Henderson73); middle] and Ag7/GAD peptide (residues 207–220) [PDB code: 1ES0 (Ref. Reference Corper125); bottom]. Each MHCII molecule is shown in a space-filling representation with surfaces colour coded according to electrostatic potential (red, negative; blue, positive). Side chains of key polymorphic residues discussed in the text are shown in a stick representation. The bound peptide is shown as a yellow ribbon with anchor residues as yellow spheres. Images were generated using Pymol along with the APBS tool and PDB2PQR web service and software package (Refs Reference Schrodinger155, Reference Baker156, Reference Dolinsky157, Reference Dolinsky158).

CD4+ T cells normally remain tolerant to self-peptides, as well as to peptides derived from innocuous foreign material (commensal organisms, food proteins, dust), while mounting protective responses against pathogens. This is possible because the functional consequences of antigen recognition depend both on the strength of the TCR interaction with peptide/MHCII, and on the the biological context. In the thymus, developing thymocytes require weak TCR ligation by self-peptide–MHC complexes on cortical TECs to survive (positive selection). Subsequently, strong TCR ligation by peptide–MHC on thymic medullary APCs (TECs or DCs) results in killing of thymocytes with dangerous levels of self-reactivity (negative selection). This key mechanism of central tolerance is supported by the expression of diverse peripheral self-antigens in medullary TECs under the control of the Autoimmune Regulator transcription factor (Ref. Reference Anderson9). Thymic positive and negative selection depends on the level of MHCII expression and on recognition of specific peptides (Ref. Reference Morris and Allen10). The percentage of surviving CD4+ T cells is small, and these cells enter the circulation either as short-lived regulatory CD4+ T cells (Tregs) (Refs Reference Liston and Rudensky11, Reference Vukmanovic-Stejic12), which dampen effector T-cell responses, or as long-lived naive T-helper cell precursors. Weak ligation by self-peptide–MHCII molecules on peripheral APCs reinforces self-tolerance (Ref. Reference Morris and Allen10) and promotes the survival of functional CD4+ T cells (Ref. Reference De Riva13). Thus, all peripheral CD4+ T cells are self-reactive, but normally maintain self-tolerance.
By contrast, during infection, CD4+ T cells initiate adaptive immune responses to nonself-peptides. DCs in infected tissues phagocytose or endocytose material from pathogens, which is fragmented into peptides, some of which bind to MHCII molecules. Triggered by proinflammatory signals, the DCs migrate to draining lymph nodes and present the pathogen-derived, MHCII-bound peptides to naive and memory CD4+ T cells, initiating their activation, proliferation and differentiation (Ref. Reference Zygmunt and Veldhoen14). Antigen presentation to the activated effector CD4+ T cells by other APCs (e.g. B cells, tissue macrophages) subsequently maintains antigenic specificity during the effector arm of the immune response.
Challenges in explaining MHCII associations with disease
Autoimmune diseases result from the activation of pathogenic effector T helper cells by self-antigens presented by MHCII molecules (e.g. Ref. Reference Di Lorenzo, Peakman and Roep15). Nonspecific inflammation or infection appears to be required to break T-cell tolerance. Thereafter, the chronic activation of infiltrating pathogenic T cells by local APCs contributes to the destruction of affected organs, alongside the pathogenic effects of autoantibodies made with help from T cells. Similarly, allergic diseases result from aberrant activation of T helper cells specific for normal, otherwise innocuous nonself-peptides, usually at mucosal surfaces. In contrast to autoimmune disease, the thymus is not thought to contribute to tolerance here, but mucosal tolerance mechanisms must be overcome.
Different MHCII alleles associated with one autoimmune disease often share polymorphisms in the groove (e.g. Figs. 1b and 2b). This suggests that the disease-associated polymorphisms determine the binding of self-peptides (e.g. Fig. 1c) and their presentation to autoaggressive T cells. Indeed, such T cells preferentially recognise autoantigen-derived peptides presented by the disease-associated MHCII alleles, rather than by other alleles that are coexpressed (see below). Such observations do not explain, however, why the presentation of self-peptides by the same MHCII alleles in the thymus and periphery is unable to maintain tolerance. Neither does it explain why other MHCII allelic variants, which usually can present other peptides from the same self-antigens, confer no risk. Thus, additional mechanisms must account for the association of particular MHCII alleles with loss of T-cell tolerance. Analogous considerations apply to MHCII-associated allergic diseases.
Complex regulation of peptide binding to MHCII molecules in vivo
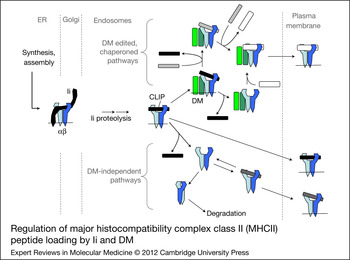
Antigen presentation by MHCII molecules is shaped by many factors besides their specificity for peptides. Importantly, peptide binding to MHCII molecules is regulated by other proteins during MHCII maturation and trafficking (Fig. 3) (reviewed in Refs Reference Neefjes5, Reference Busch and Mellins16–Reference Cresswell18). Newly synthesised MHCII α- and β-chains assemble in the endoplasmic reticulum (ER) as αβ heterodimers and rapidly associate with the invariant chain (Ii). A disordered region of Ii, including residues 81–104, folds into the peptide-binding groove of the newly assembled MHCII molecules (Ref. Reference Ghosh19) and prevents its premature occupation by other ligands in the ER (Ref. Reference Busch20). Directed by the cytoplasmic tail of Ii (reviewed in Ref. Reference Busch and Mellins16), the nascent αβIi complexes accumulate transiently in late endosomal multivesicular or multilamellar compartments. There, Ii cleavage by endosomal proteases yields MHCII molecules with their grooves still occupied by Ii remnant peptides, spanning residues 81–104 of Ii (now termed as CLIP, for ‘class II-associated Ii peptides’). CLIP must dissociate to allow binding of self- and nonself-peptides resulting from endosomal protein catabolism.
Regulation of major histocompatibility complex class II (MHCII) peptide loading by Ii and DM. MHCII chains are shown in shades of blue, Ii in black and DM in green. Events in different subcellular compartments are separated by grey dashed lines. Peptides derived from endosomal proteolysis are shown in grey or white, depending on their stability of association with MHCII (weak, grey; strong, white). Lipid membranes (thin horizontal lines) are sometimes omitted for clarity. HLA-DQ susceptibility alleles for CD and T1D, as well as the cellular context in nonobese diabetic antigen-presenting cells, appear to favour DM-independent peptide-loading pathways.

CLIP release may occur spontaneously (Ref. Reference Kropshofer, Vogt and Hämmerling21), but is accelerated by HLA-DM (H2-DM or H2-M in mice) (Refs Reference Sloan22, Reference Denzin and Cresswell23, Reference Sherman, Weber and Jensen24). DM structurally resembles the peptide-binding MHCII molecules, but lacks a peptide-binding groove (Ref. Reference Fremont25). Its lateral interaction with MHCII–CLIP complexes in endosomal membranes (Refs Reference Busch26, Reference Pashine27) catalyses CLIP release, stabilises empty MHCII molecules (Refs Reference Vogt28, Reference Denzin, Hammond and Cresswell29), accelerates exchange of endosomal peptides other than CLIP (Refs Reference Sloan22, Reference Denzin and Cresswell23, Reference Sherman, Weber and Jensen24) and, as a result of this editing process, favours the binding of peptides with slow rates of dissociation (Fig. 3, top right). Peptide-loaded MHCII molecules are finally deposited on the APC surface for inspection by CD4+ T cells.
This elegant mechanism, defined in cultured APC lines, only hints at the complexity of physiological antigen presentation. APC types differ in their content of endosomal proteases, which affects the processing of Ii and protein antigens (Refs Reference Hsing and Rudensky30, Reference Costantino31, Reference Reich32). Delivery of exogenous antigens into the MHCII pathway may involve phagocytosis (in macrophages and DCs) or receptor-mediated endocytosis, using surface immunoglobulin in B cells or lectin-type receptors in DCs (reviewed in Ref. Reference Neefjes5). Endogenous antigens might enter from the secretory pathway or, via autophagy, from the cytosol (reviewed in Ref. Reference Neefjes5). In subsets of B cells and DCs, DM activity is regulated by differential expression of HLA-DO (H2-O or H2-DO in mice), another distant MHCII homologue (Refs Reference Denzin33, Reference van Ham34). DO binds to DM and is thought to inhibit its interaction with MHCII molecules. APC types might differ in the relative abundance and trafficking of empty, CLIP-loaded and peptide-loaded MHCII molecules. For example, cortical TECs express relatively high levels of CLIP–MHCII (Ref. Reference Kasai35), whereas immature DCs express DM and empty MHCII molecules, available for peptide loading, at the cell surface (Ref. Reference Santambrogio36). Internalisation and turnover of MHCII molecules in immature DCs are regulated by β-chain ubiquitylation; activation of DCs by proinflammatory stimuli shuts down this pathway, allowing deposition of long-lived, cell surface peptide–MHCII complexes (Ref. Reference Shin37). Moreover, peptide loading pathways within one cell are heterogeneous: many peptides require Ii and DM for presentation to T cells, but other peptides are presented independently of these molecules, or might be inhibited by them (Refs Reference Lightstone38, Reference Katz39). Thus, peptide loading of MHCII molecules is modified by numerous cellular variables.
Are disease-associated MHCII molecules biochemically unusual?
These complexities are relevant to the question of how particular MHCII alleles predispose towards autoimmune disease, because MHCII alleles vary in their post-translational fate (reviewed in Ref. Reference Busch40). Some MHCII alleles release CLIP spontaneously, without DM, whereas others form very stable CLIP complexes, requiring DM for CLIP release and loading with antigenic peptides (Refs Reference Sette41, Reference Koonce42). The surface expression of many allelic variants with low CLIP affinity is reduced in the absence of DM, and their turnover is increased (Refs Reference Rinderknecht43, Reference Rinderknecht44). This is due to the loss of empty MHCII molecules after spontaneous CLIP release, or because of poor rescue by low-affinity peptide binding, in the absence of DM chaperoning and editing (Fig. 3, bottom right).
We have noted previously that many (but not all) MHCII alleles associated with autoimmune diseases form relatively unstable complexes with CLIP and discussed possible implications for autoimmune pathogenesis (Ref. Reference Busch40). Here, we review our current understanding of the overlapping MHCII associations with CD, a gastrointestinal hypersensitivity to dietary glutens, and with type 1 diabetes (T1D), an idiopathic autoimmune disease of pancreatic islets. We describe how structural polymorphism shapes both the inherent specificity for peptides and the post-translational fate of MHCII molecules, and discuss how these effects may promote immune pathology.
Celiac disease
Clinical features and association with HLA-DQ
CD is a chronic inflammatory enteropathy with diarrhea, steatorrhea, malabsorption, weight loss and, in children, growth retardation. It affects 1% of the population in developed countries, with a female bias and onset typically either in early childhood or following menopause (Ref. Reference Green and Cellier45). CD is triggered by dietary exposure to wheat glutens and their homologues in rye and barley. Heterogeneous proteins in these allergens (glutenins and gliadins, with subtypes designated by Greek letters and Roman numerals) trigger cellular and humoral hypersensitivity. Symptoms improve when the dietary triggers are eliminated, but compliance can be difficult and symptoms return upon re-exposure. Histology of affected small intestinal tissue shows villous atrophy, crypt hyperplasia and infiltration by memory and effector T helper cells into the lamina propria (Ref. Reference Halstensen and Brandtzaeg46).
CD has a clearly defined genetic component, shown by high concordance rates in monozygotic twins (Ref. Reference Houlston and Ford47). MHCII associations account for 35–40% of genetic risk (Ref. Reference Dubois48); many additional genetic risk factors have recently been identified, primarily by genome-wide association studies (GWAS) (Ref. Reference Dubois48). The two MHCII alleles associated with CD are DQA1*05:01/DQB1*02:01 and DQA1*03/DQB1*03:02, coding for the DQ2.5 and DQ8 proteins, respectively (Refs Reference Sollid49, Reference Spurkland50, Reference Spurkland51); the older protein nomenclature will be used subsequently. DQ2.5 is found in 90–95% of patients compared with 20–30% of controls; almost all DQ2.5-negative CD patients carry DQ8 (Ref. Reference Johnson52). DQ2.5 homozygosity confers a fivefold increased risk of CD, compared with heterozygotes, with intermediate risk for DQ2.5/DQ8 compound heterozygotes. The closely related alleles, DQ2.2 (DQA*0201/DQB*02) and DQ0602 (DQA1*0102/DQB1*0602), carry a very low risk for CD (Ref. Reference Harmon, Lebeck and Weidner53). Interestingly, latent CD (i.e. positive serology without clinical disease) tends to be associated with low-risk DQ genotypes (Ref. Reference Schirru54).
T-cell hyper-responsiveness to modified gluten proteins
The unique immune-stimulatory properties of gluten proteins result from a combination of their inherent properties and their processing and presentation by host APCs. The high Pro content of certain gliadin peptides renders them unusually resistant to intestinal proteolysis (Refs Reference Hausch55, Reference Shan56). Gliadin peptides may have direct proinflammatory effects (Refs Reference Hue57, Reference Di Sabatino58), but their pathogenicity depends on their specific recognition by CD4+ T cells in the lamina propria. Such T cells have been isolated from lesional tissue and blood of patients with CD after gluten challenge (Refs Reference Molberg59, Reference Gjertsen60). They are diverse in their TCR gene usage, but predominantly require peptide presentation by disease-associated DQ molecules (Refs Reference Molberg59, Reference Gjertsen60). APCs from individuals who are homozygous for the DQ susceptibility alleles present gliadin-derived peptides more efficiently than heterozygotes, correlating with disease risk (Ref. Reference Vader61).
Surprisingly, peptides derived from native gliadin sequences are not stimulatory; they bind poorly to DQ2.5 or DQ8 and consequently fail to elicit DQ-restricted CD4+ T cells. However, specific glutamine residues (Gln) within these peptides are substrates for deamidation to glutamate (Glu) by tissue transglutaminase (TG2), an enzyme in the gut epithelium (Ref. Reference Molberg62), which specifically targets Glu-x-Pro or Glu-x-x-ϕ sequence motifs (ϕ is any bulky hydrophobic residue) (Refs Reference Vader63, Reference Fleckenstein64). Deamidation can be mimicked by chemical synthesis of Gln→Glu-substituted peptides or promoted nonspecifically by heat treatment. Deamidation greatly enhances the ability of gliadin peptides to stimulate DQ2.5- or DQ8-restricted CD4+ T cells (Refs Reference Molberg62, Reference Vader63, Reference Fleckenstein64, Reference van de Wal65, Reference Quarsten66). The positioning of native Gln residues and of TG2-catalysed conversion to Glu in gliadin peptides is crucial for T-cell recognition (Refs Reference Quarsten66, Reference Arentz-Hansen67). The presentation of glutenin peptides by DQ8, however, is less dependent on TG2 (Ref. Reference van de Wal68).
Disease-associated DQ alleles bind modified gluten peptides
Pro-rich peptides, such as gliadin epitopes in CD, are poor binding substrates for most MHCII alleles, because in the core MHCII-binding region, the imidazole ring of the Pro side chain prevents participation in hydrogen bonds that tether peptides in the groove. Unusually, however, DQ2.5, the strongest CD risk allele, accepts Pro at P1, where a conserved hydrogen bond usually forms with the nitrogen atom of the peptide bond (Refs Reference Stepniak69, Reference Kim70) (Figs. 1c and 2b, top). This is due to a deletion at position 53 of the DQ2.5 α-chain, which renders this hydrogen bond dispensable (Fig. 1b; Fig. 1 legend shows DQα residue numbering conventions). At P6, DQ2.5 also can tolerate Pro, because of the unique presence of Ser30β. Disruption of hydrogen bonding normally disfavours Pro even at nonanchor positions in the binding core, but DQ2.5 allows Pro at P3 and P8 (Ref. Reference Stepniak69). Indeed, many gliadin epitopes have Pro residues at one or more of these positions.
DQ2.5 also is unusual in its ability to accommodate negatively charged peptide residues (Glu or Asp) at any position within the binding core (Ref. Reference Stepniak69) (Fig. 1c), as a result of positively charged residues (notably Arg76α and Lys71β) and extensive hydrogen bonding interactions in the groove (Ref. Reference Kim70). Except at P1, Gln is markedly less well tolerated at anchor residues than Glu, which explains the requirement for TG2 modification. The relative positions of Pro and Glu residues also matter. With Pro at P8 or a hydrophobic residue at P9 of a gliadin peptide, Gln at P6 becomes a substrate for TG2 (similarly for Pro at P6, with Gln deamidation at P4), improving binding to DQ2.5. The side chains of the remaining, unmodified Gln residues of gliadin peptides may assist binding by complementing defects in the main-chain hydrogen bond network owing to the Pro residues (Refs Reference Kim70, Reference Bergseng71).
Peptide-binding specificity also explains some of the variation in CD risk associated with DQ subtypes. DQ8, which confers less risk than DQ2.5, presents fewer Pro-rich α-gliadin peptides (Ref. Reference Shan56). One contributing factor is the presence of Arg at residue α53, which prohibits interaction with Pro at P1. Furthermore, whereas for HLA-DQ2.5 a single deamidation step at P4, P6 or P7 of a gluten peptide is sufficient to evoke a CD4+ T-cell response, for HLA-DQ8, deamidation at two positions (P1 and P9) is preferred. This might further limit the efficiency of generating DQ8-binding gliadin peptides (Refs Reference Tollefsen72, Reference Henderson73). Both factors might contribute to the lower disease risk associated with DQ8 (Ref. Reference Margaritte-Jeannin74). Unexpectedly, the nonassociated DQ2.2 variant has a peptide-binding motif that closely resembles that of DQ2.5, but presents gluten peptides less well. This might relate to difficulties in accommodating Pro at the P3 position in DQ2.2 (Refs Reference Vader61, Reference Qiao75, Reference van de Wal76), although recent work (Ref. Reference Fallang77) contests this and favours another explanation, which is discussed below.
Unusual mode of peptide acquisition by disease-associated DQ alleles
In addition to its unique peptide-binding specificity, DQ2.5 also interacts abnormally with Ii and DM. Most MHCII alleles bind CLIP in a single binding register (‘CLIP1’), shown in the crystal structure of CLIP bound to DR3 and using Met91 (human Ii numbering) to occupy the P1 position of the groove (Ref. Reference Ghosh19). DQ2.5, however, is able to bind in a noncanonical ‘CLIP2’ binding register, with Pro96 in P1 (Refs Reference Fallang78, Reference Wiesner79). In vitro, the rate of spontaneous CLIP release, in either register, from recombinant soluble DQ2.5 molecules is slower than CLIP release from DR3, and even slower than that of some gliadin peptides. Quantitative peptide extraction experiments indicate that CLIP naturally occupies the majority of DQ2.5 molecules, similar to the high occupancy of DR3 with CLIP in cells lacking DM (Refs Reference Fallang77, Reference Fallang78).
This phenotype is exaggerated by a poor interaction of DQ2.5 with DM (Ref. Reference Hou80). CLIP release from DQ2.5 is slow even in DM-sufficient cells. In vitro, at least tenfold more recombinant DM is required to release CLIP (either register) from DQ2.5 molecules than from DR3. CLIP complexes with DQ1 (DQA1*01:01, DQB1*05:01) show a normal degree of DM susceptibility. The deletion of residue α53 in DQ2.5 (as in all DQ alleles with DQA1*04 and *05 chains) is critical, because insertion of Gly, the residue at α53 in DQ1, restores sensitivity to DM (Ref. Reference Hou80). Interestingly, the insertion of Arg at this position (found in DQA1*03, and thus in DQ8) fails to restore sensitivity to DM, suggesting that DQ8 also interacts poorly with DM.
Extreme CLIP retention would prevent antigen presentation (Ref. Reference Miyazaki81). However, DQ2.5 allows sufficient CLIP release for gliadin peptide presentation. Interestingly, recent studies show that DQ2.5 resistance to DM editing actually promotes the presentation of certain gliadin peptides (Ref. Reference Hou80). Model APCs expressing wild-type DQ2.5 molecules present an immunodominant αII-gliadin (residues 62–70) peptide to T cells, with or without DM present. Expression of the DM-sensitive DQ mutant (α53Gly insertion) markedly suppresses the presentation of this peptide, whereas presentation in the absence of DM is maintained. The DQ2.5 DM interaction defect could enable the presentation of other gluten peptides in CD, which would otherwise be edited by DM.
For most other MHCII alleles, lack of DM interaction results in the presentation of peptides that form ‘unedited’, kinetically unstable complexes. However, one factor contributing to the prolonged retention of CLIP and several gliadin peptides is the presence of a Tyr at position α22 in DQ2.5, which participates in hydrogen-bonding networks with the peptide main chain (Ref. Reference Fallang77). This feature is shared with most DQ alleles, including DQ8. A few subtypes, including DQ2.2, have Phe at this position. Introduction of this change into DQ2.5 results in faster release of CLIP and gliadin peptides and reduces the persistence with which antigens are presented (Ref. Reference Fallang77). This might explain why DQ2.2 does not confer substantial risk of CD, even though its anchor motif closely resembles that of the DQ2.5 high-risk allele. The Tyr α22 effect is DM-independent: introduction of Phe at α22 into DQ2.5 does not restore DM-dependent peptide exchange (Ref. Reference Hou80).
A series of unfortunate events
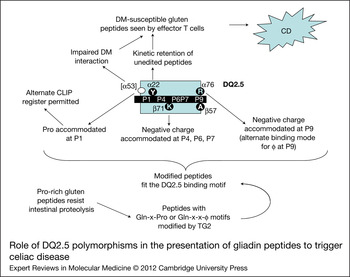
In summary, the genetic association of CD with HLA-DQ2.5 can be explained by a ‘series of unfortunate events’ (Fig. 4). The model explains why the DQ risk alleles are necessary for CD, but does not explain why, despite inescapable exposure to glutens in normal Western diets, most individuals with DQ risk alleles do not develop CD. Other genetic factors or environmental triggers, or both, must be important. The model endorses the development, now underway, of gliadin-degrading enzymes to destroy immune-stimulatory peptides in the gut, of TG2 inhibitors to prevent their immunogenic modification, of varieties of grain that lack relevant T-cell epitopes, and of allele-specific, nonimmunogenic MHCII-blocking peptides. A novel possibility is to mimic DM editing of DQ2.5 and DQ8 to reduce the presentation of gliadin peptides. Small-molecule ‘chemical chaperones’ that promote peptide exchange by MHCII have been developed (Ref. Reference Falk82). It would be interesting to know whether these agents act on DQ2.5 molecules despite their DM resistance. One caveat is that self-peptide exchange by such agents might create neo-epitopes that could trigger autoimmunity.
Role of DQ2.5 polymorphisms in the presentation of gliadin peptides to trigger celiac disease. Peptides derived from dietary glutens, rendered uniquely resistant to proteolysis by their high Pro content, survive digestion in the small intestine, only to be deamidated at critical Gln residues by epithelial TG2, enabling them to bind DQ2.5, by virtue of its unusual peptide-binding properties. The presentation of at least some peptides is boosted by inefficient DM editing of the peptide repertoire bound to DQ2.5, in combination with prolonged, sequence independent, retention of peptides. These factors promote activation of gluten-specific, disease-causing CD4+ helper T cells. This constellation of properties appears to be shared, to varying degrees, by the risk alleles, but not by the nonsusceptibility alleles. The less strongly associated DQ8 allele shares many of the key features of DQ2.5, but has a different peptide-binding motif that is less well matched to the intestinal processing and modification patterns of gliadins. The low-risk allele DQ2.2 has a permissive peptide-binding motif but does not retain gliadin peptides as persistently; other alleles lack suitable binding motifs, and some interact better with DM.

The existence of several HLA-DQ-transgenic mouse models, on various genetic backgrounds, will be helpful in exploring these therapeutic possibilities. These mice mount strong mucosal CD4+ T-cell responses to gliadins, although in many studies the prevailing cytokine secretion patterns are anti-inflammatory; clinically significant enteropathy develops only on a genetic background with particular autoimmune susceptibility (review in Ref. Reference Marietta, David and Murray83).
Type 1 diabetes
Clinical features and association with DQ
In T1D, insulin-secreting β-cells in the pancreatic islets of Langerhans are destroyed, causing insulin deficiency and leading to life-threatening hyperglycemia and ketoacidosis (reviewed in Ref. Reference Daneman84). The disease can occur at any age, but usually has juvenile onset. Insulin replacement therapy prevents acute T1D and must be maintained for life by insulin injections and glucose monitoring. Even so, life expectancy is reduced because of chronic complications from imperfect glucose control.
Human T1D has a well-recognised genetic component. MHC genes are the most important susceptibility regions (Ref. Reference Davies85), accounting for ≈50% of genetic risk (Ref. Reference Tisch and McDevitt86). In the MHCII region, the strongest association signals are found at HLA-DQB1, even though the attribution of risk to this locus is complicated by linkage disequilibrium with adjacent DQA1 and DR loci, creating conserved haplotypes. With few exceptions, a sequence feature shared between DQ risk alleles is the presence of an uncharged residue (Val, Ser or Ala) at position 57 of the β-chain. Nonsusceptibility alleles have a negatively charged aspartic acid (Asp) residue at this position. The most strongly associated alleles in Caucasians are DQ8, followed by DQ2 (Ref. Reference Todd, Bell and McDevitt87 and review in Ref. Reference Wucherpfennig88; Fig. 1b) – the same loci implicated in CD, but in reverse order. Interestingly, DR3/DR4 heterozygotes are at particularly high risk of T1D. This is thought to be due to the generation of mixed-haplotype DQ αβ heterodimers ‘in trans’ and suggests that α-chain pairing is also important. Consistent with this, one study has suggested that Arg49α is a risk-associated polymorphism (Ref. Reference Khalil89). Interestingly heterozygosity for some Asp57β alleles confers dominant protection from disease. Other MHC polymorphisms confer risk independently of DQ. In the class II region, most DR4 subtypes confer increased risk, but DRB1*04:03 does not; in the class I region, associations with HLA-A and -B are found in large family studies (Refs Reference Cucca90, Reference Polychronakos and Li91, Reference Nejentsev92). Polymorphisms at the insulin gene and several genes implicated in T-cell regulation (IL2 and its receptor, CTLA4, PTPN22) and many less-well-defined loci show weak associations with T1D in GWAS (Ref. Reference Barrett93).
The histopathology of T1D confirms immune involvement, characterised by lymphocytic infiltration into pancreatic islets; overt T1D ensues once a majority of β-cells are lost (Ref. Reference Nichols and Cooke94). Autoantibodies to islet-specific autoantigens, including insulin and glutamic acid decarboxylase (GAD), and CD4+ effector T cells specific for peptides from these autoantigens, are found in the blood of T1D patients. These autoreactivities may develop long before clinical disease onset (Ref. Reference Mallone, Brezar and Boitard95).
H2-Ag7-associated T1D in nonobese diabetic mice
The role of MHCII molecules in T1D pathogenesis has also been studied in the nonobese diabetic (NOD) mouse, a diabetes-prone mutant strain (Ref. Reference Makino96), which shows remarkable similarities with human T1D. NOD mice develop spontaneous insulitis with T-cell infiltration and autoantibodies to islet autoantigens. T1D develops around 3 months of age, with greater penetrance in females than males. Both CD4+ and CD8+ T cells are important, based on studies on T-cell-deficient mutant mice (Ref. Reference Makino97) and adoptive transfer experiments (Ref. Reference Matsumoto98).
MHCII genotype is critical for T1D in NOD mice. Their H2-Aα chain gene is identical to that of Ad (found in nonsusceptible strains), but the β-chain, designated Aβg7, is unique among inbred mouse strains, differing from Aβd at 17 positions (Ref. Reference Acha-Orbea and McDevitt99). Antibody blocking of Ag7 prevents T1D (Ref. Reference Boitard100). Like the T1D-associated DQ alleles, Ag7 has a non-Asp residue (Ser) in position β57; the adjacent position His56 is not shared with DQ (Ref. Reference Acha-Orbea and McDevitt99). Transgenic expression of mutant Aβg7 chains, with Proβ56 or Aspβ57, results in competition of mutant molecules with endogenous wild-type Aβg7 for pairing with Aα and greatly reduces T1D, indicating a critical role for these polymorphisms (Refs Reference Quartey-Papafio101, Reference Lund102). Thus, the key disease-related MHCII polymorphism in autoimmune T1D is the same in mice and humans.
Homozygous expression of I-Ag7 is required for disease in NOD mice (Ref. Reference Hattori103). This is reminiscent of the increased risk of T1D in humans homozygous for non-Asp57β alleles of DQ and of dominant protective effects of some Asp57β alleles. NOD mice lack expression of H2-Eα, the orthologue of HLA-DRα; thus, H2-A is the sole expressed MHCII protein, except possibly for low-level ‘mixed-isotype’ pairing of Aα with Eβ. Transgenic expression of Eα confers protection of NOD mice (Ref. Reference Lund102); this might be analogous to protective effects of some DR alleles in humans. Mapping of other disease genes outside the H2 region supports the idea that NOD mice recapitulate much of the pathogenesis of human T1D (Ref. Reference Polychronakos and Li91).
In NOD mice, pancreatic islet development might be abnormal at weaning (Ref. Reference Pelegri104). Myeloid APCs show early developmental defects (Ref. Reference Strid105), and may contribute to abnormal islet function and homeostasis (Ref. Reference Durant106). B-cell development is also abnormal in NOD spleen, with altered representation of transitional and marginal zone B cells (Ref. Reference Rolf107). Progression from insulitis to overt diabetes is accompanied by expansion of marginal zone B cells and their invasion into pancreatic islets, suggesting that antigen presentation by this subset contributes to pathogenesis (Ref. Reference Marino108). Indeed, B-cell-deficient NOD mice do not develop diabetes (Ref. Reference Serreze109). Antigen presentation by pancreatic DCs has also been implicated in T1D pathogenesis (Ref. Reference Mohan110). Together, these findings suggest that antigen presentation evolves over time during T1D pathogenesis and involves several APC types.
MHCII association with T1D: a role for covalently modified self?
T-cell epitopes from islet cell autoantigens, including GAD, preproinsulin and insulin B chain, have been identified in mouse and human and are generally presented by the disease-associated MHCII alleles (Ref. Reference Di Lorenzo, Peakman and Roep15). It should be noted, however, that the earliest infiltrating CD4+ T cells show evidence of clonal expansion but respond to none of the defined islet autoantigens (Refs Reference Baker111, Reference Gelber112), suggesting that the known specificities arise from epitope spreading. The peptide-binding motifs of the disease-associated DQ8 and DQ2 alleles, and of Ag7 in mice, are unusual, but the ability of islet autoepitopes to satisfy these requirements is not, by itself, sufficient to explain why T1D risk is increased by these particular risk alleles, rather than any others.
Studies of particular islet autoantigens suggest some explanations for loss of self-tolerance to specific peptides. One immunodominant peptide from insulin A chain requires a non-native disulfide bond to stimulate T cells (Ref. Reference Mannering113). Here, disulfide bond reshuffling can break self-tolerance by generating neo-self-determinants. In a different mechanism for generating neo-determinants, NOD CD4+ T cells respond to an insulin peptide bound to Ag7 in a register that is not efficiently generated by normal processing of whole insulin; by contrast, T cells to an overlapping, well-processed peptide are deleted (Ref. Reference Mohan, Petzold and Unanue114). Incomplete central tolerance to insulin could also arise from the discrepancy between low-level expression of insulin in the thymus and extremely high local concentrations of insulin in pancreatic islets. Indeed, insulin promoter polymorphisms that reduce thymic expression of insulin increase risk of T1D (reviewed in Ref. Reference Polychronakos and Li91). However, a link to particular DQ alleles or Ag7 has yet to emerge: similar mechanisms might operate in the context of other MHCII alleles that do not confer T1D risk.
Quantitative defects in antigen presentation and tolerance
Although islet autoepitopes bind the disease-associated MHCII variants, a high binding affinity does not appear necessary. At least one immunodominant insulin peptide in NOD mice does not form highly stable complexes with Ag7 (Ref. Reference Suri, Levisetti and Unanue115); an autoepitope from chromogranin A appears to have an unusual mode of binding with partial occupancy of the groove (Ref. Reference Stadinski116). Consistent with this, some crystal structures of T1D-associated MHCII alleles show suboptimal P9 side chain or pocket interactions (Ref. Reference Kim70). The relative instability of some of these complexes resembles findings in other autoimmune diseases (Ref. Reference Fairchild117), but contrasts with the good correlation between stable MHCII binding and immunodominance in response to foreign antigens (Ref. Reference Sant118). Thymic presentation of moderate affinity peptides may be inefficient, leading to escape from deletion of the T cells recognising them.
Presentation defects in NOD mice might reflect a generalised propensity towards Ag7-restricted autoreactivity. Immunisation of NOD mice with foreign protein in adjuvant leads to the activation of T cells that react with self-antigens on NOD splenocytes (Ref. Reference Ridgway119). This ‘autoproliferation’ requires Ag7 homozygosity and is suppressed by the expression of other H2-A alleles, or of H2-E, matching the genetic regulation of T1D (Ref. Reference Ridgway119). Autoreactive T cells in mouse strains carrying I-Ag7 (NOD and the H2-congenic B6.g7 strain) are more frequent compared with mice of H-2b haplotype (NOD.H-2b and B6) (Ref. Reference Kanagawa120). Thus, expression of Ag7 as the sole MHCII allele confers a defect in T-cell tolerance, which is not islet-specific. Deletion of self-reactive transgenic TCRs is highly efficient in other mouse strains, but autoreactive T cells escape into the periphery in NOD mice. Depending on the TCR, autoimmunity may affect pancreatic β cells (e.g. BDC2.5 TCR) or other target organs (Ref. Reference Mangialaio121). These transgenic systems require Ag7 for peptide presentation to pathogenic T cells, but a single copy of Ag7 is sufficient and other class II alleles fail to protect. Recent work suggests that BDC2.5 NOD mice generate an excess of αβ (versus γδ) T-cell precursors, compared with H2-identical B6.g7 mice, which may alter their subsequent thymic selection independently of Ag7 (Ref. Reference Mingueneau122), but these findings do not contradict the notion that Ag7 is inefficient at enforcing self-tolerance. Collectively, these findings argue that T1D in NOD mice arises in part because of defective thymic negative selection of diabetogenic T cells; Ag7 also might be limited in its ability to maintain peripheral tolerance and Treg's (Ref. Reference Mellanby123).
Is Ag7 a promiscuous peptide binder?
The peptide-binding specificity of the Ag7 groove may promote this generalised autoreactivity. Its peptide-binding motif, shown in Fig. 1c and based on quantification of amino acids systematically over-represented in naturally processed Ag7-binding peptides, does not seem unusual. However, in vitro assays (Refs Reference Stratmann124, Reference Corper125) show that many other side chains are permitted at P1; the small side chains preferred at P4 and P6 provide little scope for stabilising interactions. P9 shows a clear statistical preference for acidic residues, but many binding peptides have small neutral amino acids at P9. These unusually permissive side chain preferences of Ag7 allow promiscuous binding of diverse peptides from self-antigens, compared with greater selectivity of other murine MHCII alleles (Refs Reference Stratmann124, Reference Corper125). Structural studies of Ag7 are consistent with these findings (Ref. Reference Corper125). Moreover, Ag7 is thought to show a defect in the retention of bound peptides (Ref. Reference Carrasco-Marin126). Thus, Ag7 might have an intrinsic tendency to present many peptides at lower abundance and more fleetingly than other alleles, increasing the risk of errors during T-cell-negative selection. This tendency of Ag7 differs from the nonspecific peptide retention by DQ2.5 and DQ8, which confers high risk of T1D, but resembles the poor peptide retention by DQ2.2, which is not a high-risk allele despite having a non-Asp residue at β57 (Ref. Reference Cucca90). Paradoxically, Ag7 shares Tyr22α, the residue implicated in peptide retention by DQ2.5 and DQ8. Thus, the role of polymorphism at α22 in peptide retention, and thus its potential contribution to T1D pathogenesis, may differ between mice and humans.
The peptide-binding defect of Ag7 is not universal. Peptides from autoantigens, as well as from uninvolved self-proteins, with a length of at least 13 amino acids and an acidic residue at the C-terminus, show stable binding to Ag7 (Ref. Reference Reich127). Similarly, acidic P9 residues are found frequently in naturally processed peptides from APCs and pancreatic islet β-cells (Refs Reference Suri128, Reference Suri129, Reference Suri130). Crystal structures of other H2-A alleles show an inter-chain salt bridge between Aspβ57 and Arg in position α76. The structure of Ag7 bound to a GAD65 peptide shows, as expected, that Ser at β57 lacks this salt bridge, but the negatively charged P9 residue (Glu217) of the bound peptide compensates (Ref. Reference Corper125). Thus, the binding characteristics of Ag7-bound self-peptides with negative charges at P9 might be more typical of those bound to other MHCII alleles, whereas self-peptides with neutral residues at P9 may bind more loosely. The preference for peptides with acidic P9 residues is shared with non-Asp57β alleles of DQ.
Does Ag7 show defective maturation and peptide loading?
The Ser57β polymorphism also is thought to affect the post-translational fate of Ag7. Pulse/chase labelling studies show no major defects in assembly, early maturation and ER to Golgi export of Ag7 (Ref. Reference Reizis131), but defects are detectable in other assays. In Ii-deficient cells, substitution of Asp57β to Ser in Ad (as in Ag7) impairs surface expression (Ref. Reference Nalefski, Shaw and Rao132). Thus, lack of inter-chain salt bridging may compromise αβ heterodimer assembly in non-Asp57β alleles. However, as murine APC populations in vivo typically express Ii, and Ii transfection overcomes the expression defect of Ad (Aspβ57→Ser) (Ref. Reference Nalefski, Shaw and Rao132), assembly defects are unlikely to contribute much to immune defects associated with lack of Asp57β in vivo. Moreover, Ag7 αβ heterodimers expressed as recombinant soluble molecules in insect cells have been used in peptide-binding and crystallisation studies without evidence of instability (Ref. Reference Hausmann133).
Following Ii proteolysis, Ag7 might be unusual in its further maturation post-Golgi. At endosomal pH, CLIP is released rapidly in vitro from recombinant soluble Ag7 (Ref. Reference Hausmann133). The rates suggest that spontaneous CLIP release (i.e. without DM) should readily occur during endosomal trafficking of nascent MHCII molecules. This may afford opportunities for loading of peptides without participation of the editing function of DM (Ref. Reference Busch40), exacerbating promiscuous peptide binding in vivo. The low stability of Ag7/CLIP is partly attributable to the P9 pocket preferences of this allele, because stabilisation can be achieved by replacing Met98 of CLIP (murine Ii numbering) at P9 with a negatively charged residue (Ref. Reference Rinderknecht44).
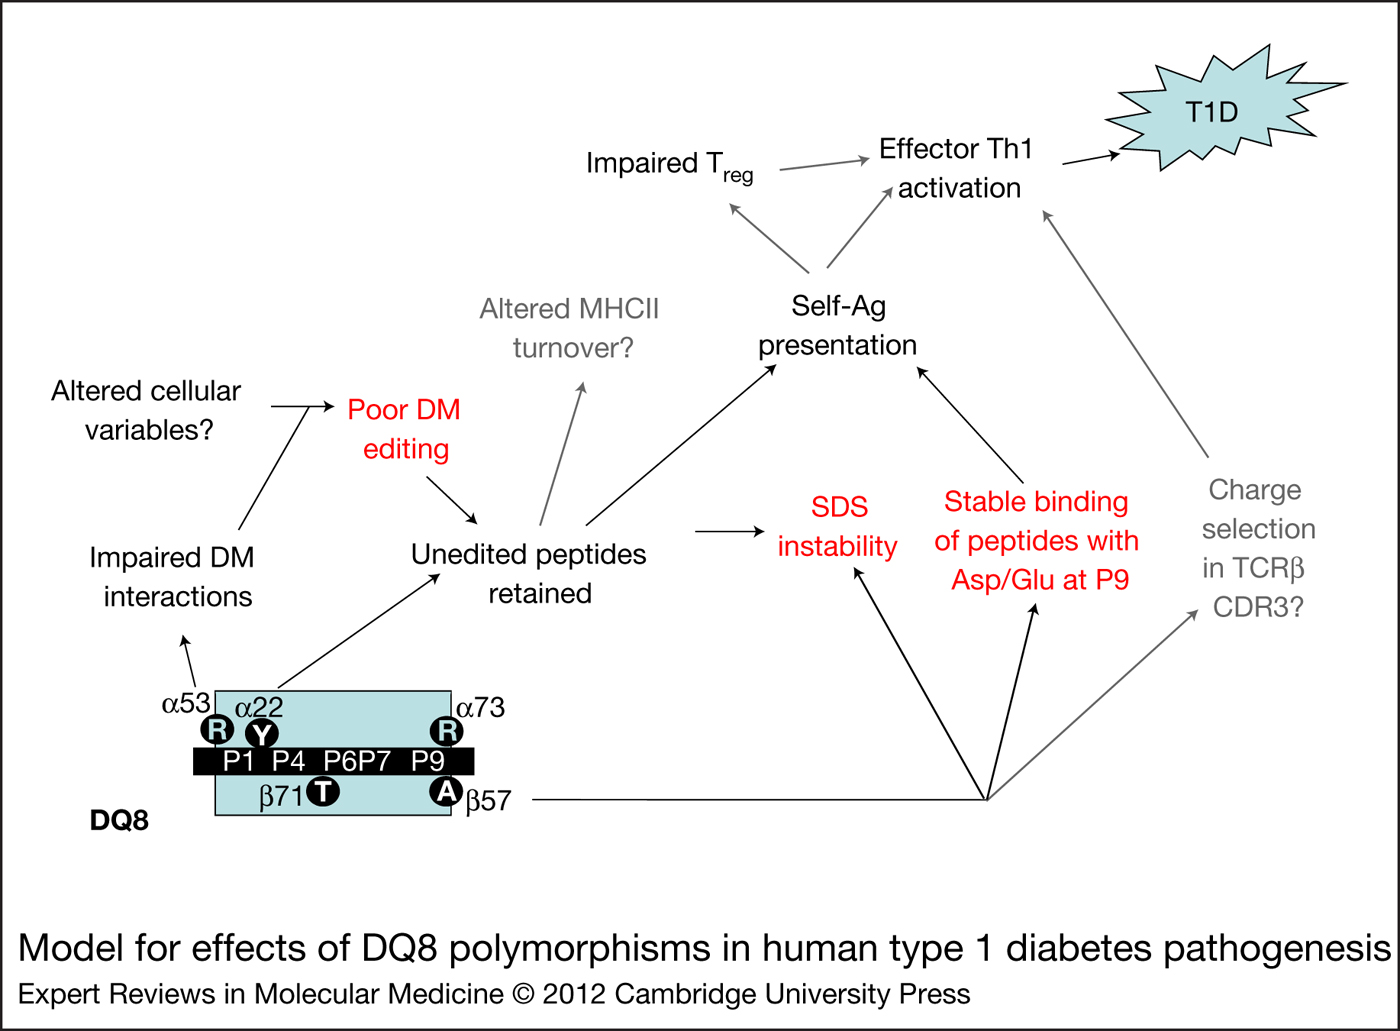
The α51–53 region, which modulates DM interactions of DQ alleles, is polymorphic among H2-A alleles, including Ag7 (Ref. Reference Cucca90). However, there is no evidence that Ag7 fails to interact with DM as a result. In transfected cells, expression of DM can aid CLIP release from Ag7 (Ref. Reference Peterson and Sant134). Moreover, Ag7 expression is reduced in mutant APC lacking H2-DM because of accelerated turnover (Ref. Reference Rinderknecht44). The surprising observation that NOD splenocytes nonetheless have increased levels of CLIP at the surface therefore suggests a CLIP exchange defect (Ref. Reference Bhatnagar135). The cellular regulation of peptide exchange also might be abnormal in PBMCs from T1D patients, which express elevated CLIP levels (Ref. Reference Silva136). This observation is consistent with the inherent resistance of the human DQ2 and DQ8 risk alleles to DM-catalysed CLIP release (see above), but other studies suggest an abnormal environment for peptide loading. In B cells from twins discordant for T1D, expression of the p35 isoform of Ii is lower in T1D and associated with a greater ability to load MHCII molecules with exogenous peptides (Ref. Reference Yan137). Moreover, a DR4-restricted GAD autoepitope was found to be presented less efficiently in cells expressing high levels of DM, suggesting that poor editing may reveal this epitope in vivo (Ref. Reference Lich138). Thus, poor DM-mediated peptide editing and loading with suboptimal peptides might be shared features of human and murine T1D antigen presentation, although the mechanisms differ and only the human DQ alleles show a pronounced inherent DM interaction defect (cf. Figs. 5 and 6).
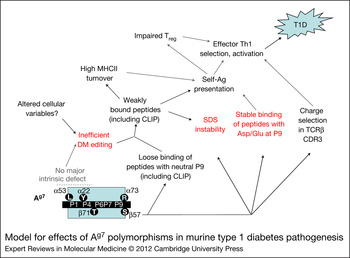
Model for effects of Ag7 polymorphisms in murine type 1 diabetes pathogenesis. Both peptide-binding specificity and use of unedited peptide loading pathways are affected by β57 polymorphism and further modified by other polymorphisms and cellular context. Features shared with DQ8 (red text, also see Fig. 6) include the P9 preference for negatively charged residues, sodium dodecyl sulfate instability and poor DM editing. Note that Ag7, unlike DQ8, has not been shown to exhibit a DM interaction defect in transfected cells, suggesting that cellular variables impair DM editing in nonobese diabetic mice. The exact causal relationships between the biochemical defects and effector T-cell selection or activation remain speculative (indicated by grey arrows).

Model for effects of DQ8 polymorphisms in human type 1 diabetes pathogenesis. See legend to Fig. 5 and text for details.
Is Ag7 unstable in NOD mice?
Another phenotype associated with the Ag7 in NOD mice is accelerated protein turnover, for example in cultured NOD splenocytes (Ref. Reference Carrasco-Marin126). The MHCII molecules in these experiments derive mostly from B cells, but Ag7 expression by NOD bone marrow-derived DCs is also diminished (Ref. Reference Strid105). The in vivo instability of Ag7 could contribute to inefficient thymic selection and peripheral tolerance. Little is known about how the disposal of internalised MHCII molecules is regulated by peptide binding, DM chaperoning and proteolysis, and how these variables are affected by MHCII polymorphism. Important variables that affect measured Ag7 turnover in NOD splenocytes remain to be addressed. Allele-specific monoclonal antibodies used for immunoprecipitation may differ in their binding to MHCII conformations with greater or lesser stability in vivo, confounding the effects of structural polymorphism (Ref. Reference Arneson, Peterson and Sant139). The relative proportion of functional subsets of splenic B cells differs between NOD and control mice. Similarly, the maturation and function of DCs are abnormal in the NOD strain (Refs Reference Strid105, Reference Marleau, Summers and Singh140).
Most MHCII alleles are stabilised by the binding of high-affinity peptides so that, at room temperature, they resist chain dissociation by the detergent, sodium dodecyl sulphate (SDS). In contrast, complexes of most alleles with Ii and CLIP are unstable in SDS and acquisition of SDS stability is normally dependent on DM-dependent endosomal peptide loading (Refs Reference Morris141, Reference Germain and Rinker142). H2-Ag7 is a notable exception, dissociating readily during SDS-PAGE (polyacrylamide gel electrophoresis) analysis of un-boiled samples (Ref. Reference Carrasco-Marin126). The β56/57 polymorphisms are a key determinant of SDS instability. Human DQ alleles also vary in their SDS stability; lower SDS stability correlates closely with increased risk for T1D conferred by DQ2 and DQ8 subtypes (Ref. Reference Ettinger143). The biological significance of this correlation is difficult to assess, and SDS stability may simply be a biochemical correlate of the genetic polymorphism. When compared with other H2-A alleles, Ag7 falls at the lower end of a spectrum of stability, rather than being an extreme outlier, but this does not rule out a contribution of Ag7 instability to the autoimmunity of NOD mice.
Peptide loading regulators and T1D pathogenesis in mice
Studies of mutant NOD mice lacking Ii confirm the importance of peptide loading regulators in T1D pathogenesis. These mice do not develop T1D and development of insulitis is impaired, even though, surprisingly, Ii-null NOD APCs present islet autoantigens well (Ref. Reference Mellanby144). Protection from T1D in the absence of Ii is associated with a reduced ratio of effector to regulatory CD4+ T cells. In contrast, B-cell development, which is impaired by Ii knockout in other mouse strains, is unaffected in NOD mice. In the absence of Ii, Ag7 molecules form heterogeneous, SDS-stable complexes, probably with ER polypeptides; moreover, H2-DM expression is reduced in Ii-deficient mice (Ref. Reference Koonce and Bikoff145). A role for peptide loading cofactors in pathogenesis is further supported by an elegant study, in which DM-catalysed peptide exchange was modulated in NOD by expression of human DO in myeloid DCs under the control of the CD11c promoter (Ref. Reference Yi146). Strikingly, this intervention protected NOD mice from diabetes, implying a critical role for DM in regulating the presentation of tolerogenic versus pathogenic self-peptides, although these studies have not yet been able to address directly the functional relevance of un-edited peptide loading or MHCII instability in pathogenesis.
Does Ag7 select unusual TCRs?
Lastly, recent work suggests that the lack of Asp57β in Ag7 also affects interactions with the TCR. This idea is consistent with enrichment for negatively charged residues observed in TCR β-chain CDR3 sequences of CD4+ T cells from NOD mice, regardless of peptide-binding specificity (Ref. Reference Yoshida147). Structural studies suggest that this is due to long-range electrostatic interactions with Arg76α. Conceivably, a gain of interactions of CDR3 regions with MHCII at the expense of interactions with the peptide may compensate for the diminished abundance of some peptides, yet increase the likelihood of errors in self- and nonself-discrimination, and thus of autoimmunity.
In summary, a functional link between poor editing of peptides presented by the T1D-associated MHCII alleles and autoimmune propensity is plausible, but remains hypothetical (Figs. 5 and 6). Islet-specific effector CD4+ Th1 cells may escape thymic deletion and peripheral tolerance mechanisms because of the inefficient baseline presentation of poorly edited, low-abundance self-peptides presented by the MHCII risk alleles; higher autoantigen doses in injured islets and pancreatic lymph nodes may overcome this defect during the initiation of autoimmunity. Moreover, inefficient self-antigen presentation in the context of T1D risk alleles may impair the generation and maintenance of Treg's that dampen autoimmunity.
Outstanding research questions
Broader conclusions emerge from these studies. The first and foremost link between the MHCII alleles and immune pathology is the fact that disease-related polymorphisms enable the presentation of peptides that are derived from otherwise innocuous self- or nonself-antigens (gliadins in CD, islet proteins in T1D) and activate pathogenic effector T cells. This alone does not, however, provide a mechanism for the MHCII association with disease, because it leaves unexplained why tolerance to these self-peptides fails, and why other MHCII alleles are not permissive for presentation of disease-related peptides. In CD, at least, the link of risk-associated polymorphisms with pathogenesis is much stronger: specific covalent modifications of gluten-derived peptides are required to enable selective binding to precisely those risk alleles. The modified peptides are unlikely to be presented consistently or efficiently in the thymus or in peripheral APCs at baseline, providing a mechanism for the lack of T-cell tolerance. A very similar paradigm has emerged recently in rheumatoid arthritis, where it is thought that modification of Arg to citrulline by peptidyl arginine deiminases at sites of inflammation might generate neo-self-determinants with greatly enhanced ability to bind to the disease-associated HLA-DR alleles (reviewed in Ref. Reference Klareskog148). Much remains to be learned, however, about the events that lead to the pathogenic convergence of antigen modification and antigen presentation in vivo.
A second principle is that altered interactions with peptide loading cofactors are relevant to the presentation of neo-self-determinants by MHCII risk alleles. In the CD example, DQ2.5 is permissive for gliadin peptide presentation because of its capacity for some spontaneous CLIP release, poor editing of the peptide repertoire by DM and its ability to retain un-edited peptides via hydrogen bond networks. Importantly, these features can be attributed to specific polymorphisms that distinguish DQ2.5 from nonsusceptibility alleles with similar peptide-binding specificity. The role of peptide editing merits further study in other autoimmune diseases. For example, in rheumatoid arthritis, some genetic evidence suggests contributions of presentation cofactors DM and its inhibitor DO to pathogenesis (Refs Reference Lee149, Reference Louis-Plence150, Reference Toussirot151).
In T1D, there is now a good understanding of the general rules for determinant selection by the risk alleles. In addition, several interrelated biochemical defects of the disease-associated DQ alleles and their murine Ag7 homologue have been identified. Nonetheless, our understanding of mechanisms and causation remains incomplete. We do not know whether, in T1D, the MHCII risk alleles are unique in their ability to present islet autoantigens, rather than merely being permissive for their presentation. Meanwhile, there is evidence in mice for increased self-reactivity of CD4+ T cells, which is associated with homozygous expression of Ag7, and for escape of pathogenic, self-reactive TCRs from negative selection. We propose that biochemical features of Ag7 and DQ risk alleles contribute to generalised perturbations in the thymic development and peripheral homeostasis or regulation of CD4+ T cells, which raise the propensity towards autoimmunity.
Several broad questions remain. Which of the several interrelated biochemical defects of the T1D risk alleles are present in vivo, shared between species and relevant to pathogenesis. How might their contributions to T-cell dysregulation be disentangled? Which of several possible homeostatic or regulatory mechanisms in T cells are disrupted by Ag7? How do other MHCII alleles confer dominant protection in this system? Future studies will capitalise on our increasing ability to manipulate interactions of non-Aspβ57 alleles with peptide loading cofactors. Advances in our ability to quantify homeostatic abnormalities in vivo, through the measurement of protein turnover and cellular homeostasis by stable isotope techniques (Refs Reference De Riva152, Reference Busch153, Reference Busch154), will also be helpful.
MHCII associations with immune pathology were first recognised over 30 years ago, but this has not led to successful therapies. However, recent work, reviewed here, has shown that MHCII risk alleles may present neo-determinants to effector CD4+ T cells and contribute to T-cell dysregulation, both of which might be amenable to manipulation in established, chronic disease. This has revived prospects that further insights into these mechanisms will not only fill our considerable gaps in understanding of genotype/phenotype relationships in complex autoimmune diseases, but could also, at long last, lead to novel therapies.
Acknowledgements and funding
E.D.M. and R.B. thank the current and past members of their laboratories for the work that contributed to the ideas synthesised in this review. R.B. and A.D.R. are funded by a Senior Research Fellowship from Arthritis Research UK (grant number 18543). T.H., W.J. and E.D.M are funded by the National Institutes of Health (grant numbers AI089080, AR061297, AI095813), by the Stanford NIH/NCRR CTSA (UL1 RR025744) and by the Lucile Packard Foundation for Children's Health.