


I. INTRODUCTION
Epidemiology is the study of the distribution and determinants of disease frequency in human populations.Footnote 1 The field is a pioneer among the health sciences, uncovering diseases and causes of disease that were previously unknown.Footnote 2 And as the discipline discovers yet more things that are bad for us, it is not surprising that people should try to sue each other in respect of some of them. Because of its pioneering characteristics, epidemiological evidence is sometimes important—or even the only—evidence available to prove that the wrong sued for caused the harm suffered. For example, to most minds, the epidemiological evidence for a general or population-level causal link between smoking and lung cancer is convincing. Medical technology is not available, however, to tell whether smoking caused a particular individual's lung cancer—what I will refer to as specific causation. Yet for a claim to succeed in the relevant torts, especially negligence, this is exactly what must be proved. Situations therefore arise in which plaintiffs seek to rely wholly or partly on epidemiological evidence to prove specific causation. This raises a difficult question, namely: Can epidemiological evidence prove or assist in proving specific causation? If not, why not; and if so, how?
This question is difficult because it raises legal and philosophical issues that can be properly addressed only with an understanding of the epidemiological concepts usually involved in this sort of evidence. This paper is an effort to disentangle the underlying conceptual issues in a way that enables the expression of a clear and rational legal position. Section II therefore lays out the relevant epidemiological concepts. Section III summarizes various legal attitudes toward the use of epidemiological evidence to prove specific causation. Section VI criticizes the rationale that has been offered for the use of epidemiological evidence to estimate the probability of specific causation and makes an alternative proposal. Section v. considers in-principle epistemic objections to the use of epidemiological evidence on the grounds that only “particularistic” evidence is relevant to determine whether an actual event has happened and generally whether there is an important difference between an “epistemic” probability that an event actually happened and a “statistical” probability that an event like that will or would happen. Section VI considers further justice-based objections to the use of epidemiological evidence, and Section VII concludes.
This paper is concerned with the significance of epidemiological evidence for specific causation. My concern is with what epidemiological evidence says about specific causation at the expense of all other issues connected with epidemiological evidence and scientific evidence more generally. That is artificial from both a legal and a philosophical perspective. Courts of law face many problems assessing epidemiological and other scientific evidence. Epistemologically, the question that I focus on is just one of many that may be asked about epidemiological evidence. Susan Haack emphasizes correctly that like other kinds of evidence, epidemiological evidence must be weighed against all other relevant evidence.Footnote 3 She cites this fact in support of the claim that epidemiological evidence is never sufficient to establish specific causation. However, this does not follow: the epidemiological evidence might be all we have to prove causation, in which case the requirement to consider all available evidence will be satisfied by considering the epidemiological evidence.
Haack's argument, important though it is, obscures an even more important question, the one lying at the heart of the convoluted literature on this topic namely: What does epidemiological evidence say about specific causation? My question is not how to tell whether epidemiological evidence is scientifically respectable or how it should be weighed against other kinds of evidence. Rather, I ask: What follows for specific causation from accepting a piece of epidemiological evidence concerning a general causal link between a wrong and a harm? I focus on what follows epistemically, with a view to saying what ought to follow legally, given existing the existing law on negligence within common-law jurisdictions.
What follows, I conclude, is that epidemiological evidence is relevant to the proof of specific causation. Epidemiological evidence says that a particular exposure causes a particular harm within a certain population. Importantly, it quantifies: it says how often the exposure causes the harm. However, its methods are limited: they measure only the net effect of the exposure, leaving open the possibility that the exposure is causing more harm than the epidemiological evidence suggests—but ruling out the possibility that it causes less. Accordingly I suggest that epidemiological evidence can be used to estimate a lower bound on the probability of causation but that no epidemiological measure can be required. Thus a relative risk (RR, defined in Section II) of greater than 2 can be used to prove causation when there is no other evidence; but RR < 2 does not disprove causation. Given high-quality epidemiological evidence, RR > 2 is sufficient for proof of specific causation when no other evidence is available but not necessary when other evidence is available.
This, I argue, is the significance of epidemiological evidence. When there is other evidence, the epidemiological evidence is to be fed into the overall evidential assessment process. My emphasis on the scenario in which there is only epidemiological evidence is not to be misread as a claim that epidemiological evidence is determinative—that it closes the causal inquiry, that RR < 2 can defeat evidence that the plaintiff was particularly at risk, or anything of the kind.
There are two serious mistakes in judicial and academic literature on this topic. The first is that RR > 2 is necessary for proof of specific causation. The second is that epidemiological evidence is never sufficient for proof of specific causation: that no matter how strong the evidence for a general causal link between a wrong and a harm, we are never thereby warranted in deciding that a particular plaintiff's harm was caused by the wrong. Probably the injustices to which the former idea has given rise have motivated some well-intentioned endorsements of the latter. Whatever the case, these are both serious errors. They are both demonstrably wrong epistemically and they are both demonstrably at odds with the general law of negligence. Both errors have led to injustices, and in particular, both have afforded successful defenses to large corporations against individuals who have, more likely than not, been harmed by their activities. My aim is to correct both these errors.
II. KEY EPIDEMIOLOGICAL CONCEPTS
Two epidemiological measures are particularly important in this context, and although they are related, they must be distinguished. They are relative risk (RR) and attributable fraction (AF, also known as attributable risk). RR is a measure of how much more common a given condition is among people who are subject to a given exposure than among those who are not.Footnote 4 It is calculated as follows:
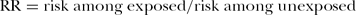
A couple of points about RR must be emphasized. First, it is crucial to realize that “risk” in this context means nothing more than incidence over a specified time interval.Footnote 5 It does not denote the product of the probability that a harm will occur and the gravity of that harm; in fact it does not even denote a probability, strictly speaking, without ancillary assumptions about the nature of probability. It is a purely statistical measure of the relative frequency with which a disease occurs in exposed and unexposed populations.
Second, although RR can be used to measure effect size, the mere performance of the above calculation has no intrinsic significance for causal inference; this calculation does not by itself amount to a causal inference. This follows from the previous point that “risk” in this usage denotes a purely statistical measure.Footnote 6 Thus before a figure for RR can be (reasonably) appealed to in support of specific causation, it must be backed by a sound causal inference at the general level. Courts often need to assess general-level inferences of this kind.Footnote 7 In particular it must be established that the RR is not due to anything other than the exposure—that there are no uncontrolled confounders and no artifacts arising from the manner in which subjects were selected and classified as exposed or diseased.Footnote 8 Even if there are independent grounds for supposing there is some causal link between exposure and harm, accounting for these potential sources of a false causal inference is necessary for the RR to be rationally understood as saying anything about that link.
The principles governing general causal inference are not the topic of this paper.Footnote 9 So henceforth it is assumed that all the RRs we discuss are backed by sound causal inferences and in particular that the possibility of confounding, misclassification, and other problems have been adequately addressed, so that the court accepts that the difference that the RR expresses between risk among exposed and unexposed is explained—caused—solely by the exposure.Footnote 10
An example: suppose (roughly correctly) that 15 percent of British male smokers get lung cancer, whereas 1.5 percent of British male nonsmokers do. Then RR = 15% / 1.5% = 10. This tells us that lung cancer is ten times as common among British male smokers than British male nonsmokers. If this RR is used to prove specific causation, it must first be accepted that the causal explanation for this difference is smoking.
The other epidemiological concept that is important in this context is AF. This is the proportion of a disease burden within a population that is “attributable” to a given exposure. Before we address the scare quotes, let us set out the calculation:
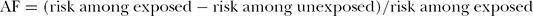
So in our smoking example, the fraction of lung cancer attributable to smoking would be (15% − 1.5%) / 15% = 0.9, or 90%, which is to say that that 90 percent of cases of lung cancer among smokers are “attributable” to smoking.
The word “attributable” is not transparent. First, AF (like RR) is a statistical measure only; it can be used to express information about a causal link, but the mere possibility of performing the calculation is no proof of causation, and merely performing the calculation is no replacement for a causal inference.
Second, even where a causal inference to explain the AF is warranted, the word “attributable” is potentially misleading, as Greenland and others point out. These authors advocate a distinction between excess and etiological fraction.Footnote 11 AF as I am describing it is excess fraction, in the sense that it tells us how many excess cases there are among the exposed group (as a fraction of the total number of cases in that group). Granted a sound causal inference, we can infer that all the excess cases are caused by the exposure. But we cannot infer that the remaining cases are not caused by the exposure. The etiologic fraction—the cases in which the exposure makes a causal contribution—could be larger. Roughly speaking, this is because, in the absence of substantive biological assumptions, it is possible that the exposure could contribute to cases that would have occurredFootnote 12 even without the exposure.Footnote 13 For example, it might be that smoking is a cause of lung cancer even among some of those who would have developed it anyway. The fact that a person would have developed lung cancer anyway does not offer automatic protection against the carcinogenic effects of cigarette smoke (a point we return to in Section IV). We cannot assume, without supporting biological evidence, that when an exposure is among the causes of a case of a disease, background factors are thereby excluded from also being causes of that case.Footnote 14 Thus when I use AF, I mean excess fraction; there is no way to calculate etiologic fraction from empirical data without supplementary assumptions.Footnote 15
The considerations of the preceding paragraph are so widely ignored in the judicial treatment of epidemiological evidence that I do not think I have seen them discussed judicially at all. Yet, as I argue below, they are central to the correct usage of epidemiological evidence in proving specific causation because they give rise to an epistemic asymmetry between proof and disproof that, as far as I am aware, is also without clear and explicit judicial recognition.Footnote 16
Before moving to discuss the uses that are made of these measures, it is important to appreciate that both RR and AF are specific to populations. This is obvious for AF, because a fraction must be a fraction of something, and a diseased population is the obvious candidate. But it is easy to slip into thinking of RR as a property of an exposure-disease pair without specifying the exposed and unexposed populations that the RR compares.Footnote 17 In fact, RR (like AF) is a function of exposure, disease, and population. To see why, recall that I do not specify an age range for the (fictitious) RR associated with smoking among British males. Suppose we select an age range of fourteen to eighteen. If RR was close to 1 in that group, that would not show that smoking does not cause lung cancer. The likeliest explanation would be that few teenagers get lung cancer regardless of whether they smoke.Footnote 18 It follows that there is no such thing as the RR of lung cancer for smoking, independent of the specification of an exposed populationFootnote 19 and an unexposed population that is suitable to act as a control.Footnote 20
Finally, it is evident that RR and AF are related, as they can be calculated from the same data. The formula for calculating AF from RR (as they are defined here) is:Footnote 21
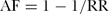
This calculation is significant for our purposes because it has sometimes been used in legal contexts to calculate the probability of specific causation from epidemiological data, that probability being equated to AF.Footnote 22 For example, some courts would use our cigarette data to calculate a probability that a particular British male smoker's lung cancer was caused by smoking at 0.9. Coupled with an assumption to the effect that the appropriate standard of proof can be represented by a probability of > 0.5, this would yield the consequence that specific causation was proved; whereas RR of 2 or less would yield a probability of 0.5 or less, meaning causation was not proved. The equation of AF with probability of causation, as defined here, has been heavily criticized, and rightly so, by epidemiologists such as Greenland. We consider these criticisms in Section IV. The auxiliary assumption concerning the standard of proof and, more generally, the relevance of this kind of evidence for proving specific causation are also heavily criticized, this time by legal scholars. We consider some of these criticisms in Sections V and VI. But first let us consider some of the ways that courts in England, Scotland, and the United States have handled attempts to prove specific causation using epidemiological evidence.
III. LEGAL ATTITUDES TO EPIDEMIOLOGICAL EVIDENCE
It is possible to distil three main attitudes toward the use of epidemiological evidence in proof of specific causation out of the rather convoluted jurisprudence and commentary on the topic:
• that epidemiological evidence is irrelevant to proof of specific causation;
• that where only epidemiological evidence is available, normal causation rules may sometimes be relaxed, so increase in risk can satisfy the causation element; and
• that the threshold for proof of specific causation using epidemiological evidence is RR > 2.
These attitudes are not mutually exclusive. The increased-risk approach might be motivated partly by the view that epidemiological evidence is strictly irrelevant; and the view that RR > 2 is the threshold for proof is also compatible with allowing proof of increased risk where RR ≤ 2 but policy considerations suggest that the claimant should succeed. Let us examine each in turn.
A. Epidemiological Evidence Is Irrelevant to Proof of Specific Causation
This view has received frequent statements. For example, Michael Dore writes, “Epidemiological evidence, like other generalized evidence, deals with categories of occurrences rather than particular individual occurrences. . . . Such evidence may help demonstrate that a particular event occurred, but only when accompanied by more specific evidence.”Footnote 23 Again, Melissa Moore Thomson claims, “statistic-based epidemiological study results should not be applied directly to establish the likelihood of causation in an individual plaintiff.”Footnote 24 And Andrew See (writing in the Defence Counsel Journal) asserts, “Epidemiology studies are relevant only to the issue of general causation and cannot establish whether an exposure or factor caused disease or injury in a specific individual.”Footnote 25
But perhaps the most striking statement of this position occurs in the Scottish case of McTear v. Imperial Tobacco Ltd.Footnote 26 Lord Nimmo Smith felt unable to conclude on the basis of the evidence before him that even the general causal link between smoking and lung cancer was proven, even though the Scottish Parliament was at that time legislating on the basis of this evidence.Footnote 27 But he went on to say that even if he had, he would not have considered this evidence to be relevant to specific causation, despite AF = 90%, or RR = 10 (as in our example):
epidemiological evidence cannot be used to make statements about individual causation. . . . Epidemiology cannot provide information on the likelihood that an exposure produced an individual's condition. The population attributable risk is a measure for populations only and does not imply a likelihood of disease occurrence within an individual, contingent upon that individual's exposure.Footnote 28
These assertions are apparently grounded on the fact that epidemiological studies and the measures they produce, such as RR and AF, apply only to populations and not individuals. But this is a non sequitur, most dramatically obvious in the case where the population-level claim in question is a universal generalization. Suppose all epidemiologists smoke: this is a fact about a population. Suppose also that Richard is an epidemiologist. It follows that Richard smokes. This counterexample is not realistic, but it proves that it simply does not follow that, because epidemiology measures properties of populations, it says nothing about individuals. Populations are composed of individuals. For this reason, it is at least sometimes possible to conclude something about an individual on the basis of a fact about a population of which the individual is a member. The part-whole relation can be a reliable guide to inference.
Of course, epidemiology rarely, if ever, pronounces a trait to be universal among a population. Thus modus ponens will not, in general, be available. Nevertheless, the idea that epidemiological evidence is always and in all ways irrelevant to individuals is clearly mistaken for more realistic examples too. At risk of laboring a point that ought to be obvious, note that if this consideration were decisive, then the smoker who gives up smoking in order to avoid lung cancer on the strength of an epidemiological study would be acting irrationally. The study applies to populations and so, on the view I am criticizing, “does not imply a likelihood of disease occurrence within an individual, contingent upon that individual's exposure.”Footnote 29 Yet quitting is a sensible, not an irrational, move for a smoker wishing to avoid lung cancer. If one knows that smokers develop lung cancer ten times as often as nonsmokers, and moreover that this is because smoking causes lung cancer, and if one has no further information as to whether one will suffer lung cancer either as a smoker or a nonsmoker, then quitting smoking is clearly a good—though not fail-safe—strategy for avoiding lung cancer.
This reasoning uses epidemiological data concerning populations to make an individual decision about “a likelihood of disease occurrence within an individual, contingent upon that individual's exposure.”Footnote 30 If this reasoning is good, that shows that the mere fact that epidemiological studies and measures concern populations does not mean that they are wholly irrelevant to causation in individuals.Footnote 31 And if this reasoning is bad, then we must condemn a great deal more than the proposed use of epidemiological studies. This rationale would require individuals to ignore great swathes of advice, not only on health, but also on nutrition, house prices, what precautions to take with regard to personal safety in a particular area of the city, and the prospects of survival upon leaping from a third-story window.
Any such claim doubting the relevance of epidemiological evidence on the basis that it concerns populations must be more sophisticated, therefore. It must argue that the sort of claims that epidemiology makes about populations are unsuited to supporting the sort of claims that need proving at law. A more sophisticated defense of the irrelevance position is offered by Richard Wright, who distinguishes ex ante and ex post probabilities.Footnote 32 He allows that epidemiological evidence is relevant to individuals assessing the ex ante probability of some event, that is, the probability that it will happen before it has (or has not), but not the ex post probability, that is, the probability that it did happen. And it is the latter probability that is at issue in proving specific causation, Wright claims. So the smoker who uses epidemiological evidence to assess the probability that he will get lung cancer is using that evidence correctly. It does tell him how likely he is to get lung cancer, and by extension it may be informative as to how likely it is that smoking will cause lung cancer. However, when the smoker goes on to contract lung cancer, epidemiological evidence does bear on whether smoking did cause his lung cancer. Epidemiological evidence is informative on the former but not the latter point, Wright claims, and the latter is what must be proved to establish specific causation.
We assess this argument in more detail in Section V; suffice it to note here that it is the only plausible version of the irrelevance stance.
B. Where Only Epidemiological Evidence Is Available, Normal Causation Rules Should Be Relaxed so that Proof of Increased Risk Suffices
There is relatively little discussion of epidemiological evidence in English law, and one reason for that is the development of a rather pragmatic exception to the normal rules of proof of causation, made explicit in Fairchild v. Glenhaven Funeral Services.Footnote 33 Although this exception was not motivated by concerns about epidemiological evidence, it is potentially applicable in cases where epidemiological evidence is at stake. In Fairchild it was held that mesothelioma sufferers did not have to prove which exposure to asbestos caused their mesothelioma. The exception is explicitly policy based.Footnote 34 The injustice it is meant to correct arises because, as Lord Hoffmann puts it, “a rule requiring proof of a [causal] link between the defendant's asbestos and the claimant's disease would, with the arbitrary exception of single-employer cases, empty the duty [to protect employees from exposure to asbestos] of content.”Footnote 35
Although the discussion does not explicitly concern epidemiological evidence, the approach clearly could be extended to cases where proof of causation is attempted by epidemiological evidence. Just as multiple employment empties a duty of content, so, it might be argued, the fact that a disease occurs even without an exposure empties the duty not to expose others to a known agent of that disease of content. This connection was made by the Court of Appeal in Sienkiewicz v. Greif Ltd.,Footnote 36 where there was a nontortious exposure to asbestos arising from background levels in the claimant's town. The judges in that case concluded, unsurprisingly, that background exposure to the same agent should not relieve a defendant of liability (and this was confirmed by the Supreme Court).Footnote 37 And it is hard to see why background exposure to some different agent of the same disease should be handled any differently, in the absence—as we are supposing—of a diagnostic test to distinguish the different kinds of causes.
Accordingly one might maintain that when epidemiological evidence suggests that a tortfeasor has materially increased the risk of a harm to a claimant, but the claimant cannot prove a causal link in her particular case, the claimant may succeed, provided that there are good policy grounds for allowing this. This position is compatible with a dim view of epidemiological evidence in general, such that it can never prove causation; or, on a positive view of epidemiological evidence, this position might be reserved for those situations where the evidence is insufficient (e.g., where RR ≤ 2, as discussed later in this section).
Strictly, there are two ways to understand the significance of increased risk. One is, as I present it above, as a relaxation of the usual rules for proving causation so that in certain circumstances, proof of materially increased risk is allowed to suffice for proof of the causation element.Footnote 38 The other is the view that increased risk amounts to a compensable harm of its own: a new tort. This view appears to be endorsed in Sienkiewicz.Footnote 39
It is not my present concern to refute the increased-risk approach. Some version of it may be unavoidable, for policy reasons, in at least some cases. Nevertheless the approach clearly needs to be confined. This is because each of the interpretations just offered has its drawbacks.
Regarding the first, as Wright points out, it is clearly fallacious to equate causing harm with increased risk of that harm, because the risk of a harm is not identical with that harmFootnote 40—even if the risk is also a harm.Footnote 41 This follows from the fact that the one may occur without the other.Footnote 42 Treating increased risk (even materially increased risk) as a relaxed test for causation collapses the distinction between increasing the risk of a harm and causing that same harm, because it allows compensation for the latter on proof of the former. That is objectionable in a number of ways.Footnote 43
First, it is prima facie unjust to hold a person to account as if a set of facts has been proved when it has not. Second, even if there may be circumstances defeating this prima facie injustice, these must be specified if conceptual rigor is to be preserved. Conceptual rigor matters for consistency, predictability, and transparency. The mere fact that a law yields an undesirable outcome does not provide a legal justification for pretending that elements of liability have been proved when they have not. If the court were to adjust at will its view of what satisfies an element of liability, depending on the overall outcome it regards as desirable, then it is hard to see what point would remain in breaking down liability into elements, as the outcome regarding each element would depend on the overall outcome, and not vice versa. Therefore, if exceptions to proof of elements of liability are allowed, they must be clearly confined in scope. Third, even if exceptions are clearly confined, they remain prima facie undesirable because of the element of pretence involved. It is better, if possible, to hold people liable only for what they have been proved to be liable for. Complete consistency in this sense may be an impossible goal, but it is a goal nonetheless; hence the equation of increased risk with causation must be a last resort.
In Sections IV to VI I argue that epidemiological evidence does not always require one to resort to an increased-risk test.Footnote 44
The increased-risk approach might also be interpreted as creating a new tort. In earlier work, Wright also endorses a version of the view that increased risk is a legally cognizable wrong,Footnote 45 but in later work he acknowledges the conceptual difficulties of this approach. In particular, if the compensable wrong is creating a risk, then it is unclear why compensation should be awarded only when the harm that the risk is a risk of eventuates.Footnote 46
Nevertheless the approach does have advocates. The majority in Barker is clear that the head of damage compensated for in that case is increased risk. Chris Miller endorses this interpretation and defends it:
. . .it is hard to see injury and its expectation value as “distinct” concepts. By confining attention (and liability) strictly to eventuated risks, the risk and the injury, although distinguishable concepts, remain intimately tied together. By analogy: I have a body and that body has weight; they are separate but closely related concepts, but it is not meaningful to speak of my body weight as being something distinct from my body.Footnote 47
The trouble with this distinction between eventuated and uneventuated risks is, again, that the difference between them seems to be whether the risked harm has occurred. We might ask when the compensable risk arises. If it is intimately bound up with the harm, then presumably it comes into being when the harm does, just as body weight comes into being when the body does.Footnote 48 But risks usually come into being before the harm risked. It might be argued that the risk that is compensated for is a different one from the antecedent risk of an event, and that the risk compensated for is a special one that occurs only when the harm is eventuated. But that stretches the normal notion of risk beyond recognition. Assuming, then, that a risk usually exists (or starts existing) before the eventuation of the harm that is risked, the two are both conceptually and empirically distinguishable. We must again face the question as to why the risk is treated as a compensable harm only when a different harm—the harm that the risk is a risk of—occurs.Footnote 49
None of this is meant to be a decisive rejection of the increased-risk approach. It may be that in some cases, justice requires that increased risk be allowed either to satisfy the causation element of liability or as a legally cognizable harm. It may also be that the just outcome in some cases of uncertainty appears to be some form of apportionment among defendants; or the just outcome may be thought to be a partial award to all claimants in recognition of the fact that only some of their harms are compensable and the evidence does not tell us which. The increased-risk approach would lend itself to achieving outcomes such as these.
The preceding discussion does not concern the desirability of these outcomes. The point is just that, justified or not, the increased-risk approach is conceptually difficult, whether as a relaxed test for causation or a legally cognizable harm. The increased-risk approach will always be less satisfactory than proving a causal link because it amounts to either a pretence or a very odd kind of liability. It is not an improvement on the usual approaches to causation; it is a solution of last resort, which we should not and in practice do not fall back on where causation is easily settled. Therefore even if the increased-risk approach is allowed to stand, it is necessary to understand the significance of epidemiological evidence in order to identify those cases where the danger of emptying a duty of content truly arises.Footnote 50
C. Epidemiological Evidence Can Prove Specific Causation, and the Threshold for Proof is RR > 2
When courts and commentators accept that epidemiological evidence is relevant to proof of specific causation, they usually take the threshold for proof of causation to be RR > 2. This is the view of English courts when they are not worrying about the Fairchild exception. In XYZ & Others v. Schering Health Care Ltd.,Footnote 51 the claimants accepted that proving RR > 2 was necessary for their claim to succeed, given the absence of other evidence, and Mr. Justice Mackay approved.Footnote 52 The judge found the most likely figure for RR to be 1.7 and therefore that the case must fail regardless of whether general causation was established.Footnote 53 It is, of course, possible that a case such as this would now activate the Fairchild exception, in which case merely showing any material increase in risk would suffice; but the case presumably remains authoritative where the policy considerations governing the Fairchild exception are not activated.
On the other hand, in Novartis Grimsby Ltd. v. Cookson,Footnote 54 causation was successfully established using RR > 2. Per Lady Justice Smith:
Put in terms of risk, the occupational exposure had more than doubled the risk [of the bladder cancer complained of] due to smoking. . . . if the correct test for causation in a case such as this is the “but for” test and nothing less will do, that test is plainly satisfied on the facts as found. . . . In terms of risk, if the occupational exposure more than doubles the risk due to smoking, it must, as a matter of logic, be probable that the disease was caused by the former.Footnote 55
Lady Justice Smith was in fact making two claims here. First she was claiming that the but-for test is satisfied when an exposure more than doubles the risk of a harm. Second she was claiming that causation is proved when an exposure doubles the risk of a harm.
It is important to distinguish the but-for test from the causation it is supposed to test for, because the but-for test is subject to some well-known criticisms.Footnote 56 Clearly it is the second proposition—that causation can be proved—that is of primary importance. Satisfying the but-for test is of instrumental value at most. The second proposition was confirmed, also by Lady Justice Smith, when Sienkiewicz was at the Court of Appeal:
In my view, it must now be taken that, saving the expression of a different view by the Supreme Court, in a case of multiple potential causes, a claimant can demonstrate causation in a case by showing that the tortious exposure has at least doubled the risk arising from the non-tortious cause or causes.Footnote 57
At the Supreme Court, however, a different opinion was indeed expressed. In fact, several different opinions were expressed, coalescing on a general but vague suspicion of epidemiological evidence in proof of specific causation.
Lord Philips came closest to endorsing the probative sufficiency of epidemiological evidence for specific causation:
Where there are competing alternative, rather than cumulative, potential causes of a disease or injury, such as in Hotson, I can see no reason in principle why epidemiological reason should not be used to show that one of the causes was more than twice as likely as all the others put together to have caused the disease or injury.Footnote 58
Lord Rodger disagreed, however, holding that statistical evidence can prove a probability of causation but not the fact that causation occurred in this specific case.Footnote 59 Baroness Hale fell somewhere in between, inclining toward Lord Phillips in principle in the view that statistical evidence cannot simply be regarded as irrelevant to fact-finding but worrying that judges “mix” statistical evidence wrongly with other kinds of evidence in determining their final finding;Footnote 60 thus she directed that “it would be wrong for judges to change their fact-finding behaviour because of anything said in this case.”Footnote 61 Logically this would leave Lady Justice Smith's remark untouched, but it hardly amounts to a ringing endorsement. Lord Brown did not discuss epidemiological evidence. Lord Mance was reluctant to place too much weight on epidemiological evidence because “the law is concerned with the rights and wrongs of an individual situation, and should not treat people and even companies as statistics,”Footnote 62 although he identified as common ground the view that epidemiological evidence can be used “in conjunction with specific evidence.”Footnote 63 Perhaps it is common ground because it is so ambiguous: on a minimal reading, evidence that the plaintiff was exposed to the harmful substance would satisfy this requirement, yet this would not be enough for those who oppose this use of epidemiological evidence.
Lord Kerr held that there must be “evidence connecting avowedly relevant statistical information produced by the epidemiological studies to the facts of the case,”Footnote 64 but again, he did not tell us what that evidence might be. And Lord Dyson concluded that epidemiological evidence cannot prove causation, only probability of causation, and that whether epidemiological evidence should be allowed in legal proof of causation is a matter of policy.Footnote 65 This is a gamut of claims, centering on a general skepticism—with the exception of Lord Philips—about the use of epidemiological evidence for direct, sufficient, or sole proof of causation without some legal adjustment. I reject most of these claims below.
The attitude of American courts is even more complex.Footnote 66 In particular, there was a discussion following Daubert v. Merrell Dow Pharmaceuticals, Inc.,Footnote 67 as to whether RR > 2 was required for epidemiological evidence to be admitted.Footnote 68 Although the question of admissibility (especially where a jury is concerned) is distinct from the question of probative value, the two are clearly related here. The putative link, presumably, would be that a fact finder could not legitimately—and therefore should not be permitted to—base a finding that an exposure caused a harm on epidemiological evidence when RR ≤ 2. But this reasoning is invalid for scientific reasons, as we see in the next section.
When epidemiological evidence is admitted, the advice of the Reference Manual on Scientific Evidence produced by the Federal Judicial Center is that causation may be proved when RR > 2 and that RR ≤ 2 is insufficient to prove causation.Footnote 69 The Manual is careful to point out—correctly—that the overall probability assigned to causation may differ from that suggested by the epidemiological evidence when further evidence specific to the individual plaintiff is factored in.Footnote 70
What is the significance of RR > 2? We must assess the evidence for the claim that RR > 2, of course, and whether it is backed by a causal inference at the general level (whether it is causally explained). And we must remember, of course, that whatever it says, it must be weighed against other evidence. But assuming these requirements are satisfied, what, if anything, does RR > 2 say about specific causation? Despite the frequency with which the figure is mentioned, I have found no explication that is at once clear and correct. The next section is an attempt to get clear on exactly what epidemiological evidence says about specific causation, assuming it says anything at all. Sections V and VI ask whether indeed it does say anything at all that is epistemically and legally relevant to proof of specific causation, answering the irrelevance attitude discussed previously in this section.
IV. THE SIGNIFICANCE OF RR > 2
The Reference Manual on Scientific Evidence attempts to explain the significance of RR > 2 as follows:
Recall that a relative risk of 1.0 means that the agent has no effect on the incidence of disease. When the relative risk reaches 2.0, the agent is responsible for an equal number of cases of disease as all other background causes. Thus, a relative risk of 2.0 . . . implies a 50% likelihood that an exposed individual's disease was caused by the agent. A relative risk greater than 2.0 would permit an inference that an individual plaintiff's disease was more likely than not caused by the implicated agent.Footnote 71
The Manual goes on to put the same test in terms of AF > 50%: “When the attributable risk exceeds 50% (equivalent to a relative risk greater than 2.0), this logically might lead one to believe that the agent was more likely than not the cause of the plaintiff's disease.”Footnote 72
This reasoning equates the probability of causation (PC) with AF, which in turn is related to RR, as shown in Section II, implying that:
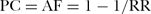
According to this formula, sometimes known as the probability of causation (PC) formula, when RR = 1, PC = 0; and when RR reaches 2, PC will reach 50 percent.Footnote 73
There are two problems with the reasoning cited in the Reference Manual. First, it is unclearly stated. Second, it is fallacious.
Regarding clarity, even if we accept the premise that RR = 1 means no effect (strictly speaking a false premise, as we shall see), we are given no reason for thinking that when RR reaches 2, there is a 50 percent probability that the exposure caused the disease. The word “Thus” at the start of the third sentence cited in that passage does not constitute a reason. Similarly, we are given no reason for thinking that AF = 50% implies a probability of causation of 50 percent (and the word “logically” does not amount to a reason). These are non sequiturs. The same lack of clarity infects most statements both judicial and extrajudicial.Footnote 74
Presumably, the reasoning is that when AF = 50%, and a general causal inference has been accepted, then 50 percent of the cases in the exposed population are caused by the exposure. And therefore the chance that the exposure is a cause of a case of the disease randomly selected from the exposed population of sufferers exceeds 50 percent when AF exceeds 50 percent (and RR > 2). The remaining assumption is that claimants are randomly selected with respect to the epidemiological evidence.
But the reasoning just cited is fallacious, exemplifying a common error. The error is evident from the discussion in Section II. As pointed out there, AF as it is being used in these passages is a statistical measure referring to excess fraction—the excess cases (as a proportion of the total cases in the exposed group) that occur in the exposed group, as compared to the unexposed. It is possible for the etiologic fraction—the fraction of cases caused by the exposure—to be larger, perhaps much larger.Footnote 75 Therefore it does not follow from an AF of 50 percent that 50 percent of the cases in the exposed group are caused by the exposure, even assuming—as we are—that the exposure causally explains the AF and thus that the general causation issue has been settled.
Moreover, the formula relating AF and RR (AF = 1 − 1/RR) holds only when AF is understood as an excess, not etiologic, fraction. Therefore, contrary to what is asserted in the passage cited from the Manual, RR = 1 (or AF = 50%) does not mean that the agent is not causing the disease in the population in question. It implies only that the agent has no net effect on the incidence of the disease—no net effect on the number of new cases in the time period that these figures concern. RR = 1 means no net effect, but no net effect does not mean no effect. By the same token, RR = 2 does not imply a 50 percent likelihood of individual causation. It implies only that the exposure gives rise to a net excess in the proportion of cases in the exposed population compared to the unexposed population that is equal to 50 percent of the total cases in the exposed population.Footnote 76
This might look like a purely theoretical objection. But it is not. The PC formula relies on substantive biological assumptions that are often violated.Footnote 77 Most obviously, it assumes that the exposure is not a cause of the disease among that proportion of cases that you would expect to find in an unexposed population. This is flagrantly ridiculous in many cases. Consider, for example, a fictitious group of Himalayan porters. One might imagine that carrying heavy loads up and down mountains increases their risk of back injury. Among those porters suffering back injury will be some who for anatomical reasons would have developed a back injury anyway. But having a weak back does not protect these porters from the effects of carrying heavy loads. On the contrary, it is quite possible that carrying a heavy load will be a cause of back injury among many or even all those porters whose backs were such that they would have developed a back injury even in a less physically demanding profession. Endorsing the PC formula amounts to endorsing the astonishing view that a person who would develop a disease without the exposure in question is thereby protected from the effects of that exposure: that having a weak back will protect a Himalayan porter from the harm that carrying a heavy load would otherwise do to his back. It does not take any great conceptual sophistication to see that this is an error.
In a series of articles, Greenland provides a number of examples of ways that the PC formula can underestimate the probability of causation. An exposure might accelerate a disease so that those who are at risk die before featuring in the study.Footnote 78 An exposure might cause the disease in some and prevent it in others, which will not show up in RR or AF, as these are measures of net impact.Footnote 79 In short, when epidemiological studies indicate that RR > 1 and that this is to be explained causally, that does not settle the question as to what proportion of the exposed cases is due to the exposure.
There is, however, an asymmetry here. Although RR and AF can massively underestimate the probability of specific causation, they cannot overestimate it, assuming—as we are—that the general causation issue has been settled (and that our inquiry is prior to, feeds into, and does not replace a weighing of all the relevant evidence). This is because to settle the general causation issue, it is necessary to infer that the difference between the exposed and unexposed groups is not due to some defect in the comparison (e.g., uncontrolled confounders; misclassification of subjects as exposed or diseased)Footnote 80 but is in fact caused by the exposure. Granted this inference, it follows that all the excess incidence must be caused by the exposure. That is just what it means to accept that potential defects in the comparison have been eliminated and the general causal inference is sound. For example, it would simply not be accurate to claim that AF for lung cancer among British male smokers compared to nonsmokers is 90 percent, nor that RR is 10, if there were some other live possibility as to why smokers develop lung cancer so much more often.
Thus Greenland and James Robins write, “Epidemiologic data does place a nonzero lower bound on the probability of causation when [AF] > 0.”Footnote 81
Because excess fraction and etiologic fraction may not be equal (the latter being larger under many if not most biological models),Footnote 82 it is fallacious to equate the probability of causation in a randomly selected specific case with AF (and thus with 1 − 1/RR). However, although the etiological fraction may be larger than the excess fraction, it cannot be smaller—consistent with the assumption that the general causation issue has been settled with respect to the AF figure in question. Accepting that an exposure causes a certain excess proportion of cases in the exposed group logically entails that at least that proportion of cases features the exposure as a cause. But as shown above, it does not logically prevent there being more cases caused by the exposure. To cite an AF of 90 percent or an RR of 10 for male British smokers with lung cancer would be inaccurate, or at least highly misleading, if there remained some live possibility of an alternative explanation for at least some of the excess incidence, whereas these figures remain accurate even if it is suspected (as it may reasonably be) that smoking plays a role in more than 90 percent of cases of smokers with lung cancer. AF and RR express numerical differences between incidences in populations, and explaining those differences is not equivalent to explaining the incidence in either population.Footnote 83
This suggests that the PC formula should be replaced with a “PC inequality”:

Or, equivalently:
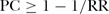
These inequalities require two caveats. First, they assume that the incidence in the exposed group is greater than that in the unexposed group, that is, that RR > 1.Footnote 84 This is a plausible assumption in the context of litigation, because if the harm is more common among the unexposed group, this suggests prima facie that the exposure has a net protective effect, and it is hard to see how a net protective effect would generate claims for damages in the way that in fact net harmful effects have done. In any case it is easy to check whether the assumption is satisfied. Second, as emphasized at the outset, the formula must not be treated as determinative. Other evidence may bear on the probability that the fact finder ought to assign to causation; to this extent the aforementioned Manual is quite correct. Epidemiological evidence must be weighed against other relevant evidence.
The epistemic position with regard to epidemiological evidence is thus surprisingly simple, though delicate to state clearly. Epidemiological evidence says not how probable specific causation is but how improbable it is not.Footnote 85 Once the general causation issue is settled and a figure for RR or AF is accepted, it follows that at least the proportion of cases indicated by the AF is caused by the exposure. If we accept that the claimant is a randomly selected exposed person, then the force of that evidence is that the probability that the exposure caused the harm in that case is not less than AF.
However, this proposal does not answer Wright's objection that epidemiological evidence is irrelevant to ex post probabilities altogether. So far I am ignoring that objection for the sake of clear statement. Before we turn to this conceptual objection to epidemiological evidence, it is worth noting that the foregoing reasoning applies equally to the but-for test. Suppose that as well as excess and etiologic fraction, we define but-for fraction: the proportion of an exposed population who would not have developed the disease but for the exposure. The but-for fraction could be much greater than the excess fraction (because the exposure could prevent the disease in some while causing it in others, etc.). But it could not be less—provided that a causal explanation of the excess fraction is accepted. That would tantamount to claiming that the excess fraction arose due to some interfering factor or factors and not because of the exposure, or else that it was not caused at all, which is even more strange. On this basis it is a paradigmatic inference that but for the exposure, the excess would not have occurred—for any viable interpretation of “but for.”Footnote 86
Jonathan Schaffer has put it to me (in correspondence) that the asymmetry I seek to capture with my “PC inequality” arises because of an asymmetry in my starting assumptions. My conclusion follows if we make the epistemic assumption that a causal inference is warranted at the general level but refuse to make the biological assumptions necessary to move from my PC inequality to the PC formula I reject. But why make the epistemic assumption and not the biological one?
My answer is, first, that it is realistic to assume that epidemiological evidence sometimes warrants a general causal inference, and so it is reasonable and, I hope, useful to confine the discussion to what follows from that. It is not, however, realistic to assume a given biological model for diseases in this context, because we are focusing on the situation where the biology of the disease is not well understood. As we see at the outset, this is typically the reason for appealing to epidemiological evidence in the first place. Moreover, the biological facts that must obtain for epidemiological evidence to provide an upper bound on the probability of causation are rarely instantiated. Greenland and Robins write, “We know of no cancer or other important chronic disease for which current biomedical knowledge allows one to exclude mechanisms that violate the assumptions needed to claim that PC = [AF].”Footnote 87
More generally, as my Himalayan porter with the bad back is supposed to illustrate, it is quite implausible that the requisite assumptions are widely instantiated. Interaction is common, and exposures that simultaneously protect against the effect of other exposures when they cause a disease are rare.
My second reply to Schaffer's point is that if we want to find out what the epidemiological evidence says about specific causation, we must make the assumption that it is good. Bad epidemiological evidence, like bad evidence more generally, does not say much about anything (or, at least, what it says cannot be stated in a general way). However, we do not need to make a biological assumption about the nature of the disease in question merely in order to understand what epidemiological evidence says, especially not when these assumptions are so rarely satisfied. Granted, the epidemiological evidence might say something different in the light of further knowledge about the biology of the disease; but this, again, departs from the question I want to tackle, which is what the epidemiological evidence itself says, before other evidence is considered.
V. THE EPISTEMIC SIGNIFICANCE OF EPIDEMIOLOGICAL EVIDENCE
If epidemiological evidence says anything about specific causation, then what it says is in the form of an inequality: in the absence of other evidence, the probability that the exposure caused the harm in a randomly selected case is at least the attributable fraction (AF). But there is a strong current of opinion among both judges and commentators that epidemiological evidence is not relevant to the proof of specific causation in this direct way: that it does not, in fact, say anything about how probable it is that the exposure caused the harm in a particular case.
There are in fact a number of different objections on this theme. Let us distinguish epistemological from legal objections, where the latter claim something more than just that epidemiological evidence is epistemically deficient with regard to the specific causation issue. We consider legal objections in the next section.
The epistemological objections turn on the fact that epidemiological evidence concerns populations and not individuals. But as argued in Section III, this bare fact does not amount to a cogent objection to the epistemic relevance of epidemiological evidence to individuals, and in fact both conceptual and empirical arguments demonstrate that epidemiological evidence is relevant to individuals in some circumstances.
One possible way to flesh out the objection is to argue that coherent use of epidemiological evidence requires knowing something about the mechanism(s) by which the exposure causes the harm.Footnote 88 A disambiguation is necessary here. On one understanding, what we need to know is a general scientific fact about how the exposure causes the harm when it does so. As Jane Stapleton emphasizes, this will not get us any further with our question; to prove specific causation, we need to know how the harm in fact was caused on this particular occasion.Footnote 89 Thus the other disambiguation of the objection is that we must know what mechanism gave rise to this particular case of disease before we can use epidemiological evidence. But if we know that, then we have settled the specific causation issue already, and the epidemiological evidence is entirely redundant. The requirement that we know which mechanism operated on this particular occasion thus cannot be a precondition on the relevance of epidemiological evidence; rather, it is a denial of its relevance. The implication of the denial is that we must always know what mechanism gives rise to an effect in order ever to know that causation occurs. But this is radically implausible. I can know that drinking whisky caused my hangover without having the faintest idea how. Moreover, to insist that I must always know the mechanism underlying a causal phenomenon is to plunge into a regress, because the mechanisms in question will typically also involve causal relations (at least in the sorts of cases we are concerned with here).Footnote 90 Thus the objection fails on either disambiguation.
A different line of argument is developed by Wright, who distinguishes ex ante and ex post probabilities. According to Wright, the epistemic worry is that statistical information derived from population-level studies “takes the eye off the ball by asking what was likely to happen ex ante, or what the abstract statistical odds were, rather than focusing on what actually happened ex post.”Footnote 91 Wright's ex ante/ex post distinction is tied up with his view of causation, which he sees in terms of causal generalizations and causal laws. A causal generalization might be that smoking causes lung cancer. A causal law would be the full specification of all those factors that are present when smoking causes lung cancer. According to Wright, we use causal generalizations because we generally have “imperfect knowledge” and therefore often cannot state causal laws.Footnote 92
In this context, an ex ante “causal probability” is the probability that “the causal law underlying a causal generalization will be fully instantiated if the generalization is fully instantiated.” Footnote 93 So it is the probability that the exceptionless causal law underlying “Smoking causes lung cancer” will be instantiated if a person smokes and develops lung cancer—meaning the probability that when smoking and lung cancer both occur, smoking causes the lung cancer.Footnote 94 On the other hand, an ex post probability is “a case-specific probability, based solely on the particularistic evidence specific to a particular occasion, that the causal law underlying a possibly applicable causal generalization was fully instantiated on the particular occasion.”Footnote 95
It is evident from these definitions that the weight of the ex ante/ex post distinction must be borne by the definition of “particularistic evidence.” Otherwise the only other distinction is whether the probability concerns the future instantiation of a causal law or its past instantiation. That distinction is surely not relevant in this context. Usually evidence as to the occurrence of an event retains its force regardless of whether the event has occurred at the time the evidence is assessed. Of course, it may be silly to rely after an event solely on evidence that was available before it happened. Predictions as to who will win a football match are disregarded after the match is played, but not because they lose their force—rather, because better evidence is available. Likewise, the problem with epidemiological evidence cannot be merely that the event in question now lies in the past. The evidence is as good for retrodiction or “postdiction” as for prediction, and Wright acknowledges this point.Footnote 96
The distinction between ex ante and ex post probabilities, then, is not between probability of a future event and probability of a past event. Within the materials provided by the definitions offered, the distinction must therefore have to do with the kind of evidence that supports each respective kind of probability. Wright writes, “An item of ‘particularistic evidence’ is a concrete feature of a particular occasion that instantiates or negates the instantiation of one of the abstract elements in a possibly applicable causal generalization.”
In support of his distinction Wright cites Day v. Boston,Footnote 97 where the court pointed out that the slightest evidence that a roll of a die resulted in a 6 would outweigh “all the probability otherwise.”Footnote 98 Wright proceeds to claim that, “To prove that a causal generalization and its underlying causal law have been instantiated, one must prove that all the abstract elements in the causal generalization and the underlying causal law have been instantiated. Only particularistic evidence can establish such instantiation.”Footnote 99
Since only particularistic evidence can bear on whether a causal generalization was in fact instantiated, and only ex post—not ex ante—probabilities are backed by particularistic evidence, only ex post probabilities can bear on whether a causal law was instantiated. Thus only ex post probabilities bear on whether a particular claimant's harm was caused by a particular exposure.
Despite Wright's strenuous efforts, the ex post/ex ante distinction remains elusive. There are several difficulties. First, all the weight is on “particularistic evidence.” But what makes evidence “particular” or “specific” to a given case? Jones has smoked twenty cigarettes a day for the last forty years. Jones, the cigarettes, the days, and the years were all particular and concrete. It is also true that he has lung cancer. The lung cancer is not abstract; it is particular and concrete. To that extent these are pieces of “particularistic evidence”; they are facts about Jones. Yet they clearly bear on the probability, which Wright wants to dismiss as ex ante, that is yielded by considering the epidemiological evidence that RR for British male smokers, of which Jones is one, is 10.
One possible response is that the facts cited are not particular, because they do not mention anything special about Jones's smoking or lung cancer. They go equally for many other smokers. But that will always be true unless we provide unique features of Jones's situation. Yet this is not a sound requirement on evidence. First, why should a claimant prove that her case is unique in order to succeed? It is possible that two cases may be alike, if not tout court, at least on the legally salient facts before the court. Why should a case turn on the extrinsic fact that other, similar cases exist? Two throws of a die may both result in a 6. Moreover it is the similarities with other occasions on which a die has come up 6 that allows an eyewitness to confirm that this was what happened on a particular occasion and indeed to express what she saw to an audience.Footnote 100 Second, in legal practice cases are usually considered to be easier to settle when they share features with other cases. Third, it is a fundamental philosophical point that causation is something we learn about from experience. A causal finding about an entirely alien sequence of events would be a mere guess.Footnote 101 To this extent there is a serious prospect that unique features of Jones's case, far from being crucial, would be epistemically irrelevant, because it is the similarities, and not the differences, between Jones's case and others that take center stage in any causal inferences we might make.
It cannot be, then, that particularistic evidence consists in features of a situation that are unique. Such features may be wholly irrelevant to the inference at hand; and nonunique features might be germane.
There is a more basic and perhaps obvious problem with Wright's proposal, however: it rests on a piece of speculative metaphysics. The view of the nature of causation and its relation to laws that Wright espouses is contested by many philosophers. For Wright, a causal law is an exceptionless regularity, and causation occurs when the regularity is instantiated. There are many philosophical objections to the claim that laws of nature are exceptionless regularities. They are serious objections, and in consequence, the popularity of regularity theories of law and causation among philosophers has been in decline since the second half of the last century. None of this means that they are indefensible or that Wright is wrong about the nature of causation. But as others have noted,Footnote 102 Wright does not acknowledge the full force of the difficulties that his view faces nor the strangeness of basing a practical recommendation on an uncertain metaphysical theory. It is wrong, epistemically and morally, to justify excluding epidemiological evidence at law on the basis of a controversial stance in speculative metaphysics. The basis of Wright's argument is far too uncertain and contested to form the basis of any legal doctrine. Even philosophers who agree that laws of nature are exceptionless regularities would probably hesitate to deploy their theory in this way. If Wright's position is to be supported, another, less speculative basis must be found.
A better interpretation (which Wright would not accept) might be that evidence is particularistic when it is sensitive to the truth of the hypothesis in question. On this interpretation, particularistic evidence as regards the claim that Jones's smoking caused his lung cancer does not consist in unique features of Jones's situation. He is demanding features of the situation which would be different if Jones's smoking was not caused by lung cancer.Footnote 103 Thus it might be objected that statistical evidence of the sort provided by epidemiology is not sensitive to the correctness of the inference in any particular case. The evidence would be just the same if Jones's lung cancer were not caused by smoking as if it were. Particularistic evidence, on the other hand, might be understood as evidence that would have been different if the hypothesis it is adduced to prove were false. This interpretation is an expression of the epistemological stance known as counterfactual reliabilism, according to which a good inductive inference must be such that the evidence is sensitive to the truth-value of the conclusion reached.Footnote 104 Statistical evidence clearly violates this condition in application to individuals, because ex hypothesi the evidence is the same for every individual and therefore warrants the same conclusion for each.
This objection raises difficult questions. Although some philosophers endorse sensitivity conditions on evidence, others roundly reject them.Footnote 105 Again, we should be wary of settling practical disputes by resorting to philosophical views that are themselves actively disputed. Moreover, even if this understanding of particularistic evidence does distinguish it neatly from epidemiological evidence, it hardly follows that the latter must be ignored. On the contrary, if it can be shown that ignoring epidemiological evidence is a bad idea, that would be a problem for counterfactual reliabilism.
And indeed, the second serious problem with the proposed distinction between ex ante and ex post probabilities is that ignoring the latter commits an epistemic fallacy and demonstrably leads to errors. Contrary to what might seem intuitive, it is always necessary to weigh what Wright would label the ex ante probability against whatever sorts of evidence Wright would accept as particularistic. In a nutshell, this is because you cannot simply disregard old evidence when new evidence comes in.
For example, suppose that we have an ex ante probability of 1/6 that a die will come up 6. Suppose we throw the die and it comes up 6. In normal circumstances, we are not aware of weighing up a 1/6 statistical probability against the (unquantified) probability that our eyes are functioning correctly. Indeed, we are probably not aware of it because we probably do not do it. But now suppose that instead of turning up a 6, the die turns into a butterfly. Then it would be both reasonable and intuitive (if we keep our wits about us) to compare the ex ante probability (albeit not readily quantifiable) of this occurrence with the ex post probability based on the particularistic evidence provided by our visual experience. The latter is 1, because that is what we see; but it is surely reasonable to doubt that the die really turned into a butterfly. Because the particularistic evidence in both the 6 case and the butterfly case is the same, the ex post probability to which it gives rise is presumably the same. Yet it is surely rational to be less certain that the die really did turn into a butterfly than that you really did roll a 6 in the first case. That is because it is surely rational to take into account the background frequency with which events occur in the relevant circumstances when deciding whether a particular event did in fact occur.Footnote 106 To deny this is to make an epistemic error.
There is a plausible explanation for the prevalence of the error of ignoring epidemiological evidence in proof of specific causation. The error is an instance of the well-documented human tendency to ignore “base rates” in calculating probabilities.Footnote 107 A base rate is, roughly, the frequency with which a given event generally occurs in the circumstances in question. If this is not taken into consideration when estimating the probability that an event has in fact occurred, then errors result. To take a well-known example, if a disease occurs among one in a thousand people in a population, and a medical test for the disease has a 5 percent false-positive rate,Footnote 108 it would be erroneous to conclude that an individual testing positive has a 95 percent chance of having the disease. On average, for every thousand people tested, fifty will test positive when they do not in fact have the disease. In addition, assuming no false negatives, on average a further one person on average will test positive because he or she has the disease. The correct probability that a given positive test result in this population indicates the disease is therefore one in fifty-one, or roughly 2 percent. And that means that the probability that the positive test result is caused by the disease in any individual case is about 2 percent. In this case, ignoring the epidemiological evidence as to the prevalence of the disease in estimating the probability of specific causation leads to a huge error—an estimate of 95 percent when the correct figure is about 2 percent.Footnote 109
The relevance of this example is that epidemiological evidence is typically problematic in cases where there is no test to distinguish those cases of the disease that are caused by the exposure from those that are not. Were a test available to distinguish, say, cancers caused by smoking from those that are not, presumably that would amount to particularistic evidence.Footnote 110 Yet this evidence would not entirely displace epidemiological evidence—or at least, it should not, epistemically speaking. Rather, it ought to be weighed against that evidence. But this seems incompatible with a strong distinction between ex ante and ex post probabilities, where the latter are supported by particularistic evidence and the former derive from epidemiological evidence. To this extent, the mooted distinction between ex ante and ex post probabilities represents an epistemic fallacy.
It might be replied that both the false-positive rate and the base rate are ex ante probabilities. In the medical test example, the false-positive rate is presumably drawn from statistical data just as much as is the base rate of the disease. But even granting that assumption, the objection is a weak one. For it leaves the objector committed to ignoring not only base rates but even false-positive rates. This is a reductio ad absurdum of the suggestion that ex ante probabilities are irrelevant to determining whether particular events have occurred. For it is obviously absurd to ignore the reliability statistics for a medical test when forming a view as to the probability that the disease-event it purports to detect has occurred.
Wright illustrates some of the problems he perceives in the use of statistical evidence with a discussion of Hotson v. East Berkshire Area Health Authority.Footnote 111 There it was found that there was a 75 percent chance that a permanent injury suffered following a delay in medical treatment would have occurred anyway and therefore that the burden of proof of causation was not discharged. Wright argues that this is a non sequitur.Footnote 112 I agree, but the criticism here has nothing to do with the use of statistical evidence per se. It is a criticism of the use of the but-for test. The kernel of Wright's argument is that even if the permanent injury would have occurred without the delay in treatment, it does not follow—and indeed seems unlikely—that the delay was not among the causes of the permanent injury. It seems to me that this criticism is correct. It concerns the misunderstanding of epidemiological evidence identified in Section IV of this paper and it is answered by the proposal made there that epidemiological evidence should be regarded not as providing a figure for the probability of causation but as assisting in the estimation of a lower bound.
Let us finish this section with two slightly different objections. The first is that “probability” remains undefined. This is not the place for a discourse on interpretations of probability.Footnote 113 The epidemiological measures AF and RR lend themselves to a frequency interpretation, if they are to be interpreted as probabilities at all. A frequency interpretation sees a probability as the frequency of an event in the indefinitely long run (e.g., the proportion of heads you would get if you endlessly tossed coins). Epidemiological evidence arguably provides a good estimate of this sort of probability. The probability for specific causation might be understood as a single-case chance conditional on the evidence, what Hugh Mellor calls an epistemic probability;Footnote 114 or it might be a rationally constrained subjective degree of belief, sometimes called a credence. In either case, we would need some principle along the lines of David Lewis's well-known Principal Principle, Footnote 115 which states roughly that credences ought to be apportioned to objective chances where the latter are long-run frequencies. (If epistemic probabilities are preferred to credences, then we would need some similar principle relating the single-case chance, given evidence regarding a long-run frequency) The Principal Principle is a subject of philosophical dispute, but some version of it is highly plausible—to the extent that it is regarded by some as a necessary condition on any adequate theory of objective chance.Footnote 116 As far as I can see, nothing further of relevance in this context turns upon the interpretation of probability that is chosen. All that is required is that it makes sense to think of an event as having a degree of probability in the light of given evidence, and that that probability can change in the light of further evidence.Footnote 117
Second, it might be objected that this line on epidemiological evidence commits us to an implausible stance on the notorious “blue bus problem,”Footnote 118 which is intended to illustrate both the attractiveness and the silliness of allowing proof by purely statistical evidence.Footnote 119 Suppose a claimant is hit by a bus she does not see, but it is known that 75 percent of the buses in town are run by the Blue Bus Company. Does that mean that there is a 75 percent probability that she was hit by a blue bus, and moreover, should she succeed on that basis? My approach to epidemiological evidence might appear to support a positive answer, at least to the first part of the question (we deal with legal standards of proof in Section VI).This is at least in tension with a body of judicial and academic opinion.
But the objection is not accurate. The blue bus problem concerns the use of statistics more generally, including what Wright calls “naked statistics”Footnote 120 that are not supported by any causal inference. We, however, are concerned with statistical measures that are causally explained. It might be that the remaining 25 percent of buses are run by freelance cowboys who account for almost all traffic accidents in the city. A closer analogy would be a case where 75 percent of injuries relevantly like the claimant's are caused by Blue Buses. In that case, the significance of that evidence would indeed be a 75 percent chance that the injury was caused by a Blue Bus.Footnote 121 But in that case, we would not be using naked statistics as the basis for inferring specific causation. We would first be clothing the statistics in a general causal inference; and it is the general causal claim, quantified but not exhausted by the statistical fact, that licences the inference to the specific causal claim.
It does not follow, in any case, that the claimant must succeed against the Blue Bus Company. Indeed, the question, properly put, is not whether she must but whether she can succeed.Footnote 122 There may be other evidence (as I repeatedly emphasize in the epidemiological case). Moreover, the lack of other evidence in a case like this may itself tell heavily against the claimant, given that it is relatively easy to identify the color of a bus. Then the difference between this case and the epidemiological one concerns not what the evidence says but how clear the total evidential picture is, and the clarity of that picture depends in part on what evidence might in principle be available.
Of course, the blue bus problem may be set up so as to make the lack of other evidence insignificant: the bus hit from behind, it was misty, and so on.Footnote 123 Such attempts deserve some suspicion: common sense is not easily instructed to ignore the fact that when buses strike, there is usually more than just statistical evidence available. This is because buses are big, noisy, and full of people. However, diseases are not like buses. When trying to prove specific causation using epidemiological evidence, there is no possibility of eyewitness testimony. When only epidemiological evidence is used, that is generally because clinical science cannot produce anything better. If a claimant sought to rely on epidemiological evidence to prove causation for a harm that was comfortably within the scope of clinical science, they would be on shakier epistemic ground, because the total evidential picture, taking into account the evidence that might in principle have been available to the claimant, would be weaker.Footnote 124
What does, however, remain to be discussed is the legal significance of the probabilities that epidemiological evidence can, if my argument is right, confer upon specific causation. Let us turn to that.
VI. THE LEGAL FORCE OF EPIDEMIOLOGICAL EVIDENCE
Even if it is accepted that epidemiological evidence has epistemic force of the sort and degree I describe above, its legal force remains to be determined. In particular, it does not follow from a probability of specific causation of more than 50 percent conferred by epidemiological evidence that a claimant must succeed. The simplest reason for this is the point already rehearsed a number of times: that the probability conferred by the fact finder must depend on all the evidence and not just the epidemiological evidence. But let us set that point aside—for example, suppose that only epidemiological evidence in the form of an RR or AF backed by a good causal inference is available for the proof of specific causation (and it is not reasonable to expect any other kind of evidence, given the current state of medical science). Does epidemiological evidence satisfy the legal standard of proof, and if so, at what level of AF and RR?
It seems to me that once the epistemic relevance of epidemiological evidence has been admitted, legal grounds for excluding it would need to be very compelling indeed. Take, for example, Lord Nimmo Smith's decision to refuse compensation to Mr. McTear's widow, a decision that he would have maintained even if he had found the general causation issue proved at a level of RR = 10.Footnote 125 On average, faced with ten such claimants, Lord Nimmo Smith would decide wrongly on this issue for nine of them. This is uncontestable; what is contested is the relevance of this fact to making a decision in any of the cases. But if the argument of Section V is correct, this fact is relevant. And Lord Nimmo Smith probably decided wrongly in Mr. McTear's case, assuming that a probability of 0.9 or greater (which, by the argument of Section IV, the evidence shows) falls within the scope of “probably.” As a matter of natural justice, it seems to me that the law must find a very good reason if it is to endorse findings of fact which, like Lord Nimmo's, are probably false on the available evidence.
One such reason is precisely that a probability of 0.9 or more, or indeed any numerical probability, does not fall within the legal meaning of “probably.” Thus Charles Nesson writes:
“probability” as we use the term in law, particularly in the civil standard of proof, is not a hard-edged mathematical concept. It is, rather, a concept that incorporates less rigid ideas of justice and reflects the judicial function of resolving disputes in the real world, where values shift and knowledge is uncertain. An outcome is “probable” if it best accomplishes a just and acceptable resolution of the dispute. Probability, as a legal concept in the law of proof, suggests wisdom, probity, and approbation—not favorable betting odds.Footnote 126
Stripping away the rhetoric, there are two points here. The first is the negative point that probability, in a legal context, is not a mathematical concept, which is presumably supposed to imply that it cannot or should not be quantified and thus is not properly dictated by evidence that yields mathematical probabilities (numbers between 0 and 1). The second is the positive point that probability in the legal context is not a purely epistemic notion at all but includes normative considerations motivated by justice.
The negative point has been developed by other commentators into a distinction between a quantified probability attached to an event in some putatively irrelevant way and the notion of probability employed in or required to satisfy the standard of proof. For example, Steve Gold writes, “Juries should not be instructed that the preponderance standard means that plaintiffs must prove a fact probability greater than 50%. Rather, they should be instructed that plaintiffs must establish certain facts . . . by evidence which convinces juries that the fact is more likely true than not.”Footnote 127
More recently, a similar line is argued by Wright, who maintains that the correct standard of proof for this element of this kind of liability is preponderance of evidence and that this is not accurately represented by “a 50+ percent statistical probability,” as a matter either of logic or of psychology.Footnote 128 Wright claims that the preponderance-of-evidence standard is satisfied by attainment of “the slightest degree of belief” in the truth of the proposition to be proved.Footnote 129
Wright seems to be opposing the expression of a degree of belief as a number between 0 and 1 and advocating instead a different meaning for “degree of belief”—a meaning that implies that even if you have only the slightest degree of belief, you do believe that the event in question occurred. It is indeed arguable that quantifying degree of belief in this way involves some fiction. It does not follow, however, and it is not true that evidence that presents quantified probabilities should have no effect on our beliefs. Even if we accept Wright's conception of a degree of belief and of its relation to the standard of proof, it does not follow that we must accept only “unquantified” probabilities and reject “statistical” ones.
In various places Wright claims that the probabilities relevant to the degree of belief whose formation amounts to satisfaction of the standard of proof are not quantified. For example, he says:
The final judgement on what actually happened depends on whether the unquantified ex post probability associated with a possibly applicable causal generalization . . . is sufficient, in comparison with the unquantified ex post probability associated with competing causal generalizations, to produce the required degree of belief in the truth that the first causal generalisation and its underlying law were the ones that were fully instantiated on the particular occasion.Footnote 130
In the previous section I dealt with the objection to ex ante probabilities. It remains to consider the potential objection that only unquantified probabilities are legally relevant. There is surely no plausibility to this objection. It is implausible that a probability should be epistemically irrelevant merely because it is quantified, as shown in the previous section. And once epistemic relevance is accepted, some positive grounds need to be found for ignoring this evidence. The mere fact that a probability is quantified does not in itself provide any such grounds.
Thus once it is accepted that quantified probabilities can inform beliefs, we face a question as to how they relate to the legal standard of proof. This interpretive issue cannot be ducked. Suppose Nesson is correct that probabilities in law are not usually quantified, and Gold and Wright are correct that the standard of proof is not best expressed as a probability in excess of 0.5. The emerging question is: When should a fact finder form “the slightest degree of belief” that the event in question occurredFootnote 131 when faced with a quantified probability that that event occurred (and no further evidence is available)? When is the preponderance-of-evidence or more-likely-than-not standard satisfied?
In the civil case, there is surely only one right answer: when the only evidence is a quantified probability whose accuracy is not in dispute, the standard of proof is met by when the numerical probability exceeds 0.5. This is the only way to give effect to the principle that she who asserts proves, while sustaining impartiality. A lower standard would favor claimants. A higher standard would favor defendants. These propositions assume, of course, an equal probability of rectitude between claimants and defendants. But that is what courts ought to assume: that is impartiality.Footnote 132
(Would it not be equally impartial to award damages in proportion to the probability that has been proved?Footnote 133 So, for example, if the finding is of 70 percent probability of causation, then perhaps 70 percent of a full award should be made; and if the probability is 20 percent, that should be awarded. This proposal may be impartial, but it amounts to an entirely different system of awarding damages from the one that the law in this area currently employs. It would make full compensation very difficult to attain even when it is probably deserved and small awards easy to attain even when they are probably not deserved. It would require judges to quantify their overall estimates of the probability of their conclusions, which is difficult to do even in those cases where some of the evidence is quantitative. And even if the approach were confined to the present context (i.e., epidemiological evidence), it would be unworkable because of a point I stress repeatedly: that epidemiological evidence provides an estimate not of the probability of causation but of a lower bound for that probability (see Section IV). Thus “an award proportionate to the probability of causation,” if based on epidemiological evidence, could mean anything between AF and 100 percent.)
The second, positive claim that Nesson makes is that in law, “probability” is a normative rather than—or as well as—an epistemic concept. One way to pursue this point is to consider the fact that epidemiological evidence applies equally to all claimants. Thus, if the epidemiological evidence is strong enough to support a case, every claimant will succeed; whereas if it is too weak, every claimant will fail.Footnote 134 This has an air of paradox because the very same evidence tells us that not all claimants should succeed and that not all should fail. It also has an air of injustice: courts accepting this evidence know that they are making findings that are factually wrong in at least some cases, and, prima facie, that is not just.
It may be that normative objections could be developed on this basis. But the primary concern of this paper is with the epistemic force of epidemiological evidence. To that extent I am content to leave normative objections aside.
Nonetheless, it is worth noting that any normative objections to the use of epidemiological objections cannot arise from the mere possibility of error. Every finding of fact comes with some degree of uncertainty. What is unusual about epidemiological evidence (and perhaps statistical evidence more generally) is that the degree of uncertainty is quantified. We can say how many times, in a series of ten or one hundred or one thousand findings of fact, the court will err if it relies upon that evidence alone. The mere fact that the evidence tells us this ought not to deter us from using that evidence, because the mere fact that other kinds of evidence do not quantify their own error rates does not imply that they never lead us into error. It is highly implausible to suppose that fact finders do not or should not consider the reliability of all the various kinds of evidence that count as “particularistic.” Should the fact finder ignore the fact that one witness is a reputable accountant, another an alcoholic rock star, and a third the defendant's mother? Clearly not. And there are sometimes statistical facts about the past reliability of certain kinds of evidence. It is highly implausible that ignorance of these facts improves either the epistemic or the normative situation with regard to use of this sort of evidence. It is difficult to avoid the suspicion that at least some of the resistance to the use of epidemiological (and perhaps some other statistical) evidence arises from a reluctance to face the fact of fallibility—or more precisely, the fact that fallibility over a series of findings entails either actual error or improbable luck.Footnote 135
VII. CONCLUSION
Epidemiological evidence does not merely settle the “causal capacity” issue;Footnote 136 it can also quantify the effect of an exposure in terms of the difference in incidence between exposed and unexposed populations. Where the difference is causally explained so that confounders are eliminated, what the epidemiological evidence says about specific causation can be expressed as an inequality:Footnote 137

Or:
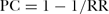
Epidemiological evidence does not say that the probability of specific causation is a certain figure; it says that the probability of specific causation is at least a certain figure. Epidemiological evidence must of course always be weighed against other evidence, and so this “at least” must be understood as confined to the force of the epidemiological evidence and not as expressing a tout court lower bound on the probability of specific causation.
When no other evidence is available to a fact finder, it is legitimate to be guided by the epidemiological evidence (assuming it is of a sufficiently high quality to warrant a causal inference at the general level, meaning a causal explanation of AF and RR). On examination, the attempt to distinguish this sort of evidence on epistemic grounds from “particularistic” evidence fails. To refuse to consider epidemiological evidence in assessing specific causation is to endorse a known epistemic fallacy (ignoring the base rate), and thus the practical endorsement of this policy leads and probably has led to errors. Courts must not ignore epidemiological evidence for proof of specific causation. As Peter Tillers puts it, “A prohibition of group-to-individual inferences exclusively on epistemic grounds is impossible.”Footnote 138
There may be normative objections to allowing epidemiological evidence in proof of specific causation, either in general or in a particular case. But whatever normative objections there may be, no such objections arise either from the mere fact that epidemiological evidence provides quantified probabilities or from the mere fact that admitting epidemiological evidence implies admitting a quantified risk of error.
In the present context, the likeliest case where normative considerations will come into play is where RR ≤ 2 or else where RR is unknown. It is here that courts might choose to employ the materially increased-risk approach (in English law, the Fairchild exception) and allow proof of increased risk in place of proof of causation (either as sufficient to prove causation or as a harm in itself). Note, however, that RR ≤ 2 is compatible with a finding of causation, by the argument of Section IV. Moreover, as discussed in that section, there are many diseases whose etiology is such that a finding of causation would be epistemically, not only normatively, correct when RR < 2. This suggests that further biological evidence as to the etiology of the disease may help a claimant establish causation on the balance of probabilities even if the evidence is not particular to the claimant. Thus, for example, evidence that an exposure would be likely to aggravate an existing predisposition to the disease in question might suffice, along with RR between 1 and 2, to make it more likely than not that the claimant's disease was caused by the exposure.Footnote 139 In effect, the claimant would be arguing that the etiology of the disease is such that the etiologic fraction is probably greater than the excess fraction. This is another way (apart from proof of causation when RR > 2) in which the approach proposed in this paper provides a way to confine the need to deploy the materially increased-risk approach.
What, then, is the ultimate legal recommendation? It is threefold. First, if epidemiological evidence warrants a general causal inference concerning persons suitably similar to the claimant who have been exposed in sufficiently similar ways, then it must also be considered to be evidence bearing on specific causation (where “similarity” is to be assessed by the degree to which plausibly causative factors are common between the claimant's situation and those of the study subjects). Second, in the absence of any other evidence, the significance of epidemiological evidence for specific causation is measured in the way I describe, by the PC inequality, assuming that the conditions set out in Section IV are met. Third, specific evidence does not override epidemiological evidence (nor vice versa) but should be balanced against it, just as base rates must be taken into account in using medical tests.
But the final word must be one of caution. Epidemiological evidence is not determinative of specific causation. It must be considered alongside other evidence, and its quality must be assessed. The purpose of this paper has been to identify what epidemiological evidence says about specific causation. The focus has been on understanding the content of the message, not assessing its quality. How convincing that message is in any particular case must also depend on the quality of the epidemiological evidence and on the strength and content of all the other available evidence.


