The aquaporins (AQPs) are a family of small, hydrophobic, integral membrane proteins (~30 kDa/monomer) that are expressed widely in the animal and plant kingdoms, with 13 members identified to date in mammals. AQPs are expressed in many epithelia and endothelia involved in fluid transport, such as kidney tubules, glandular epithelia and choroid plexus, as well as in cell types that do not carry out significant fluid transport, such as skin and fat cells. In most cell types the AQPs reside constitutively at the cell plasma membrane, with the notable exception of AQP2 in kidney collecting duct, where vasopressin regulates AQP2 trafficking between endosomes and the cell plasma membrane.
High-resolution structures have been obtained for several AQPs, and show the assembly of AQP monomers in tetramers, with individual monomers containing six tilted α-helical domains forming a barrel-like structure in which the first three and last three helices exhibit inverted symmetry (Refs Reference Gonen and Walz1, Reference Fujiyoshi2). Molecular dynamics simulations suggest tortuous, single-file passage of water through a narrow <0.3 nm pore, in which steric and electrostatic factors prevent transport of protons and other small molecules (Ref. Reference Hub and de Groot3). AQPs 1, 2, 4, 5 and 8 are primarily water selective, whereas AQPs 3, 7 and 9 (called ‘aquaglyceroporins’) also transport glycerol and possibly other small solutes. Water transport by some AQPs is inhibited by nonspecific, cysteine-sulphydral-reactive compounds such as mercuric chloride (HgCl2). There is considerable interest, although little reported progress, in the identification of nontoxic AQP-selective inhibitors, which could serve as valuable research tools and clinical therapies.
Tissue distribution and regulation studies have provided indirect evidence for the involvement of AQPs in a variety of physiological processes. In the case of AQP2, nephrogenic diabetes insipidus in subjects with AQP2 mutations indicated the requirement of AQP2 for the formation of a concentrated urine (Ref. Reference Deen4). Much of the knowledge of AQP functions in mammalian physiology has come from phenotype analysis of mice lacking the various mammalian AQPs. One paradigm that has emerged is that tissue-specific AQP expression does not mandate AQP involvement in a physiologically important process, as was found for several AQPs in lung (Ref. Reference Verkman5) and intestine (Ref. Reference Verkman, Thiagarajah and Johnson6), AQP4 in skeletal muscle (Ref. Reference Yang7), AQP5 in sweat gland (Ref. Reference Song, Sonawane and Verkman8), and AQP8 in multiple tissues (Ref. Reference Yang9). Functional analysis of cells and tissues from knockout mice has also tested proposed roles of AQPs in gas transport and intracellular organellar function, as well as in AQP protein–protein interactions. Although there is evidence that some AQPs may allow transport of CO2 and NH3 (Refs Reference Holm10, Reference Cooper and Boron11), physiological studies in mice and transport measurement in isolated tissues have provided evidence against a physiologically significant role of AQPs in gas transport (Refs Reference Yang12, Reference Fang13, Reference Yang14). Negative data were also found for the proposed involvement of AQPs in mitochondrial function (Ref. Reference Yang, Zhao and Verkman15) and in a key AQP protein–protein interaction in the central nervous system – a proposed interaction between AQP4 and the inwardly rectifying K+ channel Kir4.1 responsible for K+ ion uptake by glial cells during neuroexcitation (Refs Reference Zhang and Verkman16, Reference Ruiz-Ederra, Zhang and Verkman17).
Balancing the many negative phenotype studies, data from knockout mice implicate important roles of AQPs in kidney, brain, eye, skin, fat and exocrine glands, suggesting their involvement in major organ functions and disease processes, including urinary concentrating, brain swelling, epilepsy, glaucoma, cancer and obesity. This reviews focuses on these AQP roles and their significance in normal organ physiology and disease. Figure 1 provides a schematic summary of the various AQP roles in mammalian physiology, and is referred to in the various sections below.
Aquaporin functions in mammalian physiology. Water-transporting functions of aquaporins (AQPs) are shown in the top half of the figure; glycerol-transporting functions are shown in the lower half of the figure. (a) AQP facilitates rapid, near-isomolar transepithelial fluid secretion: AQP deficiency in an epithelium such as salivary gland slows osmotic water transport into the acinar lumen, resulting in the secretion of a reduced volume of a hypertonic fluid. Numbers represent hypothetical fluid osmolalities. (b) Expression of AQPs 2, 3 and 4 in the kidney collecting duct facilitates the production of a concentrated urine: AQP deficiency reduces transepithelial water permeability, preventing osmotic equilibration of lumenal fluid and impairing urinary concentrating ability. Numbers represent hypothetical fluid osmolalities. (c) Proposed mechanism of AQP-facilitated cell migration, showing water entry into protruding lamellipodia in migrating cells. (d) AQP4-dependent neuroexcitation, showing AQP4-facilitated water transport in glial cells, which communicate with neurons through changes in extracellular space volume and K+ concentration. (e) AQP3 facilitates glycerol entry in the epidermis, allowing water retention (glycerol functions as an osmolyte) and biosynthesis: in AQP deficiency the steady-state glycerol content in epidermis and stratum corneum in skin is reduced, accounting for reduced skin hydration. (f) Proposed mechanism of AQP3-facilitated cell proliferation involving increased cellular glycerol and consequent increased ATP energy and biosynthesis. (g) AQP7 facilitates glycerol escape from adipocytes: adipocyte hypertrophy is seen in AQP7 deficiency, possibly as a result of impaired AQP7-dependent glycerol escape from adipocytes, resulting in cellular glycerol accumulation and increased triglyceride content. See text for further explanations. Abbreviations: G3P, glycerol-3-phosphate; TG, triglyceride.

Epithelial fluid transport
Active fluid secretion and absorption
AQPs are expressed in many epithelia, such as kidney tubules, glands, choroid plexus, ciliary body and alveoli, where they increase transepithelial osmotic water permeability. One consequence of increased transepithelial water permeability is active (also referred to as ‘facilitated’ or ‘near-isosmolar’) fluid secretion and absorption. Active fluid transport involves the creation of an osmotic gradient (generally quite small) across an epithelium by active ion/solute transport, which drives water transport through highly water-permeable epithelial cell membranes (Fig. 1a). Reduced epithelial cell osmotic water permeability can consequently impair active fluid transport and osmotic water equilibration, resulting in the secretion (or absorption) of a reduced volume of inappropriately hypertonic fluid. This prediction has been confirmed in AQP5-knockout mice in salivary gland (Refs Reference Ma18, Reference Krane19) and airway submucosal gland (Ref. Reference Song and Verkman20). Defective fluid secretion has also been found in AQP1-knockout mice in choroid plexus (Ref. Reference Oshio21), which produces cerebrospinal fluid, and in ciliary epithelium (Ref. Reference Zhang, Vetrivel and Verkman22), which produces ocular aqueous fluid. In each of these systems the rate of transepithelial fluid secretion, normalised to epithelial surface area, is very high, such that the reduced but non-zero water permeability in AQP deficiency impacts on transepithelial osmotic equilibration. Of note, because of the substantial intrinsic water permeability of lipid bilayers, AQP deficiency is generally not associated with more than a five- to tenfold reduction in transepithelial osmotic water permeability. Very rapid, active transepithelial fluid absorption occurs in kidney proximal tubule, where the majority of fluid filtered by the glomerulus is reabsorbed. Proximal-tubule fluid absorption is impaired in mice lacking the proximal-tubule water channel AQP1 (Ref. Reference Schnermann23), resulting in inappropriately hypertonic absorbed fluid (Ref. Reference Vallon, Verkman and Schnermann24).
By contrast to these examples of AQP-dependent transepithelial fluid secretion and absorption, there are examples where AQP deletion does not affect active fluid secretion or absorption. In lung alveolus, although deletion of AQP1 or AQP5 each reduces airspace-capillary water permeability by about tenfold, active fluid absorption is not impaired under normal physiological conditions (Refs Reference Bai25, Reference Ma26), including during rapid airspace fluid absorption in the neonatal lung and during stresses such as lung injury (Ref. Reference Song27). Similarly, deletion of AQPs does not impair active fluid absorption in the airways (Ref. Reference Song28), peritoneal cavity (Ref. Reference Yang29) and pleural cavity (Ref. Reference Song30), or fluid secretion by the sweat gland (Ref. Reference Song, Sonawane and Verkman8). The common feature of these examples is that the area-normalised rates of transepithelial fluid transport are substantially lower than those where AQP deletion impairs fluid transport. Thus, as predicted from the considerations in Fig. 1a, whether AQPs are required to facilitate transepithelial fluid transport depends on the rate of fluid transport.
Osmotic equilibration across kidney tubules and the urinary concentrating mechanism
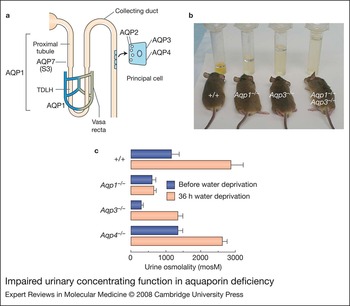
Another anticipated role of AQPs is in water transport across kidney tubules and microvessels (vasa recta), which is required for the formation of a concentrated urine. The major AQPs expressed in the kidney are AQPs 1, 2, 3, 4 and 7 (Fig. 2a). Deletion of the genes for AQP1 and/or AQP3 in mice results in marked polyuria, as seen in 24 h urine collections (Fig. 2b) (Refs Reference Ma31, Reference Ma32). Measurement of urine osmolalities in mice before and after 36 h water deprivation (Fig. 2c) shows that urinary osmolality in AQP1-null mice is low and does not increase with water deprivation, resulting in severe dehydration. AQP3-null mice are able to generate a partially concentrated urine in response to water deprivation, whereas AQP4-null mice manifest only a mild defect in maximum urinary concentrating ability (Ref. Reference Ma33).
Impaired urinary concentrating function in aquaporin deficiency. Deletion of aquaporins (AQPs) in kidney results in increased urinary output and reduced urinary osmolality. (a) Sites of AQP expression in kidney, showing AQP1 expression in the proximal tubule, thin descending limb of Henle (TDLH) and outer medulllary descending vasa recta, AQP2 expression at the lumen membrane and endosomes in collecting duct, and AQP3 and AQP4 at the basolateral membrane in collecting duct. (b) 24 h urine collections showing polyuria in mice lacking AQP1 and AQP3, individually and together. (c) Urine osmolalities before and after 36 h water deprivation (standard error shown). Data summarised from Refs 31, 32 and 33. (The nomenclature style Aqp is used to denote mouse aquaporin genes here, but the style AQP is used throughout the main text of this article to denote mammalian AQP proteins in general.)

AQP1 deletion produces polyuria and unresponsiveness to water deprivation by two distinct mechanisms: impaired near-isosmolar water reabsorption in the proximal tubule, as described above, and reduced medullary hypertonicity resulting from impaired countercurrent multiplication and exchange (a consequence of low water permeability in the thin descending limb of Henle and outer medullary descending vasa recta). Transepithelial osmotic water permeability in the isolated microperfused S2 segment of proximal tubule was reduced by about fivefold in AQP1-knockout mice (Ref. Reference Schnermann23), indicating that most water transport in the proximal tubule is transcellular and AQP1 dependent. AQP1 also provides the major route for transepithelial water permeability in the thin descending limb of Henle and outer medullary descending vasa recta (Refs Reference Chou34, Reference Pallone35). These results support the conclusions that AQP1 is the principal water channel in these segments, and that AQP1 plays a key role in the antidiuretic kidney in the generation of the hypertonicity of the medullary interstitium by countercurrent multiplication and exchange. The aquaglyceroporin AQP7 is expressed in a small distal segment (S3 segment) of the proximal tubule; however, its deletion in mice is not associated with significant impairment in urinary concentrating ability, but rather with an impairment of glycerol clearance, whose significance remains unclear (Ref. Reference Sohara36).
AQP3 and AQP4 are expressed at the basolateral membrane of collecting duct epithelium, with relatively greater expression of AQP3 in cortical and outer medullary collecting duct, and AQP4 in inner medullary collecting duct. In contrast to AQP1 deficiency, countercurrent multiplication and exchange mechanisms in AQP3/AQP4-null mice are basically intact. The polyuria in AQP3-null mice results from reduced osmotic water permeability of cortical collecting duct basolateral membrane (Ref. Reference Ma32). Reduced transepithelial osmosis across the collecting duct epithelium interferes with osmotic water extraction from fluid flowing through the tubule lumen (as shown in Fig. 1b), resulting in the excretion of an inappropriately large volume of dilute urine. AQP4-null mice manifest only a mild impairment in maximal urinary concentrating ability (Ref. Reference Ma33), despite a fourfold reduced water permeability in microperfused inner medullary collecting duct (Ref. Reference Chou37), in part because of the relatively greater quantity of fluid absorbed by cortical versus inner medullary segments of the collecting duct. Several mouse models of AQP2 gene deletion and mutation (reviewed in Ref. Reference Verkman38) support the conclusion from humans with nephrogenic diabetes insipidus that AQP2 is the major vasopressin-regulated water channel whose apical membrane targeting in collecting duct during antidiuresis is crucial for the formation of a concentrated urine. Because transepithelial water transport in collecting duct is transcellular, the impairment in urinary concentration resulting from reduced water permeability (Fig. 1b) can result from reduced water permeability of the serial apical (AQP2-containing) or basolateral (AQP3/AQP4-containing) membrane barriers.
Brain swelling
Another major AQP role related to its water transport function is in brain water balance. AQP4 is expressed in glial cells (astrocytes) throughout the brain and spinal cord, particularly at sites of fluid transport at blood–brain and brain–cerebrospinal-fluid (CSF) interfaces. AQP4 expression is polarised to glial cell foot processes in contact with blood vessels, and in the dense glial cell processes that form the glia limitans lining the CSF-bathed pial and ependymal surfaces in the subarachnoid space and the ventricles. AQP4 provides the major route for water transport across glial cell membranes. Osmotic water permeability in glial cells cultured from AQP4-null mice was sevenfold lower than that from wild-type mice (Ref. Reference Solenov39). Also, greatly slowed accumulation of brain water was found in AQP4-null mice in response to serum hypo-osmolality, as monitored by a noninvasive near-infrared optical method (Ref. Reference Thiagarajah, Papadopoulos and Verkman40), or by brain wet-to-dry weight ratios (Ref. Reference Papadopoulos and Verkman41).
Classification of brain oedema
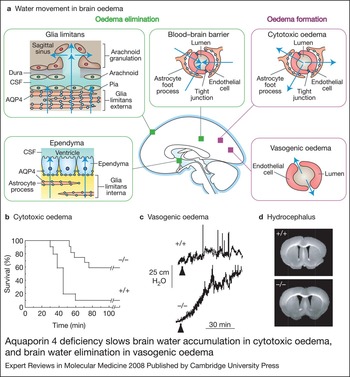
According to the Klatzo classification (Ref. Reference Klatzo42), brain oedema can be classified as cytotoxic (cell swelling) oedema or vasogenic (leaky vessel) oedema (Fig. 3a). In cytotoxic oedema, excess water moves from the vasculature into the brain parenchyma through an intact blood–brain barrier. The forces driving water flow to form cytotoxic oedema are osmotic, generated in water intoxication by reduced plasma osmolality, and in ischaemia and other pathologies by impaired Na+/K+-ATPase pump function with consequent Na+ and water accumulation in brain cells. When the blood–brain barrier becomes disrupted (as in brain tumour or abscess), water is driven by hydrostatic forces from the vasculature into the extracellular space of the brain in an AQP4-independent manner to form vasogenic oedema. Excess brain water is eliminated primarily through the glia limiting membrane into the CSF, and to a lesser extent back through the blood–brain barrier into the blood. The blood–brain barrier may become an important route for water elimination in obstructive hydrocephalus when other routes or water exit are impaired.
Aquaporin 4 deficiency slows brain water accumulation in cytotoxic oedema, and brain water elimination in vasogenic oedema. (a) Routes of water movement in brain during oedema formation and elimination. Oedema formation involves water movement through the blood–brain barrier, which is intact in cytotoxic oedema and disrupted in vasogenic oedema. Oedema elimination involves water movement across the glia limitans, ependyma and blood–brain barrier. Aquaporin 4 (AQP4) expression in glial cells is shown as blue circles. Oedema elimination schematics adapted from Ref. 46 (© 2004 FASEB), with permission. (b) Water intoxication model of cytotoxic oedema. AQP4-null mice show improved survival after acute water intoxication produced by intraperitoneal water injection. Adapted from Ref. 43. (c) Increased elevation in intracranial pressure in AQP4-null mice during continuous intraparenchymal infusion of artificial cerebrospinal fluid (0.5 µl/min). The recordings show intracranial pressure with fluid infusion begun at the arrows. Adapted from Ref. 46 (© 2004 FASEB), with permission. (d) Accelerated progression of hydrocephalus in AQP4 deficiency, as shown by the larger size of lateral ventricles in AQP4-null mice at 5 days after kaolin injection. Adapted from Ref. 48.

Cytotoxic brain oedema
Phenotype analysis of AQP4-null mice has provided compelling evidence for AQP4-facilitated brain water accumulation in cytotoxic oedema and for AQP4-facilitated brain water elimination in vasogenic oedema. Water intoxication, produced experimentally in mice by intraperitoneal water injection, is an example of pure cytotoxic oedema in which water is driven osmotically into the brain through an intact blood–brain barrier. AQP4-null mice have remarkably improved survival following water intoxication compared with wild-type mice (Fig. 3b), with reduced brain water accumulation and glial cell foot-process swelling (Ref. Reference Manley43). Reduced brain swelling and improved clinical outcome was also found in AQP4-null mice in a model of ischaemic stroke produced by transient middle cerebral artery occlusion (Ref. Reference Manley43) and in a model of bacterial meningitis produced by intracisternal streptococcus injection (Ref. Reference Papadopoulos and Verkman41). Reduced brain swelling in water intoxication was also reported in α-syntrophin-null mice, which secondarily manifest disrupted brain AQP4 expression (Ref. Reference Amiry-Moghaddam44). AQP4 inhibition may thus provide a new approach to reduce brain swelling in cytotoxic oedema, which would complement the currently available therapies, including decompressive craniectomy and intravenous mannitol administration – techniques that have changed little over the last century. Recently, greatly improved outcome with neuronal preservation was found in AQP4-null mice in a model of spinal cord compression injury (Ref. Reference Saadoun45), which is likely a consequence of reduced water entry into the spinal cord in AQP4 deficiency by a cytotoxic-like mechanism.
Vasogenic brain oedema and hydrocephalus
By contrast to these examples of cytotoxic oedema, AQP4 deletion in mice increases brain water accumulation and worsens outcome in vasogenic brain oedema and hydrocephalus. In a model of pure vasogenic oedema produced by continuous intraparenchymal fluid infusion, there was increased brain water accumulation with greater elevation in intracranial pressure in AQP4 deficiency (Ref. Reference Papadopoulos46) (Fig. 3c). Similar findings were obtained in other examples of vasogenic oedema, including brain tumour, brain abscess and focal cortical freeze injury (Refs Reference Papadopoulos46, Reference Bloch47), supporting the conclusion that in vasogenic oedema fluid is eliminated primarily by an AQP4-dependent route. Finally, in a kaolin-injection model of obstructive hydrocephalus, producing what has been called ‘interstitial oedema’, AQP4-null mice develop marked ventricular enlargement (Fig. 3d), probably due to reduced transependymal water clearance (Ref. Reference Bloch, Manley and Verkman48).
AQP4 is thus a major determinant of fluid movement into and out of the brain. Many brain pathologies, such as impact injury and toxic encephalopathies, produce brain oedema by a combination of cytotoxic and vasogenic mechanisms, each with a different time course and severity, so it is difficult a priori to predict whether and when AQP4 inhibition would be beneficial or detrimental.
Swelling of ocular tissues
As in the brain, AQPs in the eye are likely to be important in fluid balance and pathology in some ocular tissues. The eye expresses several AQPs at putative sites of fluid transport. The expression of MIP (major intrinsic protein, also referred to as AQP0) in lens fibre has been known for many years. Mutations in AQP0 in humans are associated with congenital cataracts (Ref. Reference Berry49), and recent data suggest the involvement of AQP0 in lens fibre cell adhesion (Ref. Reference Gonen and Walz1). AQP1 is expressed in corneal endothelium, and at sites of aqueous fluid production (ciliary epithelium) and outflow (trabecular meshwork). AQP3 is expressed in the conjunctival epithelium. AQP4 is expressed in Müller cells in retina, and is coexpressed with AQP1 in nonpigmented ciliary epithelium. AQP5 is expressed in corneal epithelia. This expression pattern provides indirect evidence for AQP involvement in intraocular pressure regulation (AQP1 and AQP4) (Ref. Reference Zhang, Vetrivel and Verkman22), corneal and lens transparency (AQP0, AQP1 and AQP5) (Refs Reference Ruiz-Ederra and Verkman50, Reference Thiagarajah and Verkman51), visual signal transduction (AQP4) (Ref. Reference Li, Patil and Verkman52), tear film homeostasis (AQP3 and AQP5) (Ref. Reference Levin and Verkman53), and conjunctival barrier function (AQP3) (Ref. Reference Levin and Verkman53). These possibilities have been examined systematically by phenotype analysis of AQP-knockout mice. We focus here on AQP involvement in ocular tissue swelling.
Cornea and lens swelling
In cornea, endothelial cell AQP1 and epithelial cell AQP5 are involved in corneal stromal water balance, and thus maintenance of corneal transparency. Corneal thickness is reduced compared with normal in AQP1-null mice and increased in AQP5-null mice (Ref. Reference Thiagarajah and Verkman51). In an experimental model of corneal swelling produced by exposure of the ocular surface to hypo-osmolar fluid, the recovery of corneal transparency and thickness after hypotonic swelling was greatly delayed in AQP1-null mice. AQP1 is also expressed in the epithelial cell layer surrounding the lens, where it plays a role in lens water balance (Ref. Reference Ruiz-Ederra and Verkman50). Although AQP1 deletion did not alter baseline lens morphology or transparency, loss of lens transparency was greatly increased in an in vitro model of cataractogenesis produced by incubation of lenses in high-glucose solutions. Cataract formation was also greatly accelerated in AQP1-null mice in an in vivo model of cataractogenesis produced by acetaminophen toxicity. Notwithstanding lack of a clear-cut mechanism for these observations, the results suggest the interesting possibility of reducing corneal and lens oedema by AQP1 upregulation.
Retinal swelling
There is also evidence implicating AQP4 in retinal swelling. AQP4 is expressed in Müller cells in retina, where it is involved in light signal transduction (see section ‘Neural signal transduction’ below). Based on the protection against cytotoxic brain oedema conferred by AQP4 gene deletion, the possibility was tested that AQP4 deletion protects the retina in a transient ischaemia–reperfusion model produced by 45–60 min elevation in intraocular pressure to 120 mmHg (Ref. Reference Da and Verkman54). Retinal structure and cell number were remarkably preserved in AQP4-null mice, particularly in the inner nuclear and plexiform layers of retina where Müller cells are concentrated. Retinal function and cell survival were also improved in AQP4-null mice, with electroretinographic evidence of significant attenuation of the reduction in b-wave amplitudes. Whether the neuroprotective effects of AQP4 deletion in retina can be exploited in the therapy of human ocular disease remains to be explored.
Cell migration
Impaired angiogenesis in AQP1 deficiency
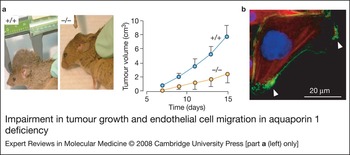
Phenotype analysis of AQP1-null mice led to the discovery of AQP involvement in cell migration. Given the expression of AQP1 in tumour microvessels (Ref. Reference Endo55), the involvement of AQP1 in tumour angiogenesis was tested (Ref. Reference Saadoun56). AQP1 deletion in mice reduced tumour growth following subcutaneous injection of melanoma cells (Fig. 4a), which was associated with increased tumour necrosis and reduced blood-vessel formation within the tumour bed. In experiments to elucidate the mechanism of defective tumour angiogenesis in AQP1 deficiency, it was found that cultured aortic endothelial cells from AQP1-null mice migrated several-fold slower towards a chemotactic stimulus than AQP1-expressing endothelial cells. Other processes involved in angiogenesis, including endothelial cell proliferation and adhesion, were not impaired in AQP1 deficiency. Transfection of AQP1 or other AQPs into cells that do not express AQPs increased their migration, suggesting the involvement of AQP-facilitated cell membrane water permeability in cell migration. In the migrating cells, AQP1 becomes polarised to the front end of cells (Fig. 4b), and is associated with increased turnover of cell membrane protrusions (lamellipodia), suggesting that AQPs at the leading edge of migrating cells facilitate their migration.
Impairment in tumour growth and endothelial cell migration in aquaporin 1 deficiency. Aquaporin 1 (AQP1) deletion impairs tumour angiogenesis because, in part, of reduced migration of endothelial cells. (a, left) Reduced tumour size in AQP1-null mouse, two weeks after subcutaneous injection of one million B16F10 melanoma cells. (a, right) Tumour growth data (ten mice per group). (b) AQP1 protein (green) polarisation to lamellipodia (arrows) in a migrating CHO cell. Graph in part a and image in part b reprinted from Ref. 56.

Reduced tumour spread, glial scarring and wound healing in AQP deficiency
Follow-up experiments showed that AQPs facilitate cell migration independent of AQP and cell type. AQP4 facilitates astrocyte cell migration (Refs Reference Saadoun57, Reference Auguste58), AQP3 facilitates migration of corneal epithelial cells (Ref. Reference Levin and Verkman59) and epidermal cells (Ref. Reference Hara-Chikuma and Verkman60), and AQP1 facilitates the migration of cultured renal proximal tubule cells (Ref. Reference Hara-Chikuma and Verkman61), B16F10 melanoma and 4T1 breast cancer cells (Ref. Reference Hu and Verkman62). These studies also demonstrated that AQP-facilitated cell migration participates not only in angiogenesis but also in other processes including tumour cell spread, glial scar formation, and wound healing. AQP1 expression in tumour cells increases their migration across endothelial barriers, local invasiveness and metastatic potential (Ref. Reference Hu and Verkman62). AQP4 deletion in glial cells reduces their migration toward a stab wound in vivo (Ref. Reference Auguste58) and the rate of glial scar formation (Ref. Reference Saadoun57). AQP3 deletion impairs closure of cutaneous wounds (Ref. Reference Hara-Chikuma and Verkman60) and corneal wounds (Ref. Reference Levin and Verkman59). Although not yet tested, AQPs may also be involved in organ regeneration and immune cell chemotaxis.
Mechanisms of AQP-facilitated cell migration
The enhanced cell migration found for multiple structurally different AQPs, independent of their modulation method (transfection, knockout, RNA inhibition), suggests that AQP-facilitated water transport is the responsible mechanism. AQPs might accelerate cell migration by facilitating rapid changes in cell volume that accompany changes in cell shape as cells squeeze through the narrow extracellular space. Water flow across the cell membrane may also allow migrating cells to generate hydrostatic forces to push apart adjacent stationary cells. This mechanism, however, does not account for the polarisation of AQPs to the front end of migrating cells or for AQP enhancement of lamellipodial dynamics, which support a role for water movement across the leading edge of migrating cells, as was proposed previously (Ref. Reference Condeelis63). According to this hypothesis, actin depolymerisation and ion influx increase cytoplasmic osmolality at the front end of the migrating cell, driving water influx across the plasma membrane (Fig. 1c). Water influx would thus expand the adjacent plasma membrane by increased local hydrostatic pressure, followed by actin repolymerisation to stabilise the cell membrane protrusion. There is evidence that regional hydrostatic pressure changes within cells do not equilibrate throughout the cytoplasm on scales of 10 µm and 10 s (Ref. Reference Charras64), and could thus contribute to the formation of localised cell membrane protrusions. Further studies, including direct measurements of water flow across the leading edge of migrating cells, are needed to validate these ideas.
Neural signal transduction
Impaired neural signal transduction in AQP4 deficiency
AQP4 appears to play an unexpected role in neural function. AQP4 is expressed in supportive cells adjacent to electrically excitable cells, as in glia versus neurons in brain and spinal cord, Müller versus bipolar cells in retina, and supportive versus hair cells in the inner ear. Electrophysiological measurements indicated impaired auditory and visual signal tranduction in AQP4-null mice, seen as increased auditory brainstem response thresholds (Refs Reference Li and Verkman65, Reference Mhatre66) and reduced electroretinographic potentials (Ref. Reference Li, Patil and Verkman52). In brain, seizure susceptibility in response to the convulsant pentylenetetrazol was reduced in AQP4-null mice (Ref. Reference Binder67). In freely moving mice, electrically induced seizures following hippocampal stimulation, as measured by electroencephalography, showed greater threshold and remarkably longer duration in AQP4-null mice (Ref. Reference Binder68). In agreement with these findings, α-syntrophin-deficient mice developed more-severe behavioural seizures than wild-type mice following hyperthermia (Ref. Reference Amiry-Moghaddam69). Recently, defective olfaction was found in AQP4-null mice as demonstrated in behavioural studies and odorant-induced electro-olfactogram responses (Ref. Reference Lu70).
Possible mechanisms of impaired neuroexcitation in AQP4 deficiency
The mechanisms for altered neuroexcitation in AQP4 deficiency are unclear at present (Fig. 1d). Delayed K+ uptake from brain extracellular space (ECS) in AQP4 deficiency has been suggested, which may account for the prolonged seizure phenotype. Measurements of [K+] in brain cortex in living mice using K+-sensitive microelectrodes showed significant slowing of K+ clearance following electrical stimulation (Ref. Reference Binder68). Using a K+-sensitive fluorescent dye applied directly to the brain in living mice following craniectomy, altered K+ wave dynamics were found in a cortical spreading depression model of neuroexcitation, again with delayed K+ clearance (Ref. Reference Padmawar, Yao and Bloch71). How delayed K+ reuptake from the ECS is related to AQP4 deficiency is not known. It has been proposed that AQP4 associates in a functionally significant manner with Kir4.1, such that that reduced K+-channel function in AQP4 deficiency might account for the delay in K+ clearance. However, recent patch-clamp studies in astroglia (Ref. Reference Zhang and Verkman16) and Müller cells (Ref. Reference Ruiz-Ederra, Zhang and Verkman17) provide evidence against this mechanism. Another possible mechanism involves ECS expansion in AQP4 deficiency, which may account in part for reduced seizure susceptibility and prolonged seizure duration in AQP4-null mice. An expanded ECS would provide a larger aqueous volume to dilute K+ released into the ECS during neuroexcitation, thereby slowing changes in ECS K+ concentration. There is evidence for an expanded ECS in AQP4 deficiency from cortical surface photobleaching (Ref. Reference Binder72) and microfibreoptic photobleaching (Ref. Reference Zador73) measurements of the diffusion of fluorescently labelled macromolecules in mouse brain. It remains unclear, however, whether ECS expansion in AQP4 deficiency could account fully for the altered ECS K+ dynamics. Perhaps reduced water permeability in AQP4 deficiency may be responsible for defective neuroexcitation function by a mechanism involving impaired cell volume responses. Alternative possible mechanisms include AQP4 interaction with key ion channels, perhaps through PDZ-domain interactions, and maladaptive regulation in AQP4 deficiency of other transporters involved in neuroexcitation.
Glycerol transport by the aquaglyceroporins
For many years the physiological significance of glycerol transport by the aquaglyceroporins was unclear. Phenotype studies of mice lacking aquaglyceroporins have produced a number of remarkable findings for the involvement of AQP3 in epidermal biology and cell proliferation, and of AQP7 in adipocyte metabolism. A recent report on AQP9-null mice showed a subtle phenotype suggestive of impaired hepatic glycerol uptake (Ref. Reference Rojek74), although the mechanism remains to be established as does its proposed significance to diabetes.
AQP3 and skin function
The stratum corneum (SC) is the most superficial layer of skin, consisting of a lamellar lipid layer and terminally differentiated keratinocytes that originate from actively proliferating keratinocytes in lower epidermis. SC hydration is an important determinant of skin appearance and physical properties, and depends on several factors including the external humidity, and SC structure, lipid/protein composition, barrier properties, and concentration of water-retaining osmolytes.
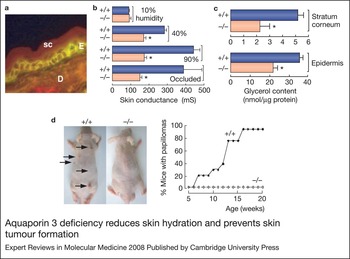
AQP3 is expressed strongly in the basal layer of keratinocytes (Fig. 5a). SC hydration is reduced in AQP3-null mice as measured by high-frequency skin conductance (Ref. Reference Ma75) (Fig. 5b), which is a linear index of SC water content. Exposure of mice to high humidity or occlusion increased SC hydration in wild-type, but not AQP3-null mice, indicating that water transport through AQP3 is not a rate-limiting factor in transepidermal water loss. If reduced SC hydration is related to a balance between evaporative water loss from the SC and water replacement through AQP3-containing basal keratinocytes, then preventing water loss by high humidity or occlusion should have corrected the defect in SC hydration in AQP3-null mice, which it did not. Skin phenotype analysis also indicated delayed barrier recovery after SC removal by tape-stripping in AQP3-null mice, as well as decreased skin elasticity and delayed wound healing (Ref. Reference Ma75).
Aquaporin 3 deficiency reduces skin hydration and prevents skin tumour formation. Aquaporin 3 (AQP3) is expressed in the basal layer of keratinocytes in normal skin, and its deletion in mice produces dry skin because of reduced skin glycerol content, and resistance to tumourigenesis. (a) Immunofluorescence showing AQP3 expression (yellow/green) in basal layer of epidermis in mice. Abbreviations: D, dermis; E, epidermis; SC, stratum corneum. Image reproduced from Ref. 75 (© 2008 The American Society for Biochemistry and Molecular Biology), with permission. (b) Reduced statum corneum water content in AQP3-null mice, measured by high-frequency skin surface conductance (five mice per group, *P < 0.01). Skin conductance was measured after 24 h exposure to relative humidity of 10, 40 or 90%; ‘occluded’ indicates a plastic occlusion dressing that prevents evaporative water loss. Reprinted from Ref. 75 (© 2008 The American Society for Biochemistry and Molecular Biology), with permission. (c) Reduced glycerol content in stratum corneum and epidermis of AQP3-null mice (*P < 0.01). Adapted from Ref. 76 (© 2008 The American Society for Biochemistry and Molecular Biology), with permission. (d, left) Absence of cutaneous papillomas in AQP3-null mice treated with an initiator (once) and twice-weekly applications of a promoter for 20 weeks. Arrows point to papillomas. (d, right) Percentage of mice with papillomas after initiator treatment. Part d adapted from Ref. 78 (© 2008 American Society for Microbiology), with permission.

A systematic analysis of SC and epidermal ultrastructure and composition revealed reduced glycerol content in SC and epidermis (Fig. 5c), with normal glycerol in dermis and serum, suggesting reduced glycerol transport from blood into the epidermis in AQP3 deficiency through the basal keratinocytes (Fig. 1e). No significant differences in wild-type versus AQP3-null mice were found in SC structure, cell turnover, lipid profile, protein content, and the concentrations of amino acids, ions and other small solutes (Ref. Reference Hara, Ma and Verkman76). These observations suggest that reduced epidermal and SC glycerol content is responsible for the abnormal skin phenotype in AQP3-null mice. Because glycerol is a water-retaining osmolyte, or ‘natural moisturising factor’, reduced SC glycerol reduces SC hydration and skin elasticity; furthermore, because of its biosynthetic role in the epidermis (see next section), reduced epidermal glycerol is predicted to delay barrier recovery function and wound healing. In support of this hypothesis, glycerol replacement by topical or systemic routes corrected the phenotype abnormalities in AQP3-null mice, and SC glycerol content correlated well with SC water content (Ref. Reference Hara and Verkman77). These findings indicate an important role for AQP3 and glycerol in epidermal function, providing a rational scientific basis for the long-standing practice of including glycerol in cosmetic and skin medicinal preparations.
AQP3 and cell proliferation
Recent data support the unexpected involvement of AQP3 in cell proliferation in certain cell types. Remarkably, mice lacking AQP3 failed to produce cutaneous papillomas in an inducer–promoter model of skin cancer, whereas wild-type mice produced multiple tumours (Fig. 5d) (Ref. Reference Hara-Chikuma and Verkman78). The motivation for studying AQP3 and skin tumours was the strong expression of AQP3 in basal cells in human skin squamous cell carcinomas, and data showing AQP3-facilitated cell proliferation in several cell types. Wound healing and corneal epithelial cell proliferation are impaired in AQP3 deficiency (Ref. Reference Levin and Verkman59), as is the healing of cutaneous wounds (Ref. Reference Hara-Chikuma and Verkman60) and regeneration of the colonic epithelium in experimental colitis (Ref. Reference Thiagarajah, Zhao and Verkman79).
Experiments to establish the cellular mechanisms responsible for the impaired tumourigenesis phenotype showed impaired promoter-induced cell proliferation in AQP3-null or -knockdown keratinocyte cell cultures. AQP3-deficient keratinocytes had reduced content of glycerol, its metabolite glycerol-3-phosphate, and ATP, without impairment of mitochondrial function. Glycerol supplementation or AQP3 adenoviral infection (but not AQP1 adenoviral infection) corrected the defects in keratinocyte proliferation and increased ATP. Further studies revealed correlations between cell proliferation, and ATP and glycerol content. It was proposed that AQP3-facilitated glycerol transport is an important determinant of epidermal cell proliferation and tumourigenesis by a mechanism in which glycerol is a key regulator of cellular ATP energy (Fig. 1f). The mechanism also shows glycerol biosynthetic incorporation into lipids, and positive feedback in which cell proliferation increases AQP3 expression. These findings have potential implications in the prevention and therapy of skin and other cancers, and raise concerns in the use of cosmetics containing ingredients that increase epidermal AQP3 expression whose goal is to improve skin moisture and appearance (Ref. Reference Verkman80).
AQP7 and fat metabolism
AQP7 is expressed in the plasma membrane of adipocytes. Although wild-type and AQP7-null mice grow at similar rates as assessed by mouse weight, over time AQP7-null mice develop significantly greater fat mass compared with wild-type mice (Ref. Reference Hara-Chikuma81). Adipocytes from adult AQP3-null mice are several-fold larger than those from wild-type mice, suggesting that the greater fat mass in the AQP7-null mice is a consequence of adipocyte hypertrophy. Concentrations of glycerol and triglycerides in serum were unaffected by AQP7 deletion, but adipocyte glycerol and triglyceride concentrations were significantly elevated in AQP7-null mice, suggesting a mechanism for the progressive adipocyte hypertrophy in AQP7 deficiency. Plasma membrane glycerol permeability was reduced significantly in adipocytes of AQP7-null mice, as was glycerol release. However, lipolysis, as measured by free fatty acid release from isolated adipocytes, was similar in wild-type and AQP7-deficient mice, as was lipogenesis, as assayed from the incorporation of [14C]glucose into triglycerides. From these results, we proposed a simple mechanism for progressive triglyceride accumulation in AQP7-deficient adipocytes (Fig. 1g), in which reduced plasma membrane glycerol permeability in AQP7 deficiency produces an increased glycerol concentration in adipocyte cytoplasm, resulting in increased glycerol-3-phosphate and triglyceride biosynthesis. Similar conclusions about fat metabolism in AQP7 deficiency were reported independently (Ref. Reference Hibuse82), although with some relatively minor differences in phenotype findings compared with our results. It was speculated that AQP7 plays an important role in the pathogenesis of human obesity (reviewed in Ref. Reference Funahashi83), although whether this is the case remains to be determined.
Clinical implications/applications
Notwithstanding differences in mouse versus human physiology, the involvement of AQPs in major physiological processes in mouse models likely has a number of clinical implications. The requirement of AQPs for the formation of a concentrated urine suggests that AQP inhibitors, or ‘AQP-aquaretics’, would act as unique diuretics with potential utility in diuretic-refractory oedematous states such as severe congestive heart failure. Inhibitors of various AQPs are also predicted to have potential efficacy in reducing water entry into the brain in cytotoxic oedema, in improving the outcome following spinal cord injury, in reducing aqueous fluid production in glaucoma, in inhibiting glial scar formation, in reducing angiogenesis and tumour spread, in reducing cell proliferation in certain cancers, and in increasing seizure threshold in epilepsy. Drugs that increase AQP function, acting for example by increasing AQP expression, are predicted to have potential efficacy in reducing fat mass in obesity, in accelerating brain water clearance in vasogenic oedema, and in promoting wound healing and tissue regeneration following injury. Validation of these predictions will require the development of appropriate AQP-specific modulators. Another AQP-related clinical application is in disease diagnosis, as demonstrated for serum AQP4 autoantibodies in diagnosing the optic–spinal form of multiple sclerosis (Ref. Reference Lennon84), and for urinary AQP2 protein in distinguishing among various aetiologies of nephrogenic diabetes insipidus (Ref. Reference Rai85). Other AQP-related disease markers are likely to be identified. The possibility of AQP polymorphisms contributing to human disease is largely unexplored. It would be worthwhile, for example, to investigate polymorphisms in AQP4 in brain diseases such as hydrocephalus, in AQP3 in skin diseases, and in various AQPs in cancer. Last, the modulation of AQP expression in disease states may be clinically important. In some cases altered AQP expression appears to be a maladaptive response, as in the case of reduced renal AQP2 expression in various forms of polyuria, which further impairs urinary concentrating ability (Ref. Reference Kwon86), and AQP4 upregulation in various aetiologies of brain swelling, which may exacerbate brain water accumulation. There is an expanding literature on altered AQP expression in human diseases, with evidence for altered AQP3 expression in skin diseases (Ref. Reference Hara-Chikuma and Verkman87), AQP4 expression in epilepsy (Ref. Reference Lee88), and AQP7 expression in obesity and metabolic diseases (Ref. Reference Ceperuelo-Mallafré89). In most cases, however, it will likely be difficult to establish the cellular mechanisms and clinical significance of such observations.
Research in progress and outstanding research questions
There remain many unanswered questions about the roles of AQPs in mammalian physiology, as well as exciting opportunities for clinical applications. Although water transport has been studied for many decades and AQP proteins were identified in the early 1990s, many of the new AQP cellular functions were recognised only in the past few years, so it is likely that additional new AQP functions will be discovered. Much work remains in the precise elucidation of cellular mechanisms responsible for AQP involvement in cell migration, neural signal transduction and in vasogenic brain oedema, and in the precise role of the aquaglyceroporins in cellular metabolism and proliferation. Finally, as mentioned in the previous section, identification of chemical AQP-selective modulators is a high priority in ongoing research, as small-molecule AQP inhibitors and upregulators have the potential to serve as new tools to study AQP function and as potential therapies for major human diseases.
Acknowledgements and funding
The contributions of many collaborators and trainees who shaped the ideas presented here are greatly acknowledged: Drs D. Binder, M. Hara-Chikuma, T. Ma, G. Manley, M. Papadopoulos, S. Saadoun, Y. Song, J. Thiagarajah, B. Yang and many others. The AQP mechanism and mouse phenotype studies were supported primarily by the National Institutes of Health, through awards R37 DK35124, R37 EB00415, R01 EY13574, R01 HL59198, R01 HL73856, and P30 DK72517.