Introduction
Laryngoplastic phonosurgery is commonly performed to improve laryngeal incompetence in patients with vocal fold paralysis and/or vocal fold atrophy. Many surgical techniques to correct laryngeal incompetence have been devised.
There are three major categories of laryngoplastic phonosurgery including: endoscopic phonosurgery, external laryngoplastic phonosurgery such as laryngeal framework surgery and arytenoid adduction, and nerve-muscle surgery of the larynx.Reference Woo1
Arytenoid adduction is rarely performed alone and is usually a supplemental surgical procedure used with medialisation laryngoplasty to correct a large posterior glottal gap. There is some controversy as to how much the posterior gap can be closed by medialisation laryngoplasty alone.
Injection laryngoplasty is commonly performed to improve glottal incompetence in patients with vocal fold paralysis and/or vocal fold atrophy. In order to improve a large posterior glottal gap and/or aspiration, injections should not only be administered at the membranous portion of the vocal fold in the thyroarytenoid muscle, but also at the cartilaginous portion of the vocal fold to make adduction arytenopexy possible. Regarding the cartilaginous portion of the vocal fold, the precise injection location is unclear and commonly described as ‘lateral to the vocal process’.Reference Laccourreye, Paczona, Ageel, Hans, Brasnu and Crevier-Buchman2, Reference Rosen and Simpson3
Surgical histoanatomy for adduction arytenopexy with injection laryngoplasty was investigated using whole-organ serial laryngeal section study.
Materials and methods
Ten adult human larynges (from five men and five women) obtained from autopsy cases were investigated using the whole-organ serial section technique. The specimens were fixed in 10 per cent formalin, decalcified in 5 per cent hydrochloric acid, dehydrated in graded concentrations of ethanol and embedded in paraffin. Transverse and coronal serial sections were made.
Haematoxylin and eosin stain and elastica van Gieson stain were employed for each section, and microscopic observation was performed.
Results
The origin of the thyroarytenoid muscle is the inner surface of the thyroid cartilage, and the injection laryngoplasty material is inserted into the muscular process and oblong fovea of the arytenoid cartilage (Figure 1).
Anterior view of the arytenoid and cricoid cartilages. A = injection route lateral to oblong fovea; B = injection route lateral to triangular fovea
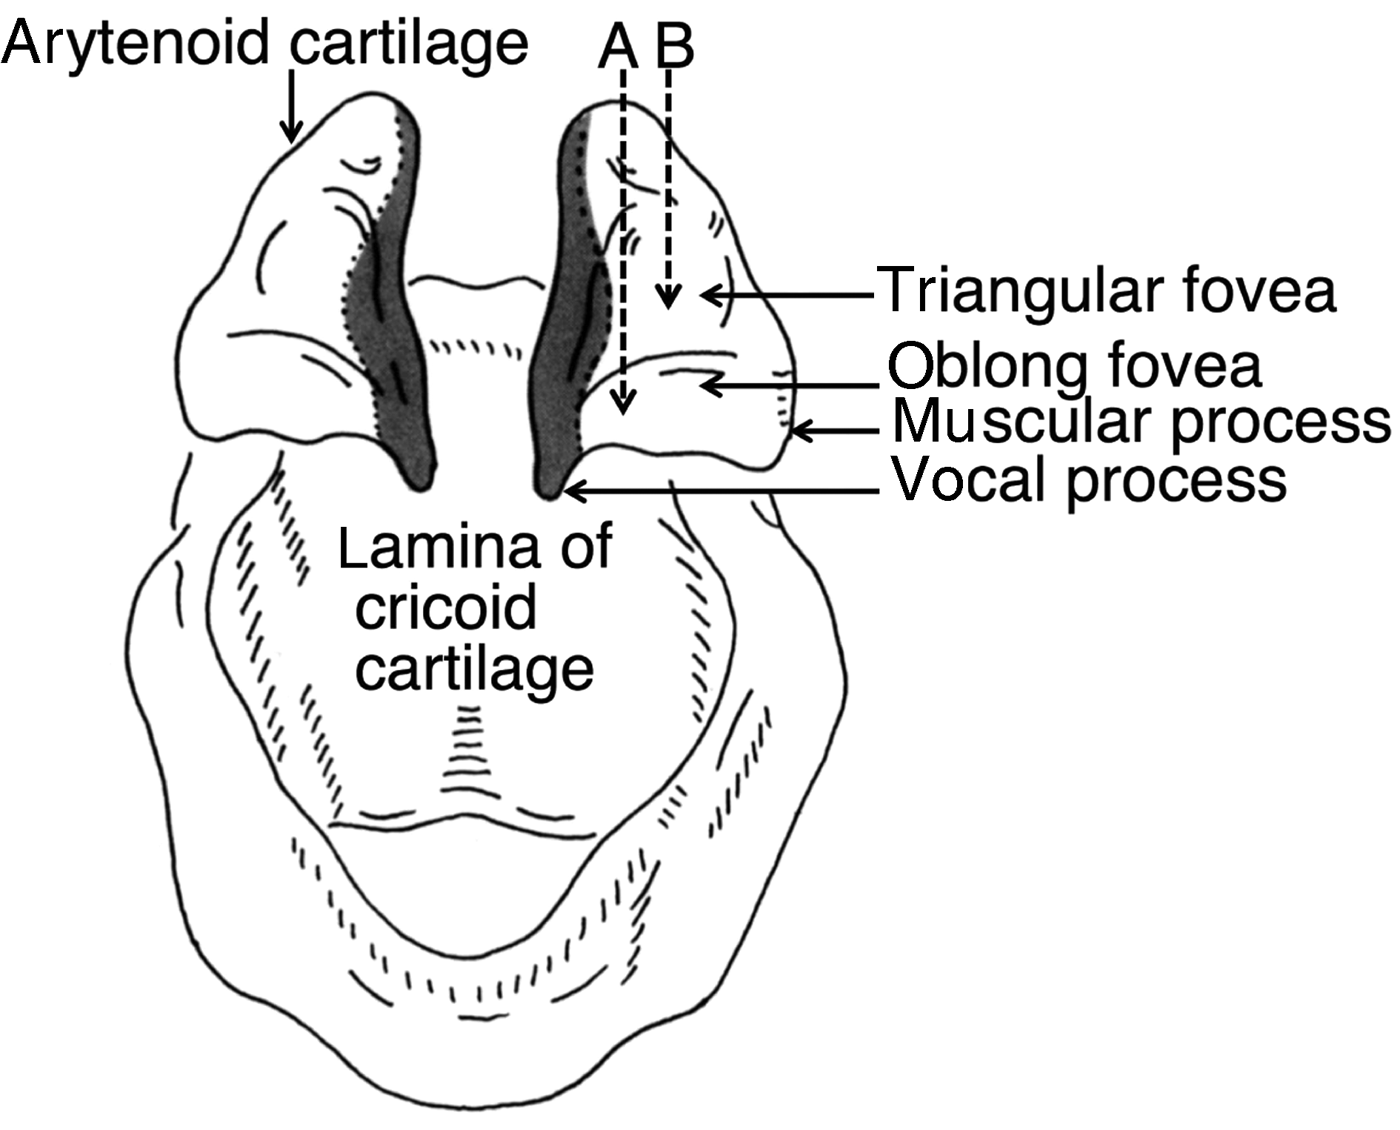
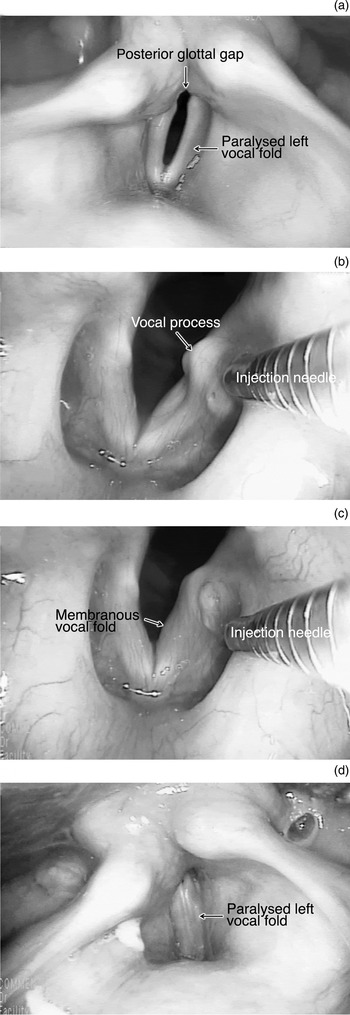
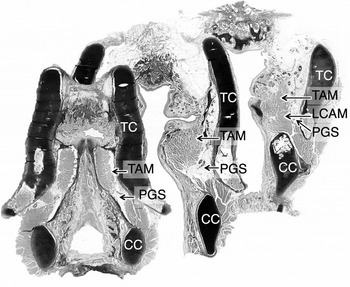
Figure 2b shows an injection into the thyroarytenoid muscle at the cartilaginous portion of the vocal fold. The vertical thickness of the posterior aspect (anterolateral to the oblong fovea) of the thyroarytenoid muscle was relatively thin (3.4 ± 0.4 mm), especially in females (3.2 ± 0.3 mm) (Figure 3). Consequently, when adduction arytenopexy by injection laryngoplasty is performed at the cartilaginous portion of the vocal fold (injecting into the thyroarytenoid muscle anterolateral to the oblong fovea of the arytenoid cartilage), care should be taken to ensure the correct depth of needle placement.
Transnasal injection laryngoplasty by use of video endoscopy under topical anaesthesia, showing: (a) pre-operative endoscopic view from above, during phonation; (b) injection being administered in the thyroarytenoid muscle at the cartilaginous portion of the vocal fold; (c) injection being given in the thyroarytenoid muscle at the membranous portion of the vocal fold; and (d) post-operative endoscopic view from above, during phonation.

Three-dimensional structure of the thyroarytenoid muscle shown by coronal whole-organ serial laryngeal sections. Note that the anterior aspect of the thyroarytenoid muscle was thick vertically. However, the posterior aspect (lateral to the vocal process and oblong fovea) of the thyroarytenoid muscle was thin vertically. TC = thyroid cartilage; TAM = thyroarytenoid muscle; LCAM = lateral cricoarytenoid muscle; PGS = paraglottic space; CC = cricoid cartilage
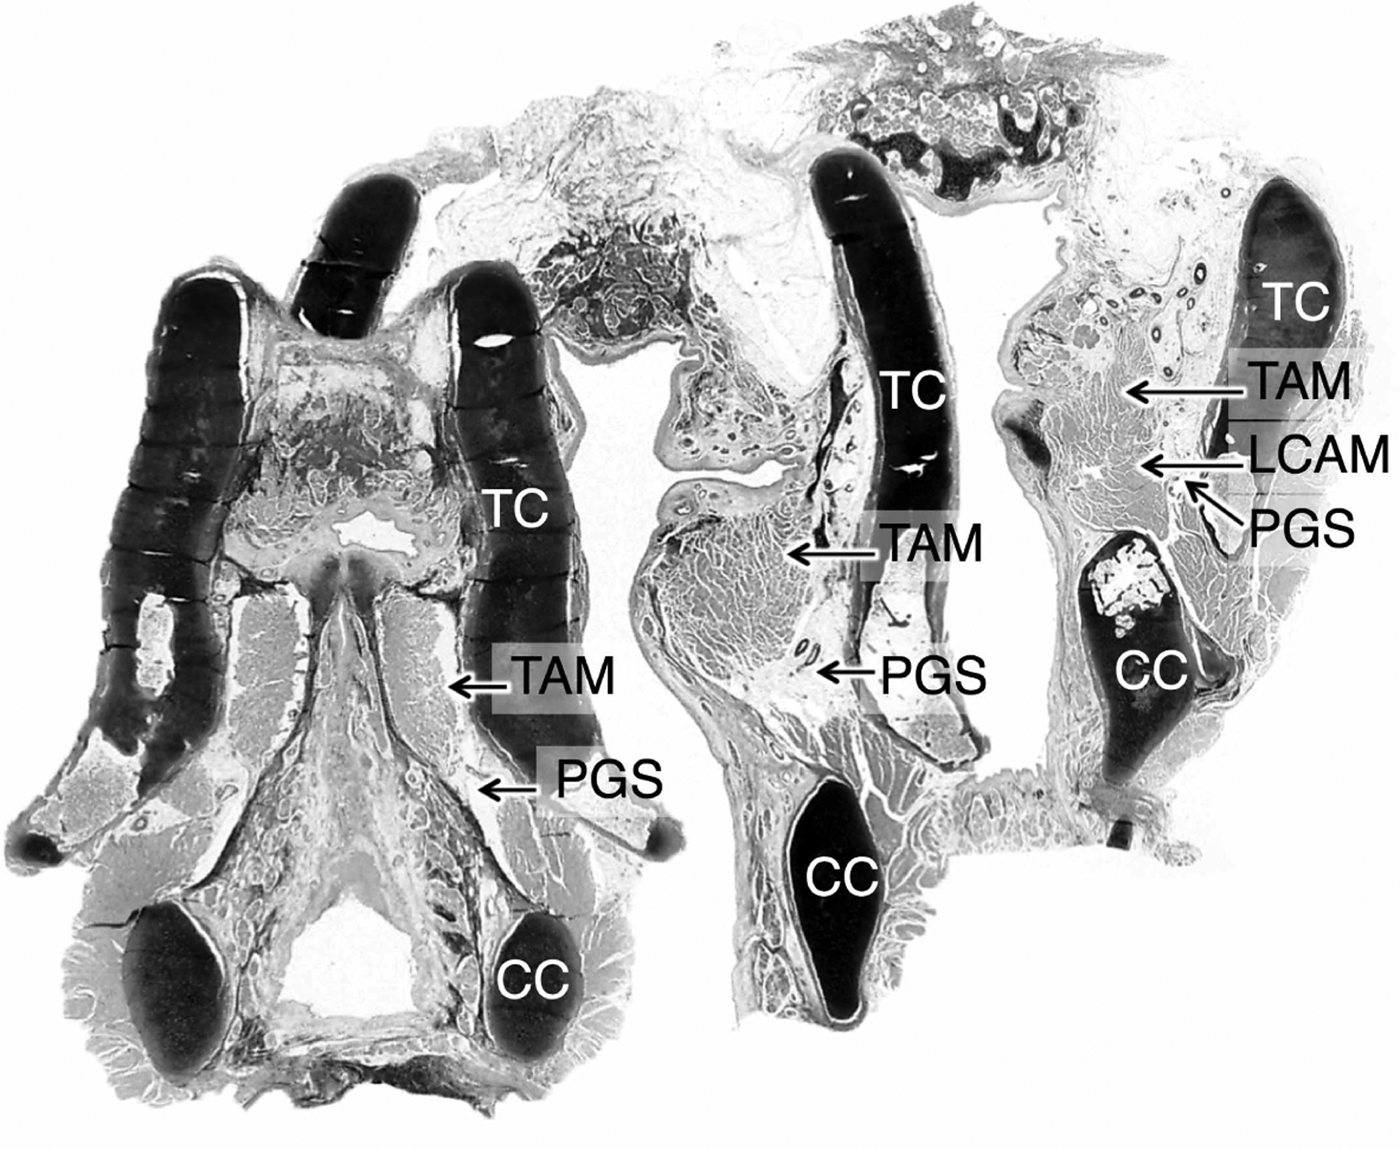
If the needle is placed too deep, augmentation substances will be injected into the lateral cricoarytenoid muscle, located beneath the thyroarytenoid muscle, or into the paraglottic space, located inferolateral to the thyroarytenoid muscle (Figure 4).
Schema of the three-dimensional structure of the left thyroarytenoid muscle and surrounding tissue. 1 = injection being administered in the thyroarytenoid muscle at the membranous portion of the vocal fold; 2 = injection being given in the thyroarytenoid muscle at the cartilaginous portion of the vocal fold
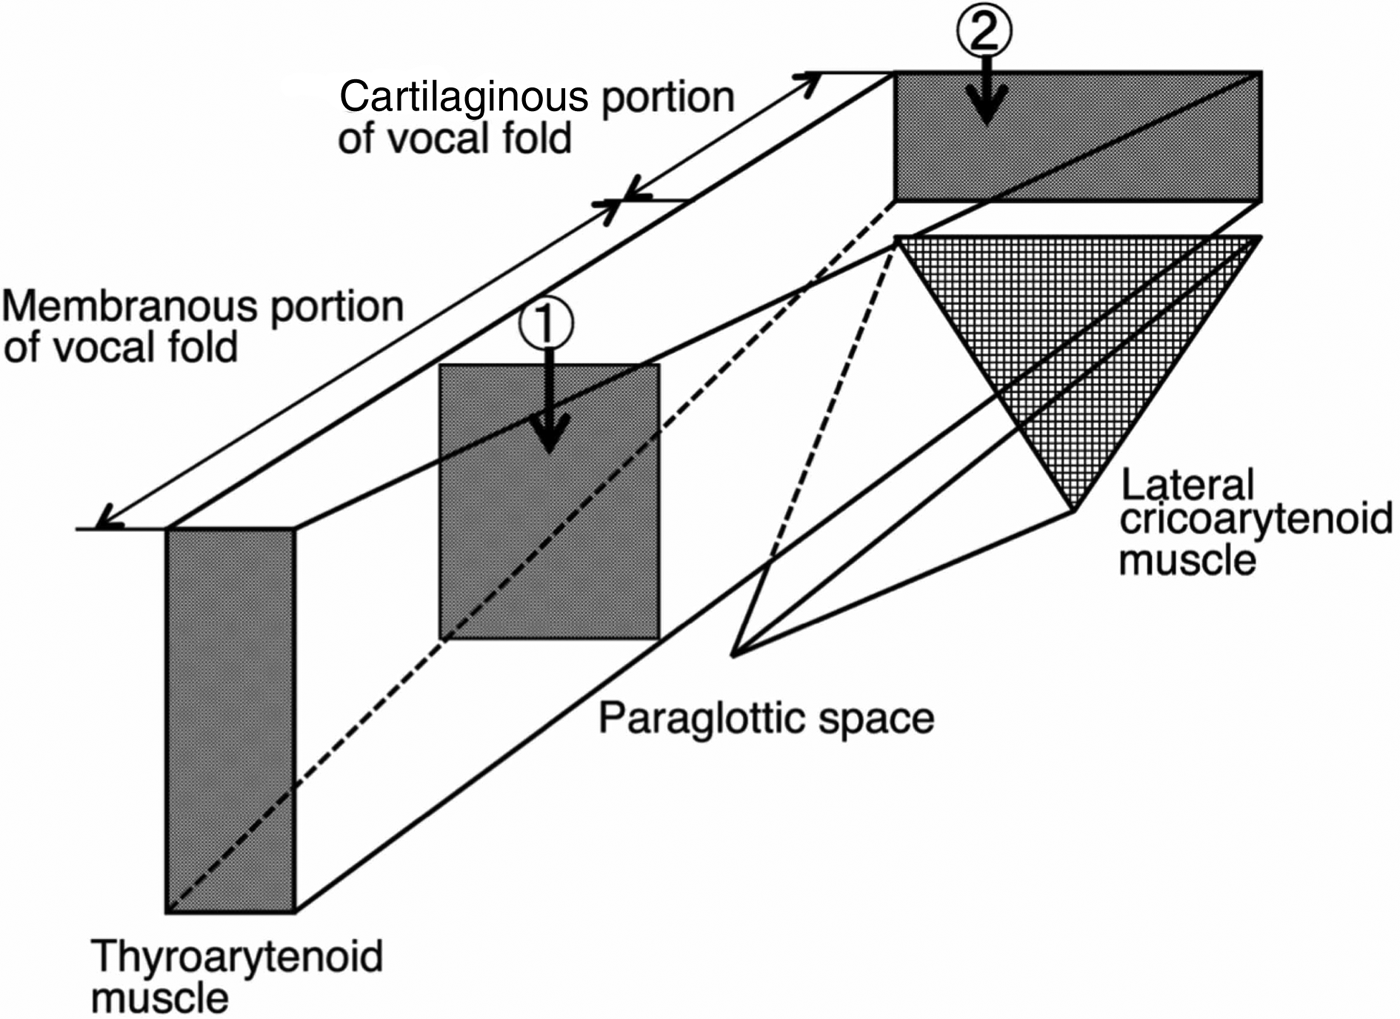
Figure 2c shows injection into the thyroarytenoid muscle at the membranous portion of the vocal fold. The anterior aspect of the thyroarytenoid muscle was relatively thick vertically (Figure 3). However, if the needle is placed too deep at the membranous portion of the vocal fold, augmentation substances will be injected into the paraglottic space located inferior to the thyroarytenoid muscle (Figure 4).
Discussion
The arytenoid cartilage is tetrahedron shaped, and the bottom surface forms the cricoarytenoid joint. The anterolateral surface of the arytenoid cartilage has two foveae: the oblong fovea and the triangular fovea (Figure 1). The oblong fovea faces the anterolateral direction, and the triangular fovea faces the anterior direction. The posterior part of the thyroarytenoid muscle attaches to the oblong fovea and muscular process of the arytenoid cartilage.
Cricoarytenoid joint
The mechanics of the cricoarytenoid joint control abduction and adduction of the vocal fold.Reference Von Leden and Moore4 The structural arrangement of the cricoarytenoid joint permits two principle types of motion: a rocking or rotating movement around the axis of the joint, and a linear glide parallel to this axis.Reference Von Leden and Moore4 The principle axis of the joint extends in a dorsomediocranial and ventrolaterocaudal direction.Reference Von Leden and Moore4
From anatomical and physiological perspectives, forces from the anterolateral to the posteromedial direction allow the arytenoid cartilage to glide, and forces from the superolateral to the inferomedial direction rock and rotate the arytenoid cartilage. Consequently, both forces make adduction arytenopexy possible.
Vocal fold atrophy
Atrophy is a decrease in the size and function of a cell, tissue or organ.Reference Rubin, Farber, Rubin and Farber5 Clinically, it is often recognised as a diminution in the size or function of an organ.Reference Rubin, Farber, Rubin and Farber5
Vocal fold atrophy can therefore be defined as a decrease in the size and function of the vocal fold.Reference Sato6 The human vocal fold has a layered structure consisting of the epithelium, the superficial, intermediate and deep layers of the lamina propria, and the vocalis muscle.Reference Hirano7, Reference Hirano and Sato8 The superficial layer is referred to as Reinke's space. The vocal ligament consists of intermediate and deep layers. This layered structure is very important for vibration.Reference Hirano7 Therefore, vocal fold atrophy can also be defined as a diminution in the size of each portion of the layered structure and in the function of the vocal fold.Reference Sato6
Vocal fold atrophy and augmentation surgery
As mentioned above, to improve a large posterior glottal gap and/or aspiration using injection laryngoplasty, injections should be administered at the cartilaginous portion of the vocal fold, as well as at the membranous portion of the vocal fold in the thyroarytenoid muscle, to make adduction arytenopexy possible. Regarding the cartilaginous portion of the vocal fold, the precise injection location is unclear and commonly described as ‘lateral to the vocal process’.Reference Laccourreye, Paczona, Ageel, Hans, Brasnu and Crevier-Buchman2, Reference Rosen and Simpson3
The ultimate goal of augmentation surgery is to expand the atrophic tissue and/or organ, and to restore function. Consequently, when injection laryngoplasty is performed, the injection should be administered in the atrophic thyroarytenoid muscle at the cartilaginous portion of the vocal fold. At our institution, the injection is given in the atrophic thyroarytenoid muscle anterolateral to the oblong fovea of the arytenoid cartilage.Reference Sato, Umeno and Nakashima9–Reference Sato, Umeno and Nakashima11
This investigation revealed that the vertical thickness of the posterior aspect of the thyroarytenoid muscle is thin. Consequently, when adduction arytenopexy by injection laryngoplasty is performed (injecting into the thyroarytenoid muscle anterolateral to the oblong fovea of the arytenoid cartilage), care should be taken to ensure the correct depth of needle placement. If the needle is placed too deep, augmentation substances will be injected into the lateral cricoarytenoid muscle, located beneath the thyroarytenoid muscle, or into the paraglottic space, located inferolateral to the thyroarytenoid muscle. Adduction arytenopexy using injection laryngoplasty cannot then be achieved.
There are a few injectable biomaterials available for vocal fold augmentation surgery. We chose calcium hydroxylapatite and atelocollagen because they are commonly used for transendoscopic injection laryngoplasty. Breathy hypophonia and glottal incompetence were improved in all cases within a day of this surgical procedure. However, injected atelocollagen may be resorbed with time (24 months’ follow up).
Advantages of technique
It is generally said that a patient with a unilateral midfold gap is the ideal candidate for medialisation laryngoplasty alone.Reference Woo1 Additionally, cases in which a manual compression test shows effective glottic closure are also ideal. Woo reported that medialisation laryngoplasty alone may be considered in patients with: a midfold gap, stroboscopic findings of a short closed phase, a pre-operative phonation time of longer than 5 seconds, a positive response to medial compression testing and a pre-operative phonatory flow of less than 300 cm3/second.Reference Woo1 If a patient has both a unilateral midfold gap and a large posterior gap, and shows no improvement during a manual compression test, medialisation laryngoplasty alone may be inadequate to correct the glottic defect and needs to be combined with a posterior closure procedure.Reference Woo1
The advantages associated with adduction arytenopexy using injection laryngoplasty include: (1) the ability to perform medialisation laryngoplasty and arytenoid adduction without the need for external laryngoplastic phonosurgery; and (2) the ability to carry out medialisation laryngoplasty and adduction arytenopexy simultaneously with medialisation injection laryngoplasty.
The problems with this surgical procedure are: (1) the degree to which posterior gaps, especially large posterior gaps, can be closed; and (2) the difficulty in injecting the materials into the proper location for adduction arytenopexy. Knowledge of the three-dimensional structure of the larynx is indispensable to perform this surgical procedure.
It is obvious that arytenoid adduction via the external approach is a reliable surgical procedure. Adduction arytenopexy using injection laryngoplasty is a reliable option for laryngoplastic phonosurgery performed on patients suffering from vocal fold paralysis with aspiration and/or a large posterior gap. It is important to select patients who will benefit from this surgical intervention.
Conclusion
In order to make adduction arytenopexy possible, the injection is administered in the atrophic thyroarytenoid muscle anterolateral to the oblong fovea of the arytenoid cartilage (the thyroarytenoid muscle at the cartilaginous portion of the vocal fold). The injection location and the amount of injected material should be modified based on aspiration and the pathological conditions of the voice disorder. Knowledge of the three-dimensional structure of the larynx is crucial for performing this surgical procedure and for injecting the materials into the proper location and in the proper amount, in order to improve the voice disorder and aspiration. If the needle is placed too deep, augmentation substances will be injected into the lateral cricoarytenoid muscle, located beneath the thyroarytenoid muscle, or into the paraglottic space, located inferolateral to the thyroarytenoid muscle.
Competing interests
None declared