


Introduction
Rapid economic development is expected to gradually shift the global age structure from a pyramid to an olive shape (Zhang et al. Reference Zhang, Zhang and Zhang2015). Owing to the acceleration of population ageing in Japan, South Korea and European countries, these regions were estimated to evolve into some of the world’s most super-aged areas by 2025. Data from China’s Seventh Population Census (2020) (Akimov et al. Reference Akimov, Gemueva and Semenova2021) suggest that the proportion of the population aged ≥ 65 increased by 4.63 per cent between 2010 and 2020. This rise is 2.72 per cent higher than the previous decade; it is anticipated that the degree of population ageing in China will continue to escalate in the future, surpassing the average level observed in developed countries (The Lancet 2022).
The ageing process is marked by a deterioration in functional capabilities and a weakening of social support networks for older adults (Deary et al. Reference Deary, Corley, Gow, Harris, Houlihan, Marioni, Penke, Rafnsson and Starr2009). Cognitive impairment is frequently highlighted as one of the most severe functional impairments experienced by older adults. It refers to a condition that significantly impacts essential functions such as learning, language acquisition and memory retention. China has emerged as the country with the highest number of patients experiencing cognitive impairment worldwide. Approximately one in seven older people experience cognitive impairment, which significantly impacts the quality of life and the level of social engagement (Campos et al. Reference Campos, Teixeira, Moraes, Cadorin, Morelli, Lidio, Medeiros, Garcez, Keller, Kucharska, Da Rosa, Ceretta, Quevedo and Budni2024). Therefore, with the growing ageing population in China, prevention and management of cognitive impairment in older adults has become a critical public health priority. In response, the Healthy China 2030 initiative designates enhancing cognitive health and preventing or delaying the onset of cognitive impairments in older adults as key objectives. In this context, identifying protective factors against cognitive impairment in older adults and exploring the underlying mechanisms will aid in the prevention of cognitive decline, thereby contributing to healthy ageing.
A large corpus of literature posits that social networks and social support are important for health in old age (Jeon et al. Reference Jeon, Chung, Chung and Song2016; Bhatia et al. Reference Bhatia, Hirsch, Arnold, Newman and Mukamal2023), and support from family and society exerts a profound influence on cognitive function (Sims et al. Reference Sims, Hosey, Levy, Whitfield, Katzel and Waldstein2014; Fan et al. Reference Fan, Lv, Tu, Zhang, Yu and Wang2021). As individuals age, their social support network tends to shrink, with external sources of support, such as relationships with co-workers and friends, gradually weakening. Consequently, the role of intergenerational support within the family becomes increasingly prominent (Li et al. Reference Li, Jiang and Zhang2019). According to the traditional ‘nurture–support’ feedback model (Fingerman et al. Reference Fingerman, Sechrist and Birditt2013), intergenerational support involves a reciprocal exchange, with support flowing both from the child to the parent and vice versa (Chen et al. Reference Chen, Liu and Mair2011). Intergenerational support takes two forms: one-way support, provided solely by either the offspring or the parent, and two-way support, involving reciprocal exchanges (Wang Reference Wang2024). Furthermore, three main types of intergenerational support have been identified: financial, care-giving and emotional support (Liao et al. Reference Liao, Qi, Xiong, Yan and Wang2020; Yang and Jia Reference Yang and Jia2022).
Existing evidence has linked intergenerational support to cognitive function in later life, yet the conceptual distinction between one-way and two-way support remains insufficiently examined. From a theoretical perspective, these two forms reflect different relational dynamics. Social exchange theory suggests that one-way support, whether given or received, may create asymmetrical dependence or burden, potentially inducing stress that is detrimental to cognitive health (Lupien et al. Reference Lupien, McEwen, Gunnar and Heim2009). By contrast, two-way support reflects a more balanced exchange that may enhance relational stability and social integration. Reciprocity theory further suggests that the opportunity to both provide and receive support reinforces older adults’ sense of social value and generativity, thereby contributing to cognitive reserve (Stern Reference Stern2012). In addition, role theory proposes that maintaining multiple family roles may promote active engagement and mental stimulation (Sieber Reference Sieber1974). Taken together, these perspectives suggest that two-way intergenerational support may be more protective of cognitive function than one-way support.
Although existing research has explored the relationship between intergenerational support and cognitive function in older adults, significant limitations remain in this area. First, most of the existing studies have focused on the effects of a single specific type of intergenerational support on cognitive function. For example, older adults with financial support from their adult children are less likely to develop cognitive impairment (Deng et al. Reference Deng, Hu, Wu, Dong and Wu2010; Wang et al. Reference Wang, He and Dong2015; Xu et al. Reference Xu, Burr, Kim and Cong2019). According to Sims et al. (Reference Sims, Hosey, Levy, Whitfield, Katzel and Waldstein2014), receiving financial support from children without the ability to make financial rewards may be negatively associated with cognitive performance in older people. Liao et al. (Reference Liao, Qi, Xiong, Yan and Wang2020) revealed that moderate intensity and frequency of care-giving was associated with better cognitive function in a Chinese middle-aged and older population. Bon Sanga and Bordoneb (Reference Bonsang and Bordone2013) argued that informal care provided by children has a significant negative impact on mothers’ cognitive function. Furthermore, Eisele et al. (Reference Eisele, Zimmermann, Köhler, Wiese, Heser, Tebarth, Weeg, Olbrich, Pentzek, Fuchs, Weyerer, Werle, Leicht, König, Luppa, Riedel-Heller, Maier and Scherer2012) discovered that emotional support had no effect on cognition; the findings of Xu and Luo (Reference Xu and Luo2022) confirmed that emotional support greatly contributed to the cognitive health of middle-aged and older parents. Despite existing literature exploring the relationship between various forms of intergenerational support and cognitive function, the field lacks a comprehensive analysis and comparative study of these different forms of support.
Second, most existing research has focused on one-way intergenerational support. Indeed, older adults with higher levels of family support from their children have better cognitive function and slower cognitive decline (Ping and Bei Reference Ping and Bei2011; Zhu et al. Reference Zhu, Hu and Efird2012; Kelly et al. Reference Kelly, Duff, Kelly, McHugh Power, Brennan, Lawlor and Loughrey2017). Peng et al. (Reference Peng, Burr and Han2023) revealed that receiving financial or care-giving support from children promoted cognitive performance in rural China. However, the provision of primary financial support by the offspring may also increase the risk of cognitive impairment in older adults (Yang and Jia Reference Yang and Jia2022). Sharma et al. (Reference Sharma, Chakrabarti and Grover2016) and Zwar et al. (Reference Zwar, König and Hajek2018) collectively discovered that both sharing household chores and providing informal care-giving support to children can have a protective effect on the cognitive function of older adults, with a particular benefit observed in female care-givers. Older parents who provide support to their children are more likely to have cognitive impairment because informal care-givers are under more stress than non-care-givers (Minkler Reference Minkler1997; Pinquart and Sörensen Reference Pinquart and Sörensen2003; Lupien et al. Reference Lupien, McEwen, Gunnar and Heim2009). Although previous research has investigated the effect of intergenerational support on cognitive function in older adults, limited attention has been given to the reciprocal nature of intergenerational support. Two-way intergenerational support, characterized by the reciprocal exchange of resources and emotions, may exert a more pronounced influence on cognitive health in older adults by fostering intergenerational balance. Therefore, the association between two-way intergenerational support and cognitive function in older adults warrants further investigation.
In summary, although some studies have explored the relationship between intergenerational support and cognitive function in older adults, they have not offered a comparative analysis of different types of intergenerational support. More importantly, there is a notable gap in the literature regarding the effect of two-way intergenerational support, as compared to one-way support, on cognitive function in older adults. In this study, based on a nationally representative survey from China, we first used the ordered probit (Oprobit) model and marginal effects to examine the effects of different types of two-way and one-way intergenerational support on cognitive function in older adults. Subsequently, we applied the instrumental variable with conditional mixed process (IV-CMP) estimation method to test the robustness between intergenerational support and cognitive function. Finally, to account for potential differences between urban and rural areas in China, as well as gender disparities, we stratified the extracted data by geographic region and gender to analyse heterogeneity.
Methods
Data source
The data utilized in this study derived from the Chinese Longitudinal Healthy Longevity Survey (CLHLS) (Center for Healthy Aging and Development Studies 2020), which was conducted by Peking University and the Chinese Center for Disease Control and Prevention, spanning the years 2011, 2014 and 2018. In the survey, a random selection of half the total number of counties and cities from 22 Chinese provinces served as survey sites, thereby covering approximately 85 per cent of the country’s population. Unequally proportional random sampling and multi-stage sampling methods were used to survey adults aged ≥ 65 years. The original dataset consisted of 32,831 observations. After excluding cases with missing data, the final sample included 21,528 individuals: 7,771 individuals in 2011, 4,667 in 2014 and 9,090 in 2018. The CLHLS dataset provides comprehensive data on demographics, family structure, economic status, lifestyle, intergenerational support, health and cognitive function. Statistical analysis was performed using Stata software (v.14.0; Stata Corp., College Station, TX, USA).
Data analysis
Oprobit model
The dependent variable in this study is the cognitive function of older adults, which is measured on a discrete ordinal scale ranging from 0 to 3, with 0, 1, 2 and 3 representing ‘No cognitive impairment’, ‘Mild cognitive impairment’, ‘Moderate cognitive impairment’ and ‘Severe cognitive impairment’, respectively. Given the ordinal nature of the data, the Oprobit model was deemed more appropriate for analysis, formulated as follows:
 \begin{equation*}mms{e^*} = F\left( {\alpha + \beta suppor{t_i} + \gamma contro{l_i} + {\varepsilon _i}} \right)\end{equation*}
where 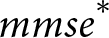 $mms{e^*}$represents the latent variable of cognitive function of the
 $i$th older adult;
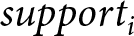 $suppor{t_i}$ represents the intergenerational support;
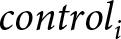 $contro{l_i}$ represents a series of control variables including socio-demographic characteristics, lifestyle habits, health status and social security; and
 ${\varepsilon _i}$ is the random error term. The function F(.) represents a non-linear mapping. The coefficients of the Oprobit model denote the direction of change in the underlying latent variable rather than directly influencing the probability of the outcome. Consequently, these coefficients are not immediately interpretable, necessitating the computation of marginal effects to elucidate the impact of independent variables on the dependent variable. Marginal effects quantify the average shift in the dependent variable in response to a minute change in the independent variable, formulated as follows:
 \begin{align*}ME\left( {suppor{t_i}} \right) &= {{\Phi }}ME\left( {suppor{t_i}} \right) \\&= {{\Phi }}\left( {{\beta _0} + {\beta _1}suppor{t_i} + {\beta _2}contro{l_i} + {\sigma _j}} \right)\\&\quad\cdot\phi \left( {{\beta _0} + {\beta _1}suppor{t_i} + {\beta _2}contro{l_i} + {\sigma _{j - 1}}} \right)\cdot{\beta _{j - 1}}\end{align*}
where 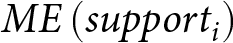 $ME\left( {suppor{t_i}} \right)$ represents the marginal effect of the independent variable
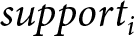 $suppor{t_i}$ and denotes the probability of change in the dependent variable
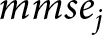 $mms{e_j}$ across categories when
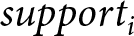 $suppor{t_i}$ is increased by one unit; Φ is the cumulative distribution function of the standard normal distribution;
 $\phi $ is the probability density function of the standard normal distribution; and
 ${\sigma _j}$is the delimitation threshold parameter, which is used to identify different categories of the dependent variable.
Robust test model
To address endogeneity issues, including self-selection bias and collider bias in the Oprobit model, this study employed an IV-CMP estimation method, as developed by Roodman (Reference Roodman2011), to ensure robust analysis. This approach optimizes the treatment effect of intergenerational support, verifies the causal relationship between intergenerational support and cognitive function, and provides more robust conclusions. Using IV-CMP requires prioritizing the identification of appropriate instrumental variables. To ensure their validity, we conducted a weak instrumental variable test for linear models to scrutinize the regression outcomes (Chyi and Mao Reference Chyi and Mao2012).
Variable selection
Cognitive function
The Mini-Mental State Examination (MMSE) was employed to evaluate the cognitive function of the respondents. The MMSE consists of five dimensions: orientation, memory, attention and calculation, recall, and language ability, with a total of 30 items. The overall score ranges from 0 to 30, with higher scores indicating better cognitive function. Following established clinical conventions, the MMSE score was further categorized into four ordered groups to capture the severity of cognitive impairment (Folstein et al. Reference Folstein, Folstein and McHugh1975): no impairment (24–30 points), mild impairment (18–23 points), moderate impairment (10–17 points) and severe impairment (0–9 points). To ensure consistency, higher levels of the categorical variable correspond to lower MMSE scores, indicating worse cognitive function.
Intergenerational support
A total of three independent variables were established from the three types of intergenerational support:
(i) Intergenerational financial support: The intergenerational financial support variable derived from the questionnaire items ‘In the past year, how much money in cash (or in kind) did your children give you?’ and ‘In the past year, how much money in cash (or in kind) did you give your children?’. The responses to these questions were used to categorize the receipt and provision of financial support, respectively. In our study, intergenerational financial support was categorized into four distinct classifications: ‘No support’ if neither providing nor receiving exceeded \$0 per year; ‘Provided financial support alone’ if the older adult provided more than \$0 per year but did not receive any support; ‘Received financial support alone’ if the older adult received over \$0 per year but did not provide any support; and ‘Two-way financial support’ if the older adult both provided and received support exceeding \$0 per year.
(ii) Intergenerational care-giving support: The intergenerational care-giving support variable derived from the questionnaire items ‘Who primarily cares for you when you are not feeling well or when you are sick?’ and ‘Are you currently engaged/participating in any of the following activities: housework, cooking, childcare, etc.?’. The responses to these questions were used to categorize the receipt and provision of care-giving support, respectively. The receipt of care-giving support was categorized as ‘Yes’ if the answer to the first question was children, grandchildren or similar relatives, and ‘No’ for all other responses. The provision of care-giving support was defined as ‘Yes’ if the second question was answered affirmatively, and ‘No’ in all other cases. Intergenerational care-giving support was classified into four categories: ‘No support’, defined as the absence of both providing and receiving care; ‘Provided care-giving support alone’, when the older adult provided childcare exclusively to their children; ‘Received care-giving support alone’, when the older adult received informal care exclusively from their children; and ‘Two-way care-giving support’, when the older adult both provided and received care-giving support.
(iii) Intergenerational emotional support: Intergenerational emotional support is inherently reciprocal and bidirectional (Sommer and Buhl Reference Sommer and Buhl2018). It was defined using the questionnaire item ‘Who do you talk to the most in your spare time?’. Responses were coded as ‘Intergenerational emotional support exists’ if participants selected ‘son, daughter, daughter-in-law, son-in-law, grandchildren or spouse’, and as ‘No intergenerational emotional support exists’ for all other responses. Therefore, 0 signified the absence of intergenerational emotional support, whereas 1 indicated the presence of such support. This measure captures the primary channel of emotional interaction within the family and is aligned with the study’s focus on the direction and reciprocity of intergenerational support rather than its intensity.
Instrumental variable selection in the IV-CMP model
A valid instrumental variable in the IV-CMP model must satisfy two fundamental conditions: it must be correlated with the endogenous explanatory variable and it must be uncorrelated with the dependent variable. The instrumental variable selected for this study was the number of children, as identified in a previous study (Bolin et al. Reference Bolin, Lindgren and Lundborg2008). Intergenerational support is strongly correlated with the number of children older adults have (Zhang et al. Reference Zhang, Li, Li and Wang2025). A greater number of children can increase the demands on older parents to provide financial, care-giving and emotional support. Meanwhile, older adults with more children are likely to receive greater resources and emotional support from their offspring.
Although the number of children may potentially affect cognitive function through other pathways, such as economic resources, psychological stress or social engagement, we minimize these concerns by controlling for a comprehensive set of demographic, socio-economic and health-related characteristics. After accounting for these factors, the remaining variation in the number of children is more plausibly associated with intergenerational support rather than directly affecting cognitive function. Therefore, the exclusion restriction is reasonably satisfied in the present study, although it cannot be directly tested.
To examine the validity of the instrumental variable, we conducted weak instrument tests, and the first-stage F-statistics indicate that the instrument is sufficiently strong. As only one instrumental variable (number of children) is employed, the model is exactly identified, and over-identification tests are not applicable. We adopt a single-instrument approach to avoid introducing potentially invalid instruments that may violate the exclusion restriction.
Other control variables
Other control variables included socio-demographic characteristics, lifestyle habits, health status and social security. Socio-demographic characteristics variables included age, gender, duration of formal education, residential area, marital status and income. Income level in yuan was categorized based on annual household earnings as ≤ 30,000, 30,001–50,000, 50,001–100,000 and > 100,000. Lifestyle habit variables included smoking, drinking and daily exercise. Health status variables referred to hearing impairment, self-reported health, chronic disease, depression and ability to perform activities of daily living (ADLs). Ability to perform ADLs was assessed using the Katz scale (Katz Reference Katz1963) and categorized into three groups based on scores: no, low and high disability. Social security variables included participation in insurance and community services.
Results
Basic characteristics of participants
Table 1 provides a detailed description of the samples. Overall, 79.3 per cent of individuals were aged ≥ 75 years and 43.6 per cent of the participants were male. Half of the older adults (51.6%) lived in the urban areas and 86.2 per cent of the participants reported ≤ 6 years of formal education. Furthermore, more than half of the participants had no spouse (59.8%), reported no hearing impairment (56.8%) and had an annual income of ≤ 30,000 yuan (62.3%). Less than one-third participated in daily exercise (31.0%), and 83.5 per cent and 84.5 per cent of the participants were non-smokers and non-drinkers, respectively. Approximately 24.6 per cent of the participants reported a disability, and more than half reported diagnosis with at least one chronic disease (62.4%). Furthermore, 12.7 per cent of older adults in this study experienced symptoms of depression. The majority of participants in the sample (81.8%) have social insurance.
Basic characterization of included subjects

Table 1 Long description
Variables and values are listed as counts with percentages, plus a mean with standard deviation for number of children, for 21,528 observations. Age groups are 20.7 per cent for the first age row, 28.2 per cent for 65 to 74, 26.6 per cent for 75 to 84, and 24.5 per cent for 85 to 94; the row labeled greater than or equal to 95 has no value shown. Gender is 43.6 per cent male and 56.4 per cent female. Duration of formal education is 54.8 per cent for 0 year, 31.4 per cent for 1 to 6 years, 7.4 per cent for 7 to 9 years, and 6.4 per cent for 10 years or more. Residential area is 51.6 per cent urban and 48.4 per cent rural, and marital status is 59.8 per cent without spouse and 40.2 per cent with spouse; number of children is 4.2 with standard deviation 2.0. Income is 62.3 per cent at 30,000 or less, 15.0 per cent at 30,001 to 50,000, 19.7 per cent at 50,001 to 100,000, and 3.0 per cent above 100,000. Hearing impairment is 56.8 per cent no and 43.2 per cent yes; self reported health is 21.5 per cent bad, 36.1 per cent moderate, and 42.4 per cent good. Chronic disease is 37.6 per cent no chronic disease, 27.3 per cent one chronic disease, and 35.1 per cent multiple chronic diseases; depression is 87.3 per cent no and 12.7 per cent yes; ADL is 74.8 per cent no disability, 15.9 per cent low disability, and 9.3 per cent high disability. Community services are 42.8 per cent no and 57.2 per cent yes.
Intergenerational support and cognitive function among the older adults
Table 2 shows the status of intergenerational support and cognitive function. In terms of financial support, ∼45.0 per cent of older adults received financial support alone from their children, 4.0 per cent provided financial support alone to their children and 34.1 per cent of older adults experienced a two-way financial support arrangement with their children. Regarding care-giving support, 20.7 per cent of older adults provided care-giving alone to their children, 35.1 per cent received care-giving alone from their children and 35.0 per cent of older adults engaged in two-way intergenerational care-giving. With regard to intergenerational emotional support, 75.2 per cent of older participants reported sharing intergenerational emotional support with their children. As shown in Table 2, 34.2 per cent of older adults in the sample experienced cognitive impairment. Specifically, 13.6 per cent, 9.1 per cent and 11.5 per cent of the older demographic exhibited mild, moderate and severe cognitive impairment, respectively.
Intergenerational support and cognitive function among older adults

Table 2 Long description
Variables and Value columns list counts with percentages for intergenerational financial, caregiving, and emotional support, plus cognitive function categories and total observations. For financial support, none is 3636 people, 16.9 per cent; provided alone is 856, 4.0 per cent; received alone is 9688, 45.0 per cent; two way is 7348, 34.1 per cent. For caregiving support, none is 1980, 9.2 per cent; provided alone is 4457, 20.7 per cent; received alone is 7561, 35.1 per cent; two way is 7530, 35.0 per cent. For emotional support, none is 5348, 24.8 per cent and two way is 16,180, 75.2 per cent. Cognitive function categories are mild impairment 2931, 13.6 per cent; moderate impairment 1968, 9.1 per cent; and severe impairment 2465, 11.5 per cent. Observations are 21,528.
Effects of intergenerational support on cognitive function among the older adults
Supplementary Table 2 shows the association between intergenerational support and cognitive function. After controlling for socio-demographic factors, older adults who provided financial support alone (Coef. = −0.164), received financial support alone (Coef. = −0.080) and engaged in two-way financial support with their children (Coef. = −0.197) were all significantly associated with a lower risk of cognitive impairment. Regarding intergenerational care-giving support, providing care-giving alone was significantly associated with a lower risk of cognitive impairment in older adults (Coef. = −0.374), as was two-way care-giving support (Coef. = −0.267). In contrast, having received care-giving alone was significantly associated with a higher risk of cognitive impairment in older adults (Coef. = 0.112). Furthermore, a significant negative correlation between intergenerational emotional support and cognitive impairment was observed in older adults (Coef. = −0.241). Other socio-demographic factors, including age, gender, duration of formal education, residential area, marital status, exercise, hearing impairment, self-reported health, chronic disease, depression, ability to perform ADLs, having insurance and community services, were significantly associated with cognitive function.
Table 3 summarizes the results of the marginal effects analysis, which revealed that intergenerational support had significant effects on cognitive function. Across most types of intergenerational support, positive marginal effects were observed for the ‘No cognitive impairment’ category, indicating that intergenerational support increased the probability of older adults maintaining intact cognitive function, while correspondingly reducing the probabilities of mild, moderate and severe cognitive impairment.
Results of marginal effects

Table 3 Long description
Marginal effects with standard errors in parentheses are reported for cognitive function categories: no cognitive impairment, mild cognitive impairment, moderate cognitive impairment, and severe cognitive impairment. For intergenerational financial support compared with none, provided alone is 0.036, minus 0.009, minus 0.009, and minus 0.018; received alone is 0.018, minus 0.004, minus 0.004, and minus 0.009; two way is 0.044, minus 0.011, minus 0.011, and minus 0.022. For intergenerational caregiving support compared with none, provided alone is 0.086, minus 0.024, minus 0.023, and minus 0.038; received alone is minus 0.028, 0.007, 0.007, and 0.014; two way is 0.063, minus 0.017, minus 0.017, and minus 0.029. Intergenerational emotional support, two way compared with none, is 0.053, minus 0.012, minus 0.013, and minus 0.028. Compared with age 65 to 74 years, age 75 to 84 is minus 0.071, 0.027, 0.021, and 0.023; age 85 to 94 is minus 0.168, 0.058, 0.048, and 0.061; age 95 years or older is minus 0.268, 0.082, 0.076, and 0.109. Compared with male, female is minus 0.049, 0.012, 0.012, and 0.024; compared with urban, rural is minus 0.015, 0.004, 0.004, and 0.008; compared with without spouse, with spouse is 0.031, minus 0.008, minus 0.008, and minus 0.015. Compared with no disability, low disability is minus 0.094, 0.023, 0.027, and 0.044, and high disability is minus 0.285, 0.046, 0.073, and 0.166.
Note: *p ≤ 0.1, **p ≤ 0.05, ***p ≤ 0.01
Specifically, older adults who provided financial support alone were associated with a 3.6 per cent higher probability of having no cognitive impairment and a 0.9 per cent, 0.9 per cent and 1.8 per cent lower likelihood of mild, moderate and severe cognitive impairment, respectively. Similarly, having received financial support alone was associated with a 1.8 per cent increase in the probability of having no cognitive impairment, accompanied by reductions of 0.4 per cent, 0.4 per cent and 0.9 per cent in the likelihood of mild, moderate and severe cognitive impairment, respectively. In contrast, two-way financial support showed stronger protective effects, increasing the probability of having no cognitive impairment by 4.4 per cent, while reducing the likelihood of mild, moderate and severe cognitive impairment by 1.1 per cent, 1.1 per cent and 2.2 per cent, respectively.
Regarding care-giving support, having provided care-giving support alone increased the probability of having no cognitive impairment by 8.6 per cent, while reducing the likelihood of mild, moderate and severe cognitive impairment by 2.4 per cent, 2.3 per cent and 3.8 per cent, respectively. Two-way care-giving support increased the probability of having no cognitive impairment by 6.3 per cent, accompanied by reductions of 1.7 per cent, 1.7 per cent and 2.9 per cent in the likelihood of cognitive impairment. However, having received care-giving support alone had a detrimental effect, decreasing the probability of having no cognitive impairment by 2.8 per cent and increasing the likelihood of mild, moderate and severe cognitive impairment by 0.7 per cent, 0.7 per cent and 1.4 per cent, respectively.
Furthermore, intergenerational emotional support increased the probability of having no cognitive impairment by 5.3 per cent, while reducing the likelihood of mild, moderate and severe cognitive impairment by 1.2 per cent, 1.3 per cent and 2.8 per cent, respectively.
Robustness test based on the IV-CMP estimation
The results of the IV-CMP analysis provided robust evidence of the significant effect of intergenerational support on cognitive function (Table 4). The Atanhrho_12 parameters (0.641, 0.284, 0.567) were all significant at the 1 per cent level, indicating that intergenerational financial, care-giving and emotional support are endogenous variables, supporting the reliability of the IV-CMP model. The number of children correlated with all three endogenous variables (financial: 0.065; care-giving: 0.089; emotional: 0.024), confirming the validity of the instrumental variable in addressing endogeneity.
Robust test based on IV-CMP

Table 4 Long description
Coefficients with standard errors are reported for two models: Oprobit Model and IV CMP Model. Under Oprobit Model, the outcome column is Cognitive function and the instrument column is IV: Number of children; under IV CMP Model, the outcome column is Cognitive function and the second column is Atanhro_12. Intergenerational financial support uses None as the reference: Provided alone is minus 0.164 with three stars for Cognitive function and 0.065 with three stars for IV: Number of children, and under IV CMP it is minus 0.451 with three stars for Cognitive function and 0.641 with three stars for Atanhro_12; Received alone is minus 0.080 with three stars for Cognitive function and minus 0.794 with three stars for Atanhro_12; Two way is minus 0.197 with three stars for Cognitive function and minus 1.617 with three stars for Atanhro_12. Intergenerational caregiving support uses None as the reference: Provided alone is minus 0.374 with three stars for Cognitive function and 0.089 with three stars for IV: Number of children, and under IV CMP it is minus 0.605 with three stars for Cognitive function and 0.284 with three stars for Atanhro_12; Received alone is 0.112 with three stars for Cognitive function and minus 0.468 with three stars for Atanhro_12; Two way is minus 0.327 with three stars for Cognitive function and minus 1.121 with three stars for Atanhro_12. Intergenerational emotional support lists only Two way: minus 0.241 with three stars for Cognitive function and 0.024 with three stars for IV: Number of children, and under IV CMP it is minus 1.047 with three stars for Cognitive function and 0.567 with three stars for Atanhro_12. The row, Control variables, indicates Control in all four columns.
Note: *p ≤ 0.1, **p ≤ 0.05, ***p ≤ 0.01
The IV-CMP results revealed that intergenerational support – both one-way and two-way – significantly mitigated cognitive impairment. These findings were consistent with the Oprobit model analyses, except for the case of having received care-giving support alone, indicating the robustness of the results. The mitigating effects of intergenerational support on cognitive impairment in the IV-CMP model were as follows: provided financial support alone (−0.451), received financial support alone (−0.794), two-way financial support (−1.617), provided care-giving support alone (−0.605), received care-giving support alone (−0.468), two-way care-giving support (−1.121) and intergenerational emotional support (−1.047). In addition, we conducted the weak instrumental variable test (Supplementary Table 3); the F-statistics for all columns were > 10 and were considered significant at the 1 per cent level (financial: F = 1282.81; care-giving: F = 1326.77; emotional: F = 1991.74); the Wald test also revealed that the smallest eigenvalue statistic exceeded the 10 per cent critical value, providing strong evidence that number of children is not a weak instrument.
Heterogeneity analysis
Urban–rural heterogeneity
Figure 1 summarizes the urban–rural disparities in the marginal effect of intergenerational support on cognitive function in older adults. All the regression estimates were controlled for socio-demographic factors. The Chow test was used to examine differences in the formation coefficients (Chow test = 2.89, P < 0.01). Having provided financial support alone reduced the risk of mild, moderate and severe cognitive impairment by 0.8 per cent, 0.8 per cent and 1.6 per cent in urban-living older adults, which was significantly lower than that in their rural counterparts (1.2 per cent, 1.3 per cent and 2.5 per cent, respectively), whereas having received financial support alone reduced the risk by 0.5 per cent, 0.5 per cent and 1.1 per cent in urban older adults but had no significant effect in rural populations. Two-way financial support reduced the risk of mild, moderate and severe cognitive impairment by 1.3 per cent, 1.2 per cent and 2.5 per cent in urban older adults, which was significantly higher than that of their rural counterparts (0.8 per cent, 0.9 per cent and 1.8 per cent). Regarding intergenerational care-giving support, having provided care-giving support alone reduced the risk of moderate and severe cognitive impairment by 2.3 per cent and 3.7 per cent in urban older adults, significantly lower than in rural areas (2.5% and 4.1%). However, having received care-giving support alone increased the risk of mild, moderate and severe cognitive impairment by 0.7 per cent, 0.8 per cent and 1.4 per cent in urban older adults, with no significant effect in rural counterparts. Two-way care-giving support reduced the risk of mild, moderate and severe cognitive impairment by 1.5 per cent, 1.4 per cent and 2.3 per cent, respectively, in urban older adults, which was significantly lower than that in rural areas (2.0%, 2.1% and 3.6%, respectively). In addition, having received intergenerational emotional support significantly reduced the risk of moderate and severe cognitive impairment by 1.2 per cent and 2.6 per cent, respectively, in urban-living older adults, which was significantly lower than the rates observed in rural counterparts (1.4% and 3.0%, respectively).
Results of the marginal effects for estimating urban−rural heterogeneity.

Figure 1 Long description
Two line graphs titled Average marginal effects Urban and Average marginal effects Rural. Both graphs plot types of intergenerational support on the horizontal axis, including financial support, caregiving support and emotional support. The vertical axis represents average marginal effects, ranging from 0.000 to 0.025. The urban graph shows peaks in financial support for severe impairment at approximately 0.016 and caregiving support for moderate impairment at around 0.023. The rural graph displays higher effects for financial support in severe impairment at about 0.025 and caregiving support for moderate impairment at approximately 0.025. Legends indicate significance levels with asterisks: one asterisk for p less than 0.1, two for p less than 0.05 and three for p less than 0.01. Each graph includes four lines representing different levels of cognitive impairment: no impairment, mild impairment, moderate impairment and severe impairment. The urban graph shows lower effects compared to rural settings, especially in financial support for severe impairment. The lines are differentiated by style and markers, with each series corresponding to an impairment level. The Chow test value is 2.89 with significance at p less than 0.01.
Gender-based heterogeneity
Figure 2 presents findings supporting gender-based disparities in the marginal effect of intergenerational support on cognitive function among older adults (Chow test = 9.26, p < 0.01). Having provided financial support alone reduced the risk of mild, moderate and severe cognitive impairment by 0.7 per cent, 1.0 per cent and 2.5 per cent in older females, with no significant effect observed in older men; a similar pattern was observed in adults having received financial support alone (0.5%, 0.7%, 1.9%, respectively). Two-way financial support reduced the risk of mild, moderate and severe cognitive impairment by 0.8 per cent, 0.6 per cent and 0.9 per cent, respectively, in older men, which was significantly lower than that observed in older women (0.9%, 1.4% and 3.4%, respectively). Having provided care-giving support alone reduced the risk of moderate and severe cognitive impairment in older men by 1.7 per cent and 2.3 per cent, respectively, which was significantly lower than that observed in older women (2.8% and 5.2%, respectively). Having received care-giving support alone reduced the risk of mild, moderate and severe cognitive impairment in older men by 1.0 per cent, 0.8 per cent and 1.2 per cent, respectively, whereas in older women it had no significant effect on mild or moderate impairment but increased the risk of severe cognitive impairment by 1.5 per cent. Two-way care-giving support reduced the risk of moderate and severe cognitive impairment in older men by 1.2 per cent and 1.6 per cent, respectively, which was lower than the reductions observed in older women (2.1% and 4.1%, respectively). Similarly, intergenerational emotional support reduced the risk of moderate and severe cognitive impairment in older men by 1.0 per cent and 1.7 per cent, respectively, which was significantly lower than the corresponding reductions in women (1.4% and 3.8%).
Results of the marginal effects for estimating gender-based heterogeneity.

Figure 2 Long description
The composite figure contains two line graphs side by side, titled ′Average marginal effects (Male)′ and ′Average marginal effects (Female)′. Each graph shares the same axis structure. The x-axis is labeled ′Types of intergenerational support′ with no units shown and lists the following categories in order: no cognitive impairment, mild cognitive impairment, moderately cognitive impairment and severe cognitive impairment. The y-axis is labeled ′Average marginal effects′ with no units shown, ranging from negative 0.04 to positive 0.04. Four lines appear in each panel, each representing a different level of cognitive impairment: no cognitive impairment, mild, moderate and severe. In the male panel, the lines for mild, moderate and severe cognitive impairment generally remain close to zero or show small negative values across most support types, with the severe impairment line showing a slightly more negative value near certain support categories. Asterisk markers appear at several data points, indicating statistical significance at p less than 0.1, p less than 0.05 and p less than 0.01 as noted in the legend below the graphs. In the female panel, the lines show wider separation, particularly for the severe cognitive impairment line, which reaches more negative values compared to the male panel, with the most negative values appearing at certain support type categories. The no cognitive impairment line in both panels trends in the positive direction to offset the negative values on other lines. The Chow test statistic is reported as 9.26, with p less than 0.01, printed below both panels. The note below states: p less than 0.1 is marked with one asterisk, p less than 0.05 with two asterisks and p less than 0.01 with three asterisks.
To formally assess whether the effects of intergenerational support differ across subgroups, we conducted heterogeneity tests by estimating interaction terms between intergenerational support variables and subgroup indicators (urban–rural residence and gender). The results are presented in Supplementary Table 4.
For urban–rural differences, the joint tests of interaction terms are not statistically significant for intergenerational financial support (χ2 = 3.11, p = 0.375), care-giving support (χ2 = 0.68, p = 0.878) or emotional support (χ2 = 0.03, p = 0.872). Similarly, for gender differences, none of the interaction terms reach statistical significance (financial support: χ2 = 3.76, p = 0.288; care-giving support: χ2 = 1.71, p = 0.634; emotional support: χ2 = 0.76, p = 0.385).
These findings indicate that, although subgroup analyses suggest some variation in the estimated effects, the differences across urban–rural and gender groups are not statistically significant. Overall, the effects of intergenerational support on cognitive function appear to be broadly consistent across sub-populations.
Discussion
Intergenerational support plays a crucial role in mitigating cognitive impairment (Sharifi et al. Reference Sharifi, Babaei Khorzoughi, Khaledi-Paveh and Rahmati2023). However, the effect of two-way intergenerational support on cognitive function in older adults remains insufficiently understood. Our study conducted a comparative analysis of the effects of two-way and one-way intergenerational support on cognitive function among older Chinese adults. Additionally, robustness checks and heterogeneity analyses were performed, stratifying the data by geographic region and gender.
The marginal effects analysis revealed that two-way financial support, two-way care-giving support and intergenerational emotional support all had a significant mitigating effect on varying degrees of cognitive impairment risk, particularly for severe patients. These findings were further validated through robustness tests. Regarding one-way intergenerational support, having provided financial support alone, having received financial support alone and having provided care-giving support alone were also significantly associated with a reduced risk of varying degrees of cognitive impairment. These findings aligned with existing research (Deng et al. Reference Deng, Hu, Wu, Dong and Wu2010; Wang et al. Reference Wang, He and Dong2015; Xu et al. Reference Xu, Burr, Kim and Cong2019). Therefore, fostering intergenerational support may be an effective strategy for mitigating cognitive impairment risk in older adults. Furthermore, our study found that two-way financial support was more effective than one-way support in reducing the risk of cognitive impairment of varying degrees. This result supports the view that reciprocal financial exchanges not only involve the transfer of financial resources but also foster a sense of mutual responsibility and contribution, as well as active communication and engagement between the giver and the receiver (Sharifi et al. Reference Sharifi, Babaei Khorzoughi, Khaledi-Paveh and Rahmati2023). This reciprocal interaction may play a more effective protective role in preserving cognitive health in older adults. In contrast, although receiving or providing financial support alone may reduce the risk of cognitive impairment in older adults, it offers less interaction and feedback, thereby limiting its protective effects on cognitive function (Shu et al. Reference Shu, Xiao, Dai, Han and Liu2021). Hence, strategies that encourage reciprocal financial exchanges between older adults and their families, such as establishing a shared family financial support system, should be promoted to effectively enhance cognitive wellbeing for older adults.
Unexpectedly, two-way care-giving support had a weaker effect on reducing the risk of cognitive impairment in older adults compared with having provided care-giving support alone in older adults. Two-way care-giving involves frequent role switching and responsibility sharing, requiring older adults to alternate between being care-givers and care recipients. This role conflict may lead to distraction and depletion of cognitive resources (Yoo et al. Reference Yoo, Moon, Park, Lee and Choi2023), which could diminish the protective effect of intergenerational support on cognitive impairment. In contrast, previous studies have shown that when older adults provided care-giving alone to their children, the roles were clearer and tasks more defined, allowing for better cognitive resource allocation (Yang and Jia Reference Yang and Jia2022). Moreover, when older adults provide care-giving alone, it may maximize their self-worth and sense of accomplishment (Adam et al. Reference Adam, Bonsang, Grotz and Perelman2013), thereby better supporting cognitive health. Our findings also indicated that emotional support, as a form of two-way intergenerational support, was also significantly associated with a reduced risk of cognitive impairment in older adults, particularly for severe cases, which is in agreement with a previous report (Sharifi et al. Reference Sharifi, Babaei Khorzoughi, Khaledi-Paveh and Rahmati2023). Therefore, targeted interventions should promote intergenerational emotional support through family engagement, strengthening family cohesion, enhancing emotional bonds and reducing risk of cognitive impairment.
Our findings indicate that, among the three types of two-way intergenerational support, two-way care-giving support exhibited the most significant mitigating effect on the risk of cognitive impairment by varying degrees in older adults, while two-way financial support had the weakest effect. This may be attributed to the fact that, in contrast with financial support, two-way care-giving support requires more direct involvement in the daily lives of older adults. It not only addresses their physical needs but also fosters meaningful interactions between care-givers and recipients. Providing and receiving care-giving requires problem-solving, decision-making and active communication (Zwar et al. Reference Zwar, König and Hajek2018), which play a crucial role in promoting mental wellbeing and preserving cognitive function in older adults. Meanwhile, having provided care-giving support alone had the most significant effect on mitigating the risk of cognitive impairment among the three types of one-way intergenerational support. It also demonstrated a stronger effect on reducing cognitive impairment risk compared with the two-way care-giving support, as noted earlier. Therefore, interventions to prevent cognitive impairment should prioritize encouraging older adults to assume appropriate care-giving responsibilities and promote reciprocal care-giving relationships, as these may enhance cognitive engagement, emotional connection and social interaction.
Rural China is typically characterized by multigenerational family structures and close intergenerational bonds, whereas urban areas increasingly consist of smaller, more variable nuclear family units (Liu Reference Liu2014). Our findings indicate that rural older adults may derive greater cognitive benefits from providing financial support alone to their offspring compared with their urban counterparts, which is consistent with previous studies (Peng et al. Reference Peng, Burr and Han2023). Meanwhile, having received financial support alone had no significant effect on adult cognition in rural areas. Given the more homogeneous social structures and traditional cultural norms in rural China, such as filial piety, patriarchal family structure and family collectivism (Yuan and Wang Reference Yuan and Wang2011; Yan Reference Yan2016), older adults living in a rural setting may view providing – rather than receiving – financial support as a key way to affirm their social value and autonomy, which may contribute to a greater sense of self-worth and, in turn, result in enhanced cognitive benefits. However, our study showed that two-way financial support acted as a stronger protective factor against cognitive impairment among urban older adults than among their rural counterparts. This may be owing to the weaker influence of traditional norms in urban areas (Liu Reference Liu2014), where both providing and receiving financial support benefit cognition health. Additionally, urban environments offer better health-care access, social participation and promotion of healthy behaviour (Sarkar and Webster Reference Sarkar and Webster2017), enhancing the efficacy of intergenerational financial support in protecting cognitive health. In terms of intergenerational care-giving support, our findings revealed that both two-way care-giving support and providing care-giving alone were more effective in reducing the risk of cognitive impairment among rural older adults than among their urban counterparts. A possible explanation is that multigenerational family structures, stronger intergenerational ties and traditional care-giving roles in rural China provide a greater sense of fulfilment and family engagement (Shi Reference Shi2017), which better protects the cognitive health of older adults. Finally, our study indicates that intergenerational emotional support was linked to a reduced risk of moderate and severe cognitive impairment in both urban and rural areas, with a stronger impact in rural settings. This finding may be attributed to the relatively stable family structures, stronger intergenerational ties, deeper cultural continuity and reduced environmental stress present in rural communities (Wu and Yuan Reference Wu and Yuan2023), which together enhance the buffering effects of emotional support on cognitive impairment.
Regarding gender disparities on the effects of intergenerational support on cognitive function among older adults, our study found that two-way financial support was more beneficial for women than men, especially in reducing the risk of moderate and severe cognitive impairment. Meanwhile, both providing and receiving financial support alone have stronger effects on reducing the risk of cognitive impairment in older women than in older men, which is in accordance with previous studies (Okamoto and Tanaka Reference Okamoto and Tanaka2004; Sharma et al. Reference Sharma, Chakrabarti and Grover2016; Zwar et al. Reference Zwar, König and Hajek2018). In addition, both care-giving support – whether provided alone or two-way – and intergenerational emotional support showed stronger protective effects among older women than men, especially in reducing moderate and severe cognitive impairment risk, which contrasts with the findings of recent research (Yang and Jia Reference Yang and Jia2022). These gender-based disparities may stem from the traditional care-giving role of the woman, stronger emotional engagement in family relationships, greater sensitivity to reciprocity and heightened psychological gains from support exchanges (Glauber Reference Glauber2017; Tavero et al. Reference Tavero, García, Seda, Serrano, Cabrera and Rodríguez2018). These factors may enhance their sense of self-worth and emotional wellbeing, thereby contributing more significantly to cognitive health. Therefore, it is essential to implement gender-based sensitive strategies that promote flexible care-giving roles, challenge traditional gender-based norms and ensure access to mental health support, thereby enabling both men and women to benefit fully from intergenerational support and maintain cognitive health in later life.
Our study was subject to certain limitations that should be acknowledged. Firstly, the absence of unified criteria for selecting measurement indicators in current research on intergenerational support may constrain the generalizability and comparability of our findings. Relatedly, our classification of two-way support relied on binary indicators of provision and receipt, which cannot capture variation in the intensity, frequency or quality of support. Future research with continuous or ordinal measures is needed to further refine this relationship. Secondly, the reliance on self-reported data in the questionnaire design introduces the potential for recall bias, which may compromise the accuracy and validity of the data. Thirdly, although we utilized three waves of data from the CLHLS (2011, 2014, 2018), our main analytical approach treated these as pooled cross-sections rather than a true panel. Consequently, our models did not account for within-individual correlations over time through individual-level random effects, fixed effects or cluster-robust standard errors. This may lead to under-estimated standard errors and overly optimistic p-values. Future studies with panel data models or more sophisticated longitudinal techniques would enable stronger causal inference and a more nuanced understanding of cognitive trajectories over time. Fourthly, the selection of control variables may lack sufficient comprehensiveness, potentially limiting the scope and robustness of the study findings.
Conclusion
Our study suggested that, in China, two-way financial, care-giving and emotional support significantly reduced the risk of cognitive impairment, especially for more severe patients. Moreover, two-way financial support was more effective than one-way support in reducing the risk of cognitive impairment by varying degrees. However, two-way care-giving support had a weaker effect on reducing cognitive impairment risk in older adults compared with having provided care-giving support alone. Furthermore, our data showed that two-way care-giving had the strongest effect in reducing the risk of cognitive impairment among the three types of two-way intergenerational support, whereas two-way financial support had the weakest. Finally, our findings revealed disparities in the effect of intergenerational support on cognitive function comparing older adults from rural and urban areas and between men and women; this provides a scientific basis for designing tailored intervention strategies to address cognitive impairment risks in different demographic groups.
Supplementary material
The supplementary material for this article can be found at https://doi.org/10.1017/S0144686X26101056
Acknowledgements
Thanks to all participants for their support and assistance with our research.
Author contributions
Sunxi Mao led the analysis of the data and the writing of the draft manuscript; Tianyu Wang participated in the data analysis and writing; Xinyi Wang contributed to the writing; and Zinan Zhang and Zhonghua Wang contributed equally to the study design and interpretation of the data and helped in the writing of the final draft manuscript. All authors read and approved the final manuscript.
Financial support
This study was funded by the National Natural Science Foundation of China (No. 72374108). The funding body was not involved in the design of the study, in the data collection, analysis and interpretation or in the writing of the manuscript.
Competing interests
The authors declare no conflict of interest.
Ethical standards
This study was approved by the Academic Research Ethics Committee of Nanjing Medical University (Reference No. 2,022,460). All procedures were carried out in accordance with the ethical standards of the Helsinki Declaration. Participants provided informed consent prior to the data collection. The study utilized data from the Chinese Longitudinal Healthy Longevity Survey (CLHLS), which is publicly available in the CLHLS repository, http://opendata.pku.edu.cn/dataset.xhtml?persistentId=10.18170/DVN/WBO7LK.



