PS01.1
Psychotherapy improves exercise tolerance in patients with “pink puffer” syndrome
Sherif Alsayed
New Jeddah Clinic Hospital, Jeddah, Saudi Arabia
Anxiety is common in the “pink puffer” syndrome associated with chronic obstructive pulmonary disease (COPD). The degree of anxiety correlates well with perceived dyspnoea. This study examines the effect of psychotherapy on anxiety, exercise tolerance, and dyspnoea. 10 patients with stable COPD (mean forced expiratory volume in one second (FEV1) = 1.25 L) had six 90 min sessions of cognitive and behavioural psychotherapy at weekly intervals. Patients completed the Beck Anxiety Inventory (BAI), 1 day before and 1 weeks after therapy. FEV1, forced vital capacity (FVC), blood gas tensions and 6 min walking distance (6MWD) were measured. 10 control patients attended weekly for lung function and 6MWD for 6 weeks, but had no psychotherapy. There were no differences in mean baseline (BAI) score, lung function, blood gas tensions or 6MWD between groups. After treatment, the BAI score had decreased from 43.10 to 20.6 (p< 0.001), in association, the mean 6MWD had also improved in the psychotherapy group only, from 333 to 559 m (p<0.001), an increase of 75%.
In conclusion, six sessions of cognitive and behavioural psychotherapy produced a good improvement in exercise tolerance in anxious patients with chronic obstructive pulmonary disease (pink puffer).
PS01.2
GERD and anxiety in patients with severe COPD
Sherif Alsayed
New Jeddah Clinic Hospital, Jeddah, Saudi Arabia
Objectives: to detect the impact of anxiety on shaping the prevalence of gastro-intestinal reflux disease (GERD) in patients with severe chronic obstructive pulmonary disease (COPD).
Methods: we examined the prevalence of symptomatic GERD, using the Vigneri score, in 29 male patients with COPD. Esophageal 24 h pH monitoring was used to document the diagnosis of GERD in symptomatic group. Beck Anxiety inventory was used to detect the impact of anxiety on expressing GERD symptoms.
Results: reflux disease symptoms were recorded in eighteen patients of the studied group (62%). GERD was diagnosed, based on esophageal 24 h PH monitoring, in only 11 patients of those expressing symptoms of GERD. Mean of Anxiety score was correlated significantly with the number and frequency of symptom presentation in patients with symptoms of GERD, reflecting the attribution of different symptoms of anxiety to the GERD syndrome. Also Anxiety scores correlated positively with time (total) PH reflecting the effect of anxiety on the severity of GERD syndrome.
Conclusion: Patients with severe chronic obstructive pulmonary disease have a high prevalence of symptomatic gastro-oesophageal reflux. However True GERD was documented in a fewer number of them. Psychological factors, such as anxiety and somatisation, may play a role, particularly in those patients without esophageal inflammation.
PS01.3
Démence: Prévention et approche psychothérapeutique dans le contexte d'un hôpital de jour de la clinique de la mémoire à Montréal
N Shamlian; Arthur Amyot; D Danis
Hopital Sacré-Coeur de Montréal, Montréal, QC, Canada
Dans le contexte d'un vieillissement appréhendé de la population et d'une augmentation de certaines pathologies telles les démences et des comorbidités neuropsychiatriques, le département de psychiatrie de l'hôpital du Sacré-Coeur de Montréal a développé une clinique de la mémoire depuis 2005.
Dans cette clinique, les professionnels de troisième ligne offrent des services de diagnostic et de traitement avec un retour à la première et deuxième ligne pour le suivi des patients. Avec l'expérience, il est devenu clair que les patients et leurs aidants se retrouvaient bien seuls pour faire face à l'annonce d'un diagnostic difficile et la mise en place d'un traitement approprié. Des ressources communautaires sont disponibles mais peu utilisées au début par le patient qui est plutot en phase de choc ou de déni face à une maladie difficile à accepter pour lui et sa famille.
C'est dans ce contexte, que nous avons pensé développer un service d'hôpital de jour afin de mettre en application les mesures de prévention en plus de débuter un traitement le plus rapidement possible avec un suivi approprié. De plus, le traitement peut alors offrir des interventions à la fois somatiques mais aussi psychothérapeutiques et de stimulation cognitive.
Il nous semble ainsi que nous offrons un lieu thérapeutique plus complet et diversifié tenant à la fois compte des aspects médicaux et de la souffrance psychique de cette population qui a trop peu accès à des soins adaptés.
Ainsi, Dre Shamlian présentera dans un premier temps des pistes de compréhension psychodynamique des patients souffrant de démence, ainsi que diverses approches thérapeutiques qui ont été tentées avec cette clientèle. Dans un deuxième temps, Dr Arthur Amyot présentera une illustration de l'approche psychothérapeutique auprès de patients de gérontopsychiatrie et de la clinique de la mémoire. Par la suite, Mr Danis présentera le projet de notre hôpital de jour d'un point de vue clinique et organisationnel.
PS01.4
Neighbourhood socioeconomic status predicts survival but not clinical diagnosis of cognitive decline: A report from the Canadian Study of Health and Aging
Melissa Andrew1; K Rockwood2
1Dalhousie University, Halifax, NS, Canada; 2Dalhousie University, Halifax, NS, Canada
Background: Neighbourhood socioeconomic conditions have been associated with several health outcomes. Whether contextual socioeconomic status (SES) increases risk of cognitive decline or mortality among older Canadians is unclear. We investigated whether neighbourhood-level income, income inequality, educational attainment, and unemployment influenced the risk of mortality or incident clinically-diagnosed cognitive decline (dementia or Cognitive Impairment, not Dementia; CIND) over ten years in a cohort of older Canadians.
Methods: 10,263 older adults aged 65+ years were followed for ten years in the Canadian Study of Health and Aging. Incident dementia and CIND were diagnosed using a screening interview followed by clinical examination. Baseline SES at the individual level was measured by educational attainment. Participants were linked to their community of residence using postal codes. Neighbourhood-level socioeconomic indicators were abstracted at the Census Enumeration Area. Associations between SES and mortality, incident CIND and dementia were calculated using logistic regression; analyses were adjusted for age, sex, and individual-level education.
Results: The mean age was 76.5 (SD 7.5) years, and 61% were women. Mean number of years of education was 9.9 (SD 3.9); 33% of the cohort had completed high school education (grade 12). By 10 years, 984 (9.6%) of the cohort had been diagnosed with incident dementia, 923 (9.0%) had been diagnosed with CIND, and 5150 (54%) had died. Lower neighbourhood-level SES was not associated with dementia or CIND diagnosis, but was associated with increased odds of death when each contextual factor was modeled separately. In a model including all SES factors, higher neighbourhood-level education predicted better odds of survival independent of individual-level educational attainment (OR 0.91, 95% CI:0.88–0.96, p<0.001).
Conclusion: In this cohort of older Canadians, lower neighbourhood SES was associated with increased odds of death but not with dementia or CIND diagnosis.
PS01.5
Clinical and neuropsychological risk factors to conversion of mild cognitive impairment to Alzheimer's disease
Julio Armas Castro
Policlínico Universitario Heroes de Giron, Havana City, Cuba
Background: Mild Cognitive Impairment defines a transitional stage between normal ageing and dementia, and reflects the clinical situation where a person has memory complaints and objective evidence of cognitive impairment but no evidence of dementia.
Aim: To investigate the clinical and neuropsychological risk factors associated of conversion to dementia of Alzheimer's type for subjects with Mild Cognitive Impairment (MCI).
Methods and Materials: Forty-two subjects consecutively recruited who met the operational criteria for MCI underwent multidimensional clinical assessment and a neuropsychological battery at baseline and at follow-up, after 6, 12 and 36 months. Diagnosis for Alzheimer's dementia was based on NINCDS-ADRDA criteria.
Results: Demented MCI were older (mean age 73.5–8.5 vs. 69.2–7.0; p<0.006) when compared to Stable and their global cognitive performances, at baseline, were more compromised when assessed by CAMCOG and by MMSE. Approximately 50% of MCI cases with memory impairment progressed to dementia. Demented were similarly compromised in basic activities of daily living but more compromised on instrumental daily functions. No effects of lifestyle, internal diseases or education were confirmed. The most important neuropsychological risk factors were results in Global CAMCOG test and subtests Orientation, Perception and Memory.
Conclusions: In subjects with MCI poor global cognitive performance at baseline, the worsening on executive functions and on functional status but not the worsening on memory functions are independently associated with the conversion to dementia of Alzheimer's type at 2 years follow-up.
PS01.6
Restless legs syndrome in the elderly: Prevalence, impact on quality of sleep and association with major depressive disorder
Jae Nam Bae1; W Kim1; B Kim2; S Kim5; S Chang3; D Lee4; M Cho2
1Inha University Hospital, Incheon, South Korea; 2Seoul National University Hospital, Seoul, South Korea; 3Kyungpook National University Hospital, Daegu, South Korea; 4Inje University College of Medicine, Seoul, South Korea; 5In-Gwang Mental Hospital, Gwangju, South Korea
Background: In older population, prevalence of RLS seems to increase although it is not proven yet. A few studies have examined the potential association between RLS and major depressive disorder in older population.
Objective: We examined the prevalence of RLS, association between RLS and demographic variables, impact of RLS on quality of sleep, and the association between RLS and major depressive disorder in elderly population.
Methods: Face-to-face household survey was conducted in four different regions of Korea from June 2008 to August 2008. There were 2,524 subjects, aged more than 65, and the response rate was 69.0% (number of responders was 1,738). The diagnosis of RLS was made by using the RLS questionnaire (the Korean version of Paradigm of questions for epidemiology studies of RLS). Past medical histories were grouped as nine disease categories which physician diagnosed. Nine disease categories were as follows: hypertension, diabetes mellitus, hyperlipidemia, stroke, heart disease (angina, arrhythmia, heart failure, myocardial infarction), atherosclerosis, peripheral vessel disease, abdominal aortic aneurysm, anemia, and renal disease. The quality of sleep was measured by five items of insomnia severity index. Major depressive disorder was diagnosed by the diagnostic section of depressive disorder in Korean version of composite international diagnostic interview (K-CIDI).
Results: The prevalence of RLS in older population was 10.7% (men 8.9%; women 11.9%) and it seemed to increase with age, reaching a peak prevalence of 18.5% in the elderly aged more than 90. 21.5% of subjects with RLS and 31.0% of subjects without RLS had past medical history. Anemia and renal diseases had significant association with RLS (p<0.05). The subjects with RLS reported to have worse quality of sleep in five items of insomnia severity index than subjects without RLS (P<0.001). 31.2% of subjects with RLS and 17.5% of subjects without RLS had major depressive disorder. Odd ratios with confidence interval (1.99, [1.40, 2.82]) for risk of major depressive disorder suggested strong association between RLS and major depressive disorder.
Conclusion: Major depressive disorder may be one of the important risk factors for RLS. Future investigations should focus on the mechanism underlying the association between RLS and major depressive disorder.
PS01.7
Addressing needs of comfort, social attention and sensory stimulation to reduce verbally disruptive behaviors in nursing home residents
Annick Bedard1; P Landreville1; P Voyer2; R Verreault3; J Vezina1
1Universite Laval, Quebec, QC, Canada; 2Universite Laval, Quebec, QC, Canada; 3Universite Laval, Quebec, QC, Canada
Introduction: Verbally disruptive behaviors (VDB) is a frequent behavioral symptom of dementia. It refers to verbal or vocal behavior which is repetitive, disruptive or inappropriate such as screaming, repetitive requests or cursing. VDB manifested by dementia patients can be interpreted as means to express unsatisfied needs. The objective of this study is to assess the efficacy of an intervention based on the need-driven dementia-compromised behaviors model to reduce VDB in dementia residents in long-term care facilities.
Methods: A single-group repeated-measure design was used with 26 participants. The intervention addresses three needs that seem important in dementia nursing home patients with VDB: comfort, social attention and stimulation. It uses different strategies to correct some sources of discomfort and to provide social interaction and sensory stimulation. It was applied during six 30-minutes sessions by trained therapists and was individualized for each participant. The frequency and duration of VDB were measured with real-time computer-assisted direct observation. These observations were realized by non-participant trained observers and taken several times before, during, and after the treatment.
Results: The results reveal a progressive decline of VDB frequency across the experimental phases and a statistically significant reduction of VDB duration during the intervention phase compared with baseline. However, the intervention effect on VDB duration is limited to the period during which participants are exposed to the treatment. Over half (54%) of participants present a behaviorally important improvement of VDB duration (>50% reduction) during the treatment phase.
Conclusion: The intervention seems to be effective to reduce VDB duration and improve the behaviour of an important proportion of patients.
PS01.8
Improve GP use of screening for cognitive impairment: The GPCOG website
Henry Brodaty1; D Pond3; B Draper2; K Seeher2
1University of New South Wales, Coogee, NSW, Australia; 2Prince of Wales Hospital, Randwick, NSW, Australia; 3University of Newcastle, Newcastle, NSW, Australia
Background: Alzheimer's disease and other types of dementia are the main cause of disability among the elderly. It is estimated that the number of people with dementia will double every 20 years, leading to more than 100 million people affected by 2050. Yet, dementia is often under-diagnosed. General Practitioners (GP)—as the main source of medical care for this clientele—blame lack of time and paucity of suitable screening instruments for under-diagnosing dementia. The General Practitioner Assessment of Cognition (GPCOG) is a reliable, valid and efficient instrument to screen for dementia specifically in a primary care setting. It takes less than 6 minutes to administer both the patient and the caregiver interview and it performs at least as well as the standard screening tool, the Mini-mental State Examination (MMSE). It is available in various languages including English, French, Spanish, Italian, Greek, German and Mandarin/Cantonese. Recent reviews of dementia screening tools for the primary care setting recommended the use of the GPCOG and claimed the importance of making computerized screening tools available.
Aims: In order to enhance GP screening for cognitive impairment and diagnosis of dementia, we aimed to establish and promulgate a website that provides electronic versions of the GPCOG and dementia assessment and management guidelines to primary care practitioners (PCPs), i.e. GPs and associated Nurse Practitioners as well as to assess the take up rates and utility of the website and these aids.
Method: Support was received from the International Collaboration for the Care of the Elderly (ICCE), Canada, and the National Initiative for the Care of the Elderly (NICE), Canada. Qualitative interviews with GPs were conducted to explore the requirements of such a website. Moreover, an extensive literature research on available national and international guidelines for assessment and management of dementia patients in primary care was performed. In total 22 guidelines from 14 countries were found, of which ten were suitable for the primary care setting and have been made available on the website. The use of this website is free of charge, is available in various languages and can be accessed on www.gpcog.com.au. The website also contains a very brief feedback questionnaire which can be completed by the GP after administering the GPCOG online. Anonymous website related data will be used for evaluation of website.
Results: Evaluation of the website is currently underway; results are expected in mid-2009.
Conclusion: The multi-lingual website www.gpcog.com.au makes a screening tool for cognitive impairment (the GPCOG) available to GPs all over the world. It provides health professionals with national and international guidelines and gives recommendations for further investigations that should be conducted once cognitive impairment is indicated.
PS01.9
Complex behaviours in acute care: An Australian approach
Kelly Burns
Peninsula Health, Frankston, VIC, Australia
Caring for patients with complex behaviours in the acute care setting is met with many challenges and risks for the patient, staff and the organisation. Providing staffing resource at Peninsula Health, Victoria, Australia to manage these complex patients was found to lack continuity of care, specialised skill and clear care goals. These concerns were identified as leading to further care issues for patients such as use of restraint, over prescribing of psychotropic medication and associated side effects, further confusion, functional decline and increased length of stay. In addition, these care issues placed a high demand on extra staffing resources and nurse bank was unable to meet this demand relying on agency nurses at an increased financial cost. The quality of care for individual patients did not significantly improve as a result of the amount of resource spent. An innovative approach needed to be sought.
The Cognition Care Support Team (CCST) is a unique team of trained staff incorporating Division 2 Registered Nurses, Personal Care Attendants and a Diversional Therapist. The CCST are dedicated to delivering increased supervision and supportive care to patients who are identified to be at risk or who place others at risk due to their memory or thinking difficulties. The team responds to the individual needs of the patient who may require support for behaviours of concern such as agitation, interference with therapies, wandering, high risk of falls, or mental illness.
The team initiate the process of behaviour assessment, observation & monitoring, carer liaison, and develop a behaviour management plan. The team also provide Diversional activities to promote engagement and positive stimulation aimed at maintaining and improving the level of physical and cognitive function. The team promote confusion minimisation to prevent potential for decline.
The aim of the team is to reduce and minimise behaviours of concern (BOC), thereby moderating the potential for further complications such as unnecessary prescribing of medications and use of restraint, hence minimising functional decline, dehydration, falls risk and the risk of further confusion. Additional outcomes include reduction in the length of time required for individualised 1:1 care, which will potentially reduce the length of stay. The team also provides support for the ward staff in ongoing care of the patient through an effective management plan and through education resulting in modifying risk as trained staff will recognise and report behavioural changes early. The team further provides support and liaison with the family/carer.
This presentation will provide some insight into the challenges faced when introducing such a team and will discuss evaluation outcomes. How does this team work in practice? Have we demonstrated direct benefits to the patient, staff and Peninsula Health? What are the emerging trends from this project?
PS01.10
Psychoeducational intervention program: Effects on the attitudes and health perception of caregivers of patients with schizophrenia
Alejandra Caqueo-Urízar1; J Gutiérrez-Maldonado2; M Ferrer-Gracía2
1University of Tarapacá, Arica, Chile; 2University of Barcelona, Barcelona, Spain
Background: In recent years there has been increased interest in the role played by families in the treatment of patients with schizophrenia. Some family interventions may significantly reduce clinical difficulties and may have a positive impact, both emotionally and economically. The aim of this study is to assess the efficacy of a family psychoeducational program in changing attitude and health perception in relatives of patients with schizophrenia.
Methods: Sample: 45 relatives, usual caregivers of patients with schizophrenia at a public mental health outpatient centre in Arica (Chile).
Instruments: Attitudes of Relatives toward Schizophrenia Questionnaire and General Health Questionnaire SF-36.
Procedure: The sample was randomly divided into a control group, in which caregivers received the usual treatment (a monthly interview with a psychiatric nurse), and an experimental group, which participated in a family psychoeducational intervention program in addition to the usual treatment. Medication remained unchanged in both groups.
Results: The psychoeducational program was effective in modifying caregivers' attitudes. However, it had no effect on their health perception.
Conclusions: This family psychoeducational treatment program modifies the negative attitudes of relatives towards schizophrenia. However, health problems may not be improved by programs of this kind, or it may be that the effects of these interventions are seen only in the long term.
PS01.11
The feasibility of serving liquid yoghurt supplemented with probiotic bacteria
Maine Carlsson1; Y Gustafson1; L Håglin2; S Eriksson1
1Geriatric Medicine, Umeå, Sweden; 2Family Medicine, Umeå, Sweden
Constipation and body weight loss are prevalent among old people. Treatment with different species of lactic acid bacteria has been suggested for various forms of gastrointestinal disorders. This pilot study was performed to assess the feasibility of administering and consuming a drinkable yoghurt containing Lactobacillus rhamnosus LB 21 and Lactococcus L1A, and to evaluate the influence on bowel movements and body weight in 15 people with dementia, aged 65–95 years, in residential care facility. A drinkable yoghurt (Verum Drickyoghurt(c)) with added bacteria was served daily for 6 months in conjunction with ordinary food intake. Body weight, bowel movement frequency and consistency, food and fluid intake and time spent in various activities were recorded for two weeks pre-intervention, and 3 times during the follow-up period. This study showed that the yoghurt was easy to serve, with few side effects for the participants and that the various recording forms and diaries were easy for the staff to complete. The extra intake of yoghurt did not have any detectable beneficial effect on bowel movements. The overnight fast was almost 15 hours per day. Body weight decreased by 0.65 kg/month (95% confidence interval. 0.27–0.97). The present study design was feasible in this group of old people with dementia. The absence of any detectable effect of the supplement on constipation, but rather a considerable loss in body weight, indicate that further research is needed in a large randomised controlled trial, if associations between dementia, constipation and energy balance are to be understood.
PS01.12
Aging and schizophrenia
David Casey
University of Louisville, Louisville, KY, United States
Schizophrenia is generally described as a chronic psychotic disorder, but is associated with a number of controversies. These include its definition and boundaries, as well as its relationship with other disorders. In this presentation, the controversies to be explored include the relationship of late-life onset psychosis with early-life onset schizophrenia and whether these should be considered as one or several disorders. Also, issues associated with cognitive loss and schizophrenia will be discussed, including characterization, disability, and treatment of these problems. Finally, the growing body of knowledge pertaining to medical co-morbidity and schizophrenia will be presented. These will include its association with type II diabetes mellitus, the metabolic syndrome, cardiovascular disease, obesity, smoking, substance abuse, and premature death. The possible roles of iatrogenic factors in these medical issues, including the atypical antipsychotics, will be discussed. Poor self-care, diet, and medical non-adherence may also play important roles. Recent research has highlighted an enormous association between schizophrenia and reduced life span, by several decades. This presents a challenge to the medical community: reinterpret schizophrenia as a chronic, multi-faceted medical condition whose treatment includes coordinated medical, social, and psychiatric care.
PS01.13
Palliative care, geriatric psychiatry and dementia care
David Casey
University of Louisville, Louisville, KY, United States
Palliative care is an interdisciplinary approach that is focused on relief of pain and suffering in advanced or terminal illness. It emphasizes a cope rather than cure approach. The focus is on symptom management, psychosocial support, communication, coordinated care, and grief and bereavement support for patients and families. Palliative care approaches avoid intensive medical interventions. Hospice is a related concept. Psychiatric symptoms are a part of death and dying but often go unrecognized and untreated. Depression, anxiety, eating problems, and fatigue are important symptoms with psychiatric implications. Psychiatric mortality of this type at the end of life is a treatable condition. Psychiatrists or other physicians may not be trained or prepared to deal with the end of life. Depression may occur in up to 50% of terminal patients, while delirium may be present in up to 80%. Psychiatric issues at the end of life are important in any age group—children, adults, and especially geriatric patients, who are at the greatest risk of death. Death and dying often present ethical and spiritual issues that psychiatrists can use their clinical skills to address. Terminal illness may also occur in the context of chronic psychiatric disorders such as schizophrenia. The psychiatrist is usually a consultant to the multidisciplinary team, managing psychiatric issues and assisting in managing pain and family issues. Psychotherapy—existential, dynamic, CBT, or supportive—may be helpful. The psychiatrist also plays a liaison role in educating and supporting staff, as well as helping staff and families understand and cope with difficult patient behaviors. Psychiatrists may be confronted with personality disorders, which may include hostility, splitting, abandonment fears, dependency issues, and non-adherence. Psychiatrists are trained in communication and may assist in resolving conflicts on the team, with patients, or among family members. Psychiatrists are also alert to differences in approaches to illness and death in different cultures.
Dementia is of particular interest to geriatric psychiatrists. Most dementias, including Alzheimer's disease, are incurable. Alzheimer's disease is progressive, disabling, and significantly shortens life span. Therefore, it can be conceptualized as a terminal disorder. Median survival after diagnosis varies by study but may be approximated at about 4.5 years. Nursing home patients with dementia have on average about a 2 year survival. Dementia is associated with psychological distress and many patients have physical pain, which may contribute greatly to behavioral problems but which is difficult to recognize. Significant medical co-morbidity is common. A traditional medical approach seeks definitive management of these comorbid conditions. This requires a motivated, cooperative patient who can make treatment decisions. Dementia patients are increasingly unable to make such decisions, express preferences, or participate in their own care. They may resist medical procedures, requiring sedation or restraint. Medical specialists may struggle with the ethics of treatment/no treatment decisions. Family conflict over these management decisions is common. Acknowledging the terminal nature of dementia permits a shift to a palliative care approach—especially in advanced dementia. Emphasis should be on relief of suffering in the near term. This treatment philosophy recognizes that an aggressive or intrusive approach to comorbid conditions may be fruitless or even counterproductive. This should lead to a review of goals of treatment for both new and chronic medical conditions, including diagnostic procedures, hospitalization, and medications. Frequently, medications used for long term management of chronic medical conditions contribute little in this setting and may be discontinued. Limiting polypharmacy is a key to reducing delirium. Nutrition is always an issue. Feeding tubes are rarely useful in advanced dementia. These decisions require a case-by-case approach, and may not allow for the usual practice guidelines for the co-morbid conditions. They also embody value judgments rather than only medical judgments.
PS01.14
Spiritual feeling in elderly people: An empirical research
Giovanni Cesa-Bianchi; C Cristini
Psychology Section, Milan, Italy
Introduction: Spiritual feeling in the elderly age appears more frequently and acquires some features, produced by specific behaviour and mental attitudes. Spirituality in elderly people often steers and ascribes a peculiar significance to the personal meaning of life. Furthermore many elderly people imagine an afterlife expressing present desires.
Hypotheses: 1) Females have a more spiritual feeling than males; 2) the practices regarding spirituality are more active in elderly people who live in rural areas; 3) institutionalized people attend spiritual TV-ceremonies more than domiciled.
Methods: The researchers interviewed 150 over sixty-five people (75 F., 75 M.), belonging to two age groups (under and above 75 years): domiciled and institutionalized, living in rural and urban areas.
Materials: A) Questionnaire applied through a semistructured interview with many areas; B) Geriatric Depression Scale (GDS); C) Self Depression Scale by Zung W.W.K. (SDS); D) Mini-Mental State Examination (MMSE). We have excluded the persons with MMSE scores <24. Chi square has been applied.
Results: Women (89.33%) seem more faithful than men (73.33%) and more used to expressing their spirituality (X = 7.7563, p < 0.01), especially in the country areas. There are more faithful widows (X = 6.0874, p < 0.25) and single women (X = 6.3232, p < 0.25), especially over 75 years old. People of middle-low education (84.62%) are more spiritual. Only 57.14% of graduated admit to being faithful (X = 5.1974, p < 0.25). Spiritual feeling is supported by practices like prayer (often before sleeping) and the participation in spiritual and ritual ceremonies, which is more frequent in women (57.33%) than in men (24.67%) and especially over 75 years old in country areas. Many institutionalized people attend religious TV-ceremonies, especially institutionalized women over 75 years of age. Most elderly people, especially men, domiciled and living in city areas, don't report specific images of afterlife (X = 4.1823, p < 0.5). Predominant images concern tranquility, peace and freedom, especially in institutionalized people and above all in those who are no longer independant or in individuals who are ill. GDS and SDS show a greater change of mood in women, in elderly institutionalized people and those living in city areas; the spiritual feeling and practices seem to improve the levels of mood.
Conclusions: Spiritual feeling is particularly frequent and active in many elderly people, especially women over 75 years of age, living in rural areas; it experiences socio-cultural, historical, traditional and environmental influence, but also emotional modulations expressed by relief desires and meaning interpretations.
PS01.15
Predictors of change in health-related quality of life among older people with depression: A longitudinal study
Sally Chan; H Chiu; W Chien; W Goggins; D Thompson
The Chinese University of Hong Kong, Hong Kong, SAR PR China
Background: The World Health Organization projects that depressive disorder will be the second leading cause of disability in the world by 2020. Depression is the most prevalent functional mental disorder in later life. Hong Kong, one of China's special administrative regions, has a population of about 7 million, of which 12.5% are aged 65 or above. It is estimated that about 5% (40,000) of the elderly population suffers from depression. To date, there is a limited understanding of the link between the treatment of depression and improvement in HRQoL. The majority of available studies of HRQoL are cross-sectional and seldom provide information on important predictors of HRQoL over time in the elderly population. Further, the majority of available studies have been conducted in Western countries, so the findings of such studies may not be applicable to non-Western cultures.
Objective: To identify predictors of change in health-related quality of life (HRQoL) among older people with depression.
Design: A longitudinal study with data collected at the time of the first consultation of participants at a regional outpatient department in Hong Kong and 12 months later.
Sample: A convenience sample of older depressed patients was recruited from one regional psychogeriatric OPD in Hong Kong. The inclusion criteria were: age ≥65, Hong Kong Chinese resident, residing in the community, a diagnosis of depressive disorder according to the criteria of the Diagnostic and Statistical Manual of Mental Disorders IV (DSM-IV) (American Psychiatric Association, 2000), and the ability to understand and speak Cantonese. A total of 77 participants were recruited.
Measures: Physical Health Condition Checklist, Geriatric Depression Scale (GDS), Modified Barthel Index (MBI), Instrumental Activities of Daily Living (IADL) scale, Social Support Questionnaire (SSQ), and World Health Organization Quality of Life Scale-Brief Version (WHOQOL).
Results: The participants had a mean age of 72.7 (SD = 5.1) (range: 65–86). Sixty-one (79.2%) of the 77 subjects were female. Many were illiterate (36.8%) or had only primary-level education (53.9%). The sample was almost equally split between those married (46.8%) and widowed (42.9%), with the rest being divorced (10.4%). All patients were taking antidepressant medication. Significant improvements between the first and second assessments were noted in the Physical Health Condition Checklist, MBI, and GDS scores, the number of the social support subscales of the SSQ, and the total WHOQOL scores. The results of linear regression models showed that the increases in the Physical Health Condition and IADL scores and decreases in the GDS scores were significantly associated with higher final WHOQOL scores.
Discussion and conclusion: Interventions for depression were effective in improving the participants' overall condition and their perceived HRQoL. Interventions to alleviate the level of depression of older people, promote their physical health, enhance their instrumental activities of daily living ability and social relationship could help improve their perceived HRQoL. This study highlights the need for a holistic and interdisciplinary approach to planning innovative services to meet the health needs of this target group.
PS01.16
Prevalence of behavioural and psychological symptoms in Chinese older persons with dementia and mild cognitive impairment: A population-based study
Wai Chi Chan1; L Lam2; C Tam2; V Lui2; S Chan2; W Chan3; H Chiu2
1Castle Peak Hospital, Hong Kong, SAR PR China; 2Chinese University of Hong Kong, Hong Kong, SAR PR China; 3Department of Health, Hong Kong, SAR PR China
Background: Behavioural and psychological symptoms are associated with significant deleterious effects on both care-recipients and caregivers. While epidemiological data are fundamental to understanding BPSD, except for a few population-based studies conducted in the developed countries, most existing information is based on convenience clinic samples. To our knowledge, there has been no population-based study examining BPSD in community-dwelling older adults with dementia or mild cognitive impairment (MCI) in Asian communities.
Methods: This survey was conducted in Hong Kong from 2005 to 2006. We recruited 934 community-dwelling older adults (137 with dementia, 226 with MCI, 571 normal controls). BPSD were assessed using the Chinese version of Neuropsychiatric Inventory (CNPI). The prevalence of BPSD were determined. Principal components factor analysis with varimax rotation was computed on the CNPI subscores to identify behavioural syndromes.
Results: The prevalence of BPSD in persons with dementia, MCI and normal controls were 58.0%, 37.8% and 26.1% respectively. Apathy, depression, and night-time behavioural disturbance were the most common symptoms. Three factors accounting for 51.7% of variance were identified: (1) motivation/mood factor: depression/dysphoria, anxiety, apathy, night-time behavioural disturbance, and changes in appetite and eating behaviour; (2) frontal factor: agitation, disinhibition, irritability/lability, and aberrant motor behaviour; and (3) psychotic factor: delusions and hallucinations.
Conclusions: This is the first population-based study looking into BPSD in Chinese older adults with dementia and MCI. As in developed countries, BPSD among Chinese are common. Similar behavioural syndromes (factors) are also identified in the study.
PS01.17
Treatment in elderly psychotic patients: Experience in amisulpride
Jen-Yeu Chen; T Chen; M Chen; G Mo; Y Liu; L Kung; Y Yu
Yu-Li Veterans Hospital, Yuli, Taiwan
Objective: The primary objective of this study was to evaluate the tolerability of treatment with amisulpride in elderly chronic patients with psychosis aged over 60 years; evaluation of efficacy was a secondary objective.
Methods: The study included patients of either sex aged 60 years or older fulfilling DSM-IV diagnostic criteria for psychotic disorders and who presented psychotic symptoms severe enough to require antipsychotic medication. Subjects were selected from a chronic mental hospital. They had been treated with antipsychotics for many years and were switched to amisulpride with flexible dose for twelve weeks. Safety assessment involved adverse event reporting, physical examination, blood pressure, heart rate and ECG monitoring, and laboratory tests. Extrapyramidal symptoms were evaluated with the Simpson-Angus Scale, Barnes Akathisia Scale and the AIMS. Efficacy parameters were changes in score on the PANSS, CGI and CASI.
Results: Forty-four patients (mean age: 67.0±5.7 years) were included, and thirty-three patients completed 12-week study. Eleven patients discontinued the study due to the emergence of acute psychotic episode. Mean dosage of antipsychotics equivalent to chloropromazine in baseline is 331.25±293.5 mg, and mean dosage of amisulpride at end point is 347.67±205.27 mg/day. The PANSS total score mildly decreased at the end of study with no significant difference. Significant improvement of negative symptom domain in PANSS scale was noted in the end of study. Mild increase of SAS score was noted in the end of study compared to baseline with no significance. No significant change of extrapyramidal symptoms was seen after switching to amisulpride. No change of ECG or biochemical data, such as fasting glucose, cholesterol, and triglyceride, between baseline and end point was found.
Conclusion: Amisulpride is generally well tolerated in elderly patients with psychosis, and was efficacious in this study population.
PS01.18
Sensitivity and specificity of the PHQ-9 for depression in elderly Chinese patients in primary care
Shulin Chen
Zhejiang University, Hangzhou, China
Introduction: The PHQ-9 is well validated for use in primary care, addresses both depression severity and diagnosis, and facilitates communication among primary care clinicians, care managers, and the collaborating psychiatrists. This study was designed to determine the suitability of the PHQ-9 for use in the Chinese primary care setting and to test the sensitivity and specificity with elderly primary care patients.
Methods: Measures: 1) The Mandarin version of the Patient Health Questionnaire (PHQ-9) was used to screen for depression; 2) the Structured Clinical Interview for DSM-IV (SCID) mood disorders module was used to establish the diagnosis of major affective disorder. Subjects: 350 people aged ≥60 years who visited the primary care clinic were invited to participate in the study. The remaining 284 subjects constitute the sample examined here, a response rate of 81%. Procedure: The PHQ-9 was administered by primary care clinic nurses trained in its use. All subjects who scored ≥10 on PHQ-9, and 5% of those who scored <10 were contacted within one week by study personnel who scheduled a SCID interview. Statistical analysis: Feasibility measures of interest included training, administration time, administration difficulties, scoring time, scoring problems, and sensitivity and specificity of the PHQ-9 for depression, suing the SCID diagnosis as the reference standard.
Results: Distribution of PHQ-9 scores according to depression diagnostic status: Depression diagnostic status was determined by 2 psychiatric nurses using the SCID interview. There were 52 (18.3%) participants with PHQ-9 score ≥10. Twelve participants (5%) with PHQ-9 score <10 were also selected to be interviewed by the psychiatric nurses. In the total 64 participants entering the interview program, 39 participants were diagnosed as depressive disorder, including 31 patients with major depression, 3 with dysthmic depression and 5 with mild depression. The mean PHQ-9 score was 14.4 (SD, 3.6) in the 39 patients with depression, and 3.6 (SD, 3.4) in the 245 participants with no depressive disorder. Most patients (89.7%) with depression had scores of 10 or greater on PHQ-9 (see Table 2).
Reliability and efficiency of the PHQ-9: Training time for the two nurses in primary care consisted of about 45 minutes reviewing the purpose, format, items, scoring, and sample responses. Duration of administration of the PHQ-9 by interview format ranged from 4–12 minutes, and the mean time was 6.3 minutes (SD, 2.1). No major administration difficulties were reported, and no subject was unable to complete the PHQ-9 or objected to the content of the items. The internal reliability of the PHQ-9 was excellent with a Cronbach's a of 0.91.
Criterion validity: The sensitivity and specificity of the PHQ-9 are shown in Table 1. At the cutpoint ≥5, the sensitivity and specificity of the measure were 100% and 71.8% respectively; using the cutpoint of ≥10, the sensitivity and specificity were 84.6% and 96.7%.
Receiver operating characteristic (ROC) curve analysis supports the criterion validity of the PHQ-9 in successfully differentiating between depressed and nondepressed participants (AUC = 0.91, standard errors = 0.03, 95% confidence interval = 0.86–0.97).
Discussion: We found the PHQ-9 to be an easy instrument to use for screening for older depression in the Chinese primary care settings. Administration was straightforward, training time was minimal, and subject acceptance was high. The PHQ-9 also demonstrated high criterion validity for the diagnosis of depression. The sensitivity and specificity were 84.6% and 96.7% respectively at the cutpoint ≥10. Like the English version of the scale, the Chinese PHQ-9 is an efficient and reliable screening measure for late life depression. It is useful as a research measure for estimating the prevalence of depression and as a clinical aid to the primary care clinician in China.
PS01.19
The effect of memantine on serum total antioxidant capacity in Alzheimer's dementia
Jin Sook Cheon1; B Oh2; H Kim3; W Cho4; J Lee5; H Yoon6
1Kosin University College of Medicine & Gospel Hospital, Busan, South Korea; 2Yonsei University Severance Mental Health Hospital, Kyungido Kwangju, South Korea; 3Guduk Hospital, Busan, South Korea; 4Dongsuh Hospital, Masan, South Korea; 5Joeungangan Hospital, Gimhae, South Korea; 6Jinyounghansuh Hospital, Gimhae, South Korea
Objectives: To evaluate whether memantine causes change in a peripheral blood marker of oxidative stress, to identify influencing factors, and to suggest its usefulness to measure the effect of memantine in clinical practice.
Methods: The subjects were 66 patients with Alzheimer's dementia and 60 healthy controls. The demographic data were obtained by structured interviews. The cognitive disorder was assessed by the MMSE, severity of dementia by the CDR and the GDS, and function by the ADL. The serum total antioxidant capacity (TAC) was measured by chemiluminescence method, once in the control group and three times (before memantine administration, 1 month after memantine administration and 2 months after memantine administration) in the patient group.
Results: 1) As compared with TAC before memantine administration (mean 1.762, SD 0.133mmol/L), TAC (mean 2.096, SD 0.172 mmol/L) increased at 2 months after, higher than TAC at 1 month after (mean 1.865, SD 0.283 mmol/L) and TAC of controls (mean 1.935, SD 0.194 mmol/L) (p<0.001, respectively). 2) TAC of patient group was different according to MMSE, CDR, GDS and ADL before, according to sex and age at 1 month after, and according to ADL at 2 months after memantine administration (p<0.05, respectively). 3) Effect of memantine on TAC correlated with sex, age and duration of dementia at 1 month after memantine, and with severity of dementia (CDR and GDS, p<0.05 respectively) and function (ADL, p<0.05) at 2 months after memantine administration.
Conclusion: To evaluate effect of memantine treatment on moderate to severe Alzheimer's dementia, a peripheral blood marker of oxidative stress seemed to be preferable to clinical scales.
PS01.20
Is HPA-axis functioning associated with cognitive functioning in older persons?
Hannie Comijs1; L Gerritsen2; D Deeg1; B Penninx1; M Geerlings2
1VU University Medical Center, Amsterdam, Netherlands; 2University Medical Center Utrecht, Utrecht, Netherlands
It was investigated whether cortisol levels were associated with cognitive decline in older persons and whether this association was modified by the sex, age and APOE-ε4. Data were used from LASA, an ongoing population-based cohort study (55–85 years) with follow-up measurements every three years. Blood cortisol levels were available from 1,509 persons and levels of salivary cortisol after awakening and late in the evening were available from 1,069 persons. During all measurements global cognitive functioning, memory performance and processing speed and potential confounders were assessed. With linear mixed models the associations between cortisol and cognitive outcomes were estimated, adjusted for confounding variables.
High levels of cortisol were associated with poorer performance on verbal learning. High levels of cortisol were also associated with slower speed of information processing in women, but not in men.
With respect to cognitive decline over a period of 4 years, we found that lower morning salivary cortisol levels, higher evening cortisol levels, and flattened diurnal variability of cortisol levels were associated with increased risk for memory decline in APOE-ε4 carriers but not in non-carriers. Cortisol levels were not associated with decline in global cognitive functioning or information processing speed in APOE-ε4 carriers or in non-carriers.
In conclusion, in this older population, higher levels of both blood and salivary cortisol were associated with poorer memory functions, and with a higher rate of decline in memory, but the latter only in APOE-ε4 carriers.
PS01.21
Opinions and emotions in elderly people living in a nursing home
Carlo Cristini; G Cesa-Bianchi
University of Brescia, Brescia, Italy
Introduction: The increase of elderly population implies more psychogeriatric disorders; many ill, alone, poor, emarginated people need a peculiar attention, understanding, holding; they often desire a safe, curative and restful environment like an efficient nursing home; especially persons presenting a mild cognitive impairment need a sensible acceptation and a possibility to express their opinions and emotions.
Methods: The investigation aim was to examine emotions, opinions, and habits in institutionalized people of different age (under and above 75 years old), females and males, healthy or with cognitive decline.
Hypotheses: 1) Institutionalized elderly people could have some difficulties expressing their emotions; 2) cognitive levels differentiate the relationship and communication; 3) in nursing homes, males seem to be less involved by maladjustment.
Materials: 1) Multiareas questionnaires presented in semistructured interview; 2) Geriatric Depression Scale (GDS); 3) Self Depression Scale by Zung W.W.K. (SDS); 4) Zung Self-Rating Anxiety Scale (SAS); 5) Mini-Mental State Examination (MMSE). We have interviewed 80 institutionalized people (41 F., 39 M.), 40 with MMSE score <24 (A group, with cognitive decline) and 40 with MSSE scores >24 (B group, healthy). Chi square has been applied.
Results: average age is 79.07 years. Level of education is low. In the A group there are more widows (X = 4.0525 p. < 05). They are more satisfied towards sleep, health, autonomy, and take more drugs. Illness is considered a natural event (65.00%), especially after seventy-five years, bad luck (36.25%), restriction (20.00%), fatality (15.00%) especially the A group (X = 9.8039 p. < 005). Present condition of life is acceptance (55.00%), especially after seventy-five, sadness (31.25%), especially the A group. Persons seem satisfied about their life (68.65%), about housing (70.00%) especially the A group, about assistance (71.25%), about relationship with other guests (65.00%). The future causes feelings of worry (32.50%) more in women, serenity (33.33%), especially in the A group (X = 9.8327 p < .005), sadness (23.75%), fear, especially in women, (X = 5.8163 p < .025), trust, especially A group, (X = 6.1346 p.<025). The sample desires a quiet death (53.75%), especially after seventy-five, and good health (41.25%); it feels respected in its own privacy; nevertheless some women display trouble, shame, mortification; only 31.25%, especially men, express emotions; some persons wish to communicate their emotions, but don't, especially the A group (X = 9.8327 p < .005). Sexual interest appears especially in men (X = 11.8805 p<.001). 38,75% express anger, especially men, the A group more weeping (X = 9.9282 P<.005); 23.75% are afraid to be left alone, 21.75% to be not understood, to be ignored: in A group more women (X = 6.3865 p<.01); 65.00% perceives a positive opinion by other persons, 48.75% thinks to induce respect, more men and B group (X = 4.0525 p<.05), 28.75% love. GDS and SDS have showed more depression levels in women and in A group.
Conclusions: The B group has given more answers, but, qualitatively, answers seem to overlap in two groups. Institutionalized men seem more reassured, especially after seventy-five years; women seem less adjusted to admission, and to losing health and autonomy. Elderly people presenting cognitive problems feel more the protective function of admission and highlight communicational and relational value of emotions.
PS01.22
Relationships between locomotor activity and cognitive performance in Alzheimer's disease
R David1; E Mulin1; N Bordone1; A Rivet1; L Friedman2; J Zeitzer2; J Yesavage3; P Robert1
1Centre Mémoire de Ressources et de Recherche, Nice, France; 2Stanford University, Stanford, CA, United States; 3VA Palo Alto Health Care System, Palo Alto, CA, United States
Objectives: To evaluate relationships between daytime motor activity (using ambulatory actigraphy) and scores on neuropsychological evaluation.
Material and method: Thirty subjects with diagnosis of mild AD (age = 79.2 ± 6.29; MMSE = 21.5 ± 3.1) were recruited at the Nice Memory Center, and were divided in two subgroups (presence or absence of apathy) according to the Diagnostic Criteria of Apathy (DCA, 2009).
Locomotor activity was assessed using a wrist-worn actigraph for 75 minutes, during which a neuropsychological and behavioral examination were performed (60 minutes) followed by 15 minutes of free activity.
General cognitive status was determined in the course of a comprehensive clinical assessment and included the Mini Mental State Examination (MMSE), Trail Making Test (TMT, parts A and B), digit spans (WAIS III-R), phonological and semantic verbal Fluency, a naming test (DO 80) and the Frontal Assessment Battery at bedside (FAB).
Results: Apathy and No apathy subgroups were equivalent in terms of age, sex ratio, MMSE and MADRS score.
AD patients with apathy had significant lower mean motor activity (p < 0.01), lower total score on Frontal Assessment Battery (FAB) (p < 0.05) and performed significantly lower on verbal fluency task (p < 0.05). Moreover, mean motor activity correlated negatively with TMT B score (p < 0.05) and positively with FAB (p < 0.01) and spans scores (p < 0.05).
Conclusion: Reduced daytime levels of motor activity were associated with reduced performances on frontal and executive tasks in mild Alzheimer's disease.
PS01.23
The NPI-C: A clinician-rated assessment of neuropsychiatric symptoms in dementia
Kate de Medeiros1; P Robert2; S Gauthier3; F Stella4; A Politis5; F Taragano6; J Kremer7; A Brugnolo8; A Porsteinsson9; Y Geda10; H Brodaty11; C Lyketsos12
1The Copper Ridge Institute & The Johns Hopkins School of Medicine, Sykesville, MD, United States; 2Hôpital CIMIEZ, Nice, France; 3McGill Centre for Studies in Aging, Montreal, QC, Canada; 4Sao Paulo State University, Sao Paulo, Brazil; 5Eginition Hospital, Univ. of Athens Medical School, Athens, Greece; 6CEMIC, School of Medicine & Research Institute, Buenos Aires, Argentina; 7El Instituto Privado Kremer, Cordoba, Argentina; 8University of Genoa, Genoa, Italy; 9University of Rochester School of Medicine, Rochester, NY, United States; 10Mayo Clinic, Rochester, MN, United States; 11Prince of Wales Hospital, Randwick, NSW, Australia; 12Johns Hopkins Bayview Medical Center & The Johns Hopkins School of Medicine, Baltimore, MD, United States
Measurement of neuropsychiatric symptoms (NPS) is crucial in dementia research, especially in clinical trials targeting individual NPS or NPS groups. The Neuropsychiatric Inventory (NPI) has been widely accepted as the standard NPS measure. However, it has several limitations: it is administered to care givers only; there is uncertainty about the reliability of individual items as opposed to domain ratings; few items are specific to severe or mild dementia; and it has limited depth of items in specific domains. As a result, the NPI is less sensitive to change than measures that incorporate clinical judgment. There is also the lack of a single measure of NPS that can be used in several settings, including clinical trials. To address these limitations, we have developed a revised and expanded version of the NPI, known as the NPI-C. The NPI-C includes expanded domains and items (79 new items and two additional domains), and a clinician rating methodology. Face validity for new items was obtained through a Delphi panel of 7 experts in dementia research. Inter-rater reliability and concurrent validity were examined in an international study conducted at 10 sites (3 U.S., Canada, France, Brazil, Greece, Argentina, Italy and Australia) using NPI-C versions involving 6 languages. Caregiver-patient dyads at each site were interviewed by two raters. The first rater also administered 3 additional established measures of apathy, depression and agitation so that convergent validity could be assessed. Two rating methods were also used: ratings based on responses to the original NPI provided by a caregiver during an interview; and a clinician-rating approach based on information gathered from the caregiver, the patient and other relevant clinical information. This presentation will present an overview of the NPI-C and its development as well as a detailed description of validation study results. We anticipate that the NPI-C will provide a single versatile method of rating NPS that can be used in a range of clinical studies as either a “broad spectrum” measure of several types of NPS or as a domain-specific measure when a study calls for in-depth monitoring of a limited set of domains, such as apathy or agitation.
PS01.24
The associations of gender, depression and elder abuse in a community-dwelling Chinese population: The modifying effect of social support
XinQi Dong; M Simon
Rush University, Chicago, IL, United States
Context: The World Health Organization has declared that elder abuse is a human rights issue and it is a fundamental right of older men and women to be safe and free of violence. China is the most populous country in the world and by 2050, 25% of the world's aging population will be Chinese. Yet we have the most rudimentary understanding about elder abuse in the Chinese population. Further, depression has been associated with premature morbidity and mortality. However, our current understanding of the association between depression and elder abuse in Chinese men and women is extremely limited.
Objective: The aims of this study are to: 1) examine the gender differences in the association of depression and elder abuse in a community-dwelling Chinese population; and 2) examine the potential differential modifying effect of greater social support on these associations.
Methods: We conducted a cross-sectional study of men and women aged 60 years or greater who presented to an urban medical center in NanJing, P.R.China. Elder abuse was assessed using the modified Vulnerability to Abuse Screening Scale (VASS), depression was assessed using the Geriatric Depression Screen and overall social support was measured using the Social Support Index (SSI). Logistical regression and interaction term analyses were used to assess these associations.
Result: A total of 141 women and 270 men completed the survey. Fifty-nine women (42%) and 86 men (32%) had reported elder abuse. In addition, depression was found among 17.4% of men with elder abuse and 37.3% of women with elder abuse. After adjusting for age, education, income, marital status and number of children, depression was associated with 447% increased risk for elder abuse among men (Odd Ration [OR], 4.47 (95% Confidence Interval [CI], 1.52–13.13)) and 854% increased risk for elder abuse among women (OR, 8.54, (95%CI, 2.85–25.57)). After examining the effect of greater social support on depression through interaction term analyses (social support x depression), depression was no longer associated with increased risk for elder abuse among men (Parameter Estimate (PE) = 0.62, Standard Error (SE) = 0.82, p = 0.454). However, among women, depression remained as a significant risk factor for elder abuse (PE = 1.49, SE = 0.68, p = 0.029).
Conclusion: Depression is significant risk factor for elder abuse for both men and women in this community-dwelling Chinese population. However, these increased risks may be modified by greater overall social support, which appears to have a stronger effect for men than women. Future intervention studies are needed to examine the effect of greater social support in reducing elder abuse among those with depression in Chinese population.
PS01.25
Pharmacological treatment of apathy in neurodegenerative diseases: A systematic review
Rosa Drijgers1; P Aalten1; A Winogrodzka2; F Verhey1; A Leentjens1
1Maastricht University Medical Centre, Maastricht, Netherlands; 2Maastricht University Medical Centre, Maastricht, Netherlands
Objective: To evaluate the efficacy of pharmacological treatment of apathy in patients with neurodegenerative diseases.
Methods: Systematic review of studies assessing the effects of pharmacological treatment on apathy in neurodegenerative diseases. An extensive search in the Pubmed database up to June 2008 was carried out. Two independent reviewers screened studies for eligibility. Level of evidence was assessed of all included studies.
Results: Thirty-five studies were included: 2 meta-analyses, 13 randomized controlled trials (RCTs), 14 open-label studies, 5 case series, and 1 single case study. Eight studies included apathy as a primary outcome. A cholinesterase inhibitor was investigated in 24 studies, methylphenidate in 5, and other medications in 6. One meta-analysis showed a modest improvement of apathetic symptoms during treatment with metrifonate, while the other reported no improvement during treatment with galantamine. Most RCTs of cholinesterase inhibitors reported a small but statistically significant improvement of apathetic symptoms. Given the lack of a placebo condition, no conclusions could be inferred from the results of the open studies and case reports.
Conclusions: Although some medications are promising candidates for further study, there is as yet insufficient evidence that pharmacological treatment improves apathetic symptoms in patients with neurodegenerative disease. Large-scale, placebo-controlled RCTs with apathy as a primary outcome measure are needed to establish the potential benefit of pharmacological treatment of apathy.
PS01.26
The effects of a refurbishment on residents' quality of life and well-being in two Swedish residential care facilities
Hanna Falk1; H Wijk2; L Persson1
1Institute of Health and Care Science, Gothenburg, Sweden; 2Karolinska Institutet, Stockholm, Sweden
Background: The physical environment is increasingly recognized as important in the care of elderly persons in residential care, and design is generally regarded as a therapeutic resource to promote wellbeing and functionality amongst elderly with dementia disease. A supportive physical environment in residential care facilities can be defined as prosthetic, accessible, adaptable, and safe.
Aim: To examine the effects of a refurbishment aimed to enhance the supportiveness of the physical environment on residents' quality of life and wellbeing in two Swedish residential care facilities.
Method: A pre-test–post-test design with an equivalent control group, using both proxy- and self-report measures.
Results: Significant differences between the intervention group (n = 50) and the reference group (n = 81) were found for quality of life (p = 0.007) and well-being (p = 0.02, p = 0.01) indicating a worsening for the intervention group.
Conclusion: This study does not explain the reason for decreased quality of life and wellbeing in the intervention group. However we assume that older persons are frail and vulnerable to alterations in their physical surroundings, which could be one plausible reason for our findings. This should be taken into consideration when facilities accommodating elderly persons are refurbished. By solely focusing on the physical dimension of the environment in this study we assume that interior design features alone have a diminutive importance to the care climate in terms of supporting older persons' quality of life and wellbeing.
PS01.27
Intra-institutional relocation: Effects on elderly persons' health and quality of life
Hanna Falk1; H Wijk2; L Persson1
1Institute of Health and Care Science, Gothenburg, Sweden; 2Karolinska Institutet, Stockholm, Sweden
Background: The transfer of older persons from one care setting to another has been a consistent concern of researchers and practitioners for several decades. “Relocation trauma” or “relocation stress syndrome” describes the adverse psychological and physical responses in people who move from one environment to another. Results from studies on post relocation mortality rates vary significantly. Disparities in findings, such as earlier studies suggesting increased post transfer mortality rates, and later studies suggesting no mortality effects, raise the question of whether adverse relocation effects might be determined by the nature, rather than the act itself, of relocation. As a result of the governmental upgrading of nursing homes in Sweden, residents are often forced to provisional facilities. No one knows exactly how many elderly residents are inter-institutionally relocated each year in Sweden, and there is a lack of knowledge on how these relocations affect their health and quality of life.
Aim: To explore the nature and effects of relocation on quality of life, wellbeing, perceived care climate, depression, mortality, and activities of daily living in inter-institutional relocating elderly persons.
Method: A pre-test–post-test design using a sequential explanatory mixed method strategy with a quantitative core component identifying differences between groups over time, and a qualitative supplemental component exploring residents' experiences and actions in relation to the inter-institutional relocation process.
Procedure: Two (A, B) residential care facilities undergoing inter-institutional relocation, a third (C) functioning as control facility. Target population consist of all residents at facilities A and B (n = 99), control group (n = 81). In order to include all, regardless of cognitive impairment, residents are pre-selected into one of two groups according to scores on the MMSE (high-functioning group <21 points providing self assessment and participation in semi-structured interviews, low-functioning group >20 points assessed using proxy informants).
Results: The results of this study will be presented at the International Psychiatric Association 14th International Congress in Montreal, Canada, September 2009.
PS01.29
Determining the impact of socioeconomic status on the prevalence of dementia in an inner city memory disorders clinic
Corinne Fischer1; E Yeung4; T Hansen4; S Gibbons5; L Fornazzari2; L Ringer1; T Schweizer3
1St. Michaels Hospital, Toronto, ON, Canada; 2St. Michaels Hospital, Toronto, ON, Canada; 3St. Michaels Hospital, Toronto, ON, Canada; 4University of Toronto, Toronto, ON, Canada; 5University College, Dublin, Ireland
Background: Socioeconomic status (SES) has been identified as a risk factor for the development of dementia, with low SES shown to be associated with a higher prevalence of dementia, increased psychiatric co-morbidity and worse baseline cognitive functioning. Only a minority of these studies, however, have focused on inner city populations. Furthermore, few studies have looked at multiple measures of SES including education, annualized income and neighbourhood income quintiles (residential SES).
Methods: Data on 217 patients seen in an Inner City Memory Disorders Clinic located in the city of Toronto were analyzed with respect to demographic status, clinical status and SES. Correlations were then examined looking at the relationship of SES to clinical variables and global neurocognitive status. Regression analysis was undertaken to examine the relative contribution of individual sociodemographic factors to a diagnosis of dementia.
Results: In general, there was wide variation in the sample examined with respect to SES variables including education, annualized income and neighbourhood income quintiles. Approximately one third (36%) of the sample had a diagnosis of dementia, the mean age was 66.1 years and the mean MMSE score was relatively high (25.4/30). There was a significant difference in the MMSE score between the low and high income group, with the low income group scoring a mean of 24.6/30 and the high income group scoring a mean of 26.6/30. There was a strong association between individual annual income range, education, medical co-morbidity and a diagnosis of dementia. Residential SES and psychiatric co-morbidity, however, were not associated with a diagnosis of dementia or decreased baseline cognitive functioning. Using regression analyses and accounting for covariates, age and medical co-morbidity appeared to be stronger predictors of a diagnosis of dementia than SES.
Conclusion: Patients with increased age, low education, high medical co-morbidity and low annualized income are particularly at risk for decreased cognitive functioning and dementia in an inner city setting. An additional novel finding was that increased medical co-morbidity was more predictive of a diagnosis of dementia than SES. These findings suggest that Memory Clinics located in unique populations such as the inner city should target individuals with low SES who are older and have multiple medical problems.
PS01.30
Determining the impact of medical co-morbidity on subjective and objective cognitive performance in a sample of inner city elderly
Corinne Fischer1; E Yeung3; J Depeng2; M Fortin2; L Fornazzari4; L Ringer1; T Schweizer5
1St. Michaels Hospital, Toronto, ON, Canada; 2St. Michaels Hospital, Toronto, ON, Canada; 3University of Toronto, Toronto, ON, Canada; 4St. Michael's Hospital, Toronto, ON, Canada; 5St. Michael's Hospital, Toronto, ON, Canada
Background: Increased medical co-morbidity has been found to be associated with impaired neurocognitive performance. Postulated mechanisms include the neurotoxic effects of disease and medications used to treat diseases. There has been considerably less focus on cognitive complaints in this population. The objective of this study was to compare the relationship between medical co-morbidity and objective and subjective cognitive performance in a sample of inner city elderly.
Methods: Data from 96 patients attending an inner city Memory Disorders Clinic were examined retrospectively. Medical co-morbidity was measured using the Cumulative Illness Rating index (CIRS), subjective memory complaints were measured using the Personal Assessment of Own Functioning (PAOF) and objective memory impairment was measured using the Behavioural Neurology Assessment (BNA) and Mini Mental Status Exam (MMSE). Multiple regression analyses were used to examine the correlation between medical co-morbidity and objective and subjective cognitive function.
Results: The mean age of the sample was 65.8 years, the mean number of years of education was 14.1 and the mean CIRS score was 4.9. Adjusting for the impact of other SES variables (neighbourhood income quintiles, education) and depression, medical co-morbidity correlated strongly with impaired global cognitive performance as measured by the Mini Mental Status Exam (MMSE) (p<.001) and BNA (p<.05). In addition, all of the BNA subscores (memory, verbal ability, visuospatial function, and executive function, (p<.05)) with the exception of attention (p>.05) correlated strongly with increased medical comorbidity. On the contrary, none of the subjective cognitive complaints or their subscores correlated significantly.
Conclusion: Medical co-morbidity, while strongly associated with impaired objective neurocognitive performance, is not necessarily associated with increased subjective cognitive complaints.
PS01.31
Act In case of Depression (AID): A multidisciplinary care program to improve the detection, treatment and prevention of depression in nursing homes
Debby Gerritsen1; M Smalbrugge2; S Teerenstra3; E Adang3; E Derksen1; R Koopmans1
1Radboud University Medical Centre, Nijmegen, Netherlands; 2VU Medical Center, Amsterdam, Netherlands; 3Radboud University Medical Centre, Nijmegen, Netherlands
Background: The high prevalence of depression and depressive symptoms is a significant problem, also in Dutch nursing homes (NHs). As depression is believed to reflect quality of care, it is one of the quality indicators of the Dutch Healthcare Inspectorate. The presence of multidisciplinary care teams in Dutch NHs offers ideal preconditions to manage depression effectively. Yet the management of depression is protocollized in the minority of Dutch NHs. Therefore, this evidence and practice based care program for multidisciplinary teams was developed. This development took place in close collaboration with NH psychologists of the Nijmegen University Network of NHs.
Care program ‘Act In case of Depression (AID)’: To identify and treat depression and to monitor treatment effects, the care program AID proposes an evidence based standardization of 5 components in the management of depression. These five components are: identification of depressive symptoms, screening, diagnosis, treatment and monitoring of treatment. The care program encompasses a standardized use of measurement instruments and diagnostical methods, and treatment according to a protocol that combines psychosocial and pharmacological interventions. The care program is based on and in accordance with national and international guidelines. Cooperation between the disciplines is prearranged. As the ability of nursing staff to detect depression can and should be enhanced, a training program for the nursing staff is the starting point. The training encompasses identification and understanding of depressive symptoms and supporting NH residents with depression.
Study design and methods: The AID study investigates the effectiveness of the care program AID. It is a 19-month longitudinal controlled study on 14 somatic and 14 dementia units that, in a stepped wedge design, all will implement the care program. All residents of the participating units will be included (provided informed consent is given). Primary outcomes are the frequency of depression on the units and quality of life of residents on the units. Economic evaluation will be part of this study.
Conclusion: This care program is expected to have a positive effect on the frequency of depression and on the quality of life of residents, and will prevent progression of depressive symptoms into depression. The study will further provide insight into the cost-effectiveness of the care program.
PS01.32
Basal hypothalamic pituitary adrenal axis activity and hippocampal volumes: The SMART-MR study
Lotte Gerritsen1; A Knoops2; Y van der Graaf1; W Mali2; M Geerlings1
1University Medical Center Utrecht, Utrecht, Netherlands; 2University Medical Center Utrecht, Utrecht, Netherlands
Background: Smaller hippocampal volumes have been associated with neuropsychiatric disorders, like depression and Alzheimer's disease, and it has frequently been hypothesized that high levels of glucocorticoids explain this association. However, few studies examined the direct relation between hypothalamic-pituitary-adrenal (HPA) axis activity and hippocampal volumes. We examined the association between different aspects of HPA-axis activity and hippocampal volumes in a large sample of middle aged persons.
Methods: Within the SMART-MR study, a cohort study on early brain changes on MRI among patients with a history of arterial disease, diurnal cortisol rhythm was assessed with 6 saliva samples, collected at awakening and 30, 45 and 60 minutes thereafter, and at 10PM and 11PM in 383 participants (mean age 62 ± 9 years). Dexamethasone (0.5 mg) was administered at 11PM and saliva was sampled the next morning at awakening. Diurnal cortisol profile was defined as the cortisol awakening response; mean evening values; and the suppressibility of the HPA-axis after dexamethasone. Volumes of the hippocampus were manually traced on a 3-dimensional FFE T1-weighted MRI scan with isotropic voxels and were expressed relative to intracranial volume.
Results: Mean total relative hippocampal volume was 6.2 ± 0.7 ml. Linear regression analyses, adjusted for age, sex, vascular risk factors and global brain atrophy showed that participants with higher evening levels had smaller hippocampal volumes (B per SD increase = − 0.08 ml; 95%CI −0.15 to −0.01 ml). The awakening response and cortisol levels after dexamethasone were not significantly associated with hippocampal volume.
Conclusions: In this population, higher evening cortisol levels were associated with smaller hippocampal volumes, independent of total brain volume. The cortisol response after awaking and cortisol after dexamethasone suppression were not associated with hippocampal volume. Future studies should examine whether elevated evening cortisol is a cause or a consequence of smaller hippocampal volume and whether it increases risk for neuropsychiatric disorders.
PS01.33
Aging veterans, psychological trauma, and relapse prevention: A state of the art review
Maggie Gibson; S Gifford
St. Joseph's Health Care London, London, ON, Canada
Three lines of research converge in this presentation. First, there is a substantive body of literature that documents that war-related experience is associated with increased risk of mental health problems; second, numerous social and behavioural factors (including social support, societal acceptance, and personal coping strategies) have been associated with long term psychological adaptation in aging veterans; and third, there is evidence that the processes of aging may increase vulnerability to mental health problems associated with a personal history of war-related trauma.
It has been argued that many veterans have coped with traumatic wartime experiences throughout early and middle adulthood by using cognitive and experiential avoidance strategies (e.g., immersing themselves in work, consuming excessive alcohol), which, for a variety of documented reasons, tend to break down in later life. Never-processed memories of traumatic wartime events then resurface in the form of the re-experiencing and hyper-arousal symptoms of Posttraumatic Stress Disorder (PTSD). The treatment outcome literature clearly tells us that exposure-based methods—those that involve confronting and processing memories of trauma—are the most effective means of reducing these two clusters of PTSD symptoms. However, most older veterans have never participated in such treatment, and there is virtually no extant research on the efficacy or suitability of exposure-based treatments for older adults with PTSD. This presentation will discuss relapse prevention interventions for PTSD from a lifespan perspective, taking into account the relatively recent—and growing—availability of effective treatments for war-related trauma as well as current knowledge gaps concerning best practices for treating older veterans. The general goal of relapse prevention is to maintain functional capacities in the face of exposure to events or contexts that trigger recall of traumatic experiences. However, we argue that the specifics of intervention must accommodate anticipated age-related changes that impact functional capacities (e.g., declines in episodic memory) across the lifespan. In making this argument, we draw attention to ongoing discussions in the literature about core assumptions of PTSD (e.g., Rosen & Lilienfeld, 2008), controversy about the concept of delayed-onset PTSD (e.g., Andrews et al., 2007), and emerging thinking about the phenomenon of late-onset stress symptomatology (e.g., King et al., 2007). Opportunities to further the goal of prevention through research and theory development are identified.
PS01.34
White matter lesions and risk of depression: The SMART-MR study
Anne Grool1; Y van der Graaf1; W Mali2; M Geerlings1
1University Medical Center Utrecht, Utrecht, Netherlands; 2University Medical Center Utrecht, Utrecht, Netherlands
Objective: The vascular depression hypothesis proposes that small-vessel lesions in specific brain regions contribute to the pathogenesis of late-life depression. White matter lesions (WML) and lacunar infarcts (LI) on magnetic resonance imaging (MRI) are generally used as indicators of cerebral small-vessel disease. We examined the association between WML and LI and depressive symptoms in a large cohort of patients with symptomatic arterial disease.
Methods: Within the SMART-MR study, an ongoing cohort study among patients with symptomatic arterial disease, cross-sectional analyses were performed in 852 patients (mean age 58 ± 10 years, 77% male). At baseline, depressive symptoms were assessed with the mental health index (MHI-5), a subscale of the SF-36. Sum scores were transformed into a variable ranging from 0–100 using standard linear transformation, with lower scores representing more depressive symptoms. MRI was performed to quantify volumes of brain tissue and WML, using an automated brain segmentation program. WML volumes were expressed relative to intracranial volume. Location and number of infarcts were rated visually. Lacunar infarcts were categorized into three classes: no LI, one LI, and two or more LI. Linear regression analyses with robust standard errors were used to investigate the association between WML volume as independent variable and mental health as dependent variable, adjusted for age, sex, smoking habits, alcohol intake, hypertension, diabetes mellitus, symptomatic cerebral vascular disease and cerebral infarcts on MRI. To investigate the association between LI and mental health, linear regression analyses were used with adjustments for age, sex, smoking habits, alcohol intake, hypertension, diabetes mellitus, WML and cerebral infarcts on MRI other than LI.
Results: Median WML volume in the total study sample was 1.65 mL (10–90 percentile 0.59–7.57 mL), and median mental health score was 76 (10–90 percentile 48–92). One or more LI were present in 16% of the study sample. Regression analyses showed that higher WML volumes were associated with lower mental health scores (adjusted for age and sex, β – 0.331, 95% CI –0.581, –0.081, p = 0.009; adjusted for all covariates, β – 0.294, 95% CI –0.541, –0.047, p = 0.020). One or more LI were not significantly associated with mental health score, irrespective of adjustment for confounders (adjusted for age and sex, p = 0.092; adjusted for all covariates p = 0.555).
Conclusions: White matter lesions increase the risk for depressive symptoms, independent of age, sex, vascular risk factors and cerebral infarcts. These findings provide further support for an association between cerebrovascular disease and depression.
PS01.35
Impact of cognitive performance on the functional capacity in a population sample of elderly Brazilians
Ricardo Guerra; K Castro
Universidade Federal do Rio Grande do Norte, Natal RN, Brazil
Functional disability and cognitive impairment are conditions related to the process of human aging. Cognitive impairment is considered an important predictive factor for functional disorders in elderly populations. This study has multidisciplinary characteristics in its elaboration and execution, and it is a cross-sectional study that analyzes the association between cognitive performance and functional capacity in an elderly population sample in Natal, Brazil. A total of 213 elderly persons were assessed by the BOAS Multidimensional Questionnaire (Brazil Old Age Schedule) and the Mini-Mental State Examination (MMSE). The results of multivariate analysis and linear regression showed that age and schooling level are factors associated with cognitive performance in the elderly of this study. The final explicative model, elaborated by logistic regression, found that cognitive performance was the only predictive variable of functional incapacity for the activities of daily life even when adjusted for sociodemographic variables. The identification of factors associated to the decline of community elderly's functional state should be able to reduce impact of these conditions in functional capacity through the application of writs of prevention directed toward this end.
PS01.36
Impact of cognitive deficit on survival among a population sample of elderly Brazilians
Ricardo Guerra; A Maciel
Universidade Federal do Rio Grande do Norte, Natal RN, Brazil
Objective: To analyze cognitive deficit as a risk factor for death in elderly residents in the community and its relationship with variables related to sociodemographic factors, physical health, and functional capacity.
Material and Methods: A prospective study was carried out in the city of Santa Cruz, Brazil, in 310 randomly selected elderly individuals who were followed-up for 53 months. Predictive factors were sociodemographic and neuropsychiatric variables, physical health, and functional capacity. The statistical methods used were bivariate analysis (survival analysis), and Cox regression (multivariate analysis) with respective hazard ratios (HR). A value of P < .05 was considered statistically significant and 95% confidence intervals (CI) were calculated.
Results: A total of 60 (20.5%) elderly residents died during the study. The main cause of death was cardiovascular disease. The mean time until death was approximately 24.8 months. The main risk factors identified in Cox analysis were cognitive deficit (HR = 4.22), stroke (HR = 3.08) and dependency for basic activities of daily living (HR = 3.55).
Conclusions: Cognitive deficit is an independent risk factor for death. The results of the present study could be useful in formulating future health policies aiming to reduce mortality in the elderly.
PS01.37
Psychometric properties of the Swedish version of the Philadelphia Geriatric Center Morale scale in very old people
Martin Gustafson1; B Olofsson1; B Nygren2; Y Gustafson1; H Lovheim1
1Geriatric Medicine, Umea, Sweden; 2Nursing, Umea, Sweden
Background: The Philadelphia Geriatric Center Morale scale (PGCMS) has become widely used as a measure of morale in old people. This scale is recommended by the British Geriatric Society as the preferred measure of subjective well-being or Quality of Life among old people. Three sub-scales of the PGCMS have been described previously. This article presents the first evaluation of the Swedish version of the PGCMS-17 item version.
Method: The Umeå 85+ study includes people 85, 90 and 95 years old and above. People were assessed during home visits performed by trained assessors. Two hundred and eighty seven subjects were evaluated with the PGCMS and are included in the present analysis. A sub-sample (n = 120) was re-assessed within a few months (mean 118 days) by a different assessor. Internal consistency, inter-rater test-retest reliability evaluated by intra-class correlation coefficient (ICC) and least significant change between two measurements with 95% and 80% confidence interval was calculated. A factor analysis using Varimax rotation of the items was also performed. Reliability of the items was tested using Cohen's kappa.
Results: The mean age of both samples was 89 years and 69% were women. Mean MMSE score was 23.6 ± 5.2. The mean PGCM score for the whole sample was 11.6 ± 3.2, range 1–17. The ICC was established as 0.771. Least significant change between two measurements was 5.43 at 95% level of significance and 3.55 at 80% level. For the different items Cohen's kappa ranged 0.236 to 0.701. A three factor solution of the factor analysis of the Swedish version of the PGCMS showed similar results as previously published factor analyses of the scale.
Conclusion: The Swedish version of the PGCMS seems to have satisfactory psychometric properties among very old people. The factor analysis rendered the same three sub-scales of the PGCMS as has previously been described. Based on the inter-rater test-retest the authors suggest that a change of at least three points should be required on individual level to indicate a significant change. The Swedish version of the PGCMS seems to be useful for assessing morale in very old people.
PS01.38
Psychiatric opinions in the Parish will case: A mid 19th century method for the retrospective assessment of testamentary capacity in dementia
Jeremia Heinik
Margoletz Psychogeriatric Center, Ichilov Hospital; Sackler Faculty of Medicine, Tel-Aviv University, Tel Aviv, Israel
Introduction: Henry Parish, a wealthy retired merchant, married without children, made a will in 1842, while healthy, providing for his wife and family. In 1849 he suffered a severe stroke; his right hand remained paralyzed, he could not write with the left and his speech was severely impaired. Only two or more sounds or monosyllables and some movements of the head and hand were discerned. He also suffered epileptic seizures and lost control of his bodily functions, never recovered, and died in 1856. In this physical and mental condition Mr. Parish was surrounded by his wife, her family and friends, while his own relatives were denied access to him. Throughout his illness he made three codicils that radically changed his will, favoring his wife, and excluding his family. Following his demise lack of testamentary capacity was claimed and the parties went to trial. Five psychiatrists, among other physicians, including Dr. Ray, the “father of American forensic psychiatry,” published their opinions in this case. I examined whether, based on an analysis of the recorded medical opinions, a retrospective assessment of testamentary capacity in dementia could be drawn.
Methods: This research is based on the published original medical opinions and other sources from that era, as applicable to the case.
Results: I drew a hierarchical method for the retrospective assessment of testamentary capacity in dementia consisting of four conceptual levels: 1. Demonstration of a brain disorder, of organic or emotional origin, with brain lesions observable at autopsy, and based on evidenced physical symptoms. In Mr. Parish's case the physical symptoms (paralysis, loss of speech, epilepsy, loss of bowel control) suggested extensive organic brain disease. Antecedent attacks of vertigo and some hereditary predisposition affirmed this diagnosis. An autopsy was not performed, however causative mechanisms were proposed. 2. The next conceptual level involved consecutive impairments of intellectual faculties (thought, memory, judgment, communication), affective faculties, disposition, volition, character, habits and customs. All were demonstrated in this case. By comparing the combined intellectual, social and moral nature of the testator before and after the stroke, a diagnosis of insanity and severe and continuous dementia was made. 3. In order to respond to the medico-legal question, the rational perception of his relations to others, the intelligent understanding of what he perceived was investigated and compared with his past performance. 4. The highest conceptual level was the experts' conclusion. All the psychiatrists established that Mr. Parish was of unsound mind throughout and that the codicils in question were not a rational act, that he had no free will, and lacked understanding of what he was doing. However, only Dr. Ray linked the capacity of the testator to the demands of the prevalent law.
Conclusions: The psychiatric opinions show that a clear method for the retrospective assessment of testamentary capacity in dementia was conceptualized in the mid 19th century. Retrospective assessment of testamentary capacity by psychiatric experts remains a complex issue. Insights obtained from the past might elucidate our thinking on this subject.
PS01.39
How somatically ill elderly individuals with and without a history of emotional distress act to experience satisfaction in everyday life: A qualitative study
Anne-Sofie Helvik1; V Iversen2; L Hallberg3
1Innlandet Hospital Trust, Division Tynset, Tynset, Norway; 2Norwegian University of Science and Technology, Trondheim, Norway; 3Hamstad University, Halmstad, Sweden
Background: “Successful aging” has for quite some time been of interest in classical gerontological theory. However, to our knowledge, rather few have studied the main concern for somatically ill old persons, with and without a history of emotional distress, and what they have experienced is helpful not only to prevent emotional distress, but also to optimize their well-being and satisfaction in everyday life.
Aim: This study explored the main concern for elderly Norwegian individuals with somatic health problems and what they did to optimize their well-being and satisfaction in everyday life.
Method: The study used an inductive theory-generating method, Grounded theory. This qualitative method gave the participants the ability to describe their experiences and reflections with their own words and the researcher the opportunity to focus on different aspects and qualities of a phenomenon.
In all, 14 strategically selected individuals participated, age range 68–86 years (mean 74.2 years), of both genders including hospitalized and outpatient persons. Six of the participants had a history of emotional distress. Open interviews lasting about 30 minutes were performed for each person. The interviews were tape-recorded and transcribed verbatim onto protocols. Data were analysed according to grounded theory guidelines including the use of open and focused coding.
Results: The main concern for elderly individuals with somatic problems was the maintenance of a meaningful everyday life. To manage this they were “utilizing the network of important others” and “enjoying cultural belongings.” The network generated good experiences, practical assistance, comfort etc. Appreciation of the cultural belongings included valuing nature experiences, natural resources and local and global values. Further, the elderly experienced that active involvement in life by “being occupied with interests” and “having a mission to fulfill” was helpful for maintaining a meaning in life. This involvement in life helped them to feel important and valuable. Lastly, their way of managing consequences of health problems, including both “recalibrating expectations” in life and “improving difficult situations by taking control,” were important for maintaining a meaningful life. By use of these strategies they closed the gap between the expected and the experienced life, and subsequently optimized their psychological well-being.
Conclusion: The emerging theory illuminates that elderly use their environment, are involved in life and cope with consequences of their vulnerable somatic health in order to maintain a meaningful life. Maintaining a meaningful life improved their psychological well-being. How they cope, use their environment and are involved in life may vary with health circumstances, personal resources and characteristics and environmental contexts.
PS01.40
Exploring the personality and defense mechanisms in schizophrenia and dementia
Joana Henriques-Calado; M Duarte-Silva
Faculty of Psychology and Educational Sciences, University of Lisbon, Lisboa, Portugal
The aim of this research is to explore the possible association between a specific psychic structure of personality and its defense mechanisms and the diagnoses of schizophrenia and dementia. The sample consisted of 58 female participants, 30 participants diagnosed with schizophrenia (M = 68.83 years of age, SD = 8.13) and 28 participants diagnosed with dementia (M = 83.36 years of age, SD = 7.51). The used instruments of psychological assessment were the Mini Mental State (Folstein, Folstein, & McHugh, 1975), scales of the Ego Function Assessment (Bellak, 1989) and the Defense Style Questionnaire-40 (Andrews, Singh, & Bond, 1993). The fragmentation anguish and the fusional object relation might be associated with schizophrenia and, by turn, the abandonment anguish and the anaclitic object relation with dementia. It was assumed that specific psychic structures of personality were associated with the different diagnoses; it might be that psychotic structure is connected with schizophrenia and borderline structure with dementia. Some suggestions for further research are proposed.
PS01.41
Study of the unconscious recall in Alzheimer's disease patients
Nilda Henriquez
University Toulouse II, Toulouse, France
Introduction: The slow and yet constant evolution on dementia of the Alzheimer's type (DAT) has become the major problem of our society and the memory is always affected at an early stage of the DAT.
Objective: The disorder or decline of these functions may have a profound impact on daily life activities. However, the unconscious recall is well preserved in DAT patients. Therefore, this study aims to evaluate these processes experienced by DAT patients.
Methodology: The research aims to examine this disease by submitting 20 DAT patients, at an early stage of the illness, to cognitive tests, along with a longitudinal study (11 months after) of the control group with matched subjects.
In order to test the unconscious recall, “word-completion test” in two series with different instructions were used. In order to measure the coding and unconscious memory, “semantic index recall” was used.
In order to evaluate these exams, two levels of analysis were considered: a traditional approach (on the group) and an analysis on interindividual differences. For the statistical treatment, we used the SPSS 10, 0 version software; and correlation, test X2 and ANOVAs were calculated.
Results: The statistical analysis made it possible to categorize three types of patient groups showing a great heterogeneity among them.
On test 1 “word-completion test,” the results were low. On the contrary on test 2, the performance of DAT was better. The test with facilitation strategies (semantic index recall) is better preserved in DAT. Finally, the results showed that memory declines in the DAT are not only quantitative but also qualitative (semantic paraphasia).
Conclusion: The study of the results showed that the DAT performances improve somewhat in unconscious recall (word-completion test 2) and providing facilitator strategies (semantic index recall). But this performance level did not reach the level of the control group. Therefore, the memory decline does not depend only on the person but also on the type of task, contexts, aids and instructions.
The memory declines show difficulty to access the lexical semantic stock with turns into an anomia affecting spontaneous expression on DAT patients.
PS01.42
Prolactin response to citalopram challenge predicts behavioural improvement in frontotemporal dementia
Nathan Herrmann1; S Black1; T Chow2; M Freedman2; K Lanctôt1
1Sunnybrook Health Sciences Centre, Toronto, ON, Canada; 2The Rotman Research Institute-Baycrest, Toronto, ON, Canada
Objectives: Frontotemporal dementia (FTD) is commonly accompanied by behavioural and psychological symptoms of dementia (BPSD). Previous data have demonstrated serotonergic dysfunction, which may contribute to BPSD. Currently there are few treatment options, and clinical trials evaluating treatment of BPSD with selective serotonin reuptake inhibitors (SSRI) have demonstrated conflicting results. The objective of this study was to determine if an association exists between serotonergic dysfunction and treatment response to citalopram in subjects with FTD and BPSD.
Methods: In order to measure serotonergic dysfunction, FTD subjects (Neary criteria) with BPSD (Neuropsychiatric Inventory [NPI] total ≥8) participated in a neuroendocrine challenge that measured changes in prolactin 3 hours following administration of a single dose of 30 mg citalopram. Following the challenge, subjects participated in a 6-week open-label trial of citalopram (titrated to 40 mg/day maximum). The association between prolactin response to citalopram challenge and change in NPI total score (primary outcome) over the 6-week treatment period was evaluated using Spearman rank rho. Our secondary outcomes were the NPI subscales and the Frontal Behavioural Inventory (FBI).
Results: 10 FTD (7 behavioural variant of FTD, 2 primary progressive aphasia [PPA], 1 semantic dementia) subjects were recruited (5F, 5M, age 67.0 ± 10.0 years). Repeated measures analysis demonstrated significant decreases in NPI total score (F1.1 = 5.85, p = 0.041), as well as NPI subscale scores in disinhibition and irritability (paired t-test, t9 = –3.0, p = 0.015, t9 = –3.2, p = 0.011 respectively). Repeated measures analysis demonstrated a significant decrease in FBI scores over the 6-week period (F2 = 4.4, p = 0.028). A smaller change in concentration of prolactin was significantly correlated to improvement in NPI total score from baseline to endpoint (r = 0.69, p = 0.029) and improvement in the depression subscore (r = 0.88, p = 0.001).
Conclusion: These preliminary results suggest that subjects with a blunted prolactin response following a challenge with citalopram are more likely to benefit from a 6-week trial of this SSRI.
PS01.43
Effects of memantine on functional communication in patients with moderate AD: Results of a 12-week placebo-controlled trial
J Saxton1; H Brodaty2; M Woodward3; N Gilchrist4; F Potocnik5; Robert Hofbauer6; S Yu6; H Hsu6; S Graham6; J Perhach6
1Alzheimer's Disease Research Center, University of Pittsburgh, Pittsburgh, PA, United States; 2Dementia Collaborative Research Centre, University of New South Wales and Academic Dept for Old Age Psychiatry, Randwick, NSW, Australia; 3Austin Health, Medical and Cognitive Research Unit, Heidelberg West, VIC, Australia; 4CGM Research Trust, The Princess Margaret Hospital, Christchurch, New Zealand; 5Flexivest 14 Research Centre, Bellville, South Africa; 6Forest Research Institute, Jersey City, NJ, United States
Background: Post hoc analyses of placebo-controlled studies suggest that memantine treatment may benefit language and conversation abilities of patients with Alzheimer's disease (AD). This study prospectively evaluated the effects of memantine on functional communication in patients with moderate AD.
Methods: Native English-speaking outpatients (N = 265) with AD (MMSE range: 10–19) participated in a 12-week, international, double-blind, randomized, placebo-controlled study of memantine (20 mg/day) versus placebo. Concurrent cholinesterase inhibitor treatment, stable throughout the study, was permitted but not required. The primary outcome was the baseline-to-endpoint score change on the Functional Linguistic Communication Inventory (FLCI), a patient performance measure; secondary outcome was the baseline-to-endpoint score change on the combined Social Communication and Communication of Basic Needs subscales of the American Speech-Language-Hearing Association Functional Assessment Communication Skills for Adults (ASHA FACS), a caregiver assessment. Primary analysis was based on the intent-to-treat population and the last observation carried forward (LOCF) approach, performed using a two-way ANCOVA model with treatment group and study center as factors, and baseline score as covariate. Further analyses were based on the observed cases (OC) and the mixed-effects model with repeated measures (MMRM; FLCI only). Safety and tolerability were assessed by recording treatment-emergent adverse events (TEAEs).
Results: Patients treated with memantine (n = 133) demonstrated a statistically significant (LOCF) improvement on the FLCI at Weeks 4 and 8, and trend at Week 12 (placebo: −0.6; memantine: 0.7; P = 0.070) when compared with patients treated with placebo (n = 124); improvement on the ASHA FACS was significant at Weeks 8 and 12 (placebo: −5.3; memantine: 0.5; P = 0.022). Analyses based on OC (FLCI; ASHA FACS) and MMRM (FLCI) yielded similar results. Memantine was well tolerated; only dizziness and restlessness were reported by ≥2% of memantine patients and at an incidence twice that observed in the placebo group.
Conclusion: Treatment of patients with moderate AD with memantine improves functional communication skills which can be recognized by caregivers.
PS01.44
An educative support group for female family caregivers: Impact on caregivers distress and patients' neuropsychiatry symptoms
Ali Javadpour
Shiraz University of Medical Sciences, Shiraz, Iran
In the developing world most patients with dementia live in the community. And female family caregivers are the primary source delivering care to patients. Educating and supporting the carers may reduce psychological distress and challenging behavior as well. We ran a non-pharmacological intervention focusing on education regarding dementia, behavioral problems and interactive self support group. Twenty-nine female family caregivers were assigned and divided into two groups of 15 and 14. Two-hour weekly sessions were conducted for 8 weeks. Baseline and outcome measures were assessed using Neuropsychiatry Inventory (NPI), general health questionnaire and perceived stress scale (PSS).
Initial co relational analysis demonstrated a significant correlation between GHQ and total NPI scores but not for PSS. Paired sample test revealed significant change from baseline and at the end in both GHQ score and neuropsychiatry symptoms.
This study supports the use of a non-pharmacologic intervention focusing on education in a feasible and cost benefit setting for dementia caregivers.
PS01.45
Effects of apolipoprotein E genotype on behavioral and psychological symptoms in Alzheimer's disease
Shin Gyeom Kim1; H Jung1; E Shin1; S Lee1; Y Lee1; J Park1; Y Lee2
1Soonchunhyang University Bucheon Hospital, Bucheon-si, South Korea; 2Soonchunhyang University Hospital, Seoul, South Korea
Behavioral and psychological symptoms of dementia (BPSD) are common in patients with Alzheimer's disease (AD) and have a serious impact on their quality of life and institutionalisation. Genetic determinants of AD have been demonstrated and apolipoprotein E (APOE) ε4 allele is the only risk factor robustly associated with AD. However, previous investigations on APOE have produced inconsistent findings on BPSD. We explored the relationship between the APOE ε4 allele and a wide spectrum of behavioral and psychological symptoms of AD patients.
Sixty two subjects with probable AD were recruited from the Dementia clinic. All the subjects had been examined by psychiatrists with advanced training in neuropsychiatry and dementia research according to the protocol of the Clinical Research Center for Dementia (CRCD) supported by the Ministry of Health and Welfare, Korea, and met both the fourth edition of Diagnostic and Statistical Manual of Mental disorders (DSM-IV) criteria for dementia and the National Institute for Neurological Disease and Stroke, Alzheimer's Disease and Related Disorders Association (NINCDS-ADRDA) criteria for probable AD. The subject's BPSD were assessed during an interview with the informant by using the Neuropsychiatric Inventory (NPI) consisting of 12. According to the defined criteria, the severity of each item was classified into 3 grades (from 1 to 3) and frequency of each one was classified into 4 grades (from 1 to 4). The NPI score (severity × frequency) was calculated for each item and the presence or absence of BPSD were also rated.
There is no relationship between the APOE ε4 allele and BPSD, even after controlling for the effects of age at onset, sex, educational level, duration of illness, and severity of dementia.
There was no statistically significant difference in BPSD between subjects with and without APOE ε4 allele in Korean elders with AD.
PS01.46
Effects of apolipoprotein E genotype on mortality in patients with Alzheimer's disease
Shin Gyeom Kim1; H Jung1; S Lee1; Y Lee1; E Shin1; I Woo2
1Soonchunhyang University Bucheon Hospital, Bucheon, South Korea; 2Soonchunhyang University Hospital, Seoul, South Korea
The ε4 allele of apolipoprotein (APOE) has been associated with an increased risk and earlier onset of Alzheimer's disease (AD), but whether it affects mortality in patients with the disease is not consistently confirmed. This study aimed to assess the effect of APOE ε4 allele on mortality in patients with AD.
APOE genotyping had been performed on 200 patients recruited from patients with probable AD registered in the Dementia and Age-associated Cognitive Decline Clinic of a university hospital and in a service program for the early detection and management of dementia in the community between 1996 and 2006. All the subjects had been examined according to the protocol of the Korean Version of the Consortium to Establish a Registry for Alzheimer's Disease Assessment Packet (CERAD-K) at baseline. Subjects were dichotomized into 88 patients with and 112 patients without at least one ε4 allele. Cox's proportional hazards regression models were used to identify the effect of the selected variables including the ε4 allele on mortality.
Forty patients with and 49 patients without the ε4 allele had died by December 2006. Median survival from onset of AD did not differ by the ε4 allele carrier status (10.2 years in the ε4-positive group, 9.1 years in the ε4-negative group). There were no differences between ε4-positive and ε4-negative group in age at baseline, sex, education, age at onset, duration of AD, or severity of dementia. Significant factors that affect mortality during the follow-up included age at baseline and age at onset. Adjusting for age at baseline and age at onset, the presence of an ε4 allele did not show increased risk of mortality (RR = 0.98, 95% CI = 0.64−1.49) and the risk of effect of the ε4 allele did not vary by age, sex, or education in this sample.
This study provides the first information about the effect of the ε4 allele on mortality in Oriental elderly with AD. The APOE ε4 allele was not associated with mortality in patients with AD.
PS01.47
Are drivers with frontotemporal lobar degeneration more dangerous than those with Alzheimer's disease?
R Tanikatsu1; M Iseki1; Naoto Kamimura1; S Shimodera1; M Ikeda2
1Kochi Medical School, Nankoku, Japan; 2Kumamoto University, Kumamoto, Japan
Most driving proficiency studies have focused on Alzheimer's disease (AD), while little has been reported in frontotemporal lobar degeneration (FTLD), which is characterized by the alteration in personality and social conduct.
By its very nature, the impact FTLD has on driving behavior may differ from that seen in AD although there has been no report regarding the driving skills in FTLD. To address this issue, we retrospectively studied driving history in 20 patients who fulfilled the international FTLD criteria, and 47 patients with probable AD, among consecutive outpatients. Changes in driving behavior, traffic accidents and violations arising after the onset of dementia were investigated by interviewing family members and the results were compared. There were 16 men and 4 women in the FTLD group (mean age, 67.6 [SD8.5] years; mean MMSE, 19.2 [SD7.3]) and 30 men and 17 women in the AD group (mean age, 69.9 [SD10.3] years; mean MMSE, 19.5 [SD5.6]). Driving behavior reported in FTLD was as follows: difficulty in adequately maintaining the inter-car distance (70%), collisions (75%), ignoring road signs and signals (35%), and distraction (50%). In contrast, the AD group experienced problems with forgetting the destination (72.3%) and difficulty getting the car in and out of the garage (21.3%). The risk of traffic accidents/violations was significantly higher in FTLD than in AD (14/20 (70%) vs 9/47 (19.1%), p<0.001, Fisher's exact test). In addition, the latency from dementia symptom onset to the first accident was significantly shorter in FTLD than in AD (1.44 years [SD0.58] vs. 3.4 years [SD1.6], Mann-Whitney U test p < 0.05).
Our results indicate qualitative differences in driving behavior between FTLD and AD and suggest a higher risk of traffic accidents/violations in the former group. Physicians should be aware that a diagnosis of FTLD may have more profound implications for public road safety than AD. When assessing fitness to drive, physicians need to recognize that unsafe driving behavior may arise from different reasons according to dementia subtype.
PS01.48
Transition of distinctive symptoms of semantic dementia during longitudinal clinical observation
Tetsuo Kashibayashi1; M Ikeda2; K Komori1; S Shinagawa3; H Shimizu1; Y Toyota1; T Mori1; T Ishikawa1; R Fukuhara1; S Ueno1; S Tanimukai1
1Ehime University Graduate School of Medicine, Ehime, Toon-city, Japan; 2Faculty of Medical and Pharmaceutical Science, Kumamoto University, Kumamoto, Japan; 3Jikei University School of Medicine, Tokyo, Japan
Objective: The aim of this study is to examine the clinical course of the psychiatric symptoms, language symptoms and activities of daily living (ADL) in a number of Semantic Dementia (SD) patients to chart the longitudinal progression of their distinctive symptoms. We also aim to reveal the common course of the clinical symptoms of SD.
Methods: 19 consecutive SD patients visiting the Higher Brain Function Clinic of the Department of Neuropsychiatry at Ehime University Hospital between January 1997 and June 2007 were examined. We examined the first appearance of each symptom from disease onset, along with the total follow up period duration. Symptoms were classified into 24 distinct categories from the following domains based on previous studies; 10 psychiatric symptoms, 5 cognitive symptoms and 9 symptoms concerned with ADL.
Results: 14 cases had left-dominant atrophy and five had right-dominant atrophy. The mean age at the first consultation was 65.5 ± 9.4 years old and the mean duration from the appearance of symptoms to the first examination was 2.8±1.5 years. Around 3 years post-onset, language impairments, including anomia, impaired word comprehension, reduction of speech or paraphasia, were observed among all cases. Approximately 3 to 5 years post-onset, psychiatric symptoms including stereotypic behavior, disinhibition, mental rigidity, inflexibility or aggression, loss of personal awareness, loss of social awareness and apathy were observed, and patients had difficulty with their work or housework. At more than 5 years post-onset, many patients retired from their work and had episodes of getting lost. Many of these patients required regular help to eat, and developed dressing impairment, incontinence and mutism at an average of 7.1 years after onset, while other psychiatric symptoms including disinhibition, irritability and aggression were not remarkable.
Conclusions: Our findings clarify the progression of distinctive symptoms of SD and suggest the clinical course of SD can be divided into three stages like Alzheimer's disease. A better understanding of the progression of distinctive symptoms may assist in the accurate diagnosis of SD.
PS01.49
Correlations of subjective reports and polysomnographic findings in Korean obstructive sleep apnea patients
Seong Hwan Kim; S Sang Myeong Cheon; K Oh; J Choi; D Lee
Dong-A University, Busan, South Korea
Purpose: In South Korea, screening tools to assess sleep quality or obstructive sleep apnea (OSA) are subjective questionnaires that were developed in western countries. However, these widely used sleep questionnaires were not yet verified in Korea. The purpose of this study was to examine correlations between patients' subjective symptom complaints and objective polysomnographic findings.
Method: A retrospective chart review of 71 consecutive patients reporting snoring or observed apnea with or without daytime drowsiness was conducted. Patients and their bed partner accomplished the subjective sleep questionnaires (The Epworth sleepiness scale, Pittsburgh Sleep Quality Index, Global Sleep Assessment Questionnaire, Bed Partner Questionnaire) and underwent diagnostic overnight polysomnography (PSG).
Result: There was no difference in sleepiness scales between patients with or without obstructive sleep apnea according to PSG study. But some questions about snoring or reports of bed partners of patients, such as “Does your bed partner complain about your snoring or apnea?”, showed significant differences. The authors could not find differences in subjective reports according to severity of obstructive sleep apnea. However some complaints or reports of bed partners, including “How bothersome is patient's snoring to you during last 4 weeks?”, correlated well with sleep parameters in correlation analysis.
Conclusion: This study showed bed partner report is more accurate than patient's subjective sleep questionnaire in predicting OSA.
PS01.50
The whole pill or a crushed one—does it matter?
Øyvind Kirkevold1; K Engedal2
1Aging and Health, Tønsberg, Norway; 2Ullevål University Hospital, Oslo, Norway
Background: Several studies show that it is common to crush, split or open pills or capsules in order to give persons with swallowing difficulties their medication. It is claimed that this could be problematic. Such practice can lead to a change of dosage because it can be difficult to know how much of the medication is taken or a change in effect when enteric coated pills or capsules with depot effect are crushed or opened. It is also suggested that the practice of crushing medication can pollute the environment when nurses inhale dust from the crushed pills. This may be a serious problem regarding antibiotics and cytotoxics.
Aim: We designed a study to examine the practice of mixing medication into the patients' food and beverages and how often this practice includes medications where it is stated in Norwegian pharmaceutical compendium (‘Felleskatalogen’) that such practice should not be done.
Material and methods: Data were collected from 151 nursing-home wards with 2,108 patients. Data from 162 patients were not analysed due to short stay in the wards (159) or refusal (3) to participate. Thus, data from 1,943 patients were analysed. The usage of drugs was registered by the Anatomic Therapeutic Chemical Register (ATC code). Further it was registered in what form the drug was given (pill, injection, suppositories etc.), and how it was given (mixed in foodstuff or beverages).
Results: Out of 1,943 patients 18 did not receive any medication and 453 (23.3%) received at least one medication mixed into their food or beverages. Of them 197 (10.1%) patients got a medication crushed or opened against the recommendations and/or decree of the Norwegian pharmaceutical compendium. This practice included 23 of a list of 64 medications in the compendium. Of the 197 patients 124 got one medicine in this irregular way, whereas 73 patients got more than one drug in this way, mixed into their foodstuff.
Conclusions: Even though most medications given per os are designed to be digested and may well be distributed together with foodstuff it is a problem to crush pills and open capsules and mix them into food or beverages. When medications that are not meant to be crushed or opened are mixed into food or beverages it should be considered as a failure in the routines of administration of medication. So, crushing a pill or not does matter.
PS01.51
Coercive measures—rather not
Øyvind Kirkevold; B Lillesveen; K Engedal
Aging and Health, Tønsberg, Norway
Background: In the year 2000 a study showed that use of restraints, use of pressure and force in the performance of activities for daily living, covert medication and other coercive measures were common in Norwegian nursing homes. It was further reported that the professional caregivers did not always consider such actions as compulsive or coercive measures and they demonstrated a low level of reflection about the use of such measures.
Aim: To raise the awareness of own practice and to give the employees in nursing homes time to reflect over the practise described above, a development project called “Coercive measures—rather not” was carried out. It was underlined that the project should be inexpensive, simple, feasible and easy to implement in daily practice in a nursing home.
Method: A pilot study was carried out with 108 caregivers. A study program consisting of a small textbook, a work book and a VHS/DVD with introduction to five group discussions was developed. The themes for the group discussions were: a) Mapping of ADL function and BPSD, b) Use of constraints in the daily care, c) Covert medication, d) How to prevent agitation, e) Physical restraints. All caregivers in a nursing home ward were divided into groups of five to ten participants. Based on the topic for the group meeting, and examples from the introduction on VHS/DVD, the groups discussed patients from own nursing home ward. The focus in the discussions was to find out how to help the patient without the use of coercive measures. The groups met every second or third week. After the pilot the project was evaluated.
Results: The study was carried out and evaluated in 2002. A questionnaire was given to the 108 caregivers; registered nurses and nurse assistants. In all, 103 were satisfied with the content of the program, and they concluded that a structured program with possibilities to reflect on own practice is useful. However the general view was that some conditions must be met: a) The employer must take the initiative and support the groups. b) It must be mandatory to attend the meetings. c) To participate in the groups should give credits. d) The groups should give written response from the meetings to the other caregivers in the ward.
What happened after the pilot? After the evaluation a teaching package that consisted of a set of textbooks, work books and a VHS/DVD was produced. In addition a short instruction for the group leaders was produced. The packages were distributed with economical support from the Norwegian Health Directorate. From 2003 to 2009 about 4500 caregivers in nursing homes all over Norway have participated in the program. Due to changes in Norwegian legislation the program is now under revision.
PS01.52
Frequency of adverse drug reactions after a fast dosing regimen in antidementic treatment with rivastigmin in a hospital setting
Claus Koeppel; C Stelzl
Wenckebach Klinikum, Berlin, Germany
Objective: A slow increase in dose is recommended for initiation of antidementic treatment with antidementic drugs like rivastigmin. If antidementic therapy is started during stay in a geriatric clinic with an average duration of 18 days a faster increase in dosing may be justified since the patient may be closely monitored for side effects by the geriatric team. We therefore studied the frequency of side effects in patients on a geriatric ward after a fast dosing regimen of rivastigmin.
Patients and methods: 24 patients (mean age 83.4 ± 2.7 years; 14 females, 8 males) with suspected dementia of Alzheimer's type were included in the study. Besides standard diagnostic procedures including a multidimensional geriatric assessment all patients were interviewed by a neuropsychologist and had a cerebral CT scan. 13 patients had mild, 9 moderate dementia or mild dementia. Dementia was most likely of Alzheimer's type (18) and 4 of Parkinson's type. All patients had not been on antidementics before. In the patients 1.5 mg rivastigmin was started twice a day for 7 days and than increased to 3 mg. Adverse drug reactions were monitored by the nursing staff and during the daily visit of the physicians.
Results: In none of the patients was a change in eating behavior observed. Side effects like disorientation, agitation, arrhythmia, ECG changes, headache, vertigo, gait disturbances, behavioral abnormalities, nausea or vomiting, and dizziness were not observed. There were no effects on blood pressure or pulse during initiation of therapy or dose increase.
Discussion: In the patients included in the study no adverse drug reactions were observed under a fast dosing regimen with rivastigmin and a close side effect monitoring in a hospital setting. This approach may have some advantages over a slow dosing regimen in an ambulant setting and might lead to earlier treatment effects.
Conclusion: A faster dosing regimen for rivastigmin seems to be not associated with increased side effects and may have some advantages over the recommended slow dosing approach.
PS01.53
Frequency of delirium in geriatric patients after treatment with opioids
Claus Koeppel
Wenckebach Klinikum, Berlin, Germany
Objectives: Delirium is a potential adverse drug reaction especially in elderly patients with cognitive dysfunction after opioids. Pain control of strong pain normally requires opioids in combination with other analgesics. Delirium as a side effect of opioid therapy may cause serious problems in finding a similar effective analgesic medication.
Patients and methods: The files of 1279 geriatric patients (2007/2008) receiving opioids for pain control (tramadol, morphin, fentanyl, oxycodon, hydromorphon, buprenorphin) were screened for adverse drug reactions like delirium. Besides standard diagnostic procedures including a multidimensional geriatric assessment (including Barthel index, Minimental test, geriatric depression scale, Tinetti test, hand grip test, Timed up and go) all patients were interviewed by a neuropsychologist. Pain was assessed by visual analogue scale.
Results: 9 of a total of 1279 patients (mean age 82.1 ± 1,7 years, 6 females, 3 males) had delirium after opioids and were included in the study (0.7% of the total number patients treated with opioids). All patients with delirium had mild to moderate cognitive dysfunction (mean MMST 17 ± 2 points). Opioids had to be withdrawn and switched to other analgesics in these patients and combination with other classes of analgesic drugs. Sufficient pain control could be achieved in 15 of the patients. In 9 of the patients relief from pain was probably due to recovery from surgical procedures.
Discussion: Delirium in patients with cognitive dysfunction after opioids may raise serious problems. A combination of non-opioids should then be optimized.
Conclusion: Delirium after opioids is a rare adverse drug reaction mainly occurring in patients with preexisting cognitive dysfunction. A careful optimization process of analgesic therapy is then required.
PS01.54
Implementation of guidelines for nurses and GPs as a strategy to manage challenging behavior of people with dementia in nursing homes
Cornelia Krüger1; D Hardenacke1; M Halek1; H Mayer1; G Bureick2; S Wilm2; S Bartholomeyczik1
1University of Witten/Herdecke, Witten, Germany; 2University of Witten/Herdecke, Witten, Germany
Purpose: Residents with dementia in nursing homes often show challenging behavior, which has been identified as one of the primary concerns caregivers, nurses and physicians face in long term care. The ongoing study aims at improving residents' QoL and reducing challenging behavior of residents and thus caregivers' burden. Therefore two guidelines and multidisciplinary case conferences are implemented. The guideline for nurses contains seven recommendations on dealing with challenging behavior. The first recommendation refers to an understanding of residents' behavior as a kind of interaction with certain reasons that have to be understood. The guideline for GPs focuses on diagnosis and medical treatment of dementia. Multidisciplinary case conferences are accomplished in nursing homes. In these meetings nurses, physicians and the residents' relatives jointly detect reasons for residents' behavior. For this purpose they rely on a standardized instrument. Furthermore these interventions are supposed to improve the communication between the different caring actors.
Method: The study is conducted in the two German cities of Witten and Dortmund (North-Rhine-Westphalia). It uses a pre-post-test design. The residents (n = 182, MMST < 24) QoL (Qualidem), challenging behavior (NPI-NH) and physical maintenance (PSMS) are assessed before and 9 months after the intervention beginning (trainings and case conferences). In addition a chart analysis is carried out. Moreover nurses and GPs are interviewed about their feelings on working with demented people showing challenging behavior and about their experiences of the collaboration.
Results: The study's preliminary results will be presented and experiences with the trainings and case conferences and their possible influence on challenging behaviors will be discussed.
Conclusion: The use of case conferences in nursing homes by well trained professionals to find out reasons for residents' challenging behavior could have an influence on the occurrence of this behavior.
PS01.55
Cognitive-behavioural, resource-sensitive treatment for early dementia in Alzheimer's disease (CORDIAL)
Alexander Kurz
Technische Universität München, Munich, Germany
Background: Alzheimer's disease can be diagnosed at an early clinical stage, but pharmacological treatments remain unsatisfactory. patients' needs including preservation of functional ability are not met, and their abilities in terms of learning and adaptive potential are underused.
Methods: The CORDIAL study is a multi-centre, randomised, controlled, parallel-group study which evaluates the efficacy of a cognitive-behavioural intervention in 200 patients at the early clinical stage of Alzheimer's disease (MMSE ≥ 21). The treatment includes 12 weekly individual sessions of which 6 also involve the patients' caregivers. The programme focuses on establishing daily routines, using external memory aids, strengthening personal identity, and enhancing pleasurable activities. Routine medical treatment is used as a comparator. The primary outcome measure is the patients' functional ability; secondary outcome measures include quality of life, mood, and non-cognitive symptoms. Assessments are performed by independent raters who are blind to the patients' group assignment. Quality of data is ensured by regular on-site monitoring.
Results: At the time of writing, 186 patients have been recruited (mean age 74 years, 55% males). The cognitive-behavioural intervention achieves a high social validity and a remarkably low drop-out rate. Information on the efficacy of the intervention will be presented and discussed.
Conclusion: A novel cognitive-behavioural intervention for patients with early Alzheimer's disease is presented which aims at enhancing functional ability and emotional coping. If proven successful cognitive-behavioural therapy might become a regular component of the management of individuals with early dementia.
PS01.56
Perceived discrimination and psychological well being of elderly immigrants and visible minorities in Canada
Daniel Lai
University of Calgary, Calgary, AB, Canada
Introduction: The growth of the immigrant population and associated cultural diversity has prompted the research community and the policy sector to examine the role of exclusion and discrimination. However, little research has been conducted to examine the racial and ethnic discrimination experienced by elderly immigrants and ethno-cultural minority groups in Canada. This study focuses on the relationship between the perceived racial and ethnic discrimination, social exclusion and the well-being of elderly immigrants and visible minorities in Canada. The research question examined was “What is the effect of perceived discrimination on variables related to social exclusion and the well-being of elderly immigrants and elderly visible minorities?”
Method: Secondary data analysis was used, using data obtained from elderly 65 years and older in the 2002 Ethnic Diversity Survey conducted by Statistics Canada. Sample weights are applied to ensure accurate estimation of population parameters. For a statistical method that requires a measure of significance, standardized weights were used. Data analysis was conducted using SPSS version 16.0 to perform ordinal logistic regression, binominal logistic regression, and hierarchical OLS multiple regression, depending on the level of measure of the dependent variable included each set of analysis.
Results: Elderly immigrants who immigrated after 1961 and those who are visible minorities reported higher rates of discrimination compared to Canadian born or Caucasian elderly people. Visible minority status was the most important correlate of discrimination. Being a visible minority caused an individual to be 4.5 times more likely to experience discrimination. For the elderly immigrants, when controlling for age, gender, marital status, education, and visible minority status, those who reported having experienced discrimination were 41% less likely than those who did not experience discrimination to report a higher level of life satisfaction. Similar findings were reported for the Canadian born elderly and the Caucasian elderly. Most importantly, having experienced discrimination correlated significantly with lower levels of trust toward people in many settings, higher levels of feeling out of place, and higher levels of worry about hate crimes for most of above elderly subgroups.
Conclusion: Policies and programs are needed to support immigrant and visible minority elderly who are dealing with discrimination and related challenges. Programs and support should begin to take into consideration the perceived discrimination reported and its subsequent effects on well-being. The trajectory of how discrimination affects older adults, particularly elderly immigrants and visible minorities, as well as the effects of other contextual factors such as neighbourhood size and the ethno-cultural composition of one's social networks, need to be further examined in longitudinal studies.
PS01.57
Characteristics of poststroke depression in Chinese older people
Chi-leung Lam1; S Li2
1North District Hospital, Hong Kong, SAR PR China; 2Castle Peak Hospital, Hong Kong, SAR PR China
With ageing population, western diet and reduced mortality rate of stroke, poststroke depression becomes an important clinical issue among the patients, physicians and liaison psychiatrists in Hong Kong. There are limited local studies available about poststroke depression and management of stroke survivors with depressive disorders. The case records of sixty subjects who were attending the rehabilitation programs of a geriatric day hospital and were referred to the liaison psychiatric service for older people for suspected poststroke depression over a year were studied. The characteristics of these subjects were compared with those of sixty matched controls who were being referred to the liaison psychiatric service for older people and were not diagnosed to have poststroke depression. The age, sex and years of education of the two groups of subjects were controlled in order to focus on the clinical variables which may describe the characteristics of Chinese older people with poststroke depression. Poststroke Depression was diagnosed according to the results of Chinese Geriatric Depression Scale and the Diagnostic and Statistical Manual of Mental Disorders, fourth edition. After statistical analysis, the presence of chronic physical problems, cardiovascular risk factors, high mini-mental state examination scores and past history of mental illness were associated with depressive disorders in stroke survivors. Subsequent multivariate logistic regression analysis revealed that the presence of cardiovascular risk factors (3.9% of variance), high mini-mental state examination scores (17.2% of variance) and past history of mental illness (8.8% of variance) remained to be statistically significant in patients with poststroke depression. The characteristics of poststroke depression in this selected group of Chinese older people are similar to those of the Western populations. Based on the results, clinicians might follow up those poststroke older people with the above at risk characteristics more closely in order to detect poststroke depression early.
PS01.58
Treatment with memantine improves nursing care burden in severe Alzheimer's disease
Krista Lanctot1; G Eryavec2; N Herrmann1
1Sunnybrook Health Sciences Centre, Toronto, ON, Canada; 2North York General Hospital, Toronto, ON, Canada
Purpose: Memantine is an NMDA-receptor antagonist used in the treatment of moderate to severe Alzheimer's disease (AD). Evidence suggests that memantine improves neuropsychiatric symptoms in AD, but it is unknown whether these changes impact nursing burden. The objective of this study was to examine the impact of memantine on nursing care burden, and correlates of decreased burden.
Methods: Nursing home residents with severe AD (MMSE<15) and agitation/aggression (Neuropsychiatric Inventory-nursing home version (NPI-NH) total score ≥10 with a score of ≥1 on the agitation/aggression subscale) entered a 3-month, open-label trial of 20mg QD memantine. Baseline and monthly assessments included the Modified Nursing Care Assessment Scale (M-NCAS), a scale measuring nursing strain (primary), the NPI-NH, the Cohen-Mansfield Agitation Inventory (CMAI) and the MMSE.
Results: 19 of 32 subjects have been recruited to date (17M/2F, average age 85.9 ± 4.4 years with baseline MMSE scores of 7.0 ± 8.0). The M-NCAS demonstrated a significant decrease on the total score (137.3 ± 19.2 vs. 123.8 ± 18.4, paired t-test, p = 0.014) as well as the attitude and strain subscales (66.1 ± 14.4 vs. 56.9 ± 14.5, paired t-test, p<0.01 and 70.53 ± 5.9 vs. 65.7 ± 5.7, paired t-test, p = 0.02) at the endpoint. Completer analysis (n = 14) found an association between change in nursing burden (% change M-NCAS total) and changes in CMAI (r = 0.58, p = 0.040), but not NPI total (r = 0.31, p = 0.30) or MMSE (r = 0.32, p = 0.30).
Conclusions: A significant improvement in nursing care burden was observed following 3-month treatment with memantine. This decrease in nursing burden was correlated with improvements specifically in agitation, but not in total NPI scores or memory. Further recruitment of subjects will provide a more data regarding correlates of decreased nursing burden in institutionalized patients with AD treated with memantine.
PS01.59
Reducing verbally disruptive behaviours in patients with dementia: Correlates of individual response to a need-oriented intervention
Philippe Landreville1; A Bédard1; P Voyer2; R Verreault3; J Vézina1
1Université Laval, Québec, QC, Canada; 2Université Laval, Québec, QC, Canada; 3Université Laval, Québec, QC, Canada
Introduction: Verbally disruptive behaviours (VDB) include manifestations such as repetitive questioning, screaming, and negativism. It is one of the most prevalent behavioural symptoms associated with dementia. VDB have been related to unmet needs or goals, such as need for social interaction and sensory stimulation, and treatment addressing such needs has shown favourable results. The profile of patients most likely to improve with this type of intervention is unclear, however. The purpose of this presentation, which is based on data from a trial of a need-oriented intervention to reduce VDB, is to report correlates of individual response to this form of treatment.
Methods: The sample (N = 26) was composed of residents of long-term care facilities with a diagnosis of dementia and presenting VDB several times a day. A single-group repeated measures design was used. The intervention, which combined different techniques to provide social interaction and sensory stimulation activities and to reduce discomfort, was individualized and applied during 30 minutes sessions conducted by a trained therapist. Duration of VDB was recorded by trained observers. A change ratio of VDB (pretreatment VDB-VDB during treatment/pretreatment VDB) was calculated for each participant and served as an indicator of change as a function of the intervention. The relationships between the change ratio and various individual and treatment characteristics were analysed.
Results: Men and people with non-Alzheimer's types of dementia show more improvement with the treatment. Greater autonomy in activities of daily living (ADL), higher cognitive functioning, higher engagement during the intervention, more frequent requests for assistance (other than for ADL), and a longer duration of the social interaction component during the intervention is also associated with a better treatment response. A longer duration of the sensory stimulation component, more disruptive VDB and VDB manifested by groaning and verbal nonsense (no discernible meaning) are associated with a poorer response to intervention. A stepwise multiple regression analysis using all these variables indicates a significant (p < .01) relationship between the change ratio and the level of cognitive functioning. This variable alone explains 57% of the variance in treatment response. The introduction of other variables in the model does not improve the explanation of the response to treatment significantly.
Conclusion: Individual response to a need-oriented intervention to reduce VDB seems to be related to various patient and treatment characteristics. These need to be taken into account to increase the likelihood of successful outcome.
PS01.60
Improvement of depression and quality of life in elderly psychiatric inpatients
M Lapid; K Piderman; S Stevens; S Ryan; M Clark; T Rummans
Mayo Clinic, Rochester, MN, United States
Quality of life in the elderly may be adversely affected by severe depression. Our study results indicate that improvement of depression at the end of psychiatric hospitalization is associated with an improvement of overall quality of life of the depressed elderly. Addressing quality of life in the depressed elderly may help prevent further disability secondary to depression.
PS01.61
Enhancing resilience and quality of life in depressed family dementia caregivers: A randomized placebo-controlled trial of escitalopram
Helen Lavretsky; M Irwin
UCLA, Los Angeles, CA, United States
Background: We assessed the potential of an antidepressant drug, escitalopram, to improve resilience to stress and quality of life in depressed family dementia caregivers in a randomized placebo-controlled double-blind trial.
Methods: We recruited 40 family caregivers (43–91 years of age, 25 children and 15 spouses; 26 women) who were taking care of their parents or spouses with Alzheimer's disease and randomized them to receive either escitalopram 10 mg/day or placebo for 12 weeks. We assessed the severity of depression, negative ruminations, resilience, burden, distress, quality of life, severity of care-recipient's cognitive and behavioral disturbances, and proinflammatory cytokines at baseline and at follow up. HDRS scores at baseline ranged between 7–28. The groups were stratified by the diagnosis of major and minor depression.
Results: Most outcomes favored escitalopram over placebo. The severity of depression improved with the drug compared to placebo (F = 5.5; df = 23; P = 0.02). Interestingly, subjects who took escitalopram demonstrated 60% improvement in resilience compared to 2% improvement in resilience in those on placebo (t = −2.2; p = 0.04). We observed reduction in pro-inflammatory cytokine levels correlated with reduction in depression severity (r = −0.5) in both treatment groups. Although the magnitude of improvement in depression was greater in subjects with major depression, the final HAM-D scores did not differ between those with major or minor depression.
Discussion: We concluded that antidepressant use in caregivers can improve depression, boost resilience and energy, ease burden and distress, and improve quality of life. Inflammation may improve as a result of decrease in the depression severity with either drug or placebo. Our result needs to be confirmed in a larger sample.
PS01.62
When long-term care becomes hard time: The elderly in prison
Kevin Lawless; L Pisani; A Lyle
Alberta Hospital Edmonton, Edmonton, AB, Canada
As the number of elderly persons in society increases, one can expect a corresponding increase in the number of older individuals in contact with the criminal justice system. Consequently, it is also likely that there will be an increase in the number of elderly prisoners. The objective of this study was to test this hypothesis. A comparison was made of the offender demographics from two Federal penitentiaries in Alberta, Canada. The data compared two specific days, separated by five years (April 13, 2003 vs. April 13, 2008). An additional review of the Correctional Services of Canada data compared all serving inmates in the country for those two days. The Edmonton Institution for Men is a maximum security prison in Edmonton, Alberta. During this study period, there was a 500% increase in older offenders (> = 50 years of age) serving time for murder, and a 200% increase in older sexual offenders. Bowden Penitentiary is a medium security prison located south of Red Deer, Alberta. The number of younger offenders (<50 years of age) increased by 5%. The total number of older offenders increased by 35% (48 vs. 65), with the majority being between 50 and 59 years old. There was a 33% increase in those serving time for sexual offenses (9 inmates) and a 133% increase in non-sexual violent offenders (8 inmates). The data for all serving inmates in Canada for the study period indicates that while the total offender population increased by 7%, the increase in all age categories of older offenders was greater than 32%. The increase in geriatric offenders (47% for those > = 65 years of age) was 7 times that of the general inmate population. Older inmates bring with them a host of medical and psychiatric conditions that often require specialized health services currently unavailable in prison. Aged and disabled individuals often require physical modifications to their environment and specialized convalescent treatment for their many and varied conditions. Correctional facilities designed for a younger, more physically able population, create hazards for those older and infirm inmates with reduced mobility. Specialized medical services may not be readily available, resulting in a delay of treatment for major conditions. Decimated family and peer relationships result in further isolation. Prisons offer programs to rehabilitate inmates. These programs are necessary for success upon release; however, the older prisoner is often deemed a poor candidate for these activities. Consequently, there are few facilities outside the prison system willing to take these inmates. The projected increase to Alberta's elderly population is 500,000 by the year 2016. It is reasonable to conceive that a significant number of these older individuals will find themselves in conflict with the law, thus further burdening an already overburdened justice and healthcare system.
PS01.63
Alive or dead: Legal directives, undue influence and abuse
Kevin Lawless; L Pisani; A Lyle
Alberta Hospital Edmonton, Edmonton, AB, Canada
The purpose of this current study is to highlight areas of potential undue influence and abuse in a vulnerable geriatric population. The life expectancy and financial assets of the baby boom generation are expected to increase; therefore, this group will posses unprecedented wealth available for their personal use or the posthumous distribution to others. In addition, many members of this aging population will suffer from medical, psychiatric or social conditions that will render them vulnerable to manipulation and fraud by unscrupulous individuals. This undue influence can result in personal harm, financial ruin and the disinheritance of intended beneficiaries and rightful heirs. Undue influence in the creation of Wills has been an area of concern for professionals for many years, yet no formal guidelines exist to protect against this abusive action. Governments have recently developed Personal Directives and Enduring Powers of Attorney to assist in the care of those who are unable to manage on their own. It is intended that these documents be the primary tools in preventing abuse of living individuals when they are completed appropriately. However, if the Professionals who assist in the completion of these directives lack knowledge about the risk factors and recommended interventions when undue influence is suspected, these Professionals may become unwitting accomplices.
This initiative will examine three cases that demonstrate incidents of undue influence where Professionals were involved in the creation of a legal directive of a vulnerable victim. Case 1 examines a 70-year-old man who, in spite of a history of psychiatric symptoms and cognitive deficits, was able to have an Immediate Enduring Power of Attorney legally drawn-up naming his neighbor as his Agent. This neighbor then charged him rent after purchasing the victim's house for $1 and subsequently procured his pension cheques. Case 2 describes the financial abuse of an 85-year-old woman with dementia by a drug-addicted daughter who had repeated dealings with the bank before they reported the on-going abuse. Case 3 portrays a 79-year-old woman with multiple fractures who was befriended by a co-patient who took over her life by having a lawyer draw up a Personal Directive, Power of Attorney and Will naming a dubious third party as her Agent, Attorney and beneficiary. In all three cases the undue influence exercised by others was not immediately detected by the Professionals who were contracted to assist in drawing up the legal directives.
It is our hope that increased awareness about the problem of undue influence and abuse in the geriatric population will result in Professional bodies educating themselves and their colleagues about this matter. Professionals must explore the many issues present in cases of undue influence and apply guidelines to their practices to help prevent the abuse of this vulnerable population.
PS01.65
Are advanced glycation end products a specific biochemical marker for early detection of Alzheimer's disease?
Jerzy Leszek; A Gamian; M Staniszewska
University of Wroclaw, Wroclaw, Poland
Background: Potential candidates for a specific biomarker for early detection of Alzheimer's disease (AD) might be advanced glycation end-products (AGEs) considered to be involved in AD etiopathogenesis.
Objectives: In the current study the contents of AGEs was examined with an immunochemical assay in the sera of AD patients.
Methods: Subjects with AD (n = 27, age range 57–89 years) and non-AD (vascular) dementia (n = 23, age range 54–79 years) were included in the study. The results were compared to the healthy controls groups: older people (n = 66, age range 52–89 years) and younger people (n = 59, age range 21–49 years). The ELISA inhibition test for the determination of AGEs is based on a rabbit anti-AGE, affinity purified antibody and a model AGE-myoglobin antigen, where serum sample treated with proteinase K is used as an inhibitor. For the measurement of immune complexes and anti-AGE antibodies the corresponding ELISA tests have been applied.
Results: The AGEs level in AD group (38.6 U AGE) was lower than in non-AD group (40 U AGE), but the difference was not statistically significant. The mean level of total AGEs in the sera of AD patients were significantly lower than in the controls: 60.2/49.5 U AGE. The relations were not observed regarding to the immune complexes levels. The mean level of total IC in AD group (78.1) was slightly lower than in controls (73.2/74.8) but the differences were not statistically significant.
Conclusion: The work revealed the lower level of circulating serum AGEs products in patients with AD. Potential utility of the finding on the level of specific biomarker, needs more comprehensive investigation.
PS01.67
The creation of a world's first city-wide elderly suicide prevention service—how did we do it in Hong Kong?
Siu Wah Li
Castle Peak Hospital, Hong Kong, SAR PR China
Although it is a worldwide phenomenon that elderly people have the highest suicide rate, there is surprisingly no large scale, city-wide elderly prevention service in the world.
In 2003 in Hong Kong (population 7 million), a city-wide elderly suicide prevention service was started to provide coverage to all the city's 80,000 elderly. We believe this is the first of its kind in the world.
The service delivery is based on the fact that, although multi-factorial, depressive illness is the single most important factor in elderly suicide.
The service aims to identify early elderly suffering from depressive illness, especially the severe ones and also elderly with suicidal intent or attempts and then to treat these elderly effectively and quickly. By doing so, it is expected that it will have a positive impact on the prevention of elderly suicide.
The presentation will discuss the two-tier model Hong Kong is using for this service and why we adopt this model. We will also discuss the extensive involvement of the elderly social services as a partner in the first tier.
Relevant service data will be presented. The limitations, and the challenges, will be further explored.
PS01.68
The monk and the psychiatrist: Why Buddhism is relevant to psychiatry
Siu Wah Li
Castle Peak Hospital, Hong Kong, SAR PR China
Although both Buddhism and Psychiatry work to relieve mental suffering of mankind, curiously, their paths almost never meet. It could not, and should not be so.
There are now minor adaptations of some of the Buddhist meditation skills into psychiatric practice, mostly in the form of relaxation exercise or mindfulness training, but not much more.
This author, himself not a Buddhist, argues that Buddhism can be potentially much more useful to Psychiatry.
To start, Buddhism is actually very psychological in its orientation and devoted a lot of its canon to analysing the psychological makeup of man. Some of the canon should give valuable insight into the working of the mind and would be a great help to psychiatry.
Buddhism very much stresses compassion, and this author believes this would be a very useful framework, apart from empathy, to frame doctors’ aspiration to our patients.
Wisdom is another concept central to Buddhism. Again, if used correctly, this would help in dealing with the ever-changing clinical challenges of psychiatrists.
Finally, Buddhism should prove to be very rewarding for the unwinding of us psychiatrists after a hard day's work. The author will share with you his experience in this.
PS01.69
Living alone, loneliness, and psychological well-being of the elderly in Singapore
Lena Lim; E Kua; T Ng
National University of Singapore, Singapore
Studies of the psychological well-being of elderly who live alone have yielded inconsistent results. Few investigators have distinguished living alone from loneliness in the same study. Being alone does not equate to being lonely although it may be associated with increased risk of loneliness. While loneliness is a subjective emotional experience of one's personal relationships, living alone is an objective measure of one's living arrangement. The present study sought to examine the unique effects of living alone and loneliness and their interaction on the psychological well-being in a community sample of older adults aged 55 years and above in Singapore who were followed up for 2 years. There was a significant interactional effect of loneliness and living alone on depression at baseline with control for covariates such that lonely elderly who lived alone had higher depression in GDS score than lonely elderly who lived with others. However, there was no significant difference on GDS scores between non-lonely elderly who lived alone and those who lived with others at baseline. After controlling for differences in other associated factors, lonely elderly were also more likely to be depressed and associated lower quality of life in SF-12 MCS score at follow-up than elderly who did not feel lonely. Living alone was also associated with lower MCS scores of quality of life at follow-up.
PS01.70
Correlation between severity of delusions and regional cerebral blood flow in Alzheimer's disease
Teruyuki Matsuoka; J Narumoto; K Shibata; A Okamura; K Nakamura; K Fukui
Graduate School of Medical Science, Kyoto Prefectural University of Medicine, Kyoto, Japan
Background: Psychoses such as delusions and hallucinations are commonly observed in Alzheimer's disease (AD). Psychosis in AD increases caregiver burden and risk of institutionalization, and often becomes a clinical problem because of its difficulty to treat. In the treatment of AD, donepezil is the only drug available in Japan. Although antipsychotic drugs are used to treat psychosis in AD, there is some doubt about the validity of them in AD. Moreover, many studies have reported that antipsychotic drugs increase mortality in AD. Therefore, for the development of treatment strategy, it is important to demonstrate the neurological pathophysiology of psychosis in AD.
Objectives: The purpose of this study was to identify the brain region associated with severity of delusions in AD using SPECT.
Methods: Fourteen patients who met the National Institute of Neurological and Communicative Disorders and Stroke and the Alzheimer's Disease and Related Disorders Association criteria for probable AD and had at least 1 point on the delusions subscale score of Neuropsychiatric Inventory (NPI) (2 men and 12 women, mean age: 76.5 ± 6.0) participated in this study. Informed consent was obtained from all of the patients. Mean Mini-Mental State Examination (MMSE) score was 20.8 ± 3.8. Regional cerebral blood flow (rCBF) was measured by N-isopropyl-p-123I-iodoamphetamine single photon emission computed tomography. Image analysis was performed using SPM5 software (the Wellcome Department of Imaging Neuroscience, Institute of Neurology, University College London) running in MATLAB 7.5 (Mathworks, Sherborn, MA). The images were spatially normalized to the Montreal Neurological Institute (MNI) template and were smoothed with a 12-mm full-width at half-maximum isotropic Gaussian Kernel. Multiple regression analysis was performed to identify linear correlation between the delusions subscale score of NPI and rCBF. Other subscale scores of NPI and MMSE score were included as covariates. Voxels that had a t statistic greater than 6.96 (p < 0.01, uncorrected) were considered to be significant.
Results: The delusions subscale score of NPI was negatively correlated with rCBF in the right insula (MNI coordinates: X = 46, Y = 14, Z = −8).
Conclusions: Previous studies suggested that the insula played an important role in the processing of emotion and visceral sensory, the perception of emotional significance, and the integration between the external stimuli and internal milieu [1, 2, 3, 4]. Therefore, the present result might be interpreted that the emotional dysregulation caused by the dysfunction of the right insula is associated with the severity of delusions in AD.
[1] Davidson, R. J., Irwin, W.: The functional neuroanatomy of emotion and affective style. Trends Cogn Sci. 1999;3(1):11–21.
[2] Mesulam, M. M., Mufson, E. J.: Insula of the old world monkey. III: Efferent cortical output and comments on function. J Comp Neurol. 1982;212(1):38–52.
[3] Nagai, M., Kishi, K., Kato, S.: Insular cortex and neuropsychiatric disorders: a review of recent literature. Eur Psychiatry. 2007;22(6):387–94.
[4] Reiman, E. M., Lane, R. D., Ahern, G. L., Schwartz, G. E., Davidson, R. J., Friston, K. J., et al.: Neuroanatomical correlates of externally and internally generated human emotion. Am J Psychiatry. 1997;154(7):918–25.
PS01.71
Post-operative cognitive decline in older people undergoing elective joint replacement surgery: The CAPES study
Pamela Melding1; F Stapelberg5; S Mitrovic-Tosovic3; R Worrall4; J Stewart1; A Clarke2; L Rowlands2; J Bryce2; C Howie2
1University of Auckland, North Shore City, New Zealand; 2Centre for Clinical Excellence and Effective Practice, Auckland, New Zealand; 3Waitemata District Health Board, Auckland, New Zealand; 4Auckland District Health Board, Auckland, New Zealand; 5Counties Manukau District Health Board, Auckland, New Zealand
Every year, thousands of older people have major surgery. After the surgery, some notice that aspects of their memory or thinking deteriorate, an unexpected and unpredicted adverse event for them and their families. Overseas studies indicate that post-operative cognitive decline (POCD) occurs in one or more cognitive aspects in 5–30% of people having elective surgery. The most consistent data indicates a rate of at least 10%. This is significant, compared to the rate of overall decline in the general population, which is about 3% per year. The CAPES study is a novel longitudinal clinical study designed to assess the prevalence and risks for post-operative cognitive decline in older people following elective surgery in New Zealand patients. Our main hypothesis of the study was that a major risk factor for post-operative cognitive decline (POCD) was undetected mild cognitive impairment (MCI) or subclinical dementia. We also considered that pre-existing depression, particularly of vascular origin, cerebrovascular insufficiency, diabetes, hypertension, hypotension, and cigarette smoking may also be risk factors because of their effect on cerebral circulation.
Method: The study was a longitudinal, clinical study of patients over age 55, undergoing elective joint replacement surgery at two major hospitals in Auckland. The patients are recruited on entry to the waiting list. Three hundred subjects were initially recruited. The patients were assessed on 6 occasions, (3 in the six months before surgery and 3 in the year after surgery) with a Depression Rating Scale (GDS), an Anxiety Inventory (STAI), Bedside Cognitive Status (GP Cog), Health Status and a Quality-of-Life scale, plus the Cognitive Drug Research (CDR) Assessment Battery. Peripoperative medical, surgical and medication data and a post operative delirium screen on each patient were included in the data collection. The mode of anaesthesia was mostly sedation and regional analgesia.
Results: The attrition rate was less than 25%. Some patients were too sick to have surgery and were followed up in a control group. Pre-surgery cognition was assessed by comparing the patient's scores with normative database scores. A change in cognitive scores of 1 SD in one or more of the composite CDR measures from baseline pre-surgery to 6 weeks and 1 year post surgery measures denoted cognitive change. Post operative cognitive decline was at its highest prevalence in the first week after surgery, when patients were still taking powerful pain medication, and the prevalence reduced over the one year follow-up. Several patients improved their cognition. The risk factor of pre-existing cognitive impairment as a predictor of POCD is discussed in this presentation.
PS01.72
Cognitive impairment is associated with low blood pressure in very old people
Lena Molander; H Lövheim; Y Gustafson
Department of Community Medicine and Rehabilitation, Geriatric medicine, Umeå, Sweden
Objectives: To investigate the association between blood pressure and cognitive impairment defined by the Mini-Mental State Examination (MMSE) in very old people.
Design: Population-based cross-sectional study.
Setting: County of Västerbotten, Sweden and county of Österbotten, Finland.
Participants: Half of all 85-year-olds, all 90-year-olds and all 95 years or older, in one urban and five rural municipalities in the north of Sweden as well as in two municipalities in the north of Finland, in total 575 individuals.
Measurements: Participants were visited and interviewed in their home using a structured protocol and data was also collected from medical charts and caregivers, when applicable. Systolic (SBP) and diastolic blood pressure (DBP) was measured and mean arterial pressure (MAP), pulse pressure (PP) and Body Mass Index calculated. Assessments were made using the following scales: Mini-Mental State Examination, Barthel Activities of Daily Living Index, Geriatric Depression Scale-15, Philadelphia Geriatric Center Morale Scale, Organic Brain Syndrome scale.
Results: MMSE scores were significantly lower in the quartiles with the lowest SBP (≤120 mmHg) and DBP (≤65 mmHg). Participants with dementia had significantly lower mean SBP, DBP, PP and MAP. Hypertension was associated with better results on the MMSE. In univariate linear regression SBP, DBP and MAP were associated with MMSE in a non-linear fashion, where both high and low pressures were associated with lower scores. The relation between PP and MMSE scores was linear. In multivariate analysis, including some demographic factors and diagnoses, all blood pressure parameters except DBP remained significantly associated with MMSE in the same pattern.
Conclusion: There is a connection between blood pressure and cognitive impairment defined as lower scores on the MMSE in the very old, where both low and high SBP and MAP and low PP coincide with lower MMSE scores after adjustment for a number of health factors, suggesting an independent impact of blood pressure in itself.
PS01.73
Apathy assessment using ambulatory actigraphy short-time recording in mild Alzheimer's disease
Emmanuel Mulin1; R David1; A Rivet1; L Friedman2; J Zeitzer2; J Yesavage2; P Robert1
1Centre de Mémoire de Ressources et de Recherche, Nice, France; 2Stanford University, Stanford, CA, United States
Objective: Apathy is the most frequent neuropsychiatric symptom across all stages of Alzheimer's disease (AD) in studies using the Neuropsychiatric Inventory. The absence of reliable objective measure is one of the main difficulties in assessing apathy. The aim of the study was to stress the relationship between apathy and motor activity using ambulatory actigraphy in individuals with mild AD.
Methods: Thirty subjects with diagnosis of AD (with apathy, mean age: 78,65 +/– 7,36; MMSE: 22,59 +/– 2,72; without apathy, mean age: 80,20 +/– 4,96; MMSE: 20,40 +/– 3,16) and fifteen healthy controls (age: 73,13 +/– 6.01) were recruited at the Nice Memory Center. Patients with a score greater than three on the Apathy Inventory (AI), caregiver version, were considered as having apathy. Patients were divided into two subgroups (with and without apathy) according to Diagnostic Criteria of Apathy (DCA, 2009). Quantitative assessment of apathy was done using the AI consisting of three dimensions: emotional blunting, lack of initiative and lack of interest. Locomotor activity was assessed using a wrist-worn actigraph for 75 minutes during which neuropsychological and behavioural examinations were performed (60 minutes) followed by 15 minutes of free activity.
Results: AD patients showed lower mean motor activity than healthy subjects (p < 0,05). AD patients with apathy had lower mean motor activity than AD patients without apathy. AI total score correlated negatively with mean motor activity. Most of the total score correlation was accounted for by correlations between the apathy dimensions lack of initiative (r = –0,35; p < 0,05) and lack of interest (r = –0,31; p<0,05), with mean motor activity.
Conclusion: Ambulatory actigraphy could be an objective technique to assess apathy as part of routine assessment of AD patients.
PS01.74
Music therapy in the management of depression
Audun Myskja
University of Bergen, Oppegård, Norway
This oral presentation will present the study The day the music died—a pilot study comparing a no music therapy to a music therapy condition in a Norwegian nursing home.
This study showed a significant fall in MADRS depression rating in the music therapy condition, compared with the no music therapy condition, MADRS falling from 20,1 to 11,8 on an average, using crossover design (n = 84). Staff at the institution was stable, and there were no significant changes in medication.
The presentation will give an overview of the present study, and sketch practical factors important for success with music therapy in nursing homes, based on five projects in thirteen nursing homes in Norway in the period 2000–2008.
Features of the presentation include: overview of research literature on music therapy and depression; which music methods are most effective in depression; how these can be applied in nursing homes; audio samples; and video clips from individual and group treatment in nursing homes.
Myskja, A. The day the music died—a pilot study comparing a no music therapy to a music therapy condition in a Norwegian nursing home. Nordic Journal of Music Therapy, 2008; 17: 30–40.
PS01.75
The attitudes and practices of general practitioners regarding dementia diagnosis and management in Japan
Jin Narumoto; K Shibata; T Matsuoka; A Okamura; K Nakamura; K Fukui
Kyoto Prefectural University of Medicine, Kyoto, Japan
Background: General practitioners (GPs) in Japan are now required to play a primary role in diagnosis and management of dementia because of the increasing number of the patients due to the rapid growth of older population and the lack of specialists. However, Japanese GPs have never been formally educated about dementia throughout their career and have little partnership with the specialists.
Objectives: The purpose of this study was to delineate the actual situation of GPs’ clinical practice regarding dementia diagnosis and management in order to investigate their need for support and education from the specialists.
Methods: Data were collected from GPs (n = 175) who were working in Kyoto Prefecture, Japan and attended the lecture about dementia that was held by the Kyoto Medical Association at three places in 2008. They filled out the questionnaire after the lecture.
Results: Most GPs (80%) treated patients with dementia in their practice. Some of them (33%) received no support from the specialists regarding treatment of dementia. GPs answered that the most important thing for the management of the patients in the community was to improve their own ability in managing the patients with dementia. Regarding cognitive screening test, Hasegawa Dementia Scale Revised (HDS-R) was the most popular test (n = 105). Most of the GPs (88%) out of those who treated the patients with dementia had an experience of prescribing donepezil that was the only acetylcholine esterase inhibitor for Alzheimer's disease available in Japan. Considerable number of them had an experience of prescribing antipsychotics, such as haloperidol (n = 55) and risperidone (n = 40), to treat behavioral and psychological symptoms of dementia (BPSD). Finally, they found it difficult in managing the patients to deal with BPSD (n = 82) and to find a hospital to send their patient to (n = 82) when their patient needed to be hospitalized because of severe BPSD.
Conclusions: Although GPs in Japan had started to treat the patients with dementia, there remained a significant portion of GPs without support from the specialists. It is urgent to develop partnerships between GPs and the specialists. Since GPs have a positive attitude toward mastering the knowledge about dementia, the specialists would be responsible for providing better support and education to them. The majority of GPs used HDS-R as a screening test. This can be explained by the fact that the score of HDS-R is incorporated in the doctor's opinion paper of long-term care insurance. Since HDS-R does not cover visuospatial function, it would be plausible to propose GPs add Clock Drawing Test. Considering frequent prescription of antipsychotics, the specialists should provide updated information about antipsychotics including increased mortality among the patients with dementia who are treated with antipsychotics and appropriate way of prescription. Finally, among the specialists of dementia including the geriatrician and the neurologist, the geriatric psychiatrists might be the most required specialist to support GPs because the GPs have trouble dealing with BPSD.
PS01.76
Risk factors for development of depression in the elderly
Sammy Ng; H Ng; W Chan; K Ho
Department of Health, HKSAR, Hong Kong, SAR PR China
This study aims to identify risk factors for development of depression in the elderly.
Methods: Health data collected during two consecutive health assessments of elders enrolled in 18 Elderly Health Centres of Department of Health of Hong Kong from 2001 to 2003 were analysed. The association between development of depression, based on Geriatric Depression Scale (GDS), and potential risk factors were tested by univariate analyses, followed by multivariate logistic regression analysis.
Results: Out of 22513 elders who enrolled for the first time between 1 Jan 2001 to 31 Dec 2003 and underwent the first health assessment, 16537 re-enrolled subsequently and underwent the second health assessment after a median period of 17 months. Among 15191 elders who were found to be not depressed (score < 8 on GDS) at the first health assessment, 534 (3.5%) were found to have depression (score ≥ 8 on GDS) at the second health assessment. Risk factors development of depression included female sex (OR 1.29, 95% CI 1.04–1.60), working full time or part time (OR 1.77, CI 1.05–3.00), uneducated (OR 1.44, 95% CI 1.10–1.88), poor self-rated health (OR 1.78, 95% CI 1.37–2.32), dependence on government assistance for living (OR 1.74, 95% CI 1.39–2.17), impaired functional ability (OR 1.40, 95% CI 1.03–1.90), eating difficulty (OR 1.55, 95% CI 1.09–2.21), hearing loss (OR 1.45, 95% CI 1.08–1.95), eye problem (OR 1.54, 95% CI 1.01–2.34), musculoskeletal problem (OR 1.38, 95% 1.15–1.66) and miscellaneous medical conditions (OR 1.27, 95% CI 1.06–1.54). Exercise, especially aerobic exercise (OR 0.65, 95% CI 0.45–0.93) and traditional Chinese exercise (OR 0.56, 95% CI 0.40–0.77) were found to be protective against development of depression.
Implication: Promotion of exercise, proper management of elders’ medical conditions and tackling problems associated with eating and activities of daily living could help prevent the development of depression among community dwelling elders.
PS01.77
Risk and protective factors of dementia: Findings from the Singapore Longitudinal Ageing Studies
Tze Ng1; E Kua1; L Feng1; M Niti2; K Yap3; P Yap3
1National University of Singapore Yong Loo Lin School of Medicine, Singapore, 2Ministry of Health, Singapore; 3Alexandra Hospital, Singapore
We examined risk and protective factors of dementia in cross-sectional and longitudinal analyses of data in the Singapore National Mental Health Survey (SNMHSE) 2003 and the Singapore Longitudinal Ageing Studies (SLAS). The SNMHSE was a diagnostic interview survey of 1,092 seniors and the SLAS followed up a cohort of 2,800 older adults aged 55+ at 2 yearly intervals from 2004.
Dementia prevalence was estimated to be 6.0% among seniors aged 60 and above, cognitive impairment in 24%, both consistently higher in older age, women, and Malay and Indian (versus Chinese) in multivariate analysis that controlled for a wide range of variables.
Leisure time and physical, social and productive activities were found to be associated with less cognitive decline, but productive activities appeared to show the strongest independent effect.
Depressive symptoms were associated with cognitive decline, evidently in men (not women), and in APOE-e4 carriers.
Untreated hypertension was associated with cognitive impairment. As well, orthostatic hypotension in hypotensive seniors was associated with cognitive impairment, suggesting a possible role as an early co-morbid marker of a primary incipient dementia.
Metabolic syndrome was associated with cognitive decline. The use of statins in cognitively impaired seniors was associated with lowered risk of cognitive decline, especially in APOE-e4 carriers.
There was evidence of neuroprotective effects of nutritional factors including micronutrients and anti-oxidants. Across the range of values of albumin and haemoglobin, linear inverse relations with cognitive impairment and decline were observed.
Serum folate was associated with performance on tests of memory and language. Homocysteine was negatively associated with performance on tests of constructional ability and processing speed. B12 level was associated with performance on tests of attention, working memory and learning, only in APOE-e4 carriers.
SLAS participants who regularly consumed omega-3 supplements were less likely to show cognitive decline.
Regular tea consumption was associated with lowered risks of cognitive impairment and decline, and better performance on a wide range of cognitive functions, effects not similarly observed with coffee drinking.
Regular curry intake which contains turmeric and is rich in curcumins was found to be associated with better cognitive performance.
PS01.78
Relation with cholesterol and attempted suicide in elderly patients
Evaristo Nieto; A Blázquez; C Hernández; J Fernández; P Bonet
Althaia Xarxa Assistencial, Manresa, Spain
Introduction: Case-control and cross-sectional studies have demonstrated lower cholesterol levels in patients admitted following suicide attempts compared to those admitted without an attempt. However, no studies to date have examined the association of cholesterol levels and attempted suicide in elderly patients.
Aims: The aim of the present study was to assess the relationship between cholesterol levels and suicidality in elderly patients.
Methods: Subjects: The index population of 197 patients was recruited from elders (65 years or more) admitted consecutively for first-lifetime to the psychiatric unit. Of these, 42 elders were hospitalized following any act of deliberate self harm or parasuicide and the rest of 155 elders were admitted for first-lifetime to the psychiatric unit without any previous suicidal act.
Attempted suicide classification: Drug overdoses and superficial wrist cutting were classified as non-violent methods of suicide; all other methods were classified as violent. The lethality of suicide attempts was classified in serious (require at least 24 hours of medical hospitalization before psychiatric ingress) or non-serious suicide attempts, in the opposite.
Determination of cholesterol levels: All total cholesterol levels were determined in the first 3 days after the patients were hospitalized.
Statistical Analysis: In first analysis we compared total cholesterol levels between suicidal and non-suicidal elders groups. In second analysis group of violent suicide attempters were compared for serum total cholesterol with group of non-violent suicide attempters, and with group of non-suicidal elderly psychiatric inpatients. In third analysis group of serious suicide attempters were compared for serum total cholesterol with group of non-serious suicide attempters and with group of non-suicidal elderly psychiatric inpatients. The comparison between the different groups were made using t de Student for non-paired samples.
Results: There were no differences in total cholesterol levels between the groups of elderly suicide attempters (mean of 4,74 mmol/l) and non-suicidal elderly psychiatric controls (mean of 4,82 mmol/l). There were no differences in total cholesterol levels between the groups of elderly suicide violent attempters (N = 14, the majority suicidal gesture without serious lethality, mean of 4,82 mmol/l) and elderly psychiatric controls (mean of 4,82 mmol/l) or elderly suicide non-violent attempters (N = 28, mean of 4,71 mmol/l).
Serious suicide attempters had significantly (P < 0.003) lower total cholesterol (N = 14 mean of 4,08 mmol/l) compared with those with non-serious suicide attempts (N = 28, mean of 5,08 mmol/l) and significantly (P < 0.01) lower total cholesterol compared with non-suicidal elderly psychiatric controls (mean of 4,82 mmol/l).
Conclusion: Only elderly suicide attempters with serious lethality had significantly low levels of total cholesterol compared with non-serious suicide attempters (including violent suicidal gesture) and with non-suicidal psychiatric elders.
PS01.79
Suicide attempts in the elderly immediately before their first psychiatric hospitalization
Evaristo Nieto; M Puig; R Planet; M Viladrich; L Villar; E Pons; P Bonet
Althaia Xarxa Assistencial, Manresa, Spain
Introduction: In many countries the oldest age groups have the highest suicide rates. Few studies in clinical samples of elderly patients analyze the risk factors of suicide attempts among this group of age. The retrospective study of elderly psychiatric inpatients offers the possibility of obtaining a large sample of elderly suicide attempters and shows in detail the clinical situation just after the attempt.
Subjects: This was a retrospective study. All the elderly patients (>65 years old) admitted consecutively for first lifetime to the acute psychiatric Unit of Althaia Xarxa Assistencial of Manresa during a 13 years period (1996–2008) were included as study subjects. If elders were admitted following an attempted suicide, they were included in the Elderly Suicide Attempters group. All other elders were included in the Elderly Non-Suicide Attempters group.
Procedure: The charts of all elderly inpatients were reviewed retrospectively. The basic data, such as sociodemographic information, psychiatric and medical diagnosis, details of suicide attempt, past suicide attempts, and family history were obtained. The psychiatric diagnosis according to DSM-IV criteria of the index hospitalization was recorded.
Statistical Analysis: Data were analyzed with SPSS. The proportions of categorical variables between suicide attempters and non-suicide attempters were compared with χ2 test. Student's t test was used to compare normally distributed continuous variables. Multivariate analysis with multinomial logistic regression was used with their 95% confidence intervals for all explanatory variables.
Results: Of the 225 elders admitted during the study period, 51 (22.7%) were admitted as a result of suicide attempt. There were significantly more men in the group of elderly attempters (53% vs 35%, P<0.04). Elderly attempters (mean of 76,4 years), were significantly (P<0.03) older than non attempters (mean of 74,1). Elderly attempters had significantly more previous suicide attempts (P < 0.000). In the group of elderly attempters there were significantly more patients diagnosed with unipolar major depression and adaptive depressive disorder (P < 0.000) and significantly fewer patients had psychotic symptoms (P < 0.000). No other significant differences were found between the groups among the other variables examined: organic or psychiatric comorbidity, alcohol abuse, previous psychiatric history, immediately previous treatment with antidepressants, and duration of psychiatric admission failed to distinguish between suicide attempters and non-attempters. After multivariate analysis with multinomial logistic regression the previous suicide attempts (P < 0.001) the diagnosis of unipolar depression or adaptive disorders (P < 0.004), the absence of psychotic symptoms (P < 0.015), the male gender (P < 0.011) and the older age (P < 0.036) remained as significant risk factors of the group of elders with suicide attempts.
Conclusion: The history of previous suicide attempt, the diagnostic of unipolar depression or adaptive disorder, the absence of psychotic symptoms, the male gender and the older age are significant risk factors for attempted suicide in elders admitted for first lifetime to the acute psychiatric Unit.
PS01.80
Working criteria of mild cognitive impairment (MCI) in community: Findings from the Gwangju dementia and mild cognitive impairment study (GDEMCIS)
K Lee1; Byoung Hoon Oh2; W Hahm3; H Cheong4; C Hong5
1Bundang Cha Hospital, Seongnam-si, South Korea; 2Yonsei Univ. College of Medicine, Gwangju, South Korea; 3Keyo Hospital, Uiwang-si, South Korea; 4Sunghkyunkwan University, Suwon, South Korea; 5Ajou University, Suwon, South Korea
Background: Reported rates of mild cognitive impairment (MCI) range widely depending on methodologic differences, including specific sample characteristics, cognitive measures used, normative samples used for neuropsychological tests, and diagnostic criteria. The purpose of this study was to ascertain the existence of subtypes of MCI and investigate their clinical and neuropsychological characteristics.
Methods: We classified 3 subtypes of MCI based on modified CRCD working criteria.
Results: 384 patients (252 females and 132 males) were enrolled as MCI and analyzed. MCI I showed higher cognitive function and lower depression score than MCI II. There's no difference in clinical characteristics between amnestic type and non-amnestic type.
Conclusions: We investigated various clinical features of MCI according to their subtypes and ascertained heterogeneity of MCI subgroups. Prospective cohort studies with clinicopathological correlations will help to clarify whether some of the subtypes of mild cognitive impairment are prodromal stages of specific dementias, paving the way for early therapeutic interventions.
PS01.81
The SYMBOL study: A new dementia screening test for elderly immigrants
J. Parlevliet1; M Goudsmit3; J Campen4; S Rooij1; B Schmand2
1AMC, Amsterdam, Netherlands; 2AMC, Amsterdam, Netherlands; 3Slotervaartziekenhuis, Amsterdam, Netherlands; 4Slotervaartziekenhuis, Amsterdam, Netherlands
Background: North-west European countries have had a large influx of immigrant laborers from Turkey and Morocco during the 1960s and 1970s. Furthermore, in the 1980s many immigrants from Surinam came to the Netherlands. A large percentage of these first generation immigrants are illiterate, or have had only few years of formal education. Many never learned to properly speak the language of their new country. This generation is now aging, which poses a problem for health care workers.
Cognitive decline and dementia in particular are difficult to evaluate in elderly immigrants, because of their different cultural background, the linguistic barrier, and their low level of education. For this reason, we developed a non-verbal test for dementia screening using materials that are cross-culturally applicable. The test measures two cognitive domains that are known to be affected early in the dementia process: memory (immediate and delayed recognition) and executive function (mental flexibility, inhibition and divided attention). The test takes approximately 30 minutes to administer. Test materials are presented on paper; test instructions are given by digitally recorded voice samples in the native language of the subject. A digital scoring system was developed to enhance scoring accuracy. The test proved to be effective in discriminating healthy and demented Dutch elderly. Further, it proved to be non-culturally biased in a pilot study among 45 Turkish elderly.
Methods: We are currently investigating six groups of subjects, all with different native languages: Turkish, Moroccan Arabic, Moroccan Berbers, Surinamese Hindu, Sranantongo and Dutch (30 healthy subjects and about five subjects with dementia per group). Dementia was diagnosed by an independent geriatrician. In the elderly controls dementia was excluded in a short interview with the Informant Questionnaire for Cognitive Decline in the Elderly (IQCODE, Jorm, 1989).
An interpreter screened control subjects for eligibility in the study. The test was administered by a neuropsychologist or a geriatrician.
Results: At the IPA congress, the SYMBOL test and the results of this study will be presented.
We hope to show that the SYMBOL test is not culturally biased, and is able to detect dementia in elderly immigrants with little or no education, and that it can be applied in situations in which a language barrier needs to be overcome.
PS01.82
The importance of different factors of excess disability on quality of life in elderly people with dementia
Heidrun Pawlowski1; E Pijpers1; C Wolfs2; F Verhey2
1Maastricht University Medical Center, Maastricht, Netherlands; 2Maastricht University Medical Center, Maastricht, Netherlands
Background: In an ageing population, we face an increasing number of people with multiple physical, mental and social problems who require an integrated multidisciplinary approach to their management. Excess disability is a term which refers to the observation that many older patients with dementia are more functionally impaired than would be expected according to the stage or severity of their disorder. In the management of multi-morbid demented elderly people, it is important to understand the relative effects of coexisting nondementia illnesses on quality of life.
Purpose: To estimate the relative effects of coexisting nondementia illnesses on quality of life in demented elderly people.
Materials and methods: Cross-sectional baseline data were derived from the MEDICIE (Maastricht Evaluation of a Diagnostic Intervention for Cognitively Impaired Elderly) study (Wolfs et al.). This randomised controlled trial focused on a multidisciplinary approach to patients with psychogeriatric problems (i.e. dementia, somatic problems with co-morbid psychiatric disorders) in the Diagnostic Observation Centre for Psychogeriatric Patients (DOC-PG). Our study included 137 patients (35% men) with a mean age of 79 years and MMSE 22. We assessed the severity of cognitive impairment with the Global Deterioration Scale (GDS), depression with the Cornell Scale for depression in Dementia (CSDD), neuropsychiatric symptoms with the Neuropsychiatric Inventory (NPI), and co-morbidity with the Cumulative Illness Rating Scale (Geriatric) (CIRS(G)). Quality of life was measured with the visual analogue scale (VAS) of the EuroQd measure EQ-5D. We used SPSS for Windows 15.0 for statistical analyses.
Results: Descriptive analyses of patients showed: 25% mild, 62% moderate, and 12% severe cognitive impairment; 30% depression. In co-morbidity, patient's median score was 6 out of 13 categories in the CIRS(G). Co-morbidity categories with a high prevalence were E.N.T. (81%), vascular (80%), musculosceletal (77%), heart (66%), and genitourinary (63%) problems. Univariate analyses revealed a significant correlation between quality of life and severity of cognitive impairment (r – 0.503), depression (r – 0.442), neuropsychiatric symptoms (r – 0.443), and physical co-morbidity (r – 0.424). Musculosceletal problems had the highest significant correlation (r – 0.367) within the physical co-morbidity. Multiple regression analyses showed that only the severity of cognitive impairment, depression and physical co-morbidity (musculosceletal problems) had a significant influence on quality of life. They explained together about 50% of overall quality of life. Severity of cognitive impairment (b – 0.432) had the highest impact on quality of life, followed by depression (b – 0.298) and physical co-morbidity (b – 0.278).
Conclusion: The severity of cognitive impairment had a major influence on quality of life in elderly out-patients with dementia, followed by depression and musculosceletal problems. The management of these patients should not only focus on the treatment of cognitive disorders but also on an optimal treatment of depression and musculosceletal problems.
Reference
Wolfs, C. A. et al.: Economic evaluation of an integrated diagnostic approach for psychogeriatric patients: results of a randomized controlled trial. Arch Gen Psychiatry. 2009 Mar;66(3):313–23.
PS01.83
Ready . . . set . . . count! Prevalence of elder abuse in a hospitalized geriatric psychiatry population
L Pisani; Kevin Lawless; A Lyle; C North
Alberta Hospital Edmonton, Edmonton, AB, Canada
The prevention of elder abuse is increasingly important as current estimates show the world's population of seniors over 65 will triple between 2008 and 2050 and their proportion of the population will increase from 7.7 percent to 16.5 percent (US Census Bureau, 2008). As seniors age there is an increase in the rate at which they are diagnosed with a dementia and co morbid psychiatric disorders, reaching nearly 50 per cent of people over 85 (American Association for Geriatric Psychiatry, 2004,¶ 20). Individuals with dementia and psychiatric disorders are also more likely to be victims of elder abuse (Patterson & Ploeg, 2007). According to the World Health Organization (WHO, 2002), the health sector should take a lead role in dealing with elder abuse and the public health approach of primary, secondary and tertiary prevention is recommended. Seniors admitted to Alberta Hospital Edmonton have many of the risk factors for elder abuse and while we are aware that many cases occur, the actual number and types of abuse are unknown. To reach our goal of increased involvement in the elder abuse response, an education program for interdisciplinary staff was implemented and a tool was designed to capture prevalence information of known abuse cases, which are activities of primary and secondary prevention. Extensive research on the current knowledge about elder abuse including multiple system responses was conducted to prepare for the education sessions. Set education sessions were attended by all staff on two units to share the research findings and introduce a data collection tool to be used at multidisciplinary conferences. This collection tool counts the types of abuse reported at admission and at discharge as well as identifying if the patient was the victim or the perpetrator of the elder abuse. An interdisciplinary confidence level was determined and documented at the time of discharge. Staff welcomed the education sessions with 98 percent reporting that the information was new to them. The multidisciplinary team piloted the data collection form on June 13, 2008, World Elder Abuse Awareness Day. Prevalence studies show the rate of elder abuse in the general population to be 4–6% with the rate of abuse rising in dependent populations to 25%. Data collected from Alberta Hospital Edmonton will be presented. Given the high prevalence of elder abuse within this hospitalized population, elder abuse education should be a standard part of geriatric mental health education. Increased involvement in the elder abuse response was achieved through staff awareness education and a knowledge of the prevalence of types of abuse treated. This information will provide the base line data needed to address elder abuse interventions which are activities of tertiary prevention.
PS01.84
Pressure points: The relationship between geriatric medicine and geriatric psychiatry
Colin Powell
University of Calgary, Calgary, AB, Canada
This paper will review the differences and similarities between these two related yet distinct clinical specialties. We have common challenges clinically and administratively. We often see the same patients. We employ common clinical methods and techniques with comparable clinical objectives. We often seem to face the same barriers and obstacles. We share the same difficulties in recruitment.
Specifically, the paper will analyze how we recognize and remedy: organicity, chronicity, frailty and co-morbidity. It will acknowledge and explore our relationship with our parent disciplines of Internal Medicine and Psychiatry and also our interdependence with colleagues in Family Medicine, Nursing, the Rehabilitation Therapies, Psychology, Social Work and Pharmacy.
Among others, we shall examine the ‘difficult spots’ of competence assessments, acceptance of each specialty's expertise and recommendations, dementia—whose patients?
The work is based on establishing, nurturing and maturing geriatric and geropsychiatry services in Canada (three sites) and the UK (two sites) in the past 40 years.
PS01.85
Are there specific psychological and behavioural symptoms of depression in dementia patients?
Annie Prado-Jean1; P Thomas2; P Nubukpo1; L Bernard-Bourzeix1; N Dechamps1; T Dantoine1; P Couratier1; J Clement1
1Memory Research and Resource of Limousin Center, Limoges, France; 2Centre de Psychiatrie du Sujet Agé, Limoges, France
Background: Psychological and behavioural symptoms in dementia (BPSD) are very frequent, so that 95% of patients have at least one. A third of persons with dementia have depressive symptoms, and concomitant BPSD are very frequent.
Objective: The study aimed to characterize these psychological and behavioural manifestations of depression in patients with dementia.
Methods: We recruited 331 patients with dementia from several nursing homes of Limousin-France. The depression was diagnosed by the Cornell Scale for depression in dementia (CSDD) with a cut-off of 7, and the BPSD were assessed using Neuropsychiatric inventory (NPI).
Results: Of 331 individuals with dementia, 42.9% (n = 142) had depression and 75.8% (n = 251) had BPSD. All BPSD were significantly (p<0.0001) more present in depressed patients. But we did not have significantly difference for sex and age. The most common NPI symptoms in depressed patients other than depression were agitation (43.7%), anxiety (42.9%), apathy (41.5%) and irritability (40.8%). Four NPI-based factors were indentified (60.8% of the common variance): environmental factor (irritability, disinhibition, agitation), positive factors (elation, hallucination, delirium), emotional factor (anxiety, apathy, appetite disturbance) and circadian factor (aberrant motor behavior, sleep disturbance). The depression in dementia patients was significantly associated with environmental, positive and emotional factors.
Conclusion: BPSD are a common and major problem. Although they have previously been considered isolated symptoms, it is important to assess co-morbidity with depression in order to have better therapeutic attitudes.
PS01.86
A training program for people with dementia and their family caregivers: A randomized controlled trial
Anna-Eva Prick1; J De Lange2; E Scherder1; A Pot1
1Vrije Universiteit, Amsterdam, Netherlands; 2Netherlands Institute of Mental Health and Addiction, Utrecht, Netherlands
Introduction: People with dementia and their caregivers can suffer a lot from dementia. Providing care to people with dementia is a heavy responsibility which can affect the health and normal lives of family caregivers. There is no cure for dementia, but prevention and treatment focused on behaviour problems that may result from the dementia and the care situation is feasible. A recent review shows that combined interventions both for dementia patients as for their caregivers are effective to diminish depressive symptoms. One combined intervention is developed by Linda Teri and her colleagues (2003). People with dementia together with their caregivers received an exercise program. The caregivers were also trained in behaviour management techniques to deal with behaviour disturbances. People with dementia who participated in the intervention program performed significantly better on measures of physical function and measures of affective status compared to the care as usual group. For our study we translated and adapted this intervention program to the Dutch situation and at the moment we investigate whether it is feasible and effective for both people with dementia and their caregivers.
Methods and materials: The patient-caregiver dyads (N = 160) are randomly assigned to the training program or care-as-usual with attention. The duration of the exercise training is three months. Measurements take place at baseline, at the end of the training program after 3 months and at 6 and 12-months after baseline. The intervention effect is measured by trained interviewers. In comparison to the effectiveness study of Teri, we added some measures. Next to the Cornell Depression Scale and the Hamilton Depression Rating Scale, instruments to measure physical and cognitive functioning are being used. In addition, we study the effects of the integrated treatment program on the mood and cortisol level of the caregivers. Analyses will be performed using generalized estimating equations for linear, logistic, and Poisson regression.
Results and discussion: At the moment, the pilot study takes place. The results of the pilot will be presented and discussed at the congress.
PS01.87
Determining the usefulness of brief cognitive screening tools in early detection of dementia: A retrospective chart review
Christopher Prince; P Parenteau; M Cosentino; C Carter; K Schryburt-Brown; P Prince
ROHCG/BMHC, Brockville, ON, Canada
As awareness and understanding of dementia grows, patients are referred earlier in the disease process and diagnostic reliability becomes an increasingly important issue. The Brockville Geriatric Mental Health Community Team (GMHCT) utilizes three brief cognitive screening tests, such as the Mini Mental State Examination (MMSE), the Montreal Cognitive Assessment (MoCA), and Kingston Standardized Cognitive Assessment – Revised (KSCA-R) to assess cognition. The present study was proposed to identify which test provided the best results in sensitivity, specificity, and accuracy to detect early dementia.
This poster presents findings of a retrospective review of 40 charts of individuals diagnosed with progressive dementia (e.g., Alzheimer's disease) confirmed with neuroimaging, neuropsychological, and behavioural data (e.g., checklist of behaviours associated with dementia). Demographic data for the 40 cases are presented. MMSE, MoCA, and KSCA-R scores are compared for sensitivity and specificity using recommended cut-off scores for each test (e.g., 26 and below for the MoCA). Direct comparisons between the three tests using Pearson r correlations are also presented. Suggestions are offered for the use of brief screening tools in the early detection of dementia in community dwelling elderly population.
PS01.88
Organizational model “liaison-attachment” for revealing among elderly somatic patients in general hospital the persons with co-morbid mental disorders and their treatment by psychiatrists together with internists
Vladimir Prokudin1; Y Boyko2
1Russian State Medical University, Moscow, Russia; 2Moscow Medical Academy for Postgraduate Education, Moscow, Russia
During the last 10 years the psychotherapeutic/psychiatric department was organized in a large Moscow general hospital N 36 (1700 beds). Were revealing 18427 somatic patients with co-morbid mental disorders (6,7% from total quantity of hospitalized persons for 10 years). Distribution on age: 18–19 1,6%, 20–39 20,2%, 40–59 32,8%, 60 years and more 45,4%, or 8374 elderly patients). Clinical analysis of these 8374 persons had shown: 2/3 with neuritic, somatoform, psychosomatic disorders, 1/3 with organic psychosis, alcohol deliriums and different levels of dementia. In treatment such patients were using small doses of atypical neuroleptics, antidepressants, anxiolytics with combination psychotherapy and psychological correction. Organization model “liaison-attachment” had shown itself as optimal for somatic patients (especially for elderly ones) with comorbid mental disorders because their treatment is carried out in the same place (in general hospital but not in mental hospital) in very convenient conditions without any stigmatization and discrimination. All of this created evident improvement in quality of life of elderly patients.
PS01.89
Delivering service to older adults with mental health problems living in the community: Creating a path to prevention
Andrée-Anne Provençal1; A Regenstreif2
1Université du Québec à Montréal, Montréal, QC, Canada; 2CSSS Cavendish, Montréal, QC, Canada
Older adults with mental health problems suffer from the double stigma of being older adults and having mental health problems. Stigma is only one reason why this population underutilizes mental health services. Other reasons for not accessing mental health services include denial, social isolation, lack of information, inadequate evaluations, fragmented or non-existent services (Dallaire et al. 2003). It is estimated that 50% of the population of older adults with mental health problems living in the community do not receive services appropriate for their needs (Statistics Canada, 2003).
In 2004–2005, 22.3% of the Centre de Santé et Services Sociaux (CSSS) Cavendish's population who received mental health services were over the age of 65 years. This is higher than the 16.6% found on the island of Montreal where the CSSS is located (Benigeri, 2007). This elevated rate of older adults on the territory was only one contextual reality. With the mental health reform (Plan d'action en santé mentale 2005–2010) which stressed the need for a continuum of care (usually defined within the context of the inter-relation between resources) for the mentally ill, there was the reorganization of services within the CSSS Cavendish resulting in the integration of 2 distinct mental health programs: adults and older adults (which included the Mental Health 60+ specialized program). This movement was a welcomed and timely opportunity towards the much needed development of the Lifespan Continuum of Care Model. Such an approach was necessary as it has already been established and recognized that older adults with mental health problems are a growing population with specific needs. To provide not only a more comprehensive service to our 60 plus population, we started reviewing the needs of adults 21 years plus so that our adult clientele age with a better quality and quantity of life. This Lifespan approach integrates an ecological point of view of aging with a mental illness and offers curative interventions that are also preventive in nature.
In the Winter of 2009, we undertook a needs assessment of people aged 60 and over with mental health problems living in the CSSS Cavendish's catchment area, to better understand our population in order to provide a comprehensive bio-psycho-social response to our adult clientele. This consultation included the participation of internal staff (managers, interdisciplinary practitioners), clients, caregivers and community partners of the CSSS in a needs assessment committee. The needs assessment provided vital information that helped establish priorities and create interventions to be implemented and evaluated. It also offered a unique opportunity to assemble sometimes diverging voices and created partnerships with those targeting the well being of the older adult population suffering from mental health problems and living in the community.
This presentation will provide participants with:
1) A better understanding of the needs of older adults with mental health problems living in the community
2) A better comprehension of the Lifespan Continuum of Care Model
3) Knowledge to address different barriers to service delivery with this specific population
PS01.90
Memory clinics in the Netherlands: Development 1998—2008
Inez Ramakers, S Bouwens, C Wolfs, F Verhey
MUMC, Maastricht, Netherlands
Background: Memory Clinics (MC's) are multidisciplinary teams that are especially involved in early diagnosis, treatment and advice for patients with dementia. In 1998 and 2004, two overviews about MC's in the Netherlands are published. Since 2004, several new MC's have started. Besides that, there are several other settings in the Netherlands that are not operational as a ‘MC’, but share the primary aims of early diagnosis of dementia. In order to attain more insight in the current situation of health care facilities about the early diagnosis of dementia in the Netherlands, it is important to update the survey. The aim of this study was to determine the number, characteristics and working methods of MC's and comparable settings in the Netherlands in 2008, and to investigate the changes since the surveys in 1998 and 2004.
Methods: A survey with questions about the organisation, number and nature of referrals, diagnostic workup and working methods of the MC was sent to all operational MC's and comparable settings in the Netherlands. Data from the survey in 2008 will be compared to the data of previous surveys (2004 and 1998).
Results: The data of 2008 are currently being collected, but will be presented at the IPA congress. Results from previous surveys showed that MC's in the Netherlands had had a strong development from 1998 to 2004. The number of operational settings was increased from 12 in 1998 to 40 in 2004, and the settings were more equally distributed with respect to the topographical location in the country. While dementia was the most common syndromal diagnosis, an increasing number of subjects with milder memory problems visited MC's. The total capacity of all settings showed a strong increase since 1998. Given that the incidence of dementia in the Netherlands is about 22.500 patients per year, less than 5% of the new demented patients were seen at a MC in 1998, compared to 22% in 2004. We expect that this number will increase again for the situation of 2008.
Discussion: The today's functioning of MC's in the Netherlands, and their current place in the regular care will be discussed. In addition, the development since the surveys in 1998 and 2004, and their implications will be described. In addition, some recommendations will be given.
PS01.91
Care mapping: A possible method for development of dementia care?
Anne Marie Rokstad1; S Vatne2
1Ullevaal University Hospital, Oslo, Norway; 2Molde University College, Molde, Norway
Background: Dementia Care Mapping (DCM) was developed in the UK in the early 1990s and is used as a method to evaluate and develop dementia care in several countries. In this study DCM was introduced in a Norwegian nursing home.
Objective: The objective of the study was to gather information of how DCM influenced the development of dementia care in a nursing home unit, especially focusing on how the method initiated reflections in the nursing staff and how this affected their practise.
Design and Method: The study had a descriptive design and the main findings were gathered in qualitative focus group interviews with staff members directly involved in the DCM-mapping and feedback process. The leader of the unit was interviewed in the end. The interviews were taped and transcribed. In the data analysis the total data material initially was read to gain an overview and to identify main themes in the text material. Then the text was coded in units of meaning based on these main themes and compared with background data from the DCM-mappings.
Results: Based on the DCM feedback, the nursing staff described increased consciousness, self-reflection and sheered reflection. They describe how feedback confirmed their work and that they got an experience of worth and acknowledgment. Examples of good care practice pointed out in the feedback sessions, increased the staffs’ security in choosing actions in challenging situations and sensitivity to patients needs. As a consequence, the need for time and place for the staff to reflect on their own practise was revealed.
Conclusion: This study illustrates that DCM can be an useful method in developing dementia care, by consciousness-raising and reflection on the nursing staffs own practise. However, meeting arenas for the staff reflection about challenging situation is a prerequisite.
PS01.92
Caring for people with dementia: It's really time to do something now!
Karim Saad; P Smith; M Rochfort
NHS West Midlands, Birmingham, United Kingdom
The only “Lord Darzi” Clinical Pathway Group for Dementia in England details the challenges for service provision faced by our increasing longevity and the demographic profile in the West Midlands. This includes a regional increase in prevalence of 38% over the next 13 years and 154% over the next 43 years. Young Onset Dementia is thought to be three times more prevalent in the West Midlands Asian population.
The consequences of this are not only a massive projected rise in prevalence of Dementia but many of those with Dementia will also develop or have other co-morbidities and thus require access to very structured coordinated services. At the same time we expect a sharp shortfall in the numbers of intimate carers for this group of people.
Currently there is no single overarching ‘Dementia’ service. Current service provision spans primary care, community care, social services, the acute sector, Voluntary, Charity and Independent sectors. This leads to many key and unnecessary issues for people with Dementia and their carers. These issues include lack of access to services, lack of continuity within and between a range of services and service providers, inconsistencies between funding sources during the disease journey and lack of advanced care planning. A noticeable absence of any advanced care planning is evident for end of life care for people with Dementia. It is particularly important to start such decision-making processes while people with Dementia have capacity. In essence this is a reactive focus to care which leads to crisis situations which could be prevented, and which often result in inappropriate use of unscheduled care.
Based on this we set a vision for future dementia services and eight standards we might expect. Those include a strong emphasis on prevention, including public education campaigns, school education, and alcohol harm reduction strategies.
For the first time a regional dementia pathway is outlined as a reference guide for developing services. This includes two new posts to improve pathway navigation.
We make a number of measurable Recommendations to develop services for the next decade and metrics to monitor progress.
We suggest that health economies in England need to jointly plan and commission an overarching dementia clinical pathway with social care and the ‘third’ sector in order to create dementia services fit for the 21st century. This model may be of benefit to service planners in other settings. It's really time to do something now!
PS01.93
Homicide, psychopathy and aging
Tuula Saarela1; H Putkonen2; G Weizmann-Henelius2; E Repo- Tiihonen3; N Lindberg4; M Eronen2; H Hakkanen-Nyholm5
1Helsinki City Health Centre, Helsinki, Finland; 2Vanha Vaasa Hospital, Vaasa, Finland; 3Niuvanniemi Hospital, Kuopio, Finland; 4Helsinki University Hospital, Helsinki, Finland; 5Helsinki University, Dept. of Psychology, Helsinki, Finland
The aim of this study was to compare elderly homicide offenders with a younger control group with special emphasis on psychopathy as measured by the PCL-R (Psychopathy Checklist-Revised) which is a 20-item rating scale based on a semi-structured interview and a review of collateral information. The nationwide registered-based case-control study included all homicide offenders aged 60 or older having been assigned to forensic psychiatric examination in Finland 1995–2004. They were compared with a gender matched group of younger offenders. The assessed variables were PCL-R scores, psychosocial history, index offence and psychiatric variables.
The results showed that the offenders over 60 years of age were diagnosed less often than the younger ones with drug dependence and personality disorders and more often with dementia and physical illnesses. The mean PCL-R scores were lower in the older group, the difference being significant.
We conclude that even though there seems to be an alcohol abusing subgroup of older offenders similar to the younger ones, there also exists a subgroup of older offenders quite unlike the typical homicide offenders. Both subgroups should be noted in developing services for the elderly.
PS01.95
Coping with illness and aging: An introduction to group psychotherapy with older adults
Ken Schwartz
Baycrest, Toronto, ON, Canada
The overall cost-efficacy and effectiveness of both outpatient (Burlingame et al., 2004) and inpatient dynamic, interactional and relational group psychotherapy (Kosters et al., 2006) has been demonstrated. Group psychotherapy has been shown to be as effective as individual psychotherapy in meta-analytic reviews (Burlingame et al., 2004). More clinical work and research has been suggested to clarify and interpret the research findings with respect to the elderly (Burlingame et al., 2004). Unfortunately, group psychotherapy even in these challenging economic conditions is still considered an after-thought, especially when it comes to psychotherapy with older adults. In this presentation, clinical examples will be described based on the presenter's experience in developing and employing an integrated group psychotherapy model over the past thirteen years of conducting groups in both a Psychiatric Day Hospital for Depressed Elderly (Schwartz, 2004) and in various nursing home settings with individuals with mild degrees of cognitive impairment or dementia (Schwartz, 2007). The principles of group psychotherapy, themes and challenges as they especially apply to these populations will be illustrated. The success of the groups in improving the self-esteem, sense of community and quality of life for group members will be described.
Reference
Burlingame, G. M., MacKenzie, K. R., & Strauss, B.: “Small-Group Treatment: Evidence For Effectiveness and Mechanisms Of Change”, in M. J. Lambert (Ed.), Bergin and Garfield's Handbook of Psychotherapy and Behavioral Change (5th ed.). New York: Wiley, 2004.
Kosters, M., Burlingame, G. M., Nachtigall, C., & Strauss, B.: “A Meta-Analytic Review of the Effectiveness of Inpatient Group Psychotherapy” Group Dynamics: Theory, Research, and Practice, 2006.
Schwartz, K. M.: “Concurrent Group and Individual Psychotherapy in a Psychiatric Day Hospital for Depressed Elderly” International Journal of Group Psychotherapy. 2004; 54(27):177–201.
Schwartz, K. M.: “Remembering the Forgotten: Psychotherapy Groups for the Nursing Home Resident” International Journal of Group Psychotherapy. 2007; 57(4):497–514.
PS01.96
Citalopram versus other antidepressants for late-life depression: A systematic review and meta-analysis
Dallas Seitz1; D Conn2; S Gill3
1Baycrest Centre, Toronto, ON, Canada; 2Baycrest Centre, Toronto, ON, Canada; 3Queen's University, Kingston, ON, Canada
Many treatment guidelines list citalopram as a first-line treatment late-life depression (LLD) and citalopram is frequently used for this indication. Little is known of efficacy and tolerability of citalopram when compared to other antidepressants for LLD.
Methods: A search of MEDLINE, EMBASE and the Cochrane Library was performed to identify studies comparing citalopram to any other antidepressants for LLD (major depressive disorder in those age ≥ 65 years). Both randomized and non-randomized studies were included. Efficacy was evaluated by depression remission rates as measured on standardized depression rating scales. Medication tolerability was evaluated through rates of trial withdrawals due to adverse events. Meta-analysis was undertaken to determine the relative risks of efficacy and tolerability outcomes for citalopram compared to other antidepressants.
Results: Seven studies comparing citalopram to other antidepressants for LLD were identified. These studies included a total of 647 participants treated with citalopram (mean age = 73.4 years, 68% female) and 641 participants treated with other antidepressants (mean age = 74.1 years, 73% female). Four studies compared citalopram to tricylic antidepressants (1 with desipramine, 1 with nortriptyline, and 2 with amitriptyline), and 3 studies compared citalopram to other antidepressants (1 study each with venlafaxine, mianserin, and reboxetine). The efficacy and tolerability of citalopram was similar to other antidepressants in the individual studies. The relative risk of depression remission was similar for citalopram when compared to other antidepressants [relative risk (RR) = 0.92; 95% confidence interval (CI): 0.82–1.03] in meta-analysis of the four studies reporting this outcome. A total of 5 studies reported information on trial withdrawals with no significant difference in the relative risk of trial withdrawal due to adverse effects for citalopram when compared to other antidepressants [RR = 0.75; 95% CI: 0.55–1.03].
Conclusions: There are few high-quality trials directly comparing citalopram to other antidepressants for LLD. There was no statistically significant difference in efficacy and tolerability between citalopram and other antidepressants although there were trends towards decreased efficacy and increased tolerability for citalopram when compared to other antidepressants. Further large-scale studies comparing citalopram to other suitable first-line alternatives are needed before concluding that citalopram is the best initial treatment for LLD.
PS01.97
Comparison of elderly suicide rates among migrants in England and Wales with their country of origin
Ajit Shah
West London Mental Health NHS Trust, Middlesex, United Kingdom
Background: The black and minority ethnic (BME) elderly population size in England and Wales has progressively increased over the last three decades. Only two studies, both well over a decade old, have compared suicide rates in BME groups in England and Wales with those in their country of origin.
Methods: A study comparing suicide rates among elderly migrants in England and Wales and in their country of origin using the latest available mortality data from the Office of National Statistics and the World Health Organization was conducted.
Results: There were wide variations in standardised mortality ratios for elderly suicides among migrants from different countries compared with those born in England and Wales and in their country of origin. There was convergence towards elderly suicide rates for England and Wales in some migrant groups in males in the age-bands 65–74 years and 75+ years, and in females in the age-band 75+ years. However, males aged 75+ years from most migrant groups had higher rates than those born in England and Wales.
Conclusion: A more detailed analysis of suicide of older people from migrant groups is required to determine vulnerability and protective influences. Factors requiring examination include: reasons for migration, the process of migration, the degree of acculturation and assimilation, duration in England and Wales, the prevalence of mental illness, access to old age psychiatry services, life expectancy, family structure and household size, and socio-economic status.
PS01.98
Characteristics of eating and swallowing problems in DLB patients
Shunichiro Shinagawa1; H Adachi2; Y Toyota3; T Mori3; R Fukuhara3; M Ikeda4
1The Jikei University School of Medicine, Tokyo, Japan; 2Osaka University Health Care Center, Osaka, Japan; 3Ehime University Graduate School of Medicine, Ehime, Japan; 4Faculty of Medical and Pharmaceutical Sciences, Kumamoto University, Kumamoto, Japan
Background: Eating problems occur frequently in demented patients, and almost half of all patients with Parkinson's disease have such problems. Therefore, it has been considered that eating problems are common in dementia with lewy Bodies (DLB). However, few systematic studies have investigated on eating problems in DLB patients. The aim of this study was to clarify the frequency and characteristics of eating problems in patients with DLB.
Method: We examined 29 consecutive patients with DLB and 33 with Alzheimer's disease (AD) in terms of age, sex, education, mini-mental state examination (MMSE), clinical dementia rating (CDR), neuropsychiatric inventory (NPI), Unified Parkinson disease Rating Scale (UPDRS), fluctuations in cognition, and usage of neuroleptic drugs/antiparkinsonian drugs. We employed a comprehensive questionnaire comprising 40 items and compared the scores between the two groups.
Results: DLB patients showed significantly higher scores than AD patients for “difficulty in swallowing foods”, “difficulty in swallowing liquids”, “coughing or choking when swallowing”, “taking a long time to swallow”, “suffering from sputum”, “loss of appetite”, “need watching or help”, and “constipation”. Only the UPDRS score significantly affected the scores for “difficulty in swallowing foods”, “taking a long time to swallow” and “needs watching or help” score, whereas only the NPI score affected the score for “loss of appetite”. The scores for UPDRS, NPI and CDR significantly affected the scores for “difficulty in swallowing liquids”. No significant independent variables affected the scores for “coughing or choking when swallowing”, “suffering from sputum” and “constipation”.
Conclusion: Although DLB patients show many eating problems, the causes of each problem vary, and the severity of dementia or Parkinsonism is not the only determinant.
PS01.99
Maintenance electroconvulsive therapy in the treatment of Parkinson's disease
Robert Shulman
Rush University Medical Center, Skokie, IL, United States
Parkinson's disease, a neurodegenerative disorder affects over 1% of the population over 60 years of age. Despite many new pharmacologic agents, Parkinson's disease remains a progressively deteriorating illness often complicated by psychiatric morbidity including depression, anxiety and dementia. Non-pharmacologic treatments have been employed in Parkinson's disease including pallidotomy and most recently deep brain stimulation.
Electroconvulsive therapy (ECT) was noted to provide benefit for Parkinson's disease as early as 1947. There have been numerous reports on this subject published in the literature in the intervening years, predominantly regarding Parkinson's disease with co-morbid psychiatric illness, usually depression. There have been few reports of ECT specifically for the movement disorder symptoms of Parkinson's disease and still fewer articles reporting on the use of maintenance ECT in this condition.
The author reported one such case, published in Geriatrics November 2003. We now present a review of the worldwide literature through a MEDLINE search on the use of maintenance ECT in Parkinson's disease. Parameters of study include whether the primary purpose of ECT was for the movement disorder of Parkinson's disease or for psychiatric comorbidity. Each case was examined for frequency and duration of treatment and outcome. Secondary measures include an assessment of function, whether concomitant medications could be reduced, an assessment of side effects from ECT versus beneficial diminishing of medication side effects if there was a reduction of pharmacologic agents, and the global impression of each report's author on the effects of maintenance ECT in Parkinson's disease.
PS01.100
Increasing probability of success in Phase 3 trials of putative disease-modifying treatments for Alzheimer's disease
Eric Siemers
Eli Lilly and Company, Indianapolis, IN, United States
Background: Phase 3 trials for putative disease-modifying treatments for Alzheimer's disease (AD) require large number of patients treated for many months. Clear criteria to increase the probability of success in such trials based on Phase 1 and 2 clinical trial data do not exist.
Methods: A variety of biomarkers including plasma amyloid-β (Aβ), cerebrospinal fluid (CSF) Aβ, CSF tau, and amyloid imaging using [123I] 6-iodo-2-(4’-dimethylamino)phenyl-imidazo[1,2-a]pyridine (IMPY) single photon emission computed tomography (SPECT) scans were used in six Phase 1 and 2 studies of a gamma secretase inhibitor (semagacestat) and two Phase 1 and 2 studies of a monoclonal antibody binding to Aβ (solanezumab). These biomarkers were assessed in addition to clinical cognitive scores using the Alzheimer's Disease Assessment Scale-cognition (ADAS-cog). Phase 2 studies in mild-moderate AD patients included treatment periods of 14 and 12 weeks for semagacestat and solanezumab, respectively. Samples sizes were less than 40 subjects per treatment arm for all studies.
Results: Robust changes in plasma Aβ were demonstrated for both semagacestat and solanezumab in Phase 1 and 2 studies. Changes in CSF Aβ were initially obscured by sub-optimal timing of lumbar punctures in studies of semagacestat; however, with serial CSF sampling, changes in CSF Aβ were demonstrated. CSF Aβ changed after single or multiple doses of solanezumab. CSF tau was unchanged in the Phase 2 trials, although numeric trends for reduction were present for semagacestat. Amyloid plaque load as assessed with SPECT scans did not change in the solanezumab Phase 2 study. ADAS-cog scores were unchanged in Phase 2 trials of both semagacestat and solanezumab.
Conclusions: Changes in plasma and CSF Aβ can be demonstrated in Phase 1 and 2 studies of treatments targeting the Aβ peptide. Phase 2 studies lasting 12 to 14 weeks may be too short to demonstrate changes in clinical cognitive scores or CSF tau. Results from the ongoing Phase 3 trials of semagacestat and solanezumab will ultimately determine the predictive value of these Phase 2 biomarker changes.
PS01.102
Placebo-controlled trial of quetiapine for sleep disturbance in dementia
C Singer; Francine Nanda
University of Vermont College of Medicine, Burlington, VT, United States
Introduction: Sleep disturbance is common in dementia and very stressful for caregivers. Since quetiapine is commonly used to treat neuropsychiatric symptoms, including sleep disturbance, in Alzheimer's disease (AD), we are systematically investigating its sleep-promoting effects in this population.
Methods: This is an on-going, single-blind placebo-controlled trial. Thirteen patients with either AD or non-AD dementia were treated with a one-week placebo run-in, followed by 8 weeks of quetiapine, dosed through a flexible dose-titration schedule, increasing the dose by 25 mg each week to a maximum dose of 200 mg per night. Dose titration was based on clinical response and drug tolerability. Wrist-actigraph scored sleep was the primary outcome measure.
Results: The average doses across weeks ranged from 25 mg at week 1 to 125.00 mg. The maximum dose achieved in the flexible titration ranged from 25 mg to 200 mg. Nocturnal total sleep time (NTST) between 20:00 and 08:00 (in minutes by wrist-actigraph) increased during quetiapine treatment weeks. At week 8 (mean dose 125.00 mg qhs; range 50–200), there was an average increase of 83.657 minutes per night compared to placebo baseline (p = 0.002). Time awake after sleep onset (WASO) decreased 35.304 minutes compared to placebo baseline (p = 0.012) at week 8. The total nighttime sleep data are shown in the table below.
Table: Nighttime sleep
Week of Mean dose N Mean NTST Mean Difference from baseline SE p value
Treatment (min.) (min.)
Week 0 0 mg 12 389.983 - - _
Week 1 25 mg 12 425.905 -35.923* 12.514 .005
Week 2 45.83 mg 12 414.550 -24.567 16.138 .132
Week 3 68.18 mg 11 438.032 -48.049* 18.438 .012
Week 4 86.36 mg 11 438.937 -48.954* 19.754 .018
Week 5 100.00 mg 11 439.795 -49.813* 20.576 .022
Week 6 117.50 mg 11 434.882 -44.899* 21.103 .045
Week 7 122.50 mg 10 447.001 -57.018* 21.784 .017
Week 8 125.00 mg 8 473.640 -83.657* 23.059 .002
*: p-value less than .05
Three serious adverse events occurred; injurious fall in one patient that was considered to be possibly-drug related, a pre-existing partial bowel obstruction non drug-related as the patient was on placebo and mental confusion associated with hypokalemia experienced by a patient who had a pre-existing renal failure (50 mg), not drug-related. Non serious adverse events were also reported including non-injurious falls, nausea, vomiting, and drowsiness.
Conclusion: Quetiapine increased nighttime sleep relative to placebo baseline in this initial cohort of an on-going study. The > 80 minute increase in total sleep time at night and the > 35 minute reduction in WASO at the end of the study are very large treatment effect sizes in this population. Quetiapine appears to be well tolerated with a slow, conservative titration schedule. A larger clinical trial is warranted.
Support: This study was supported by an investigator-initiated research grant provided by AstraZeneca to Dr. Singer.
PS01.103
Dilemmas in consent signing for cognitively impaired subjects: An international perspective
Gary Sinoff
Carmel Medical Center, Haifa, Israel
The population of the world today is aging at a rate which is alarming to all who study the elderly. With the arrival of the “baby boomers” in the present millennium, the elderly are reaching percentages unthought-of in the past with many Western World countries reporting 20% or more of their population over the age of 65. A concomitant problem to the aging population is the increase in the number of elderly suffering from cognitive decline, and especially from dementia. The prevalence for dementia increases with age from 10–15% at 65 reaching 40% in those over the age of 85. When one realizes that the elderly also have a disproportional rate of admission to hospital, then one can understand that a high percentage of geriatric in-patients are suffering from dementia. Prior to any study on human subjects, investigators need to receive permission from the Internal Review Board (IRB) of each individual hospital. These IRBs are in charge of ensuring that the study will fulfill the ethical codes set by local and international standard guidelines. The basic concept of consent to participate in a study is that the subject is able to fulfill the criteria of decision-making process: understanding, appreciation, reasoning and expressing a choice. It is obvious that the demented are incapable of this decision-making process and therefore will need the “guidance” of others. The process of legal guardianship is usually a long drawn-out process and unfortunately most demented elderly do not have legal guardianship, resulting in difficulties to include this population in studies which are for their and their families’ benefit.
There is an urgent need to study elderly in-patients in epidemiological and longitudinal studies and to understand factors predicting functional decline in this vulnerable population, especially if demented. This ethical dilemma was raised in a letter sent out by this author to clinical researchers in the field of dementia study throughout the world, presenting them with the problem in a prospective clinical study of geriatric in-patients which is to include the study of demented persons as well. The replies from the researchers showed that each country, (England, Canada, America, Ireland, Australia, Nigeria, Israel and Hong-Kong) is grappling with this problem. This is not a study but an attempt to raise the issue to a level where clinical researchers may start to study the problem and present some sort of international consensus for epidemiological studies on the demented elderly.
PS01.104
Effect of oxcarbazepine in the treatment of agitation and aggression in severe dementia
Oskar Sommer
Sykehuset Innlandet, Reinsvoll, Norway
Background/Aims: Mood stabilizers valproate and carbamazepine had been investigated as treatment of agitation and aggression in patients with dementia in four and two RCTs respectively. Only one study with carbamazepine showed a statistically significant effect. In lack of better evidence, carbamazepine has been recommended as treatment in this population. We wanted to evaluate the efficacy of oxcarbazepine (OXC) because it is similar to carbamazepine in its chemical structure and the biological effect on receptors, but usually better tolerated than carbamazepine.
Methods: This is an eight week, multicenter, randomized, double-blind, placebo-controlled trial carried out independently from the pharmaceutical industry. Change in agitation and aggression subscores on the Neuropsychiatric Inventory – Nursing Home Version (NPI-NH) was the primary outcome. The secondary outcomes were the change in the caregivers' total burden score (measured by the NPI-NH) and change in the Brief Agitation Rating Scale (BARS).
Results: Out of 168 screened institutionalized patients at 35 sites 103 were randomized to the trial. After eight weeks, no statistically significant differences were found between the two groups for all outcomes. A trend was observed, however, in favor of the OXC group in the reduction of the score on the BARS (p = 0.07). In our trial the profile of adverse events showed that sedation was the main side-effect; it occurred in 25% of the patients.
Conclusion and discussion: Sedation is a side-effect that must be considered as a particular disadvantage for physically and mentally ill patients. Consequently, there was a stronger tendency toward ataxia and falls among this group. In sum, these side-effects may lead to serious concerns when using OXC in this population. The placebo group showed a 36.3% reduction in agitation and aggression score on the NPI-NH compared to 39.0% in the OXC group. Therefore, poor statistical power may be one reason why we could not prove that OXC was efficacious. This and other drug studies had shown that the placebo response in patients with dementia is high, which highlights the importance of psychosocial, environmental, and educational strategies in treating behavioral and psychological symptoms in dementia.
PS01.105
Precipitating factors for falls in patients with dementia on a psychogeriatric ward
Sofie Strandberg2; S Eriksson2; Y Gustafson1; L Lundin-Olsson2
1Geriatric Medicine, Umeå, Sweden; 2Physiotherapy, Umeå, Sweden
Objectives: To identify precipitating factors causing falls among people with dementia on a psychogeriatric ward.
Design: Prospective fall registration study with analysis of the circumstances surrounding each fall event.
Setting: A psychogeriatric ward in a hospital in the North of Sweden.
Participants: 223 inpatients with any type of diagnosed dementia, of whom 91 fell at least once. Of these, 46 were women and 45 were men (mean age 80.3 years, range 60–94).
Measurements: All falls that occurred during a two-year period on a psychogeriatric ward were registered. Circumstances associated with each fall event were analysed by independent reviewers, possible precipitating factors were documented, evaluated and the most likely precipitating and predisposing factors were identified.
Results: A total of 298 falls were registered, 62% were sustained by men. The most likely factor or combination of factors could be ascertained in 247 falls (83%). Falls took place at all hours around the clock and almost half of the falls (44%) occurred during the night shift, between 9 p.m. and 7 a.m. Acute disease or symptoms of disease and/or acute drug side effects were judged to be precipitating factors, alone or in combination with other factors, in three out of four falls.
Conclusion: It is possible to identify many precipitating factors that may contribute to a fall. Falls in people with dementia should be regarded as a symptom of acute disease or as a drug side effect until proven otherwise. Prompt detection of these relevant factors is therefore essential.
PS01.106
Four cases of dementia with Lewy bodies that responded favorably to donepezil hydrochloride
Kazuki Tabata; F Morikawa; J Naoe
Asahikawa Keisenkai Hospital, Asahikawa, Hokkaido, Japan
Introduction: Patients with dementia with Lewy bodies (DLB) are likely to develop complications due to low physical reserve capacity associated with autonomic disorders and have poor prognoses. Herein, we present four patients with probable DLB who responded very favorably to donepezil hydrochloride. Caution was exercised to ensure anonymity and prevent leakage of private information.
Case presentation: Case 1. A 73-year-old woman. In X-2, she developed apathy at the age of 69, and in X, she was admitted at the age of 71. Dementia, Hoehn and Yahr grade I Parkinsonism and active hallucination were confirmed, and MIBG myocardial scintigraphy showed low MIBG accumulation. The patient was diagnosed with probable DLB. Drug therapy-resistant apathy improved with electroshock therapy. In December X, the patient developed complications, and therapy required three months. Once the complications healed, donepezil hydrochloride therapy was started in April X, and hallucination and apathy dissipated. In July X, the patient was discharged first to a healthcare facility and then to her home. At the age of 73, neuropsychological testing showed an MMSE score of 24 points, which was an improvement compared to the time of admission.
Case 2. A 79-year-old man. In X-1, he became forgetful. The patient was diagnosed with Alzheimer's dementia at another hospital; however, due to delirium, he was referred to our hospital in July X at the age of 78. After admission, Hoehn and Yahr grade I Parkinsonism was confirmed, and he reported hallucinations, such as “the room is burning”. MIBG myocardial scintigraphy confirmed low MIBG accumulation. Marked aspiration resulted in aspiration pneumonia soon after admission, which exacerbated to sepsis. The patient's condition transiently worsened, and it took two months to treat complications. During this time, the patient could not communicate, and in terms of ADL, the patient became bedridden. When the complications healed in August X, donepezil hydrochloride was administered, and the patient became able to communicate. With swallowing training, the patient could eat, and with physical rehabilitation, the patient could walk with an aid. His cognitive symptoms also improved, and a neuropsychological test conducted in December X showed an MMSE score of 29 points. In comparison to the time of admission, the results were markedly improved, and the patient no longer required extensive care. At present, the patient is waiting for a space at a group home.
Case 3. An 87-year-old man. In X-3, the patient became forgetful at the age of 84. In X-1, the patient had hallucinations at the age of 86, and cognitive function fluctuated. In September X, the patient visited the hospital at the age of 87. Dementia, Hoehn and Yahr grade III-IV Parkinsonism and hallucination were observed, and MIBG myocardial scintigraphy confirmed low MIGB accumulation. The patient was diagnosed with probable DLB. Parkinsonism exacerbated made the patient unable to eat, and since the patient experienced daily episodes of confusion, he was admitted in October X at the age of 87. Donepezil hydrochloride administration improved his confusion, and physical rehabilitation slightly improved Parkinsonism. Although the results of neuropsychological tests did not improve, the level of required care decreased, and at present (X+1), we are in the process of finding a placement for the patient.
Case 4. An 80-year-old man. In X, the patient developed delirium after undergoing surgery for bladder cancer at the age of 80, and in November X, the patient was admitted to the hospital. After admission, cognitive symptoms, fluctuating cognitive function, Hoehn and Yahr grade II Parkinsonism and hallucination were confirmed, and the patient was diagnosed with probable DLB. Starting in December X, donepezil hydrochloride was administered, and fluctuating cognitive function and hallucination improved. Neuropsychological testing showed that his MMSE scores had improved from 24 to 27 points, and the patient was subsequently discharged.
Conclusions: Four DLB patients who responded to donepezil hydrochloride were reported. In Cases 1 and 2, the behavioral and psychological symptoms of dementia (BPSD) associated with DLB improved, and in Cases 3 and 4, cognitive function fluctuation associated with DLB improved. DLB patients are likely to develop complications due to low physical reserve capacity, and it is generally considered that prognosis is poor when Parkinsonism exacerbates. Although the cases have been followed for only a short period of time, appropriate therapeutic interventions may improve DLB symptoms.
PS01.107
A quick test of cognitive speed as a screening tool for elderly Japanese patients with early stage of dementia: A validation study
Fumi Takahashi1; S Awata2; M Yamashita1; S Fukushima1; K Takamatsu1; S Fujiwara1; E Wiig3; N Nielsen4; L Minthon5
1Sendai City Hospital, Sendai, Japan; 2Tokyo Metropolitan Institute of Gerontology, Tokyo, Japan; 3Knowledge Research Institute, Arlington, TX, United States; 4Hvidovre Hospital, Copenhagen, Denmark; 5University Hospital MAS, Malmø and Lund University, Malmø, Sweden
Background: A Quick Test of Cognitive Speed (AQT) Color-Form Naming consists of three sets of stimuli (colors, forms, and color-form combinations) and is implicated in integrated part of cognitive functions including perception, naming, selective and divided attention, working memory and set shifting. The clinical outcome of the AQT is measured by time (seconds) it takes to name each stimuli page. It has been validated as a screening tool for patients with early stage of dementia in English, Spanish, Scandinavian, and Greek speaking countries.
Objective: The aim of this study is to evaluate the validity of the AQT as a screening tool for elderly Japanese patients with early stage of dementia.
Methods: A sample of 162 patients with Alzheimer's disease (AD), 64 patients with mild cognitive impairment (MCI), and 25 normal healthy volunteers underwent a set of routine clinical examinations including the AQT, MMSE, COGNISTAT and CDR. Patients with AD met the NINCDS-ADRDA and the DSM-IV criteria. MCI was defined as CDR 0.5 with significant decline in single or multiple cognitive domain without apparent impairment in IADL. Normal healthy volunteer was defined as CDR 0.
Results: To evaluate the concurrent validity, all subjects were selected. The AQT color-form naming time significantly correlated with the total scores on the MMSE (P < 0.001), COGNISTAT (P < 0.001), CDR (P < 0.001), and each subscore of the cognitive domains examined in the COGNISTAT (attention, orientation, memory, and judgment: P < 0.05; comprehension, repetition, naming, constructional ability, calculation, and similarities: P < 0.001 To evaluate the discriminate validity, three sex-, age-, and education level-matched groups were selected: 24 patients with AD (CDR 1), 24 patients with MCI (CDR 0.5), and 24 normal healthy volunteers (CDR 0). The AQT color-form naming time was significantly worse in AD and MCI groups compared with control group (AD = MCI>control). The receiver-operating characteristics curve (ROC) analysis revealed that the AQT color-form naming time significantly discriminated patients with AD from normal healthy volunteers (AUC = 0.94, 95%CI = 0.88–1.00, P < 0.001). A cut-off of > 76 yielded the best sensitivity/specificity trade off: sensitivity 0.88 and specificity 0.83. The AQT color-form naming time also significantly discriminated patients with cognitive decline (MCI or AD) from normal healthy volunteers (AUC = 0.90, 95%CI = 0.83–0.97, P < 0.001). A cut-off of > 76 yielded the best sensitivity/specificity trade off: sensitivity 0.83 and specificity 0.83.
Conclusion: Since MCI or CDR 0.5 is suggested a high-risk state for dementia, the present findings indicate that the AQT color-form naming test is a useful screening tool for patients with very early-stage dementia in elderly Japanese population.
PS01.108
Models for day care programs for persons with dementia: The Norwegian dementia plan 2015
Liv Taranrød
Ageing and Health, Norwegian Centre for Research, Education and Service Development, Tønsberg, Norway
Background: In 2007 the Norwegian Ministry of Health and Care presented the Government's Dementia Plan containing strategies as well as specific initiatives for the period until 2015. In this plan day programs and adapted activities were defined as essential and fundamental elements of integrated care services that should be offered to persons with dementia. The Norwegian Centre of Dementia Research was asked to implement and evaluate various models for day programs for persons with dementia during a period of three years.
Aim: To develop models for day programs for people with dementia of good quality that can be established in every Norwegian municipality.
Method: The project is divided into two steps: 1) A survey comprising all Norwegian municipalities to examine how many of them have provide a day care program for persons with dementia, 2) Implementation and evaluation of the various models. In this part 28 small and large municipalities were invited to participate in developing and implementing various day care programs for a 12 months period (“models”). Health care personnel were offered training, including how to use evaluation tools. Patients were assessed by Clinical Dementia Rating Scale (CDR), Neuropsychiatric Inventory (NPI), Brody and Lawton's IADL scale. The family carers’ burden of care was measured by the relatives' Stress Scale (RSS). In addition, management, organisation, content and economy of the models will be evaluated.
Results: The survey showed that 130 of 431 municipalities already had established a day care program, and that 6.5% of persons with dementia living at home were offered this type of services. The implementation started in 2008, 35 different day programs were planed or established in 28 municipalities. 26 affiliated to nursing homes and eight as independent day care centres and in one municipality a day care program was established in the patients' own homes and will be further developed during the project. In all, 140 health and social care personnel participated in the training courses on how to use the standardised assessment tools and evaluation questionnaires. The development project is ongoing and no evaluation results are so far available.
Conclusion: In Norway approximately 30% of the municipalities have specialized day care programs for persons with dementia. A national plan has been set up to develop various models to increase the number of such centres. The implementation of models is ongoing.
PS01.109
Caregivers? sociodemographic characteristics in metropolitan France: Data from 28, 205 contacts
Philippe Thomas1; J Ankri2; S Renaut3
1Esquirol Hospital, Limoges Cedex, France; 2APHP, Paris, France; 3CNAM, Paris, France
A countrywide sample of 28205 persons, representative of French society, older than 15, were recruited by telephone for this study (BVA Institute). The situation of informal and familial caregivers was studied: sociodemographic characteristics of patients and caregivers, pathologies cared.
Results: In the population studied, 2567 informal and familial caregivers were pinpointed, corresponding to 9.13% of the French population: 320 persons cared for an adult, victim of an accident, 233 persons for an adult, crippled since birth. Besides, 1986 persons were caregivers of adults with acquired diseases, corresponding to 7.04% of the French population. caregivers' ages are mainly around 50. Women caregivers are more numerous than men, for all the ages, except for the population over 75: older caregivers are more often male. Caregivers mainly have no or no longer any professional activities. The older the patient, the older the caregiver, and greater the time given for the caring. This study allowed to point out the main pathologies concerned by the informal caregiving. Aging, without other precise specification, is the first cited by the caregivers (24% of cases). Alzheimer's disease is the second disease cited (17%), followed by cecity due to macula disease (15%) and heart insufficiency (14%). This study also pinpointed the hidden caregivers in a western country. Theses caregivers are younger than 20 years, and are usually not taken into account by the social services. This mainly concerned young girls, in charge of patients with eye or heart problems. In a country like France, their number is over 165 000.
Conclusions: This study carried out thanks to a large panel of persons enables us to specify the situation of caregivers in a western country.
PS01.110
Usefulness of the DatScan for the aetiological diagnosis of hallucinations in the elderly
Philippe Thomas1; A Prado-Jean1; J Monteil2; J Clement1
1Esquirol Hospital, Limoges Cedex, France; 2University Hospital, Limoges, France
Hallucinations are an atypical symptomatology in the elderly, and sometimes aetiology is not clear. Severe depression, drug side effects, Lewy body disease (LBD) and psychosis can be responsible with possible overlaps. Treatments of these causes are quite different, so a precise diagnosis is necessary. Brain dopamine metabolism discriminates between psychosis with an increased dopamine activity and LBD with a reduced activity. DatScan was used in this study to obtain precise medical diagnosis of hallucinated old persons over 65.
Methods: The protocol was approved by the regional ethical committee. Forty eight old persons with hallucinations were recruited after their formal acceptation to join: 19 with LBD, 15 Alzheimer's disease, 4 depression, 10 psychosis. A medical assessment including research of depression, drug side effects, parkinsonism and antecedent of fall was performed. Each person had a neuropsychological evaluation. DatScan was realised in the department of nuclear medicine with a semi quantitative measure of the dopamine synthesis in the striatum. A ratio was obtained between striatum and cerebellum fixations. Fifteen patients with Parkinson's disease but without cognitive disorders or hallucinations had a DatScan in order to assess a tremor, and their results were compared with those of Lewy body disease patient.
Results: Twenty-two patients with a LBD have a reduced dopamine synthesis in the striatum. DatScan for all of them shows a lower activity (ratio 1.79 + 0.4) than for depressed patients, with or without cognitive disorders, with Alzheimer's disease or psychosis (ration > 3), even if a parkinsonism due to a side effect of antipsychotic drugs is present. Nevertheless, DatScan does not discriminate between LBD and Parkinson's disease.
Conclusion: DatScan can be useful to diagnose LBD in hallucinated patients and to discriminate this cause from other situations where old persons can be hallucinated.
PS01.111
Does an integrated activity program reduce carer burden and improve function for institutionalized elderly with dementia?
Winnie Ting; M Cheung; S Ng; S Wan; W Chan
Elderly Health Service, Hong Kong, SAR PR China
A 12-session integrated activity program was developed for institutionalized elderly with dementia followed by on-the-job training to the staff in the private residential care homes for the elderly. Program effectiveness and staff perception in implementation were explored.
Objectives: To determine the effects of an integrated activity program on carer burden, daily functioning and behaviour changes of residents living in private residential care homes for the elderly (PRCHE), and to ascertain the capability and perception of PRCHE staff in implementing the program.
Participants: 50 residents aged 65 or above with a diagnosis of mild to moderate stage dementia and MMSE scores ranged between 8 and 22 were recruited from four PRCHEs.
Design: Single blinded randomised controlled study.
Methods: Participants were randomized to the 12-session intervention and control groups. The integrated activity program aimed to provide opportunities for optimal stimulation, social interaction and enjoyment of the participants. It included elements on reality orientation, reminiscence, daily living skills and cognitive stimulation. The program was run by occupational therapists and PRCHE staff, who were taught about the intervention by the OTs, over a period of six weeks. Data were collected at baseline and within 2 weeks after the program. The Chinese version of the Disability for Dementia was used to evaluate performance of daily living. The Cohen Mansfield Agitation Inventory was used to measure the occurrences of observable agitative behaviours. With the use of semi-structured interviews, subjective ratings of carer burden and their perception in organizing and running activities for elderly with dementia were asked.
Results: 48 (96%) residents participated in the study. A significant decrease in subjective ratings of carer burden (mean difference –4.76, 95% CI –8.97 to –0.55) was found in the study group when compared to the control group. No significant difference was found in daily functioning (mean difference –0.02, 95% CI –0.10 to 0.07) and occurrences of behavioural disturbances (mean difference –2.07, 95% CI –6.46 to 2.31). 13% of 31 carers expressed full confidence in running dementia activity program and 26% totally agreed that activity participation would lead to better quality of life of the demented residents. Difficulties in allocating time and human resources, and handling behaviours of the demented elderly during activities were reported by some carers.
Conclusion: The study is still undergoing. Although the impact on the function and behavioural disturbance of demented residents is not clear at this stage, this result suggested that integrated activity program can help to reduce the burden of carers.
PS01.112
Neuropsychiatric morbidity amongst urban and rural elderlies in Northern India: Report from a community based epidemiological study
Sarvada Tiwari; R Tripathi
CSM Medical University, Lucknow, UP, India, Lucknow, India
The epidemiological studies in India in Geriatric Mental Health addressing morbidities, psychosocial, economic and demographic issues show differing results. These differences are because of differing methodologies, case criteria, locations etc. As a result the issue was revisited using a stringent methodology. The study was supported by the Indian Council of Medical Research (ICMR), New Delhi, India, in urban and rural areas of Lucknow—a North Indian City. The urban study has been completed and the rural is in progress.
Objective: To study and compare the psychiatric morbidity amongst urban and rural elderlies with special reference to cognitive disorders.
Material & Methods: The study universe consisted of randomly selected urban and rural localities of Lucknow. Elderlies 55 years and above fulfilling stringent intake criteria and giving informed consent formed the study sample (urban- N = 2283; rural- N = 1260). Included elderlies were subjected to initial screening through Mini Mental Status Examination and Survey Psychiatric Assessment Schedule to identify ‘suspects’ for cognitive and neuropsychiatric disorders. The ‘suspects’ were then subjected to detailed assessment through Cambridge Mental Disorder of the Elderly Examination- Revised (CAMDEX-R) for cognitive disorders and Schedule for Clinical Assessment in Neuropsychiatry (SCAN) for neuropsychiatric disorders other than cognitive disorders. The categorization of neuropsychiatric and cognitive disorders was done on the basis of ICD-X and another sub group of Sub Syndromal Mental Health Problems was identified based on a popular definition (having one or two symptoms necessitating help seeking but not amounting to a definitive diagnostic category).
The recruited elderlies were also subjected to comprehensive physical, neurological examination (using PNE) and pathological/radiological investigations. Following this, the elderlies were categorized as per their mental and physical health status in different categories. Comparison of psychiatric morbidity was done between rural and urban areas dividing the rural and urban samples into two groups, 1) ‘stepping in’ (55–59 years) and 2) ‘stepped in’ (60 yrs. & above) elderlies termed as Pre Elderly Group and Elderly group respectively.
Results: Contrary to popular belief, the overall prevalence of psychiatric morbidity (neuropsychiatric and cognitive) was found more in rural (24.4%) than urban (19.3%) areas in Elderly Group. The Pre Elderly Group showed a similar pattern for rural (20.5%) and urban (11.4%) subjects. Further, analysis of the sample revealed similar observations and neuropsychiatric disorders were found to be more prevalent in rural Pre Elderly Group subjects (16.8%) than their urban counterparts (9.4%). The Elderly Group followed the suit (rural – 14.6%; urban – 11.8%).
The analysis for Cognitive Disorders revealed a prevalence of (3.7%) in rural and (2.0%) in urban Pre Elderly Group. For Elderly Group it was 9.8% in rural and 7.6% in urban subjects. A differing pattern was noticed for sub syndromal mental health problems. These were less in rural (2.0%) than urban (2.9%) Pre Elderly Group subjects. Even the Elderly Group had more sub syndromal mental health problems in urban areas (6.6%) than rural areas (3.6%). The results of the study are discussed in the light of psycho-socio-economic matrix of the rural and urban areas vis-à-vis psychiatric morbidity in Pre and Elderly Group subjects.
PS01.113
Effects of discontinuing benzodiazepine-derivative hypnotics on cognitive and motor functions in the elderly
Kenichi Tsunoda1; H Uchida2; A Tanabe3; T Suzuki4; K Watanabe2; H Kashima2
1Minami-hanno Hospital, Saitama, Japan; 2Keio University, School of Medicine, Tokyo, Japan; 3National Defence Medical College, Saitama, Japan; 4Centre for Addiction and Mental Health, Toronto, ON, Canada
Objective: Benzodiazepines (BZDs) have been reported to cause negative impacts on motor as well as cognitive functions, which in turn could result in lethal incidents including falls especially in the elderly. This notwithstanding, few trials have evaluated a feasibility and benefits of discontinuing BZD-derivative hypnotics in a systematic manner in this frail population. In this study, we examined changes in motor and cognitive functions following discontinuation of BZD hypnotics in elderly persons.
Methods: In this 8-week open-label study, subjects aged 65 or older who received BZD as a hypnotic and did not have any unstable physical illness, or neurological disorder were recruited. The BZD dose was tapered off in 4 weeks by a weekly 25% reduction. The following assessments were performed 12 hours postdose at baseline and at endpoint: the Clinical Stabilometric Platform (CSP), the Repeatable Battery for the Assessment of Neuropsychological Status (RBANS), the Critical Flicker Fusion Test (CFF), and the Leeds Sleep Evaluation Questionnaire (LSEQ). The CSP measures the stability of body, with eyes opened or closed. This study was approved by the institutional review board, and subjects provided written informed consent after receiving detailed information about the protocol.
Results: 28 subjects were enrolled (mean age = 76.9 years, mean flunitrazepam equivalent BZD dose = 1.6 mg/day). Psychiatric diagnoses (DSM-IV) of subjects were as follows: sleep disorder (n = 11), schizophrenia (n = 9), and dementia (n = 8). 24 subjects completed this study. Among those completers, significant changes were found in the total length of the trunk motion (63.1 cm to 57.8 cm with eyes opened and 79.9 cm to 64.1 cm with eyes closed). Significant improvements were also observed in the CFF and RBANS total score (27.0 Hz to 29.0 Hz and 98.7 to 120.2, respectively). No worsening in the LSEQ was found in those completers in terms of Getting to Sleep, Quality of Sleep, Awakening from Sleep, or Behavior following Wakefulness items. The reason for dropouts was a worsening of insomnia (n = 4).
Conclusion: The preliminary findings of this study suggest that discontinuation of BZD hypnotics may be feasible in a majority of elderly persons and will provide a recovery in cognitive function and benefits in the stability of body during the daytime. These preliminary findings suggest the need of discontinuing, at least tapering, those toxic medications in older people.
PS01.114
Plotting the course: Identifying opportunities for knowledge transfer in LTC
L Van Bussel; Ann Jarvie
St. Joseph's Health Care – London, London, ON, Canada
Health care providers in Long Term Care (LTC) have frequently experienced barriers when they attempt to access external resources to provide support and care for residents who experience mood symptoms and responsive behaviour. Early identification and intervention for residents in LTC experiencing these symptoms can often result in the prevention of a crisis situation. In Ontario, access to external resources was the most common concern reported by LTC healthcare providers, especially during crisis situations (MOHLTC, 2007). With the plethora of evidence based research and best practice guidelines (CCSMH, 2006) and education modules; health care providers in LTC may often feel inundated with information. Navigating a path through these resources to develop a plan for the effectively engaging in knowledge transfer may prove challenging for some teams. In order to facilitate strategies for knowledge transfer and to assist teams to effectively access external resources, The Specialized Geriatrics Services of Southwestern Ontario (SGS) conducted a series of focus groups in local urban and rural LTC homes, to help inform them of the needs of LTC health providers, with respect to these two issues. The use of focus group has been identified by Krueger & Casey (2000) as an excellent way to obtain perceptions on a defined area of interest in a permissive, non-threatening manner. The purpose of this poster will be to share preliminary results of the focus group data analysis, as well as next steps for the working group.
PS01.115
Routine outcome monitoring in mental health care for older adults
Marjolein Veerbeek; M Depla; A Pot
Netherlands Institute of Mental Health and Addiction, Utrecht, Netherlands
Introduction: In order to enhance the quality of care provided, there is a growing emphasis on transparency in mental health care. In the Netherlands there is no systematic way in which quality of mental health care is measured. This information is essential for policymakers to see whether their policy has the expected results or that adjustments should be made. Routine Outcome Monitoring (ROM) can be used to establish the quality of treatment. Besides, ROM provides regular information to professional and client about the course and severity of symptoms during treatment, which can enhance treatment and make it more efficient.
To give insight in the quality of care for older adults, we designed the ‘Mental health care Monitor older adults' (MEMO). MEMO should provide insight in 1) whether older adults profit from their treatment in terms of mental and social functioning 2) whether older adults are satisfied with the care they receive and 3) the type of treatment older adults get.
Design: A surveillance network of mental health care institutions is started, to routinely measure quality of mental health care provided for older adults. In order to do this, an electronic system is developed. MEMO will act over a five year period and every year the same information (HoNOS 65+, consumer satisfaction) will be collected to give insight in trends in the quality of Dutch mental health care for older adults (MEMO Basic). Besides this basic information a specific disorder will be focused on every year to give insight in the quality of mental health care provided for this specific type of clients. The first year additional data will be collected on older adults with depression with the GDS-15 (MEMO Depression).
Results: In this presentation we will show which factors support or hamper the implementation of ROM in mental health care for older adults. Furthermore, some preliminary results on the type of clients that enter mental health care and to what extent they profit from their treatment will be presented.
PS01.116
Response rates to questionnaires on sexuality in the elderly
Laurence Villeneuve1; G Trudel1; M Preville3; R Boyer2; V Fréchette1
1University of Quebec at Montreal, Montreal, QC, Canada; 2Fernand-Séguin Research Centre, QC, Canada; 3Charles-Lemoyne Research Centre, QC, Canada
This presentation examines the response rates of older people to questionnaires on sexuality in the elderly. Few studies have examined the level of interest in sexuality in the elderly and the fact that most of them continue to have sexual intercourse (e.g., Starr, & Weiner, 1981; Brecher, 1984). Trudel (2002) found that elderly subjects have a more conservative attitude towards sex and less sexual fantasies and fewer sexual behaviors compared to younger subjects. It seems that sexuality does change with age. In this presentation, we will discuss some of the difficulties involved in evaluating sexual behavior in the elderly because most questionnaires on sexuality were not specifically validated in this segment of the population. In this study, 511 francophone couples (511 women, 511 men) aged 65 years old and over answered three sexual questionnaires that were not specifically validated for the elderly: Derogatis Sexual Functioning Inventory (DSFI), International Index of Erectile Function (IIEF), and Female Sexual Function Index (FSFI). According to the FSFI and IIEF results, 7% of the data were missing (i.e. more than 20% of items were not answered for each questionnaire), but for the DSFI the amount of missing data increased to 25%. It seems that some items on these questionnaires don't correspond to the sexual reality of the elderly. We will put forth hypotheses to explain this lack of response rates.
PS01.117
Precipitating factors associated with delirium among demented long-term care residents
Philippe Voyer1; S Richard2; L Doucet3; N Cyr3; P Carmicheal2
1Laval University, Quebec City, QC, Canada; 2Center for Excellence in Aging, Quebec City, QC, Canada; 3Centre de Santé et de services sociaux de la Vieille-Capitale, Quebec City, QC, Canada
Overview: Delirium is a common and serious problem in long-term care settings. Identification of risk factors for delirium is important because it enables health care professionals to quickly identify individuals at risk for delirium and implement preventive interventions to avoid its development. The purpose of this study was to investigate the precipitating factors associated with delirium among demented long-term care residents and to assess the cumulative effect of these factors on the likelihood of having delirium.
Method and materials: One hundred and fifty-five long-term care residents aged 65 and older with a diagnostic of dementia participated in this cross-sectional study. Logistic regression analyses were performed to assess the association between the 10 precipitating factors considered and the presence of delirium. Delirium was defined as meeting the Confusion Assessment Method criteria for either definite or probable delirium. A risk score was also computed as the number of precipitating factors for which an individual was considered at risk and a logistic regression model was fitted using the risk score as the independent variable.
Results: The prevalence of delirium in this sample was 70.3%. Use of physical restraints (OR: 4.64, 95% CI: 2.61–8.27) was found to be the most important factor associated with delirium. The likelihood of being in delirium increased with the number of precipitating factors present (OR: 2.53, 95% CI: 1.42–4.49). In addition to physical restraints use, modifiable risk factors identified included level of sensory stimulation and adequacy of physical environment.
Conclusion: Demented residents in LTC constitute a frail population. Health care professionals should be aware that for these individuals, only a limited number of precipitating factors need to be present to increase their likelihood of being in delirium. Among all precipitating variables analyzed, physical restraints appear to have an important effect on the presence of delirium. This result underscores the need to educate all caregivers about the hazards of using physical restraints and to implement protocols aimed at reducing such practices among this population.
PS01.118
Apolipoprotein E genotype, age of onset and MMSE in mild Alzheimer's disease in caucasians within an Australian community based memory disorders clinic
Bernard Walsh
HNEHealth, New Lambton, NSW, Australia
520 (age range 52 to 94 years, 59.3% females) consecutive, community dwelling caucasians with mild Alzheimer's disease presenting to the Adult Cognitive Impairment Clinic, Newcastle, Australia in the years 2005, 2006 & 2007 were studied for ApoE genotype, age at diagnosis and MMSE. This clinic functions within a primary community setting with a defined catchment area and so appears more representative of AD persons and their community distribution than perhaps more tertiary institutions. Each subject meets the criteria for both “Probable Alzheimer's disease” via DSM IV and for “Mild Dementia” using the Clinical Dementia Rating Scale (CDR 1:0). The results demonstrated a similar excess of females across all subgroups. The ApoE4 allele frequency for the group was 56.4% comprising of 10.75% homozygous (E4:E4) and 45.65% heterozygous (single E4 allele). This is markedly in excess of the 13% frequency demonstrated in reference non-diseased populations. With increasing ApoE4 allele load, the study demonstrated a progressively younger mean age of onset (E4:E4 = 75y, Single E4 = 78.4y, NoE4 = 79.6y, E2 without E4 = 81.3y), a lower median MMSE score (E4:E4 = 19, Single E4 = 22.5, NoE4 = 25), and a smaller range of age of onset (E4:E4 = 28.3y, Single E4 = 38.8y, No E4 = 39.6y). When the subgroup of persons having an E2 allele (but no E4 allele) was compared to the E4:E4, single E4 and E3:E3 groupings, this E2 subgroup had the highest mean age of disease onset of any genotype.
Conclusion: Community living caucasians in Australia with Mild Alzheimer's Disease demonstrate younger age of onset, a narrower range of age of onset and a lower mean MMSE at diagnosis with increasing ApoE4 allele load and this is consistent with the current literature on the interaction of ApoE4 and the amyloid protein of AD.
PS01.119
Geriatric psychiatry outreach to long-term care facilities can reduce in-patient admissions
Andrew Wiens1; C Ward2; M Rivard1
1University of Ottawa, Ottawa, ON, Canada; 2University of British Columbia, QC, Canada
This observational study compares the rate of admission to a geriatric psychiatry in-patient unit from long-term care (LTC) facilities who receive outreach services from a multi-disciplinary liaison-style outreach team and those who have consultation-only services from a geriatric psychiatrist. We conducted a retrospective review of routinely gathered admission data of patients referred to our geriatric psychiatry 26 bed in-patient service from LTC facilities in Ottawa. Data for the past five fiscal years (April 2003–March 2008) was compared for two types of services. Our geriatric psychiatry outreach service to 21 LTC facilities (3625 beds) in Ottawa is comprised of teams of geriatric psychiatrists and geriatric psychiatry outreach nurses that utilize a liaison-style approach. It is part of an integrated geriatric psychiatry service based in a tertiary psychiatric teaching hospital. The number of admissions from this liaison-style service was compared to those from three LTC facilities (535 beds) in the city who receive on-site consultation from a geriatric psychiatrist alone. The average rate of admission per 100 LTC beds derived from this data is 1.0 for the liaison-style outreach service versus 2.02 for the consultative model (psychiatrist-only). This suggests a benchmark of 1.0% of patients in LTC required admission over the course of one year with such an integrated program. This lower rate of admission has potentially significant cost implications. A net savings between the cost of avoiding an inpatient admission relative to the costs of providing a liaison-style outreach service to these LTC homes is demonstrated.
PS01.120
Cochrane systematic review of treatments to prevent the recurrence of depression in older people
Philip Wilkinson; Z Izmeth
University of Oxford, Oxford, United Kingdom
The long term prognosis of late life depression is poor, with around a quarter of patients becoming depressed within two years of remission or recovery, and a third suffering one or more relapses after two years. Effective longer term treatments of depression in older adults are crucial in reducing the levels of disability, morbidity and mortality.
Pharmacological and psychological treatments are widely used in the acute phase of treatment of depression in older adults and are often continued during remission and into recovery. Given the long-term impact of depression and the resources involved in long-term treatment it is important to determine the efficacy of pharmacological and psychological treatments alone or in combination in reducing the risk or recurrence of relapse following successful acute phase treatment.
The aims of this systematic review were to identify and critically appraise randomised controlled trials conducted with adults aged 60 and over, to provide a meta-analysis of their results if possible, and to determine the relative efficacy of different treatments in order to inform clinical decisions. Withdrawal rates through physical illness, side effects and death were also studied. The review included trials of antidepressant medication, any structured psychological treatments of any duration and combinations of the two administered in the continuation and maintenance phases of treatment. ECT or lithium used as continuation or maintenance treatments were excluded. Trial participants suffering from bipolar disorder, dementia and other mental disorder were also excluded. Following electronic searching of Cochrane databases and hand searching over 1900 papers were screened. While there were many randomised controlled trials that included both older and younger people none included separate analyses of results from older people. There were few that trials that recruited only people 60 and over.
Ten trials of a number of different antidepressant medications and psychological treatments have been identified and the combined findings of these studies will presented. The implications of the findings for clinical practice will be discussed along with the merits and disadvantages of conducting trials with older adults only.
PS01.121
Decision-making in dementia: Choosing from care and treatment options
Claire Wolfs1; M de Vugt1; F Stevens2; P Verkade3; F Verhey1
1University Hospital of Maastricht, Maastricht, Netherlands; 2University of Maastricht, Maastricht, Netherlands; 3The Geriant Foundation, Maastricht Region North of Amsterdam, Netherlands
Background: The number of patients suffering from dementia is expected to increase in the coming decades. This calls for an improvement and expansion of the treatment options. However, examination of the current clinical practice in the Netherlands reveals that treatment options are often not sufficiently utilized by the patients and/or their caregivers. It is not clear why this is the case.
Aim: Study questions were (1) to what extent and in what way, patients suffering from a cognitive impairment or dementia, utilize the available treatment options and (2) which factors play a role in the making of a well considered choice from these options. The study consists of three phases:
1) An inventarisation of the choices patients and their caregivers make;
2) Identification of factors that play a role in making a well considered choice from available care and treatment options;
3) A concrete solution to support patients and caregivers in the decision-making process.
Method: Questionnaires, semi-structured interviews by telephone, and focus-group interviews.
Participants: Inclusion criteria: 1) cognitive disorder or dementia; 2) living at home; 3) availability of an informal caregiver or proxy; and 4) a proposal for treatment or care
Results: 1) Counseling, treatment through medication, activities, and support, were the categories that were utilized the most. Patients and caregivers indicated “they would appreciate more regular counseling” and “an overview of the available treatment options” and “help with refusal of patients”. Most important reasons for declining care were “the patient refuses” and “we manage perfectly without help”. 2) Type of service, relation with the patient, diagnosis, severity of the dementia, and burden were the factors that predict the proposed, utilized and non-utilized treatment options. Half the patients and caregivers indicated they did not feel they had a choice in selecting care or treatment from multiple options. The other half indicated that it was a difficult choice because “it was more an emotional process”, “the patient refuses everything” and “there is no overview of treatment options”. 3) Patients and caregivers would appreciate a complete overview of the available treatment options directly after diagnosis, using the patient's and caregiver's needs as a starting point, placed in time according to the different stages of the dementia.
Conclusions: Most patients and caregivers are not aware of the treatment options available to them, or of the fact that they can choose from these options. Awareness of these options is necessary to avoid situations in which patients and caregivers find themselves with their backs against the wall and the need for care support has become an acute necessity. Health care professionals should play an important role with regard to this “empowerment” of patients and their caregivers.
PS01.122
Patient specific prescriber education and feedback is effective in reducing use of antipsychotics in the elderly
E Roughead1; A Gilbert1; M Woodward2; L. Kalisch1
1University of South Australia, Adelaide, SA, Australia; 2Austin Health, Melbourne, VIC, Australia
Antipsychotic medicines were originally developed to treat hallucinations and delusions associated with psychosis, particularly schizophrenia. While the prevalence of schizophrenia in the elderly is relatively low (estimated at 0.5 to 1%), cross-sectional studies have reported at least 25% of nursing home residents are prescribed these medicines. Increasingly, antipsychotics are used to treat behavioural and psychological symptoms of dementia (BPSD), with no strong evidence base and significantly increased risk of adverse events. Use of antipsychotics is likely to increase over time in elderly populations with increasing prevalence of dementia. This study aimed to improve use of antipsychotics in the elderly Australian veteran population by providing education and patient-specific feedback to prescribers.
The Department of Veterans’ Affairs (DVA) Pharmacy Claims database contains details of all medicines dispensed to veterans for which DVA pays a subsidy. We undertook an analysis of that database targeting veterans aged 65 years and over on 1st January 2007, who had been dispensed at least two antipsychotic prescriptions (ATC group N05A) in the six months December 2006 to May 2007. The primary general practitioner (GP) caring for the targeted veterans were identified from the data and were sent written information on the non-pharmacological and pharmacological management of BPSD, benefits and risks of antipsychotics in BPSD, and availability and dosing schedules of antipsychotics in BPSD. Patient-specific feedback detailing current antipsychotic medicines and medication review services received by each veteran was included. To determine the impact of this education intervention, time series trends in rates of antipsychotic dispensings were compared between targeted veterans (time period December 2006 to February 2008) and a historical cohort (identical period one year prior). To ensure that no inappropriate therapeutic shift occurred, the rate of targeted veterans per month dispensed hypnotics/anxiolytics (ATC codes N05CD, N05CF, N05BA) was assessed and compared to historical controls.
6,990 veterans met the inclusion criteria and the 3,884 GPs caring for these veterans were mailed patient specific education and feedback regarding use of antipsychotics. Analysis of antipsychotic dispensing amongst targeted veterans showed initial higher use of atypical antipsychotics than the historical controls; however, after provision of written education to GPs, use fell to levels similar to historical controls. Use of low dose risperidone fell in the targeted cohort compared to historical controls. There appears to have been no substitute prescribing to hypnotics/anxiolytics as replacement therapy for antipsychotics, with the lowest rate of hypnotic use being observed in the targeted cohort.
Analysis of trends in dispensing of antipsychotics suggests a reduction in use of antipsychotics in the targeted veterans relative to historical controls, particularly for low dose risperidone. Importantly, use of hypnotics and anxiolytics did not increase, suggesting no inappropriate therapeutic shift occurred to this group of medicines. Patient specific feedback and education to prescribers appears to be effective in improving use of antipsychotics in this elderly population.
PS01.123
Urinary incontinence in elderly patients with senile dementia of Alzheimer's type in Japan
Hideyuki Yoshioka1; N Hayashi1; H Komori1; Y Izumi1; T Watanabe1; M Yokode2; T Kita2; T Kumada1
1Kyoto Postal Services Agency Hospital, Kyoto, Japan; 2Kyoto University Hospital, Kyoto, Japan
The purpose of this study was to evaluate the prevalence of urinary incontinence in elderly patients with senile dementia of Alzheimer's type (SDAT) in Japan. 140 SDAT patients (81.2±4.6 years of age, 89 women and 51 men) with urinary incontinence were investigated to evaluate the correlations among prevalence, grade and risk factors of urinary incontinence. Of these patients, 74% had urinary incontinence, and the half of these patients showed high grade incontinence. Incontinence predominantly worsened along with SDAT and behavior disturbance, but was not closely correlated with combined diseases, drug therapy, or urinary infection. These patients exhibited accelerated reflexes of urinary muscles (overactive bladder: OAB), and SDAT was closely correlated with urinary incontinence. In conclusion, SDAT and behavior disturbance were independent risk factors of urinary incontinence in the elderly patients, and accelerated reflexes of urinary muscles (OAB) were considered to be the cause of the urinary incontinence.
PS01.124
The effect of bright light therapy on depression, sleep disruptions, and salivary cortisol level among institutionalized older adults
Mann-Chian Wu; H Sung; T Li
Tzu Chi College of Technology, Hualien City, Hualien County, Taiwan
Older adults who reside in nursing homes often have limited opportunities for outdoor activities and therefore less exposure to sun light due to the limitation of environmental designs and shortage of nursing staff. Bright light therapy has been suggested as an alternative intervention to sun exposure and has shown positive outcomes in managing seasonal affective disorders, depression, sleep problems, and circadian rhythm disturbances among older adults. However, little is known about the effect of bright light therapy on the level of salivary cortisol among older adults residing in long-term care facilities in Taiwan. This study aimed to evaluate the effect of bright light therapy on depression, sleep disturbances, and the salivary cortisol level among older adults in a nursing home. A quasi-experimental design with a purposive sample was used. Bright light therapy was administered via Apollo Brite Life IV, which is a light box with 10000 lux, to 13 older adults for 30 minutes in the morning three times a week, over four week period in the activity room. The participants sit on the chairs or wheelchairs in front of the Apollo Brite Life IV with a distance of five feet between the participants and the light box in the activity room. Geriatric Depression Scale was used to assess the level of depression, and a Sleep Disturbance Checklist was used to assess sleep disruptions at night at baseline and week 4. Saliva were collected before and after the bright light therapy session foe testing the cortisol concentration. The results indicate that participants who received 4 weeks of light therapy had a significant reduction in their depression scores at post-test (p < .001), and a significant reduction on frequencies of sleep disruptions at post-test (p < .05). The study also found that the level of salivary cortisol was reduced significantly after the bright light therapy session (p < .001). Bright light therapy can be a safe and viable modality to improve physiological and psychological outcomes and has the potential to promote mental well-being and sleep quality of older adults residing in long-term care settings.
PS01.126
Brain volume changes in 2 years and a cross sectional examination of MR spectroscopy of posterior portion cingulate gyrus in patients with Alzheimer's disease
Shifu Xiao1; T Wang1; X Li1; M Chen2
1Shanghai Mental Health Center, Shanghai Jiaotong University School of Medicine, Shanghai, China; 2Ruijing Hospital, Shanghai Jiaotong University School of Medicine, Shanghai, China
Objective: To study the brain volume changes of patients with Alzheimer's disease and assess the H-MRS characteristic of posterior portion cingulate gyrus and the correlations with MMSE, ADAS-cog in patients with mild-moderate Alzheimer's disease.
Methods: 23 patients with Alzheimer's disease and 23 gender, age and education matched normal controls participated at the baseline. 10 patients with Alzheimer's disease and 11 normal controls remained at the follow-up. Hippocampus formation, amygdala, entorhinal cortex (EC), perirhinal cortex (PC), cornu temporale, uncus distance etc. were measured with 3D-MRI at baseline and follow-up after 2 years. 24 AD patients, 8 VD patients and 11 gender and age and education matched normal controls were studied with H-MRS. All of the subjects were assessed by MMSE and ADAS-Cog.
Results: There were significant difference of the uncus distance (AD vs NC: 11SD4 vs 7SD3, P<0. 01), the total temporal horn VOL (AD vs NC: 1. 21SD1. 00 vs 0. 59SD0. 54, P<0. 05), the total entorhinal cortex VOL (AD vs NC: 2. 52SD0. 86 vs 3. 67SD0. 54, P<0. 01), the total perirhinal cortex VOL (AD vs NC: 2. 19SD0. 62 vs 3. 39SD0. 51, P<0. 01), the total hippocampus (AD vs NC: 3. 23SD0. 75 vs 3. 98SD0. 38, P<0. 01) at the baseline. The significant differences of the uncus distance(AD vs NC: 11SD4 vs 7SD4, P<0. 01), the total temporal horn VOL (AD vs NC: 6.74SD4. 60 vs 0. 60SD0. 58, P<0. 01), the total entorhinal cortex VOL (AD vs NC: 1. 79SD0. 56 vs 2. 76SD0. 50, P<0. 01), the total perirhinal cortex VOL (AD vs NC: 1. 77SD0. 59 vs 2. 76SD0. 41, P<0. 01), the total hippocampus VOL (AD vs NC: 2. 80SD0. 80 vs 3. 59SD0. 38, P<0. 01) still remained at the follow-up. The most salient shrinkage was observed in hippocampus. The standardized annually VOL shrinkage rate was 11% for AD and 7% for NC, and there was significant differences between the two groups. The ratio of NAA/Cr was 1.24SD0.12, mI/Cr was 0.74SD0.15 in AD group posterior portion cingulate gyrus, the ratio of NAA/Cr was1.25SD0.15, mI/Cr was 0.65SD0.15 in VD group. The ratio of NAA/Cr was 1.46SD0.19, mI/Cr was 0.62SD0.09 in NC group. The ratio of NAA/Cr was significant difference in three groups. The ratio of NAA/Cr was significant difference between AD group and NC group and between VD group and NC group. The ratio of mI/Cr was significant difference between AD group and NC group. But there was no significant difference between VD group and NC group. The ratio of NAA/Cr and mI/Cr were no significant difference between AD group and VD group. There were statistical significant correlations between the ratio of NAA/Cr and MMSE score (r = 0.731,P = 0.000), there were statistical significant correlations between the ratio of NAA/Cr and ADAS-cog score (r = –0.541,P = 0.011).
Conclusion: The present study confirmed that the AD patients obviously brain atrophy compared to normal controls at the structures of entorhinal cortex, perirhinal cortex, hippocampus formation, and have obviously extension compared to normal controls at the structures of cornu temporale and uncus distance. The shrinkage rate of hippocampus can be used as marker for diagnosis and progress of Alzheimer's disease. The ratio of NAA/Cr was obviously decreased in posterior portion cingulate gyrus of AD group, and had statistical significant correlations with the score of MMSE and ADAS-cog. If the ratio of NAA/Cr measured in the posterior portion cingulated gyrus small than 1.31 was used as criteria of AD, the positive predictive value of AD was 73% and negative predictive value was 71% in this study. The H-MRS characteristic of posterior portion cingulate gyrus could not well different early AD from VD.
PS01.128
Evaluating the effect of memantine on the rate of brain atrophy in patients with Alzheimer's disease: A multi-centre imaging study
D Wilkinson
Moorgreen Hospital, Southampton, United Kingdom
Preclinical evidence shows that memantine can decrease the neuronal toxicity associated with excessive activation of NMDA receptors in vitro. At therapeutically relevant doses, memantine provides protection in vivo from a variety of neurotoxic insults believed to contribute to the pathology of AD. Currently, it is not known whether the preclinical findings translate into the potential for memantine to alter disease pathology in humans. For the cellular pathological processes occurring in AD, brain atrophy can be used as an indirect marker. Serial MRI registration is a sensitive, reliable, well-validated method for monitoring rates of brain atrophy in AD patients. Brain atrophy measured by serial MRI has been shown to correlate well with cognitive decline in AD.
The primary objective of this study is to use MRI to explore the effects of memantine on the rate of brain atrophy, by assessing total brain volume (TBV), in patients with probable AD during one year of treatment. The secondary objectives are to evaluate the effects of memantine on additional MRI measures, cognitive and behavioural outcomes, and associations between changes in clinical and MRI outcomes as well as to evaluate the safety and tolerability of memantine.
This study is a 1-year, multinational, multi-centre, randomised, double-blind, placebo-controlled, fixed-dose trial in outpatients aged 50 years or older, diagnosed with probable AD according to the NINCDS-ADRDA criteria, Mini Mental State Examination (MMSE) score of 12–20 (inclusive), and Modified Hachinski Ischaemia score of ≤ 4 at screening. Centralised reading of T1- and T2-weighted MRI scans conducted at screening should be consistent with a diagnosis of probable AD without evidence of other significant neurodegenerative or neurological disorder. Patients are allowed in the study whether on concomitant cholinesterase inhibitor therapy or not, but stratification was used to ensure equal allocation within each group to memantine and placebo treatment. The study included a screening period of 3 weeks followed by 52 weeks of double-blind treatment with memantine. Memantine was uptitrated to 20 mg/day in 5 mg increments over the first 3 weeks of the double-blind period. The boundary shift integral technique was used to assess direct changes in TBV. The TBV change is selected as primary endpoint as it includes all potential areas of brain loss and quantification is semi-automated. MRI scans of the patients were done at screening, Week 4, 42, and 52. Cognitive outcomes were evaluated by Controlled Oral Word Associations Test, Category Fluency, Stroop, and Orientation at screening, baseline, Week 4, 12, 24, 42, and 52. The Neuropsychiatric Inventory at baseline, Week 12, 24, and 52, evaluated behavioural outcome. Safety was monitored through adverse events, concomitant medications, and vital signs. The preliminary results of this study will be presented.
PS01.130
Dissemination and transfer of guideline recommendations into practice: A survey of the members of the Canadian Academy of Geriatric Psychiatry (CAGP)
D Conn1; M Donnelly2; S Sanders3; K Wilson4; S Helsdingen4
1Baycrest & University of Toronto, Toronto, ON, Canada; 2University of British Columbia, Vancouver, BC, Canada; 3Calgary Health Region, Calgary, AB, Canada; 4Canadian Coalition for seniors' Mental Health, Toronto, ON, Canada
Overview: In January 2005, the Canadian Coalition for seniors' Mental Health (CCSMH) was awarded funding by the Public Health Agency of Canada, Population Health Fund to lead and facilitate the development of evidence-based recommendations for best practice National Guidelines in four key areas of seniors' mental health. In May, 2006, the following guidelines were released:
– The Assessment and Treatment of Delirium
– The Assessment and Treatment of Depression
– The Assessment of Suicide Risk and Prevention of Suicide
– The Assessment and Treatment of Mental Health Issues in Long Term Care Homes (Focus on Mood & Behaviour Symptoms)
In 2006, an in-depth dissemination program followed with all CAGP members receiving the four guidelines in a special mailing. To date, over 11,500 hard copies of these guidelines have been disseminated across Canada and an additional 11,000 copies were downloaded from the website from over 40 countries.
In 2007, the Public Health Agency of Canada, Population Health Fund contributed additional funding to further enhance dissemination of the guidelines and to define activities to implement and evaluate the CCSMH National Guidelines. Seven pilot projects were developed to implement the guidelines in a variety of settings across Canada. One of the projects surveyed the utilization of the guidelines by CAGP members and evaluated their impact on practice.
An online survey regarding use of the guidelines was sent by the CAGP Board to 155 English-speaking members of the CAGP in April & June, 2008 (prior to the release of the Guidelines in French). 45% of members responded. The responders rated the guidelines as highly useful and 56% reported that the guidelines had resulted in a change of their clinical practice. 39% of the responders reported that they had a commitment from their organization to disseminate the guidelines and 33% had a commitment to implement them.
Learning objectives:
– Awareness of how recommendations from best-practice guidelines can be disseminated and implemented in professional practice.
– Knowledge of some of the organizational issues that effect the dissemination and implementation of guidelines.
– Appreciation of the impact of the CCSMH national guidelines in clinical practice settings.
PS01.134
Longitudinal course of neuropsychiatric symptoms in patients with (pre)dementia: Epidemiology, natural course, and treatment
Roland Wetzels1; George Savva2; Philippe Robert3; Clive Ballard4
1Radboud University Nijmegen, Nijmegen, Netherlands; 2University of Cambridge, Cambridge, United Kingdom; 3Hôpital de Cimiez, Nice, France; 4King's College London, London, United Kingdom
Neuropsychiatric symptoms of dementia and the challenges they present are as important as those of cognitive losses (A. Burns, 2009). Outpatient studies have shown that neuropsychiatric symptoms are highly prevalent in dementia. This truly international symposium will present exiting new data on the epidemiology, natural course and predictors of neuropsychiatric symptoms in patients with pre-dementia or MCI and in nursing home patients. Moreover, longitudinal data will enhance our understanding of apathy and depression as Alzheimer's disease evolves.
Course of neuropsychiatric symptoms and concomitant psychotropic medication over a two-year period in dementia patients in Dutch nursing homes.
Introduction: Neuropsychiatric symptoms(NPS) are common in dementia patients. Preliminary results from the Waalbed-II-study after a one-year follow-up showed that individual NPS are highly prevalent but show different courses. The objective of this study was to determine the course of a wide range of neuropsychiatric symptoms in Dutch nursing home patients with dementia over a two-year period and concomitant use of psychotropic drugs.
Method: All patients on 14 dementia special care units (SCU) in nine nursing homes in the Netherlands were eligible. Patients had to meet DSM-IV diagnosis for dementia, had to be institutionalized for at least four weeks and had to have no life-threatening disease at the time of the baseline measurement. Nosologic dementia diagnosis was determined according to the Dutch guideline (CBO 2005) ‘diagnosis and treatment of dementia’ and international approved criteria. At baseline, patients' characteristics were registered. Severity of dementia was assessed with the Global Deterioration Scale (GDS), and cognitive functioning was assessed with both the MMSE and the short-Severe Impairment Battery (s-SIB). At baseline and successive six-months intervals, symptoms were observed by licensed vocational nurses during regular care-giving in an observational period prior to assessment. Neuropsychiatric symptoms were assessed using the Neuropsychiatric Inventory-Nursing Home (NPI-NH) version. Psychotropic medication was classified using the Anatomical Therapeutical Chemical- classification and grouped into antipsychotics, anxiolytics, hypnotics, antidepressants, antiepileptics, and anti-dementia drugs and described as present or absent. Patients had a two year follow-up, with five assessments in total.
Results: 290 dementia patients were included at baseline, of which 117 were analysed after two-year follow-up. Average age at baseline was 84 years (SD 7.1) and 76% were female. 38.6% of patients suffered from Alzheimer's dementia, 10.4% from vascular dementia, 6.2% had mixed dementia, and 44.6% had other dementia diagnosis. 70% of patients had severe to very severe cognitive decline (GDS stage 6 or 7); average MMSE was 7/30 (SD6.25) and average s-SIB was 26/50 (SD17.3). High prevalences were seen for agitation, apathy, irritability and aberrant motor behaviour; the least for hallucination and euphoria. Cumulative prevalence overall reached more than 95%; individual symptoms showed different courses. Persistent use of antidepressants and antipsychotics was high regardless the course of symptom.
Conclusion: After completion, this prospective cohort study is the first to describe the course of neuropsychiatric symptoms and the concomitant use of psychotropic medication in a large group of nursing home dementia patients with a two-year follow-up. These results will have practical implications for the pharmacological treatment of neuropsychiatric symptoms and advocate the use of non-pharmacological interventions instead.
Epidemiology of BPSD in older people with mild cognitive impairment
Introduction: Behavioural and psychological symptoms are common in people with dementia and present many challenges for people with dementia and their carers. ‘Mild cognitive impairment’ (MCI) is a term used to describe a state of cognitive impairment not sufficient for dementia but associated with an increased risk of dementia progression. Understanding the association between BPSD and cognitive impairment in the non-demented population is important both in the management of MCI and to understand the development of BPSD in dementia. We have previously reported the prevalence of BPSD in the older population without dementia. In this study we describe further the epidemiology of BPSD in this population, specifically with respect to the component criteria necessary for a case diagnosis of MCI.
Methods: The Medical Research Council Cognitive Function and Ageing Study is a multi-phase multi-centre study of ageing with 13004 participants aged 65 years or over at baseline. A detailed assessment including measures of behavioural and psychological symptoms was undertaken in a stratified subsample of 2640 participants of which 2050 did not have dementia. The assessment included interviews with study participants and informants, and included measures of depression, anxiety, elation, sleep problems, apathy, agitation, delusions, hallucinations, irritability, confabulation, and wandering. The prevalence of each symptom was found across strata of global cognitive function and age. Logistic regression adjusting for sociodemographic factors was used to assess the association between the presence of symptoms and the component criteria necessary for a case diagnosis of MCI including global cognitive function, objective memory impairment, subjective memory complaint and functional impairment.
Results: The prevalence of each of the behavioural and psychological symptoms was found to be less in the population without dementia than in those with dementia. In those without dementia prevalence increased with increasing cognitive impairment. Symptoms were slightly more common in individuals aged over 75 years, but after adjustment for cognitive impairment tended to be more common in those aged 65–74 years. In multivariable analyses, subjective memory complaint was associated with the presence of all symptoms, while objective memory impairment was associated with only anxiety, agitation and symptoms of psychosis. Most symptoms were significantly more common in those with severe functional impairments.
Conclusion: Behavioural and psychological symptoms are present in a significant proportion of the population without dementia, and their presence is related to the nature and severity of cognitive and functional impairments. Assessment and management of BPSD is required in individuals with cognitive impairments not at the threshold for dementia. Understanding the natural history of the relationships between domains of impairment and BPSD will improve the treatment and management of both cognitive and non-cognitive symptoms of dementia.
Apathy in Alzheimer's disease: a 4 years follow up in the REAL-FR cohort
Introduction: There is wide acknowledgement that apathy is an important behavioural syndrome in Alzheimer's disease and in various neuropsychiatric disorders. In light of recent research and the renewed interest in the correlates and impacts of apathy, and in its treatments, it is important to develop criteria for apathy that will be widely accepted, have clear operational steps, and that will be easily applied in practice and research settings. Meeting these needs is the focus of the task force meeting organized in April 2008.
The task force includes members of the Association Française de Psychiatrie Biologique, the European Psychiatric Association, the European Alzheimer's Disease Consortium and experts from Europe, Australia and North America. Apathy is defined as a disorder of motivation that persists over time and should meet the following requirements. Firstly, the core feature of apathy, diminished motivation, must be present for at least four weeks; secondly two of the three dimensions of apathy (reduced goal-directed behaviour, goal-directed cognitive activity, and emotions) must also be present; thirdly there should be identifiable functional impairments attributable to the apathy. Finally, exclusion criteria are specified to exclude symptoms and states that mimic apathy.
Evolution of apathy will be illustrated with the PHRC REAL.FR data. The multicenter PHRC REAL-FR cohort is a longitudinal study for community-dwelling patients with a diagnosis of AD. The present study describes the 4 years evolution of apathy and depression.
Method: 686 patients were recruited. The present study deals with the 207 patients (mean age = 76.5SD ±0.47; mean MMSE score = 21,1 SD = 0.26). At baseline patients were divided in 4 subgroups according to the Neuropsychiatric Inventory (NPI) dimensions scores. The cut off score >3 on the frequency x severity score was chosen because considered as clinically significant. Group A = patients with apathy only; Group D = patients with depression only; Group AD = patients with apathy and depression; Group 0 = patients without apathy and depression NPI items.
Results: At baseline the following repartition was observed; without apathy and depression (53.3%); with apathy alone (33.6%), with depression alone (5.8%), with apathy and depression (7.3%). The 4 subgroups were not stable during the follow up period (chi square test p = 0.04). The number of patients with apathy increase whereas the number of patients without apathy and depression decrease (Linear-by-Linear Association test; p = 0.001).
For the 4 subgroup defined with the baseline apathy and depression criteria, 48 months follow up data indicated that there were no significant differences between groups in MMSE, IADL and Zarit scores evolution.
Conclusion: During the course of the disease patients without symptoms tend to become more apathetic but not more depressed.
PS01.136
Finding abuse in dementia patients; don't just ask!
Kevin Lawless1, Leslie Pisani1, Christine A. Walsh2
1Alberta Hospital Edmonton, Edmonton, AB, Canada; 2University of Calgary, Calgary, AB, Canada
The prevention of elder abuse is increasingly important as current estimates show the world's population of adults over age 65 rising dramatically. Even more alarming is the rising proportion of very old adults; the proportion of Canadian adults aged 85 and over is expected to nearly double by 2026 (Statistics Canada, 2007). This aging population will be associated with a concomitant rise in the rate of those diagnosed with dementia. As many older adults with dementia are hospitalized, the opportunity exists for abuse screening but the question remains as to which instrument is most suitable for this population as they present unique challenges and are often not included in the development and testing of screening instruments. This presentation summarizes literature on the utility and feasibility of screening for elder abuse, discusses strategies to improve screen implementation and reviews elder abuse screens comparing characteristics and features to identify the most suitable screens for a hospital setting with older adults who have dementia. For clinicians, the Elder Assessment Instrument and the Brief Abuse Screens for the Elderly are best suited for the population as they are brief and have psychometric data available. The brief Hwalek-Sengstock Elder Abuse Screening Test has many of the desired features of screens for the older adult to complete. The Modified Conflict Tactics Scale (MCTS), which has been used for both the older adult and the non-professional caregiver, has many of the recommended characteristics including use with the population of interest and acceptability with caregivers. Preliminary data from a trial of the MCTS applied to a group of elderly adults in a tertiary care psychiatric hospital, many of whom have a diagnosis of dementia, will be reported.
PS01.140
International perspectives on dementia education, training and knowledge transfer
Colleen Doyle4; Murna Downs1; Brian Draper2; Jocelyn Angus3; Colleen Doyle4
1Bradford University, Bradford, United Kingdom; 2University of New South Wales, Sydney, NSW, Australia; 3Victoria University, Melbourne, VIC, Australia; 4National Ageing Research Institute, Melbourne, VIC, Australia
Dementia education, training and knowledge transfer are vital to inform practice among health professionals who work with people living with dementia. This symposium brings together experts from the UK and Australia to discuss the latest developments in education, training and knowledge transfer and provide international perspectives on future directions.
The role of higher education in transforming the quality of dementia care
There is now widespread concern about the inadequate care and support provided to people with dementia from diagnosis to death. It is acknowledged that while there is a range of effective ways to care for and support people with dementia and their families from diagnosis to death, these have yet to become integral to practice. In England, for example, the National Dementia Strategy seeks to transform the quality of dementia care. One of the key components to transforming the quality of care is to ensure we have an informed and effective workforce. We will argue here that in order to transform the quality of care we need to distinguish between the aims of training and education. Whilst there is a place for skills-based workplace training, Higher Education in dementia studies has a key role to play in the provision of specialist knowledge and skills in dementia care emphasizing as it does the development of critical thinking, reflection and action. In this paper we will describe dementia studies in Bradford University available at both undergraduate and postgraduate levels. We will outline their aims and learning outcomes, curricula, approach to teaching, learning and assessment. We will describe the nature of students who study with us, noting their fit with the Higher Education Funding Council in England's agenda for widening participation in higher education. Higher Education in dementia studies has a unique role to play in equipping practitioners and professionals with the information, skills and attitudes to realize the potential for quality of life for people with dementia and their families.
Translating dementia research into practice
There is a gap between the knowledge obtained in dementia research and the practical use of it. This review examines the concept of knowledge translation (KT) and the process of translating research into practice in the field of dementia. KT in dementia practice involves key players including researchers, educators, clinicians, policymakers, the general public and consumers who act within a multidimensional network, disseminating findings widely to effect changes in community awareness, clinical practice and health policy. Challenges include the volume of dementia research; difficulties in determining who is responsible for KT; the problems of premature KT; the lack of resources to perform KT; the paucity of research about effective KT strategies; and the characteristics of the dementia care workforce. Key features of effective KT include a simple compelling message; use of interpersonal contact and roles; a practical framework with an emphasis on ‘know-how’; and the provision of resources and support. More effective dementia KT will require a commitment by key players to engage in the process, a better understanding of effective KT strategies, adequate resources, and judicious selection of appropriate evidence-based information.
Leadership: A central tenet for postgraduate dementia services curricula development
Background: In the next decades of the 21st Century, the global ageing of populations will challenge every nation's ability to provide leadership by qualified health professionals to reshape and improve health care delivery systems. The challenge for educators is to design and deliver courses that will give students the knowledge and skills they need to confidently fill that leadership role in dementia care services.
Method: This paper explores the ways in which curriculum can develop graduates who are ready to become leaders in shaping the industry they will be leading. Within this context, the Master of Health Science-Aged Services program at Victoria University, Melbourne, Australia is used as a case study to describe the process by which the concept of leadership is used as the key driver in curriculum development, teaching practices and learning outcomes.
Results: Evaluation instruments employed in a variety of purposes including teaching, curriculum planning and unit appraisal are discussed. Challenges for the future are proposed including the need for postgraduate programs in dementia to seek stronger national and international benchmarks and associations with other educational institutions to promote leadership and a vision of what is possible and desirable in dementia provision.
Ten years on: the development of education and training in dementia care in Australia
Ten years ago, in reviewing service-based and tertiary institution-based education and training in dementia care in Australia we commented on a widely held belief that carers just needed ‘a kind heart and common sense’ in order to work in residential care (Doyle & Ward, 1998). This attitudinal barrier to effective provision of education and training in the field has begun to recede but has not disappeared altogether. Attitudinal change is not helped by the working conditions and career pathways that we provide in aged care. In Australia, nurses working in aged care are still paid at a lower rate than nurses working in the acute sector. The challenge for educators and trainers is to provide information as effectively and efficiently as possible in the face of both attitudinal and fiscal barriers.
PS01.144
Biomarkers in early diagnosis of neurodegenerative disorders
Jerzy Leszek
University of Wroclaw, Wroclaw, Poland
Early diagnosis and adequate treatment are of crucial importance for slowing the development of neurodegenerative disorders. It is desirable to find a specific biochemical marker, easy to determine in body fluids, for early detection of the disorders that could also be useful in monitoring the effects of therapeutic treatment. The authors of this symposium will present their new findings in this matter on the pharmacogenomic, neurochemical, and biochemical levels.
Biomarkers and pharmacogenomic in Alzheimer's disease
Neurochemical dementia diagnosis: biomarkers in the CSF and blood
Emerging biomarkers of oxidative stress in neurodegenerative disorders
Are advanced glycation end products a specific biochemical marker for early detection of Alzheimer's disease?
PS01.146
Using spontaneous activity opportunities to promote engagement of people with BPSD in residential care
Alissa Westphal; R Attoe; D Harris
St Vincent's Aged Psychiatry Service, St Vincent's Hospital (Melbourne), Kew, VIC, Australia
Up to 90% of people with dementia experience behavioural and psychological symptoms of dementia (BPSD) during the course of their illness. The presence of these symptoms can be due to unmet needs for engagement in meaningful activity. However, with the progression of dementia, engaging in activities can become more difficult and can require significant carer support and intervention.
This paper reports on a project that aimed to maximize opportunities for spontaneous activity within a residential care facility that houses people with moderately severe to severe BPSD.
The environment within the 30 bed aged psychiatry residential care facility was modified to incorporate themed activity stations and environmental fixtures. Data was collection on the change in behavioural and psychological symptoms of dementia of the residents and care worker and family satisfaction. Post measures of well-being were also collected.
Practical and achievable examples of how activity opportunities can be incorporated into the environment, the management of associated risks and the manner in which the activities can be utilized and modified will be presented. The responses of residents with dementia, their family/carers and care workers and outcomes associated with changes in BPSD will be discussed.
PS01.148
Clinically meaningful measurement of BPSD in residential care
Alissa Westphal1; R Attoe1; C Bryant2
1St Vincent's Aged Psychiatry Service, St Vincent's Hospital (Melbourne), Kew, VIC, Australia; 2Royal Women's Hospital, Carlton, VIC, Australia
Behavioural and psychological symptoms of dementia (BPSD) are prevalent within residential care. The impact of these symptoms on the person with dementia and those around them has been extensively documented. Given the impact of BPSD it is frequently necessary to implement interventions that reduce their occurrence and or severity.
Assessment of BPSD is recommended as the first step in developing effective interventions and this often involves using a formalized assessment tool to measure the presence and severity of symptoms. Whilst a plethora of assessment tools exist for this purpose they have limited clinical usefulness as a result of high time demands for completion, lack of validity and reliability and poor sensitivity to symptom change.
This presentation reports on the development of the Behavioural Assessment Reporting Tool (BART) and addresses its clinical utility as an assessment for behavioural symptoms of dementia in residential care. The BART utilizes the Nursing Home Problem Behaviour Scale categories to obtain a temporal record of behavioural symptoms over 24 hours for a week long period. It may be used prior to and following any intervention in order to assess changes in behavioural symptoms.
Preliminary outcomes of reliability studies together with feedback from care workers who have utilized the tool will be discussed. Case examples will be provided to illustrate the clinical utility of the BART.
PS02.1
Cognitive deficits associated with low and high glycated hemoglobin levels: A cross-sectional study of aged people in a community
Hidenori Amano1; H Yoshida1; K Fujita2; S Kumagai3; Y Fujiwara1; S Shinkai1
1Tokyo Metropolitan Institute of Gerontology, Tokyo, Japan; 2Akita University, Akita, Japan; 3University of Human Arts and Sciences, Saitama, Japan
Although the acute effects of extremely low blood glucose levels, i.e., hypoglycemia are well known, the chronic effects of moderately low levels have not yet been elucidated. We have demonstrated that low as well as high glycated hemoglobin (GHb) levels are associated with decreased intellectual activity in an elderly population. The present study examined the cross-sectional relationship between GHb levels and cognitive performance in aged people.
We conducted a health check-up program that included medical examinations, blood tests, anthropological measurements, a cognitive test (mini-mental state examination; MMSE), and a sociological interview in a Japanese community. The study included 358 participants (women, 61%; age, 76.3 ± 5.1 years) who did not have a stroke history. They were divided into 4 groups: a diabetic group that included patients who were being medicated for diabetes mellitus and individuals who had GHb ≥ 6.5% and 3 non-diabetic groups (GHb, 3.7–5.0%/5.1–5.4%/5.5–6.4%). Within each of the 2 age strata (≤74 years/≥75 years), the cognitive performance (the MMSE total score and 5 subscores corresponding to the subheadings) of each of the GHb groups was compared to that of the middle GHb group as a reference; we controlled for possible confounders by means of linear regression. The MMSE total score (mean ± SD) was 27.0 ± 2.9. In the younger stratum, there was no statistical relationship between the GHb groups and the MMSE total or subordinate scores. In the older stratum, however, both low and high GHb levels were associated with a decreased MMSE total score (p < .05, p < .05), after controlling for sex, age, education, auditory impairments, and visual ones. Negative effects of low GHb on 2 MMSE subscores representing orientation and recall were observed (p < .05, p < .05). There were no significant associations between high GHb and the MMSE subscores, although the negative effects of high GHb on attention and calculation and language subscores approached statistical significance (p = .06, p = .06).
The relationship between the MMSE scores and the diabetic group was not significant. The relationships between GHb and MMSE scores in the older stratum were not substantially altered by excluding individuals with low serum albumin levels (<3.8 g/dl).
Thus, the association between chronic blood glucose levels and cognitive function increases with aging. High blood glucose levels correlate with global cognitive deficits, whereas low levels are associated with cognitive deficits of specific domains that require intact medial temporal lobes. The latter association could not be explained by malnutrition due to cognitive deficits, supposing that the serum albumin level adequately represents nutritional status. There is a possibility that chronically low blood glucose levels in the older old can be harmful to the efficient functioning and integrity of specific parts of the brain.
PS02.2
Bringing the Wii generation to residential care
Alissa Westphal; R Attoe; D Harris
St Vincent's Aged Psychiatry Service, St Vincent's Hospital (Melbourne), Kew, VIC, Australia
Within residential care, maximizing the functioning of people with dementia can be challenging particularly when behavioral and psychological symptoms (BPSD) are present. New technological equipment is increasingly being used to address some issues associated with managing behavioral symptoms and maintaining functioning. This paper presents the findings of a project that utilized the Wii with a group of people with moderate to severe BPSD within a specialized residential care setting. The Wii uses remote 3D controls to engage users in physically interacting with games. Whilst largely unfamiliar to this generation, the Wii engages residents on a multi-sensory level to promote physical movement, social interaction and enjoyment.
A single case study design was utilised to examine the impact of this new technological activity on resident's levels of behavioural and psychological symptoms of dementia and well being. Responses of care workers and families were also collected using survey research methods.
Single case results of this pilot analysis on the use of the Wii will be presented. Changes in behavioural and psychological symptoms of dementia and well being will be discussed in the context of differences in dementia types, stages and pre-morbid interests. The engagement of staff in a new technological activity will also be presented.
PS02.3
Managing behavioural symptoms of fronto-temporal dementia using a non-pharmacological approach
R Attoe; Alissa Westphal
St Vincent's Aged Psychiatry Service, St Vincent's Hospital (Melbourne), Kew, VIC, Australia
Researchers estimate that at least 2% of all people with dementia have fronto-temporal dementia (FTD). Initial symptoms of FTD are primarily associated with changes in personality and behaviour. Whilst there are a number of behavioural variants, ranging from overactive to apathetic behavioural spectrums, people with mild to moderate FTD tend to have intact short term memory. The presence of such behavioural symptoms, for example, emotional and behavioural dysregulation, disinhibition and sexually inappropriateness in the presence of an intact short term memory can result in care workers misinterpreting the degree of impairment and the underlying causes for the behaviours. Consequently, there can be a high degree of care burden due to difficulties managing behavioural symptoms and poor understanding of the same.
A case study approach was used to investigate the impact of non pharmacological interventions in managing behavioural symptoms of FTD for three older people in residential care facilities. The Queen Elizabeth Behavioural Assessment Graphical System and Zarit's modified Care Burden Interview were used to assess behavioural symptoms and care worker stress respectively prior to and following the implementation of a comprehensive individualised behaviour management plan.
Reductions in both behavioural symptoms and care worker stress were achieved and all people were able to remain in their residential care facilities instead of being moved.
Modifying the environment and approach used together with providing appropriate activities and education can assist care workers in more effectively managing behavioural symptoms in people with FTD.
PS02.4
Validity and reliability of the Cornell scale in a Norwegian patient sample
Maria Barca1; G Selbaek2; K Moksnes3; E Aakhus4; I Ulstein1; O Baekkedal5; K Engedal1
1Norwegian Center for Ageing and Health, Oslo, Norway; 2Innlandet Hospital Trust, Ottestad, Norway; 3Vardaasen, Ullevaal University Hospital, Oslo, Norway; 4Innlandet Hospital Trust – Reinsvoll, Reinsvoll, Norway; 5Innlandet Hospital Trust – Sanderud, Sanderud, Norway
Background: Around 20–50% of patients with dementia have depressive symptoms/depressive disorder. Cornell scale is considered to be the best scale to rate depressive symptoms of depression in demented patients. Studies from different countries have showed that the scale has good reliability and validity. It is translated to Norwegian, but no validity study has been performed.
Objectives: The objective is to investigate the scale's reliability and validity. This is an ongoing study.
Methods: The inter-rater reliability study will include 60 patients with and without dementia, 30 in nursing homes and 30 in a department of old age psychiatry. These patients will be evaluated by two nurses who are present at an interview with the primary caregivers of the patient. They will independently score the patients symptoms according to the Cornell scale. So far 47 patients are included.
The validity study will include 200 patients with and without dementia: 70 from three nursing homes, 70 from three departments of old age psychiatry and 60 from a geriatric department. The patients are examined by psychiatrists, which have access to the patient's records. Diagnosis of depression will be made according to the diagnostic criteria of ICD-10, DSM-IV and a revised version of the Provisional diagnostic criteria for depression in Alzheimer's disease in cases where the patients has a diagnosis of dementia or MCI. The psychiatrist s are ‘blinded’ to the Cornell scale score. The patients are evaluated with the Cornell scale by a research nurse, who also interviews the primary caregiver of the patient. In addition age, gender, ADL function, CDR score, MMSE score, use of medication and information about diseases are collected. So far 98 patients are included: 68 from nursing homes, 27 from old age psychiatry and 3 from geriatric medicine.
Results: In the reliability study, 11 men, mean age 81 years (sd = 7.9) and 36 women, mean age 85 years (sd = 7.7) are included. Of them 21.3% have MCI and 65.9% dementia, whereas 42.6% has depression according to ICD-10. Cronbach's alpha of Cornell scale is 0.99; Spearman rho between sum scores of the raters is 0.94 and average Kappa is 0.90 (0.78–1.00).
In the validity study, 26 men, mean age 81 years (sd = 8.3) and 72 women, mean age 84 years (sd = 7.8) are included. Of them 13.5% have MCI and 73.4% dementia, whereas 41 (41.8%) have depression according to ICD-10, 27 (27.6%) according to DSM-IV and 37 (37.8%) according to PDC-dAD. The best cut-off was 7/8, see table.
Conclusion: The Norwegian version of the Cornell scale has good reliability and fairly good validity. The best cut-off is 7/8.
PS02.5
Enhancing early detection: Proactive screening for dementia for people with Down's syndrome
Ben Hobson1; D Webb1; L Sprague1; M Grizzell2; S Benbow2
1Wolverhampton PCT NHS, Wolverhampton, United Kingdom; 2Wolverhampton PCT NHS, Wolverhampton, United Kingdom
Aims: There is an increased risk of developing dementia for people with Down's Syndrome as they age. Considering the difficulties inherent in assessing and monitoring deterioration in this population, there is a need for preliminary screening to be carried out. A proactive screening project was established in Wolverhampton, a multicultural city in central England with a population of approximately 250,000, to identify those individuals who had a current diagnosis of Down's Syndrome, were aged over 30 years old and did not have a current diagnosis of any dementia-type illness. This project is intended to fill the gap in services between Learning Disabilities and the Memory Clinic, which is part of the old age psychiatry service and co-ordinates anti-dementia treatment for people of all ages who develop Alzheimer's disease.
Method: The Broad Screen Checklist of Observed Changes (BSCOC) is an informant-based measure of general functioning and abilities of an individual. The measure covers six domains: Health, Physical Competencies, Sensory Integration, Perceptual/Cognitive, Social/Emotional, Activities of Daily Living as well as a total overall score. Individuals who present with changes in certain domains can then be referred to the appropriate services for a more comprehensive assessment and monitored further using the BSCOC. Individuals who are not referred are re-screened with the BSCOC annually.
Results: As of 15th March 2009, 62 individuals have been identified who are eligible for screening. Currently 32 have been screened with 13 individuals referred to the Dementia Care Pathway for further investigation. This compares with 11 individuals who had been diagnosed with dementia in the past three years using a reactive service.
Discussion: Proactively identifying and screening individuals to provide a baseline measurement is of importance to assist in diagnosis of dementia, otherwise this at risk group may not have early appropriate access to anti-dementia drug treatment and other interventions. The BSCOC by its very nature assesses a broad range of domains which may signpost health professionals to appropriate support more accurately. Links between the Learning Disability Service and the Memory Clinic are being developed to ensure these individuals receive appropriate and timely support. Individuals diagnosed with dementia are also being supported to access mainstream Old Age Psychiatry and Psychology Services.
PS02.6
Cross-national elderly suicide rates and socioeconomic status
Ravi Bhat1; A Shah2
1The University of Melbourne, Shepparton, VIC, Australia; 2University of Central Lancashire, Preston, United Kingdom
Socioeconomic status may influence cross-national variations in elderly suicide rates. The relationship between suicide rates for older adults 65 years and older in both sexes various socio-economic and related measures was evaluated. The measures included per capita gross domestic product (GDP), income inequality (as measured by the Gini coefficient), the proportion of GDP spent on health, per capita expenditure on health and child mortality rates along with life expectancy. Cross national suicide data and most measures were collected from the data provided by the World Health Organization while data on income equality was obtained from the United Nations website.
There was no significant correlation between GDP and suicide rates in most age bands studied however there was a significant negative correlation between the Gini coefficient and elderly suicide rates. There was a significant positive correlation between per capita expenditure on health and elderly suicide rates. In contrast there was significant positive correlation between the proportion of GDP spent on health and suicide rates for only males. There was also a significant correlation between the elderly population size and the proportion of elderly in the population and elderly suicide rates. In addition there was a significant negative correlation between child mortality rates and elderly suicide rates.
There are methodological limitations concerning validity of cross-national data. However, the data considered in this study was the best available data and evaluation of distal risk factors may help development of public health preventative strategies. It is likely, as suggested by James Riley that income is an enabling factor, which boosts or diminishes life expectancy depending how it is spent. In this study per capita GDP was significantly positively correlated with the proportion of GDP spent on health, per capita expenditure on health, and life expectancy for both males and females and significantly negatively correlated with the Gini coefficient. Thus higher income may in the first instance be positively associated with elderly suicide rates by both increasing the elderly population size. Later these effects may be modified depending in whether this leads to increased provision of healthcare services for the elderly. The significant negative correlation between income inequality and elderly suicide rates is more difficult to explain. In this study the countries with lower GDP were more likely to be associated with higher income inequality. This suggests that overall proportion of elderly in the population is lower and also raises the possible role of economic adversity in elderly suicides. Moreover, other studies have noted a positive correlation between income inequality and suicides of younger people, which suggests that there may be lower number of people living to the age of risk.
It has been noted that the achievements of high-income countries in increasing survivorship has come with capital intensive investments, more recently poorer countries have achieved similar results with strategies of social development without first becoming rich (Riley, 2001). The question to be explored is whether poorer countries can compensate for distal effects on elderly suicide rates with innovative, relatively low-cost programs.
PS02.7
“Attention: Prevention!” Sniffing around the nursing home for sources and strengths
Theresia Botteram
Stichting voor Regionale Zorgverlening, Middelburg, Netherlands
In a training-programme for teams of nurses on psychogeriatric and psychiatric wards of our nursing home, we try to explore and develop tools to search for sources and strengths. Not only within the clients, to help them discover and translate their needs and wishes, but also within themselves, to enhance their skills and their—and the clients'—quality of life, thus creating parallel processes.
For our training, we borrowed from the ABC-cognitive behavioral and mediation techniques (Hamer and Voesten, 2006), The Strengths Model (Rapp and Goscha, 2005) and from the concept of a Plan for Early Detection of signals and symptoms (Van der Werf, Huiberts and Goedhart, 1998).
The team is challenged to contribute to the content and development of the education-programme in every possible way and to immediately integrate the newly acquired knowledge and skills while working with the clients.
The hypothesis is that, by discovering and using “Uplifting Balloons” and avoiding and eliminating “Weighing Bricks” in thought, feeling and action of both clients and nursing-staff, we can diminish the use of behavioral disturbance oriented medication. This is the focus of the ward's geriatrician, while the clinical gerontologist, familiar with both clients and team members, is functioning as the trainer.
Interaction, new ideas and fun are considered as essentials during the training and on the overall Prevention Mission in our nursing home.
PS02.8
A computerized memory training protocol for people with depression and cognitive deficit
Valentin Bragin; M Chemodanova; A Vaysman; I Bragin; E Grinayt; P Chernyavskyy
Stress Relief and Memory Training Center, Brooklyn, NY, United States
Background: Cognitive deficit often accompanies depression in elderly people. We postulate that cognitive training may be considered as an important adjunct modality to be utilized alongside a traditional treatment regimen of medication and psychotherapy.
Objective: The goal of this presentation is to describe a unique memory training protocol for depressed, cognitively impaired patients and present first training session data.
Design: 34 geriatric, computer-naïve, medically ill patients with mild to moderate depression and concomitant memory problems participated in cognitive training; this was their first experience with this protocol.
Materials and Methods: 12 male and 22 female patients (age 77.8 ± 5.4, education 14.1 ± 3.1) participated in this training. They were initially evaluated by the Mini Mental Status Exam. An original, computerized training protocol has been developed for use with different visual targets; for this trial, the target utilized was flowers. The protocol consists of two parts. The first part is a 40 trial N-back task (3-back task). The patients were required to identify pictures shown for the first time as a new picture and then recognize pictures that were presented before. Approximately 25% of the pictures were displayed a second time for recognition. The second part is a learning task. During the learning task, the patients memorized a set of 10 simultaneously presented targets (pictures). The pictures appeared on the screen for multiple trials. After every trial, the patients selected these targets among 10 additional computer-generated targets. The trials continued until the patients memorized the maximum number of targets. Then the patients were asked to recognize these same targets five minutes later. Performance and errors were calculated for both tasks. Descriptive statistics and Spearman Correlations were performed on SPSS 16.
Results: MMSE score ranged from 23 to 30 (28.4 ± 2.2). For the N back task performance was 7.2 ± 2.5 and total errors were 7.9 ± 4.3. For the learning task, after the first trial, performance was 5.6 ± 2.2 and errors (intrusions) were 3.3 ± 2.1. In the learning task, the minimum number of steps to achieve maximum results was 4.2 ± 1.6; maximum performance was 9.4 ± 1.1. Performance on five minute recall decreased to 7.9 ± 2.4 and the number of errors were 1.9 ± 2.1. No significant correlations were seen between performances on the two tasks. Total errors on the N-back task were positively correlated with first trial errors on the learning task (r = .426, p < .001) and negatively correlated with five minute recall performance on the learning task (r = −.372, p < .003).
Conclusion: A cognitive memory training protocol was designed as a part of an integrative treatment program for depressed, cognitively impaired, medically ill elderly people. The training was well tolerated and had a positive impact on the patients' emotional state. Future research needs to be done to evaluate the efficacy of this protocol.
PS02.9
Referrals and clinical outcomes in a rural Old Age Psychiatry service over a three year period
K Carroll1; Ravi Bhat2
1Centre for Older Persons Health, Shepparton, VIC, Australia; 2The University of Melbourne, Shepparton, VIC, Australia
We analysed all referrals and clinical outcomes to a rural Old Age Psychiatry Service in Victoria, Australia over a three year period from 2004 to 2006. Goulburn Valley Area Mental Health Service is a rural service based in Shepparton 190 kms from metropolitan Melbourne, with a catchment area of 22, 000 square kms with approximately 18, 000 people aged 65 years or above. The service currently has five aged inpatient beds that co-exist with 15 adult inpatient beds in a common unit.
We had 419, 337 and 419 referrals in the years 2004, 2005, 2006 respectively. The median age of people referred was 76 years. Most of the referrals for all three years were from General Practitioners (GPs) either directly or indirectly; about a quarter of the referrals were from residential aged care facilities and; about 10–15% were either self referred or from family members. 66% of those referred were taken up for detailed assessment. This figure rose from 58% in 2004 to 70% in both 2005 and 2006. Nearly 90% of those assessed were provided with treatment and follow-up. Around 40% of the people assessed lived at a distance between 50 km to 150 km away from Shepparton. A quarter of those assessed had a primary diagnosis of dementia and another quarter had a mood disorder. Delirium was diagnosed in nearly 10% of the cases and functional psychoses in another 10%. 8% were diagnosed with the ICD-10 category of “neurotic, stress-related and somatoform disorders” which in this instance mainly comprised of anxiety and adjustment disorders. Interestingly 9% of cases received no psychiatric diagnoses following a detailed assessment. Diagnostic data was missing in 8% of the cases. Of all the people assessed only 12% were admitted to the inpatient unit. The bed occupancy rate for this period was 57%. More than three quarters of the admissions were for either mood disorders or functional psychoses. Patients with delirium and dementia were rarely admitted.
The tyranny of distance was a major obstacle to assessment. This has a major influence on time taken to travel and coordinate services, especially for those people living in the community. Although >90% of elderly in Australia live in the community nearly half the referrals in our study were from hospitals or residential care facilities. This is an understandable consequence of the high rates of cognitive impairment, physical co-morbidity and functional decline seen in people in these settings. The rate of acceptance for detailed assessments increased from 2004 to 2006. The reasons for this increase are unclear however of note was that the triage process was more closely monitored from the year 2004.
Dementias and mood disorders were commonly diagnosed however only those with mood disorders and psychotic disorders were more commonly admitted to the inpatient unit. Use of inpatient facility was limited and this is likely to be due to the co-location with adult inpatient beds. As a result the service has decided to move the five inpatient beds to an independent location.
PS02.10
Post-operative delirium: Search for biomarkers
Joaquim Cerejeira1; V Nogueira1; P Batista1; H Firmino1; E Mukaetova-Ladinska2
1Hospitais Universidade Coimbra, Coimbra, Portugal; 2Newcastle University, Newcastle, United Kingdom
Post-operative delirium is known to be a frequent and often under-recognized disorder in elderly patients undergoing major surgical procedures, especially in the acute clinical setting. Delirium is independently associated with adverse outcomes consisting not only in increased hospital stay, morbidity and mortality at the short term but also long term effects such as cognitive and functional deterioration and higher rates of institutionalization. Early recognition of delirium and prompt preventive measures can improve the outcome of patients and have important implications on the quality of health care. Although many predictive models were developed, based on pre-, intra- and postoperative risk factors, there is still no reliable method to identify preoperatively the likelihood of postoperative delirium in a particular patient. Furthermore, clinical assessment of delirium, even with brief tools such as Confusion Assessment Method (CAM), is time consuming and is heavily reliant on subjective observations that are vulnerable to the fluctuating presentation of delirium. Recent evidence based on animal studies revealed that the presence of peripheral immune signals culminates, through a complex system of communication involving the blood-brain barrier, in the activation of microglial cells and the production of cytokines in the brain, thus ultimately causing neuronal dysfunction.
In the current presentation, we will review the existing data about peripheral biomarkers for delirium, translating the results from previous research into clinical practice, and we will present preliminary results from an ongoing study in patients over 60 years old undergoing elective hip replacement in the Orthopaedic Department of Coimbra University Hospitals (Portugal). Identifying blood biomarkers as neurobehavioural correlates of an exaggerated neuroinflammatory response following peripheral immune activation will guide the development of sensitive and specific blood test to predict, diagnose and monitor delirium in the elderly. Sensitive biological markers are important to assist in the risk assessment, early detection, diagnosis and monitoring of delirium in order to minimise the long-term disability and poor outcome associated with this condition in the elderly.
PS02.11
Subjective memory complaints, satisfaction with life and cognitive function in an elderly institutionalized population
T Santos2; Nuno Madeira1; S Rocha3; J Cerejeira1
1Hospitais Universidade Coimbra, Coimbra, Portugal; 2Hospital Infante D. Pedro, Aveiro, Portugal; 3Fundação Luíz Bernardo de Almeida, Vale de Cambra, Portugal
Evaluating the nature and severity of psychiatric symptoms in the elderly is often a difficult task, either due to difficulties in speech and cognition or to overvalued beliefs and worries about a potential mental deterioration. Memory loss, in particular, is a very common symptom, which can occur related to disorders such as depression or dementia, but also as a subjective complaint underlying a more generic dissatisfaction and detachment from life interests. In other cases, memory impairment is underestimated by patients with lack of insight.
The authors studied a population of 100 elderly patients admitted in a nursing home for more than 6 months prior to the study. Portuguese versions of 5 psychometric instruments were applied: MMSE—Mini-Mental Scale Examination (Folstein et al. 1975); GDS—Geriatric Depression Scale (Yevesage et al. 1983); SMC—Subjective Memory Complaints (Schmand et al. 1996); SWLS—Satisfaction With Life Scale (Pavot & Diener 1993) and GDS—Global Deterioration Scale (Reisberg et al. 1982).
The authors address the results obtained, and their relation with the existing literature, in particular the correlations between subjective memory complaints and levels of satisfaction with life. The focus is also put on the relation between those two constructs and the degree of cognitive function.
PS02.12
Late-onset bipolar disorder
Nuno Madeira1; T Santos2; J Cerejeira1
1Hospitais Universidade Coimbra, Coimbra, Portugal; 2Hospital Infante D. Pedro, Aveiro, Portugal
Bipolar disorder is a condition that commonly arises in late adolescence and early adulthood, although in a substantial proportion of patients the onset happens later in life. More than 10% of new-onset mania cases have been found to occur in individuals over 50 years. Bipolar disorder accounts for 10% to 25% of all geriatric patients with mood disorders and 5% of admissions to psychogeriatric inpatient units.
However, while bipolar disorder in old age is a growing public health problem, there is a relative paucity of published data about late-life manic episodes. Geriatric bipolar disorder has in fact been relatively neglected in comparison with research conducted on younger populations.
Late onset bipolar disorder (LOPD) may be more strongly associated with organic factors, such as cerebrovascular risk; neuroimagiological studies of older bipolar patients have documented a greater prevalence of findings such as white matter hyperintensities. In addition, differences in treatment response and prognosis have also been reported in LOBD patients. Evidence concerning cognitive decline has arisen. Frequent medical comorbidities present additional challenges to clinicians.
The authors present the clinical case of an elderly woman whose admission was due to a first manic episode. Based on current literature, they conduct a critical review of clinical, pathophysiological, and management issues regarding late-onset bipolar disorder.
PS02.13
Verbal fluency, but not apathy or agitation, correlate with cortical thickness in Alzheimer's disease
H Tayeb2; E Nikelski1; A Evans2; Howard Chertkow1
1Jewish General Hospital, Montreal, QC, Canada; 2McGill University, Montreal, QC, Canada
Objective: To assess whether major forms of behavioral abnormalities (specifically apathy, and agitation) in Alzheimer's disease (AD) correlate with cortical thinning in specific brain regions such as frontal lobes.
Rationale: A major goal of neuropsychiatry is to establish brain/behavior correlations for psychiatric symptoms. There is evidence (largely from functional imaging) to suggest that apathy and agitation relate to neurochemical and functional changes in frontal lobe structures. Lesion and anatomic (MRI) imaging evidence (as well as functional) points to the localization of cognitive functions such as categorical fluency in the frontal lobes as well. There have been few large scale comparisons of anatomic imaging with both sets of deficits to compare the robustness of these localizations—i.e. are neuropsychiatric symptom complexes localized in the brain to the same degree as cognitive deficits?
Methods: T1 volumes for 160 AD subjects (Ages: 57–91, mean = 75, MMSE scores: 20–27, mean = 23.2) were acquired from the ADNI (Alzheimer Disease Neuroimaging Initiative) database, and processed at the Montreal Neurological Institute by a fully automated analysis pipeline. Cortical surfaces were used to extract cortical thickness values at 40,962 vertices. Statistical analysis consisted of regressing cortical thickness onto cognitive (verbal fluency for categories) and neuropsychiatric (apathy and agitation scores from the short version of the Neuropsychiatric Inventory, NPI) measures.
Results: Verbal fluency scores correlated significantly with cortical thickness measures in the left posterior/superior temporal, anterior temporal, and middle and inferior frontal regions. Similar regions were correlated (but far less extensively) on the right side. Neither apathy or agitation measures correlated with cortical thickness in any brain region.
Discussion: Cortical thinning in AD correlated with impairment in fluency in regions predicted through lesion studies and functional imaging. In contrast, previous brain/behavioral correlations for the neuropsychiatric abnormalities in AD failed to be supported. Four reasons (separately or together) might explain this discrepancy; the impairment is chemical/functional and not anatomic, the localization is more variable than for cognition, the measures used were too imprecise, or the constructs themselves are too heterogeneous to support localization. Further work will be needed to distinguish these possibilities.
Acknowledgements: ADNI, CIHR (Canada), and King Abdul Aziz University, Saudi Arabia.
PS02.14
Early identification of adverse dopaminergic and serotonergic medication side effects within geriatric rehabilitation and long-term care settings: Staff knowledge and importance of continuing education
Paul Clements1; S Bauer2
1Insight Health Network, Margate, FL, United States; 2Functional Pathways, Knoxville, TN, United States
Medicines that affect dopaminergic and serotonergic neurotransmission are increasingly used within geriatric rehabilitation and long-term care settings for a variety of psychiatric and non-psychiatric conditions. In many cases these medicines are not prescribed by or routinely monitored by geropsychiatric specialists. The authors opine that the potential risk for disability or death related to failure of timely identification of neuroleptic malignant syndrome, serotonin syndrome and extra-pyramidal symptoms necessitates that all professional staff working in facilities that care for older adults possess basic knowledge of these medicines syndromes. Data from a convenience sample drawn from a geographically diverse group of non-physician, geriatric healthcare professionals indicates considerable lack of knowledge regarding the potential for these medicines to produce serious side effects. The authors propose a strategy to remedy the knowledge deficit, improve medication monitoring and reduce adverse outcomes.
PS02.15
Psychotropics and antiepileptic drugs among old people with learning disabilities: A preliminary report
Ennio Cocco
Institution de Lavigny, Lavigny, Switzerland
Background: Aging of people with learning disabilities is growing up in developed countries. In fact, these last years, there has been a rise of life expectancy for individuals with mental retardation because of many factors, including a better epilepsy management. In the same way, utilization of psychotropic drugs is increasing in this population. Little is known about poly-pharmacy among old people with intellectual impairment, and especially about the dimensions of psychiatric problems linked to epilepsy among the aging population living in long-term care institutions. Moreover, little is known about the possible role of epilepsy and antiepileptic drugs in cognitive decline among individuals with intellectual disabilities.
Aim: To investigate the topic of the double prescription of antiepileptic (AE) and neuroleptic (NL) drugs, in the context of a wider research project concerning the problem of poly-pharmacy among old people with learning disabilities, especially psychotropic poly-pharmacy.
Methods: Two samples of people with learning disabilities were studied, the first one living at an institution with a neurological (antiepileptic) mission, the second one living in a long-term facility without neurological or medical mission. A descriptive, cross-sectional survey of the pharmacological treatment patterns was made. Only chronically (daily) administered drugs were take into account. All residents over sixty have been included in the survey.
Results: In the first institution 26 subjects were eligible by the age criteria, 12 males and 14 females (age range: 60–80 years). In the second institution 6 subjects were eligible, 4 males and 2 females (age range: 62–74). Finally, the whole sample was of 32 residents, 16 males and 16 females. All subjects received drugs, with a span between a minimum of 2 up to 15 substances prescribed. 29 subjects (90.6%) were under poly-pharmacy (five drugs or more). Only 2 subjects over 32 (6.3%) were free from psychotropic and antiepileptic drugs. 9 subjects (28.1%) received AE drugs (one or more), 9 (28.1%) received NL drugs, 12 (37.5%) received both (AE and NL drugs) and 2 subjects (6.3%) received none.
Discussion: Poly-pharmacy is probably very common among institutionalized old people with learning disabilities; psychotropics utilization, particularly neuroleptics, too. From a preliminary, descriptive point of view, the treatment for epilepsy seems associated to an increased exposition to the neuroleptic prescription.
Conclusion: More research is needed, to better explore the management of problem behaviour (linked to epilepsy or not) in aging people with intellectual deficits and their links with cognitive decline.
PS02.16
Prevalence and detection of depression and impact of cognitive enhancers on neuropsychiatric symptoms in nursing homes in elderly patients with Alzheimer's disease and related dementia
Jean-Francois Cote1; F Rousseau1; C Hudon2; N Gagnon1; A Bureau3
1Laval University, Quebec, QC, Canada; 2Laval University, Quebec, QC, Canada; 3Laval University, Quebec, QC, Canada
Objectives: Dementia and depression are two of the most prevalent psychiatric disorders affecting nursing home residents. However, the diagnosis of depression complicating dementia is often overlooked. The objectives of this study are: to establish the prevalence of depression in nursing home patients with dementia; to evaluate the ability of the nursing home clinical team to detect depression in this population of patients; and to establish the prevalence of neuropsychiatric symptoms in this population of patients and the impact of cholinesterase inhibitors and memantine on these symptoms.
Method: We conducted a cross-sectional study of detection and prevalence of depression among nursing home subjects aged 60 years and older suffering from Alzheimer's disease, mixed dementia or vascular dementia and living in Quebec City. The Cornell Scale for Depression in Dementia (CSDD), Neuropsychiatric Inventory (NPI), Quality-of-life in Alzheimer Disease Scale (QOL-AD), Structured Clinical Interview for DSM-IV (SCID-IV), Mini Mental State Examination (MMSE) and the Global Deterioration Scale/Functional Assessment Staging (GDS/FAST) were administered to each subject. There were also a chart review and a nurse interview prior to subject examination. Clinical assessment and chart review were conducted by independent blinded raters.
Results: We identified 252 subjects from eight nursing homes. Of those, 98 were included (38.9%), 90 were excluded (35.7%) and 64 declined consent (25.4%). Mean age of our sample of 98 subjects was 85 years (SD 7.0). Forty-five percent had Alzheimer's disease, while 29% had mixed dementia and 26% had vascular dementia. Forty-six percent of the subjects were taking an antidepressant, and 26.5% were taking a cholinesterase inhibitor. Only one subject was taking memantine. Mean scores on the rating scales were as follows: MMSE 13 (SD 7.3), NPI total 15.7 (SD 16.1), CSDD 4.3 (SD 3.2), QOL-AD 34.5 (SD 4.4) and GDS/FAST 6. We found 14 active cases of depression among the 98 subjects, while only 5 of them had been identified by the primary care team (prevalences of 14.4% vs 5.1%, p = 0.004; sensitivity of detection by the primary care team of 35.7%, 95%CI 10.6–60.8). There was not a statistically significant difference of mean NPI total score between those treated and untreated with a cholinesterase inhibitor (12.7 vs 16.8, p = 0.267), and no difference either between those with and without an antidepressant (15.8 vs 15.4, p = 0.904).
Conclusion: Our results indicate that depressive syndromes are highly prevalent among nursing home residents who have dementia. However, they remain significantly underdiagnosed. While neuropsychiatric symptoms appear to be prevalent as well, cholinesterase inhibitors or antidepressants do not seem to have a significant impact on them.
PS02.17
Constraints: A treatment for patient security? A process of thought-out care
N de Mul2; L Englebert2; Michael Schuerch1
1ISoCL- Pérî, Liege, Belgium; 2Intercommunale des Soins Spécialisés de Liège, Liège, Belgium
The geriatric pole of the Intercommunale de Soins Spécialisés de Liège (ISoCL), Belgium, cares for elderly patients, acute and subacute geriatric, neurological, psychogeriatric, revalidation and palliative care settings. The main objective is to guarantee efficient, safe and acceptable care for all patients.
Our daily task is to approach our patients in their globality. To do so, we must take into account their diverse associated physical ailments and the severity of their diseases. In the process, we can never lose sight of their dignity and quality of life. Thus, we need projects and strategic approaches permitting risk management while maintaining security.
The first reason given for constraints is the security of the patient. Whereas the first responsibilities of a nurse are to care, to comfort and to help maintain the patient's autonomy. It can then seem paradoxical to impose care under constraint and to deprive elderly, fragile patients of their liberty. Even though the serious risks tied to the use of constraints are well known, they are used daily in our units. This implies that we must put into place adequate means and procedures, otherwise the quality of care risks being contested by those being cared for resulting in a loss of confidence and conflict.
Different motivators, such as the legislation, guidelines, and caregiver interest led us to conduct a project on physical constraints using the cycle of continuous quality improvement (the Deming wheel). A plan of action was elaborated by a pluridisciplinary team with the following objectives:
– Inform the patient and his entourage.
– Assure secure and comfortable care.
– Promote alternative methods among the caregivers.
– Develop tools of good professional practice.
– Assure the traceability of information and surveillance.
– Inventory.
To begin with, however, we wished to do a study on all patients in our two clinics so as to respond to different questions such as prevalence, the material used, the reasons and objectives given for this treatment. Among the actions undertaken, we created care procedures specific to the Belgian context, including all aspects of physical constraint. To support this procedure, different documents were created such as a reference care plan, a care diagram permitting continuous notification of constraint and material used as well as an informative brochure for patients. This approach allows caregivers to decide objectively and ethically, whether to constrain the patient or not. The patient and his family are included in this decision process. Training centered on a multidisciplinary approach allowed us to implement this project. A second prevalence study will be organized to evaluate the impact of this training.
Ultimately, our hope is that the instauration of constraints will be the result of a methodic, rigorous and humane process. It will take into consideration all possible alternatives. It will permit us to opt for the most efficient and less restrictive measures so as to insure best security for the patient and to guarantee that constraints will never be used to blackmail, put under pressure or to repress.
PS02.18
Correlates of the perception of benefits of using health services for a mental health problem
Karine Demers1; M Préville2; M Dubois1
1Research Center on Aging, University of Sherbrooke, Sherbrooke, QC, Canada; 2Hôpital Charles LeMoyne's Research Centre, Greenfield Park, QC, Canada
Several studies showed that attitudes toward health services impacted the decision to consult. Particularly, it has been suggested that the perception of benefits was an important determinant of the health services utilization. However, no study was conducted to document factors associated with the perception of benefits of using health services for a mental health problem in the older adult population. The data used in this study stems from the Senior's Health Survey (2005–2007). The population consists of persons 65 years of age and older, non-institutionalized, French-speaking, and without cognitive impairment (MMSE ≥ 22) (n = 2798). Perceived benefits of using health services for mental health problems was partly measured using a French adaptation of four questions from the Emotional/Nervous Benefits Scale developed by Saleeby (2000). A multiple linear regression analysis using a backward elimination procedure was conducted to estimate the uncounfounded effect of the potential predictors studied. Our results showed that age (p = 0.000), annual family income (p = 0.001), geographical area (p = 0.000), social support (p = 0.037), number of depressive and anxious symptoms (p = 0.000), perceived physical health status (p = 0.030), concerns about health (p = 0.000) and level of stress (p = 0.036) were significant correlates of the perception of benefits. We suggest that the sensibilization activities aiming to encourage health services utilization for mental health problems focus on the specificity of sub-groups of old people rather than on a uniform strategy.
PS02.19
Verbal cued recall is a better predictor of conversion to Alzheimer's disease than visual cued recall
Eva Dierckx1; S Engelborghs2; R De Raedt5; M Van Buggenhout4; P De Deyn3; I Ponjaert-Kristoffersen1
1Vrije Universiteit Brussel, Brussels, Belgium; 2Middelheim General Hospital (ZNA), Antwerp, Belgium; 3University of Antwerp, Antwerp, Belgium; 4University of Antwerp, Antwerp, Belgium; 5Ghent University, Ghent, Belgium
Background: With the ongoing development of new disease-modifying treatments for Alzheimer's disease (AD), there is an increasing need for early diagnosis. This study was set up to investigate whether tests of cued recall are able to predict conversion to AD among Mild Cognitive Impairment (MCI) patients.
Methods: At baseline the cognitive part of the Cambridge Examination for Mental Disorders of the Elderly (CAMCOG), the Mini Mental Status Examination (MMSE), the Geriatric Depression Scale (GDS), the Memory Impairment Screen plus (MISplus; a verbal cued recall task) and the Visual Association Test (VAT; a visual cued recall task) were administered to 40 patients of a memory clinic diagnosed with MCI (according to Petersen's criteria). After approximately 3.5 years, a follow up diagnosis was established. Of those who were seen for follow up (n = 27), 17 fulfilled (NINCDS-ADRDA) criteria of probable AD (i.e. converters), while 10 did not convert to dementia (i.e. nonconverters).
Results: After a binary logistic regression analysis with the MISplus and the VAT as independent variables, only the MISplus remained in the analysis.
Conclusion: This prospective, longitudinal study showed that the MISplus, a delayed verbal cued recall test, is a better indicator of conversion to AD than the VAT, a visual cued recall test.
PS02.20
Advance directives for those who lack capacity and their importance in “Living well with dementia” (tertiary prevention)
Paul Divall
AWP NHS Trust, Bath, United Kingdom
A description and review of the law and its implementation in England: Advance refusals are now enshrined in English law following implementation of the Mental Capacity Act 2005. The presentation will look at advance refusals and the validity of advance statements in the English jurisdiction, hoping to engage debate with those from other jurisdictions around the issues of advance directives. (Part of the “Living well with dementia” programme from the National Dementia Strategy of England and Wales)
PS02.21
Reconnecting the social network of the elderly mentally ill: Social connection in German psychogeriatric day hospitals
Lutz Drach
HELIOS-Kliniken Schwerin, Schwerin, Germany
Lack of social activities increases the risk of mental disorders, especially depression, in the elderly considerably. During the course of a mental disorder elderly patients are often affected by loss of social role and relations. The prognosis of depression in old age depends on the successful reconnection of the patient's social network.
Two surveys in the 60 German psychogeriatric day hospitals using a questionnaire demonstrated that some kind of social connection on a regular basis is performed in the vast majority of these institutions.
Most day hospitals used local facilities for healthy senior citizens for connection of their patients, alone or in combination with the attendance of specialized activities for the mentally ill (e. g. psychogeriatric day centers). Only a small number of day hospitals were activating in psychiatric institutions alone. Only five day hospitals are activating their patients in social activities for the healthy elderly without the presence of staff from the beginning. In the majority of settings patients are accompanied by staff during their out-of-hospital activities. The differences in the ways of social connection between the day hospitals may be due to different patients, differences in availability of facilities for healthy senior citizens or other local peculiarities.
PS02.22
The Hospital Dementia Services Project: A mixed methods approach to assess outcomes for people with dementia admitted to hospital
Brian Draper1; D Gibson2; A Peut3; R Karmel3; P Anderson3; L York3; I Seebus3
1University of NSW, Randwick, NSW, Australia; 2University of Canberra, Canberra, ACT, Australia; 3Australian Institute of Health and Welfare, Canberra, ACT, Australia
Background: People with dementia are relatively high users of hospitals; however, there is considerable evidence that hospitals can be hazardous places for them with prolonged length of stay, increased risk of delirium and a strong association with entry into residential aged care post discharge. It is hypothesised that hospitals that have the resources and policies that focus on quality dementia care will have better outcomes. This presentation describes a mixed methods approach of examining the relationships between service delivery in public hospitals and outcomes for persons with dementia in the state of New South Wales (NSW), Australia (total population 6.9 million) in 2006–2007.
Aims: To explore whether hospital-based aged care and dementia services influence outcomes for people with dementia who are admitted to hospital; and to determine whether the level and mix of these services is associated with different patient outcomes, including lower rates of discharge to residential aged care services.
Methods: The project's innovative research design takes a mixed-methods approach that facilitates the integration of analyses at the patient, hospital and regional levels in NSW during 2006–2007. Data linkage by the Australian Institute of Health and Welfare (AIHW) of existing administrative datasets for public hospitals and key government-funded aged care programs will create a dataset of completed hospital stays (approximately 400,000) matched to post-hospital use of residential aged care services (approximately 35,000), allowing us to track the dementia patient's pathway through the system. A census of all public NSW hospitals (approximately 230) and key informant interviews in selected locations will provide information about hospital-based services, and explore the interaction between hospital aged care and dementia services and the community and residential aged care sectors. A classification of aged care planning regions in NSW will be developed according to operational community care and residential care places in each region.
Results: High stakeholder engagement is a central component of the study, and will ensure that the study provides findings that can be used to inform practice. Three hospital surveys have been developed and piloted (Aged Care Services, Specialist Mental Health for Older Persons Services, and a General Hospital Survey) and these will be undertaken during 2009.This process has involved an engagement with each of the eight area health services in NSW, Aged Care Services, Specialist Mental Health for Older Persons Services, and the NSW Health department. AIHW have developed the data linkage methodology and obtained the necessary administrative data for linkage.
Conclusion: The mixed methods approach adopted by this project has challenges and complexities in research design and analysis that will allow a better understanding of the types of services and their features which produce better outcomes for people with dementia.
PS02.23
Using social network analysis in assessment of structure and functioning of dementia networks
Irena Draskovic1; M Otero1; M Olde Rikkert2; M Vernooij-Dassen3
1Radboud University Nijmegen Medical Centre, Nijmegen, Netherlands; 2Radboud University Nijmegen Medical Centre, Nijmegen, Netherlands; 3Radboud University Nijmegen Medical Centre, Nijmegen, Netherlands
Background and Objective: It has become increasingly clear that network formation is essential for the provision of coherent care services in complex chronic care. In the Netherlands, examples of successful care networks are Palliative Care Networks, Parkinson Network (ParkNet), and, more recently, Dementia Networks. The aim of the present study is to explore the characteristics of dementia networks using Social Network Analysis.
Method and Analysis: A questionnaire was administered amongst the representatives of the organizations participating in dementia networks. Four care systems were distinguished: Primary, Secondary, and Tertiary care, and Other (e.g., local government, police, insurance companies). Possible network partners in the region were exhaustively listed in a table. The participants marked all of their actual partners and answered questions regarding the kind of contact (4 options), satisfaction with contact (scale 1–7), and need for more contact, per partner. Participants as well as their network partners were grouped into the four care systems (Primary, Secondary, Tertiary, and Other). Frequency of contacts was entered into a data matrix. Using NetDraw (UCINET suite, Analytic Technologies), we constructed a visual representation of the network, illustrating the degree of connectedness, centrality, and reciprocity of contacts between the 4 categories of providers.
Results:Clustering coefficient is the likelihood that any 2 nodes that are connected to the same node are connected themselves. For the present network the overall clustering coefficient was 21.00 (highest CC secondary care: 27,33). Reciprocity is the degree to which all relations are unidirectional. In the present study, Reciprocity was 0.5, indicating that 50% of the relations are unidirectional. Centralization is the degree to which a network approaches the configuration of a “star” (1 node at the center that connects to all other nodes; no nodes have connections to any other node except the central node). The centralization score is expressed as percentage and varies from 0 (every member is connected to every other member) to 100 (all members are connected to only 1 member). The centralization percentage thus indicates the degree of asymmetry in the distribution of connections in the network. A high centralization score (NetCentr) indicates that some members receive many more connections than others. High InDegree centralization indicates that only a restricted number of ‘nodes’ is ‘contacted’ by others, and high OutDegree centralization indicates that a restricted number of ‘nodes’ radiates ‘outbound’ connections. In the present study, NetCentr = 36.04%, Heterog. = 25.56%, Normal = 0.75%; NetCentrOut = 4.20%, and NetCentrIn = 57.06%.
Discussion: SNA was used to explore characteristics of dementia networks in the Dutch province of Gelderland. The results show that half of the network ties were reciprocal while clustering was shown to be the strongest for the Secondary care (ambulatory, specialist care). Both findings call for improvements in communication between the network participants, such as more frequent back-referral from secondary to primary and tertiary care. Centralization in the network was low to moderate indicating that there were no ‘stars’ in the network. InDegree centralization was higher than the OutDegree centralization indicating that most members in the network enter into relationships but not with all other categories of care providers. Comparison with the situation at T-2, will show effects of regional improvement actions on the network parameters
PS02.24
Prevalence of strain in nursing care of people with dementia in Sweden and Australia: Another step toward the development of preventive means
Anna-Karin Edberg1; K Anderson2; A Orrung Wallin1; M Bird2
1Lund University, Lund, Sweden; 2Greater Southern Area Health Service, Queanbeyan, NSW, Australia
Earlier research has shown that if personnel working in dementia care are satisfied with their work situation the quality of care increases. The formal caregivers' situation is thus an important factor concerning care quality in dementia care and increased knowledge about factors causing strain is an important step towards the development of preventive means.
Aim: The aim of the study was to investigate factors causing caregiver strain in dementia care in Sweden and Australia.
Methods: The sample consisted of 927 formal caregivers (RNs, LPNs, social workers and nurses aides) from Sweden and Australia (mean age 44 years, 94% women, mean work experience 11 years). A majority of the staff (85%) worked in residential care. Data was collected using the Strain in Dementia Care Scale (SDC-scale) that is under development. The current SDC-scale consists of (a) a demographic section, (b) 64 items where participants grade their experience of the frequency and amount of stress in relation to predefined situations, and (c) 11 emotions that the participants grade in relation to the presence in their daily work.
Results: The preliminary findings show that the most frequent situations were assessed to be related to personal care, that the residents were highly dependent on staff, did embarrassing things and when they themselves were not able to do as much as they wanted because of lack of time. Also, thoughts about how residents had been before they developed dementia were common. Significant differences were seen between the Swedish and Australian sample where the Australian sample assessed higher frequency on items related to emotional aspects such as worries about being emotionally affected and difficulties understanding the residents' needs. The Swedish sample assessed higher frequency for example concerning the use of restraints.
The most stressful situations were assessed to be when the staff could not do as much as they wanted because of lack of time, or saw that the residents suffered or did not receive the care that they were entitled to. The staff also experienced strain when the residents' families or the staff seemed to have difficulties understanding the effects of dementia, which influenced the way they behaved. Significant differences were seen between the Swedish and Australian sample on several items where the Australian sample generally reported higher stress. The most common emotion in relation to caring for people with dementia was joy/happiness and satisfaction, followed by sadness on clients' behalf and frustration.
Conclusion: Even though positive emotions were most common in their daily work, several aspects were highlighted as being stressful and causing strain. One of the most prevalent experiences was that they wanted to do so much more than they actually had the possibility to do. The analysis is ongoing and additional analyses concerning the influence of age, work experience and education will be made and presented at the conference. The data collected will also form the base for an investigation of the psychometric properties of the instrument, leading to a reduction of the number of items.
PS02.25
Phonetic versus semantic fluency in early Parkinson's disease
Eva Elgh1; M Domellöf2; L Forsgren2
1Geriatrics, Umeå, Sweden; 2Neurology, Umeå, Sweden
Tests of verbal fluency are designed to evaluate spontaneous production of words beginning with a given letter (phonetic association) or a given category (semantic association) within a limited amount of time. Prefrontal cortex has been shown to be involved in language functions in general and in verbal fluency in particular. Distinct and different brain structures in the prefrontal lobe and temporal lobe are involved in these different fluency processes. Parkinson's disease (PD) is a common neurodegenerative disorder with predominantly movement disabilities but also with cognitive difficulties early in the course of the disease. The aim of this study was to investigate phonetic and semantic fluency in early Parkinson's disease.
Methods: Patients were identified in a longitudinal population based study of idiopathic non-drug induced parkinsonism. 88 newly diagnosed patients with PD and no dementia were included during a four year period. The patients and 30 age- and sex-matched healthy control subjects underwent a comprehensive neuropsychological assessment including a test of phonetic and semantic fluency, the Controlled Oral Word Association (COWA) test.
Result: There were significant differences between PD-patients and controls in category fluency (p = 0.009) but not in letter fluency (p = 0.942).
Conclusion: The results indicate that brain regions involved in semantic association (right medial frontal gyrus) might be damaged early in the course of Parkinson's disease while brain regions involved in phonetic association (right medial and inferior temporal gyrus) are spared.
PS02.26
The geriatric psychopathology from the perspective of informational levels of the psychic model
Virgil Enatescu
County Hospital Satu Mare, Satu Mare, Romania
Psychic functions are based on the processing of significations. From this perspective, psychic functions can be approached as information. The information itself is structured on levels of complexity. The classic model of blocks of psychic functions does not present these levels. The informational levels we are considering are statistical, gnosic and heuristic Parallel with the continuous increase in the complexity of phenomena, the first level is the biophysical, followed by the biochemical level, the synaptic neuronal level, neuronal circuits, neuronal networks, non-reflected logical structures, the verbalization filter and the one of figurative representations, reflected logical structures, interpersonal communication and the microgroups’ noosphere. Both anthropology and ontogenesis presume humanization occurs with the structuring of verbalization filter, which allows the development of reflected thinking. To our surprise, similar conclusions have been reached by anthropologists like Timoty. Also, most psychopathological models in use now have an included space in the model and, consequently, have some common ground with it. The model was created and developed during 35 years of research, initially being accepted only by cybernetics, informatics, and, in the last decade, by psychiatrists.
The model has some relations with biological psychiatry, psychopharmacology, psychotherapy and some currently used models in psychopathology, in both practice and theory. Without excluding the validity of other perspectives, the model allows for an easier understanding and approach of normal and pathologic psychic phenomenon including geriatric psychopathological phenomena.
PS02.27
Estimates of caregiver time spent assisting with activities of daily living in an investigator-initiated clinical trial of galantamine
Sherri Fay2; L Hamilton2; K Rockwood1
1Dalhousie University, Halifax, NS, Canada; 2Capital District Health Authority, Halifax, NS, Canada
Alzheimer's disease (AD) is associated with the progressive deterioration of cognitive abilities, behaviour and self-care. As the dementia progresses, husbands, wives, offspring and siblings take on increasing responsibility for patient care. Several studies have shown that cholinesterase inhibitor therapy, such as treatment with the drug galantamine, can lessen carer burden, particularly in terms of time spent assisting with daily activities. We investigated whether that was the case in the Video Imaging Synthesis of Treating Alzheimer's disease (VISTA) study.
Methods: This is a secondary analysis of the VISTA study, a 4-month, investigator initiated, randomized placebo-controlled trial of galantamine in patients with mild-to-moderate AD (n = 130; mean age = 77, sd = 8; 63% women; 67% mild AD). At baseline and 4 months, carers completed an Allocation of Caregiver Time Survey (ACTS) indicating how much time (in hours and minutes) they spent assisting with activities of daily living (ADLs, for example bathing, dressing, meal preparation, shopping, transportation, etc.) on a typical day, and the number of days such assistance was rendered in the past week (summarized as hours per week). Information was also collected on the amount of time carers were able to leave patients alone on a typical day and whether carers felt additional supervision was required for patient safety (e.g. to prevent falls, wandering, etc.). We report differences by treatment group at baseline and 4 months (pla = placebo, gal = galantamine).
Results: The ACTS survey was completed by 119/130 carers at baseline (pla = 59, gal = 60) and by 99/109 carers of patients who remained in the study at the end of 4 months (pla = 49, gal = 50). At baseline, carers of patients randomized to galantamine were spending approximately 5 hours less per week assisting with ADLs than carers of patients randomized to placebo (mean 17.5 sd = 15 vs. 22.5 sd = 18.5, respectively). However, after 4 months, carers of patients treated with placebo reported a slight reduction in time spent assisting (mean change = –0.93 hours sd = 17.14) while carers of galantamine patients reported a substantial average increase (4.13 hours sd = 19.17). At 4 months, more carers of galantamine treated patients indicated that their loved ones needed supervision for safety than had been indicated at baseline (86% vs 81%), while carers of patients in the placebo group lowered their estimates (71% vs 76%).
Conclusion: The ACTS did not detect benefit in favour of galantamine in terms of carer time spent assisting patients with daily activities for those who participated in the VISTA study. This may be due in part to an imbalanced design that assigned more moderate patients to the placebo group (39% vs 27% in gal, as reported in CMAJ,2006;174:1099–1105): the milder patients in the galantamine group may have had more capacity for decline. Additional analyses stratified by severity (pending) may shed more light. Analyses of time spent by ADL items (also pending) may also provide additional perspective.
PS02.28
Episodic memory for actions versus episodic verbal memory: A comparative study between young and older Portuguese adults
A Silva2; M Pinho2; Horácio Firmino1; M Simões2
1Coimbra University Hospitals, Coimbra, Portugal; 2Faculty of Psychology and Sciences of Education—University of Coimbra, Coimbra, Portugal
Background: Following the first studies about episodic memory for actions (Engelkamp & Krumnaker, 1981; Cohen, 1980), it was assumed that there is an enhancement in recall of simple instructions when they are performed over when they are only verbally presented—the subject performed task (SPT) effect. Since then, it was also assumed that there are differences between episodic memory for actions and episodic verbal memory concerning the underlying mechanisms, and the quality of subject's performance. Researchers tried to characterize the age-related influence in this effect (Backman & Nilsson, 1985) and observed that there were no significant differences between young adults and older adults, despite the first having better performance. However, other studies provide contradictory results (Brooks & Gardiner, 1994; Earles, 1996) that can be explained, at least partially, because different methods were used. At the present time, in Portugal, there is only one known study with SPT applied to a sample of university students (Freitas & Albuquerque, 2007). The present exploratory study intends to adapt the SPT paradigm to Portuguese older adults in order to assess the effects of aging on memory for actions. We also aim to disentangle explanations for SPT effect.
Hypothesis: If motor encoding is added to the memory trace when subjects performed the actions comprised in the instructions then it is expected that there will be a higher recall level in this task for both groups in comparison with recall in the verbal learning task (observation of SPT effect in both groups). It is also expected that differences in recall between groups in SPT are not eliminated but significantly reduced.
Participants/Methods: Study participants included 80 healthy subjects (40 with age range between 35 and 44 years old, and 40 with age range between 70 and 75 years old) with 4 to 6 years of education. Subjects were recruited in the community, home care centres and Senior Universities. The design is within-subjects, which includes a Memory for Actions Test (Pinho & Silva, 2008) comprising two lists with 16 simple instructions (object-action pairs) each. For one of the lists the participants only read the instructions—verbal condition, and for the other list the instructions are performed by the participants—SPT condition. Then a free recall test is administered. Additionally, a comprehensive neuropsychological assessment battery is also administered: Addenbrooke Cognitive Evaluation – Revised (Hodge & Mioshi, 2005), Source Memory test; Symbol Search (WAIS-III), Vocabulary (WAIS-III), Digit-Symbol Coding (WAIS-III); Word Pairs Test (Pinho & Simões, 2008); Visual Patterns Test (Della Sala et al., 1997); Letter-Number Sequencing (WMS-III); Geriatric Depression Scale (Yesavaje et al., 1983) and Beck Depression Inventory (Beck, 1996).
Results/Conclusion: The level of recall in both groups is greater in the SPT condition than in verbal condition, and despite the better performance for younger adults this result is only significant in the verbal condition. In short, the SPT effect is observed for both groups. We discuss the explanations concerning the underlying processes involved in this type of episodic memory, and we consider the use of this paradigm for rehabilitation purposes.
PS02.29
The Coimbra's University Hospital Battery (CUHB): A new resource for measuring neuropsychological function in psychiatric practice
L Pires2; A Leal2; Horácio Firmino1; M Simões2; M Pinho2; M Vilar2
1Coimbra University Hospitals, Coimbra, Portugal; 2Faculty of Psychology and Sciences of Education—University of Coimbra, Coimbra, Portugal
This work presents the elaboration processes of the structured neuropsychological evaluation battery that is currently under exploration in Psychiatry Clinic of Coimbra's University Hospitals (CUH). We also present the preliminary results of its administration within older adults assessed in this Hospital of Coimbra (Portugal). This battery was designed with the main purpose of improving the diagnostic capacity and mental health care in Gerontopsychiatric Services.
Purposes: 1. Test the validity and utility of different measures constituting our battery, aiming to achieve a higher degree of diagnostic capacity and discrimination of healthy aging from the most common late-life disorders (Depression, Mild Cognitive Impairment—MCI and Alzheimer's disease—AD). 2. Analyze the neuropsychological performances achieved with CUHB. 3. Analyze the cognitive profiles of Alzheimer's disease and cognitive impairments of different etiologies.
Sample: This study was performed with 120 subjects (n = 51 males and n = 69 females; age max. 85 and min. 55, mean = 67.12, S.D. = 8.77; years of education, mean = 6.38, S.D. = 3.76) among community dwelling elders assisted in this Central Hospital. Our sample is constituted by healthy subjects (n = 30), depression patients (n = 30), MCI patients (n = 30) and AD patients (n = 30).
Methodology: Selection of CUHB's instruments have regarded at least one of the following main criteria: (i) sampling the cognitive function and psychopathological symptomatology usually related to our under study conditions; (ii) international acknowledgment in the field; (iii) have been developed for the use in geriatric population. CUHB's instruments are: Addenbrooke's Cognitive Examination Revised (ACE-R) and Mini Mental State Examination (MMSE); Vocabulary, Digit Symbol and Symbol Search subtests (WAIS-III); Letter-Number Sequence and Spatial Span subtests (WMS-III); Verbal Paired Associates (Episodic and Semantic Memory), Prospective Memory, Memory for actions (Incidental Memory); Trail Making A & B; Verbal Fluency (Category and Letter Fluency); Rey 15 item (“reduced effort”); Geriatric Depression Scale (GDS) and Geriatric Anxiety Inventory (GAI).
Results: Our results are analyzed by function or dimension and by instrument for each of the study groups. We proceed to a comparative analysis of the answers and performances obtained with CUHB.
Conclusions: The nature of our results suggests the CUHB's utility in categorizing and distinguishing the performance's patterns achieved by our experimental groups. The compressive, structured and wide nature of CUHB, allows us to recommend its use in different circumstances such as: follow up; design and monitoring of clinical interventions; prediction of the course of cognitive decline; staging dementia and identifying weakness and strengths for rehabilitation purposes.
PS02.30
Functional Assessment of Adults and Older Adults Inventory (IAFAI): Adaptation and validation studies
M Simões2; Horácio Firmino1; S Silva2; L Sousa2; M Vilar2; S Freitas2; L Pires2
1Coimbra University Hospitals, Coimbra, Portugal; 2Faculty of Psychology and Sciences of Education—University of Coimbra, Coimbra, Portugal
Functional capacity represents a wide range of everyday skills that are necessary for independent living within home and community. Functional deficits are common, aged-related features and the impaired ability to perform daily activities, particularly the instrumental activities of daily living (IADL), is an essential feature for the clinical diagnosis of Alzheimer's disease (AD). The development of the Functional Assessment of Adults and Older Adults Inventory (IAFAI), including, simultaneously, in 3 different domains, the basic activities of daily living and the instrumental, household and advanced, activities of daily living, intend to fill a gap in the field of functional assessment. This new questionnaire (that could be administered to the patient and/or to his/her caregiver) contains, in the majority of its domains, representative items of the ability of initiative, planning/organization and execution of tasks, and combines the assessment of the level of difficulty with the assessment of the need for assistance.
Objectives: With this exploratory study we have the following aims: (i) the analysis of the psychometric qualities of IAFAI; (ii) the elaboration of the final version of IAFAI and the construction of a brief module for screening the functional capacity; (iii) determine what are the main functional characteristics that distinguish healthy older adults from older adults with AD and, (iv) elucidate what are the cognitive domains that are strongly correlated with the ability to perform IADL.
Participants: 60 community-dwelling older adults (30 healthy older adults and 30 older adults with the clinical diagnosis of mild AD), aged between 65 and 75 years and with four or more years of education.
Methods: A comprehensive neuropsychological assessment battery was selected to evaluate general cognitive functioning (Mini Mental State Examination and Addenbrooke's Cognitive Examination – Revised); executive function (Trail Making Test A & B and Verbal Fluency Test); processing speed (Digit Symbol Substitution and Digit Symbol Copy, WAIS – IIII); working memory (Spatial Span and Letter Number Sequencing, WMS-III); episodic and semantic memory (Word Pairs Associated); spatial and prospective memory (the tasks “route”, “message” and “personal object” from the Rivermead Behavioural Memory Test – II); motor function (Grooved Pegboard Test); emotional symptoms (Geriatric Depression Scale) and, for the assessment of the activities of daily living, the Functional Assessment of Adults and Older Adults Inventory.
Expected Results: We expect that the IAFAI could discriminate the cluster of healthy older adults from the cluster of older adults with Alzheimer's disease and, that the neuropsychological measures whose results evidence the strongest correlation with the results in this new measure of activities of daily living, specifically, in the domains of IADL, are, foremost, the measures of executive functioning and, after these, the measures of memory (with emphasis on the selected tasks of prospective memory, by its ecological validity) and the measure of speed processing, according to past research in this area.
PS02.31
Misplaced Objects Test: Diagnostic validity and utility for the screening of mild cognitive impairment
Horácio Firmino1; P Batista2; M Simões2; M Pinho2; L Pires2; L Sousa2
1Coimbra University Hospitals, Coimbra, Portugal; 2Faculty of Psychology and Sciences of Education—University of Coimbra, Coimbra, Portugal
Background: Memory of where one has placed common objects is a frequently mentioned complaint in the clinic, and is presented by many of the patients with Mild Cognitive Impairment. Several investigations that used traditional measures demonstrated their sensitivity to brain dysfunction. However the use of this type of instruments creates difficulties in the assessment of aged people, since they are not familiar with the neuropsychological assessment procedures. In this context, it is important to develop instruments that respond to these difficulties and that show also good generalizability to everyday life, i.e. good ecologic validity.
The Misplaced Objects Test is a computerized test of object location recall and a measure of everyday visual memory that allows the assessment of this memory failure. Delayed recall of 20 common objects that the subject has placed using a touch sensitive screen in a computer-simulated 12-room house is evaluated with three measures. Scores include the number of objects found on the first attempt, the number of objects found on the second attempt, and the total number of objects found on both attempts.
Aims: The present exploratory study aims to obtain information regarding validity and clinical utility of the Misplaced Objects Test.
Methods: Test performance was evaluated in a group of patients at ages from 55 to 80 years. Our sample consists of 40 geriatric outpatients (Coimbra University Hospitals), divided in two clinical groups: (i) Unimpaired Cognitive Functioning (control group) (n = 20), (ii) Mild Cognitive Impairment (n = 20). An additional third group (university students) (n = 20; ages 19–22 years) was also used as a comparison. Performance was evaluated in relation to age, education, gender, and emotional status, as well as in relation to several traditional neuropsychological measures. Another study (concurrent validity) was also considered by the exam of the correlations between the Misplaced Objects Test and other memory tests (Corsi Block test, Word List Memory Test).
Conclusions: Computerized testing was commonly well accepted by the subjects, and several features of the test demonstrated its suitability for clinical applications in populations with cognitive impairment. There were significant positive correlations between performance in the Misplaced Objects Test and performance in the other memory assessment tests. Thus, the Misplaced Objects Test may be a useful tool for the assessment of Mild Cognitive Impairment patients. It may be applied for early diagnosis, assessment of progression of disease and demonstration of treatment effects.
PS02.32
The impact of the behavioural symptoms of dementia in the informal caregiver: indicators of burden, satisfaction and psychopathology
A Silva2; S Silva2; S França2; J Cerejeira1; Horácio Firmino1; M Simões2
1Coimbra University Hospitals, Coimbra, Portugal; 2Faculty of Psychology and Sciences of Education—University of Coimbra, Coimbra, Portugal
Background: Dementia care in developing countries will continue to be provided by co-resident caregivers at home, as the family is considered the major support of the dependent older adult. Behavioral and Psychological Symptoms of Dementia are known to be difficult to manage, and those that have most impact on the caregiver are the aggressive behaviour, sleep disturbances and hallucinations. The consequences of care assistance in this context for the informal caregiver is described in terms of anxiety and depressive symptoms, and also of physical morbidity (e.g. weak immunitary system, bad health perception, high incidence of chronic diseases, physical fatigue, etc).
Objectives: With this study we seek the explanation of (1) the nature of the care and perception that caregiver has of his burden (negative element of the care assistance) and (2) the satisfaction degree of the caregiver (positive element of care assistance). As an additional objective, we intend to link these vectors with the presence of psychopathology in the informal caregiver.
Participants: The cross-sectional study subjects are the patients and their caregivers, interviewed in the Gerontopsychiatric Outpatient Unit of the Psychiatric Clinic in the Coimbra's University Hospitals.
Methods: We collect the demographic information with the CUIDE (Older adults' Caregivers in Europe). In the subjects with the clinical diagnosis of Alzheimer's disease (AD), we assess the general cognitive functioning (Mini Mental State Examination) and the presence of depressive symptoms (Geriatric Depression Scale – 15). In order to assess the Behavioral and Psychological Symptoms of Dementia we use the Neuropsychiatric Inventory. The impact of these symptoms on the caregiver is assessed by measures of burden of care and the psychological well being of the caregiver, respectively, the Carer's Assessment of Difficulties Index (CADI) and the Carer's Assessment of Satisfaction Index (CASI). To assess the care assistance's needs, we use the Easy Care. Last, for the assessment of subjective perception of health, we selected the General Health Questionnaire and, to assess the presence of psychopathology, the Brief Symptoms Inventory.
Expected Results: With this methodology, we expect to find that the presence of behavioural symptoms in patients with AD and the high perception of care assistance's needs, is strongly correlated with the perception of burden and the presence of psychopathology in the informal caregiver.
Conclusions: To be effective, dementia care services in developing countries need to focus on management of BPSD at home. We believe that this investigation and similar studies of behavioral changes and associated caregiver burden across the spectrum of dementia will be helpful in determining appropriate strategies for patient management and caregiver support.
PS02.33
Pronouns resolution in Mild Cognitive Impairment patients and in healthy elderly: A study with event related potentials
Horácio Firmino1; S França2; J Leitão2
1Coimbra University Hospitals, Coimbra, Portugal; 2Faculty of Psychology and Sciences of Education—University of Coimbra, Coimbra, Portugal
Objectives: The present study aims at characterizing the differences between Mild Cognitive Impairment (MCI) patients and healthy elderly individuals with respect to the Event Related Potentials (ERPs) elicited by pronoun resolution within a sentence comprehension task.
Rationale: Pronoun resolution can be processed via a syntactic route or via a more costly discourse/semantic route. When resolution takes place at the syntactic level, the pronoun is treated as a variable in logical syntax and instantiated with a c-commanding antecedent. The more costly discourse/semantic route is the only one available when the pronoun's antecedent doesn't structurally dominate it from a c-command position. In such cases, a discourse representation is created for the pronoun, which is then assigned, via a coreference link, a referential value retrieved from discourse storage.
General syntactic processing, unlike discourse/semantic processing, is considered to be well preserved in mild/moderate Alzheimer's disease (AD). Therefore, we hypothesized that contrasting pronoun resolution via the syntactic route with pronoun resolution via the discourse/semantic route could provide insightful information about progression to AD.
Materials: Gender agreement in complex sentences was manipulated in order to cause pronoun resolution either with the c-commanding NP (1: syntactic route condition) or with the NP in a genitive recess (2: discourse/semantic route condition), e.g.:
(1) [[The butler]MASC of [the countess]FEM](i)MASC quarreled with the servant to whom he(i)MASC had lent some money.
(2) [[The employee]FEM of [the butcher](i)MASC]FEM quarreled with the client to whom he(i)MASC had sold spoilt sausages.
Participants: 20 MCI patients (CDR = 0.5, objective memory deficit in either WMS-III episodic memory test or the WMS-III logic memory test, Peterson MCI clinical criteria) and 20 healthy controls were recruited for the study. Exclusion criteria: Neurological or psychiatric pathology, history of traumatic brain injury.
Results: The discourse/semantic condition differentiates MCI patients and controls. This difference presents itself in one of two distinct patterns:
[A] An enhanced N400
[B] An Absent N400, and an enhanced Late Positive Component.
We interpret [A] as an index of hindered strength for the associative link encoding the pronoun-antecedent coreference relation, and [B] as a result from failure to establish the coreference link with the appropriate antecedent. We further hypothesize that [A] and [B] differentiate patients in risk for rapid progression (pattern B) and stable MCI patients (pattern A).
PS02.34
Falls in somatic and dementia wards at community care units
Edit Fonad; A Emami; T Robins Wahlin; B Winblad; H Sandmark
Karolinska Institutet, Tyreso, Sweden
Introduction: Falls and fall injuries are common problems for patients at nursing homes in Sweden. Impaired cognitive function, a poor sense of orientation and a high intake of medicine, can lead to an increase in falls among older people.
Aim: The objective of this study was to investigate the associations between falls and: fall risks, fractures, the use of physical restraints and the use of certain medications in somatic and dementia wards, respectively.
Method: The study design is ecological, and aggregated data regarding falls, fall risk assessments, fractures, the use of physical restraints and medication were collected between 2000 and 2003. The Pearson correlation analysis and regression analyses were used to investigate associations between fall risks, medication, fractures, wheelchair bound situations, bed rails and falls.
Results: The total number of reported fall incidents was 2651; of these, 737 incidents were registered in dementia wards and 1914 in somatic wards. Dementia wards and somatic wards differed regarding falls and fractures, as it was only in dementia wards that falls were associated with fractures. There was also a significant correlation between falls and assessed risk of falling, the use of certain medication, and physical restraints such as wheelchairs and bed rails in dementia wards. Falls at somatic wards were associated with the use of sleeping pills with benzodiazepines.
Conclusion: For dementia wards there were associations between falls and fractures, physical restraints and the use of certain medications. Fractures were associated with the use of neuroleptics, sleeping pills and sleeping pills with benzodiazepines. At somatic wards, falls correlated with the use of sleeping pills with benzodiazepines, and with the use of wheelchairs and bed rails.
PS02.35
Evaluating nocturnal activity in demented inpatients by a short semi-quantitative scale
S Banerjee1; Georgina Franco1; P Moulin1; F Stenkeeste2; P Couturier1
1Grenoble University Hospital, France, Grenoble, France; 2INSERM, Toulouse, France
Introduction: Evaluating nocturnal activity is part of the follow up of behavioural problems in geriatrics, especially in severe dementia patients. Even in specialized units their follow up is tiring, time consuming and nocturnal activity is usually based on scales that depend on the staff appreciation. Our goal was to evaluate a semi quantitative scale for inpatients with high nocturnal activity and to see their applicability and acceptability by the staff.
Methods and Material: We used two patient bedrooms equipped with the GARDIEN® system that uses passive infrared sensors to monitor activity. We analyse the nocturnal activity between midnight and 6 o'clock from patients hospitalised for 7 days. The patient or their legal person gave an informed consent. The night staff used the assessment scale. This scale has 4 scores: 0 = no observation of any mobility or getting up from bed. 1 = getting up from bed once or two times. 2 = getting up from bed > 2 times and less than 5 and 3 = getting up from the bed more than 5 times. The same scale was then fulfilled by experts using the automated printed reports from the GARDIEN® System as a Gold standard.
Results: We registered a total of 352 nights gathered from 27 patients, 11 men and 16 women. Mean age was 82 years. All patients were hospitalised for medical reasons; including 19 with dementia of different types. The mean MMSE for these patients was 13/30. For the group with dementia (295 nights observed) the kappa was 0.45 (95%CI 0.38–0.52) and 0.27 (95%CI 0.08–0.46) for the cognitively normal group (57 nights). This difference between the populations is related to under evaluation by staff for low activity, especially in normal patients.
Conclusion: This scale can be useful to quantify nocturnal activity in elderly patients with severe dementia and can contribute to the follow up of behavioural problems in a more objective way.
PS02.36
Models for diagnosing dementia in primary health care: The Norwegian Dementia Plan 2015
Margit Gausdal; L Gjøra
Ageing and Health. Norwegian centre for Research, Education and Service Development, Oslo, Norway
Background: In 2008 the Norwegian ministry of health and care services presented a Government's Dementia Plan for Norway containing strategies as well as specific initiatives for the period until 2015. The Norwegian Centre of Dementia Research was asked to carry out a three year long developmental program to implement and evaluate models for diagnosing dementia in primary health care.
Aim: Develop models for diagnosing dementia in primary health care.
Method: The project is divided into four phases: 1) To carry out courses for municipality health personnel throughout the country, 2) carry out a survey on how dementia is diagnosed in primary care today, 3) develop and implement various models in a variety of small and large municipalities, 4) evaluate and recommend models.
Results: Approximately 2000 individuals participated in the 35 courses on how to diagnose for employees in the community health care during 2007 and 2008. The survey revealed that in 2007 108 of 431municipals in Norway had dementia teams or a co-coordinator that carried out dementia work-up in collaboration with the patient's family doctor. Of these, 85 were dementia-teams and 23 were dementia-coordinators. The staff of the teams was in 105 municipalities a nurse, in 32 an occupational therapist, in 36 a nurse's aid, in 35 a general practitioner
Based on previous knowledge and information from the survey a standardised dementia work-up has been described as a close co-operation between a dementia team (ideally consisting of a nurse and an occupational therapist) and the patient's family doctor. Standardised assessment tools like IQCODE, RSS, ADL scale, MMSE, Clockdrawing test and Cornell scale are recommended.
In 2008, 27 municipalities were invited to take part in the implementation of new models that will last for 12 months. In this part of the program, which is ongoing, the participants are offered free courses and supervision according to a fix plan. During the implementation phase the new teams will collect data from the dementia work-up, and how the teams co-operate with the family doctors.
Conclusion: About 25% of all Norwegian municipalities have a dementia team that works together with the patients' family doctor in diagnosing dementia. A national plan has been set up to develop new models for diagnosing dementia in primary care. The implementation of new models is ongoing.
PS02.37
A retrospective study on characteristics of long-term users (the clients and the family caregivers) receiving Kin Chin Dementia Day Care in Hong Kong
Wong Gemma; W Lui; O Sin
School of Professional and Continuing Education, The University of Hong Kong, Hong Kong, SAR PR China
Community Support Services are essential to Dementia Care. In Hong Kong, Kin Chi Dementia Day Care has been serving the local community for ten years. During the period of service provision, the centre has been receiving referrals from all areas including walk in cases. A small drop out was observed but the majority of them are long term service users. 10% of the discontinued cases returned to seek day care services after a period of absence. The explanation given by most caregivers is that they have observed a decline of cognitive and social functionings when they stopped all Dementia Services.
In order to understand the rationale for continuing the service with Kin Chi Dementia Day Care, a retrospective review has been adopted to look at the characteristics of users including clients and family caregivers. A detail of social demographic characteristics, health status, cognitive functioning, and caregivers' burden and daily hassles will be presented and discussed. Most important of all, the process of development of attachment amongst the clients and the family caregivers to the day care centre will be explored and analysed. Furthermore, the focus group will provide an insight on the effects of community care management toward the social and emotional growth of the clients and the family caregivers.
PS02.38
Psychometric properties of the French version of the Dyadic Adjustment Scale in the elderly
Maria Goldfarb1; G Trudel1; R Boyer2; M Préville3
1Universite du Quebec a Montreal, Montreal, QC, Canada; 2Centre de recherche Fernand Seguin, Montreal, QC, Canada; 3Centre de recherche de l'hôpital Charles LeMoyne, Greenfield Park, QC, Canada
The Dyadic Adjustment Scale (Spanier, 1976) is a widely used instrument used to measure the quality of a conjugal relationship. This scale has been validated in many languages, including French. However, it has not yet been validated in the elderly population. The present study examined the internal validity and factor structure of the scale and its subscales in 1175 married individuals aged 65 years and more. While high reliability was confirmed for the total scale, some items were unnecessary. Reliability was high or acceptable for the subscales but it was lower than the one reported by Spanier (1976). Finally, confirmatory factor analysis revealed a good fit for the original factor structure. The implication of these results will be discussed.
PS02.39
The preventive value of health-based daycare for patients suffering from dementia
Margret Gustafsdottir
University of Iceland, Reykjavik, Iceland
The purpose of this interpretive phenomenological study was to explore collaboration between families and staff in daycare units caring for elders suffering from dementia.
Data were collected over a period of five years in longitudinal individual interviews with family members of eight patients (27 interviews), group interviews with staff (8 groups of staff comprising 3–4 staff per group), and participant observation. The sites of the study were the only three dedicated daycare units for patients with dementia operating in Reykjavík (the capital city) when the study commenced in 2003. One of them functioned under the auspices of the City of Reykjavík, the second under the auspices of the Alzheimer Association and the third under the auspices of a private body constituted by a number of organisations. Since then four more units have opened: the seventh unit opened in the autumn of 2008. All seven units are located in and around Reykjavík; three are operated by the Alzheimer Association.
The Icelandic Act on Services for the Elderly defines daycare as a support measure for those who need continual supervision and care in order to be able to continue living at home. All daycare units for patients suffering from dementia in Iceland are health-based and administered by RNs, and visited weekly by an appointed geriatrician. Indeed, the patients' condition is closely monitored in the units, while health promotion practices are upheld with regard to intake of air, fluid and nutrition, elimination, activity and rest, as well as personal hygiene. Clearly the interviewees, both family and staff, believed that this approach supported the wellbeing of the dementia suffers and helped them to continue living at home. However, both parties recognised the paradox of the situation, as they were confronted with the deteriorating process of the illness and eventual nursing home placement.
And indeed the first patient entered a nursing home only a few months after the recruitment of his family into the study. Others continued to participate in the study until as recently as late last year, after attending daycare for four years. The spouse of this patient repeatedly said during those years: “I can manage while they are willing to keep him in the daycare.”
Asked about their stance during this time, the daycare staff never faltered in their belief that they should and could go on caring for the deteriorating patient, so long as the spouse was willing to keep things going at home with the help of a very supportive family.
For this family in the study, as for others, it was very important to address health promotion practices and health-related issues with the staff of the units. By these means they could discuss how they could give their ill family member a helping hand and how to manage particular behaviour problems or relieve feelings of malaise. For the family, it was especially important to be able to talk openly with health professionals about the illness and the demands of care, as they assured themselves of its preventive value.
PS02.40
Family's relief in dementia-based daycare as the attendance to personal hygiene is handed over to staff
Margret Gustafsdottir
University of Iceland, Reykjavik, Iceland
The purpose of this interpretive phenomenological study was to explore collaboration between families and staff in daycare units caring for elders suffering from dementia.
Data was collected in three special dementia-based care units (capacity of 55 placements). The data collection consisted of longitudinal individual interviews with family (27 interviews with 8 family members), group interviews with staff (in total 24 staff members in 8 groups), and participant observation.
The findings from the interviews show that assistance with personal hygiene is a very sensitive issue for the demented patient. Regular swimming sessions twice a week are part of the program in two of the three units and have in a way solved this issue in many cased especially in the beginning of a stay of a patient. Swimming is a cultural sport in the country and most of the patients enjoy to go swimming. The staff may give the patients a hand as they prepare for swimming or after the session so receiving assistance with personal care becomes part of the swimming tour. Swimming sessions may later turn into bathing ones when a tour to the swimming hall becomes too difficult. However, assistance with bathing and toileting regime becomes a part of a particular patient's schedule of the day. The assistance is fitted to an individual's practices and mood without any hassle. Family members found that this aspect of the daycare was really helpful and provided a valuable relief. Following terms were used to describe how this care was reflected in “dignity”, “pride” and “pleasure” of the patient. The family also emphasized that this kind of help reduced stress in their relationship with the patient. These findings show that increased understanding of the modes of handling personal hygiene may make it possible to improve care of the patient suffering from dementia.
PS02.41
Lost and found: How long do caregivers spend searching for misplaced items?
Laura Hamilton1; S Fay1; K Rockwood2
1Capital District Health Authority, Halifax, NS, Canada; 2Capital District Health Authority, Halifax, NS, Canada
Background: Misplacing objects is commonly identified as a “warning sign” of Alzheimer's disease, described especially as the inappropriate placement of items (e.g. watch in the sugar bowl). Previous work from the VISTA trial has shown that patients and carers more commonly described misplacing as the frequent inability to remember or locate items recently in ones’ possession. We compare the number of carers who indicated they assisted in finding things on a systematic measure of the amount of time carers spend engaged in care-giving activities, to the number of patients for whom misplacing was described as a re-occurring problem during the clinical interview process.
Methods: This is a secondary, qualitative analysis of the Video Imaging Synthesis of Treating Alzheimer's Disease (VISTA) study, a 4-month, randomized, placebo-controlled trial of galantamine which consisted of video recorded, semi-structured, goal tracking and assessment interviews with 130 community-dwelling patients with mild-to-moderate AD (mean age = 77 ±7.7; 63% women; 67% mild AD). Interviews were coded and analysed using framework analysis to capture and summarize patient/care descriptions of the impact misplacing has on everyday life. Other assessments, not video-recorded, included Allocation for Caregiver Time survey (ACTS) which includes a question regarding the amount time spent helping to “find things” in the past week.
Results: Previous work from the VISTA trial identified a total of 96/130 patients for whom misplacing was a problem. Of these, 32 carers indicated that they were often required to search for items lost or misplaced by patients. Results from the ACTS indicate that searching is a much more common activity. Most carers who completed the ACTS (93/122, 76%) had recently spent time assisting the patient with finding things (including 28/32 who reported this in the clinical interviews). In fact, helping the patient find things was an activity carers engaged in approximately 39 minutes a day, 4 days per week. Only 19/96 (20%) carers of patients who were described as having a misplacing problem indicated on the ACTS that they did not spend time assisting the patient with finding things.
Conclusion: Misplacing is a common symptom in mild to moderate AD and “searching for things” is a common activity carers engage in as a result of this symptom. Even when patients do not have a described misplacing problem, carers report spending a substantial amount of time (~40 minutes) searching for items, with or on behalf of the patient, on a near daily basis. Further work on strategies to help reduce patient misplacing may have the effect of reducing caregiver burden by reducing the amount of time carers currently spend searching.
PS02.42
A randomized, controlled comparative open label study of a traditional Japanese medicine, yokukansan, on the behavioral and psychological symptoms of dementia in patients with Alzheimer's disease
Yoshihito Hayashi1; Y Mitsuyama2; Y Ishida1
1University of Miyazaki, Miyazaki, Japan; 2Daigo Hospital, Miyazaki, Japan
Objective: This randomized, controlled comparative open label study examined the efficacy and safety of yokukansan (YKS) on the behavioral and psychological symptoms of dementia (BPSD) and activities of daily living (ADL).
Method: Sixty-three patients with Alzheimer's disease (AD) (26 men and 37 women, mean +/− SD age = 76.2 +/− 7.6 years) according to DSM-IV criteria were investigated. Participants were randomly assigned to the YKS group (N = 30) or control group (N = 33) and treated for 4 weeks. The Neuropsychiatric Inventory (NPI) for the assessment of BPSD, the Mini-Mental State Examination (MMSE) for cognitive function, and the Disability Assessment of Dementia (DAD) for ADL were evaluated at baseline and the end of treatment. In case patients showed insufficient response to treatment during the trial, risperidone, a serotonin-dopamine antagonist, was temporarily added to the regimen.
Results: Sixty-two patients completed the trial. Risperidone was used as needed in 2 patients in total. Significant improvements in NPI scores were observed in the YKS group, but not in the control group. The results of MMSE and DAD scores did not change during the observation period in either group.
Conclusion: YKS improves BPSD significantly in patients with AD. Follow-up studies using a double-blinded, placebo-controlled design conducted over a longer period should be carried out.
PS02.43
A multicenter open label study to investigate the effect of a traditional Japanese medicine, yokukansan, on the behavioral and psychological symptoms of dementia in patients with Alzheimer's disease
Yoshihito Hayashi1; Y Mitsuyama2; Y Ishida1
1University of Miyazaki, Miyazaki, Japan; 2Daigo Hospital, Miyazaki, Japan
Objective: The aim of this study was to investigate the efficacy and safety of yokukansan (YKS) on the behavioral and psychological symptoms of dementia (BPSD) in patients with Alzheimer's disease (AD).
Methods: Twenty-nine patients with AD (16 men and 13 women, mean +/− SD age = 75.6 +/− 9.0 years) participated in the study. Treatment with YKS was given for 4 weeks. The Mini-Mental State Examination (MMSE) was used for the assessment of cognitive function. BPSD were evaluated using the Neuropsychiatric Inventory (NPI). The Disability Assessment for Dementia (DAD) Index was used to assess disability in daily life. These assessments were evaluated at baseline and the end of treatment.
Results: Twenty-six patients completed the trial. After 4 weeks-treatment with YKS, significant improvement in the mean NPI score was observed. The results of MMSE and DAD scores did not change between baseline and the end of the treatment. No serious adverse effects caused by YKS were observed.
Conclusions: YKS treatment significantly improved BPSD, but did not cause any decline in cognitive function or ADL with no serious adverse effects in patients with AD. The present results suggest that YKS is beneficial in the treatment of BPSD and that it can possibly reduce the burden of care on patients with AD. Further studies with larger number of patients using a double-blind placebo-controlled design over a longer period should be performed.
PS02.44
Significant others’ experiences of the hip fracture recovery period of older patients with and without cognitive impairment
Ann-Marie Hedman2; L Strömberg2; M Grafström1; K Heikkilä3
1Karolinska institutet, Stockholm, Sweden; 2The Swedish Red Cross University College of Nursing, Stockholm, Sweden; 3Växjö University, Växjö, Sweden
Background: Several studies expose disparities between patients with and without cognitive impairment, both regarding treatment and outcomes after hip fracture
Aim: To investigate how significant others to cognitively impaired and cognitively intact hip fracture patients experienced the first six months post fracture and to elucidate whether there are differences in their experiences due to the patients' cognitive state.
Design: A descript study from a sample of two groups of significant others to patients with hip fracture
Methods: Eleven diaries written by significant others (aged 37 to 73 years) of patients with and without cognitive impairment for a period of six months post hip facture were analysed with qualitative content analysis.
Results: Significant others to the impaired group were dissatisfied when dealing with health care professionals. They experienced that staff had a negative attitude towards patients and that there was a lack of rehabilitation, physical exercise, and pain relief. When complications occurred among patients in the cognitively impaired group, their significant others felt distressed because of their suffering. Significant others to cognitively intact patients were satisfied when the patient's recovery period proceeded as expected, but felt strained when complications occurred, since they felt that they had an obligation to care for the person.
Conclusions and Relevance for Clinical Practice: A more attentive and supportive approach to the cognitively impaired patients is required to reduce the significant others’ dissatisfaction or emotional distress.
Keywords: cognitive impairment, diary, hip fracture, significant other, qualitative content analysis, emotional distress
PS02.45
Assessing experienced meaning in life among older adults: The development and initial validation of the EMIL
Marnin Heisel
The University of Western Ontario, London, ON, Canada
The North American older adult population is growing rapidly, creating capacity concerns in the healthcare system. Although many older adults enjoy excellent physical and mental health, a substantial proportion does not. Older adults have high rates of suicide worldwide, and the older adult population is increasing rapidly, necessitating research on factors promoting resiliency, health, and well-being in later life.
Research has indicated positive associations between Meaning in Life (MIL) and adaptive factors, including management of chronic pain, life satisfaction, perceived social support, and psychological well-being, and negative associations with depression and other indices of psychopathology including suicide ideation (Heisel & Flett, 2007, 2008). Frankl (1985) provided an early description of the salutary role of MIL in preventing despair and suicide and indicated that meaning is typically discovered in Creative, Experiential, and Attitudinal sources, referring to that which we contribute to life through work, art, sport, and creative pursuits (Creative), that which we receive from life through our sensory experiences and enjoyment of activities and relationships (Experiential), and the attitudes we adopt towards both successes and challenges in life (Attitudinal). He additionally posited the existence of Ultimate meaning, referring to the perception that one's life serves a greater purpose. A multidimensional approach to MIL fits well with the transitions characteristic of later life; however, most extant measures treat MIL as a unidimensional construct and were not developed or validated with older adults.
The present study describes the development and initial validation of the Experienced Meaning in Life scale (EMIL) with a community-residing older adult sample. Subscales were created consistent with Frankl's (1985) theoretical treatment of MIL, assessing Creative, Experiential, Attitudinal, and Ultimate sources of Meaning. The EMIL is the first measure designed specifically to assess these four sources of MIL among older adults.
The present paper describes the development and initial validation of the EMIL among a community-residing older adult sample, assessing internal consistency, 2-week test-retest reliability, and convergent (life satisfaction, purpose in life, spirituality, and psychological well-being) and discriminant validity (suicide ideation, depression, hopelessness, and physical health complaints). Findings to date indicate strong internal consistency, test-retest reliability, and construct validity.
The role of MIL will be discussed as a potential resiliency factor protecting against suicide among older adults and in the broader context of existential approaches to late-life mental healthcare.
PS02.46
Late life suicide prevention toolkit: Life saving tools for health care providers
M Heisel1; M Donnelly2; S Moore3
1University of British Columbia, Vancouver, BC, Canada; 2University of Western Ontario, London, ON, Canada; 3Athabasa University, Calgary, AB, Canada
Older adults have among the highest rates of suicide worldwide and employ highly lethal means of self-injury. Research and clinical interventions for suicidal seniors have lagged behind those for younger adults and mental health populations. Research tells us that the majority of older adults who die by suicide have seen a front-line health care provider in the prior month. Increased understanding of risk and resiliency, clinical assessment and intervention, and prevention practices are desperately needed as the population of older Canadians continues to grow.
In 2006, the Canadian Coalition for seniors' Mental Health (CCSMH) created Canada's first ever interdisciplinary, evidence-based Guideline on the Assessment of Suicide Risk and Prevention of Suicide in older adults (with funding from the Public Health Agency of Canada). To date, no other country in the world has such a document, providing recommendations both for the assessment of suicide risk and resiliency, and regarding intervening to prevent suicide among older adults. A committee of clinicians, researchers, academics and advocates have developed the Late Life Suicide Prevention Toolkit in order to distill the CCSMH guideline and its recommendations into easy-to-use tools that can be used by front-line health care providers as well as educators in health education programs at universities and colleges.
The Late Life Suicide Prevention Toolkit includes:
– CCSMH National Guideline for seniors' Mental Health: The Assessment of Suicide Risk and Prevention of Suicide
– Clinician pocket-card: Suicide: Assessment & Prevention for Older Adults
– Interactive, case-based DVD: Suicide Assessment & Prevention for Older Adults: Life Saving Tools for Health Care Providers
– Material for educators: facilitator's guide and PowerPoint presentation
A multi-pronged dissemination plan is being implemented and plans are already underway to augment the toolkit. Learning objectives: By the end of this workshop, participants will be able to demonstrate:
– Familiarity with the epidemiology and risk and resiliency factors associated with suicide among older adults
– Knowledge of suicide warning signs and key questions to assess for suicide risk and resiliency factors
– Awareness of current tools available to health care providers for the assessment of suicide risk and prevention of suicide among older adults
PS02.47
Cognitive domains from Thai-Montreal Cognitive Assessment to discriminate between amnestic MCI and mild AD from normal aging
Solasinee Hemrungrojn1; T Charernboon2; M Phanasathit2; S Tangwongchai1; K Phanthumchinda3; Z Nasreddine4
1Chulalongkorn University, Bangkok, Thailand; 2Faculty of Medicine, Thammasat University, Phrathumtani, Thailand; 3Faculty of Medicine, Chulalongkorn University, Bangkok, Thailand; 4McGill University, Montreal, QC, Canada
It is well known that early Alzheimer's disease (AD) patients are impaired in memory, visuospatial and executive functions. However, in recent years, the literature has reported that amnestic MCI (aMCI) is associated with a decrease in a variety of cognitive tasks, especially speed of mental process and executive functions. There are increasingly more studies aiming at specifying the characters of the cognitive decline in normal aging, aMCI, and early AD that are able to differentiate these conditions.
Objective: We are interested in determining whether there is a continuum between memory and other cognitive abilities for normal aging, aMCI and early AD patients. The aim of our study was to examine differences between normal aging, aMCI and early AD patients in the performance of several cognitive tasks.
Method: The sample was composed of 60 subjects aged above 50 years old consecutively included from the memory clinic at the university hospital, the King Chulalongkorn Memorial Hospital, in Bangkok, Thailand. 20 patients were diagnosed as aMCI with the Clinical Dementia Rating Scale stage 0.5 and 20 patients had been treated for mild Alzheimer's disease (AD) according to NINCDS-ADRDA, DSM IV-TR criteria and CDR stage 1. 20 geriatric patients were randomly selected as normal subjects with CDR stage 0. All participants were assessed with Thai version of MMSE, Thai-Montreal Cognitive Assessment (Thai-MoCA), and CDR administered by trained psychiatrists. Written informed consents were given by the patients or authorizing caregivers. Statistical analyses have been performed by using t-test and binary logistic regression analysis.
Result: There were statistically significant differences between means score of Thai-MoCA in normal subjects, aMCI and mild AD (26.80, 22.25 and 12.40). The aMCI patients had significantly lower scores in visuospatial, naming, attention, and delayed recall tasks than normal aging. Furthermore, we found that delayed recall and attention were able to differentiate aMCI and normal subjects in binary logistic regression model. Early AD patients had significantly lower scores in every tasks of Thai-MoCA than aMCI from both univariate and binary logistic regression analysis.
Conclusion: From our finding, delayed recall and attention would be the predictive cognitive domains that were able to differentiate aMCI from normal aging, whereas marked cognitive deficits in every domain when screening with Thai-MoCA were found among early AD patients.
PS02.48
Dementia among elderly people receiving in-home care
Lisbeth Hogset1; R Hårstad2; G Selbaek3
1Innlandet Hospital Trust, Ottestad, Norway; 2Innlandet Hospital Trust, Ottestad, Norway; 3Innlandet Hospital Trust, Ottestad, Norway
Introduction: In Norway, around eight percent of people 70 years or older receive in-home care. Giving good care to this group of people requires close cooperation between professional caregivers and general practitioners in the municipalities. This particularly applies to people with cognitive impairment or dementia. Little is known about the prevalence of dementia among elderly people receiving in-home care. We are conducting a study including a representative sample of 650 persons who receive in-home care in the South-Eastern part of Norway. This presentation gives preliminary results after analysing the results of the first 108 included cases.
Material and method: The sample comprised subjects 70 years of age or older receiving in-home care in fourteen municipalities, representing urban and rural areas. Certified municipal health-workers collected the data using standardized interviews, after participating in a one-day course on how to perform the interviews. They interviewed the included subjects and their closest personal caregivers. The standardized interview included the Informant Questionnaire on Cognitive Decline in the Elderly (IQ-code), the Clinical Dementia Rating Scale (CDR), the Clock Drawing Test (CDT) and the Mini-Mental-State Examination (MMSE).
Results: The mean age of those in the sample was 83.3 years (SD 5.3) (range 70–96 years), 69 percent were women, 70 percent lived alone, and 59 percent were widowed. Memory failure was reported by 53.4 of the included persons. The mean MMSE-score was 24.2 (SD 4.4), the mean Clock Drawing Test score was 3.3 (SD 1.5) (range 0–5), the mean IQ-code score was 3.5 (SD 0.6). Dementia, defined as a score of 1 or higher on the CDR, was present in 28 percent. Correspondingly we defined cut-off scores for the MMSE and the IQ-code. An MMSE-score of 23 or lower was present in 37.0 percent and an IQ-code score of 3.6 or higher was present in 28.7 percent. The Spearmann correlation coefficients between the different measures of cognitive impairment were 0.79 (CDR vs IQ-code), −0.52 (CDR vs MMSE), −0.52 (MMSE vs IQ-code), 0.60 (MMSE vs CDT), −0.39 (CDT vs IQ-code), −0.43 (CDT vs CDR), all correlations significant at the 0.01 level. The correlations between subjectively experienced memory failure and the measures of cognitive impairment ranged from 0.08 to 0.25. Five persons (4.8 percent) had received a diagnosis of dementia. Among those with dementia as measured by the CDR (CDR ≥ 1), 17.2 percent had received a dementia diagnosis.
Conclusion: The first Norwegian study to investigate cognitive impairment among elderly people receiving in-home care indicates that dementia is highly prevalent in this group. Different measures and cut-offs for dementia give prevalence estimates from 28 to 37 percent. The correlations between different measures of cognitive impairment were moderate to strong. However, the relationship between the person's own report of memory failure and the presence of dementia seems to be weak. Only a minority of the patients with dementia had received a dementia diagnosis. This finding indicates that a closer cooperation between the general practitioners and the institutions providing in-home care in the municipalities is needed.
PS02.49
Digital calendar and message board support people with memory problems at home: Results from the MPOWER pilot trial in Norway
Torhild Holthe1; I Haug-Olsen2; M Mikalsen3
1Norwegian Centre for Dementia Research, Tönsberg, Norway; 2Municipality of Trondheim, Trondheim, Norway; 3SINTEF ICT, Trondheim, Norway
The EU-project “Middleware Platform for empowering older people and people with cognitive impairment – MPOWER” tested one Proof-of-Concept-Application (POCA) in the city of Trondheim, Norway. The POCA consisted of a PC with touch screen, which was connected to Internet by ADSL. The graphical interface was provided from University of Cyprus, and the server was administered from Austrian Research Centre in Vienna.
The aim with the pilot trial was to assess whether a digital activity plan and message board would be usable and useful for the target group. Further to test that the technical platform functioned as expected, and what services that should be improved. Family carers and nurses could add appointments into the calendar and the message board, which the user could read and thereby get an overview of the plan of the day. Seven respondents were recruited from the home based services in three districts of Trondheim. Two men and five women participated between 2 and 18 months. Age ranged from 65 to 89.
Results: Three of the respondents withdrew from the project after a short time (before 3 months). The other four valued the POCA differently. The POCA was highest valued by those who had memory problems, and their carers. The most critical point was to what extent one could rely on the Internet connection.
In order to address the scope of the conference I will present how the POCA enabled a woman with memory deficits to better cope with everyday living, and how her family carers experienced the POCA as a support, as well as describe the challenges regarding Internet connection and infrastructure that must be addressed in order for the POCA to be reliable.
PS02.50
“School for Carers:” A measure to educate and support family carers for persons with dementia?
Kirsti Hotvedt; T Westerberg
Ageing and Health, Norwegian Centre for Research, Education and Service Development, Oslo, Norway
Overview: “School for Carers” – a model to improve family carers’ knowledge about dementia and give them support.
Background: As a part of the Norwegian Government's Dementia Plan towards 2015 the Norwegian Centre for Dementia Research was instructed by the Directorate of Health Affairs to carry out a nationwide project on how to establish and run “School for Carers” in the municipalities. The aim of the program is to improve carers’ knowledge about dementia, to support them and to give help on how to cope with the burden of care. An educational program was actually first established in Norway in 1992. A survey of existing services for family carers took place in 2007. The result showed that only 15% of the municipalities had established services for family carers, of which 20% organised “schools”.
Objectives: The objectives of the study was to disseminate knowledge on how to establish and run “schools” for carers in different parts of Norway and to evaluate the impact of this intervention in family carers.
Design and Method: With support from the project 37 municipalities of different size coming from different geographical regions have established “School for Carers”. The schools offer five to seven meetings of 3 hours duration, focusing on specific themes like communication, behavioural problems and legislation. In each meeting a lecture is given by a specialist and is followed by discussions in smaller groups. Twenty of the 37 municipalities have finished the program and an evaluation has been carried out by questionnaires to 527 family carers.
Preliminary results: The result from the 20 “schools” includes answers from 376 of the 527 family carers that received the questionnaire; 79% women and 21% men. Of them 56% were children and 33% spouses of the persons with dementia, whereas the remaining 11% were other relatives. The largest group (69%) among the respondents was carers for persons with dementia living at home, the remaining lived in nursing homes. Of those living at home 31% lived together with the patient. More than 70% of the respondents replied that they had never participated in educational programs about dementia. The main findings are: 80% found it useful to participate in the program and 73% found that they had learned more on how to cope with different tasks in their role as caregivers and almost all reported that the “school” had contributed to improved contact with professional caregivers, local dementia organisations and other family carers.
Conclusions: So far, the model for “School for Carers” consisting of five to seven lectures and group discussions, seems to appeal to family carers. The educational program provides an opportunity for carers to build a network with professional caregivers as well as other carers.
PS02.51
Addressing complexity in the face of scarcity: The Wisconsin Geriatric Psychiatry Initiative after 6 years
Timothy Howell1; APS Team2; L Buel3; M Gleeson4; A Khan5; C Swanson-Hayes6; S Waters-Castillo7
1University of Wisconsin, Madison, WI, United States; 2Milwaukee County Department on Aging, Milwaukee, WI, United States; 3University of Wisconsin, Madison, WI, United States; 4Abundant Life Manor, Milwaukee, WI, United States; 5University of Wisconsin, Madison, WI, United States; 6Wisconsin Department of Human Services, Madison, WI, United States; 7University of Wisconsin, Madison, WI, United States
Objective: To describe the efforts of the Wisconsin Geriatric Psychiatry Initiative (WGPI), a small but growing group of geriatrics and other professionals working together with state and local organizations to develop systems that enhance the delivery of mental health services to older adults in Wisconsin and beyond.
Design: Case study
Materials and Methods: A description of current initiatives by the WGPI to more widely disseminate basic principles of geriatric psychiatry to health care, long-term care and aging network providers. The WGPI approach, recognized in 2004 as innovative by the Annapolis Coalition on Behavioral Health Workforce Education, has 4 components, each evidence-based: (1) the Wisconsin “Star” Method, an heuristic device easily adaptable to audiences with different levels of knowledge, skills, and attitudes; (2) teaching by utilizing case-based, on-site indirect consultations; (3) network weaving; (4) a social entrepreneurial approach to funding.
Results: Wisconsin has a number of programs for older adults, supported by private, local, state and federal agencies. Psychiatric morbidity is high in the populations served by these programs, and geriatric mental health resources are scarce. Mobilizing geriatric professionals to devote some of their time to providing indirect care through evidence-based consultative teaching (C-T), and to supporting other care providers, on an ongoing basis, may help to address the growing needs. The WGPI now provides C-T sessions to care teams in 7 organizations, and at one site these are linked by teleconferencing to 5 additional teams in 4 states. It has also established an ongoing geriatric mental health certification program and an on-line resource website. The Star Method is being integrated into the Continuing Medical Education section of the American Geriatric Society's website. Responses to the WGPI's efforts continue to be positive, and progress has been made toward a self-sustaining level of financial support. Major challenges include measuring results and expanding the network.
Conclusion: Attempting to shape Wisconsin's limited geropsychiatric resources into a viable infrastructure continues to be a daunting task. But models of indirect care appear to hold significant promise as parts of the effort to enhance geropsychiatric services in Wisconsin and beyond.
PS02.52
A volumetric brain MRI study in early-onset and late-onset bipolar disorder
Shou-Hung Huang1; S Tsai2; Y Huang1; J Hsu3
1Taipei Medical University Hospital, Taipei, Taiwan; 2Taipei Medical University, Taipei, Taiwan; 3Shin Kong Wu Ho-Su Memorial Hospital, Taipei, Taiwan
Objectives: There are few studies that have examined posterior cingulate gyrus size in mood disorder. We hypothesized the volumetric reduction at posterior right cingulate gyrus is tightly associated with the late-onset mania.
Methods: We recruited 44 bipolar patients, including 25 early-onset and 19 late-onset bipolar patients, and underwent volumetric magnetic resonance imaging at 1.5 T. The analytic method is based on hidden Markov random field model with expectation-maximization algorithm. The cut-off age was 45 years old.
Results: Volume of left caudate (p = 0.022) and left medial frontal cortex (p = 0.013) appeared significantly larger in late-onset group. On the contrary, post right cingulate gyrus appeared smaller in late-onset group (p = 0.019). Comorbidity with cerebro-vascular disease revealed higher in late-onset mania (p = 0.072).
Conclusions: The volume posterior right cingulate gyrus decreases in late-onset mania. It is one of the most resistant areas to aging effect. Our data showed potentially more prevalent cerebrovascular disease exists in late-onset group. These findings provide the volumetric change of posterior right cingulate gyrus might play a role of late-onset mania. However, the causal relationship needs further studies.
PS02.53
A symptomatologic consideration of somatoform disorders in the elderly
Keisuke Inamura; N Tsuno; S Shinagawa; K Nakayama
The Jikei University School of Medicine, Tokyo, Japan
Somatic complaints are common in elderly people. Somatoform disorders in elderly are related to various factors characterized by ageing process such as functional decline, increase of physical illness, psychosocial problems and life events. Moreover, the etiology of somatoform disorder is more heterogeneous in elderly people than in younger. It is reasonable to assume that there are some differences between younger and older people regarding the symptomatology of somatoform disorders. However, the current diagnostic criteria of somatoform disorder, such as DSM-IV or ICD-10, do not take into consideration ageing related factors.
In this pilot study, we examined the symptomatologic difference of somatic complaints in elderly patients with somatoform disorder. Admitted elderly patients diagnosed with somatoform disorders by DSM-IV-TR were divided into two groups; positive group: patients with positive findings at MRI, SPECT or EEG; and negative group: patients without these findings. Patients were excluded if they had received a diagnosis of dementia or organic brain syndrome.
Results suggested some significant symptomatologic differences between positive group and negative group. Somatic symptom showed more stereotyped complaint in positive group than in negative group. The characteristics of complaints are defined as follows;
1. Somatic complaints are egosyntonic.
2. Strength of somatic complaint is not associated with depressive mood.
3. Strength of somatic complaint had no waxing and waning and never develop by psychosocial factors.
4. Patients rarely talk about the opportunities causing somatic complaints.
5. The form and expression of complaints is stereotypic.
Some of the differences seen between positive group and negative regarding the symptomatology of somatoform disorders may be due to differences between etiology and phenomenologic profile in the disorder. The result of this report would enable an effective treatment in elderly patients with somatoform disorders.
PS02.54
Link between psychological stressors and burden of medical conditions in older adults: A psychosomatic approach
Ali Javadpour
Shiraz University of Medical Sciences, Shiraz, Iran
Objective: While many studies have focused on the relationship between stress and health, few have examined the impact of psychological stressors on physical health in older adults. In geriatric practice the impact of psychological distress on health status has been undermined due to ageism, atypical presentation and less tendency to report negative affect among elderly people. The current study investigated the correlation of psychological distress and burden of medical conditions in a sample of older people.
Method: A convenient study sample of 120 elderly subjects recruited from the places where there was greater chance for the elderly people to attend. Data collected by a trained research assistant using perceived stress scale, cumulative illness rating scale, geriatric depressive scale and a demographic questionnaire.
Results: Our participants perceived higher level of stress than the average for their age. Moreover, in current study, the burden of medical condition significantly correlated to the level of perceived stress (r = .197, p = .044). In further regression analysis perceived stress was the strongest predictor for physical health morbidity (R2 = .049, significant f = .03) as well.
Conclusions: The result of this study suggested that the psychological stressors contribute to poor health outcome in older adults, the era that is usually overlooked due to ageism and age related physiological changes. The medical practitioners could consider a psychosomatic approach in dealing with medical conditions in their aged patients.
PS02.55
Compassion fatigue: Myths and realities for professionals working with older adults
Elaine Jurkowski
Southern Illinois University Carbondale, Carbondale, IL, United States
Compassion Fatigue (CF) is becoming recognized in helping professions as a silent disease which is beginning to impact people in the helping professions who are increasingly stressed, and impacted by trauma for prolonged periods of time. Professionals working with older adults are a group of silent victims, whose vulnerability is often unnoticed and underestimated. Thus, unrecognized CF for professionals can lead to a lack of ability to detect signs of mental distress for older adult consumers. This presentation will describe some of the signs and symptoms of CF, differentiate CF from “burnout” and present some findings on the incidence and prevalence for professionals working with older adults. Data examining CF from professionals working in urban and rural settings in the United States will be explored to showcase how this silent epidemic is impacting the lives of people in helping professions. A compassion fatigue scale, which measures areas of compassion satisfaction, compassion fatigue and burnout will be examined among a sample of helping professionals. Findings suggest that the longer a person has been in their specific role, the more likely they are to be suffering from burnout and compassion fatigue, and the more likely they are to suffer from dissatisfaction with their role. Solutions will be addressed at the conclusion of the paper.
PS02.56
Rehospitalisation in late-life mental illness: Can patient characteristics provide clues to prevent readmissions?
N Kang1; Barbara Buree1; R Malyuk1; C Wong2; A Kang1
1Riverview Hospital, Coquitlam, BC, Canada; 2Simon Fraser University, Burnaby, BC, Canada
The geriatric psychiatry program at Riverview Hospital (RVH), a provincial tertiary care facility, mandates the use of standardized clinical assessment of all patients at admission, every three months and at discharge. Assessments include the Neuropsychiatric Inventory to assess psychiatric problems, the Functional Independence Measure to determine ADL needs, the Modified Cumulative Illness Rating Scale to establish medical complexity, and the RVH Geriatric Psychiatry Needs Assessment to identify clinical, diagnostic and demographic characteristics and are linked to the Medication Administration Record. This information is used to measure outcomes of treatment and aid in determining treatment options during the hospital stay.
A project to retrospectively analyze outcome data received ethical research approval and facilitated the development of a clinical database. Analysis of admission and discharge data after 4 years of entry found that the scales were sensitive to change. At discharge, patients had fewer psychiatric symptoms, were improved behaviourally and functionally more independent. Level of cognitive impairment was a moderating variable for care requirements and length of stay. It also revealed that greater than 60% of the population requiring hospitalization were patients with moderate-severe dementia with behavioural symptoms.
At the present time, over 900 patient admissions have been added to the database. With the move to providing provincially decentralized geriatric psychiatry care, the number of patients requiring readmission and the potential impact on community facilities has not been well studied. This study delineates the characteristics of patients readmitted to our program.
Methods: Retrospective review of all patients readmitted over the most recent five-year period. Demographic, diagnostic and behavioural characteristics, scale scores and medication information are compared with the total patient group. SPSS was used for summary and multivariate statistics.
Results: Readmitted patients were significantly more likely to have a diagnosis of chronic mental illness such as depression (with previous episodes), schizophrenia spectrum disorders and bipolar disorders. These patients were younger, less cognitively impaired and more independent functionally, particularly with regards to mobility. The majority of patients were readmitted from long-term care (LTC) facilities, followed by acute care hospitals.
Conclusions: Although tertiary geriatric psychiatry admissions are dominated by patients with moderate to severe dementia with behavioural symptoms, patients with chronic mental illness (CMI) are more likely to be readmitted. These readmissions can impact the quality of life of patients, not only by the relapse of psychiatric conditions but also the disruptive change in treatment milieu. In addition, hospitalizations are the most costly means of providing health care.
These preliminary results clearly identify the need for close community follow-up of elderly patients with chronic mental illness. Identifying early signs of relapse may signal an opportunity for assertive interventions to prevent readmissions. It is of interest to note that the majority of these readmissions come from long-term care facilities. Dementia diagnoses now predominate in LTC; younger, more cognitively intact and higher functioning CMI patients do not fit well into the LTC model and may require specialized support to minimize rehospitalisations.
PS02.57
Association of cognitive dysfunction with white matter hyperintensity in Alzheimer's disease and mild cognitive impairment
Baik Seok Kee; S Yoon; D Park; Y Lee
Chung-Ang University Hospital, Seoul, South Korea
Objectives: We investigated the relationship between periventricular and deep white matter hyperintensity and cognitive function in Alzheimer's disease and mild cognitive impairment.
Methods: T2-weighted MRI scans were performed in 41 subjects with Alzheimer's disease, 38 subjects with mild cognitive impairment and 38 control subjects. Periventricular and deep white matter hyperintensities were rated on a Fazekas 0–3 scale by a medical specialist of the department of radiology blind to clinical diagnosis. Cognitive function was assessed by using Cognitive Assessment and Reference Diagnoses System.
Results: No significant differences between demographic characteristics and vascular risk factors were revealed comparing AD, MCI and controls. The frequencies of AD were significantly higher than those of MCI and normal control in grade 2 and 3 of periventricular hyperintensity and grade 3 of deep white matter hyperintensity. The scores of amnesia, executive function and attention were significantly lower in grade 2 and 3 of periventricular hyperintensity than in grade 0 and 1. The scores of attention were significantly lower in grade 3 of deep white matter hyperintensity than in grade 0, 1 and 2.
Conclusion: Periventricular hyperintensities are associated with cognitive decline in amnesia, executive function and attention, while deep white matter hyperintensities are associated with cognitive decline in attention.
Key words: white matter hyperintensity, Alzheimer's disease, mild cognitive impairment
PS02.58
A correlation among plasma Aβ42, depressive symptoms, and cognitive function in the Korean elderly
Do Hoon Kim1; S Kang2; Y Moon3
1Chuncheon Sacred Heart Hospital, Hallym University, Chuncheon, South Korea; 2Chuncheon National Hospital, Chuncheon, South Korea; 3Chuncheon Sacred Heart Hospital, Hallym University, Chuncheon, South Korea
Objectives: This study aims to investigate whether plasma Aβ 42 levels are associated with depressive symptoms and/or cognitive function in community dwelling elderly.
Methods: Subjects were 132 participants of a population-based study of community dwelling elderly above 65 year old for early detection screening project in Inje and Cheolwon area in Gangwon province. Symptoms of depression were evaluated by SGDS-K (Short Geriatric Depression Scale of Korean version) and MMSE-KC (Mini-Mental State Examination-Korean version) scale was used to assess cognitive function. Plasma Aβ 42 levels were measured with human amyloid beta ELISA Kit.
Results: The elderly with depression (SGDS-K score > 8) had lower plasma Aβ 42 than those without depression (p < 0.05). Plasma Aβ 42 levels were positively correlated with SGDS-K score (p < 0.05). However, MMSE-KC score was inversely associated with plasma Aβ 42 level (p < 0.01). In regression analysis, plasma Aβ 42 level was associated with MMSE-KC (β = −0.27, F = 9.65, p < 0.01) and SGDS-K (β = 0.19, F = 5.00, p < 0.05).
Conclusion: Depressive symptoms and cognitive decline were associated with high level of plasma Aβ 42 level in community dwelling elderly. Prospective cohort study may be needed in a large community elderly sample in the future to confirm these associations.
PS02.59
Clinical characteristics of mild cognitive impairment subjects of Korean dementia clinics
Seong Yoon Kim1; C Chung1; J Lee1; D Na3; K Cha2; S Kim5; D Kim4
1Asan Medical Center, Seoul, South Korea; 2MunGyeong Jeil Hospital, MunGyeong, South Korea; 3Samsung Medical Center, Seoul, South Korea; 4Samsung Medical Center, Seoul, South Korea; 5Seoul National Univ. Bundang Hospital, SeongNam, South Korea
Introduction: The Clinical Research Center for Dementia (CRCD), a clinical research group of neurologists and psychiatrists specializing in dementia, has started a longitudinal cohort study (the CREDOS, Clinical Research for Dementia of South Korea) to build up a hospital based cohort of dementia patients.
Purpose of this article: Early stage of dementia can not be clearly defined because of the overlap with the deteriorating cognitive abilities of normal adults. The clinical characteristics of the mild cognitive impairment (MCI) subjects and vascular MCI (VCI) subjects recruited to the cohort might be helpful in delineating the clinical differences among MCI, VCI and normal subjects.
Methods: For the diagnosis and registration, the authors developed the Dementia Evaluation Package, which is comprised of the clinical evaluation form and caregiver questionnaire. Online registry for the CREDOS study was also set up.
Standardized neuropsychological battery used for the evaluation of the cognitive state of the subjects were either Seoul Neuropsychological Screening Battery (SNSB) or CERAD-NP Korean version (CERAD-NP-K). On the T2 axial or FLAIR images, the authors evaluated the severity of ischemia according to the modified Fajekas's and Shelten's criteria. The area around the lateral ventricles (periventricular area) and deep white matter area (especially the centrum semi ovale area) was separately evaluated and the results were combined to give out a final ischemia score.
Considering the two most important axes of cognition and white matter lesion on MRI, we thought we can map dementia with slowly progressive type on the two dimensional plane, which is composed of “cognition impairment” on Y axis, and “ischemia on MRI” on X axis. Hence, the D-matrix (diagnosis matrix). Subjects included in II-1 or II-2 were defined as MCI, and subjects included in II-3 were defined as VCI.
A total of 386 subjects of mild cognitive impairment were recruited from the dementia clinics of 45 centers. Among them, 363 subjects were classified as mild cognitive impairment (MCI), and remaining 23 subjects as vascular MCI (VCI).
Results: The subjects of two groups (MCI and VCI) were assigned to four subtypes of MCI: Amnestic MCI multiple domain (MCI vs. VCI, 55.9% vs. 69.6%), Amnestic MCI single domain (27.3% vs. 4.4%), Non-amnestic MCI multiple domain (2.8% vs. 8.7%) and Non-amnestic MCI single domain (14.1% vs. 17.4%). Cognitive impairment of multiple domains was more prevalent in VCI than in MCI (58.7% vs. 78.3%) but memory domain impairment was more prevalent in MCI than in VCI (83.2% vs. 73.9%). There was no significant difference in the geriatric depression scale scores and MMSE scores between MCI and VCI.
Discussion: These results showed the clinical characteristics of the MCI subjects and the different prevalence of MCI and VCI.
Acknowledgement: This study was supported by a grant of the Korean Health 21 R&D Project, Ministry of Health & Welfare, Republic of Korea (A050079).
PS02.60
The use of the occupational therapy intervention in a Singapore nursing home
Ls Lee1; P Han2
1Man Fut Tong Nursing Home, Singapore, Singapore; 2Alexandra Hospital, Singapore, Singapore
In Singapore, there are approximately 390,000 elderly persons aged over 65 years in the year 2008, constituting to about 8.5% of the total population. By year 2030, this number is estimated to reach 796,000 or 18.9% of our population. When the elderly cannot care for themselves or their family cannot cope with the elderly caregiving needs, institutionalization may become an option. There are currently 64 nursing homes in Singapore, comprising 35 private homes and 5 voluntary welfare homes. In total, they provide about 6,400 beds and have an occupancy rate of close to 90%. Elderly often view nursing home as an unwanted last option and relate poor quality of life (QOL) in nursing home.
This paper illustrates how Occupational Therapy (OT) intervention is done in a local nursing home. The role of the Occupational Therapist is to optimise and maintain the residents' participation in occupations and activities of daily living to prevent functional decline and improve in QOL. Using the person centered care approach, programmes and activities are being planned and implemented based on the results of the assessments.
Assessments such as Abbreviated Mental Test, Interest checklist, Fall risk assessment, Modified Barthel Index, Resident Assessment Form and semi structured interview were used to gather information on the cognitive, physical and psychological status of the patients.
The intervention mainly included activities of daily living and instrumental activities of daily living retraining, cognitive therapy, physical and wellness activities, social and recreational activities, reminiscence therapy, and community integration. Collaboration with external organization on different projects created more variety of activities for the residents.
These OT interventions that focus on rehabilitation and promoting QOL were used to prevent functional decline of residents in nursing home apart from providing medical and nursing care to the residents. Further research would be required to examine the effectiveness of such OT interventions in long term facilities in Singapore.
PS02.61
Magnetic resonance imaging (MRI) DVD patient education for improving MRI knowledge and reducing anxiety in older adults undergoing MRI procedures
Wen-li Lee1; H Sung2; L Huang3
1Tzu Chi College of Technology, Hualien, Taiwan; 2Tzu Chi College of Technology, Hualien, Taiwan; 3Tzu Chi General Hospital, Hualien, Taiwan
Anxiety has been reported for patients undergoing MRI procedures. Anxiety associated with such procedures may be related to unfamiliarity with the procedures, concerns about their prognosis, the predictability of aversive experiences, anticipation of discomfort, and lost of control. The MRI environment may be intimidating and unpleasant for older adults undergoing such procedure, and sometimes it can result in interruption or termination of the scan, which can lead to a waste of resources and negative clinical impacts on patient's treatment process. Written materials about MRI have been the common strategies that are distributed to the patients undergoing MRI prior to their examinations in many clinical settings; however, written information may be inadequate and may not be read when older adults have difficulties in reading or have considerable anxieties. Face-to-face patient teaching is less likely to be taken place when there are constant problems of shortage of staff in busy radiological departments. Therefore, a well-designed MRI patient education that is suitable for older adults will be essential to assist in improving the MRI knowledge and reducing the level of anxiety of older adults undergoing MRI. This study aimed to evaluate the effects of MRI DVD patient education on MRI knowledge and level of anxiety in older adults undergoing MRI. This study used a one-group pre and post-test design. All participants were assessed for MRI knowledge by a MRI knowledge questionnaire and their level of anxiety by Spielberger Trait Anxiety Inventory-State (STAI-S) at baseline and post-test prior to their MRI procedure. Nineteen participants received a 10-minute MRI DVD patient education via a portable computer prior to their MRI procedure in addition to routine MRI printed material. The study found that after receiving the MRI DVD patient education, the MRI knowledge of the older adults were improved significantly (p = .027), and their anxiety was reduced significantly (p = .001). A 10-minute MRI DVD patient education can be a useful strategy to assist in improving older adults' MRI knowledge and reduce their anxiety when there is short of staff for face-to-face patient teaching for examinations and procedures in the clinical settings. The MRI DVD patient education can be a strategy which is effective, easy to implement, and requires less staff in a busy radiological department.
PS02.62
Regional brain gray matter changes in Alzheimer's disease with delusion: 2-year follow-up study
Hae Woo Lee2; H Jeon3; S Jang4; J Bae5; J Lee6; J Kim7; J Sohn9; B Kim8; J Cho1
1Seoul National University College of Medicine, Seoul, South Korea; 2Seoul National University College of Medicine, Seoul, South Korea; 3Sungkyunkwan University School of Medicine, Seoul, South Korea; 4Kyungpook National University College of Medicine, Daegu, South Korea; 5College of Medicine, Inha University, Incheon, South Korea; 6Seoul National University Boramae Hospital, Seoul, South Korea; 7Dongguk University International Hospital, Goyang, South Korea; 8Seoul National University College of Medicine, Seoul, South Korea; 9Seoul National University College of Medicine, Seoul, South Korea
Delusion is common psychiatric and disabling symptom in subjects with Alzheimer's disease (AD). The aim of this study was to investigate the regional alteration in regional gray matter densities associated with the delusion in AD in 2-years longitudinal follow-up. A total of 44 patients with Alzheimer's disease (18 subjects with delusional symptom/26 without delusional symptom) was included in this study. We assessed the subjects by clinical evaluation, the CERAD-K battery, the Neuropsychiatric Inventory (NPI), and MR imaging at baseline and at 2-year follow up respectively. The MR brain images were transformed with spatial normalization and analyzed with a voxel based morphometry (VBM) using SPM5. MMSE scores were significantly decreased in AD with delusion group from 17.1 to 13.2 (p = 0.0002), but not in AD without delusion group (p = 0.27). The gray matter densities showed significant difference between those with delusion and without delusion in Rt. parietal lobe and precuneus at baseline. At follow up, the gray matter density of right frontal lobe significantly reduced in the delusional group, compared with the non-delusional group (Z = 4.39, p < .001). In conclusion, the reduction of regional gray matter densities differs between AD with delusion group and without delusion group at follow-up, especially in the right frontal lobe.
PS02.63
Performance of the General Practitioner Assessment of Cognition (GPCOG) in people with low education
Dong Woo Lee1; J Choi2; K Oh3; S Kim4
1Sanggye Paik Hospital, Inje University, Seoul, South Korea; 2National Medical Center, Seoul, South Korea; 3Kangbuk Samsung Hospital, School of Medicine, Seoul, South Korea; 4Dong-A University College of Medicine, Busan, South Korea
Purpose: General practitioner assessment of cognition (GPCOG), developed by Brodaty, is a novel and promising screening test of dementia. In this study, we evaluated the performance of Korean version of GPCOG (GPCOG-K) in people with low education.
Method: 1) 92 elderly people living in community were evaluated with GPCOG-K. 2) All the subjects underwent psychiatric assessment including MMSE, Geriatric Depression Scale-short version, neuropsychological battery of Consortium to English a Registry of Alzheimer's Disease Korean version (CERAD-K(NP)), and clinical interview for diagnosis of dementia by geriatric psychiatrist. 3) Receiver operator characteristic (ROC) analyses were used to assess the performance of the GPCO-K in people with low education. The results of the analysis was compared with that in the whole subjects.
Results: 1) There were 44 low-educated people whose education year was 3 years or less. 2) In this group, area under the curve (AUC) of GPCOG-K (total items) was 0.931, and AUC of MMSE was 0.825. 3) The optimal cut-off point of GPCOG-K (total items) was 3/4 in low-educated people, and was 4/5 in the whole subject.
Conclusion: 1) GPCOG-K was superior to MMSE in detecting dementia in people with low-education. 2) Applying a different cut-off point of GPCOG for low-educated people may result in better performance of GPCOG-K.
PS02.64
Saliva cortisol awakening response in patients with mild cognitive impairment
Karin Lind; A Edman; A Nordlund; A Wallin
Institute of Neuroscience and Physiology, Mölndal, Sweden
Background: In a previous cross-sectional study, an increased cortisol awakening response (CAR) was demonstrated in patients with mild cognitive impairment (MCI), by contrast with healthy controls. The results speak in favour of the involvement of stress-related mechanisms in the pathogenesis of MCI.
Objectives: The aim of the present study was to test if CAR may predict deterioration from MCI into overt dementia.
Material and method: 38 patients with MCI and 13 healthy controls were included in the two-day study. Saliva samplings were performed five times in day one before an evening intake of 0.5 mg dexamethasone, and five times the following day. Unbound cortisol was analysed in each sample. The procedure was repeated after a 2-year period. Cognitive function was assessed by way of the Mini-Mental State Examination.
Results: Preliminary results did not demonstrate a CAR pattern that predicts the further progression from MCI to dementia. Also, the change in cortisol levels was not congruent with changes in cognitive impairment during the study period.
Conclusion: The results of the present study did not provide evidence for the involvement of stress-related mechanisms in the further deterioration from MCI to overt dementia.
PS02.65
Promoting seniors mental health and well being: The seniors policy lens toolkit
Penny MacCourt
University of Victoria, Nanaimo, BC, Canada
The Seniors Mental Health Policy Lens (SMHPL) is an analytical tool, made up of a set of questions intended to promote the mental health/wellbeing of older adults, and to guide the analyses of policies and programs from a seniors' mental health perspective. The Seniors Policy Toolkit integrates the SMHPL with other Policy Lens (e.g., disability, gender), and provides background information about key concepts (e.g., principles of mental health promotion; determinants of health), and marginalized seniors' (e.g., low income; developmentally challenged, mentally ill). We have evaluated the implementation of the SMHPL and developed it as a best practice in seniors' mental health policy design. To date, the SMHPL has been implemented by government and non-government pilot sites across Canada, and adopted by the Mental Health Commission of Canada. We will describe the evaluation of the implementation of the SMHPL Toolkit, for a variety of purposes (such as advocacy, program re-design, community development), and share the results of doing so.
PS02.66
Effectiveness of psychiatric day hospital care for elderly patients with depression
Corina Carmen Meiler
Hôpitaux Universitaires, Genève, Switzerland
Although previous studies suggested that psychiatric day hospital care is a valuable alternative to inpatient treatment, its effectiveness for elderly patients is disputed. Small number of cases, poor definition of the psychotherapeutic setting and absence of systematic assessment at different time points may explain the observed discrepancies. We performed an assessment of a psychiatric day hospital treatment combining individual and group psychotherapy in a series of 122 elderly depressed outpatients with major depression or a depressive episode of bipolar disease. The geriatric depression scale, the short survey scale, the therapeutic community assessment scale and the group evaluation scale were repeated at admission, 3, 6, and 12 months and at discharge. The variables included severity of depressive symptoms, quality of life, adhesion to therapeutic community treatment and progress in groups of psychotherapy, art-therapy and psychomotricity. There was a significant reduction of depressive symptoms and improvement in mental quality of life across all time points studied. Also adhesion to therapeutic community increased and the progress in group therapy for all three groups used. Neither demographic characteristics, nor pharmacological treatment or presence of stressful life events predicted the clinic improvement. Conclusion: psychotherapeutic care program in day hospital might improve clinical status and quality of life in elderly depressed patients. It prevents from chronification of depressive disorder, helps patients to stay in their habitual environment and prevents from early institutional living.
PS02.67
Identifying capable raters for global Alzheimer's disease clinical trials: Challenges & potential solutions
D Miller; P Samuelson; K Foulds
United BioSource Corporation, Wayne, PA, United States
Background: Clinical trials in Alzheimer's disease have become increasingly global in nature. There are multiple explanations for this, including competition for patients, regulatory mandates and the likelihood of being able to more quickly achieve enrollment targets. However, with this geographic expansion, identifying raters with relevant clinical as well as clinical trial experience with this population as well as familiarity with the efficacy instruments is often challenging. As a result of this, one sponsor responded by proactively identifying these less experienced raters and providing additional training and assessment of them prior to their attending the Investigators’ Meeting (IM). Once they successfully completed their initial assessments, they would attend the IM and attempt the certification exercises with the entire group of raters. The results of this enhanced training on overall certification are described below.
Methods: Potential raters were identified as requiring enriched training based upon their experience falling below a level mutually agreed upon by both the sponsor and the rater training company. Those raters were then given enhanced didactic presentations on the primary efficacy instruments (ADAS-Cog and ADCS-ADL) and were asked to watch and rate a video interview of both instruments before attending the IM (this includes those who met criteria on their initial attempt, and those who required remediation to do so). After attending the IM, they, as part of the larger group of potential raters, were asked to watch and score a different set of videos for certification.
Results: 24% of the raters (102/419) were deemed to require enriched training. All 102 raters successfully completed the enriched training, and 84 of them (82%) met scoring certification criteria on the post-IM ADAS-Cog and 100% met the criteria on the post-IM ADCS-ADL video. This compared favorably to the experienced raters (n = 320) who were not deemed to need enriched training. That group had 269 raters (85%) successfully score the ADAS-Cog video, and 317 (99%) the ADCS-ADL video. Those raters who lacked the prerequisite experience levels also had to demonstrate their interviewing competency in additional certification exercises.
Conclusion: As Alzheimer's disease clinical trials continue to involve an increased number of countries, it is imperative to address the issue of how to successfully train raters who have less experience with this population as well as limited familiarity with the efficacy instruments. The program described above, which involves pre-IM training, demonstration of competence on multiple scoring exercises both before and at the IM, as well as on interviewing, proves that these raters can be successfully trained to criteria to rate in studies. This group of raters will continue to be monitored to determine how they perform over the course of the trial, both as a group and compared to the group of more experienced raters.
PS02.68
Psychological distress and quality of life in older people undergoing surgery
Snezana Mitrovic-Tosovic1; P Melding1; F Stapelberg2; P Merrick5; J Bryce4; R Worrall3; C Howie4; A Clark4; L Rowlands4
1Waitemata DHB, Auckland, New Zealand; 2Middlemore Hospital Counties Manakau District Health Board, Auckland, New Zealand; 3Auckland Hospital District Health Board, Auckland, New Zealand; 4Center for clinical Research and effective practice., Auckland, New Zealand; 5Massey University, Auckland, New Zealand
Psychological distress is commonly seen as a factor affecting wide variety of human functioning including sense of well-being and perception of quality of life.
The aim of this study was to examine psychological distress and its association to perception of quality of life in older people pre and post undergoing elective orthopedic surgery. This study was part of larger study examining Post Operative Cognitive Decline (POCD).
Study design: longitudinal cohort study
Setting: Two hospitals performing orthopedic surgeries in Auckland, New Zealand
Method: 240 people aged >55, recruited randomly from hospitals waiting lists. Assessment involved measures of negative emotions (depression and anxiety) measured using Geriatric depression Scale (GDS) and the State anxiety inventory STAI and quality of life measured using COOP charts. Measures were done on two points: 4–5 months prior to surgery and 1 year post surgery.
Results demonstrated a lowering in the number of participants who reported negative emotions and at the same time an increase in perception of quality of life. In addition, participants reported decline in levels of pain and improved ability to actively participate in social activities.
PS02.69
Is that useful? Korean version of the WHO Five Well-Being Index in evaluating depressive symptoms and quality of life in the aged dwelling in community
Yoosun Moon1; H Kim2; D Kim2
1Hallym University College of Medicine, Chuncheon, South Korea; 2Hallym University College of Medicine, Chuncheon, South Korea
Background: Recently the rate of depression in geriatric population has been increasing tremendously. Among many factors affecting depression, quality of life seems to be closely related to depression. Thus, a screening tool for assessing both geriatric depression and quality of life is needed.
Objective: The purpose of this study is to estimate the utility of the Korean version of the WHO Five Well-Being Index (WHO-5) in evaluating geriatric depression and quality of life as compared with SGDS-K (Short Geriatric depression scale of Korean version) that is being used widely.
Methods: A sample of 237 subjects over 60-year old living in Yanggu and Inje area in Gangwon Province, Korea were interviewed and responded to scales, including WHO-5, SGDS-K, MMSE-KC (Mini Mental Status Examination in the Korean version of the CERAD assessment packet) and GQOL-D (Geriatric Quality of Life-Dementia). The total score of WHO-5 below 13 indicates poor well-being.
Results: The score on SGDS-K negatively correlated with scores of WHO-5, MMSE-KC, and GQOL-D. The WHO-5 score inversely correlated with SGDS-K score and positively with GQOL-D, but showed no significant correlation with MMSE-KC score. Poor well-being group (WHO-5 score < 13) had lower GQOL-D score (F = 28.526, P < 0.001) and higher SGDS-K score (F = 54.544, P < 0.001). In multiple regression analysis, WHO-5 was significantly associated with GQOL-D and SGDS-K (R2 = 38, F = 73.76, P < 0.001).
Conclusion: The Korean version of WHO-5 was very useful to evaluate both depressive symptoms and quality of life in the aged dwelling in community. It seems that WHO-5 score advocates the psychologic component without affecting cognitive domain as compared with SGDS-K scale.
PS02.70
The influence of lipid profile on neuropsychological tests in community-dwelling normal elders
Seok Woo Moon1; T Kim1; J Seo1; N Lee2; J Choi1
1Konkuk Univ. Chungju Hospital, Chungju, South Korea; 2Chonju Welfare Hospital for the Elderly, Chonju, South Korea
Background: There were some studies on relationship between lipid profile (such as serum cholesterol level) and cognitive function, but the association is controversial. The aim of this study is to examine the influence of lipid profiles including total cholesterol (TC), high density lipoprotein (HDL), lower density lipoprotein (LDL), and triglyceride (TG) on neuropsychological tests in the normal elderly individuals.
Methods: The total number of subjects was 200 who were diagnosed as cognitively normal. The eight neuropsychological test domains from the CERAD neuropsychological (NP) test battery were conducted to test subjects. The test scores were evaluated by the lipid profiles. The lipid profiles of all subjects were measured including TC, HDL, LDL, and TG levels. All CERAD (NP) tests were done that day of lipid profile testing.
Results: There were no significant correlations between TC, HDL, LDL, and TG levels and neuropsychological test profiles. The HDL level was somewhat correlated with one neuropsychological test domain, but not significant.
Conclusions: The results indicate that the cognitive profiles are not correlated directly with lipid profiles in normal elderly individuals.
PS02.72
Cognitive impairment-free life expectancy in older Thai population
Weerasak Muangpaisan1; P Assantachai1; S Intalapaporn1; K Richardson2; C Brayne2
1Faculty of Medicine, Siriraj Hospital, Mahidol University, Bangkok, Thailand; 2University of Cambridge, Cambridge, United Kingdom
Background: Life expectancy (LE) has now increased globally. However, living longer does not necessarily mean living with good quality of life. Healthy LE is more important. Cognitive impairment (CI) is a major health problem in older population. It is a major cause of disability, decreases quality of life, and has high disease burden. In Thailand, the growth rate of older population is faster than the rates worldwide. Obtaining healthy life expectancy is thus crucial in Thailand to enable the public policy maker to shape health plan strategies and allocate limited resources.
Methodology: The dataset was from the Bangkok Longitudinal Study by Siriraj Hospital for the Older Men and Women (BLOSSOM), which is a community cohort study conducted from the year 2005 onwards in Bangkok, Thailand. The study included 5,936 participants aged 50 years and over from community settings within 6 suburban areas in Bangkok. Thai Mental State Examination (TMSE) score less than 18 was used to define CI as it could affect daily functions and the score is less varied. The cognitive impairment-free life expectancies (CFLE) were calculated using Sullivan's method. The percentage of CIFLE/LE was calculated to take into account the longer total LE in women. The abridged life table for the Thai population, by sex, developed by the WHO 2006 was used.
Results: (see table 1 in supplementary data) The prevalence of people with TMSE less than 18 was 6.2%. Overall, women had shorter CLFE. At the younger age group (<65 years), men and women can expect to spend around 10% and 25–30% of their LE with CI, respectively. At the very old age (>75 years), these figures are expected to be around 20–25% in men and 30% in women.
Conclusion: Women had a shorter expectancy of life living free from CI despite longer total LE. Though LE has increased, a large proportion of older population still suffer CI. Healthcare policy makers should promote preventive strategies to reduce CI in a younger age.
PS02.73
Integration of a geriatric psychiatrist into a neurology department's novel interdisciplinary memory clinic
Robert Nathan; C Manning; D Geldmacher; A Thompson-Heisterman
University of Virginia, Charlottesville, VA, United States
The Memory and Aging Care Clinic of the Department of Neurology is unique in that all disciplines are represented ONSITE during the clinic. This results in continuous communication among the staff concerning each patient seen. We believe that by the interactions illustrated in our poster we will show how our team of Neurologist, Neuropsychologist, Geriatric Psychiatrist, Geriatric/Psychiatric Nurse Practitioner, Social Worker, Nurse Coordinator, and Alzheimer Association Social Worker Representative are able to achieve our stated goals of comprehensive patient and family care.
Details of the operation will be illustrated by the following: (1) initial referral and review of records, including previous Neurological Examinations, Neuropsychological studies and Neuroimaging reports or digital materials; (2) early morning case conference to discuss all new patients as well as returning previously evaluated ones; (3) initial diagnostic evaluation by clinic neurologist; (4) neuropsychology appointment if needed; (5) psychiatry, if needed, done either following the neurological exam, the same day if possible, or at a follow up visit; (6) review of all returning cases and formulation of plans based on individual needs; and (7) viewing of evaluated psychiatric referrals by the psychiatrist along with other disciplines as needed. This same routine is followed at the noon conference for the afternoon patients. Each of the neurologists sees on average two patients in each morning and afternoon session. The follow-up patients usually number between five or six for each of these sessions.
We intend to show how based on these twice daily case conferences we are able to assign appropriate disciplines to each case and then by formal and informal (curbside) interactions, achieve optimal results. Flow charts will illustrate these interactions as the twice daily team meetings direct the team based on patients' needs previously established in the case of returning individuals.
The Clinic is a regional resource for these patients and their families, many of whom travel several hours to reach our location. This has resulted in our frequently having more than one professional in with the family during the examination. It has proven quite effective, for example, to have the psychiatrist and the nurse practitioner see the family together and formulate a treatment plan. At other times the psychiatrist and social worker have worked either together or sequentially on resolving potential placement situations. We have found the Alzheimer Association representative helpful in pointing out resources throughout the region.
In ten months the psychiatrist has evaluated forty seven patients, thirty one women and sixteen men; important summary aspects of these evaluations will be illustrated. Compilations of these clinical examples will be used to show these complex interactions and their outcomes.
Finally there will be an illustration of the economic solutions that have been implemented to ensure adequate reimbursement for the services in order to sustain the model. Differences between this and usual Consultation-Liaison will be outlined.
PS02.74
The effectiveness of continuation-maintenance ECT in reducing depressed older patients' hospital re-admissions
Daniel O'Connor1; B Gardner2; I Presnell1; D Singh3; M Tsanglis4; E White5
1Monash University, Cheltenham, VIC, Australia; 2Wantirna Hospital, Melbourne, VIC, Australia; 3Frankston Hospital, Melbourne, VIC, Australia; 4Caulfield General Medical Centre, Melbourne, VIC, Australia; 5Geelong Hospital, Geelong, VIC, Australia
Objective: To measure outcomes in aged patients with severe, treatment-resistant depression who were given ongoing outpatient continuation-maintenance ECT of varying duration to prevent remission and relapse following a successful course of acute ECT.
Methods: A retrospective chart review of 53 consecutive patients of three Australian aged psychiatry services comparing the number and length of psychiatric admissions before and after the start of continuation-maintenance ECT.
Results: Four patients had only one treatment and two received over 50 (mean 14.1). Four were still enrolled in a maintenance program two years later. In the two years after continuation-maintenance ECT started, admissions fell by 52% in number and 77% in duration compared with the previous two years. Within the actual treatment period, which varied from one patient to another, admissions fell by 94% in number and 96% in duration compared with the same period beforehand.
Conclusion: A treatment effect cannot be proven but the severity and chronicity of patients' conditions make placebo effects and spontaneous remission unlikely. Randomised, controlled trials are almost impossible in this setting and so carefully conducted reviews and case-control studies are still of value. Our findings suggest that continuation-maintenance ECT is effective in carefully selected patients at high risk of relapse.
PS02.75
Depressive symptom clusters are differentially related to intima-media thickness of the carotid artery
Richard Oude Voshaar1; B Bus1; S Holewijn2; A Stalenhoef2; M Heijer2; B Franke3; J de Graaf2
1Radboud University Nijmegen Medical Centre, Nijmegen, Netherlands; 2Radboud University Nijmegen Medical Centre, Nijmegen, Netherlands; 3Radboud University Nijmegen Medical Centre, Nijmegen, Netherlands
Background: Numerous studies have identified a relationship between depression and cardiovascular disease. This relationship may be confounded by complaints originating from subclinical atherosclerotic disease.
Objective: To examine the relationship between depression and subclinical atherosclerotic disease in the general population. We hypothesize that the relationship between depression and atherosclerosis is explained by the somatic-affective symptom cluster and not the cognitive-affective symptom cluster.
Method: Cross-sectional analyses of the baseline data of the 50 through 70 years old subgroup of the Nijmegen Biomedical Study (NBS), a cross-sectional population survey. Subclinical atherosclerortic disease are measured by the intima-media thickness (IMT) of the carotid arteries and depressive symptoms using the Beck Depression Inventory (BDI).
Results: Full data were available of 1261 people (mean age 61 years, 51% female sex). Multiple linear regression analysis yielded a significant association between the sum score of the BDI and the IMT, which remained significant after correction for potential cardiovascular confounders (beta = 0.06, p = .026). Factor analyses of the BDI-items yielded two factors, a cognitive-affective dimension and a somatic-affective dimension; only the latter one was related to the IMT in the fully adjusted models (beta = −.02, p = .43; beta = .15, p < .001, respectively).
Conclusion: The relationship between atherosclerosis and depressive symptoms is explained by the somatic-affective symptom cluster of the BDI, which is in line with the hypothesis that depression might (partly) be an epiphenomenon of atherosclerotic disease.
PS02.76
Bifrontal ECT: A systematic review and meta-analysis of efficacy and cognitive impact
Chris Plakiotis; D O'Connor
Monash University, Cheltenham, VIC, Australia
Our aim is to review the literature regarding bifrontal electroconvulsive therapy (ECT) and provide recommendations for future research in this area. Original publications were retrieved using PubMeD, EMBASE, PsycINFO, and Google Scholar. A systematic review and meta-analysis of randomised clinical trials examining efficacy and/or cognitive effects of bifrontal ECT for the treatment of depression is the centrepiece of this work. The literature regarding bifrontal ECT is limited, with small patient numbers and treatment variation across studies complicating result interpretation. However, our findings suggest that while bifrontal and bitemporal ECT may have similar efficacy, bifrontal ECT is associated with less cognitive impairment immediately after a treatment course. Bifrontal ECT may have greater efficacy than low-dose right unilateral ECT but less efficacy than high-dose right unilateral ECT. Conversely, bifrontal ECT may affect cognition more adversely than low-dose right unilateral ECT, but less so than high-dose right unilateral ECT. To further investigate the likely favourable benefit to cognitive risk profile of bifrontal ECT, detailed cognitive testing should be undertaken as part of any future, large scale studies comparing the efficacy of adequately-dosed bifrontal, bitemporal and right unilateral ECT.
PS02.77
Diagnosis of dementia: Variations between general practices in the north-west of England
Nitin Purandare1; E Gaehl1; H Martin2; J Morris3
1Psychiatry Research Group, Community Based Medicine, University of Manchester, United Kingdom; 2Ashville Surgery General Practice, Manchester, United Kingdom; 3Medical Statistics, South Manchester University Hospital NHS Trust, Manchester, United Kingdom
Background: Dementia is a major and growing health problem. Previous research in old age psychiatry settings suggests that Alzheimer's disease is under-diagnosed and remains untreated. We investigated the variations in “reported” prevalence of dementia and its difference from “estimated” prevalence in primary care.
Method: Six Primary Care Trusts (PCTs) in Greater Manchester provided data on all General Practices (GP) in their area in terms of patient list size, number of male & female patients over 65 years of age, number of patients on their Quality Outcomes Framework (QoF) dementia register and whether each practice was run by one GP (single) or by several GPs (multi).
Results: Sample in analyses included 351 GP practices with 1, 849, 532 registered patients on their lists. The total number of dementia patients on the QoF dementia register was 7405. Prevalence of dementia (rate per 1,000 based on total GP list-size) was: mean = 3.9, median = 3.5, range 0 to 15.6. Prevalence of dementia (rate per 1,000 based on GP list-size of ages 65+) was: mean = 29.9, median = 25.6, range 0 to 204. The prevalence of dementia using dementia registers (3%) seems lower than the reported prevalence of 5% in over 65s. There was significant variation in the prevalence of diagnosed dementia at both micro (GP) and macro (PCT) service organisation level (Wald chi-square 119; p < 0.001).
Conclusion: Further research is required to examine the factors that underlie these variations in diagnosis of dementia in primary care in the UK. It would be interesting to know if similar variations exist in other countries and how they are tackled successfully.
Key Words: Dementia; diagnosis; variations; general practices
PS02.78
Metabolomic fingerprinting: Diagnostic limitations of infrared spectroscopy in distinguishing Alzheimer's disease and non-Alzheimer's disease serum samples
M Zubair; D Broadhurst; W Dunn; P Begley; C Winder; S Francis-McIntyre; A Halsall; D Kell; R Goodacre; A Burns; N Purandare
University of Manchester, Manchester, United Kingdom
Background: Alzheimer's disease (AD) is a neurodegenerative disorder with no known aetiology. In the developed world AD accounts for up to 60% of all dementia cases. The prevalence rate for dementia has been estimated at 25 million people worldwide. The diagnosis of AD is informed over time, by clinical and neuropsychological tests, as well as neuroimaging. There remains a need to develop a non-invasive based quick and accurate diagnostic test, which could detect early AD changes in patients. The Fourier Transform infrared spectroscopy (FT-IR), induces and measures molecular vibrations of known chemical functional groups in biological samples. The resultant output is a characteristic metabolic fingerprint of the sample. Metabolic fingerprinting techniques have been shown to potentially distinguish disease and non-disease samples.
Objective: We wanted to see if metabolic fingerprinting analysis of AD and non-AD samples could identify an AD fingerprint. Secondly, we were interested in seeing whether the AD fingerprint altered with disease severity.
Methods: Serum samples were collected from AD patients (n = 60) at baseline and at 12 months follow-up. Controls (n = 60) were matched for sex and age with the AD baseline samples. A number of cognitive and neuropsychiatric scales were also assessed, to stratify the AD and Control groups. For FT-IR analysis, 1 μl volume of AD, Control, and stock QC serum samples were used. Transmission spectra was acquired over the mid-infrared range (4000–600cm-1).
Results: Multivariate analysis of the sample spectra, showed that there was no vibrational differences between the AD groups and Control.
Conclusion: Metabolic fingerprinting using FT-IR of AD and control serum samples is unable to discriminate between AD and non-AD samples.
Keywords: Biomarkers
PS02.79
Impact of a cholinesterase inhibitor on simulated driving ability in healthy older adults: A pilot study
R Mitchell1; H Moller2; B Murray1; M Bedard3; A Kiss1; C Zucchero Sarracini1; K Lanctôt1; N Herrmann1; Mark Rapoport1
1Sunnybrook, Toronto, ON, Canada; 2Toronto Western Hospital, Toronto, ON, Canada; 3Lakehead University, Thunder Bay, ON, Canada
Driving is central to older adults' independence and autonomy, and more than 75% of persons age 75 and over rely on driving as their primary mode of transportation. A study of healthy, middle-aged pilots showed that donepezil improved retention of skills on flight simulator tasks. There is evidence that cholinesterase inhibitors are effective in improving reaction time, attention and executive functioning in patients with dementia. This study examines whether these properties of the drug have the potential to improve simulated driving ability in the elderly.
This study used a double-blind randomized controlled design. Twenty-two healthy seniors with valid Ontario driver's licenses were recruited from the Metropolitan Toronto area via newspaper advertisements. These subjects were randomized to receive either 5 mg of donepezil or a placebo for 14 days. Subjects’ attention and reaction time were assessed at each time-point using the Psychomotor Vigilance Test (PVT) and the Attention Network Test (ANT) and. Subjects’ driving was assessed at each time-point using the York Driving Simulator with DriveSim 3 software. Outcome variables included number of collisions, deviation from posted speed limits, swerving (deviance from center of the lane), and reaction time to randomly occurring simulated wind gusts. Subjects completed the attention, reaction and driving assessments at three separate time-points: T0 – immediately before taking the first dose of donepezil or placebo, T1 – four hours after taking the first dose, and T2 – after 14 days of taking donepezil or placebo.
Eleven subjects were randomized to receive donepezil and eleven to the placebo group. Preliminary analysis of data indicated no significant group-by-time interaction for any of the variables. The placebo group, however, had a significantly faster reaction time to wind-gusts on the driving test at T2 (1.18 ± 0.26 seconds) vs. the donepezil group (1.69 ± 0.46 seconds) (F(1,19) = 8.99; p = 0.008). In addition, the placebo group had significantly reduced deviation from the center of the lane at T2 (±2.06%) vs. the donepezil group (±4.83%) (F(1,19) = 4.90; p = 0.040), and deviation of road position (±1.06%) vs. the donepezil group (±2.54%) (F(1,19) = 5.23l; p = 0.035). The groups did not significantly differ in reaction time at T2 on the PVT or ANT.
These findings are contrary to previous studies investigating the role of cholinesterase inhibitors in a healthy, younger population. Our findings point to a possible initial sedating effect of this treatment in the older population. The present study suggests the need for further studies investigating the impact of pharmacological agents on driving in older patients and those with dementia.
PS02.80
1H NMR studies of eritrocyte membrane permeability in hypertensive elderly patients complicated with stroke
Floarea Revnic; C Revnic
NIGG “Ana Aslan”, Bucharest, Romania
Introduction: Nuclear magnetic resonance (1H NMR) relaxometric exploration of peripheral blood is a useful tool in characterization of some biophysical aspects occurring in cardiovascular and cerebrovascular diseases and in the onset disease prediction.
Objective: The aim of our study was to evaluate eritrocyte membrane permeability (EMP) to water, in patients with HTA in different evolutionary stages complicated with stroke by means of 1H NMR method with an AREMI Spectrometer 0,6T, proton resonance at 25MHz. Another objective of our studies was related with the evaluation of negative charges ratio inside and outside of eritrocyte membrane by means of Na36Cl radioactive uptake method.
Material and method: 120 patients aged between 39–78 years old divided into two groups of 60 patients each: group A hypertensive patients from Cardiovascular Clinique of cardiovascular Disease Institute, have been taken in our study and 60 age matched controls. Results and discussion: Our studies have pointed out that different types of stroke exhibit a wide range of EMP values, in general below those of controls. The highest values of EMP were recorded in stroke associated with cardiovascular pathologies and the lowest values were recorded in ischemic stroke. Na36 uptake studies have pointed out that in the case of stroke patients there is an increase in quantity of negative charges within the eritrocytes and this fact could be implicated in Donnan equilibrium alteration with consequences upon membrane permeability to water.
Key words: erythrocyte membrane permeability to water (EMP), nuclear magnetic resonance (NMR), stroke, arterial hypertension
PS02.81
The relation between carotid stenosis and risk of stroke in hypertensive diabetes and non-diabetes patients
Cristian Romeo Revnic
UMF “Carol Davila”, Bucharest, Romania
Essential arterial hypertension (EHAT) is one of the main risk factors for ischemic stroke. The evaluation of intimal thickening of carotid is an important parameter in preclinical diagnosis of atherosclerosis and stroke risk evaluation in hypertensive patients. The aim of the study was to see whether there is a relationship between thickening of carotid wall and brain damage in hypertensive patients with/without diabetes. Our study has been done on 100 patients admitted in Neurological Clinique over two years.
At admission, the patients have been neurologically examined, being divided into two groups of 50 patients each: group A with type II diabetes and group B non-diabetes, symptomatic with stroke or asymptomatic, mean age: 62.31+/−6.9 years old. Carotid Doppler ultrasound examination and cranial NMR were evaluated. NMR findings were white matter lesions and infarctions. They were more frequent in hypertensive diabetes group. In hypertensive non-diabetes there were insignificant correlations between abnormal NMR findings and thickening of carotid wall versus non-diabetes. In diabetes, the associations among cortical lesions, clinically symptomatic stroke, and increasing in carotid wall thickness were found to be statistically significant in comparison with non-diabetes. NMR abnormalities were present in 90% in group A and 72% in group B consisting of arterial constriction or an atheromatous plaque confirmed in Doppler examination. Measurements of carotid wall thickness via Doppler were considered to be valuable in prediction of risk of brain damage and future stroke due to hypertension in diabetes and non-diabetes patients.
PS02.82
Clinical characteristics, psychopathology and response to treatment of elderly shoplifters
Matt Robillard; D Myran
University of Toronto, Toronto, ON, Canada
Purpose: The study was designed to detail the demographic, phenomenological, treatment response and legal disposition data in a group of elderly patients with shoplifting and kleptomania.
Method: Psychiatrists in the Department of Psychiatry at University of Toronto were canvassed to see if they were providing care to elderly patients with a diagnosis of kleptomania or had patients whom were shoplifting. A chart review was done on these outpatients and then the information was collected and analyzed.
Results: A case series of patients was collected. Data was collected for sex ratio, marital status, living arrangements, age of onset, course, items stolen, reasons listed by patient for this behavior, medical and psychiatric comorbid conditions, history of psychiatric medications and legal disposition including diversion.
Conclusions: Shoplifting behavior was not common in the psychiatric outpatient services at a large urban academic teaching hospital in Toronto. Onset of shoplifting behavior tended to have early onset and was chronic in nature. It was unrelated to medical conditions such as Parkinson's disease and cancer. None of the patients were holocaust survivors. Most common psychiatric illness was a mood disorder but the shoplifting events were not always clearly linked to mood or psychotic symptoms at the time of offence. None of the patients had attempted suicide. Patients often showed an unwillingness to get help for these symptoms and wished to deal with it on their own. Trials of SSRIs did not seem to help the behavior. In the case of one patient, adding a mood stabilizer and discontinuing the SSRI appeared to have arrested the shoplifting behavior.
PS02.83
Caregiver accounts of troublesome symptoms in people with dementia: A web-based survey
K Rockwood1; A Mitnitski2
1DementiaGuide Inc, Halifax, NS, Canada; 2Dalhousie University, Halifax, NS, Canada
Background: The clinical meaningfulness of treatments for dementia is debated. Clinical trials have been criticized for not incorporating patient and caregiver perspectives, or for limiting their input to standardized quality of life questionnaires, which might not always reflect their preferences [Molnar et al. J Am Geriatric Soc 2009;57:536–546]. Here, we report a web-based survey in which caregivers track troublesome symptoms of dementia.
Spearmann correlation coefficients between the QUALID and other measures (N = 169)
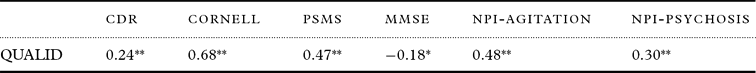
**.Correlation is significant at the 0.01 level (2-tailed)
*.Correlation is significant at the 0.05 level (2-tailed)
Methods: The data come from 522 users of the website www.dementiaguide.com, which provides information on 60 common dementia symptoms. Users are invited to select and track troublesome dementia symptoms in the people for whom they care. The data were analyzed using connectivity graphs; here the density of connections is reported. Higher density reflects a symptom being more commonly reported, with more item descriptions endorsed, and more often seen in association with other symptoms. Cluster analysis was used to identify symptom groupings.
Results: Most caregivers using www.dementiaguide.com tracked between 6–10 symptoms; 54 symptoms were tracked by at least 10% of users. The most informative symptoms were physical complaints (density score = 17); misplacing/losing objects (13); independence (10); meal preparation/cooking (9); comprehension/understanding (9); social interaction/withdrawal (8); and repetitive questions/stories (8). Cluster analysis revealed a milder group and a more severely affected group.
Discussion: Caregivers give priority to a variety of dementia symptoms. In mild dementia, impaired executive function is prominent. In moderate dementia, agnosia and apraxia are common. Many of these symptoms are either not tracked at all, or tracked only indirectly in dementia clinical trials. Efforts to improve the clinical meaningfulness of dementia trials should consider incorporating caregiver perspectives in their evaluation.
PS02.84
The reliability and validity of the Norwegian version of the Quality of Life in Late-Stage Dementia (QUALID) scale
Irene Roen1; G Selbaek2
1Innlandet Hospital Trust, Ottestad, Norway; 2Innlandet Hospital Trust, Ottestad, Norway
Background: There is a growing consensus that quality of life (Qol) is a useful measurement for evaluating treatment interventions towards persons suffering from dementia. We have translated The Quality of Life in Late-Stage Dementia (QUALID) scale, a domain-specific, short, proxy informant based instrument developed by Weiner et al. for assessing quality of life in persons with late stage dementia, into Norwegian. The QUALID scale assesses quality of life in persons with dementia with higher scores indicating worse quality of life. We present the results of a study investigating the reliability and validity of the Norwegian version of the QUALID scale.
Method: The validity study included 169 patients with dementia, all living in nursing homes in the counties of Hedmark and Oppland in the south-eastern part of Norway. Of these, 53 patients also took part in the reliability study. The assessment included a Mini-Mental-State-Examination (MMSE) of the patients and a standardized interview with the nurse who was most familiar with the patient. This interview included, apart from the Qualid scale, the Cornell scale for depression in dementia, the Neuropsychiatric Inventory (NPI), the Physical Self-Maintenance Scale (PSMS), a scale assessing level of functioning, and the Clinical Dementia Rating Scale (CDR). Internal consistency reliability was examined using Cronbach's alpha coefficient. Test-retest reliability was examined by testing the same patient twice within nine days. Intra-class correlation coefficient was calculated. Validity was tested by calculating the Spearman's correlation coefficient between the Qualid score and measures of neuropsychiatric symptoms, cognition and level of functioning.
Results: Reliability study: The mean QUALID score was 22.6 (SD 7.4) The Cronbach's alpha was 0.81. For all items but one (crying), the item-total correlation was higher than 0.3. The intra-class correlation between test and retest was 0.83.
Validation study: The mean QUALID score was 20.7 (SD 7.2) Correlations between the QULAID and cognition, level of functioning and neuropsychiatric symptoms are summarized in table 1.
Conclusions: Our study shows high internal consistency and test-retest reliability of the Norwegian version of QUALID. We found high correlation between depression and the QUALID scale. The correlation between QUALID and level of functioning, degree of dementia, agitation and psychosis, respectively, was significant, but moderate in strength. We found a strong correlation between depression, as measured with the Cornell scale, and QUALID. There was a weak, negative correlation between QUALID and cognition, as measured with the MMSE. Our findings are in line with previous studies and indicate that the Norwegian version of the QUALID scale is a reliable and valid instrument for the assessment of Quality of life in nursing home patients with dementia.
PS02.85
Occurrence of depression and its correlates in early onset dementia patients
Tor Rosness; M Barca; K Engedal
Norwegian Centre for Dementia Research, Oslo, Norway
Objective: We wanted to investigate the occurrence of depressive symptoms in early onset dementia (EOD) patients as evaluated by a memory clinic, and determine which characteristics were associated with depressive symptoms.
Method: We included 221 patients who were diagnosed with dementia before the age of 65, from a memory clinic in Oslo, Norway. Depression in these patients was measured by the Montgomery Åsberg Depression Scale (MADRS). The patients cognition was measured by the Mini Mental Status Examination (MMSE) and the Kendrick Object Learning Test (KOLT), activities in daily life (ADL) through the Rapid Disability Rating Scale (RDRS-2) and behavioural and personality changes as assessed by Measuring Behavioural Disturbance of Elderly Demented Patients (BMD). History of depression, current psychiatric co-morbidity and usage of antidepressants were recorded. Specific somatic conditions including hypothyroidism, diabetes and stroke, all well known to be associated with dementia and depression were included in the analysis.
Results: Mean age of patients was 58.2 years (5.2 SD); 50.6% were women. Of them 123 patients (55.6%) had a mild degree of depression (MADRS total score 7–19), 21 patients (9.5%) had a moderate degree of depression (MADRS total score 20–34) and only 1 patient had severe degree of depression (MADRS total score ≥ 35), according to Snaith's definition. A factor analysis was performed using oblique rotation with Kaiser normalization, which loaded two factors. The first factor described dysphoria: lack of concentration, pessimistic thoughts, inner tension, suicidal thoughts lassitude and lack of sleep. The factor (two) denoting sadness was comprised of; observed sadness, reported sadness, lack of appetite and inability to feel. In an unadjusted linear regression analysis; history of depression, usage of antidepressants and behavioural disturbances as measured by BMD were significantly associated with MADRS total score, and both factor 1 and 2. Current psychiatric co-morbidity was significant only in MADRS total score and the dysphoria factor. MMSE was only significantly associated to dysphoria. However, the results changed in a multiple (adjusted) linear regression analysis: only a history of depression was significant with a high beta (0.44) in all three independent variables (MADRS total score, dysphoria and sadness).
Conclusion: We found a high occurrence of depressive symptoms in EOD patients, 65.7% of all our patients had some degree of depression. A history of depression was the most important predictor of depression in these patients.
PS02.86
The Othello syndrome (delusional jealousy) observed in Japanese elderlies with variable etiology
Fukatsu Ryo1; M Fujii2; N Nakano3
1Saitama Medical University, Kawagoe, Japan; 2Sapporo Hills Memorial Hospital, Sapporo, Japan; 3Hokkaido Medical University, Sapporo, Japan
The Othello syndrome, or delusional jealousy, is an unique delusion characterized by false conviction of the spouse's infidelity. It has been recognized to occur often associated with elderly persons with variable etiology.
Persons with this syndrome are sometimes very dangerous because of violent behavior. We have a chance to examine twelve elderly persons with this syndrome. They have delusional disorder, dementias, mood disorder (manic period), delirium, and Charles Bonnet syndrome. We will present clinical characteristics of individual case.
PS02.87
Persistence of and changes in neuropsychiatric symptoms in mild cognitive impairment over six months in community-dwelling Korean elderly
Seung-Ho Ryu1; I Jung2; D Lee3; S Kim4; K Oh5
1School of Medicine, Konkuk University, Konkuk Univ. Hospital, Seoul, South Korea; 2College of Medicine, Korea University, Guro Hospital, Seoul, South Korea; 3College of Medicine, Inje University, Sanggyepaik Hospital, Seoul, South Korea; 4College of Medicine, Dong-A University, Dong-A Univ. Hospital, Seoul, South Korea; 5College of Medicine, Sungkyunkwan University, Kangbuk Samsung Hospital, Seoul, South Korea
Objectives: Mild cognitive impairment (MCI) may be a transitional state between normal aging and Alzheimer's disease (AD). Several studies for comprehensive neuropsychiatric symptoms in patients with MCI have revealed that the elderly with MCI suffer from various neuropsychiatric symptoms as in patients with dementia. It is important in terms of management to know their natural history and course. We aimed to determine the persistence and change in severity of neuropsychiatric symptoms over 6 months in participants with MCI.
Method: We screened 4,323 community-dwelling elderly with MMSE-KC (Korean version of MMSE in CERAD-K). 538 elders with score below –1.5 SD in MMSE-KC according to the normative data adjusted by age, sex and education were assessed by comprehensive neuropsychological test and clinical interview in the use of CERAD-K packet. Neuropsychiatric Inventory (NPI) was used to rate the severity of neuropsychiatric symptoms on 142 participants with MCI at baseline and on 131 at 6-month follow-up. We also collected information about cognition and quality of life of patients and their caregiver.
Results: 55% of MCI participants exhibited at least on or more neuropsychiatric symptoms in the previous month and 31% had clinically significant neuropsychiatric symptoms (each NPI score ≥ 4 at any NPI domain). Anxiety (42%), sleep disturbance (38%), depression (25%), apathy (20%), and irritability (15%) were most common. 110 (84.0%) of whom had persistent significant symptoms at 6-month follow-up. There was no significant difference in mean NPI score for any symptom over six months but many individuals became better or worse. 51.2% of those with at least one significant baseline symptom in any domain improved. Those with persistent symptoms had more severe baseline symptoms. Those with at least one clinically significant symptom had poorer quality of life in both patients and caregivers (p < 0.05).
Conclusions: Neuropsychiatric symptoms were highly persistent overall in the elderly with MCI but many individuals became better or worse. Persistence was predicted by having more severe symptoms at baseline. Clinically significant levels of neuropsychiatric symptoms were associated with quality of life. We conclude that it is important to assess and manage neuropsychiatric symptoms in patients with MCI.
PS02.88
The impact of an interprofessional behaviour management team
Alexandra Segal; C Séguin; A Kelly
Bruyère Continuing Care, Ottawa, ON, Canada
Currently, at St. Vincent Hospital, a 350 bed Complex Continuing Care (CCC) facility in Ottawa, Ontario, 10–15% of the patient population demonstrates behavior management issues. People are living longer with chronic disease, head injury, etc. Complex illnesses such as multiple sclerosis, stroke, past history of head injury are often accompanied by cognitive changes that manifest themselves in overt behaviour. The St. Vincent Hospital environment is focused on the treatment of medical issues (wound care, dialysis, ventilator dependent patients, Parkinson's disease, etc.) and therefore lacks the appropriate attention to the behavioural components of aforementioned disease processes.
In the past, behavioral issues in CCC were addressed via the use of physical and/or chemical restraints in concert with 24 hour sitters. With the advent of the interprofessional Behaviour Management Team (BMT)* in May 2007, interventions are currently based on patient centered care and a nonpharmacological approach. As a result, sitter usage, restraint use and pharmacological reliance have been reduced. Patients demonstrate an improvement in quality of life as indicated by a lower level of adverse symptoms.
Case studies illustrate implementation of a behavioural management plan and demonstrate positive outcomes (i.e., reduction of non-nursing care requests, decreased levels of adverse symptoms, increased appropriate social interactions, reduced physical/chemical restraints, elimination of sitter use, cost savings, increased workplace safety, higher levels of staff satisfaction, decreased staff absenteeism, increased team cohesion, eligibility for patient discharge to appropriate level of care). These positive outcomes highlight the opportunity to expand our specialized team in CCC for patients with behavior management issues wherein a specially trained, interprofessional team would efficiently utilize available financial and human resources.
*BMT consists of an Advanced Practice Nurse, Behavioral Technician and Neuropsychologist all with expertise in the area of behavior management
PS02.89
An evidence-based innovative program for caregiver burden
J Sadavoy; Andria Aiello
Mount Sinai Hospital, Toronto, ON, Canada
An evidence-based innovative program for caregiver burden has been newly developed to deliver unique, targeted and tailored skill-building interventions that provide caregivers with the tools and support to manage the care of those with dementia at home.
Informal caregivers provide most of the care for those with dementia. Compared to non-caregivers, caregivers are at twice the risk for depression and physical illness. The causes of caregiver burden are complex and are strongly associated with the ability to manage behavioral disturbances in the care recipient. Up to 90% of dementia sufferers have significant behavioral disturbances (BPSD). The data support the effectiveness of various interventions that enhance caregiver knowledge and coping skills which in turn improve overall psychological health, decrease burden, and improve quality of life for both caregiver and care recipient. The evidence suggests that enhancing practical skills and self-efficacy, as well as treating depression and providing ongoing supportive care are key elements.
The evidence-based goals of this innovative program for caregiver burden include practical skill-building; improved coping/problem solving; improved emotional regulation; enhanced sense of mastery/self-efficacy; reduced depression/anxiety; improved social (marital) interaction/support; optimized functional health of the caregiver; and adequate professional support. This 12 week active intervention includes three phases. Phase one involves an in-depth assessment out of which “scenarios” are created and scripted for use in the skills training phase. The focus of phase two is group building and group education using well-established Problem Solving Therapy and Cognitive Behavioral Therapy methods. Phase three involves hands-on skills training using scenario-based simulated situations with professional actors and intensive expert coaching. Post-intervention maintenance/reinforcement sessions are offered along with individual interventions as needed. A number of outcome measures pertaining to the evidence-based goals of the program are used to assess the efficacy of the intervention.
PS02.90
Dementia caregiver support services: What works? Caregiver narratives of their experiences with their family members’ community geriatric mental health consulting service
Sophie Sapergia
University of Calgary, Calgary, AB, Canada
Background: Over the past two decades, systematic reviews and meta-analyses have consistently found that the majority of interventions targeted directly to caregivers have little or no statistically significant impact on measures of caregiver emotional or physical health outcomes, although more recent studies appear to suggest that multi-component interventions that target both the caregiver and her or his family member may be most effective. As a result, there have been calls for rigorous qualitative examinations of caregiver experiences, allowing caregivers themselves to describe in their own words the aspects of interventions they found more or less helpful.
Research question and methods: Therefore, a narrative approach was adopted to examine the following question: What are the experiences of dementia caregivers with their family members’ community geriatric mental health service, within the context of their larger caregiving experience? Semistructured interviews were conducted with a purposively-selected sample of six caregivers.
Results: All but one of the caregivers described their relationship with their family members’ geriatric mental health therapist as central to their ability to continue to care for their family member. Therefore, most of the caregivers described themselves as relying strongly on the therapists as holistic care coordinators, system navigators, to communicate with other family members, and as a source of direct personal support in the management of the caregiving role. Most of the caregivers described their family members’ therapist as a consistent, reliable source of support over the course of their experience.
Discussion: Overall, the views of most of the caregivers in this study appeared to support the findings of more recent reviews of outcomes-focused caregiver support literature suggesting that multi-component interventions supporting both the caregiver and their family member are effective in addressing emotional and physical caregiver outcomes. Therefore, service planners may wish to emphasize these characteristics when planning caregiver support services. Such services should be subjected to further evaluation in order to provide more conclusive support.
PS02.91
The influence of pain on physical performance of patients with cancer
Daisuke Sato
Kanagawa University of Human Services, Heiseicho, Yokosuka, Kanagawa, Japan
Physical dysfunction is a frequent consequence of cancer and its treatments. Improvement of physical function therefore should be a primary goal of treatment; the use of appropriate assessment and outcome measures is fundamental. The purposes of this study were to investigate the psychometric properties of a Japanese language version of Physical Performance Test (PPT) Battery and characterize physical function in patients with cancer referred for rehabilitation.
A total of 105 patients with cancer participated in this study. All patients had a diagnosis of cancer. The subjects completed the Japanese language version of the PPT Battery: the time taken to complete various tasks, the distance walked in 6 minutes, and the distance reached forward while standing were measured. Two self-report questionnaires, one on sensory evaluation of pain and the other on affective evaluation of pain; the Functional Independence Measure (FIM), which evaluates activities of daily living; and Brief Fatigue Inventory (BFI) and European Organization for Research and Treatment of Cancer Quality of Life Questionnaire were simultaneously administered to the subjects. This study was approved by the ethical committee of our institution, and informed consent was obtained from all participants.
The results for reliability showed that the ICC values for inter-rater reliability and intra-rater reliability were 0.89 or more for every item. The results for validity showed significant associations between the scores for all of the items in the Japanese language version of the PPT Battery and total scores for the FIM and BFI.
Significant associations were found between scores for the Japanese language version of the PPT Battery and pain. Pain has a substantial impact of physical performance of patients with cancer. Fatigue also impacts physical performance. Compromised ability to perform certain physical tasks affects quality of life. Further investigation of the roles of these relevant variables is needed.
PS02.92
A randomized, controlled trial of the effectiveness of cognitive-behavioral therapy and sertraline versus a waitlist control group for anxiety disorders in older adults
Josien Schuurmans1; H Comijs2; I Weijnen3; M van den Hout4; P Emmelkamp5; R van Dyck2
1Vrije Universiteit, Amsterdam, Netherlands; 2GGZinGeest, Amsterdam, Netherlands; 3Riagg Maastricht, Maastricht, Netherlands; 4Universiteit Utrecht, Utrecht, Netherlands; 5UvA, Amsterdam, Netherlands
Objective: Anxiety disorders are highly prevalent in older adults and are associated with increased disability, a great negative impact on quality of life and an inadequate use of health care services. Nevertheless, treatment studies in this area are scarce. This study is the first to investigate the relative effectiveness of CBT compared to a SSRI (sertraline) in a RCT on the treatment of anxiety disorders in older adults.
Method: 84 patients of 60 years and over with a principal diagnosis of GAD, panic disorder, agoraphobia or social phobia were randomly assigned to one of three conditions: 15 sessions of CBT, pharmacological treatment with an SSRI (sertraline; maximum dosage 150 mg) and a wait list control group. Participants completed measures of primary outcome (anxiety) and coexistent worry and depressive symptoms at baseline, post-treatment and at 3-month follow up. Random coefficient regression analyses were performed to compare treatment outcome between the three conditions.
Results: Attrition rates were high in both treatment groups. Consequently, findings are based on a relatively small sample of completers (n = 52). Although both CBT and sertraline led to significant improvement in anxiety, worry and depressive symptoms both at post-treatment and at 3-month follow-up, sertraline showed superior results on worry symptoms. Effect size estimates for CBT were in the small to medium range, both at post-treatment (mean d = .42) and at 3-month follow-up (mean d = .35), whereas effect sizes for sertraline fell into the large range (post-treatment mean d = .94 and 3-month follow-up mean d = 1.02). The wait-list condition showed virtually no effects (post-treatment mean d = .03).
Conclusions: Our findings strongly suggest that the pharmacological treatment of late-life anxiety with SSRIs has not been given the proper attention in research to date. More research is needed to firmly establish if and what modifications are needed for the appropriate use of CBT with an older population.
This study has been published as: Schuurmans, J., Comijs, H. C., Emmelkamp, P. M., Gundy, C. M., Weijnen, I. J. C., van Hout, M. A. et al. (2006). A randomized controlled trial of the effectiveness of cognitive-behavioral therapy and sertraline versus a wait-list control group for anxiety disorders in older adults. American Journal of Geriatric Psychiatry, 14, 255–263.
PS02.93
Predictors of quality of life (QOL) among nursing home patients with dementia
Geir Selbæk1; I Røen1; K Engedal2
1Innlandet Hospital Trust, Ottestad, Norway; 2Ullevål University Hospital, Oslo, Norway
There is growing consensus on the need to apply measures of health-related quality of life (QOL) in dementia research. In Norway 40–45 percent of all persons with dementia live in nursing homes. However, there are to our knowledge no studies using disease specific measures of QOL in nursing home patients with dementia. In this presentation we investigate predictors of quality of life in a sample of 169 patients with dementia, applying the Norwegian version of the Quality of Life in Late-Stage Dementia (QUALID) scale, a domain-specific, short, proxy informant based instrument developed by Weiner et al. To identify the predictors we have performed a multivariate linear regression analysis.
PS02.94
How do young psychiatrists have interests in geriatric psychiatry? An analysis based on a multi-center questionnaire survey
Keisuke Shibata1; N Uchida2; K Uehara3; H Oda4; R Kawada5; S Kikuchi6; S Kobayashi7; M Setsuie8; T Shirasaka7; M Suzuki9; M Tateno7; W Nakano10; R Nishimura2; K Fukui1
1Kyoto Prefectural University Of Medicine, Kyoto, Japan; 2Fukuoka University, Fukuoka, Japan; 3Yokohama City University School of Medicine, Yokohama, Japan; 4Hyogo Brain and Heart Center at Himeji, Himeji, Japan; 5Kyoto University, Kyoto, Japan; 6Tohoku University Graduate School of Medicine, Sendai, Japan; 7Sapporo Medical University, Sapporo, Japan; 8National Hospital Organization Obihiro Hospital, Obihiro, Japan; 9Iki Citizens Hospital, Iki, Japan; 10University of Occupational and Environmental Health, School of Medicine, Kitakyushu, Japan
Background: According to the White Paper on Aging Society, Japan became the world's most aged country, overtaking Italy in terms of the percentage of older population in 2005, and is expected to enter an era of an “unprecedented” aging society in the future. Due to the rapid growth of older population, mental disorders of the older persons, especially senile dementia and depression, have been attracting more attention. The number of patients with dementia has been increasing and is expected to exceed 3.5 million in 2035. Reflected by these social backgrounds, from this June in Japan, the older persons aged over 75 years old would be placed under the obligation to have cognitive examinations when they renew their driver's license. Besides, dementia often becomes many problems clinically especially because of the behavior and psychological symptoms of dementia annoying patients and their caregivers. On the other hand, studies for the depression of older persons reported that the percentage of older persons with depressive state was about 15% and the mean prevalence of senile depression was about 6%. Moreover, senile depression requires much attention to treat, since older patients with depression often show atypical symptoms compared with younger patients. Although geriatric psychiatry attracts a great deal of social attention in this way and is expected to gain more importance in the future, the number of young psychiatrists who have interests in geriatric psychiatry is very few, as following some multi-center questionnaire studies reported. Miyajima et al. compared the special regions in which senior residents who selected clinical training of psychiatry had interests and showed the least percentage (<5%) of geriatric psychiatry. Similarly, Nakano et al. reported that few young psychiatrists, especially after new clinical training program, had interests in geriatric psychiatry.
Objectives: The purpose of this study is to investigate the interests of young psychiatrists in geriatric psychiatry based on multi-center questionnaire survey.
Methods: Information was obtained by the means of questionnaire for nationwide multi-center psychiatrists, using the network of Japan Young Psychiatrists Organization (JYPO, Nonprofit Organization Corporation). Statistical analyses were performed using Kruskal-Wallis test, Mann-Whitney's U-test and Bonferroni Post Hoc test.
Results: The 137 participants (104 male and 33 female) completed the questionnaire. The mean age was 33.6 ± 5.8 years and the mean period of engaging in psychiatry was 6.2 ± 5.8 years. The number of geriatric psychiatry selected for subspecialty was second least after addiction. Regarding the reason for subspecialty selection, “Worthwhile” “Hope for recovery” were significantly lower percentage and “Fewness of lawsuits” was significantly higher in the geriatric psychiatry groups than in others.
Conclusions: Consistent with previous studies, the number of psychiatrists who selected geriatric psychiatry for their own subspecialty was fewer than all other psychiatric regions except for addiction. Compared with other subspecialties, geriatric psychiatry was selected not because respondents felt it was worthwhile or offered patients hope of recovery, but because of rarity of lawsuits. Further analyses and discussions will be reported in the presentation.
PS02.95
The effect of pleasant familiar music listening on feeding difficulties, agitated behaviors, and nutrition of a community-dwelling older adult with dementia: A case study
Hui-chen Shih1; H Sung1; H Lee2
1Tzu Chi university, Hualien, Taiwan; 2Tzu Chi General hospital, Hualien, Taiwan
Feeding difficulties are commonly observed behavioral problems in older adults with dementia. Feeding difficulties, such as trouble in transferring food from plate to mouth, difficulties with swallowing or chewing, eating inappropriate amounts of food or substances, and forgetting how to use utensils, can put older adults with dementia in high risk of malnutrition and unnecessary tube feeding. With the negative consequences resulting from feeding difficulties, interventions that can promote oral intake and alleviate feeding problems of older people with dementia become vital. Music has been reported as the most common intervention for managing feeding difficulties in those with dementia in long-term care settings; however, previous studies did not consider the types and characteristics of the music. It was suggested that music, which is 60–80 beats per minute with no lyrics and familiar to the listeners, will have positive effects on behavioral and psychological outcomes. This case study aimed to evaluate the effect of pleasant familiar music listening intervention on feeding difficulties, nutrition, and body weight of an 87-year old woman diagnosed with dementia living at home. Pleasant familiar music listening intervention was delivered to the subject for 1 hour during dinner time daily for two weeks. The subject's music preferences were assessed by a Music Preference Questionnaire. The music used in the intervention was Taiwanese popular songs from the 1950–1970s that were familiar to the subject, 60–80 beats per minute with no lyrics, and performed by string instruments. Feeding difficulties were assessed by Edinburgh Feeding Evaluation in Dementia (EdFED) scale, nutritional status was assessed by Mini Nutrition Assessment (MNA), agitated behaviors were assessed by Cohen-Mansfield Agitation Inventory (CMAI), and body weight by Weight scale at pre-test and post-test. The EdFED score was decreased from 4 at pre-test to 3 at post-test, indicating that the subject's feeding difficulties were alleviated slightly after receiving two weeks of pleasant familiar music listening intervention. CMAI score was decreased from 57 at pre-test to 39 at post-test, indicating the occurrences of agitated behaviors were reduced after the music intervention. MNA score was increased from 16.5 at pre-test to 21 at post-test, indicating the subject's nutritional status was improved. In addition, the subject's body weight was increased from 46 kg to 46.2 kg after receiving the music intervention. The pleasant familiar music listening intervention has the potential to manage the feeding difficulties and agitated behaviors, and it may also improve the nutritional status and body weight of older adults with dementia. Therefore, pleasant familiar music listening can be incorporated in dementia care and may improve the quality of life of those with dementia residing in the community.
PS02.96
Atrophy of the corpus callosum in mild cognitive impairment and Alzheimer's disease
Il-Seon Shin1; S Kim2; J Kim1; S Yang1; S Kim1; J Yoon1
1Chonnam National University Medical School, Gwangju, South Korea; 2College of Medicine, Dong-A University, Busan, South Korea
Background and aims: Relatively few studies have explored atrophy of the corpus callosum (CC) in mild cognitive impairment (MCI) and Alzheimer's disease (AD). This study aimed to compare the atrophy of MCI with that of AD.
Methods: Forty-one subjects with MCI and 34 with AD were investigated using magnetic resonance imaging. In the midsagittal slice the CC was traced manually.
Results: Total callosal area was significantly reduced in patients with AD when compared with subjects with MCI. Comparison of the subdivisions of the CC showed significantly smaller CC1, CC2 and CC5 in patients with AD relative to subjects with MCI.
Conclusion: We found significant regional atrophy of the CC predominantly in the callosal rostrum and splenium in AD when compared with MCI.
Key Words: corpus callosum, mild cognitive impairment, Alzheimer's disease, magnetic resonance imaging
PS02.97
Anxiety and its correlates among older adults accessing aging services
T Richardson; Adam Simning; H He; Y Conwell
University of Rochester School of Medicine and Dentistry, Rochester, NY, United States
Objective: To assess the characteristics of anxiety in aging services network (ASN) clients.
Setting: A community social services agency that functions as the single point of entry for aging services in Monroe County, NY. Design: Cross-sectional interviews conducted by research personnel in older adult care management clients' homes.
Participants: Clients aged 60 years and older who received an in-home care manager assessment.
Measurements: Subjects were screened for anxiety symptoms with the Goldberg Anxiety Scale, and the Structured Clinical Interview for the DSM-IV (SCID) was conducted to assess for major depressive episode (MDE). Instruments covering the domains of physical health and disability, social support, negative life events, and other areas relevant to aging services were administered.
Results: Of the 378 subjects, 27% met criteria for clinically significant levels of anxiety, and MDE was present in 54% of the anxious clients. Multivariate analyses demonstrated that anxiety is associated with younger age, depression, number of medical conditions, and recent life events.
Conclusions: ASN clients who received in-home care management services were highly anxious. The majority of these anxious clients also suffered from co-occurring symptoms of major depression. Because aging services providers work with their clients to ameliorate some of the anxiety correlates, the ASNs represent a promising venue for detecting, managing, and preventing anxiety among the older adults that they serve.
PS02.98
Care needs of Indian urban elderlies and strain in their caregivers
Garima Srivastava; R Tripathi; A Kumar; S Tiwari
CSM Medical University, Lucknow, India
Background: The population of elderlies is increasing rapidly. The majority of older persons need assistance for day to day living and the dependency increases in case of having any physical or/and mental health problems. The caregivers of elderlies have received attention of researchers in recent years. The present study is an attempt to explore the care needs of urban elderlies and strain their caregivers face in caring. Identification of these variables will help to plan better intervention strategies for both the elderlies and their caregivers.
Objective: To study the care needs of urban elderlies and strains experienced by their caregivers.
Materials and Methods: The study sample consisted of 1163 caregivers aged 18 years and above recruited from a ward of urban Lucknow from households of 1216 elderlies (55 years and above). The caregivers were assessed on Problem Checklist and Strain Scale (PCLS) for care needs of elderlies and strain experienced by them. Included elderlies were subjected to initial screening through Mini-Mental Status Examination and Survey Psychiatric Assessment Schedule to identify ‘suspects’ for cognitive and neuro-psychiatric disorders. The ‘suspects’ were then subjected to detailed assessment through Cambridge Mental Disorder of the Elderly Examination Revised (CAMDEX-R) for cognitive disorders and Schedule for Clinical Assessment in Neuropsychiatry (SCAN) for neuro-psychiatric disorders other than cognitive disorders. ICD-10 criteria were followed in assigning the diagnostic labels. The recruited elderlies were also subjected to comprehensive physical, neurological examination (using PNE) and pathological/radiological investigations. Following this, the elderlies were categorized as per their mental and physical health status in different categories.
Results: Elderlies were categorized into five groups: normal, pure neuropsychiatric disorder, pure cognitive disorder, pure physical illness and having more than one co-morbid illness based on their health status. Those having pure neuropsychiatric illness without cognitive impairment were found to have more care needs in areas of self care & functioning (61.0%), followed by emotional (48.9%) and behavioral problems (48.8%). Those having cognitive disorder alone were found to have more care needs in the area of cognitive problems (64.3%). However in presence of another co-morbidity the care needs increased in the areas of self care & functioning (72.0%) behavioral (70%) and emotional problems (54.8%).
Caregivers of those elderlies suffering from more than one co morbid disorder (such as neuropsychiatric + cognitive disorder; neuropsychiatric + physical illness; cognitive + physical illness and neuropsychiatric + cognitive disorder + physical illness) experienced maximum strain in most of the areas, i.e. demand of attention (43.3%) followed by financial burden, depression (27.3%) & fear of danger (24.8%). The caregivers of cognitive disorder alone felt maximum strain and reported worry (57.1%) followed by depression (35.7%), equal strain in the area of coping and demand of attention (28.6%). The caregivers of pure neuro-psychiatric group felt maximum strain in enjoying the role of caring for elderlies (26.8%), followed by worry (21.9%), demand of attention (17.1%) and equal strain because of financial burden and fear of danger (14.6%). In case of caregivers of elderlies having pure physical illness, maximum strain was reported while carrying out the task of caring for elderlies (34.7%) followed by financial burden (24.9%) worry (22.7%) & demand of attention (19.4%). The caregivers of normal elderlies experienced maximum strain in enjoying the role of caring for elderly (35.3%) followed by demand of attention (18.7%), worry (16.7%) and financial burden (13.4%). Care givers of all the elderlies experienced problems and strain in caring for them but the nature of care needs and strains are different according to the nature of health problems.
Key words: care needs, strain, caregivers, elderlies, neuropsychiatric morbidity, cognitive disorder.
PS02.99
Lay help for the caregivers of demented outpatients: Impact on health status of patients, caregivers and lay helpers
Gabriela Stoppe
University Psychiatric Hospitals, Basel, Switzerland
International studies showed that caregiver interventions are efficacious especially when they provide the possibility to be free from caregiver role for some hours. Up to now there is no research available concerning the impact on the psychological and physical health of the involved persons.
In a program developed by the memory clinic of University of Goettingen, Germany, and a diaconic social service provider, 64 lay helpers were trained for their role in a 40-hours-course. After informed consent, at three times (T0, T1 (after 6 months), T2 (after 1 year), lay helpers, caregivers and the demented patients were interviewed and standard scales were used (SCL-90, BDI, MMSE, GDS, BEHAVE-AD, NOSGER, IADL, RuD, Adult Attachment Scale etc.).
31 demented patients were included, however from only 16 results at T2 could be obtained. Most patients were moderately to severely impaired. However, during the study, their mood, mobility and circadian stability improved. The situation of the caregivers remained stable, the lay helpers showed no “negative” trends except for the result that their attitude to ageing significantly deteriorated.
The data should be interpreted with caution because of the low number of persons included and the lack of a control group. In addition lay help is typically variable and other external factors might influence the results. However, because of the broad range of parameters investigated, interesting results are nevertheless worth discussion.
PS02.100
Depression and the competence for selection, optimisation and compensation (SOC)
Gabriela Stoppe
University Psychiatric Hospitals, Basel, Switzerland
Background: The meta theory of selection, optimisation and compensation is a concept of successful coping and especially “successful” aging (1,2). Since depression is the most prevalent psychiatric disorder in old age, we wanted to know whether depression is associated with impairment of SOC-competence on a state or trait basis.
Method: In a pilot study n = 50 inpatients took part after informed consent. They were between 21 and 73 years old and suffered from a depressive syndrome (F32, F43.2, F33, F43.1, F31, F41.2). Patients with organic and/or psychotic underlying condition were excluded. We applied a standardised scale, developed by Freund & Baltes (3). Together with standard instruments (MADRS, GDS) at the beginning and the end of inpatient treatment. For this study, data from a representative German study (ALLEE) served as control.
Results: As to be expected, SOC-competence was significantly lower compared to normal values in the depressed state. After remission however, there were no differences left. There were also no significant differences found when comparing a group of younger (<50y) and a group of older (>50y) patients.
Conclusion: We draw the preliminary conclusion that impairments in SOC competence seem to be no trait marker for depression at any age. Further study should test whether there are differences in various subtypes of depression (e.g. early versus late onset, double depression).
PS02.101
Filial maturity as predictor of caregiver burden in adult children of demented patients
Gabriela Stoppe
University Psychiatric Hospitals, Basel, Switzerland
Introduction: Filial maturity has been discussed as important part of a successful development. In this study we investigated, whether it is related to the subjective burden of care for demented parents.
Method: N = 61 adult children, who took care for a demented mother and/or father were recruited fort his study. We used the following scales and tests: The Louvain Filial Maturity Scale, the Freiburger Persönlichkeitsinventar for the personality profile, the Symptom Check List (SCL-90) for general psychopathology, the Nurses Observation Geriatric Scale (NOSGER) for the caregiver-rated symptom profile of the demented parent, the Zarit Burden Interview for caregiver burden. The demented parent was investigated by experts using a standardised interview for the diagnosis of dementia (SIDAM) and the Mini Mental Status Test for dementia severity.
Results and conclusion: Overall filial maturity was not related to the subjective caregiver burden as measured in this study. However, higher “parental consideration” was related to lower burden. And higher “filial obligation” was related to later nursing home admission. The construct deserves further scientific interest in this context.
PS02.102
Influence of apolipoprotein E genotype on cognitive function in patients with mild Alzheimer's dementia
Gabriela Stoppe1; A Saake2
1University Psychiatric Hospitals, Basel, Switzerland; 2Psychiatric Hospital Kilchberg, Kilchberg, Switzerland
Background: Apolipoprotein E allele ɛ4 is a well established risk factor for Alzheimer's dementia (AD). Its presence modifies also the influence of other risk factors as well as the conversion rate of mild cognitive impairment (MCI) to overt dementia. However, in how far it also influences the clinical presentation of AD, is not known yet.
Method: Patients of the memory clinic Göttingen were approached if they fulfilled the inclusion criteria: very mild or mild AD according to NINCDS-ADRDA criteria, MMSE 20–30, and at least two of three typical instrumental findings (hippocampal atrophy in MRI, bilateral temporo-parietal hypoperfusion in Neurolite-SPET, low Aβ1–42 and increased tau in CSF). They underwent an extensive neuropsychological investigation. A follow-up took place within one year. The study was approved by the local ethical committee.
Results: N = 74 patients (38M, 36F; mean age 68.1y; MMSE 25.9 ± 2.8) and N = 28 age- and sex- and education-matched controls could be recruited. N = 36 patients had one (N = 20) or two (N = 16) APOE-ɛ4-alleles. 53 of 57 CSF analyses revealed AD-typical findings, 64 of 74 cranial MRT revealed bilateral hippocampal or global atrophy and 42 of 64 Neurolite-SPETs showed typical findings. Results of non-memory tests—language, visuospatial ability, attention—did not reveal any difference with regard to APOE genotype. Two memory tests and a memory composite score were significantly worse in the APOE-ɛ4-positive group and was even worse in the homozygote group.
Conclusion: APOE-ɛ4 influences in a dose dependent manner the neuropsychological functioning in mild AD. This points to a special vulnerability of mesotemporal structures.
PS02.103
Do cholinesterase inhibitors for Alzheimer's disease provide more than symptomatic benefits?
Guk-Hee Suh
Hallym University College of Medicine Hangang Sacred Heart Hospital, Seoul, South Korea
Background: If the benefits of cholinesterase inhibitors (ChEIs) for Alzheimer's disease (AD) are supposed to translate to mortality reduction, all treatments for severe dementia are predicted to increase costs because the additional survival incurs further costs. This study aims to examine survival of AD patients receiving ChEIs and to compare their survival with those of AD patients who never received ChEIs and cognitively intact old psychiatric outpatients.
Methods: The retrospective cohort study used national mortality data provided by the Korean National Statistics Office and electronic database of 15 general hospitals on older patients who began outpatient treatment with psychiatric medications including ChEIs (N = 3,813). Six-year mortality rate of AD patients receiving ChEIs was compared with those of AD patients who never received ChEIs and cognitively intact old psychiatric outpatients. The authors controlled for confounding by using multivariate models and propensity-scoring methods.
Results: Observed additional survival of AD patients receiving ChEIs (mortality rate: 13.1%) when compared to AD patients who never received ChEIs (15.4%) was not statistically significant (hazard ratio: 1.03, 95% CI = 0.67–1.59). AD patients receiving ChEIs showed higher mortality rate (13.1%) compared to that of cognitively intact old psychiatric outpatients (8.6%) (hazard ratio: 1.60, 95% CI = 0.96–2.68).
Conclusions: This study does not support that ChEIs provide more than symptomatic benefits to AD patients. All ChEIs should be considered for symptomatic use only, and not to be capable of modifying either the course of AD or its longer-term clinical expression.
PS02.104
Nursing staff's attitudes, expectations, and use of music intervention for nursing home residents with dementia in Taiwan
Huei-chuan Sung1; W Lee2; G Smith3
1Tzu Chi College of Technology & Tzu Chi University, Hualien, Taiwan; 2Tzu Chi College of Technology, Hualien, Taiwan; 3University of Edinburgh, Edinburgh, United Kingdom
Music intervention has been suggested as an accessible and inexpensive non-pharmacological care approach for older adults with dementia in long-term care settings. With very limited numbers of music therapists working in long-term care settings in Taiwan, nursing staff, who provide the majority of direct care for nursing home residents, will be the most appropriate care providers to learn to arrange and implement music intervention for those with dementia. However, no studies have explored nursing home staff's attitudes, expectations, and use of music intervention for older adults with dementia in long-term care settings. The nursing staff's attitudes and expectations about music intervention may influence their desire to use and implement music intervention, and it can further contribute to its impact on the residents with dementia. This study aimed to explore nursing staff's attitudes, expectations, and use of music intervention for nursing home residents with dementia in Taiwan. A cross-sectional design was used. Self-administered questionnaires were distributed to a convenience sample of 285 nursing staff taking care of residents with dementia in long-term care facilities, and 214 nursing staff completed the questionnaires, giving a response rate of 75.1%. The majority of the nursing staff held positive attitudes toward music intervention for those with dementia, but only 30.8% had used music intervention for those with dementia in practice. The most frequent factors reported by the staff for not using music intervention for those with dementia were lack of knowledge and skills of music intervention (72.9%), lack of training of music intervention (67.3%), lack of time to provide music intervention for the residents (56.1%), lack of relevant resources in the facilities (55.1%), and lack of confidence to practice music intervention (42.5%). This study results indicate that there is a lack of formal training of music intervention in the nursing education as well as in the clinical nursing in-service programs. This result indicate that nursing staff need more formal training about music intervention and need resources and support for implementing music interventions for those with dementia in work settings. The understanding of nursing staff's attitudes, expectations, and use of music intervention can provide baseline data for nursing educators and nursing home administrators to further develop educational programs to train nursing staff about the implementation of music interventions for older adults with dementia in long-term care settings.
PS02.105
Attenuated proteolysis of FTDP-17 mutant tau in cultured cells and involvement of increased phosphorylation of tau
Toshihisa Tanaka; K Yanagi; K Kato; G Sadik; M Takeda
Osaka University Graduate School of Medicine, Osaka, Japan
In tauopathies, including FTDP-17 (frontotemporal dementia with parkinsonism linked to chromosome 17), tau protein is hyperphosphorylated, ubiquitinated and accumulated in brains, however mechanisms of the accumulation is still unclear. To understand the mechanisms of the accumulation, the protein metabolism of tau containing FTDP-17 mutations was investigated employing pulse-chase experiments. In comparison to COS-7 cells transfected with wild tau gene, attenuated proteolysis of tau was observed in the cells transfected with V337M and R406W mutant tau genes after 48 hours. To further understand the involvement of proteases in metabolisms of tau protein, some of protease inhibitors; lactacystin and MG-132; inhibitors to proteasome, CA-074Me; an inhibitor to cathepsin, and puromycin; an inhibitor to puromycin-sensitive aminopeptidase (PSA), were employed in SH-SY5Y human neuroblastoma cells. Pulse-chase experiments showed that proteolysis of tau protein in SH-SY5Y cells was attenuated when the cells were treated with 200 nM of puromycin. Increased tau protein levels were also observed in SH-SY5Y cells treated with siRNA to PSA for inhibition of expression of PSA. Those data suggest that PSA is a protease that catalyzes tau protein predominantly in SH-SY5Y cells. On the relevant of the V337M and R406W mutant tau with PSA, immunocytochemical analysis and subcellular fractionation experiments revealed that the mutations did not alter the intracellular distribution of tau, suggesting that impairment of the accessibility of tau to PSA is unlikely as a reason of attenuated proteolysis of tau protein. And western blots with phosphorylation-dependent antibodies revealed that phosphorylation of tau at Thr231, Ser396 and Ser409 was increased in the cells transfected with V337M, R406W, and R406W mutant tau gene, respectively. These results suggest that attenuated proteolysis of FTDP-17 mutant tau might be explained by the increased phosphorylation levels resulting in resistance to proteolysis.
PS02.106
Do vascular risk factors impact poststroke depressive symptoms?
Gayla Tennen1; N Herrmann1; A Li2; P Francis2; A Wong2; K Lanctot2; S Black3
1Sunnybrook Health Sciences Centre, Toronto, ON, Canada; 2Sunnybrook Health Sciences Centre, Toronto, ON, Canada; 3Sunnybrook Health Sciences Centre, Toronto, ON, Canada
Purpose: To determine the contribution of vascular risk factors to poststroke depressive symptoms.
Methods: We conducted a cross-sectional observational study of stroke patients at Sunnybrook Health Sciences Centre between July 2005 and March 2009 (n = 93). Demographic and clinical information was gathered via chart review and patient interview. Clinical assessment included CES-D, NIHSS and MMSE. Patients with depressive symptoms (CES-D> = 16; n = 34) were compared to those without depressive symptoms (n = 59) on both presence of, and number of, vascular risk factors. Risk factors examined were hypertension, hyperlipidemia, diabetes mellitus, cigarette smoking and obesity (BMI>30).
Results: There were no between group differences found in demographics or clinical characteristics (age, gender, BMI, MMSE, NIHSS, time since stroke).
In this analysis, hypertension was the only vascular risk factor found in a significantly greater proportion of those with depressive symptoms (85.3% vs 66.1% p = 0.043). The cumulative number of vascular risk factors was similar in both groups (2.05 vs 1.78 p = 0.353).
Backward step-wise logistic regression analysis of all vascular risk factors showed only hypertension (p = 0.053) independently predicted the presence of depressive symptoms (chi-square = 4.52 p = 0.034 R2 = 0.070). When NIHSS and MMSE were added to the logistic regression model, stroke severity (p = 0.102) and hypertension (p = 0.051) remained as independent predictors of presence of depressive symptoms (chi-square = 6.75 p = 0.034 R2 = 0.117).
Conclusions: Poststroke depressive symptoms were associated with hypertension, but not with other vascular risk factors. Hypertension and stroke severity were predictive of depressive symptoms. There was no association between depressive symptoms and cumulative number of risk factors. Limitations include possible lack of variability of vascular risk factors among depressed and non-depressed groups.
PS02.107
Differentiating the cognitive profile of schizophrenia from that of Alzheimer's disease and depression in late life
Christina Ting; T Rajji; Z Ismail; D Tang-Wai; N Apanasiewicz; D Miranda; D Mamo; B Mulsant
Centre for Addiction and Mental Health (CAMH), Toronto, ON, Canada
Background: To compare the cognitive profile of older patients with schizophrenia to those of patients with other neuropsychiatric disorders assessed in a hospital-based memory clinic.
Methods: Demographic, clinical, and cognitive data of all patients referred to the memory clinic at the Centre for Addiction and Mental Health between April 1, 2006 and August 15, 2008 were reviewed. We then identified four groups of older patients with: (1) late-life schizophrenia (LLS) and no dementia or depression (DEP); (2) Alzheimer's disease (AD); (3) DEP and no dementia or LLS; (4) normal cognition (NC) and no DEP or LLS.
Results: The four groups did not differ in demographic data except that patients with AD were about 12 years older than those with LLS. However, they differed on cognitive measures even after controlling for age. Patients with LLS were impaired on most cognitive measures in comparison with patients with NC but not on recalling newly learned verbal information at a short delay. They experienced equivalent performance on learning new verbal information in comparison with patients with AD, but better performance on all other measures of memory, including the ability to recall newly learned verbal information. Finally, they were more impaired than patients with DEP in overall memory.
Conclusions: Patients with LLS have a different cognitive profile than patients with AD or DEP. Particularly, memory impairment in LLS seems to be more pronounced in learning than recall. These findings suggest that cognitive and psychosocial interventions designed to compensate for learning deficits may be beneficial in LLS.
PS02.108
Cognitive functioning and bio-socio-demographic profile of pre-elderly subjects
Rakesh Tripathi; S Tiwari; A Kumar; A Misra
CSM Medical University, Lucknow, India
Background: It is well known that cognitive functions decline with advancing age particularly in elderly 60 years & above. However, similar reports are hardly available for pre-elderly (55–59 years) age group. Elderlies are the extension of the pre-elderlies. Assessment of cognitive functioning vis-à-vis bio-socio-demographic profile of pre-elderlies may be of help to plan management of the vulnerable pre-elderlies stepping in elderlies. Thus, this study was planned. It was supported by the Indian Council of Medical Research (ICMR), New Delhi, India, in urban and rural areas of Lucknow—a North Indian City.
Objective: To study the cognitive functioning vis-à-vis bio-socio-demographic profile of preelderlies.
Material & Methods: The study universe consisted of randomly selected urban localities of Lucknow. Elderlies 55 years and above fulfilling stringent intake criteria and giving informed consent formed the study sample (N = 2283). Out of 2283 subjects 447 were of pre-elderly age group (55–59 years). These index subjects were subjected to screening through Mini Mental Status Examination (MMSE) to identify ‘suspects’ for cognitive dysfunctions (MMSE positive). Age and education specific cut off criteria was used to identify MMSE positive and negative subjects. Cognitive functioning of pre-elderlies on MMSE vis a vis bio-socio-demographic characteristics was analyzed using ‘chi square’ with yate's correction wherever applicable.
Results: Out of total 447 pre-elderlies 2.7% (12) were found to be positive and 97.3% (435) negative on MMSE. Significant differences were not found on MMSE positivity and negativity status by sex, socio-economic states (SES), education and occupation. However, more females (2.9%) than males (2.3%) were found to be cognitively impaired. More pre-elderlies from ‘upper’ SES (3.2%) were found to be cognitively impaired than ‘middle’ (2.8%) and ‘lower’ (2.1%) SES. Pre-elderlies educated up to ‘12th standard or above’ (3.7%) were found to be more cognitively impaired than educated up to ‘8th standard’ (3.1%), up to ‘10th standard’ (2.1%) and below ‘4th standard’ (1.4%), though the differences were statistically non-significant. In terms of occupation, 4.8% ‘businessman’ were found to be cognitively impaired in comparison to 2.77% ‘service men’ and 2.69% subjects who were currently ‘not doing anything’.
Conclusions: Findings reveal that females, subjects from upper SES, subjects educated up to 12th standard or above, and business people were more at risk for cognitive impairment amongst pre-elderlies. However, the findings are not statistically significant. There is a need to confirm these observations on a large sample.
Key words: Cognitive Impairment, MMSE, Pre-elderlies
PS02.109
The job stress, physical and mental health of home care aides for Taiwanese community-dwelling elders with disabilities
Shin Yann Tsai1; H Sung2; Y Chiu3
1Tzu Chi College of Technology, Hualien City, Taiwan; 2Tzui Chi College of Technology, Hualien, Taiwan; 3Mennonite Social Welfare Foundation, Hualien, Taiwan
With the increased number of elders with disabilities residing at home in the community, alternative care resources to assist with families fulfilling responsibility of caring for the frail elders at home become crucial for many Taiwanese families. One such resource is home care aides. Home care aides are considered as respite care for the family members who wish to care for their frail elders at home. Home care aides can assist the families in providing care for the disabled elders, allow the elders to stay in their homes, and prevent unnecessary institutionalization. Home care aides provide the majority of direct care for the disabled elders at home, but generally work for long hours and low wages with poor benefits, resulting in negative consequences, such as burnout, physical and mental problems, and high turnover rates. This study aimed to investigate the relationship between job stress, and physical and mental health of Taiwanese home care aides who provided care for community-dwelling elders with disabilities. A cross-sectional design was used. Self-administered questionnaires were sent to a convenience sample of 296 home care aides who took care of community-dwelling elders with disabilities in eastern Taiwan, and 274 completed the questionnaires, giving a response rate of 92.5%. The Occupational Stress Index (OSI-2) was used to assess the home care aides’ job stress, physical, and mental health. The results showed that “personal responsibility” was found to be the most frequently reported stressor and “relationship” as the second most frequently reported stressor by the home care aides. However, home care aides’ job stress was negatively correlated with mental health (r = −0.54, p < .01) and physical health (r = −0.35, p < .01). Adequate on-the-job training programs are needed to help home care aides to gain the necessary practical skills and become familiar with their job responsibilities for caring for elders with disabilities. Training on effective communication and relationship skills are also recommended as a potential strategy for reducing stress and dissatisfaction.
PS02.110
Outcomes of elderly Chinese suicide attempters: An eight-year prospective study
Joshua Tsoh1; H Chiu1; S Chan1; P Duberstein2
1The Chinese University of Hong Kong (CUHK), Hong Kong, SAR PR China; 2University of Rochester Medical Center (URMC), Rochester, NY, United States
Background: While suicidal behaviors in late life is a major public health concern, hitherto there have been very limited researches published concerning the outcomes of elderly suicide attempters or their correlates, especially in Chinese populations of which the rates of suicide are among the highest in the world.
Method: In this study we examined the outcome of a consecutive cohort of 66 elderly with medically-serious suicide attempts who had been admitted to a university-affiliated regional hospital in Hong Kong in 2001–2003 through follow-up interviews of the subjects or their proxy respondents, inspection of the subjects’ medical records and the local coroners’ archives from then till now. Outcomes including the rates of overall survival and repeated suicide attempts were examined, and in relation with the baseline characteristics (socio-demographics, personality, physical illnesses, functional competence, social network and support, life events, suicide intent, past suicide attempts, and psychiatric diagnoses) using Kaplan Meier survival analyses. Independent risk factors for the stated outcomes were determined with Cox's proportional hazard regression.
Results: Sixty-two subjects (93.9%) could be traced, of which 32 (48.4%) had passed away on Mar 1, 2009. Seven subjects (10.6%) have had repeated suicide attempts that were medically serious. All these had taken place within the subsequent 1 year after the index attempt, and through which 5 (7.5%) had killed themselves. These repeated-attempters were more likely male (HR = 6.4; df = 1; p = 0.03), and had marital problems (HR = 18.2; df = 1; p < 0.001) at baseline. On the other hand, predictors for lessened overall survival included male gender (HR = 2.7; df = 1; p = 0.006), familial discord at baseline (HR = 2.13, df = 1, p = 0.04) and the presence of chronic obstructive pulmonary disease (COPD; HR = 2.8; df = 1; p = 0.04) or cancer (HR = 4.5; df = 1; p < 0.001).
Conclusions: The rate of repeated suicidal behaviours in this sample is high. The first year after a suicide attempt represents a period of particularly elevated risk. The relative lack of baseline characteristics that reliably predict eventual suicidality as an outcome might suggest the main determinants rapidly evolve or emerge within this time window. Taken together these three findings signify the need for close follow-up care of this risk-laden group as a whole, especially in the immediate post-discharge period.
PS02.111
Neural correlates of language decline in primary progressive aphasia
Mathieu Vandenbulcke1; N Nelissen2; R Vandenberghe2
1University Hospital Leuven KUL, Leuven, Belgium; 2University Hospital Leuven KUL, Leuven, Belgium
Background: Cross-sectional MRI studies in primary progressive aphasia (PPA) have revealed a correlation between the degree of left anterolateral and temporopolar atrophy and dysfunction and naming and word comprehension impairment.
Objective: To study longitudinally how within-subject changes in brain structure and function over a 1-year period correlate with decline of language.
Methods: 18 patients with PPA and 15 matched controls participated. Neurolinguistic assessment consisted of the naming and comprehension task of Aachen Aphasie Test, verbal associative-semantic task of the PALPA, Token Test and Object Decision task (BORB). For all PPA patients, we calculated a Z-score of change for each neurolinguistic test score based on the mean change and SD of controls. Significant progression was defined by a Z-score exceeding 1.96. We correlated Z-scores of change with change of gray matter volume (VBM, SPM02).
Results: Token test declined significantly in 8 patients, naming in 6, associative-semantic task in 5, comprehension in 1 of the patients and Object Decision in none. Naming decline correlated significantly with decrease of gray matter volume of the left posterior inferior temporal gyrus (−48, −44, −22, ext. 535, Z = 4.11 corr. P < 0.001, r = 0.81) and the right middle temporal gyrus (56,-34,0, ext. 758, Z = 4.38, corr. P < 0.001, r = 0.83). Decline of comprehension correlated significantly with gray matter volume change of left superior temporal gyrus (−60, −44,20, ext. 375, Z = 3.70, corr.P < 0.05, r = 0.75). Gray matter volume change did not correlate with change of Token test or Object Decision.
Conclusion: In PPA, progression of naming and language comprehension impairment is associated with left posterior temporal and right-sided temporal atrophy.
PS02.112
The effects of donepezil on dichotomous milestones in patients with Alzheimer's disease
G Waldemar1; Y Xu2; J Mackell2
1Memory Disorders Research Group, Rigshospitalet, Copenhagen, Denmark; 2Pfizer Inc, New York, NY, United States
Background: Multiple behavioral disturbances, including apathy, delusions, hallucinations, and aberrant motor behavior (ABM) can develop during the progression of Alzheimer's disease (AD). Apathy, one of the most common behavioral symptoms in patients with AD, is particularly disturbing for caregivers and may be associated with reduced functioning of activities of daily living. While treatments, such as the cholinesterase inhibitor donepezil, may impact the emergence or severity of these troublesome symptoms in patients with AD, the frequency of such events is often too low in individual clinical trials to allow accurate assessment. However, pooling data from multiple clinical studies may provide sufficient statistical power to determine any treatment benefits. The objective of this study was to evaluate whether donepezil influences the occurrence or worsening of behaviors such as apathy, delusions, hallucinations, and ABM in patients with AD in a pooled analysis.
Methods: Data were pooled from two 24-week double-blind, placebo-controlled trials of donepezil for patients with AD. For the current analyses, data were pooled only from patients with a baseline Mini-Mental State Examination (MMSE) score ≥ 10. Differences in the time to emergence/exacerbation of apathy symptoms, delusions, hallucinations, and ABM were assessed in the donepezil- and placebo-treated groups using Kaplan-Meier methods and log-rank test. The proportion of events (emergence/exacerbation of behavioral symptoms) in the donepezil and placebo groups was compared at end point using the Cochran-Mantel-Haenszel (CMH) test, stratified by baseline status. For all analyses, emergence/exacerbation of symptoms (dichotomous events) was defined as the first postbaseline occurrence of a composite score ≥ 3 (severity × frequency) for the individual Neuropsychiatric Inventory (NPI) items of apathy/indifference, delusions, hallucinations, or ABM from the 12-item NPI.
Results: Kaplan-Meier analysis demonstrated a significant delay in emergence or exacerbation of apathy symptoms in patients treated with donepezil compared with those treated with placebo (P = .0126). Furthermore, a significant delay was also observed in the emergence/exacerbation of hallucinations (P = .0431) and ABM (P = .0260). Additionally, there was a significant difference between the donepezil- and placebo-treated groups in terms of the proportion of patients showing apathy emergence/exacerbation at study end point (P = .0277); overall 16.5% of patients in the placebo group showed emergence/exacerbation of apathy by end point, compared with 10.2% of patients treated with donepezil. A significant difference was also observed between the 2 treatment groups in terms of the proportion of patients demonstrating the emergence/exacerbation of delusions (P = .0297), hallucinations (P = .0266) and AMB (P = .0181) at study end point.
Conclusions: Treatment with donepezil resulted in a significant positive effect on the emergence/exacerbation of apathy symptoms as well as delusions, hallucinations, and ABM in patients with AD. This ability to delay the emergence or worsening of apathy symptoms and other disturbing behaviors might also positively impact the caregiver and potentially delay functional impairments.
PS02.113
A pilot longitudinal study on CSF and plasma biomarker change in Alzheimer's disease and vascular dementia
Shifu Xiao1; H Wang1; X Li1; T Wang1; S Chen2
1Shanghai Mental Health Center, Shanghai Jiaotong University School of Medicine, Shanghai, China; 2Ruijing Hospital, Shanghai Jiaotong University School of Medicine, Shanghai, China
Objective: To investigate longitudinal changes of CSF levels of total-tau (T-tau), phosphorylated tau at threonine 231 (P-tau231), beta-amyloid1–42 (Aβ1–42), beta-amyloid1–40 (Aβ1–40) and plasma levels of Aβ1–42, Aβ1–40 in patients with Alzheimer's disease and vascular dementia. Methods subjects with 11 moderate AD (MMSE = 10–20), 10 severe AD (MMSE less than 9) and 7 age-matched severe VD were included at baseline, 7 AD and 6 VD completed 6 months follow-up study. CSF levels of T-tau, P-tau231, Aβ1–42, Aβ1–40 and plasma levels of Aβ1–42, Aβ1–40 were measured with sandwich ELISA.
Results: At baseline, the mean CSF level of T-tau was (470.08 SD 263.58) pg/mL in AD patients, (208.76 SD 42.24) pg/mL in VD. The mean CSF level of P-tau231 was (90.94 SD 49.86) pg/mL in AD, (42.96 SD 13.10) pg/mL in VD. The mean CSF level of Aβ1–42 was (171.48 SD 56.82) pg/mL in AD patients, (146.14 SD 37.50) pg/mL in VD. The mean CSF level of Aβ1–40 was (746.38 SD 172.02) pg/mL in AD patients, (545.10 SD 147.80) pg/mL in VD. The mean plasma level of Aβ1–42 was (34.46 SD 22.98) pg/mL in AD patients, (32.81 SD 13.15) pg/mL in VD. The mean plasma level of Aβ1–40 was (45.00 SD 13.11) pg/mL in AD patients, (48.33 SD 11.93) pg/mL in VD. The levels of CSF T-tau, P-tau231 and Aβ1–40 were significantly higher in AD compared with VD group. Only plasma Aβ1–40 significantly increased in AD group during follow-up, the other markers did not change in either group during follow-up.
Conclusion: CSF levels of T-tau, P-tau231 and Aβ1–40 are significantly higher in AD group. All the biomarkers except for plasma Aβ1–40 cannot serve as sensitive markers of disease progression of AD.
PS02.114
An analysis of neuropsychiatric symptoms in community dwelling dementia patients: Prevalence and severity
Haibo Xue1; X Yao1; J Lv2; S Bo4; x Lu5; W Fang3
1Shanghai Mental Health Center, Shanghai, China; 2School of Public Health, Fudan University, Shanghai, China; 3Center of Disease Control for Mental Health of Shanghai Changning District, Shanghai, China; 4Center of Disease Control for Mental Health of Shanghai Minghang District, Shanghai, China; 5Center of Disease Control for Mental Health of Shanghai Jiading District, Shanghai, China
Objective: To investigate the prevalence of neuropsychiatric symptoms in community dwelling dementia patients.
Methods: This is a cross-sectional study. The diagnosis of dementia was made according to the DSM-IV criteria. Instruments using to evaluate include Mini-Mental State Examination (MMSE), Ability of Daily Living (ADL) and Neuropsychiatric Inventory (NPI).
Results: One thousand two hundred seventy one dementia patients and their care givers were interviewed by trained psychiatrists and neuropsychologists. Overal1, 637 patients have at least one or more neuropsychiatric symptoms. Insomnia/night behavior disturbance was the most common symptom with prevalence of 21.9% (n = 278). The prevalence of irritability was 19.6% (n = 249), and apathy was 15.7% (n = 200). Among the 637 patients that have at least one psychiatric or behavior symptom, 501 have a NPI score more than 4 points that have clinical significance. It means that 40% of all dementia patients surveyed need clinical intervention. The NPI score is correlated with patients' education, score of ADL and MMSE.
Conclusion: Psychiatric and behavior symptoms are common symptoms of dementia patients dwelling in community. Near 40% of these patients have the symptoms that need clinical intervention.
Key words: Dementia; Neuropsychiatric symptoms; Prevalence
PS02.115
Audit on ward team meeting practice
S Zafar
Penn Hospital, Wolverhampton, United Kingdom
To establish if the ward review practice in Prof. Benbow's team on cedar ward, Penn hospital is in line with the proposed standards and to consider whether the standards are appropriate.
PS02.116
Therapy of addition for Alzheimer's disease: Combination with galantamine and memantine
Julio Zarra1; L Schmidt2
1Hospital Italiano de La Plata, La Plata, Argentina; 2Hospital Centenario, Gualeguaychú, Argentina
At the conclusion of this session, the participant should be able to demonstrate with use the association memantine – galatamine in neurocognitive disorder: Alzheimer's disease, improve cognition, behavioural symptoms, and the general state recognized as neurocognitive disorder.
Objective: The efficacy, safety, and tolerability of nootropic cholinergic agent: GALANTAMINE (with a dual mechanism of action on the cholinergic a system) and moderate affinity NMDA- receptor antagonist: MEMANTINE, were assessed taking into account the profile of patients with neurocognitive disorder: Alzheimer's disease, from the clinical aspects and the different classifications.
Methods: The experience included 188 patients who were enrolled in a prospective, observational, multicenter, and open-label study to receive 16 mg/day of galantamine and 30 mg/day of memantine for 12 months of treatment of addition.
Results: The therapeutic response was measured using the Mini Mental State Examination (MMSE), Clinical Dementia Rating (CDR), Alzheimer's Disease Assessment Scale (ADAS-GOG), Functional Activities Questionnaire (FAQ) the Clinical Global Impression Scale (CGI) and the UKU scale of adverse effects taking into account the efficacy, safety and adverse events of the treatment.
Conclusion: The final results of the study showed that galantamine with addition memantine improves cognition, behavioural symptoms, and the general well-being of patients with cognitive impairment: Alzheimer's disease. The incidence of adverse events was not significant and a very good profile of tolerability and safety was observed.
PS02.117
Mild cognitive disorder and depression: Treatment with association between galantamine and escitalopram
Julio Zarra; L Schmidt
Hospital Italiano de La Plata, La Plata, Argentina
The study was intended to evaluate the efficacy of galantamine-escitalopram association in patients with Mild Cognitive Disorder and Depression. There is a possible relation between the deficit of cerebral oxygenation and depression or relation between the serotonin system and cholinergic system in relation with disease comorbidity cognitive-depression.
Objective: To evaluate the therapeutic response in patients with comorbidity between Mild Cognitive Disorder and Depression in treatment with Galantamine, Escitalopram and the two drugs associated.
Method: A group of 300 patients with symptoms of Mild Cognitive Disorder and Depression (DSM IV-R criteria) were separated in 3 groups of 100 patients. Each group received different treatment in an 8 months period:
Group 1: Galantamine 16 mg/day
Group 2: Escitalopram 20 mg/day
Group 3: both drugs, same dose
Results: The therapeutic response evaluated in Hamilton Scale for Depression (HAM-D), Montgomery and Äsberg Depression Rating Scale (M.A.D.R.S.), Mini Mental State Examination (M.M.S.E.) and Global Clinical Impression (G.C.I.) scores during 8 months. In the third group who received the two drugs associated, subjects had much better response than the others and “brain enhancer”.
Conclusion: The group who received the association of the nootropic agent Galantamine with antidepressant (SSRIs) Escitalopram had a relevant satisfactory therapeutic response (the best result), so there is a possible relation between the deficit in cholinergic systems and depression. Could cerebral cholinergic systems deficit be a generator of Depressive Disorder?
PS02.118
Long-term efficacy and safety of galantamine in outpatients with mild cognitive disorder
Julio Zarra1; L Schmidt2
1Hospital Italiano de La Plata, La Plata, Argentina; 2Hospital Centenario, Gualeguaychú, Argentina
Purpose: Galantamine is a reversible, competitive cholinesterase inhibitor that also allosterically modulates nicotine acetylcholine receptors. Inhibition of acetylcholinesterase, the enzyme responsible for hydrolisis of acetylcholine at the cholinergic cognitive impairment. To evaluate the efficacy, safety and tolerability of galantamine in long-term in Mild Cognitive Disorder.
Methods: A multicenter, open label, prospective, observational study enrolled 800 patients, more 50 years old with Mild Neurocognitive Disorder (DSM IV criteria), during 24 months of treatment with galantamine 16 mg/day. Assessments included the Mini Mental State Examination (MMSE), Clinical Dementia Rating (CDR), Alzheimer's Disease Assessment Scale (ADAS-GOG), Seven minutes test, Wisconsin card sorting test, Boston naming test, Token test, Raven Test, Brow-Peterson test, Trail making test, Functional Activities Questionnaire (FAQ), GO-NO-GO test, Global Deterioration Scale, Global Clinical Impression (GCI) and UKU scale of Adverse Effects.
Results: A total 800 outpatients were treated with 16 mg/day galantamine during 24 months, the therapeutic response evaluated with CDR, MMSE and the tests and scales of function cognitive measuring, GCI and UKU scale of adverse effects, comparing the baseline to final scores.
Conclusion: Mild Cognitive Disorder is being examined, so there aren't enough treatments for this. A long-term treatment (24 months) galantamine improves cognition and global function, behavioural symptoms and the general well being of patients with Mild Cognitive Disorder. With incidence of adverse effects not significant and a very good profile of safety, the final results of the study suggest that galantamine may be particularly appropriate in Mild Cognitive Disorder.
PS02.119
Acceleration of hippocampus atrophy in a non-demented elderly population, the SNAC-K study
Yi Zhang1; C Qiu1; B Lena2; L Bäckman1; P Aspelin1; L Fratiglioni1; L Wahlund1
1Karolinska Institutet, Stockholm, Sweden; 2Aleris Diagnostics, Stockholm, Sweden
Background: Brain atrophy in Alzheimer's disease (AD) patients includes not only AD specific brain atrophy but also the atrophy induced by normal aging. Medial temporal lobe atrophy has been one of the most important diagnostic markers for AD, but atrophy of hippocampus and other brain structures has also been found to emerge in healthy adults, along with increasing age. It has been reported that the important age point when age-related hippocampus shrinkage starts was around mid-40s.
The first aim of this study was to create a normative database of hippocampus volume in different age cohorts (60–90+), and to investigate gender difference and lateral asymmetry in a large population-based study. The second aim was to study the aging atrophy trend (AAT, this is used by us to express the speed and acceleration of brain atrophy) and to find if an acceleration of hippocampus atrophy occurs in non-demented elderly?
Methods: 544 subjects (age 60–97 y, Female 318, and Male 226) were recruited into the MRI study by using a sub-sample of an epidemiological sample of 3363 healthy non-demented elderly populations (over 60 y) who are participating in the Swedish National study of Aging and Care in Kungsholmen (SNAC-K). Hippocampus and ventricle sizes were measured.
Results: The normalized (by intracranial volume, ICV) volumes of left, right and total hippocampus in males were smaller than that in females, although the mean of raw volumes was bigger in males. Right hippocampus was larger than the left, regardless of gender. The expansion speed of the lateral ventricles (2.80% per year in male, 2.95% in female) and 3rd ventricle (1.58%, 2.28%) was larger than the shrinkage speed of hippocampus (0.7%, 0.87%). The age point 72 years was suggested to represent the time when the acceleration of hippocampus atrophy started.
Conclusions: The males had smaller hippocampus volume (normalized by ICV) than females, however, the females are more vulnerable to hippocampus atrophy in this study-population. An acceleration of hippocampus atrophy may emerge and start around 72 years of age.
PS02.120
Usage of gabapentin in elderly bipolar patients
Matt Robillard; D Conn
University of Toronto, Toronto, ON, Canada
Purpose: To study the effectiveness of adding gabapentin (a new anticonvulsant) to geriatric bipolar patients who were in the depressed phase and were on concurrent psychotropic medications including both lithium carbonate and valproate.
Methods: A group of 5 bipolar geriatric inpatients who were in the depressed phase and not responding to antidepressant therapy were given gabapentin. Dosages were in the range of 600 to 900 mg/day and patients had a minimum trial of one month. Informed consent was obtained. Response was assessed by clinical assessment by psychiatrist as well as Hamilton Rating Scales.
Results: The group of patients included three women and two men. Four had rapid cycling subtype and one had mixed subtype. Patients were kept on both lithium and valproate and gabapentin was added as the patients had not responded to the addition of antidepressant medications. Of the five, one women with a mixed state had remission of depressive episode within 4 days. The other four patients had no response. When this patient who initially responded to gabapentin had a relapse a few months later, her mood improved when the dosage was increased from 300 mg bid to 300 mg tid. However, over the next few months she had more relapses of hypomanic episodes as well as depressive episodes. The gabapentin appeared to be well tolerated by all five who took the medication but two complained of headaches that seemed to be of a more chronic nature.
Conclusions: From this small case series it is clear that the management of refractory bipolar illness remains a challenge and that gabapentin did not appear to be effective in the acute phase of treatment. Gabapentin was well tolerated by the patients. It is not clear what is the optimal dosage for its usage in mood disorders when it is tried. Skepticism and caution are warranted in interpreting the results of an open, small, uncontrolled case series and there is a need for randomized controlled trials.
PS02.121
Does serotonin augmentation have any effect on cognition and activities of daily living in Alzheimer's dementia? A double-blind, placebo-controlled clinical trial
Arash Mowla
Bushehr University of Medical Sciences, Bushehr, Iran
Objective: Recent studies suggest that cholinergic dysfunction does not provide a complete account of age-related cognitive deficits, and other neuronal systems like monoaminergic hypofunction are involved. In several studies, selective serotonin reuptake inhibitors demonstrated promotion in neurogenesis in the hippocampus and enhanced memory and cognition. The aim of this study is to survey the effect of serotonin augmentation on cognition and activities of daily living in patients with Alzheimer's disease.
Method: The trial was designed as a 12-week randomized, placebo controlled, double-blind study. One hundred twenty-two patients aged 55 to 85 years with mild-to-moderate Alzheimer's dementia were randomly allocated in 1 of the 3 treatment groups: fluoxetine plus rivastigmine, rivastigmine alone, or placebo group. Efficacy measures comprised assessments of cognition, activities of daily living, and global functioning. Hamilton Depression Scale also was used to assess changes in mood throughout the study.
Result: Fluoxetine plus rivastigmine and rivastigmine groups demonstrated improvement on measures of cognitive and memory without any significant difference; however, the former group did better in their activities of daily living and global functioning. Patients taking placebo had significant deterioration in all the efficacy measures. Patients taking rivastigmine or rivastigmine plus fluoxetine had improvements in Hamilton Depression Scale without significant differences.
Conclusions: Concomitant use of selective serotonin-enhancing agents and acetyl cholinesterase inhibitors can provide greater benefit in activities of daily living and global functioning in patients with cognitive impairment. Because our study is preliminary, larger double-blind studies are needed to confirm the results.
PS02.122
Neurobiology of late-life depression: An update
Alan Thomas1; Ian Hickie2; J. O'Brien1; Akshya Vasudev1
1Newcastle University, Newcastle upon Tyne, United Kingdom; 2University of Sydney, Sydney, NSW, Australia
Important advances continue in our understanding of the neurobiology of depression in older people. The speakers will present some of these developments using previously unpublished data and will place these findings in their research context. Post-mortem studies of morphometric abnormalities in frontal-subcortical circuits Studies to date suggest cellular abnormalities are present in major depression but may be different in different age groups. In the prefrontal cortex a reduction in the density of glial cells in major depression has been reported in most studies in mid-life and mixed age groups with little evidence of neuronal abnormalities. However, in late-life depression no changes in glial density appear to occur but changes in pyramidal neurones have been reported in both the dorsolateral and orbitofronal cortices, especially in cortical layers 3 and 5. Similar abnormalities have been identified in the caudate nucleus.
Genetic and environmental predictors of MRI-based neuroimaging changes in late-life depression: Older persons with more severe forms of depression have increased rates of a range of deep white matter, subcortical nuclei and hippocampal abnormalities on MRI imaging. These changes are correlated with disability, cognitive dysfunction and impaired response to treatment. Predictors of these changes appear to include later age of onset of depression, as well as genetic and environmental risk factors to vascular disease and genetic risk factors to depressive disorders. Further elucidation of these risk factors may lead to more targeted prevention and early intervention programs for late-life depression. In Australia, we have begun to use these factors as the basis for specific depression prevention trials in community-based subjects with elevated depression symptom scores.
Functional Connectivity in late-life depression: Late life depression is thought to be associated with frontostriatal dysfunction. Using resting state blood oxygen level dependent (BOLD) MR imaging, spontaneous low frequency signal fluctuations act as a measure of functional connectivity between brain regions. We studied 17 older people with recovered depression and 17 controls. In controls, significant functional connectivity was seen between caudate and frontal lobes. However, in depressed subjects functional connectivity was increased and present over a much wider brain area (including parietal, frontal, subcortical and limbic regions). These new data support the view that connectivity in mood regulating circuits is disrupted in late life depression and demonstrate the utility of resting BOLD as a non invasive probe of neural function.
Blood Pressure Changes and Late-life Depression: White matter hyperintensities and vascular brain changes are present in late-life depression, though clinical studies usually do not report an excess of clinically determined vascular risk factors in this patient group. These studies have not assessed orthostatic hypotension, a recently recognised risk factor for white matter hyperintensities. We have investigated whether blood pressure changes and orthostatic hypotension occur in late-life depression and present novel data indicating there may be a relationship between depression and orthostatic blood pressure abnormalities.
PS02.123
Accelerating knowledge translation in seniors' mental health and dementia
J Le Clair2; Kimberley Wilson1; D Conn3; S Helsdingen1
1CCSMH, Toronto, ON, Canada; 2Queen's University, Kingston, ON, Canada; 3University of Toronto, Toronto, ON, Canada
In 2008, seven partner organizations came together to advance knowledge exchange in the field of seniors' mental health and dementia. Knowledge transfer and exchange has increasingly been seen as an important vehicle for advancing effective, efficient, and accessible health. The collective wisdom and collaborative interfaces between researchers, practitioners, policy makers, and consumer groups has been identified as critical to the transformational change required to bring policy to practice, practice to policy, science to services, and services to science. A growing and increasingly important population with significant needs, challenges and complex, chronic disorders are seniors, seniors with mental health challenges, and those with dementia. The Knowledge Exchange Think Tank Initiative represents Canadian partnerships to accelerate knowledge transfer to practice. The seven partners are the Canadian Coalition for seniors' Mental Health (CCSMH), the Mental Health Commission of Canada – seniors' Advisory Group, Public Health Agency of Canada, Canadian Dementia Knowledge Translation Network, National Initiative for the Care of the Elderly (NICE), Alzheimer Knowledge Exchange of Ontario (AKE), and seniors' Health Research Transfer Network (SHRTN).
The project's long-term objectives include:
1. To enhance the capacity of knowledge translation and exchange as it relates to seniors' mental health and dementia.
2. To explore and identify strategies for continuous interchange through the development of a national community of practice.
3. To highlight successful exchanges and to raise the profile of seniors' mental health and dementia for ongoing support.
4. To understand how strategies in knowledge exchange from mental health and dementia sectors can be applied to all other sectors of senior health.
5. To identify and examine the use of technology and creative communication systems to engage partners and stakeholders in collaborative initiatives across the country.
6. To streamline the knowledge exchange processes in the field of seniors' mental health and dementia to increase the knowledge and power of stakeholders and advocates.
In March 2009, the partners hosted a ‘Think Tank’ bringing together more than 85 experts in aging, mental health, dementia and knowledge exchange, including experiential experts, to discuss the key lessons for the development of a knowledge exchange centre and to explore the possibility of creating a national community of practice in the area of seniors' mental health and dementia.
This presentation will highlight the key lessons in knowledge translation with a focus on the knowledge translation in seniors' mental health and dementia, as well as reporting on the outcomes of the March 2009 National Think Tank.