The magnitude of the public health problem posed by preterm birth (PTB) is underscored by reports that approximately 540 000 premature infants are born each year and more than $26 billion is spent annually to treat them. This figure is a highly conservative estimate because it does not include rehabilitation or long-term care costs. Early PTB (less than 34 weeks of gestation) accounts for almost 70% of neonatal deaths and 75% of neonatal morbidity (Ref. Reference Stoll1). The US National Institutes of Health made translational medicine a priority (Refs Reference Zerhouni2, Reference Fagnan3). In this context, there is a pressing need to develop novel biomarkers and technologies to predict pregnancies at risk for PTB. The development of targeted primary and secondary prevention strategies and treatments to prevent PTB is vital.
Pregnancy is a critical time during a woman's reproductive life because of the unique adaptation to a new physiological challenge and defiance of the immunological rules of rejection by the placenta and developing fetus. Scientists have investigated ‘the timing of birth’ along with the development, physiology and pathophysiology of the fetus and its environment for many years (Refs Reference McLean4, Reference Zenclussen5, Reference Mendelson6). Unfortunately, the molecular mechanisms set in place to prevent the inappropriate activation of the uterine contractile machinery and PTB continue to be incompletely understood (Ref. Reference Muglia and Katz7).
There is compelling evidence to suggest that the PTB syndrome involves several underlying pathogenetic pathways and aetiological factors (Ref. Reference Buhimschi8). Four distinct pathways probably account for most spontaneous PTBs: (Reference Stoll1) maternal or fetal stress, (Reference Zerhouni2) excessive myometrial and cervical stretching, (Reference Fagnan3) decidual haemorrhage (abruption) and (Reference McLean4) infection or exaggerated inflammatory response to genital tract microbes (Ref. Reference Lockwood and Kuczynski9). Each has unique genetic and environmental predispositions and most have immunologically mediated or inflammatory components. Understanding of the role of polymorphic maternal–fetal ‘incompatibility’ in triggering PTB and the role of environmental factors in this complex equation is still in its infancy (Ref. Reference Anum10).
The diverse pathways fuelling PTB-associated uterine contractility, cervical ripening, rupture of membranes and fetal damage have been previously reviewed (Ref. Reference Lockwood and Kuczynski9). The multiple iterative pathways leading to prematurity and the complex interactions among relevant mechanisms obscure the triggering event for most PTBs. However, irrespective of the initial stimulus, it is believed that inflammation is a unifying signalling pathway leading to most term births and PTBs (Refs Reference Mendelson6, Reference Challis11, Reference Norman12, Reference Weiner13). Here, we will focus on abruption-induced PTB.
Decidual bleeding (abruption)
Clinical aspects
Placental abruption is defined as complete or partial separation of the placenta from the implantation site (Ref. Reference Hall14). Its incidence ranges from 0.5% to 2%, depending on the clinical definition and criteria used to characterise abruption intensity (Refs Reference Elsasser15, Reference Ananth16), whereas abruption-associated maternal and fetal deaths occur in <1% and 3–10% of cases, respectively (Refs Reference Hall14, Reference Ananth17). Other major maternal sequelae are renal failure, disseminated intravascular coagulation, transfusion and hysterectomy. The occurrence of abruption peaks at 24–27 weeks of gestation (Ref. Reference Oyelese and Ananth18), with more than 50% of abruption cases associated with PTB (Ref. Reference Ananth17). Consequently, the high rate of abruption-related perinatal mortality of approximately 119 cases per 1000 births is heavily confounded by prematurity (Ref. Reference Ananth and Wilcox19). Neonatal risks of prematurity include intraventricular haemorrhage, bronchopulmonary dysplasia, retinopathy prematurity, deafness and cerebral palsy. Thus, in addition to fetal hypoxic ischaemic injury, abruption increases the likelihood of short- and long-term morbidities for surviving babies.
In cases of abruption, the extent of retroplacental bleeding has a significant impact on the clinical manifestations of this condition (Ref. Reference Ananth and Wilcox19). The classic clinical presentation of acute abruption includes vaginal bleeding, uterine contractions and abnormal fetal heart rate patterns. Concealed abruption, when bleeding is not clinically evident, is of particular concern and presents a challenging diagnostic scenario. In these situations, the diagnosis of placental abruption is generally established intra- or postpartum based on fresh macroscopic or histological examination of the placenta (Refs Reference Elsasser15, Reference Salafia20).
Pathophysiology of placental abruption
The haemostatic milieu of human decidua is integral to normal human implantation and placental development (Refs Reference Lockwood and Kuczynski9, Reference Lockwood21). Survival of the blastocyst and embryo, and successful development of the fetus require that extravillous endovascular cytotrophoblasts (EVTs) gain access to the maternal circulation by penetrating the wall of the uterine spiral arteries without inciting haemorrhage (Ref. Reference Benirschke22). This process is gradual and well coordinated and provides the developing maternal–fetal unit with a vital source of oxygen and nutrients. Disarray of the highly controlled and synchronised molecular mechanisms of placenta formation at the maternal–fetal interface increases the risk of haemorrhage, leading to both abortion and abruption. The key histological finding in placental abruption is haemorrhage in the decidua basalis (Ref. Reference Hall14). Such haemorrhage is thought to result from pathological processes damaging the vascular endothelium at the uteroplacental interface (Refs Reference Elsasser15, Reference Salafia20, Reference Dommisse and Tiltman23).
Placental abruption is traditionally viewed as an acute event. However, histological evaluation of the vasculopathy accompanying decidual haemorrhage provides compelling evidence that the damage is frequently chronic (Refs Reference Elsasser15, Reference Salafia20, Reference Nath24, Reference Arias25). Indeed, the most frequently encountered histopathological lesions co-associated with chronic decidual bleeding were chronic deciduitis and villitis, hypovascularity, infarct, necrosis or fibrosis of the placenta, blood vessels with absent physiological changes, vascular thrombosis and increased numbers of circulating nucleated erythrocytes (Ref. Reference Salafia20). In addition, a recent study found that acute lesions of chorioamnionitis and funisitis were frequently associated with histological evidence of abruption (haematoma, fibrin deposition, compressed villi and haemosiderin-laden histiocytes) (Ref. Reference Elsasser15).
For an adequate understanding of the molecular mechanisms and pathways governing the process of abnormal decidual bleeding, we will first outline the crucial roles of vascular endothelium and haemostatic balance during pregnancy. We will further discuss several mechanisms responsible for the crosstalk between coagulation and inflammation, with special emphasis on abruption. Finally, we will concentrate on genetic risk factors, progesterone and tissue factor (TF)-generated thrombin that modulate the crosstalk between coagulation and inflammation leading to abruption and PTB.
Physiological roles of vascular endothelium and haemostatic balance during pregnancy
Vascular endothelium
Maintenance of pregnancy requires the proper functioning of molecular mechanisms responsible for regulating endothelial permeability and circulatory homeostasis in decidual, placental, umbilical and fetal vessels (Refs Reference Pober and Sessa26, Reference Kumar27, Reference Reznik28, Reference Liu29, Reference Pinheiro da Silva and Soriano30). In addition to its role as a mechanical barrier, the vascular endothelium maintains normal blood fluidity and vessel wall permeability, regulates leukocyte trafficking (Refs Reference Pober and Sessa26, Reference Kumar27, Reference Ley and Reutershan31) and maintains strict control of the coagulation pathways (Ref. Reference Levi and van der Poll32).
Tissue factor
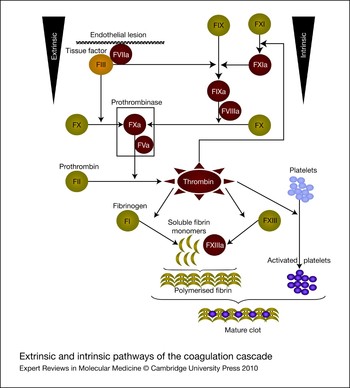
TF is a member of a cytokine receptor superfamily comprising a hydrophilic extracellular domain, a transmembrane hydrophobic domain and an intracellular tail (Refs Reference Levi and van der Poll32, Reference Bach, Nemerson and Konigsberg33, Reference Spicer34). Binding of the extracellular domain of TF to plasma-derived factor VII (FVII) or its active form, FVIIa, markedly enhances the catalytic activity (Fig. 1) (Ref. Reference Polgar, Matuskova and Wagner35). The TF–FVIIa complex activates FX and FIX, which ultimately generate thrombin that cleaves fibrinogen to fibrin and activates the platelets. Consequently, TF acts as the primary initiator of coagulation and is at the centre of the crosstalk between coagulation and inflammation pathways.
Extrinsic and intrinsic pathways of the coagulation cascade. Tissue factor (TF) is recognised as the main initiator of the coagulation cascade. Once formed, the TF–FVIIa complex initiates clotting by activating both FX and FIX thus, TF carries a unique ability to act through both intrinsic and extrinsic pathways of coagulation. Activated FIX binds to its cofactor VIIIa, to activate FX. Thus, the FVIIIa–FIXa complex of the intrinsic pathway provides an alternative route to generate FXa, which participates in the prothrombinase complex (FVa–FXa). The latter complex activates prothrombin to thrombin, which has a central role in the coagulation protease cascade. Thrombin, in turn, activates FXI, which is an alternative way of generating FIXa. Thrombin also activates FXIII, which stabilised fibrin polymers, but thrombin's most crucial functions are to cleave fibrinogen to fibrin and stimulate platelets by the cleavage of protease-activated receptors. The end result is haemostasis and thrombosis. Abbreviations: FI, factor I; FII, factor II; FIII, factor III; FV, factor V; FVII, factor VII; FIX, factor IX; FX, factor X.

Tight control of TF gene (F3) expression is crucial to maintain the balance between blood fluidity and haemostasis (Ref. Reference Moll36). The mechanisms in control of TF gene expression and its biology have recently been evaluated (Refs Reference Rao and Mackman37, Reference Popescu, Lupu and Lupu38, Reference Mackman39). However, several aspects should be emphasised. First, inhibition of the TF–FVIIa proteolytic activity by specific plasma and vascular endothelium TF pathway inhibitors (TFPIs) is a crucial protective mechanism against aberrant coagulation (i.e. thrombosis) (Refs Reference Rao and Mackman37, Reference Krikun, Lockwood and Paidas40, Reference Rao and Pendurthi41). The haemostatic balance between TF and TFPI seems to be operational in the human placenta and endothelial cells of the umbilical vein (Ref. Reference Aharon42). Second, TF is constitutively expressed on the cell surface of mesenchymal and epithelial cells localised in the brain, heart, kidney, lung, uterus and placenta (Ref. Reference Polgar, Matuskova and Wagner35). However, as demonstrated by immunohistochemical studies, endothelial cells that are in contact with the circulation do not normally express TF as a surface antigen (Refs Reference Pober and Sessa26, Reference Drake, Morrissey and Edgington43). Given that TF is primarily localised and sequestered within the vascular adventitia and tissue parenchymal cells, clotting factors cannot penetrate the intact endothelial wall to initiate the coagulation pathway. Thus, the vascular endothelium serves as a haemostatic ‘envelope’ (Ref. Reference Stassen, Arnout and Deckmyn44).
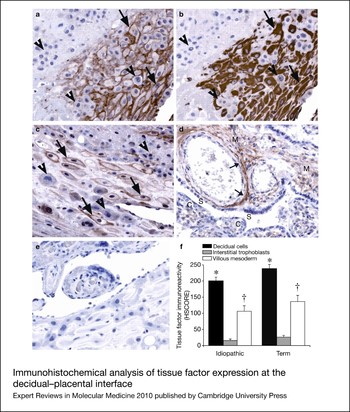
The expression and functional role of TF in human pregnancy have been previously studied (Ref. Reference Lockwood45). In humans, decidual-cell-expressed TF prevents haemorrhage, initially as blastocyst-derived EVTs breach decidual capillaries to establish the fetal–maternal circulation (Ref. Reference Lockwood and Kuczynski9). Subsequently, TF continues to have a crucial role during placenta formation because EVTs mediate decidual vessel remodelling to increase blood flow to the developing fetal–placental unit (Ref. Reference Anum10). At the maternal–fetal interface at term, immunoreactive TF levels are highest in decidual cells, with the trophoblast virtually devoid of TF immunostaining (Fig. 2) (Ref. Reference Lockwood46). These observations were also made in idiopathic PTB specimens (Ref. Reference Challis11). Thus, we can conclude that decidual-cell-expressed TF is strategically positioned at the maternal–fetal interface to meet the haemostatic demands of parturition (Ref. Reference Lockwood46).
Immunohistochemical analysis of tissue factor expression at the decidual–placental interface. Serial sections of decidual basalis specimens immunostained for tissue factor (TF) and vimentin, as shown in an idiopathic preterm specimen: (a) TF and (b) vimentin. Decidual cells (arrows), identified by positive vimentin staining, exhibit strong perimembranous TF staining. TF staining is absent in the interstitial trophoblast (arrowheads). Similar results are seen in term specimens (c). Placental villi show moderate TF staining in the mesoderm (M), in which the staining is primarily localised to perivascular adventitia (small arrows), as shown in a preterm specimen (d). The syncytiotropoblast (S) and cytotrophoblast (C) show no TF staining. Similar results are seen in term specimens (not shown). Negative control immunostaining using a nonspecific isotype-matched antibody revealed no positive signals (e). TF staining intensity (f) [bars indicate histological score (HSCORE) mean ± s.e.m.] is highest in decidual cells (*P<0.05, versus interstitial trophoblast and the villous mesoderm of the same specimen group), with moderate staining in the villous mesoderm (†P<0.05, versus interstitial trophoblast of the same specimen group). There are no significant differences in HSCORE values between specimen groups. Published with permission from Ref. Reference Lockwood46 (© 2009, The Endocrine Society).

A relevant question relates to the stimulus driving the decidual expression of TF in pregnancy. There are data to suggest that both progesterone and oestrogen have key modulatory roles (Refs Reference Lockwood47, Reference Schatz48). The concerted actions of oestradiol and progesterone induce decidualisation of stromal cells derived from the human endometrium (Refs Reference Lockwood47, Reference Schatz48). During decidualisation, the stromal cells begin to express TF. However, the absence of oestrogen or progesterone receptor (PR) recognition motifs on the TF gene promoter region prompted research aimed at exploring the involvement of other paracrine factors (Ref. Reference Lockwood49). Indeed, it was shown that progestin-enhanced TF expression ultimately requires activation of the epidermal growth factor receptor pathway (Ref. Reference Lockwood49). Moreover, in term human decidual cell monolayers, TF mRNA and protein expression were enhanced by incubation with exogenous progestin.
Observations on transgenic mice indicate that TF is crucial in pregnancy
No TF-deficient condition has been described in humans (Ref. Reference Mackman39). This emphasises the importance of TF expression to species survival while obviating the possibility of direct assessment of the effects of human TF deficiency. Adult mice that express low levels of TF suffer from haemostatic defects in the heart, lung, uterus and placenta, which are tissues that constitutively express high levels of TF (Ref. Reference Erlich50). Pregnant mice with reduced TF expression experience blood pools in the placental labyrinth and are highly susceptible to postpartum haemorrhage and death (Ref. Reference Erlich50). The importance of TF expression to survival is underscored by the observation that fetuses of murine TF gene knockouts develop fragile aberrant vessels and die of haemorrhage in utero (Ref. Reference Erlich50). However, incorporation of a human minigene expressing TF at only 1% of the wild-type level was sufficient to rescue these TF-knockout mice and enable them to produce live-born pups.
Antithrombotic mechanisms and TF
In addition to TFPIs, several other physiological mechanisms block the aberrant activation of coagulation by TF. Among these are the following: (Reference Stoll1) a blood flow profile consistent with high laminar shear stress (Ref. Reference Bergh51); (Reference Zerhouni2) cell-surface expression of heparin sulfate proteoglycans, which bind to antithrombin to greatly enhance thrombin inactivation (Ref. Reference Mertens52); (Reference Fagnan3) expression of thrombomodulin, a membrane protein that shifts the specificity of thrombin from a procoagulant converter of fibrinogen to fibrin to an anticoagulant activator of protein C (Ref. Reference Jackson and Xue53); (Reference McLean4) activated protein C and its cofactor protein S that inactivate FVa and FVIIIa, which are key cofactors of FXa and FIXa, respectively (Ref. Reference Castellino and Ploplis54); and (Reference Zenclussen5) maintenance of platelets in a quiescent state by preventing endothelial cell activation (Refs Reference Pober and Sessa26, Reference Ignarro55). All these mechanisms are present in uteroplacental circulation and have functionally relevant roles in the human placenta and in normal fetal development (Refs Reference Harris56, Reference Dempsey57).
Adaptive versus maladaptive inflammation
Inflammation is a highly coordinated process designed to guard and ensure the survivability of vertebrate organisms (Refs Reference Meeusen, Bischof and Lee58, Reference Martinon, Mayor and Tschopp59). When properly controlled, the inflammatory response is beneficial to the host, but when occurring in disarray its effects become detrimental (Ref. Reference Reddy60). Traditionally, it was thought that infection, bleeding and trauma that lead to tissue injury are the primary triggers of inflammation. It is thus not surprising to learn that substantial progress has been made in understanding the inflammatory response to the above three factors. For instance, studies of sepsis and haemorrhagic shock in humans and animal models show that both conditions are characterised by the acute release of a variety of inflammatory mediators, which can result in damaging effects on the host (Refs Reference Cinel and Opal61, Reference Benhamou62). What we have learned from both conditions is that the balance between the expression of pro- and anti-inflammatory molecules determines the magnitude of the damage.
Physiological versus pathological inflammation
As our understanding of the inflammatory process has evolved, we have gained a greater appreciation for not only the pathological but also the physiological aspects of the inflammatory process. Whereas the teleological rationale of an inflammatory response to pathological states is obvious, there is less understanding of the physiological role of inflammation, especially in reproductive tissues. For example, studies have shown that maintenance of normal cellular homeostasis in the human decidua, placenta and amniochorionic membranes involves molecules normally associated with either immune or inflammatory processes, such as interleukin (IL)-1, IL-8, tumour necrosis factor (TNF)-α, nitric oxide (NO), vascular endothelium growth factor (VEGF), angiopoietins, high-mobility group box protein-1 (HMGB-1), matrix metalloproteinases (MMPs), complement factors and soluble receptor for advanced glycation end products (Refs Reference Arcuri63, Reference Lockwood64, Reference Buhimschi65, Reference Lee66, Reference Buhimschi67, Reference Dunk68, Reference Ahmed69, Reference Holmlund70, Reference Buhimschi71). There is evidence to suggest that each of these molecules has critical effects both during normal development and throughout pathologically triggered inflammation.
Human decidua as a distinctive immune tolerance environment
Immune tolerance is necessary at the maternal–fetal interface. The cellular component (i.e. natural killer cells and macrophages) and functional regulation of the cells implicated in controlling the normal silent inflammatory process of the human uterine decidua have been extensively reviewed (Refs Reference Bulmer, Williams and Lash72, Reference Mantovani73). The gene expression profiling of human decidual macrophages confirmed that in normal pregnancy these cells display a distinctive transcriptional profile comprising a large number of genes functionally related to immunomodulation and tissue remodelling (Ref. Reference Gustafsson74). Of the 14 000 genes examined, genes encoding the chemokine CCL-18, CD209 (DC-SIGN, a C-type lectin receptor characteristically present on dendritic cells), insulin-like growth factor (IGF)-1, mannose receptor C-type (MRC)-1, S100 calcium-binding protein (calgranulin A) and fibronectin-1 were conspicuous because of their known immunological function (Ref. Reference Gustafsson74). The concerted regulation of these genes provided valuable insight into the phenotype of placental and decidual macrophages, which seems to be balanced towards immunosuppression because of the preferential expression of anti-inflammatory cytokines and chemokines (Refs Reference Mantovani73, Reference Gustafsson74). The mechanisms responsible for switching these factors from beneficial to ‘suicide’-assisted molecules are incompletely understood. However, the novel ‘danger’ theory holds that in addition to upregulation of the proinflammatory cytokines, the injured cells release alarm signals (i.e. HMGB-1), which in turn activate and amplify the inflammatory response (Refs Reference Pétrilli75, Reference Buhimschi76).
Immunity and coagulation
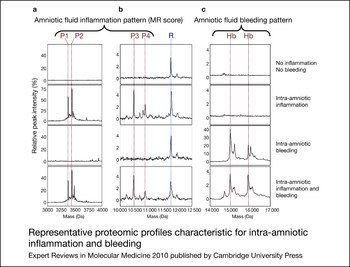
The innate and the adaptive immune systems display complementary inflammatory networks (Refs Reference Kimbrell and Beutler77, Reference Medzhitov78). During human pregnancy, the innate immune system not only resists infection, but also is poised at the crossroads between inflammation and coagulation. Proteomic studies demonstrated that the process of decidual bleeding could be attended by a robust intra-amniotic inflammatory process in the absence of infectious triggers (Fig. 3) (Ref. Reference Buhimschi80). Coagulation proteases and free haemoglobin chains control different modules of the innate immunity and a feed-forward mechanism reinforces a sterile inflammatory process (Refs Reference Norman12, Reference Mackman39, Reference Cakmak81, Reference Buhimschi and Buhimschi82, Reference Lockwood83). Strategically positioned at the maternal–fetal interface and cervical mucosa, toll-like receptors (TLRs) are major operative agents of the innate immune response against infection (Refs Reference Krikun84, Reference Koga and Mor85, Reference Buhimschi86). Moreover, recent reports suggest that activation of TLRs also contributes to the inflammatory response mediated by the endogenous release of HMGB-1 and activation of the coagulation cascade during placental abruption (Refs Reference van Zoelen87, Reference Cohen88).
Representative proteomic profiles characteristic for intra-amniotic inflammation and bleeding. Three hypervariable areas of representative surface-enhanced laser desorption ionisation time-of-flight tracings of amniotic fluid from women admitted for preterm birth are shown: (a) 3–4 kDa, (b) 10–12.5 kDa and (c) 14–17 kDa. These areas contain proteomic patterns characteristic of intra-amniotic inflammation (MR score composed of four protein biomarkers – P1, P2, P3 and P4) (Ref. Reference Buhimschi, Christner and Buhimschi79), intra-amniotic bleeding (Hb chains) or both (bottom tracings). The x-axis of the tracings represents the molecular mass in daltons; the y-axis represents the normalised peak intensity. R denotes a reference protein peak present in all fluid samples, which corresponds to a fragment of beta-2 microglobulin (originally published in Ref. Reference Buhimschi80; reproduction permitted under Creative Commons Attribution License). Abbreviations: Hb, haemoglobin; MR, mass-restricted; P1, neutrophil defensin-2; P2, neutrophil defensin-1; P3, calgranulin C; and P4, calgranulin A.

Questions about physiological and pathological engagement of the human immune system during pregnancy represent fundamental challenges for reproductive scientists. The literature on the subject is vast. We aim to illustrate the richness of the topic and set the stage for the argument that understanding the mechanisms responsible for the crosstalk between coagulation and inflammation is one critical step towards a better appreciation of the role played by these interacting pathways in abruption-induced PTB.
Significance of the crosstalk between inflammation and coagulation in the mechanism of abruption
Placental abruption can be viewed as a ‘binary’ event in which molecular signals involved in decidual bleeding arise as a consequence of either inflammation or aberrant coagulation (Refs Reference Buhimschi8, Reference Lockwood and Kuczynski9, Reference Challis11). Evidence in support of this theory is derived from studies demonstrating that inflammatory reactions occurring in the setting of infection activate the coagulation system (Ref. Reference Nath24). Aberrant bleeding and haemostasis are more common in the setting of histological chorioamnionitis (Refs Reference Elsasser15, Reference Salafia20, Reference Nath24, Reference Ananth89), suggesting a model in which proinflammatory cytokines (i.e. IL-1β and IL-6) act on the endothelium of decidual blood vessels to increase the expression of leukocyte interactive proteins [P-selectin, E-selectin, VCAM (vascular cell adhesion protein) and ICAM-1 (intercellular adhesion molecule 1)] (Refs Reference Levi and van der Poll32, Reference Arcuri63). In turn, this phenomenon leads to neutrophil infiltration and decidual vascular damage with perivascular leakage of plasma proteins and coagulation factors. The coagulation pathway is activated when circulating FVII gains access to perivascular adventitial TF and generates thrombin (Fig. 1) (Ref. Reference Lockwood90). Therefore, inflammation shifts the decidual haemostatic mechanisms in favour of thrombosis (Ref. Reference Esmon91). In an animal model of endotoxin-induced sepsis, infusion of low thrombin levels protected against lethality (Ref. Reference Taylor92), signifying that this protection was provided by an early anticoagulant and fibrinolytic response to endotoxin. Applying the same process to the decidua, it can be projected that low thrombin levels, generated in the early phase of inflammation-induced abruption, are beneficial. This phenomenon helps to explain the high frequency of histopathological lesions suggestive of chronic decidual bleeding in the absence of clinical manifestations of the disease (Refs Reference Salafia20, Reference Nath24).
The physiological mechanisms that enable decidual pro- or anticoagulant and fibrinolytic systems to prevent cataclysmic haemorrhage during pregnancy have been reviewed in detail (Ref. Reference Lockwood21). Our group previously proposed that when the process of decidual thrombin activation overwhelms the physiological anticoagulant and fibrinolytic response, the abruption process becomes systemic and clinically evident (Ref. Reference Rosen93). We demonstrated for the first time that increased thrombin activation, as assessed by circulating maternal plasma thrombin–antithrombin complexes, predicted adverse pregnancy outcomes related to prematurity (Ref. Reference Rosen93).
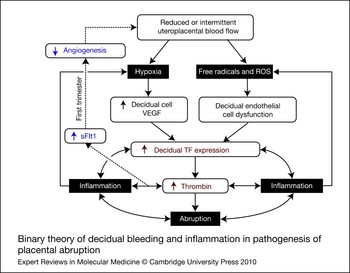
Consistent with the ‘binary’ model proposed above during placental abruption, aberrant coagulation is implicated in triggering decidual inflammation (Refs Reference Nath24, Reference Arias25, Reference Esmon91). A growing body of research suggests that maternal hypertensive disorders, trauma, idiopathic intrauterine growth restriction and possibly thrombophilias are risk factors for placental abruption (Ref. Reference Krikun, Lockwood and Paidas40). These conditions are generally associated with reduced uteroplacental blood flow, hypoxia and excess production of reactive oxygen species (ROS). Hypoxia amplifies this vicious feed-forward cycle by upregulating the expression of proangiogenic proteins and inducing decidual vasculopathy, endothelial cell dysfunction, thrombin generation, thrombosis and inflammation (Fig. 4) (Refs Reference Buhimschi71, Reference Fiedler and Augustin94). Evidence in support of the ‘binary’ model of abruption was provided by experimental results demonstrating that thrombin promotes decidual vasculogenesis and angiogenesis (Refs Reference Krikun95, Reference Lockwood96). Specifically, treatment of primary microvascular endometrial endothelial cells with VEGF or thrombin-induced TF mRNA and protein expression (Ref. Reference Lockwood96) and enhanced mRNA levels of several inflammatory cytokines, with the greatest effect seen on macrophage inflammatory protein-3α (MIP3α). Furthermore, in cultured first-trimester decidual cells, thrombin, but not IL-1β or TNF-α, enhanced the mRNA and protein levels of the antiangiogenic factor soluble fms-like tyrosine kinase-1 (sFlt-1) (Ref. Reference Lockwood96), with no effects on the expression of the angiogenic VEGF or placental growth factor. This thrombin augmentation of sFlt-1 expression in first-trimester decidual cells did not extend to cultured term decidual cells (Ref. Reference Lockwood96). These results indicate that thrombin acts on decidual cells to create an imbalance at the implantation site that interferes with angiogenesis-dependent remodelling of decidual vessels and in subsets of abruption cases (Refs Reference Lockwood90, Reference Goldman-Wohl and Yagel97).
Binary theory of decidual bleeding and inflammation in pathogenesis of placental abruption. A reduced or intermittent uteroplacental blood flow causes focal decidual hypoxia and free radicals and ROS (through reperfusion injury). Hypoxia induces the expression of decidual VEGF. This angiogenic factor acts directly on decidual endothelial cells to enhance permeability and degrade the vascular wall through MMP-2 generation. This leads to haemorrhage and aberrant endothelial expression of TF to generate additional thrombin that further induces TF expression and uteroplacental thromboses, which exacerbate reduced blood flow. Free radicals and ROS induce endothelial cell injury, which allows perivascular leakage of coagulation factors, including factor VIIa, which then comes in contact with TF, activating the extrinsic coagulation pathway. The resulting thrombin further induces TF expression as well as expression of inflammatory cytokines, leading to inflammation in the absence of a microbial attack. Abbreviations: MMP, matrix metalloproteinase; ROS, reactive oxygen species; sFlt-1: tyrosine kinase-1; TF, tissue factor; VEGF, vascular endothelium growth factor.

Thrombin altered the expression of the angiopoietin (Ang) proteins in primary cultures of human endometrial cells derived from predecidualised endometrium (Ref. Reference Krikun98). Specifically, thrombin markedly reduced angiogenic Ang-1 mRNA and protein expression in human endometrial stromal cells, while minimally decreasing the production of Ang-2 protein in human endometrial endothelial cells. These results indicate that thrombin generated from aberrant activation of haemostasis can alter decidual vascular angiogenesis, vascular integrity and homeostasis. This creates a feed-forward loop, resulting in additional thrombin formation, weakened vasculature and exacerbation of haemorrhage. Thrombin induced by increased expression of TF might act as an autocrine or paracrine enhancer of aberrant vascular remodelling, promoting uteroplacental thromboses and inducing inflammation that causes decidual bleeding in a gestational-age-dependent fashion (Refs Reference Krikun95, Reference Lockwood96). On the basis of the above data, we argue that the TF–thrombin unit is central to the crosstalk between inflammation and coagulation in abruption.
Genetic risk factors for placental abruption
A complex genetic predisposition to PTB is generally accepted (Refs Reference Chaudhari99, Reference Nesin100); however, recent epidemiological studies suggest that genetic risk factors also have an important role in the pathogenesis of abruption (Refs Reference Rasmussen, Irgens and Dalaker101, Reference Peltier102, Reference Rasmussen and Irgens103). Previous studies show that the recurrence risk of placental abruption in the same woman is higher compared with levels in the general population and that thromboembolic diseases aggregate within female relatives of women with placental abruption (Ref. Reference Kinzler104). The observation that thrombophilia has a high prevalence among women with placental abruption supports the idea of a genetic background for this condition (Refs Reference Kinzler104, Reference van der Molen105, Reference Procházka106). However, there are conflicting genetic studies involving candidate gene polymorphisms (Refs Reference Jaaskelainen107, Reference Ananth108). A recent meta-analysis identified the most frequent gene polymorphisms associated with placental abruption (Ref. Reference Zdoukopoulos and Zintzaras109). A positive association was found for coagulation factor FV Arg506Gln (OR: 3.4; 95% CI: 1.4–8.3) and for prothrombin G20210A (OR: 6.7; 95% CI: 3.2–13] polymorphisms (Ref. Reference Zdoukopoulos and Zintzaras109), which was confirmed in a large prospective cohort study of nulliparous women (OR: 12.15; 95% CI: 2.45–60.39) (Ref. Reference Said110). However, a recent study argues against this association (Ref. Reference Silver111). The association between fetal thrombophilic mutations (FV Leiden and prothrombin G20210A) and placental abruption suggested a possible fetal genotypic contribution to the occurrence of this obstetrical complication (Ref. Reference Anteby112). Abnormal placental and decidual vasculogenesis (placental infarcts, avascular terminal villi and villi infarcts) is the proposed mechanism (Ref. Reference Redline and Pappin113). Larger prospective cohort studies that include gene–gene and gene–environment interactions are needed to increase our understanding of the contribution of genetic factors to complex diseases such as placental abruption.
Progestins and molecular mechanisms leading to placental abruption
Progesterone is essential for pregnancy maintenance from implantation to parturition (Ref. Reference Smith114). The role of the progesterone ‘block’ (Ref. Reference Csapo115) in promoting uterine quiescence, controlling myometrial gap junctions and cervical ripening, and preventing PTB has been extensively analysed (Refs Reference Tita and Rouse116, Reference Mesiano and Welsh117). The decidua is a direct target for progesterone actions during human pregnancy. Several biological effects initiated by progesterone are the consequence of a variety of genomic and nongenomic mechanisms of action (Ref. Reference Merlino118). These effects are facilitated by PR isoforms (PRA and PRB). Several molecular mechanisms, including target gene transcription and cascade signalling pathways, are involved.
Role of progesterone in modulating decidual fibrinolysis and its inhibitors
Decidual haemostasis requires the concerted actions of several proteases, with plasminogen-derived plasmin having an initiating role (Ref. Reference Lockwood21). Plasminogen is a circulating zymogen that is converted to the active enzyme plasmin by cleavage at a specific amino acid bond mediated by either urokinase plasminogen activator (uPA) or tissue-type plasminogen activator (tPA). Normally, the actions of uPA and tPA are held in check by plasminogen activator inhibitor-1 (PAI-1), the fast inhibitor of the primary fibrinolytic agent, tPA (Ref. Reference Schatz and Lockwood119), and placental trophoblast-derived PAI-2. Interactions between progesterone and the PA–plasmin system have key roles in the local regulation of decidual haemostasis (Ref. Reference Lockwood21). An in vitro model of decidualisation using primary stromal cells from predecidualised human endometrium suggests that first-trimester decidua might express two crucial modulators of haemostasis, TF and PAI-1 (Ref. Reference Krikun120). In these cultured stromal cells, progestins such as medroxyprogesterone acetate (MPA) enhanced mRNA and protein levels of TF (Ref. Reference Krikun120) as well as PAI-1 (Ref. Reference Krikun121) and uPA, but not tPA (Ref. Reference Norwitz122). The progestin effects were blocked by the antiprogesterone RU486 (Ref. Reference Lockwood123). Consistent with maintenance of decidualisation during gestation, it was observed that progestins also enhanced TF and PAI-1 expression in cultured term decidual cells (Refs Reference Lockwood46, Reference Norwitz122).
Role of progesterone in the expression of decidual MMP and MMP inhibitor
Decidualisation is associated with stromal- or decidual-cell-mediated turnover of the extracellular matrix (ECM) mediated by interactions between uPA and MMPs (Refs Reference Lockwood124, Reference Schatz125). In primary cultures of leukocyte-free term decidual cells, MPA inhibited mRNA and protein levels as well as the enzymatic activity of interstitial collagenase (MMP-1) and stromelysin-1 (MMP-3) (reviewed in Ref. Reference Schatz125). Steroid withdrawal reversed this inhibition, with RU486 eliciting greater reversal. MMP-1 specifically targets fibrillar collagens whereas MMP-3 degrades several ECM proteins and activates the secreted zymogenic form of other MMPs such as pro-MMP-1 Therefore, these in vitro observations suggest that progesterone withdrawal elicits a decidual-cell-expressed ECM-degrading cascade of the decidua and fetal membranes that promotes bleeding and premature separation of the placenta.
Role of progesterone in modulating the expression of decidual cytokines
Coincident with activation of the coagulation cascade, local decidual injury causes the release of cytokines that act as autocrine or paracrine effectors of immunomodulatory, angiogenic and proliferative activities. Specifically, a causal role has been proposed for TNF-α, IL-1β, IL-6, IL-8 and IL-11 in PTB (Ref. Reference Christiaens126). A better understanding of the genesis of abruption-induced inflammation was provided by exploring the role of progesterone in modulating the expression of IL-1β and IL-11 in human term decidual cells (Ref. Reference Cakmak81). The focus on IL-11 was prompted by its known exertion of complex anti-inflammatory effects such as inhibition of endometrial TNF-α production and attenuation of IL-1β, TNF-α, IL-12 and NO production in activated macrophages (Ref. Reference Trepicchio127). Additionally, IL-11 possesses proinflammatory and uterine contraction properties by inducing prostaglandin secretion. Immunohistochemical staining of decidual sections indicated that PTB is associated with significantly enhanced decidual cell IL-11 expression. In term decidual cell cultures, thrombin and IL-1β each augmented IL-11 expression, whereas co-incubation with a progestin significantly blunted the upregulation of IL-11 expression elicited by both agents. Taken together, the results of studies presented above help to account for the role of progesterone in maintaining haemostasis throughout pregnancy by inhibiting the general proteolytic and inflammatory activity at the maternal–fetal interface.
TF and thrombin as regulators of molecular mechanisms leading to placental abruption
A key part of the ‘binary’ model (Fig. 4) of abruption-associated PTB is the evidence that TF-induced thrombin is a critical mediator of the crosstalk between coagulation, angiogenesis and inflammation. This section focuses on other mechanisms by which TF and thrombin might mediate placental abruption and PTB.
TF, thrombin and MMP activity in fetal membranes and decidua
Key to understanding the relationship between decidual bleeding and activation of amniochorion MMPs is the observation that in vivo activation of the thrombin system and histological haemorrhage are frequent complications during preterm premature rupture of the fetal membranes (PPROM) (Refs Reference Salafia20, Reference Rosen93). PPROM is one of the leading risk factors for PTB (Ref. Reference Anum128). Although anatomically part of the gravid uterus, the amniochorion membrane can be viewed as a separate, complex and heterogeneous organ because it undergoes molecular, enzymatic and biomechanical transformations different from those of the cervix and myometrium (Refs Reference Mendelson6, Reference Norman12). Many risk factors for PPROM have been identified (Refs Reference Lockwood and Kuczynski9, Reference Parry and Strauss129). However, irrespective of the cause, the final unifying pathway is weakness of the amniochorion that allows for rupture.
The fibrillar collagens (types I, III and V) provide tensile strength to the amnion (Ref. Reference Parry and Strauss129). The strength of the fetal membranes reflects a balance between synthesis and protease-induced degradation of ECM components. The molecular mechanisms responsible for the latter involve tight regulation by MMP-1, MMP-2, MMP-3 and MMP-9 and the tissue inhibitors of MMPs (TIMP-1 and TIMP-2) (Ref. Reference Parry and Strauss129). In vitro, thrombin targets and enhances the expression of MMP-1, MMP-3 and MMP-9 in term fetal membranes (Refs Reference Lockwood83, Reference Rosen130, Reference Stephenson131). Progesterone partially reverses the process. Interestingly, thrombin augments expression of PAI-1 but not uPA or tPA, as was recently shown (Ref. Reference Norwitz122). This effect was abrogated by hirudin. Collectively, these results suggest that thrombin exercises its stimulatory proteolytic effect by targeting MMPs directly and not by stimulating the expression of plasminogen system activators.
A marked decidual infiltrate of neutrophils, which are a rich source of ECM-degrading proteases, is associated with abruption-induced PPROM in the presence or absence of infection (Refs Reference Salafia20, Reference Nath24). Moreover, as previously shown, thrombin enhances the expression of IL-8 and other neutrophil chemoattractant and -activating chemokines in term decidual cell monolayers (Ref. Reference Lockwood83). Thus, it is reasonable to propose that during abruption, thrombin generated from decidual-cell-expressed TF can promote PPROM either directly, by enhanced expression of MMPs, or indirectly, by augmenting decidual expressed neutrophil chemoattractants and activators.
The mechanism of PPROM includes tissue damage secondary to both hypoxia and inflammation, as well as an increased state of oxidative stress (Refs Reference Krikun95, Reference Buhimschi132). For example, MMP activity in human fetal membranes is reduction–oxidation (redox) regulated (Ref. Reference Buhimschi132). MMP-9 activity was directly increased by the superoxide anion, a byproduct of macrophages and neutrophils, which are abundantly present in both the amniochorion and decidua in the setting of decidual bleeding. N-acetylcysteine (a glutathione precursor and direct antioxidant) dramatically decreased the amniochorionic MMP-9 activity.
Research in progress and outstanding research questions
The events that initiate activation of the immune and coagulation systems in the setting of abruption-induced PTB are incompletely understood. Unravelling the complexity of the clinical management of acute and chronic placental abruption requires elucidation of the highly controlled and synchronised biochemical circuits that exist in the decidua and amniochorionic membranes. For many years, research in decidual bleeding has concentrated on identifying, localising and evaluating the regulation of individual factors. This approach ignores the reality that abruption involves complex molecular protein-to-protein interactions that function in interconnected cellular networks regulated by specific receptors. A shift in mindset is thus required. The discovery of key biomarkers that can specifically determine whether the inflammatory and coagulation networks are silent or activated in women at risk for decidual bleeding is crucial. This approach is consistent with the idea of taking an individualised medicine approach aimed at identifying patients who might benefit from targeted interventions rather than a ‘one-size-fits-all’ therapy. The challenge is to use our knowledge to develop pharmacological agents that can specifically inhibit the proteolytic activity of thrombin, boost the anti-inflammatory activity of progesterone or lower the heightened state of oxidative stress at the maternal–fetal interface.
Acknowledgements and funding
We are indebted to the nurses, residents and fellows from the Departments of Obstetrics, Gynecology and Reproductive Sciences of Yale University, Mount Sinai Medical Center – New York, New York University School of Medicine and University of Maryland – Baltimore. This work was supported by National Institutes of Health grants RO1 HD 29540 (C.J.L.), HL 33937 (C.J.L.) and HD 047321 (I.A.B.), March of Dimes grant 21-FY05-1249 (C.J.L.), and March of Dimes Basil O'Connor Award (I.A.B.). We thank the reviewers for their helpful suggestions.