The exterior body plan of vertebrates is essentially symmetric along its medial–lateral axis, whereas the formation of internal organs displays numerous left–right differences. The left–right axis is the third body axis to form, and alteration of the normal pattern of asymmetry can manifest either in mirror-image reversal of all asymmetrical organs or randomised placement of organs.Reference Casey1 The heart is the first organ to develop asymmetrically, and cardiac morphogenesis is sensitive to aberrations in left–right positional information.Reference Kathiriya and Srivastava2 Heterotaxy syndrome is often associated with cardiac malformations that cause significant morbidity and mortality. In heterotaxy, the heart is normally patterned and formed in relation to the anterior–posterior and dorsal–ventral axis, indicating that anterior–posterior and dorsal–ventral specification can act independently from left–right specification. Patients often have malposition of the great arteries, systemic or pulmonary venous return abnormalities, and abnormal septation such as atrioventricular septal defects.
As a clinically and genetically heterogeneous disorder, heterotaxy syndrome can be associated with chromosomal abnormalities such as balanced translocations,Reference Kato, Yamada and Niikawa3, Reference Fritz, Kunz and Knudsen4 microdeletions or duplications,Reference Schinzel, Hanson, Pagon, Hoehn and Smith5 single-gene mutations, epigenetic factors, or environment teratogens.Reference Kuehl and Loffredo6 Monogenetic causes of heterotaxy syndrome segregate as autosomal recessive,Reference Chen and Monteleone7 autosomal dominant,Reference Alonso, Pierpont and Radtke8, Reference Casey, Cuneo and Vitali9 and X-linked recessive disorders.Reference Casey, Devoto, Jones and Ballabio10 Highly conserved genetic pathways control the determination of the left–right axisReference Fujinaga11, Reference Burdine and Schier12 across species from xenopus,Reference Hyatt, Lohr and Yost13 zebrafish,Reference Essner, Amack, Nyholm, Harris and Yost14 chickReference Levin, Johnson, Stern, Kuehn and Tabin15 to mouse.Reference Nonaka, Tanaka and Okada16, Reference Lowe, Supp and Sampath17 It is suggested that the initial breaking of the left–right asymmetry occurs in the node, and the nodal flow generated by the monocilia in the node leads to the establishment of morphogen gradient, including Nodal, Lefty, and Acvr2b, in either the left or right side of the body to pattern the internal organs. Zinc finger protein of the cerebellum 3 – ZIC3 – is a zinc finger transcription factor. Mutations of ZIC3 cause X-linked heterotaxy – HTX1 – and isolated congenital cardiac disease.Reference Mathias, Lacro and Jones18–Reference Chhin, Hatayama and Bozon21 Zic3 knockout mice recapitulate human HTX1, and 50% of Zic3 null embryos have randomised internal organs and abnormal cardiac looping.Reference Purandare, Ware and Kwan22 Mouse homologues of left–right determination factor 2 – LEFTYA, homologue of mouse Lefty-2 – and left–right determination factor 1 – LEFTYB, homologue of mouse Lefty-1 – mediate Nodal signalling from the node to the lateral plate mesoderm. A null mutation of Lefty-2 in mice shows left isomerism.Reference Meno, Takeuchi and Sakuma23 Mutations of LEFTYA have been identified in heterotaxy patients as well.Reference Kosaki, Bassi and Kosaki24 Activin receptor IIB – Acvr2b – is expressed asymmetrically along the left–right axis in mouse and chick. A null mutation of Acvr2b in mice results in situs ambiguous, atrial septal defect, ventricular septal defect, and splenic hypoplasia.Reference Oh and Li25 On the basis of the murine phenotype, 112 sporadic and 14 familial cases of left–right axis malformation were analysed for ACVR2B mutations, and two missense mutations were identified, leading to a conclusion that ACVR2B mutations are rare causes of human left–right axis malformation.Reference Kosaki, Gebbia and Kosaki26 Cryptic – CFC1 – belongs to the epidermal growth factor-CFC1 family and encodes extracellular protein that plays a key role in intercellular signalling pathways. CFC1 is expressed around the node and is later found in the intermediate and lateral plate mesoderm during gastrulation in mouse embryo.Reference Shen, Wang and Leder27 Homozygous Cryptic knockout mice presented laterality defects and complex cardiac malformations. The phenotypes resemble those of mice lacking the type IIB activin receptor or the homeobox-containing factor Pitx2.Reference Gaio, Schweickert and Fischer28CFC1 mutations and missense variants have been identified in patients with heterotaxy syndrome associated with congenital cardiac diseases.Reference Bamford, Roessler and Burdine29–Reference Selamet Tierney, Marans, Rutkin and Chung32
To expand the human genetic studies of heterotaxy syndrome with associated congenital cardiac disease, we screened 47 patients for mutations in ZIC3, LEFTYA, ACVR2B, and CFC1 to determine the frequency of mutations, mutation spectrum, and penetrance of the identified mutations, in order to provide data to guide the development of future genetic testing for heterotaxy syndrome.
Patient and methods
Clinical materials
The study included foetuses and children diagnosed with heterotaxy syndrome defined as segmental discordances of the thoraco-abdominal organs along the left–right axis. All patients seen at the Columbia University Medical Center were offered study entry. The study was approved by the Institutional Review Board at Columbia University Medical Center. Informed consent was obtained from parents or the patients, depending on the age of the patient. Among them, 46 patients had normal karyotypes, whereas one patient had an extra X chromosome – 47 patients, XXX. Genomic DNA was extracted from blood, tissue, or amniocytes from each patient using Puregene reagents (Gentra Systems Inc., Minneapolis, Minnesota, United States of America). Clinical data about the type of congenital cardiac disease and extracardiac phenotype were extracted from the medical record. Clinical cardiac information was reviewed by a single cardiologist (SST).
Genotyping genetic variations using PCR amplification
Primers were designed to amplify all coding regions and at least 20 basepairs of adjacent intronic sequence to capture the splice junctions for the four genes ZIC3, LEFTYA, ACVR2B, and CFC1. Primer sequences are available upon request. In brief, 20 nanograms of genomic DNA from each patient was amplified in a 20-microlitre volume containing 1 × PCR buffer, 40 nanograms of each oligonucleotide primers, 200-micromolar deoxyribonucleotide triphosphate, and 1.2 unit Taq polymerase (Promega, Madison, Wisconsin, United States of America). PCR products were purified using ExoSAP-It kit (USB Scientific, Cleveland, Ohio, United States of America) and sequenced by Sanger dideoxy sequencing on an ABI 3730xl genetic analyzer (ABI, Torrance, California, United States of America) according to the manufacturer's instructions using one of the amplification primers. Genetic variants were confirmed on a second polymerase chain reaction reaction with bi-directional sequencing, and all available family members were sequenced. Sequences were analysed with Sequencher software (Gene Codes, Ann Arbor, Michigan, United States of America). Genetic variants were compared with all reported genetic variants in the literature, in the single nucleotide polymorphism database, at www.ncbi.nlm.nih.gov/snp and at www.genome.ucsc.edu. All novel genetic variants were independently confirmed using restriction digests. Confirmed novel genetic variants were then genotyped in 100 unrelated normal individuals of the same ethnicity without congenital cardiac disease.
Results
Clinical data
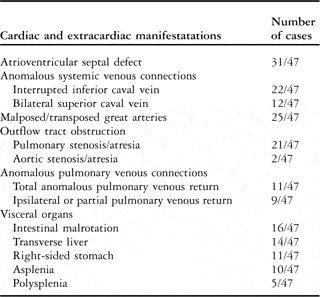
The study consisted of 23 male and 24 female patients. The ethnicity of the patients was 45% – 21 of 47 – Caucasian; 23% – 11 of 47 – Hispanic; 20% – 9 of 47 – African American; 6% – 3 of 47 Asian and Southeast Asian; and 6% – 3 of 47 – other. There were seven foetal cases with prenatal terminations, 44 sporadic cases, and 3 familial cases. Associated congenital cardiac defects included atrioventricular septal defect in 31 of the 47 patients, systemic venous anomalies in 34 of the 47 patients, transposed or malposed great arteries in 25 of the 47 patients, outflow tract obstruction in 23 of the 47 patients, and pulmonary venous anomalies in 20 of the 47 patients (Supplementary Table 1). Table 1 lists all the cardiac and extracardiac manifestations of the patients in the series.
Cardiac phenotypes of heterotaxy patients.

Mutation screening
ZIC3
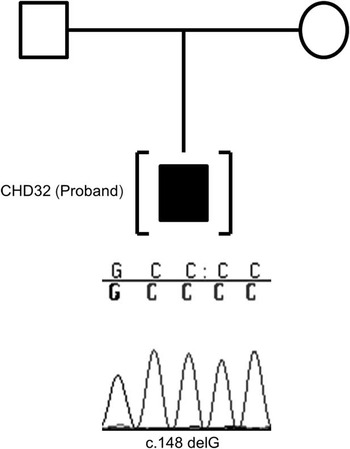
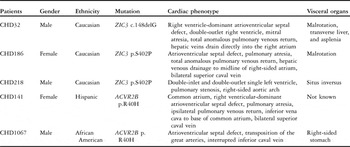
Sequencing of ZIC3 showed two novel genetic variants. CHD32 was a male patient with a c.148delG, resulting in a frameshift and putative truncated protein p.A50PfsX8 (Fig 1). CHD32 had right ventricle-dominant atrioventricular septal defect, double-outlet right ventricle, mitral atresia, and total anomalous pulmonary venous return (Table 2). The hepatic veins connected directly into the right atrium. Extracardiac manifestations included malrotation, transverse liver, and asplenia. The patient was adopted, and hence no family history or parental samples were available.
Mutation of ZIC3 exon 1 in CHD32. Sequence of ZIC3 c.148delG in proband was shown; brackets symbolise adoption.

Patients with ZIC3 and ACVR2B mutations.

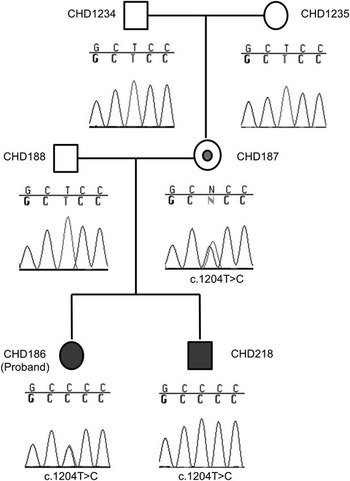
Analysis of ZIC3 in CHD186 identified a heterozygous c.1204T > C transversion, which results in substitution of p.S402P (Fig 2). The proband is a female patient with atrioventricular septal defect, pulmonary atresia, and total anomalous pulmonary venous return. She had bilateral superior caval vein with hepatic veins connecting to the midline of right-sided atrium. She had abdominal malrotation (Table 2).
ZIC3 c.1204T > C in CHD186 and the family. Pedigree indicating that the mother (CHD187) is a carrier and the two children (CHD186 and CHD218) are affected. Electropherograms of each family member show that CHD187 (unaffected mother) and CHD186 (proband, female) are heterozygous for c.1204T > C, whereas CHD218 (affected male sibling) carries the hemizygous c.1204T > C transversion, resulting in a p.S402P missense mutation. The father (CHD188) and maternal parents (CHD1234 and CHD1235) are normal; the point (CHD187) denotes carrier status.

The brother of CHD186 – CHD218 – also had the c.1204T > C transversion in ZIC3 and presented with complex cardiac disease including double-inlet and double-outlet single left ventricle, pulmonary stenosis, and a right-sided aortic arch. He had abdominal situs inversus and midline bony malformations including hypoplasia of the posterior elements of C1; rotational scoliosis of the upper cervical spine involving C2 and C3; fusion of multiple vertebral bodies including C2–C3; and two lower cervical vertebral bodies.
Analysis of the parents revealed that the mother is heterozygous for the c.1204T > C variant, whereas the father is normal, and the mother is clinically unaffected. Owing to the fact that this is X-linked recessive heterotaxy, we performed X chromosome inactivation assay and revealed that the mother had skewed X inactivation, although there was random inactivation of X chromosome in the proband (data not shown). Further studies showed that the proband's maternal grandparents do not carry the c.1204T > C variant, which indicates that the amino acid substitution p.S402P in ZIC3 was de novo in the proband's mother (Fig 2). The amino acid serine at position 402 lies within the fifth zinc finger domain and is highly conserved among human, mouse, and zebrafish (Fig 3).
Cross-species comparison of ZIC3 amino acid and locations of putative mutations. Solid rectangles in blue indicate the five C2H2 zinc finger domains. The amino acid positions for each mutation are boxed in red and types of mutations are labelled above each box. The c.148delG mutation causes a frameshift and is predicted to form truncated protein with only 57 amino acids. A missense mutation S402P was detected in the fifth zinc finger domain. Previously reported mutations are boxed in yellow and the amino acid or nucleotide positions are labelled above.

ACVR2B
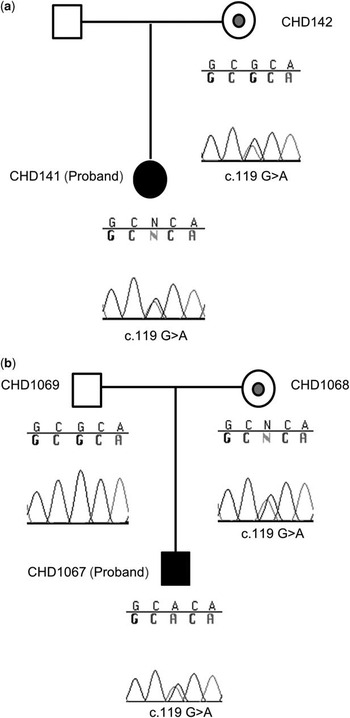
Sequencing of ACVR2B identified two patients, CHD141 and CHD1067, with an identical heterozygous c.119G > A variant (p.R40 H; Fig 4). This variant has previously been reported to be a pathogenic mutation.Reference Kosaki, Bassi and Kosaki24, Reference Kosaki, Gebbia and Kosaki26 CHD141 had right ventricle-dominant atrioventricular septal defect, pulmonary atresia, ipsilateral pulmonary venous return, inferior caval vein connecting to the base of common atrium, and bilateral superior caval vein (Table 2). CHD1067 was a foetus with atrioventricular septal defect, transposition of the great arteries, interrupted inferior vena cava, and a right-sided stomach (Table 2). The unaffected mothers of both patients carried the same heterozygous c.119G > A (p.R40 H).
An identical mutation of ACVR2B exon 2 in the two independent families. (Pedigree and sequencing results of CHD141 and the family were shown in panel a. The same mutation was identified in an unrelated family and the pedigree and sequencing results were shown in panel b. In both families, the unaffected mothers (CHD142 and CHD1068) are heterozygous for the c.119G > A transversion carried by the affected probands (CHD141 and CHD1067). The c.119G > A transversion results in a p.R40H missense mutation; the dot in the center of the pedigree symbol denotes carrier status.

Controls
The novel variants in ZIC3 were genotyped in 100 ethnically matched normal controls, and were not identified in any of the normal subjects. The mutation R40 H in ACVR2B was genotyped in 100 randomly selected individuals in the previous report and has not been identified in normal population.Reference Kosaki, Bassi and Kosaki24, Reference Kosaki, Gebbia and Kosaki26
Sequencing of CFC1 was previously performed on some of these patients (n = 25)Reference Selamet Tierney, Marans, Rutkin and Chung32 and completed in the remaining 22 pattients in this cohort. No novel mutations were identified. No mutations were identified in LEFTYA.
Discussion
Sequencing of coding regions of ZIC3, LEFTYA, ACVR2B, and CFC1 in 47 heterotaxy patients with associated cardiovascular anomalies identified two novel genetic changes in two patients for ZIC3 and a previously reported mutation in ACVR2B in two unrelated patients for a total yield of 4 of 47 positive cases (8.5%). In the family with the S402P variant in ZIC3, S402P segregated with heterotaxy within the family and was associated with skewed X inactivation in the carrier mother. The mother's mutation was de novo. These data suggested that the S402P variant is pathogenic. All of the novel genetic variants we report are highly conserved across species, are located in functionally important domains of the proteins (Fig 3), and none of the variants were present in 100 randomly selected normal individuals. These data suggested that the two novel variants in ZIC3 and the one previously reported R40 H variant in ACVR2B are likely to be pathogenic mutations.
ZIC3 functions in the early stages of embryonic development to regulate left–right axis formation. ZIC3 p.S402 is located in the alpha-helical structure of zinc finger 5 for DNA binding. The amino acid is highly conserved among species, as well as among Zic/Gli/Glis zinc finger protein superfamily,Reference Sakai-Kato, Ishiguro, Mikoshiba, Aruga and Utsunomiya-Tate33 suggesting that this amino acid maybe important for the ZIC3–DNA complex formation. ZIC3 has been reported to interact with GLI3 through GLI consensus binding site to regulate multiple aspects of neural and skeletal development.Reference Hatayama, Tomizawa and Sakai-Kato34, Reference Zhu, Zhou, Poole and Belmont35 It is speculated that S402P in ZIC3 may account for the skeletal anomalies in CHD218. CHD186 and CHD218 had different cardiac phenotypes and extracardiac manifestations that could be due to the hemizygous state of the male compared to the heterozygous female with one copy of the wild-type allele. CHD32 is a male patient who had a hemizygous c.148delG in ZIC3. This mutation is predicted to produce truncated protein p.A50PfsX8 without formation of Zinc finger domains. CHD32 had multiple complex cardiovascular abnormalities, and cardiac transplant was performed at 10 years of age. CHD32 also had extracardiac manifestations. To date, eleven nonsense, frameshift, and missense mutations in ZIC3 gene have been reported among 241 sporadic and familial heterotaxy cases, with 85% of mutations being maternally inherited, usually from unaffected mothers.Reference Ware, Peng and Zhu19 The ratio of clinically affected male to female patients with ZIC3 mutations is 2.5:1 and may be explained by skewed X inactivation.
The frequency of LEFTYA mutations in heterotaxy is low. Only one study identified two missense mutations among 126 patients to date.Reference Kosaki, Bassi and Kosaki24 In our study, no novel mutations were identified in our heterotaxy patients.
One study identified two missense mutations, p.V419I and p.R40 H in ACVR2B, in 112 sporadic and 14 familial cases.Reference Kosaki, Gebbia and Kosaki26 Our study identified the R40 H mutation in 2 of the 47 cases, both of whom inherited the mutation from an unaffected mother. R40 in ACVR2B is located in the region of extracellular domain within the region of ligand binding and is conserved across human, mouse, dog, and elephant.Reference Kosaki, Gebbia and Kosaki26 Although the patients who carry R40 H mutation in ACVR2B had distinct clinical presentations, all exhibited abnormal systemic venous return.
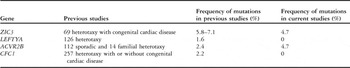
Single genes have been screened in cohorts of patients with heterotaxy, but our study is the most comprehensive genetic study that analysed ZIC3, LEFTYA, ACVR2B, and CFC1, as a panel in all heterotaxy patients with cardiac manifestations. The total yield for all four genes was 8.5%, that is, 4 of 47 cases. A comparison of the yield for each gene in previous and current studies is provided in Table 3. While this yield from these four genes is modest, it suggests that developing panels of genes to evaluate convergent phenotypes in congenital heart disease that occur in the context of inherited or sporadic diseases such as heterotaxy may be useful for diagnosis and evaluation. Our data also suggest that mutations in any one gene may account for a small percentage of cases and may be incompletely penetrant, making strategies of linkage analysis and association studies less powerful. Our study expands the mutation spectrum in heterotaxy and also suggests that additional genes are likely to be involved in the remaining 90% of cases for whom genetic changes were not identified, such as mutations in NODAL,Reference Zlotogora, Schimmel and Glaser36–Reference Mohapatra, Casey and Li38NKX2.5,Reference Watanabe, Benson, Yano, Akagi, Yoshino and Murray39, Reference Dentice, Cordeddu and Rosica40 and CRELD1.Reference Robinson, Morris and Goldmuntz41 Our study, as well as the results from previous reports,Reference Roessler, Ouspenskaia and Karkera42, Reference Roessler, Pei and Ouspenskaia43 suggests that genetic changes in more than one gene in the same pathway can converge to produce the same phenotype of heterotaxy with associated congenital cardiac disease. Patients without identified mutations will provide the substrate for identification of novel genes associated with heterotaxy using high throughput methods of genomic analysis.
Comparison of frequency of ZIC3, LEFTYA, ACVR2B, and CFC1 mutations across studies.

Acknowledgements
The authors thank the families and referring physicians for their generous contribution.