


Introduction
Currently, most health economists seem to agree that the economic costs associated with reduced or lost ability to work because of illness, called productivity losses or costs, should be included in the economic evaluation of health interventions (Herrero and Moreno-Ternero, Reference Herrero and Moreno-Ternero2009). However, the method of estimation is still a matter of debate. The most conventional approach to productivity costs valuation is based on the human capital method (HCM). The HCM equals these costs with the present discounted value of an ill person’s expected future gross wages over the period of working time lost because of the disease (Rice, Reference Rice1967). Koopmanschap and van Ineveld (Reference Koopmanschap and van Ineveld1992) have argued that this method overestimates the real losses of production to society, as it does not take account of the possibility that an ill person unable to work can be replaced by a previously unemployed individual when the economy is not at its full-employment rate. As an alternative to the HCM, Koopmanschap and colleagues (Koopmanschap and van Ineveld, Reference Koopmanschap and van Ineveld1992; Koopmanschap et al., Reference Koopmanschap, Rutten, van Ineveld and van Roijen1995) have elaborated the friction cost method (FCM). Under the FCM, productivity costs are defined as the losses of production borne by society during the transitional ‘friction’ period necessary to restore production to its level before the illness occurs plus the costs resulting from the recruitment and training of an unemployed person (Koopmanschap et al., Reference Koopmanschap, Rutten, van Ineveld and van Roijen1995). The FCM has gained in popularity in applied economic evaluation studies over the past decade. Numerous studies now provide a low and a high range value for productivity costs based on the FCM and HCM, respectively (Welte et al., Reference Welte, van den Dobbelsteen, Bos, de Melker, van Alphen, Spanjaard, Rumke and Postma2004; Oliva et al., Reference Oliva, Lobo, Lopez-Bastida, Zozaya and Romay2005; Oliva-Moreno et al., Reference Oliva-Moreno, Lopez-Bastida, Montejo-Gonzalez, Osuna-Guerrero and Duque-Gonzalez2009; Hanly et al., Reference Hanly, Timmons, Walsh and Sharp2012).
The choice between the HCM and FCM is still a controversial issue with regard to cost-effectiveness and cost-utility analyses (Krol et al., Reference Krol, Brouwer and Rutten2013). This article does not enter this debate. It rather addresses the much less discussed question of how the possibility of worker replacement assumed by the FCM can be dealt with in cost-benefit analysis (CBA). An important concern when dealing with productivity losses in the economic evaluation of health care programs is to avoid double counting, that is, including the same cost twice in the calculation (Drummond et al., Reference Drummond, Sculpher and Torrance2005). This issue is particularly at stake in CBA because of its use of measures of willingness-to-pay (WTP) to value health care benefits. Unlike measures of health outcomes such as Quality-Adjusted Life-Years (QALYs), the WTP estimates are supposed to encompass the consequences of health care beyond those concerning health-related quality of life, such as changes in income among others (Baker et al., Reference Baker, Currie and Donaldson2010). Johannesson (Reference Johannesson1996) showed that, when no replacement at work is assumed, in a publicly funded insurance system the effect of illness on social welfare can be estimated by adding the individual WTP to avoid a disease and the HCM estimates. The reasoning is that the WTP measures the impact of the disease on the utility of the ill individual, whereas the HCM accounts for the component of productivity costs that bears on other individuals in the society (Johannesson, Reference Johannesson1996).Footnote 1 Things are likely to be different when ill worker replacement takes place, as from a social welfare perspective, part of the loss the ill person experiences may be compensated for by gains made by other individuals (Koopmanschap and van Ineveld, Reference Koopmanschap and van Ineveld1992). In the literature so far, the possibility of ill worker replacement has mostly been discussed within the framework of cost-effectiveness/utility analyses where health benefits are valued in QALYs (Brouwer et al., Reference Brouwer, Koopmanschap and Rutten1997; Johannesson and Karlsson, Reference Johannesson and Karlsson1997; Koopmanschap et al., Reference Koopmanschap, Rutten, van Ineveld and van Roijen1997; Weinstein et al., Reference Weinstein, Siegel, Garber, Lipscomb, Luce, Manning and Torrance1997; Brouwer and Koopmanschap, Reference Brouwer and Koopmanschap2005). Given the increasing use of contingent valuation methods by health economists (Baker et al., Reference Baker, Currie and Donaldson2010), it also seems important to discuss this possibility in a CBA setting. In this article, the consequences of ill worker replacement on social welfare are thus investigated to determine how the measurement of WTP for health care interventions could be done so as to avoid double counting in cost-benefit analyses.
This paper makes three contributions. First, it provides the first formal analysis of the overall consequences of ill worker replacement from a social welfare perspective. This analysis characterizes the various transfers between individuals that operate as a result of worker replacement and the conditions under which they compensate each other at the social level. Second, drawing on this analysis, we highlight a problem of double counting in CBA of life-saving health care programs when productivity costs are valued according to the FCM. We show that this problem cannot be avoided with current methods of WTP measurement. Our third contribution is therefore to present and discuss two original solutions to address this problem. To the best of our knowledge, no satisfactory way to handle this double-counting issue has yet been proposed in the literature.
The paper is organized as follows. Section 2 outlines the welfarist framework with which, in section 3, we analyze the compensation mechanisms implied by ill worker replacement. Section 4 identifies a double-counting problem that arises specifically in the case of CBA of life-saving programs. In section 5, we suggest and discuss two original ways to solve this double-counting problem. Section 6 concludes.
Setting the framework
Suppose that social welfare is represented by a utilitarian function W (relation 1):
 $$W(U^{1} ,U^{2} ,...,U^{n} )=\mathop{\sum}\limits_{i=1}^n {U^{i} } $$
where U i indicates individual i’s lifetime utility in a society made up of n individuals. The function W assigns equal weight to the utility of each individual, that is, ∂W/∂U i=1 ∀i. In CBA, the utility functions U i are replaced by monetary estimates of WTP. Consequently, the unweighted sum of individual WTP represents changes in social welfare as defined by relation 1, provided that all individuals have the same marginal utility of income (Liljas and Lindgren, Reference Liljas and Lindgren.2001; Zweifel et al., Reference Zweifel, Breyer and Kifmann2009).
In addition, suppose that at each period t, an individual derives utility from his health status h t, his leisure time l t, the income he spends to consume private goods c t and from the public goods available G t. The lifetime utility U i of a representative individual i is given by the following relation:
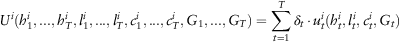 $$U^{i} (h_{1}^{i} ,...,h_{T}^{i} ,l_{1}^{i} ,...,l_{T}^{i} ,c_{1}^{i} ,...,c_{T}^{i} ,G_{1} ,...,G_{T} )=\mathop{\sum}\limits_{t=1}^T {\delta _{t} \,{\cdot }\,u_{t}^{i} (h_{t}^{i} ,l_{t}^{i} ,c_{t}^{i} ,G_{t} )} $$
where δ t is a time preference discount factor, T is the individual lifespan and u t is a one-period utility function. To simplify understanding, our subsequent analyses are based on a two-period model (before and after a health shock) and we assume no time preference.
We define the arguments of the instantaneous utility function as below (omitting the subscript):
- l i, c i, and G are thought to depend on i’s health as the health status of an individual determines his capacity to work, his income, the amount of social benefits he receives and the amount of taxes he pays. h i can be a vector of various dimensions that describe i’s health or health-related quality of life (hereafter we will use the two expressions interchangeably).
- We assume that there are no savings. Thus, the monetary value of consumption of private goods c i equals disposable income:
where s denotes the individual’s salary, b the unemployment benefits and d the disability allowances i receives. b and d are set to 0 if the individual works, s is set to 0 if he is unemployed or disabled. α (0<α<1) is a constant tax rate applied to all sources of income. $$c^{i} =\left( {1{\minus}\alpha } \right)\,{\cdot }\,\left( {s^{i} \left( {h^{i} } \right){\plus}b^{i} \left( {h^{i} } \right){\plus}d^{i} \left( {h^{i} } \right)} \right)$$
- The quantity of public goods available G is considered to be determined by the public budget P, which results from the contribution made by the n individuals who comprise society through taxes net of social transfers:
$$G=G\:\,(P)\,{\rm where}\,P=\mathop{\sum}\limits_{i=1}^n {\left( {\alpha \,{\cdot }\,s^{i} {\plus}(\alpha {\minus}1) \,{\cdot }\,(b^{i} {\plus}d^{i} )} \right)} $$
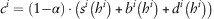
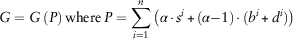
In our simple framework, the illness of a working person i induces a change in social welfare that can be decomposed into four effects:
1. A modification of h i as i’s health deteriorates either partially (case of morbidity) or totally (case of mortality).
2. A change in the quantity of i’s leisure time (l i) that increases if illness prevents the individual from working (time allocation is considered to be divided into work and leisure).
3. A reduction in i’s consumption of private goods (c i), as i’s health status determines his ability to work, his productivity level and hence his income.
4. An external effect. i’s illness may have an impact on the public budget P. Contributions received by the welfare system may decrease as i’s wage decreases and the amount of social benefits distributed increases if i receives disability allowances. This may lead to two final results: either (1) a decrease in the quantity of public goods G available if the public budget P is reduced or (2) a decrease in the private consumption of all individuals if the tax level is raised in a way that maintains P at its initial level, (i.e. before i became ill).Footnote 2 Regardless of the result, it reflects an impact of i’s disease on the society as a whole. This is referred to as the external part of the production costs because of illness (Johannesson, Reference Johannesson1996; Weinstein et al., Reference Weinstein, Siegel, Garber, Lipscomb, Luce, Manning and Torrance1997; Olsen and Richardson, Reference Olsen and Richardson1999).
Productivity costs are defined as the decrease in output resulting from illness (Liljas, Reference Liljas1998). They correspond to the addition of an individual and an external component (Weinstein et al., Reference Weinstein, Siegel, Garber, Lipscomb, Luce, Manning and Torrance1997). The individual component is the loss of income experienced by the ill or deceased person, that is, a decrease in c in our framework (effect 3). The external component reflects the productive output lost for the rest of the society as a result of the decrease in the taxes previously paid by the ill or deceased individual, that is, a decrease in the amount of public goods G in our framework (effect 4).
The consequences of worker replacement on social welfare
This section analyzes the consequences of ill worker replacement on social welfare. More specifically, we examine how transfers between individuals take place as a result of ill worker replacement. Our approach follows the line of reasoning of Brouwer and Koopmanschap (Reference Brouwer and Koopmanschap2005). These authors used a two-person two-period model to illustrate the consequences of worker replacement on the amount of leisure time available in the society. Our analysis extends this approach by also examining compensation mechanisms regarding consumption (effect 3) and public goods (effect 4), as defined in the previous section. This analysis of the impacts of ill worker replacement on social welfare is a prerequisite to determine how WTP measures can be estimated so as to avoid double counting in CBA.
Consider two individuals A and B in a society with n individuals. In a first period, A is working, whereas B is unemployed. In a second period, after a health shock, A is either ill or dead and has been replaced at work by B. We distinguish between the cases of morbidity and mortality when considering compensation mechanisms related to welfare changes between periods 1 and 2.
Case of a non-fatal disease (morbidity)
The variations in A and B’s consumption of private goods are, in monetary terms:
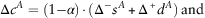 $$\Delta c^{A} =(1{\minus}\alpha ) \,{\cdot }\,(\Delta ^{{\minus}} s^{A} {\plus}\Delta ^{{\plus}} d^{A} )\,{\rm and}$$
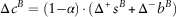 $$\Delta c^{B} =(1{\minus}\alpha ) \,{\cdot }\,(\Delta ^{{\plus}} s^{B} {\plus}\Delta ^{{\minus}} b^{B} )$$
where s i indicates individual i’s salary, b B unemployment benefits paid to B before the health change, d A disability allowances newly paid to A after the health change and α the constant tax rate. The symbol Δ is used to indicate ‘change in’ and the superscript denotes a positive or negative change.
According to the friction cost approach, replacement is complete when B’s productivity equals the productivity previously achieved by A before the health shock (Koopmanschap et al., Reference Koopmanschap, Rutten, van Ineveld and van Roijen1995). We therefore assume  $$\left| {\Delta ^{{\minus}} s^{A} } \right|=\left| {\Delta ^{{\plus}} s^{B} } \right|$$
. From equations (5a) and (5b) we consequently derive:
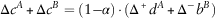 $$\Delta c^{A} {\plus}\Delta c^{B} =(1{\minus}\alpha ) \,{\cdot }\,(\Delta ^{{\plus}} d^{A} {\plus}\Delta ^{{\minus}} b^{B} )$$
Concerning the external part of the production costs, relation 4 gives us:
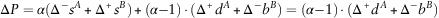 $$\Delta P=\alpha (\Delta ^{{\minus}} s^{A} {\plus}\Delta ^{{\plus}} s^{B} ){\plus}(\alpha {\minus}1) \,{\cdot }\,(\Delta ^{{\plus}} d^{A} {\plus}\Delta ^{{\minus}} b^{B} )=(\alpha {\minus}1) \,{\cdot }\,(\Delta ^{{\plus}} d^{A} {\plus}\Delta ^{{\minus}} b^{B} )$$
From relations (6) and (7), we deduce that, in monetary terms, the change in private consumption equals the change in public budget: 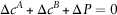 $\Delta c^{A} {\plus}\Delta c^{B} {\plus}\Delta P=0$
. This equality holds irrespective of the values of d A and d B and therefore for different types of social insurance schemes. Hence, once an ill person has been replaced at work effects 3 (private consumption) and effect 4 (external effect) balance each other out in monetary terms. As CBA assumes that the marginal utility of income is the same across individuals and that an equal social weight is ascribed to all persons, income redistributions between individuals do not affect social welfare. However, the compensation involved between equations 6 and 7 depends on a substitution between private consumption and public goods. Given the utilitarian framework set out in relations 1 and 2, this compensation will be welfare-neutral (i.e. dW=0) if one assumes that the social utility of 1 euro is the same whether it serves for private consumption or for the production of public goods.Footnote 3
Regarding the variation of the quantity of leisure time available in society, the gain in leisure time for A because of illness is compensated for by an equivalent loss of leisure time for B, or  $$\left| {\Delta ^{{\plus}} l^{A} } \right|=\left| {\Delta ^{{\minus}} l^{B} } \right|$$
. Consequently, as shown by Brouwer and Koopmanschap (Reference Brouwer and Koopmanschap2005), in the case of morbidity the total leisure time in society is left unchanged by A’s illness. This transfer of leisure time between individuals has no effect on social welfare as defined by relation 1 if the marginal utility of leisure is the same for all individuals irrespective of their health status. Otherwise, the difference in the utility of leisure enjoyed by the ill and the previously unemployed person has to be captured in the measure of health care benefits (Brouwer and Koopmanschap, Reference Brouwer and Koopmanschap2005), that is, included in WTP estimates in the case of CBA.
The above analysis puts forward two main results. First, in terms of social welfare, ill worker replacement cancels out the losses and gains in consumption and leisure because of illness provided that the social marginal utility of income and of public budget is the same. Second, taking into account the external component of productivity losses, the compensation mechanisms operate regardless of the levels of disability and unemployment insurance. There is thus no need to estimate potential differences between them when performing a CBA.
Case of mortality
Let us now consider the case of mortality. If A dies and is replaced at work by B, social insurance paymentsFootnote 4 decrease by the amount of unemployment benefits previously paid to B. The resulting variations in consumption and in public budget correspond to:
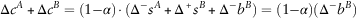 $$\Delta c^{A} {\plus}\Delta c^{B} =(1{\minus}\alpha ) \,{\cdot }\,(\Delta ^{{\minus}} s^{A} {\plus}\Delta ^{{\plus}} s^{B} {\plus}\Delta ^{{\minus}} b^{B} )=(1{\minus}\alpha )(\Delta ^{{\minus}} b^{B} )$$
 $$\Delta P=\alpha \,{\cdot }\,\Delta ^{{\minus}} s^{A} {\plus}\alpha \,{\cdot }\,\Delta ^{{\plus}} s^{B} {\plus}(\alpha {\minus}1) \,{\cdot }\,\Delta ^{{\minus}} b^{B} =(\alpha {\minus}1) \,{\cdot }\,\Delta ^{{\minus}} b^{B} $$
From relations 8 and 9, we obtain  $$\Delta c^{A} {\plus}\Delta c^{B} {\plus}\Delta P=0$$
. The total monetary value of society’s consumption is left unaffected by the death of a working person after replacement at work. As in the case of morbidity, social welfare is also unchanged provided that 1 euro spent on consumption has the same social utility as 1 euro used for the production of public goods.
However, in the case of mortality, there is no compensation for the leisure time lost by the previously unemployed person (effect 2). The utility derived from this specific component of leisure time is difficult to assess. Moreover, as has been underlined by Brouwer and Koopmanschap (Reference Brouwer and Koopmanschap2005), in the case of a long period of unemployment, the opportunity cost of leisure as compared with work is likely to be very low. For instance, many empirical studies provide evidence that unemployment is a significant source of disutility irrespective of its effect on income (Clark, Reference Clark2006; Stutzer and Frey, Reference Stutzer and Frey2010). As a consequence, the value of lost leisure time might be considered small.
To sum up, our analysis indicates that in both the case of mortality and morbidity the possibility of replacement at work cancels out the effects of changes in consumption and in leisure time resulting from illness on social welfare. In our framework, effects 3 and 4 (i.e. the individual and external part of productivity costs) compensate. The compensation mechanism operates if the social marginal utility of individual income and public budget is the same. This conclusion holds irrespective of the levels of disability and unemployment insurance.
The first implication of our analysis is that the measurement of individual WTP for health care benefits should be conducted so as to exclude the consequences of illness on income and leisure time. This result applies in a CBA where productivity costs are valued according to the FCM as this method postulates ill worker replacement. The second implication is that once replacement at work has taken place, one only needs to value the change in the ill person’s health-related quality of life (effect 1) to fully characterize the impact of illness on social welfare. In other words, we need to estimate what Currie et al. (Reference Currie, Donaldson, O’Brien, Stoddart, Torrance and Drummond2002) call a restricted form of WTP. It is worth mentioning that real situations are likely to be more complicated than our simple formal framework that assumes only two periods and uniform social benefits and tax rates. For instance, disability allowances may evolve over time and tax rates may vary with sources of income. However, our framework can be interpreted as using mean values for social benefits over time. In addition, it can easily be verified that applying different tax rates for various sources of income would not change the compensation mechanisms we described.
A risk of double counting in cost-benefit analyses of life-saving programs
To avoid risks of double counting the productivity losses in economic evaluations, Drummond et al. (Reference Drummond, Sculpher and Torrance2005) recommend estimating “the value of improved health whilst asking individuals to ignore the income effect and then to estimate productivity changes separately” (p. 86, emphasis added). Applying this approach in practice should not be problematic when estimating the value of morbidity reduction. This could be done, for example, by asking respondents to state their WTP for health care while imagining they have full income insurance.
Things are more complicated when it comes to valuing the prevention of a fatal disease. The problem is that conventional methods to the estimation of the value of life are supposed to capture the contribution of income or consumption to the individual utility. Economists commonly determine the social value of preventing a death with estimates of the ‘value of a statistical life’ (VSL). The VSL is derived from the assessment of individual monetary WTP (w) for small reductions (Δp) in the risk of death from a specific injury or illness. It is computed as the ratio w/Δp (Ashenfelter, Reference Ashenfelter2006; Mason et al., Reference Mason, Jones-Lee and Donaldson2009). This ratio measures a risk-money trade-off that represents a monetary estimation of the value of increased safety. By definition, the VSL estimates are expected to include all aspects that contribute to the enjoyment of life, such as life expectancy, health-related quality of life and anticipated future wealth or consumption (Johannesson, Reference Johannesson1996; Mason et al., Reference Mason, Jones-Lee and Donaldson2009). Theoretically, the VSL is expected to rise with wealth as a result of both decreasing marginal utility of income and the fact that rich people have more to lose than poorer ones (Viscusi and Aldy, Reference Viscusi and Aldy2003; Dolan et al., Reference Dolan, Metcalfe, Munro and Christensen2008; Anderson and Treich, Reference Anderson and Treich2011). As our previous section has shown, when a deceased worker is replaced at work, his death induces no consumption losses at the social level. The use of crude VSL estimations in CBA where replacement at work is assumed would then amount to counting the value of income (or consumption) loss one time too many. However, asking people to state a WTP to reduce an immediate fatality risk while ignoring the contribution of future consumption to their welfare seems an unworkable idea. This is so as death is inherently associated with a total loss of all aspects that make life enjoyable. There seems to be no obvious practical solution to ask people to state the value of life preservation without taking the value of future consumption into consideration.
To summarize, on the basis of our account of the consequences of worker replacement on social welfare, it appears that using the VSL estimates to measure the benefits of programs that reduce mortality amounts to double counting the avoided losses of income. The bias would potentially correspond to the present value of the expected future incomes that a person takes into account when stating her WTP for a small reduction in the risk of death. This may represent a substantial amount depending on the current age of the person and on her expected future wealth. Note that this double-counting problem does not invalidate the friction cost approach when one assumes that worker replacement is possible. Instead, it suggests that to accurately estimate the monetary value of the benefits of programs preventing death, we need to devise an empirical approach to capture the sole utility provided by the intangible aspects of a life (effect 1), that is, of factors that contribute to the ‘quality of life’ over and above consumption. We present and discuss two possible approaches in the following section.
Discussion of two possible solutions
We suggest two possible ways to overcome the risk of double counting that we have identified above to make CBA of life-preserving programs compatible with the assumption of worker replacement. The problem we highlighted arises because the VSL includes the contribution of income to the individual’s utility. The proposed approaches consist in providing a monetary estimation of the utility of the intangible components of life that correspond to the quality of life over and above the contribution of consumption. To the best of our knowledge, the methods we discuss here have not previously been associated with the issue of double counting in CBA we are concerned with. However, as shown below, their practical application does not come without difficulties.
One way to attribute a value to the intangible component of the quality of life is to subtract from the assessed VSL an estimation of the present value of the individual’s total future consumption lost because of illness. It should be possible to obtain an approximation to this value on the basis of the ill worker’s net wages. The difference between the VSL and this value would then represent the utility of being alive as compared with dead over and above the intrinsic value of consumption (Miller, Reference Miller2000). Recent estimations of VSL might provide some insights regarding this value. According to Viscusi and Aldy (Reference Viscusi and Aldy2003), the VSL–age relationship follows an inverted U-shaped pattern, whereas one might expect a steady decline with age (as life expectancy and quality of life decline the older you get). At the same time, the individual consumption curve follows an age-related trajectory very close to the VSL curve. Both individual consumption and VSL rise moderately up to one’s early 50s and then decrease to remain at the level that prevails in one’s mid-40s (Viscusi, Reference Viscusi2008). The very similar age-related shapes of the two curves suggest that the intangible component of the VSL might remain stable throughout life. However, applying the solution we suggest, that is, substracting the present value of future individual consumption from the VSL, raises some theoretical and practical difficulties.
From a theoretical perspective, this approach is relevant provided that the individual utility function is additively separable with respect to income so that the specific contribution of future incomes can be subtracted from the individual’s total lifetime utility. This is a strong requirement. In addition, it undermines one of the advantages of WTP estimates as compared with QALYs for example which is that they do not require specific assumptions about the structure of individual preferences (Hammitt, Reference Hammitt2002). From an empirical perspective, though, the feasibility of estimating a value of life net of the contribution of income has to be investigated. First, to estimate the utility of future incomes, analysts would have to make assumptions about the discount rate that should be used to represent the individuals’ time preferences and about their risk attitudes with respect to both income and life expectancy. These two components should ideally be assessed empirically or, at the least, chosen by the analyst and their influence on the results examined through a sensitivity analysis. Second, assumptions are also necessary concerning the number of years of life individuals anticipate losing when they state their WTP for reductions in the risk of death. This could possibly be determined by directly asking respondents about the life expectancy they have in mind when stating their answers. Third, the analyst must also come to terms with the specific difficulties posed by the heterogeneity of VSL estimations (Viscusi, Reference Viscusi2010), which, among other factors, vary as a function of the cause of death (Dolan et al., Reference Dolan, Metcalfe, Munro and Christensen2008) and the degree of responsibility of the victim (Covey et al., Reference Covey, Robinson, Jones-Lee and Loomes2010). It is therefore necessary to be aware that in practice this solution is likely to produce varying estimations, depending on the assumptions made by the analyst.
A second possibility involves the direct calculation of the monetary value of the intangible health-related component of quality of life. This alternative approach draws on the methodology of some recent studies that have attempted to estimate the monetary value of a QALY (Gyrd-Hansen, Reference Gyrd-Hansen2003; Mason et al., Reference Mason, Jones-Lee and Donaldson2009; Pinto-Prades et al., Reference Pinto-Prades, Loomes and Brey2009). The approach consists in estimating individuals’ WTP for small health-related quality-of-life changes as defined using the EQ-5D preference-based scale. For instance, respondents can be asked to imagine living in a specific impaired health state and to indicate the maximum monetary amount they would be ready to pay to improve their quality of life up to a given preferred health state. Their answers are then used to estimate marginal rates of substitution (MRS) between income and health attributes that serve, in turn, to derive the monetary value of a QALY, that is, the monetary value of a year in perfect health. This ‘new approach’ produced empirical estimations that are significantly lower than those obtained using the more ‘conventional approach’ for QALY monetization (Gyrd-Hansen, Reference Gyrd-Hansen2003; Mason et al., Reference Mason, Jones-Lee and Donaldson2009). This ‘conventional approach’ consists in dividing estimations of a VSL by the expected number of QALYs gained by preventing a person’s immediate death (Hirth et al., Reference Hirth, Chernew, Miller, Fendrick and Weissert2000). The difference between the ‘new’ and the ‘conventional’ approaches was found to be more than double in the Mason et al. (Reference Mason, Jones-Lee and Donaldson2009) study, for instance.
According to Mason et al. (Reference Mason, Jones-Lee and Donaldson2009), one possible reason for this discrepancy is that the two approaches evaluate two different types of QALY. The ‘new approach’ (MRS between income and health attributes) refers to a type of QALY that is derived from the value of health changes only or, in other words, the value of health-related quality of life enhancement with income held constant.Footnote 5 The ‘conventional approach’ (VSL divided by the number of expected QALYs) relates to another type of QALY interpreted as the value of the extension of life. Unlike the ‘new approach’, the ‘conventional approach’ is intended to include the value of changes in all the factors that contribute to the enjoyment of life, including income. If this interpretation is correct, the monetary value of a QALY in the ‘new approach’ represents the value of improvement in health-related quality of life only (Mason et al., Reference Mason, Jones-Lee and Donaldson2009). This type of QALY would thus correspond to a value of life estimate that does not encompass the utility of consumption. The monetary value of this specific type of QALY could then be used in CBA of life-saving programs when worker replacement is assumed.
However, this second possibility raises as yet unresolved questions. It is indeed possible to propose alternative explanations of the above-mentioned discrepancy that do not require us to differentiate between two types of QALY. According to Gyrd-Hansen (Reference Gyrd-Hansen2003), the ‘conventional approach’ to monetizing QALY (VSL divided by the number of QALYs) is based on an ex ante valuation of risk reductions, whereas the ‘new approach’ (MRS between income and health) involves an ex post valuation, as the deterioration of health is already thought to have occurred. As a consequence, the ‘conventional approach’ can incorporate an option value, which reflects utility derived from anticipation as opposed to utility derived from outcome. This option value, however, is not captured by the ‘new approach’. The question of whether these ‘conventional’ and ‘new approaches’ estimate the same type of QALY is thus still unresolved. Further work is therefore required to determine whether or not the value resulting from the ‘new approach’ includes the utility derived from consumption. If it does not, then CBAs of death-prevention programs could be made compatible with the assumption of worker replacement by including the monetary value of a QALY derived from the estimation of a MRS between income and health attributes.
Although the two solutions discussed above seek to estimate a monetary value of life that is net of the utility associated with future incomes, they are nevertheless different in nature. This stems from the fact that the intangible part of quality of life (i.e. the non consumption-related part) may consist of more than health-related quality of life. Consequently, whereas the first solution remains within the realms of CBA, the second is instead more of a monetization of cost-utility analysis or, to quote Kenkel (Reference Kenkel2006), a QALYfication of the VSL. In other words, even if they are both valid, the two solutions might provide different empirical estimations for the value of the intangible component of life. Despite this, the difference might not be large enough to systematically dismiss the second approach as irrelevant within a CBA framework. This clearly depends on the factors that contribute to the quality of life over and above health-related quality of life and consumption and, most importantly, on the size of the contribution made by these factors to the individual’s overall utility. Further investigations are therefore needed to determine whether or not these two approaches produce similar estimates.
Conclusion
In this paper, we have provided an overall account of the consequences of an ill worker replacement on social welfare. This has allowed us to highlight a specific risk of double counting that arises when the FCM is used to value productivity losses in CBA of life-saving health care programs. This problem arises because the value of prevented death as estimated using the VSL is thought to encompass all the aspects that make a life valuable, including future consumption. At the social level, the gain in future incomes resulting from health care is thus counted twice, that is, once in the VSL and once in the reduction of production losses resulting from the replacement of the ill worker. We have discussed two possible solutions to this problem. One consists in trying to adjust estimations of the VSL to take account of the contribution of future incomes to individual welfare. Another possibility is to draw on recent attempts to estimate the monetary value of a QALY based on estimation of MRS between health and income. The two solutions are somewhat different in nature, require specific assumptions and yet raise unresolved questions. Nevertheless, we argue that despite their drawbacks, these two solutions should be considered as preferable to the use of crude VSL estimates in CBA when production gains are assessed assuming replacement at work.
Acknowledgments
The authors are grateful to Sophie Béjean, David Crainich and two anonymous referees for many helpful comments and suggestions. All remaining errors are, of course, solely the responsibility of the authors.
Financial support
Financial support for this study was provided by two French government agencies, Agence Nationale pour la Recherche [ANR grant No. 05-9-30]; and Agence Nationale de Sécurité sanitaire de l'alimentation, de l'environnement et du travail [ANSES grant No. 2009-1-43]. The funding agreement ensured the authors’ independence in designing the study, interpreting the data, writing, and publishing the report.



