Introduction
The paranasal sinuses are an uncommon site for verrucous carcinoma.Reference Michaels1 In the head and neck region, the oral cavity and larynx are the most frequently described sites for this tumour.Reference Batsakis, Hybels, Crissman and Rice2 Verrucous carcinoma was first described in the oral cavity by Lauren AckermanReference Ackerman3 in 1948, as a warty, grey-white lesion with filiform projections. Its incidence of verrucous carcinoma varies from 4.5 to 9 per cent.Reference Spiro4 Differentiation from non-verrucous squamous cell carcinoma depends on the lack of cytological characteristics of malignancy.Reference Shear and Pindborg5, Reference Sternberg6 The aetiology of verrucous carcinoma remains unknown,Reference Mody and Shastri7, Reference Proffitt, Spooner and Kosek8 and the role of human papillary virus (HPV) in the tumour's pathogenesis needs to be clarified.Reference Kasperbauer, O'Halloran, Espy, Smith and Lewis9–Reference Eisenberg, Rosenberg and Krutchkoff12 Regional lymph node metastasis and distant metastasis are extremely rare.Reference Hanna and Ali13 A slow growing pattern and the ability to invade normal tissues to a limited extent demonstrates the tumour's aggressiveness.Reference Sternberg6
The patient reported below represents only the second case of verrucous carcinoma invading the orbit to be reported in the literatureReference Taybos, Feltman and Terezhalmy14 and, as far as we know, the first case of the tumour to originate in the paranasal sinuses and rapidly invade the orbit. Knowledge of this potential site of invasion, along with awareness of the aggressive feature of expansion, may help the otolaryngologist come to an early decision concerning surgical treatment.
Case report
A 58-year-old man was admitted to our hospital with a three-month history of right nasal obstruction, together with repeated epistaxis and a medial canthal mass.
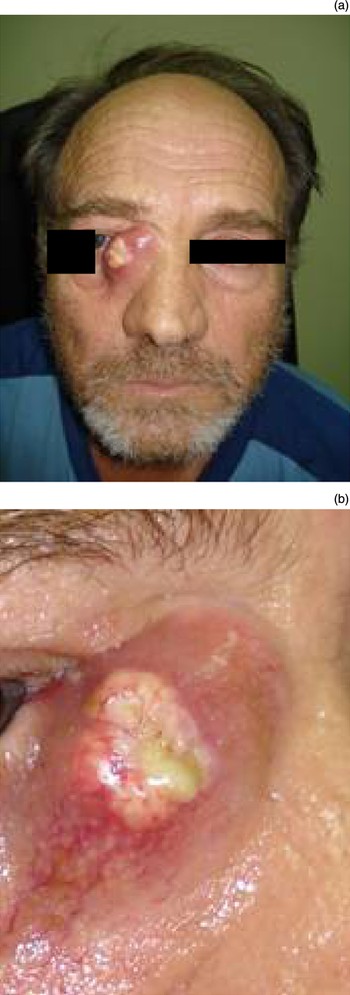
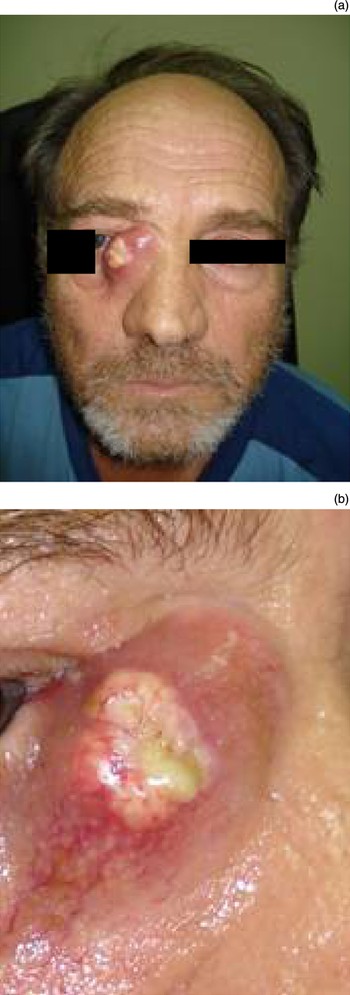
The ophthalmic examination diagnosed dacryocystitis due to obstruction of the right nasolacrimal duct (Figure 1).
Clinical photographs showing (a) a lesion involving the right medial canthus area, with diffuse swelling, erythema and (b) pus spontaneously draining from the central inflammatory region.
Two months previously, the patient had been admitted to another hospital and had received treatment with intravenous antibiotics for his condition, which had been misdiagnosed as pancolpitis with dacryocystitis as a complication. He had also undergone an incisional biopsy from the right nasal cavity growth, which on histological analysis had revealed hyperkeratotic squamous epithelium.
A general examination revealed that the patient was moderately built and nourished, with a normal gait and satisfactory vital signs. His past medical history indicated that the patient was a chronic smoker and drinker.
Intranasal examination revealed an extensive, expansive, exophytic, proliferative growth in the right nostril. The colour of the mucosa over the growth varied from white to pink. There were no obvious, palpable lymph nodes, and no evidence of distant metastasis.
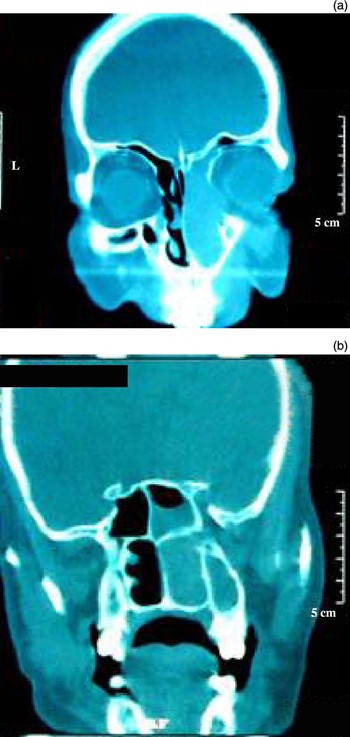
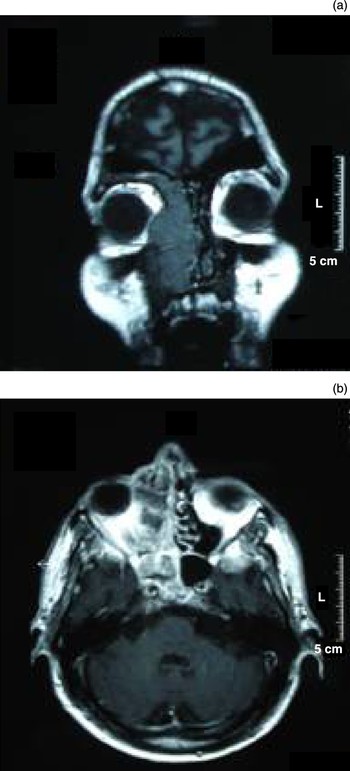
Computed tomography (CT) and magnetic resonance imaging (MRI) of the paranasal sinuses and nasal cavity revealed a soft tissue mass. This lesion was located in the right nasal cavity and the maxillary, ethmoid and sphenoid sinuses, and was associated with bony destruction of the medial wall of the maxillary sinus and lamina papyracea, and of the inferior and middle turbinates and a number of ethmoid cells (Figures 2 and 3). Figure 2 also shows absorption of the medial orbital wall and invasion of the orbit. A chest CT showed emphysema and a large right lung bulla which may cause pneumothorax during surgery.
Coronal computed tomography scans demonstrating a moderately enhanced, soft tissue lesion filling the right nasal cavity, (a) the right maxillary sinus and (b) the right sphenoid sinus. The medial wall of the orbit has been absorbed and the tumour is invading the orbit (b). L = left

Pre-operative magnetic resonance imaging scans: (a) T1-weighted, coronal scan; (b) Gd-enhanced, axial scan. The moderately enhanced mass in the nasal cavity shows heterogeneous isointensity in scan (a), but is heterogeneously hyperintense in scan (b). L = left

Since the clinical picture was one of malignancy, endoscopic removal of the tumour was performed two days after the patient's admission. Intra-operative endoscopy revealed that the right nasal cavity and middle meatus were filled with a lobulated, whitish, hard mass. Bony destruction of the lateral nasal wall, lamina papyracea and nasolacrimal apparatus, and invasion of the right orbit, were also found.
Repeated peri-operative frozen section biopsies from the nasal and medial canthal mass were negative for malignancy and non-diagnostic for the tumour. Thus, we were required to wait for the final results of histological examination, which would determine the precise treatment.
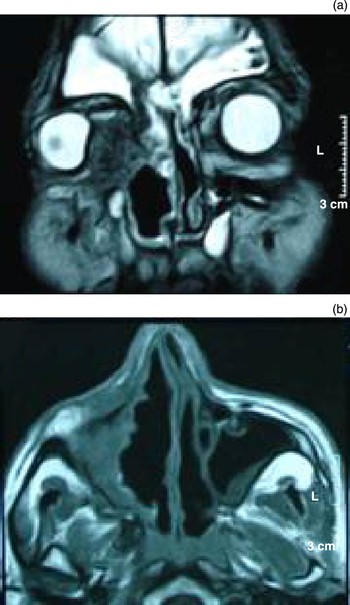
The patient's post-operative course was uncomplicated. However, rapid, continuous growth and ulceration of the medial canthal mass was noted, the patient began to complain of diplopia, and an ophthalmic examination showed reduced visual acuity of the right eye. An orbital MRI scan showed haemorrhagic and inflammatory lesions filling the right ethmoidal cells, plus post-operative changes in the right maxillary and frontal sinuses (Figure 4). This scan also revealed a mass extending to the right orbit through the lamina papyracea. The mass was compressing the right optic nerve, accounting for the patient's symptoms of optical neuropathy.
Post-operative magnetic resonance imaging scans. (a) T2-weighted, coronal scan; (b) T2-weighted, axial scan. Inflammatory lesions filling the right ethmoidal cells, post-operative changes in the right maxillary and frontal sinuses.

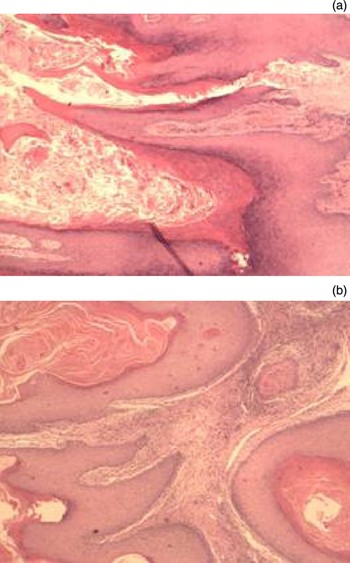
Histopathological examination of the nasal mass and the skin lesion revealed verrucous carcinoma (Figure 5). Epithelial cells exhibited vacuolation and atypia. The underlying connective tissue showed dense inflammatory infiltrate.
Photomicrographs of surgical specimens. (a) Well differentiated, stratified squamous epithelium overlying the connective tissue, with pushing margins and intact basement membrane. Epithelial cells exhibit vacuolation and atypia. The underlying connective tissue shows dense inflammatory infiltrate. (b) Keratinising, stratified, atypical squamous epithelium and acanthotic rete pegs penetrating the underlying tissues (H&E; ×100).

Due to the tumour’s aggressive behaviour, histopathological features and extent (revealed during surgery), it could not be completely excised.
The patient commenced chemotherapy with continuous infusion of Paclitaxel (Taxol) and carboplatin every three weeks (3 cycles) followed by radiotherapy. Radiotherapy included the nasal cavity and the ipsilateral paranasal sinuses. The patient was treated with radiation doses of 1.8 Gy per day, for 28 sessions, until 50.4 Gy had been delivered. By the end of the radiotherapy, the patient showed moderate response.
Discussion
Verrucous carcinoma was first described by Ackerman as an exophytic type of low grade squamous cell carcinoma with little metastatic potential, found in the oral cavity of 31 patients.Reference Eisenberg, Rosenberg and Krutchkoff12, Reference Schwartz15 Tumours fitting Ackerman's description have been reported in the literature under a variety of names, including florid papillomatosis,Reference Albert, Jakob and Rompel16 oral florid verrucosis,Reference Akyol, Anadolu, Anadolu, Ekmekci, Gürgey and Akay17 verruca acuminate,Reference Spiro4 verrucous squamous cell carcinoma,Reference Ferlito, Devaney, Rinaldo and Putzi18 papillomatoses mucosae carcinoidesReference Winnen19 and Ackerman's tumour.Reference Scheuermann and Delank20 Verrucous carcinoma has been reported in the skin, male and female genitalia, anal canal, uterine cervix, bladder, renal pelvis, and oesophagus.Reference Spiro4
In the head and neck region, verrucous carcinoma has been described in the oral cavity,Reference Walvekar, Chaukar, Deshpande, Pai, Chaturvedi and Kakade21 larynx,Reference Ferlito and Recher22 nose,Reference Paleri, Orvidas, Wight and Bradley23 earReference Hagiwara, Kanazawa, Ishikawa, Fujii, Kitamura and Noguchi24–Reference Woodson, Jurco, Alford and McGavran26 and, in one case, the orbit.Reference Taybos, Feltman and Terezhalmy14 The highest incidence is in the oral cavity, where the buccal mucosa, gingivae and retromolar areas are frequently involved.Reference McCoy and Waldron27 The glottic area of the larynx is the second most frequent site in the head and neck area.Reference Batsakis, Hybels, Crissman and Rice2 Involvement of the nose may include the paranasal sinuses,Reference Paleri, Orvidas, Wight and Bradley23 nasal septum,Reference Pothula and Jones28 collumellaReference Vico, Nagypal, Rahier and Deraemaecker29 and nasopharynx.Reference Jahn, Walter and Farkashidy30
The incidence of verrucous carcinoma varies from 4.5 to 9 per cent, with a male preponderance. Patients are generally aged between 50 and 80 years.Reference Spiro4, Reference Mody and Shastri7 The largest series come from India, where oral cancer is the most common malignant tumour (accounting for 27 per cent of all cancers).Reference Walvekar, Chaukar, Deshpande, Pai, Chaturvedi and Kakade21, Reference Rajendran, Sugathan and Augustine31 Tobacco chewing has been implicated in the high incidence of verrucous oral cancers in India.Reference Kolbusz and Goldberg32 Primary verrucous carcinoma of the sinonasal tract is rare, constituting 0.2–0.8 per cent of all malignancies and 3 per cent of head and neck malignancies.Reference Mosesson and Som33, Reference Karthikeya, Mahima and Bhavna34 Nunez et al. Reference Nunez, Suarez, Alvarez, Losa, Barthe and Fresno35 reported that malignant tumours of the sinonasal tract make up 6–10 per cent of upper respiratory tract cancers, with an annual incidence of less than 1 per 100 000 individuals.
The aetiology of sinonasal verrucous carcinoma is unclear. Habitual snuff use, tobacco chewing and poor oral hygiene have been proposed as risk factors for oral verrucous carcinoma.Reference Paleri, Orvidas, Wight and Bradley23
Molecular pathology studies have suggested that HPV infection may be associated with verrucous carcinoma of the head and neck. Human papilloma virus deoxyribo nucleic acid was identified in up to 85 per cent of patients in one series of laryngeal verrucous carcinoma.Reference Kasperbauer, O'Halloran, Espy, Smith and Lewis9 Human papilloma virus has not yet been correlated with sinonasal tract verrucous carcinoma.Reference Hagiwara, Kanazawa, Ishikawa, Fujii, Kitamura and Noguchi24 Another study found that patients with HPV-positive verrucous carcinoma had better survival rates than those with HPV-negative typical squamous cell carcinoma of the head and neck.Reference Szentirmay, Pólus, Tamás, Szentkuti, Kurcsics and Csernák36 The most common HPV subtypes found in laryngeal verrucous carcinoma are HPV-16 and -18.Reference Ferlito and Recher22 Controversially, in situ hybridisation methods suggest that laryngeal papillomas may be related to HPV, but not to verrucous carcinomas.Reference Multhaupt, Fessler and Warhol37 Chromosomal changes including, homozygous deletion, loss of heterozygosity, and mutation events detectable by immunohistochemical analyses have been investigated. The expression of p53 and epidermal growth factor receptor has been found to correlate significantly with verrucous carcinoma of the head and neck.Reference Wu, Putti and Bhuiya38 Inverted papilloma, a benign tumour, has been sporadically associated with verrucous carcinoma; however, transformation of inverted papilloma into verrucous carcinoma has not yet been verified.Reference Shiomori, Udaka, Nagatani, Fujimura, Ohbuchi and Sasaguri39
The clinical manifestations of verrucous carcinoma are closely related to the anatomical sites involved. In the sinonasal tract, verrucous carcinoma may resemble a nasal polyp or a pyocoele, with pus discharge from the nasal cavity.Reference Karthikeya, Mahima and Bhavna34, Reference Schwartz40, Reference Go, Oh and Ko41 Involvement of the nasolacrimal duct by any tumour may produce symptoms such as epiphora, blood-stained tears and epistaxis.Reference Yazici, Setzen and Meyer42–Reference Spira and Mondshine44 A history of blood-stained tears, nasal bleeding, and a rapidly growing, hard mass suggests the existence of a tumour in the lacrimal drainage system.Reference Baredes, Ludwin, Troublefield, Langer and Mirani45, Reference Spira and Mondshine46 In our patient, blood-stained tears were absent, and he was diagnosed with dacryocystitis, a condition commonly associated with dysfunction of the lacrimal drainage system. Tumour arising from the nasolacrimal duct itself is exceedingly rare.Reference Sakaida, Kobayashi, Yuta, Imanishi and Majima47 Prolonged dacryocystitis should arouse suspicion of tumour. The primary origin of locally advanced verrucous carcinoma may be unclear, since the nasolacrimal duct is closely related to the nasal cavity and the maxillary sinus. Local infiltration of verrucous carcinoma complicates the case further, since the tumour may originate from the maxillary sinus or nasal cavity and invade the nasolacrimal duct and lacrimal sac, and finally the orbit. Extension of the tumour into the orbit may cause exophthalmos and diplopia.Reference Ahmad and Esmaeli48, Reference Capone and Slamovits49
Diagnosis of verrucous carcinoma can be a dilemma. It is important to differentiate verrucous carcinoma from verrucous hyperplasia, well differentiated squamous cell carcinoma, papillary squamous cell carcinoma and squamous papilloma. Small, superficial biopsy specimens can be reported as hyperplasia or squamous cell proliferation, misleading the diagnosis.Reference Orvidas, Kerry, Lewis and Suman50 In our patient, this happened with the first two surgical specimens. Verrucous hyperplasia does not invade below the level of the basal cell layer of the neighbouring normal squamous epithelium.Reference Slootweg and Muller51 Both lesions can coexist, and verrucous hyperplasia can progress to squamous cell carcinoma or verrucous carcinoma.Reference Shear and Pindborg52 Lack of atypia helps to rule out conventional squamous cell carcinoma and papillary cell carcinoma. Verrucous carcinoma also lacks the well formed, wide, papillary fronds of squamous cell papilloma.Reference Schrader and Laberke53 Image morphometrical analysis can be of diagnostic help in cases in which no firm initial histopathological diagnosis can be obtained.Reference Cooper, Hellquist and Michaels54
The treatment of verrucous carcinoma prescribed by Ackerman included surgical excision or radiotherapy. The non-infiltrative but rather invasive character of the tumour suggests that resection with negative margins should be the primary treatment. However, verrucous carcinomas of the nasal cavity, nasopharynx and supraglottic larynx are difficult to excise with clear margins. In our patient, endoscopical, transnasal resection could not result in definitive treatment because of access limitations and tumour invasion of the orbit.
Radiotherapy can be used as an alternative or sequel to surgery, but usually results in poorer local control.Reference Koch, Trask, Hoffman, Karnell, Robinson and Zhen55 Concerns about anaplastic transformation after irradiation have been reported in the literature, and the incidence of such transformation has been reported to be as high as 30 per cent.Reference Nair, Sankaranarayanan, Padmanabhan and Madhu56 However, more recent reports suggest that, following radiotherapy, anaplastic transformation is observed occasionallyReference Yoshimura, Mishima, Obara, Nariai, Yoshimura and Mikami57 or not at all.Reference Huang, Lockwood, Irish, Ringash, Cummings and Waldron58 Furthermore, to make the puzzle even more complex, other evidence suggests that anaplastic transformation can occur in non-irradiated patients before or after surgery, or even in untreated cases.Reference Batsakis, Hybels, Crissman and Rice2, Reference Strong59
The literature on the role of chemotherapy in the treatment of verrucous carcinoma of the head and neck is limited to case reports and small series; these suggest that it can be successfully used in patients with inoperable tumours.Reference Strojan, Soba, Budihna and Auersperg60 Our patient represents the second reported case of verrucous carcinoma of the paranasal sinuses to receive post-operative chemotherapy.Reference Paleri, Orvidas, Wight and Bradley23
Verrucous carcinomas have a good prognosis, with a five year survival rate of 77 per cent.Reference Koch, Trask, Hoffman, Karnell, Robinson and Zhen55
Conclusions
Verrucous carcinoma is a variant of well differentiated squamous cell carcinoma which slowly invades local structures. It rarely develops in the paranasal sinuses. If rapid invasion occurs in this site, verrucous carcinoma may involve vital structures such as the orbit. A high index of clinical suspicion confers the advantage of early investigation. Early diagnosis improves the therapeutic outcome and diminishes the need for extended surgical procedures. Surgical excision is the treatment of choice. Radiotherapy and chemotherapy are feasible first choice options for inoperable cases, for patients not suitable for major surgery, or when functional and cosmetic impairment is possible.