Introduction
Brain size may passively protect against long-term effects of aging and disease, helping compensate for and preserve cognitive function (Mori et al., Reference Mori1997; Reynolds et al., Reference Reynolds, Johnston, Dodge, DeKosky and Ganguli1999). The exact mechanism for how this occurs remains unclear, but may be due to the complexity of neurons, synaptic connections, parenchymal density, and co-morbidities (Henneberg, Reference Henneberg1998). ICV represents the peak, total volume of white and grey matter plus cerebrospinal fluid (CSF) (Pfefferbaum et al., Reference Pfefferbaum, Mathalon, Sullivan, Rawles, Zipursky and Lim1994). Because of its association with maximum lifetime brain size, it has been proposed as a predictive measure of cognitive reserve (Katzman et al., Reference Katzman1988; Schofield et al., Reference Schofield, Logroscino, Andrews, Albert and Stern1997). A number of studies have found that patients with larger brains or ICV by autopsy or imaging had preserved cognitive function (Schofield et al., Reference Schofield, Mosesson, Stern and Mayeux1995; MacLullich et al., Reference MacLullich, Ferguson, Deary, Seckl, Starr and Wardlaw2002). Accurate ICV measures, however, currently require complex, time-consuming neuroimaging technology and analysis (Filippi et al., Reference Filippi, Rovaris, Iannucci, Mennea, Sormani and Comi2000). Thus, efficient correlates like head circumference have been proposed for ICV, as appropriate surrogate measures particularly for epidemiologic clinical studies in resource-scarce regions of the world.
There are limited previous studies on the relationship between head circumference and ICV (Jorgensen et al., Reference Jorgensen, Paridon and Quaade1961). Wolf et al. demonstrated that parenchymal volume, easily calculated from MRI-derived head circumference, is closely correlated with ICV even among patients with cognitive impairment (Wolf et al., Reference Wolf, Kruggel, Hensel, Wahlund, Arendt and Gertz2003; Reference Wolf2004). There are, however, many physiological factors besides brain size that can affect head circumference, including skull thickness, temporal wasting, and estrogen deficiency (Gurwitz et al., Reference Gurwitz, Chapman and Weizman2002; Wolf et al., Reference Wolf2004). These factors gain increasing prominence as people age. While sophisticated neuroimaging means of determining ICV exist, head circumference remains a quick, efficient strategy that is more readily available. In two population-based cross sectional studies, head circumference was inversely related to the prevalence of dementia in low and middle-income regions internationally although this may have been due to epidemiologic or statistical limitations such as reverse causality and selective mortality (Jotheeswaran et al., Reference Jotheeswaran, Williams, Stewart and Prince2011; Prince et al., Reference Prince2011). Our study is the first to assess the correlation of simple head circumference measurement with estimated ICV by MRI among older adults. We examine whether this surrogate measure may be useful as a research tool for large-scale epidemiologic studies among the geriatric population.
Methods
Study design
Our study population is a subsample of the Successful Aging after Elective Surgery (SAGES) study, a five-year prospective, observational study of postoperative delirium at Beth Israel Deaconess Medical Center (BIDMC), Brigham and Women's Hospital (BWH), and Hebrew SeniorLife in Boston, Massachusetts. Study design and eligibility criteria have been reported previously (Schmitt et al., Reference Schmitt2012). Inclusion criteria included: age ≥70 years old, English-speaking, undergoing major elective surgery at BIDMC or BWH. Exclusion criteria included diagnosis of dementia by medical record screening or patient report; cognitive impairment defined by score ≤69 or education-adjusted equivalent on the Modified Mini-Mental State (3MS) Examination (Teng and Chui, Reference Teng and Chui1987); terminal disease; total blindness; severe deafness; MRI contraindication; present neurological illness, alcohol or illicit drug abuse. All study procedures were approved by the institutional review boards at BIDMC, BWH, and Hebrew SeniorLife. All participants gave written informed consent.
Head circumference
All SAGES participants underwent head circumference measurements using standardized approaches by trained research staff, blinded to MRI results. The research staff asked participants to remove headwear and placed the inflexible paper tape measure snugly around the participant's head. The measurement extended from just above the eyebrows outwards to the most posterior occipital protuberance. Two measurements were taken, and the largest reading recorded in centimeters.
MRI acquisition
Approximately one-third of the enrolled SAGES participants elected to undergo MRI imaging prior to surgery. 99 pre-surgical MRI scans were analyzed for the present study as a convenience sample. All participants were imaged at the BIDMC Radiology Department on a 3-Tesla HDxt MRI scanner (General Electric Medical Systems, Milwaukee, WI) using a standard 8-channel head coil. MRI imaging was acquired 1–4 months before head circumference measurement.
The MRI protocol included the following image acquisitions used for ICV evaluation:
-
1. High Resolution three-dimensional (3D) anatomic imaging – Magnetization prepared fast gradient echo (MPRAGE) 3D T1-weighted sequence with TR of 7.9 ms, TE of 3.2 ms, 15 degree flip angle and 32 kHz-bandwidth, a coronal acquisition plane with 24×19 field of view, 0.94 mm in-plane resolution, 1.4 mm slices, preparation time of 1,100 ms with repeated saturation at the beginning of the SAT period, and an adiabatic inversion pulse 500 ms before imaging.
-
2. High Resolution 3D T2-weighted imaging – A 3D fast spin echo sequence (Cube™) was acquired in the sagittal plane with TR 3s, effective TE 63.6 ms, echo train length 100, bandwidth 62.5, 1 mm in-plane resolution and 128 1.6 mm slices.
-
3. Fluid Attenuated Inversion Recovery (FLAIR) – An axial acquisition with TR/TE of 9,000/156 and T1 of 2,250 was employed. Seventy 2mm slices were acquired with no interslice gap and interleaved acquisition. Nominal in-plane resolution was 1mm.
MRI analysis
MRI-derived ICV was determined using two different methods. The first method involved SPM8 software (Wellcome Institute). The New Segmentation Method provided by this software, an extension of unified segmentation method, allows for automated whole brain segmentation (Ashburner and Friston, Reference Ashburner and Friston2005) of the T1-weighted images; then grey and white matter and CSF components were totaled to yield brain volume measurement.
ICV was also determined using FSL software. First, bias-field correction to account for field inhomogeneities was performed using 3DSlicer software (www.slicer.org) (Fedorov et al., Reference Fedorov2012). ICV masks were then segmented from T2-weighted images using Brain Extraction Tool (BET) of FSL (Smith, Reference Smith2002; Smith et al., Reference Smith2002; Reference Smith2004) and subsequently reviewed and manually corrected by a neuroimaging expert (TH) using axial T2-weighted images as reference. This method for determining ICV is generally considered the gold standard by experts in neuroimaging (Smith et al., Reference Smith2002; Reference Smith2004). A second neuroimaging expert reviewed and manually corrected ten ICV masks independently to assess inter-rater reliability.
The neuroimaging experts who performed the processing and analysis of the images were blinded to the head circumference measurement and clinical data.
Statistical analysis
Data analysis for this study was performed on the first 99 patients enrolled in the SAGES study and participating in the MRI substudy. We measured associations between head circumference and MRI indices and between the MRI indices, using Pearson correlation coefficients. Discrepant cases were determined by fitting a linear regression to head circumference and ICV, allowing for a main effect and interaction with gender. The threshold for significance was p < 0.05 in all analyses.
Results
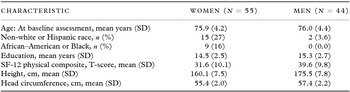
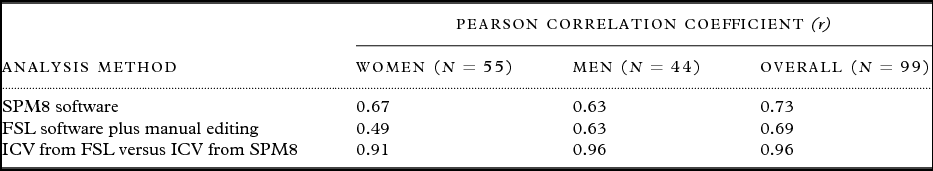
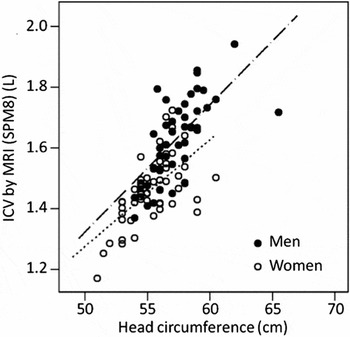
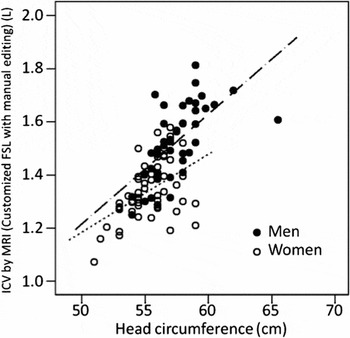
Baseline characteristics of the 99 participants are summarized in Table 1. The mean time elapsed between MRI acquisition and head circumference measurement was 50 days ± 17 (range 29–127 days). The correlation between head circumference and MRI ICV, and between the two MRI ICV measures, is summarized in Table 2. There was high positive correlation between head circumference and SPM8 software-calculated ICV overall (r = 0.73, p < 0.01) (Figure 1). There was also moderately high correlation between head circumference and SPM8-calculated ICV for women (r = 0.67, p < 0.01) and men (r = 0.63, p < 0.01) (Figure 1). There was high positive correlation between head circumference and ICV derived from FSL software plus manual editing (r = 0.69, p < 0.01) (Figure 2). The correlation was higher among men (r = 0.63, p < 0.01) but moderate among women (r = 0.49, p < 0.01) (Figure 2). The two measures of MRI ICV had very high correlation overall (r = 0.96, p < 0.01), among women (r = 0.91, p <0.01) and men (r = 0.96, p < 0.01) (Table 2). Mean residual (by sex) was evaluated for all 99 study participants; there was an overall overestimation of ICV for women and underestimation of ICV for men by head circumference.
Baseline characteristics of study participants*

*SD = standard deviation; SF-12 = short function-12; cm = centimeters.
The relationship between head circumference and ICV by MRI*

p < 0.01 in all correlations.
*ICV = intracranial volume; MRI = magnetic resonance imaging; SPM8 = statistical parametric mapping 8; FSL = functional magnetic resonance imaging of the brain software library.
The relationship between head circumference and ICV by MRI (SPM8).
The correlation between head circumference and MRI derived ICV (SPM8 analysis) for men was r = 0.67 (n = 44), for women r = 0.63 (n = 55) and overall r = 0.73 (n = 99) with p < 0.01 for all relationships. SPM8 = Statistical Parametric Mapping 8; ICV = intracranial volume; MRI = magnetic resonance imaging; L = liters; cm = centimeters. Linear functions are: ICV(SPM8) = −0.85 + 0.57 × female + 0.0413×HC + −0.012 × female × HC.

The relationship between head circumference and ICV by MRI (customized FSL with manual editing).
The correlation between head circumference and MRI derived ICV (FSL with manual editing) for men was r = 0.63 (n = 44), for women r = 0.49 (n = 55) and overall r = 0.69 (n = 99) with p < 0.01 for all relationships. FSL = Functional Magnetic Resonance Imaging of the Brain Software Library; ICV = intracranial volume; MRI = magnetic resonance imaging; L = liters; cm = centimeters. Linear functions are: ICV(FSL) = −0.78 + 0.37 × female + 0.0420 × HC + −0.0082 × female × HC.

A very relevant concern is the potential for bias in estimating associations between exposures or outcomes and head circumference measurements as variously defined. To evaluate this possibility, we regressed standardized ICV assessed with SPM8, FSL, and approximated with head circumference on height in 101 bootstrap samples and examined the variability in the regression coefficients. The mean standardized coefficient for SMP8 ICV and height was b* SPM = 0.55 (standard deviation, SD = 0.085); FSL was similar (b* FSL = 0.54 (0.089)) and head circumference consistently lower (in 91% of 101 replications b* HC < b *SPM ; b* HC = 0.46 (0.096)). Using the mean for SPM8 as the standard, the root mean squared error for SPM8 was 0.085, FSL was 0.089, and was 0.133 for head circumference. Therefore, there may be some attenuation of effects and increased variability that would accompany the use of head circumference relative to MRI measured ICV. There are sample size and statistical power concerns as well. For example, the minimum sample size needed to detect a correlation of 0.55 is n = 22, compared to n = 33 to detect a correlation of 0.46.
Discussion
This study of community-dwelling older adults scheduled for elective surgery demonstrates a moderately strong correlation between head circumference and ICV measured by MRI in older adults. The correlation was present regardless of which type of MRI analysis. SPM8 for ICV segmentation uses T1-weighted scans in which both CSF and cortical bone appear darkened, making it less accurate and more prone to inadvertently including extra dural tissue in the ICV calculation. Thus, the SPM8-calculated ICV likely correlates better with head circumference but is less accurate because it is more influenced by overall head size. FSL with manual editing is considered the gold standard for ICV segmentation because of the expert review and high T2-signal contrast between CSF and meninges, allowing for more accurate segmentation. This does, however, make FSL with manual editing a more time consuming and less feasible approach for some studies.
The relatively weaker correlation between women's head circumference and ICV by both MRI analysis methods could be expected, given the frequent presence of more hair in older women compared to men, women's hairstyles and male-pattern hair loss. Previous literature found correlations between head circumference and ICV to be r = 0.5–0.8 (Brandt, Reference Brandt1985; Graves et al., Reference Graves, Mortimer, Larson, Wenzlow, Bowen and McCormick1996), similar to our results. Most prior studies involved younger individuals without many co-morbidities. There was also a statistically significant overestimation of female ICV by head circumference and underestimation of male ICV in our study population.
To our knowledge, this is the first study to examine the correlation between head circumference and ICV among older patients. We demonstrated that even in this older population, head circumference is a quick and accurate approximation of ICV. This study suggests the stability of head circumference correlation with ICV throughout the lifespan. Several important strengths of this study include the large sample size (one of the largest to date addressing this topic), clinically rich data collection and two methods of ICV neuroimaging analysis lending robustness to our findings.
Limitations of our study include the fact that only the larger measurement of head circumference measurement was recorded, which may have decreased precision and precluded calculating a coefficient of variation. One previous study used multi-dimension measurements – height, width and length – of the human skull instead of head circumference to approximate ICV (Sahin et al., Reference Sahin2007). They also found good correlations with actual ICVs possibly because their dimensions are less susceptible to hair thickness and may characterize the shape of the entire skull better. There may also be potential limitations to generalizability. Our study is a subsample selected from surgical schedules of two large academic hospitals; study participants were generally highly functional, well-educated and not racially diverse. Thus, our findings will need future validation in larger and more heterogeneous populations.
This study helps bolster the research utility of head circumference as a simple, quick prognostic surrogate for ICV even among older persons. We do show some evidence that MRI measures of ICV are more accurate than measures derived from simple head circumference, and the use of the simple measures comes at a cost of increased variability and lower statistical power. Our study lays the groundwork for more sophisticated predictive models correlating head circumference and ICV. Head circumference can serve an important role for community-based epidemiologic studies, where MRI studies are not feasible, as an estimate of ICV and brain volume. This measurement may have particular usefulness in large-scale studies of dementia and cognitive function (Mortimer, Reference Mortimer2012) internationally. This study addresses some of the selective mortality and reverse causality concerns raised by other researchers regarding head circumference correlations with dementia (Jotheeswaran et al., Reference Jotheeswaran, Williams, Stewart and Prince2011; Prince et al., Reference Prince2011). Finally, the correlation between head circumference and cognitive reserve represents a rich area for exploration in future studies (Mortimer et al., Reference Mortimer, Snowdon and Markesbery2003).
Conflict of interest
None.
Author contributions
Drs. Jones and Inouye contributed equally as co-senior authors. We affirm that all the co-authors listed contributed significantly to the preparation of this manuscript and approve this final version to be published.
Dr. Hshieh substantially contributed to the analysis and interpretation of data, drafting the paper and revising it critically for important intellectual content. Ms. Fox and Mr. Kosar contributed to the acquisition of data, analysis and interpretation of data and revising the paper critically. Drs. Cavallari and Guttmann contributed to the acquisition of data, analysis and interpretation of data and revising the paper critically. Dr. Alsop contributed to the conception and design, analysis, and interpretation of data and revising the paper critically. Dr. Schmitt contributed to the acquisition of data, analysis, and interpretation of data and revising the paper critically. Dr. Jones contributed to the acquisition of data, analysis and interpretation of data and revising the paper critically. Dr. Marcantonio contributed to the conception and design, acquisition of data, analysis, and interpretation of data and revising the paper critically. Dr. Inouye contributed to the conception and design, acquisition of data, analysis and interpretation of data, drafting the paper and revising it critically as well as obtaining funding and administrative support.
Acknowledgments
The authors thank the patients, family members, nurses, physicians, and dedicated staff who participated in the SAGES study. This work was supported by the following sources of funding – Grants No. P01AG031720 (SKI), K07AG041835 (SKI), and K24AG035075 (ERM) from the National Institute on Aging. Dr. Hshieh is supported by an NIH funded T32 Training Grant (AG000158). Dr. Inouye holds the Milton and Shirley F. Levy Family Chair. The funding sources had no role in the study design, collection/analysis/interpretation of data, writing of the report, or decision to submit for publication. All co-authors had no potential financial or personal conflicts of interest.