Kawasaki disease is an acute systemic vasculitis of medium- and small-sized arteries that occurs predominantly in children under 5 years of age. It is now known to occur worldwide in children of all ethnicities, with different incidence rates.Reference Kawasaki 1 In Portugal, the incidence rate was 6.5 per 100,000 children aged 0–4 years in 2000–2011.Reference Laranjo, Aidos, Lourenço, Rodrigues and Pinto 2
A multifactorial aetiology is accepted, where an infectious trigger, in a favourable ambient environment, can act on genetically susceptible individuals causing Kawasaki disease.Reference Rowley 3 – Reference Duong, Silverman and Bissessar 5 It is typically self-limited, and its major complication is the occurrence of coronary artery aneurysms, which can develop in nearly 25% of untreated patients and 5–10% of treated patients. Hence, the treatment in the acute phase is focussed on preventing coronary ectasias and potential thrombotic occlusions.Reference Kato, Sugimura and Akagi 6
A good prognosis is generally expected for patients with Kawasaki disease, and no cardiac involvement or only mild and transient dilatation of the coronary arteries, without aneurysm formation, are observed in those who recover without sequelae. Although some studies performed in children and adolescents have hypothesised that previous Kawasaki disease is a potential risk factor for early onset of atherosclerosis,Reference Gupta-Malhotra, Gruber and Abraham 7 – Reference Iemura, Ishii and Sugimura 12 others have shown that the vascular changes represent a specific form of vasculopathy. Burns et al reported their findings on autopsy studies of adults who died of complications related to undiagnosed Kawasaki disease in childhood. No classical histological changes in atherosclerosis were found. Instead, long-term histopathological abnormalities such as subacute and chronic vasculitis or luminal myofibroblastic proliferation were observed, causing increased thickness of the arterial wall and decreased lumen of the coronary arteries with replacement of normal endothelium in the affected areas, by dysfunctional endothelial cells, perpetuating the inflammatory process, expressed as abnormal inflammatory parameters.Reference Newburger, Burns and Beiser 9 , Reference Mitani, Sawada and Hayakawa 10 , Reference Orenstein, Shulman and Fox 13 , Reference Burns, Shike and Gordon 14
Patients with coronary artery aneurysms and those with regressed aneurysms may also have endothelial dysfunction and increased intima-media thickness of the carotid arteries.Reference Dhillon, Clarkson and Donald 11 – Reference Noto, Okada and Yamasuge 19 There is conflicting evidence that an abnormal endothelial function can also be shown in patients without coronary involvement, long term after the Kawasaki disease episode.Reference McCrindle, McIntyre and Kim 8 , Reference Mitani, Sawada and Hayakawa 10 , Reference Dhillon, Clarkson and Donald 11 , Reference Yamakawa, Ishii and Sugimura 15 , Reference Ikemoto, Ogino and Terguchi 18 – Reference Vita and Keaney 22
Understanding vascular function long term after Kawasaki disease can enlighten our knowledge of this pathological process and the need for changes in the long-term follow-up of these patients.
Endothelial function can be assessed using reactive hyperaemia in the peripheral arteries, a physiological response based on dilatation of the target artery in response to increased blood flow after shear stress.Reference Furchgott and Zawadzki 23 – Reference Cooke, Rossitch and Andon 25 Endothelial peripheral arterial tonometry (EndoPat) is a technique that measures changes in digital pulse volume, assessed at the finger tips, before and after reactive hyperaemia.Reference Kadono, Sugiyama and Hoshiai 26 – Reference Kuvin, Patel and Sliney 29 The augmentation index, a measure of arterial stiffness, is also obtained during EndoPat examination, and several studies have demonstrated its association with cardiovascular risk factors,Reference Laurent, Cockcroft and Van Bortel 30 , Reference Newburger, Keflioglu-Scheiber and Opazo Saez 31 although it is still an exploratory method.
Carotid intima-media thickness has been used as a non-invasive method to test early or subclinical atherosclerotic changes, both in children and adults.Reference Urbina, Williams and Alpert 32 It has also been used as a surrogate marker for both coronary and peripheral artery atherosclerosis. Several studies were performed to studied carotid intima-media thickness changes in children with Kawasaki disease, showing conflicting results.Reference Gupta-Malhotra, Gruber and Abraham 7 , Reference Ikemoto, Ogino and Terguchi 18 , Reference Noto, Okada and Yamasuge 19 , Reference Meena, Rohit and Gupta 33 , Reference Lee, Ahn and You 34
The aim of this study was to access vascular function in adolescents and young adults long term after Kawasaki disease, but without coronary aneurysms or any other cardiac risk factors; the present study was a single-centre, prospective study in a Portuguese population.
Materials and methods
Overall
This present study was a single-institution, prospective study, and the investigators were blinded to the study protocol. The study was approved by the Institutional Ethics Committee, and an informed consent was obtained from all subjects or their parents.
Clinical evaluation, questionnaire administration, electrocardiography, and echocardiography were performed by the same investigator – a senior paediatric cardiologist. EndoPat and assessment of carotid artery intima-media thickness were performed always by the same senior operators, with extensive experience, for each technique, and they were unaware of patient or control status.
Study subjects
This study included 43 adolescents and young adults with previous history of Kawasaki disease without coronary aneurysms, followed-up at our centre. The Kawasaki disease group included patients diagnosed with the disease at least 5 years earlier (mean±SD: 15.8±6.8 years) and aged more than 12 years (mean±SD: 19.1±6.8 years); 43 age- and sex-matched healthy controls (mean±SD: 18.9±5.4 years) with no previous history of cardiac disease comprised the control group.
All the study participants were Portuguese, caucasians, non-smokers, defined as individuals who had never smoked, were not born prematurely, and had no medical history of hypertension, hyperglycaemia, hypercholesterolaemia, or obesity, defined as body mass index >30 for adults or BMI >30 kg/m2 for adolescents under 20 years of age – ⩾95th percentile.Reference Cole, Bellizi and Flegal 35 In addition, they did not have a family history of hereditary diseases such as homocystinuria or familial hypercholesterolaemia.
All subjects in the Kawasaki group had the diagnosis of Kawasaki disease made in conformity with international guidelines,Reference Ayusawa, Sonobe and Uemura 36 and cardiovascular examination was performed by a paediatric cardiologist. The presence of coronary aneurysms was excluded in all patients; they were all discontinued from follow-up, at least 1 year after Kawasaki disease diagnosis, without symptoms or any cardiovascular sequelae.
The control group included healthy volunteers and normal subjects referred to the paediatric cardiology outpatient clinic because of asymptomatic heart murmur, chest pain, or other ill-defined symptoms, whose investigation excluded cardiac disease; all of them willingly took part in this study.
Investigation was deferred for at least 4 weeks in subjects with acute illnesses such as febrile illness or viral syndromes.
Study protocol
All subjects were advised against consuming food and drinks, except for water, overnight or for at least 12 hours, and against performing heavy exercise and consuming caffeine on the day before the examination.
We obtained the past history for Kawasaki disease in all subjects; we measured weight, height, and blood pressure automatically on the dominant arm in the sitting position using the oscillometric method after at least 15 minutes of resting. In total, three blood pressure measurements were obtained and the mean value was used. All subjects were coded before performing other techniques, so that the investigators would remain blinded to their condition.
Endothelial function was then assessed using Endo-PAT2000 (Itamar Medical Ltd, Cesarea, Israel) in a quiet examination room at 23–25°C before blood sampling for analysis. Venous blood samples were subsequently collected. EndoPat was repeated 3–4 weeks latter to assess reproducibility of this test.
After having breakfast, all subjects underwent echocardiography, electrocardiogram, and bilateral carotid ultrasound examination.
Assessment of endothelial function
The Endothelial Pulse Amplitude Test (EndoPAT) is a CE (Conformité Européenne) mark-approved device that analyses reactive hyperaemia after compression of the non-dominant arm. This technique has been validated in adults and in different paediatric groups. The cut-off value of 1.67 indicates dysfunction for lower values. It has been demonstrated that lower Endo-PAT index is associated with increased cardiovascular risk.Reference Kuvin and Karas 37 – Reference Pinto, Laranjo and Paramés 40
The participants rested in the supine position with both hands at the same level. Specific finger probes for recording pulse amplitude volume curves were placed on the index finger of each hand, and a blood pressure cuff was placed on the non-dominant upper arm (study arm), whereas the other arm served as a the control (control arm). After continuous recording of the pulse amplitude volume curves signal from both hands for 10 minutes, the blood pressure cuff on the study arm was inflated to whichever pressure would be higher, 200 or 60 mmHg plus systolic blood pressure, for 5 minutes. The blood pressure cuff was then rapidly deflated to induce hyperaemia in the study arm while the pulse amplitude volume curves signal continued to be recorded for 10 minutes. Data were analysed automatically by the software of the device. In brief, the reactive hyperaemia index was calculated as the ratio of the average amplitude of pulse amplitude volume curves signal over 1-minute time interval, starting 90 seconds after cuff deflation, over the average amplitude of the PAT signal of the 210-second period before cuff inflation (baseline), which was then multiplied by a baseline correction software factor. Reactive hyperaemia index values from the study arm were then normalised to the control arm, in order to compensate for potential systemic changes. A reactive hyperaemia index value ⩽1.67 was used as the cut-off to diagnose endothelial dysfunction. We have demonstrated previously the feasibility, safety, and reproducibility of this test in adolescents with Kawasaki disease and normal controls.Reference Pinto, Laranjo and Paramés 40
Assessment of arterial stiffness
Arterial stiffness was measured using the augmentation index obtained during EndoPat examination. Augmentation index is defined as an increment in pressure after the first systolic shoulder to the peak of aortic pressure and is expressed as a percentage of aortic pulse pressure. Pressure sensors within this particular finger probe capture the beat-by-beat finger pulse wave amplitude, which is then filtered, amplified, and graphically displayed on a computer screen. A computerised algorithm was generated to automatically identify peak pressures and the inflection point. The augmentation index is calculated by averaging the pulse wave amplitude data over a period of 210 seconds, and is defined as the difference between the second and the first systolic peaks expressed as a percentage of the pulse pressure. The augmentation index adjusted to 75 beats/minute was calculated by adjusting the augmentation index to a 75 beats/minute variable, as this measurement is influenced by heart rate. Both variables are still considered exploratory, and the results are analysed according to this view.
Blood sampling and analysis
Fasting total cholesterol, HDL cholesterol, LDL cholesterol and triglyceride levels as well as glucose and C-reactive protein levels were collected on the day of the visit after the vascular tests were completed.
Carotid ultrasound
Carotid ultrasound examination of both carotid arteries was performed to assess the thickness of the intima-media portion of the carotid artery as a marker of structural changes of the arterial wall. An increased carotid arterial intima-media thickness has been reported as a surrogate marker of early-onset atherosclerosis.Reference Wang, Wu and Liu 4
The study was performed with a high-resolution, B-mode system equipped with a high-frequency, linear-phased array transducer (Acusson Sequoia echocardiography system C512, probe: 15 MHz–15 L8; Siemens). Measurements were performed by two senior operators, blinded to subjects diagnosis.
Subjects were allowed to rest in the supine position with slight contralateral hyperextension and lateral rotation of the neck. A clear three-lead electrocardiographic signal was simultaneously obtained. The probe was positioned laterally to obtain the best resolution image of the lumen–intima interface. Common carotid bifurcation and the proximal segment of the artery until the carotid sinus were identified in a longitudinal B-mode plane. The carotid arterial intima-media thickness measurements were obtained at the far wall of the common carotid at least in 1 cm segment at the distal end of the common carotid artery, according to the recommendations of the American Society of Echocardiography.Reference Roman, Naqvi and Gardin 41 , Reference Touboul, Hennerici and Meairs 42
The right common carotid artery and the left common carotid artery were examined, and the frames were digitally recorded. Measurements were performed offline with a semi-automatic software (SingoDynamics, Siemens, Munich, Germany); they included carotid arterial intima-media thickness means, maximums, and standard deviation. Whenever necessary, the automatic detected contour of the arterial wall was corrected manually. We also evaluated the presence of atherosclerotic plaques, defined as a focal thickness of ⩾50% of the adjacent wall or ⩾1.5 mm, or abnormalities of flow.
Statistical analysis
Patient characteristics including lipid profile and vascular variables were compared with the control group. Primary end points were EndoPat indices and carotid arterial intima-media thickness. Data were analysed using SPSS 20.0 software (SPSS, Chicago, Illinois, Unites States of America). Discrete variables are presented as frequency (percentage) or means±standard deviation. The normal distribution of variables was examined using the Shapiro–Wilk’s test. To compare them, between the Kawasaki disease group and the control group, Student’s t-test was used when normality was confirmed or the Mann–Whitney test when they did not follow a normal distribution. The analysis of categorical variables was performed using the χ2-test. If the expected frequency was lower than 5, Fisher’s exact test was utilised. A multivariate regression analysis was used to determine the relationship between reactive hyperaemia index and carotid arterial intima-media thickness, indicative of disease and the different factors including the variables that were found to be statistically significant in the bivariate analysis or the clinical impact of which had been verified in previous studies, such as age, weight, body mass index, lipid profile, and elevated C-reactive protein. A p value of <0.05 was considered statistically significant, for a confidence interval of 95%; the p values presented were not adjusted for multiple comparisons.
Results
Clinical characteristics
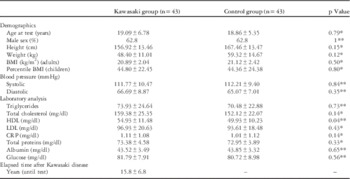
Kawasaki disease and control group patients did not differ significantly with regard to gender, age, weight, height, body mass index, and blood pressure. Both groups also had similar medical history, cardiovascular risk factors, and laboratory profile, including lipids, proteins, and C-reactive protein levels (Table 1), with no statistical significance in the univariate or multivariate analysis. There was a trend towards increased lipid profile levels in the Kawasaki disease group, with higher triglycerides (73.93 mg/dl [with a range from 143 to 24 mg/dl] versus 74.48 mg/dl [with a range from 140 to 32 mg/dl], p 0.73), total cholesterol (159.38 mg/dl [with a range from 187 to 111 mg/dl] versus 152.12 mg/dl [with a range from 178 to 110 mg/dl], p 0.14), HDL cholesterol (54.93 mg/dl [with a range from 74 to 36 mg/dl] versus 49.93 mg/dl [with a range from 69 to 30 mg/dl], p 0.04), and LDL cholesterol (96.93 mg/dl [with a range from 126 to 52 mg/dl] versus 93.61 mg/dl [with a range from 126 to 58 mg/dl], p 0.43). The only value with weak statistical significance was HDL cholesterol (p=0.04).
Descriptive variables.

BMI=body mass index; CRP=C-reactive protein
Values are means±standard deviation
* Mann–Whitney U-test
** Student’s t-test
All subjects had normal electrocardiograms and echocardiographic evaluation.
Kawasaki disease history
Patients in the Kawasaki disease group had the disease at 3.90±2.03 years of age (with a range from 7.4 to 0.4 years). The elapsed time between the acute episode and the present study was 15.8±6.8 years (with a range from 28 to 6 years), free of disease, and there were no relapses.
The vast majority of the patients had typical Kawasaki disease (95%), only two patients had the atypical form, all patients had the diagnosis according to established diagnostic criteria, and all had cardiovascular screening on the 1st day of diagnosis and on follow-up. On cardiac evaluation, 35 patients had normal coronary arteries and eight children (18.6%) had transient dilatation (Z-score <3), which returned to normal in about 1 month. Intravenous immunoglobulin was administered to 38 patients (88.4%) at an average of 7 days (with a range from 2 to 15 days) from fever onset. All patients were medicated with aspirin for 6 months, and cardiac follow-up was maintained for an average of 11 months (with a range from 8 to 21 months).
Endothelial function
The Endothelial Pulse Amplitude Test (EndoPAT) was performed and repeated; the results demonstrated their reproducibility without statistically significant differences between them in both groups: Kawasaki disease patients had a mean reactive hyperaemia index of 1.59±0.45 and 1.62±0.41 (first and second assessment, respectively), whereas control group had mean values of 1.98±0.41 and 2.01±0.43, (Table 2). There was a good correlation between both studies (Pearson’s correlation 0.958, p value <0.001).
EndoPat results.

AIx=Augmentation Index; AIx@75=Augmentation Index referred to 75 beats/minute; RHI=Reactive Hyperaemia Index
Values are means±standard deviation
* Mann–Whitney U-test
** Student’s t-test
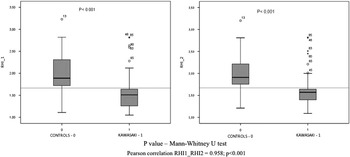
Endothelial dysfunction was found in the majority (n=34; 79.06%) of Kawasaki disease patients, when compared with a significantly lower percentage of control subjects (n=8; 18.60%). There were significant group differences in pulse wave amplitude-derived reactive hyperaemia index, with Kawasaki disease patients having a significantly lower reactive hyperaemia index when compared with the control group (1.59 and 1.62 versus 1.98 and 2.01; p<0.001) (Fig 1).
Box plots of reactive hyperaemia index (RHI) testing in Kawasaki disease patients and controls using Mann–Whitney U-test. The red line represents the cut-off value of 1.67 for RHI (normal endothelial function RHI>1.67).

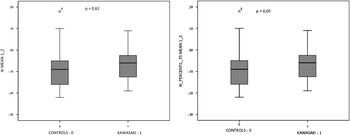
Pulse wave amplitude-derived augmentation index in both measurements were within the normal range and similar for both groups (−4.5±7 and −4±8 versus −5±9 and −4.5±9% p 0.61 and p 0.63 for Kawasaki and controls group, respectively) with no statistical significance; the same results were obtained for the augmentation index adjusted to 75 beats/minute (Table 2).
Carotid intima-media thickness
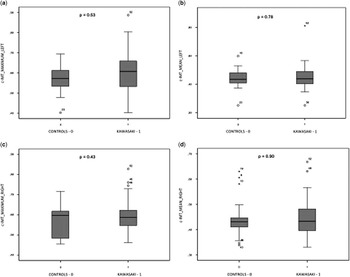
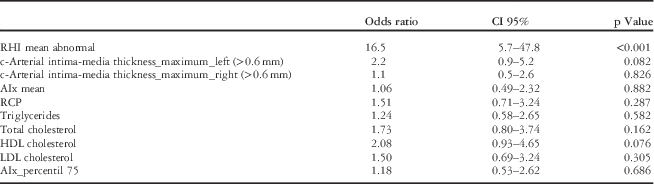
The maximum carotid arterial intima-media thickness results were slightly higher for the Kawasaki disease patients, but without significance (left common carotid artery maximum: 0.587±0.100 versus 0.575±0.065; p 0.22; right common carotid artery maximum: 0.598±0.082 versus 0.574±0.074; p 0.34), whereas the carotid arterial intima-media thickness mean values were similar for both groups, (left common carotid artery mean: 0.447±0.088 versus 0.443±0.059; p 0.93; right common carotid artery mean: 0.441±0.073 versus 0.438±0.058; p 0.89) (Table 3). There were some outliers for these values in both groups; nevertheless, when we excluded the outliers, there was no change in the significance. We also found that 97.7 and 95.3% of subjects in the Kawasaki and control group, respectively, had mean carotid arterial intima-media thickness values under 6 mm. No plaques or flow abnormalities were identified in either group by carotid ultrasound imaging (Figs 2 and 3). In the multivariate analysis, the main factor associated with Kawasaki disease was an abnormal reactive hyperaemia index (odds ratio=16.5; 95% confidence interval, 5.7-47.8; p<0.001) (Table 4).
Box plots of the mean of two measurements of augmentation indices (AI and AI_Percentil_75) testing in Kawasaki disease patients and controls.

Box plots of left and right maximum ( a and b ) and mean ( c and d ) carotid intima-media thickness (c-arterial intima-media thickness) values in Kawasaki disease patients and controls.

Right and left common carotid intima-media thickness (c-arterial intima-media thickness) measurements.

Values are means±standard deviation
* Mann–Whitney U-test
** Student’s t-test
Discussion
Kawasaki disease occurs worldwide as both endemic and community-based epidemic forms in children of all races. It is a medium-vessel vasculitis with predominant involvement of the coronary arteries. The search for an aetiological agent has been wide ranging. Kawasaki disease is accompanied by significant derangements in the immunoregulatory systemReference Rowley 3 – Reference Duong, Silverman and Bissessar 5 that lead to coronary inflammation and disruption with dilatation and aneurysm formation. Endothelial cell damage appears to occur as a result of this increased immune activity.
The long-term prognosis of Kawasaki disease, particularly in patients with normal coronary arteries, mild dilatation, or regressed coronary aneurysms, remains uncertain at present. Several authors have demonstrated that 50% of aneurysms regress within several years with a normal angiographic lumen;Reference Kato, Sugimura and Akagi 6 , Reference Mitani, Sawada and Hayakawa 10 however, histological studies and intra-coronary ultrasound examinations have demonstrated persistent abnormal arterial walls with marked thickening of intima, which may be caused by the proliferation of smooth muscle cells.Reference Iemura, Ishii and Sugimura 12 , Reference Yamakawa, Ishii and Sugimura 15
Besides these morphological abnormalities, it has also been demonstrated that Kawasaki disease has a deleterious effect on coronary artery function, years after the acute presentation, particularly in patients with persistent coronary artery aneurysms when compared with control subjects.Reference Kato, Sugimura and Akagi 6 , Reference Iemura, Ishii and Sugimura 12 , Reference Burns, Shike and Gordon 14 , Reference Yamakawa, Ishii and Sugimura 15 Abnormal coronary flow reserve has been demonstrated in Kawasaki disease patients with transiently dilated coronary arteriesReference Furuyama, Odagawa and Katoh 17 and in those without antecedent coronary artery dilation or ischaemia.Reference Hamaoka, Onouchi and Ohmochi 43 , Reference Hauser, Bengel and Kuehn 44
Abnormalities in endothelial function,Reference Mitani, Sawada and Hayakawa 10 , Reference Dhillon, Clarkson and Donald 11 , Reference Yamakawa, Ishii and Sugimura 15 , Reference Ikemoto, Ogino and Terguchi 18 , Reference Noto, Okada and Yamasuge 19 , Reference Pinto, Laranjo and Paramés 40 arterial stiffness,Reference Cheung, Wong and Ho 45 – Reference Mitani, Okuda and Shimpo 47 and carotid intima-media thickness have also been observed.Reference Meena, Rohit and Gupta 33 , Reference Lee, Ahn and You 34 , Reference Dalla Pozza, Bechtold and Urschel 48 Nevertheless, controversy persists, and other studies have failed to demonstrate those findings.Reference McCrindle, McIntyre and Kim 8 , Reference Tierney, Gal and Gauvreau 49 This uncertainty about long-term vascular function of Kawasaki disease patients without history of coronary abnormalities is also reflected on different guidelines approach on lifelong follow-up of these patients.Reference Newburger, Takahashi and Gerber 50 , Reference Newburger, Takahashi and Gerber 51
Understanding the long-term vascular function in Kawasaki disease patients is an important issue, because its presence might represent ongoing inflammatory reaction and can preclude increased cardiovascular risk and the need for serial long-term cardiac follow-up.Reference Burns, Shike and Gordon 14 , Reference Silva, Maeno and Hashmi 16 – Reference Vita and Keaney 22 , Reference Lee, Ahn and You 34 , Reference Dalla Pozza, Bechtold and Urschel 48 , Reference Gersony 52 , Reference Gordon, Kahn and Burns 53 In addition, considering that endothelium dysfunction is involved in the atherosclerotic process, this raises questions about similar pathological pathways.Reference Ross 20 – Reference Vita and Keaney 22 , Reference Deanfield, Halcox and Rabelink 27 ,54
In this study, we found significant late endothelial dysfunction but absence of increased stiffness or increased carotid intima-media thickness in the majority of Kawasaki disease patients when compared with matched controls. The endothelial-dependent microvascular relaxation abnormality may be a consequence of ongoing systemic inflammatory process with sequelar damaged endothelium. The finding of normal c-arterial intima-media thickness on both carotid arteries and the absence of differences between the two groups are consistent with the absence of subclinical atherosclerotic changes, but we can speculate that the observed histological changes in the arterial walls of Kawasaki disease patients might take longer time to evolve to atherosclerotic changes.Reference Meena, Rohit and Gupta 33 , Reference Lee, Ahn and You 34 , Reference Dalla Pozza, Bechtold and Urschel 48
Investigation of vascular function in Kawasaki disease patients has recently been revived with a number of similar studies published in the literature. Most of these studies were conducted in children with Kawasaki disease having coronary artery aneurysms. Noto et alReference Ross 20 found an increase in carotid arterial intima-media thickness, in both children and adults, late after the acute disease in patients with coronary artery lesions. Cheung et alReference Cheung, Wong and Ho 45 have speculated that the increased carotid arterial intima-media thickness in Kawasaki disease patients without coronary involvement was associated with increased systemic arterial stiffness; our study demonstrates the opposite, as we did not find a significantly increased augmentation index, a measure of arterial stiffness, or significantly increased carotid intima-media thickness, and we speculate this can represent different genetic polymorphisms.
The consistency of endothelial dysfunction, in this study, is in line with the one from Dhillon et al,Reference Dhillon, Clarkson and Donald 11 which demonstrated abnormal flow-mediated dilation of the brachial artery in 20 male subjects, who were studied 5–17 years after the onset of Kawasaki disease, irrespective of whether they had developed aneurysms during the acute phase. Endothelial dysfunction was also reported by Deng et al and Dalla Pozza et alReference Dalla Pozza, Bechtold and Urschel 48 in some children with Kawasaki disease, but without coronary artery aneurysms. Our study adds evidence to these findings and suggests that the occurrence of Kawasaki disease may have lifelong consequences even when there is no coronary artery involvement. This issue, however, is rather controversial. Studies performed in Japanese subjects, of identical characteristics, reported abnormal flow-mediated dilation only in patients who had developed coronary artery aneurysms during the acute stage of Kawasaki.Reference Noto, Okada and Yamasuge 19 , Reference Kadono, Sugiyama and Hoshiai 26 A Canadian study of 52 Kawasaki disease patients concluded that there was no evidence of long-term endothelial cell dysfunction late after Kawasaki disease onset.Reference McCrindle, McIntyre and Kim 8 A recent American study demonstrated that a mixed population of Kawasaki disease patients with and without coronary abnormalities had normal vascular health 1 year after the Kawasaki disease episode.Reference Tierney, Gal and Gauvreau 49 It is unclear whether these conflicting results reflect methodological issues or are best explained by genetic differences of the studied populations.
Children with Kawasaki disease, with or without coronary artery lesions, seem to have a more adverse cardiovascular risk profile, which requires lifelong cardiac assessment and counselling, either sporadic or serial. Whether this is a cause or a consequence of an abnormal endothelial function has not yet been assessed. We also failed to demonstrate premature or subclinical atherosclerotic changes with the used methodology. What is noteworthy is the fact that, in our sample, almost 79% of Kawasaki disease patients had endothelial dysfunction, when compared with only 17% of the control subjects.
These findings suggest that children with Kawasaki disease may have long-term sequelae, even when there is no discernible coronary artery involvement in the acute stage of the disease. Affected children should therefore be kept on long-term follow-up and counselled to reduce cardiovascular risk factors such as sedentary lifestyle, overweight, high-lipid and high-caloric meals, and alcohol or tobacco use. Further research is needed to assess whether known strategies to improve endothelial function would bring potential benefits to Kawasaki disease patients.
Logistic regression: calculated odds ratio value.

AIx=augmentation index; CI=confidence interval; RHI=reactive hyperaemia index; RCP=C-reactive protein
Acknowledgements
The authors thank Lurdes Medroa for her contribution in performing the EndoPat studies and Helena Aidos for the statistical analysis.
Financial Support
This research received no specific grant from any funding agency or from commercial or not-for-profit sectors.
Conflicts of Interest
None.
Ethical Standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national guidelines on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008, and has been approved by the institutional committees.