Relief of right ventricular outflow tract obstruction in tetralogy of Fallot or similar physiology often results in pulmonary regurgitation. The resultant chronic volume overload can lead to right ventricular dilatation, biventricular dysfunction, heart failure symptoms, arrhythmias, and sudden death.Reference Murphy, Gersh and Mair 1 – Reference Bouzas, Kilner and Gatzoulis 5 Pulmonary valve replacement can lead to improvement in functional class and a substantial decrease or normalisation of right ventricular volumes.Reference Cheung, Wong and Cheung 6 , Reference Geva, Gauvreau and Powell 7 However, there are some unsolved problems related to pulmonary valve replacement in patients with chronic pulmonary regurgitation. These include ideal valve substitute for pulmonary valve replacement and optimal timing of pulmonary valve replacement in asymptomatic patients. This article reviews evidence-based benefits and risks of pulmonary valve replacement, options for pulmonary valve substitute, and optimal timing of pulmonary valve replacement in patients with chronic pulmonary regurgitation after relief of right ventricular outflow tract obstruction.
Benefits and risks of pulmonary valve replacement
Most studies dealing with pulmonary valve replacement in patients with chronic pulmonary regurgitation have consistently reported subjective improvements in functional class.Reference Dave, Buechel and Dodge-Khatami 8 – Reference Scherptong, Hazekamp and Mulder 12 However, there are conflicting results regarding objective improvements in exercise capacity as assessed by cardiopulmonary exercise test. Ghez et alReference Ghez, Tsang and Frigiola 13 reported that although most patients showed clinical improvement after pulmonary valve replacement, maximal exercise capacity as assessed by maximal oxygen consumption did not improve after pulmonary valve replacement. Frigiola et alReference Frigiola, Tsang and Bull 10 have also found that there was no improvement in maximal oxygen consumption after pulmonary valve replacement. However, they reported that ventilatory response to carbon dioxide production at anaerobic threshold improved after pulmonary valve replacement and normalisation of ventilatory response to carbon dioxide production was most likely to occur when pulmonary valve replacement was performed at an age younger than 17.5 years.
Magnetic resonance imaging has emerged as a gold standard for evaluating right ventricular volumes and function in patients with pulmonary regurgitation. Numerous studies using magnetic resonance imaging have confirmed a substantial decrease or normalisation of right ventricular volumes after pulmonary valve replacement.Reference Geva, Gauvreau and Powell 7 – Reference Frigiola, Tsang and Bull 10 Oosterhof et al,Reference Oosterhof, van Straten and Vliegen 9 in a study of 71 patients with repaired tetralogy of Fallot, showed a decrease in right ventricular volumes of approximately 30% after pulmonary valve replacement and reported that they could not find a threshold above which right ventricular volumes did not decrease after surgery. There is a question of whether the reported decrease in right ventricular volumes after pulmonary valve replacement is merely the result of surgical right ventricular reduction – resection or plication of right ventricular outflow tract aneurysm. Although surgical right ventricular reduction at the time of pulmonary valve replacement can possibly result in a greater relative decrease in right ventricular volumes, substantial decrease in right ventricular volumes was also noted in patients who did not undergo surgical right ventricular reduction.Reference Oosterhof, van Straten and Vliegen 9
Although pulmonary valve replacement can consistently lead to a substantial decrease of right ventricular volumes, improvement in right ventricular systolic function has not been uniformly demonstrated. Studies reporting no improvement of right ventricular function enrolled patients with already depressed right ventricular function, whereas studies reporting improvement in right ventricular function enrolled patients with preserved right ventricular function.Reference Geva, Gauvreau and Powell 7 , Reference Frigiola, Tsang and Bull 10 , Reference Ghez, Tsang and Frigiola 13 – Reference Harrild, Berul and Cecchin 16 This implies that pulmonary valve replacement should be performed before irreversible right ventricular dysfunction occurs. Some authors have advocated the use of corrected right ventricular ejection fraction – calculated after excluding the volume of pulmonary regurgitation – to demonstrate improvement in right ventricular function after pulmonary valve replacement.Reference Vliegen, van Straten and de Roos 17
There have also been conflicting results regarding the impact of pulmonary valve replacement on QRS duration and arrhythmia propensity, and this also might be due to the different characteristics of the patients enrolled in the studies. Studies reporting no change of QRS duration enrolled patients with relatively longer baseline QRS duration or larger right ventricular volumes compared with those reporting improvement in QRS duration.Reference Oosterhof, van Straten and Vliegen 9 , Reference Harrild, Berul and Cecchin 16 , Reference Therrien, Siu and Harris 18 – Reference Gengsakul, Harris and Bradley 20 This implies that timely pulmonary valve replacement before severe right ventricular dilatation occurs may have a beneficial effect on QRS duration.
Currently, there are no published data showing a clear long-term survival gain of pulmonary valve replacement. Gengsakul et al,Reference Gengsakul, Harris and Bradley 20 in a matched comparison study, reported that there was no difference regarding the composite outcome of death and ventricular tachycardia between patients who had undergone pulmonary valve replacement and patients who had not undergone pulmonary valve replacement. Recently, Harrild et alReference Harrild, Berul and Cecchin 16 also reported similar results. Long-term follow-up results of carefully designed studies are mandatory to draw a definitive conclusion on this important issue.
Benefits of pulmonary valve replacement have to be weighed against the risks of this procedure. Currently, pulmonary valve replacement can be performed with low operative mortality. Cheung et al,Reference Cheung, Wong and Cheung 6 in a meta-analysis of pulmonary valve replacement after repair of tetralogy of Fallot, reported that the pooled early mortality rate was 2.1% (95% confidence interval 1.1–4.0%). The majority of patients experience an uncomplicated post-operative course, although post-operative morbidities are not negligible.Reference Dos, Dadashev and Tanous 21 Most importantly, patients are exposed to the risk of repeat pulmonary valve replacement and this is a weak facet in determining the optimal timing of pulmonary valve replacement.
Options for pulmonary valve substitute
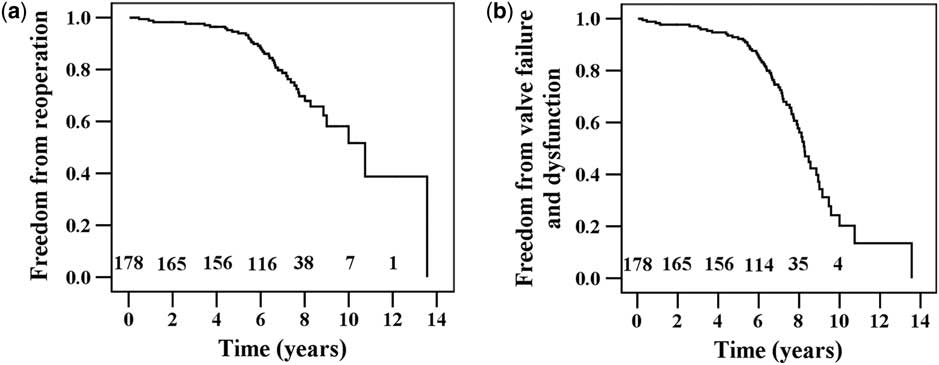
There are several options for pulmonary valve substitute, including bioprostheses, homografts, mechanical valves, and hand-sewn polytetrafluoroethylene valves. Among these, bioprosthetic valves are probably the most widely used, because they are readily available and they do not need permanent anticoagulation therapy. However, most of these bioprostheses will eventually fail and require replacement mainly owing to structural valve deterioration, more specifically leaflet calcification. Although modern design technique and anticalcification treatments applied to currently available bioprosthetic valves have greatly improved the durability of bioprostheses implanted into adult patients,Reference Borger, Ivanov, Armstrong, Christie-Hrybinsky, Feindel and David 22 , Reference McClure, Narayanasamy and Wiegerinck 23 dystrophic calcification leading to early bioprosthetic valve failure is still a great problem in children and young adults. A dominant risk factor predictive of early bioprosthetic pulmonary valve failure is younger age at the time of initial pulmonary valve replacement, as reported in previous studies.Reference Discigil, Dearani and Puga 24 , Reference Caldarone, McCrindle and Van Arsdell 25 Currently, the exact cause and mechanism of an accelerated bioprosthetic valve failure in children are not completely understood. Traditionally, active calcium metabolism of rapidly growing children has been regarded as a culprit. Recently, however, some evidences suggest that the greater immune system competence of children and young adults may contribute to an accelerated bioprosthetic valve failure.Reference Konakci, Bohle and Blumer 26 – Reference Lee, Ahn, Kim, Choi and Kim 28 In our recent study of 181 patients who underwent pulmonary valve replacement using bioprostheses, we reported that although bioprosthetic pulmonary valve function was maintained stable until 5 years after pulmonary valve replacement, approximately 80% of the patients would require reoperation or manifest valve dysfunction by 10 years (Fig 1).Reference Lee, Park and Lee 29 We also found that younger age at the time of pulmonary valve replacement was a risk factor for shorter time to repeat pulmonary valve replacement.
Durability of the bioprosthetic valves in the pulmonary position. ( a ) Overall freedom from reoperation and ( b ) overall freedom from both prosthetic valve failure and dysfunction.

Some centres prefer homograft as a valve substitute for pulmonary valve replacement. However, homograft has a drawback of limited availability and also fails in the long term. van de Woestijne et al,Reference van de Woestijne, Mokhles, de Jong, Witsenburg, Takkenberg and Bogers 30 in a recent study of pulmonary valve replacement using homograft after repair of tetralogy of Fallot, reported that freedom from redo pulmonary valve replacement was 70% at 15 years. Oosterhof et alReference Oosterhof, Meijboom and Vliegen 31 reported that freedom from homograft dysfunction was 47% at 10 years.
There are limited experiences about implanting mechanical valve in the pulmonary position.Reference Shin, Kim, Ko, Park and Seo 32 – Reference Stulak, Dearani and Burkhart 34 Although mechanical pulmonary valves can be expected to be more durable than bioprosthetic valves and homografts, permanent anticoagulation carries the inherent risk of serious bleeding events and can impair the quality of life in children and young adults. Currently, it seems reasonable that mechanical pulmonary valve replacement can be considered in highly selected patients with multiple prior operations or another need for anticoagulation such as presence of a mechanical valve in other positions.
In an effort to overcome the limited durability of bioprosthetic valves in the pulmonary position, Quintessenza et alReference Quintessenza, Jacobs, Morell, Giroud and Boucek 35 , Reference Quintessenza 36 at The Congenital Heart Institute of Florida (CHIF) introduced a new method of implanting bicuspid pulmonary valve using polytetrafluoroethylene material. Their rationale for the development of this technique was based on favourable experimental and clinical results of polytetrafluoroethylene monocusp valve.Reference Brown, Ruzmetov, Vijay, Rodefeld and Turrentine 37 In the earlier part of their experience, they used polytetrafluoroethylene material with 0.6 mm thickness and experienced a few cases of redo pulmonary valve replacement because of immobile and calcified leaflets.Reference Quintessenza, Jacobs, Chai, Morell and Lindberg 38 Freedom from redo pulmonary valve replacement of this valve was approximately 70% at 8 years.Reference Quintessenza, Jacobs, Chai, Morell and Lindberg 38 Currently, they are using polytetrafluoroethylene membrane with 0.1 mm thickness anticipating improved valve durability owing to the non-porous nature of this material, which does not allow cellular in-growth and thickening. At The Congenital Heart Institute of Florida (CHIF), three generations of bicuspid valves made of polytetrafluoroethylene membrane have been used. Generation 1 was made with 0.6-mm polytetrafluoroethylene and hand sewn into the right ventricular outflow tract. The first Generation 1 valve was inserted on December, 8, 2000, and 84 total valves have been inserted. Generation 2 is made with 0.1-mm polytetrafluoroethylene and hand sewn into the right ventricular outflow tract. The first Generation 2 valve was inserted on May, 12, 2006, 2000, and 74 total valves have been inserted. Generation 3 is made with 0.1-mm polytetrafluoroethylene and hand sewn into a polytetrafluoroethylene tube that is then used to connect the right ventricular outflow tract to the pulmonary circulation. The first Generation 3 valve was inserted on November, 6, 2009, and 43 total valves have been inserted.
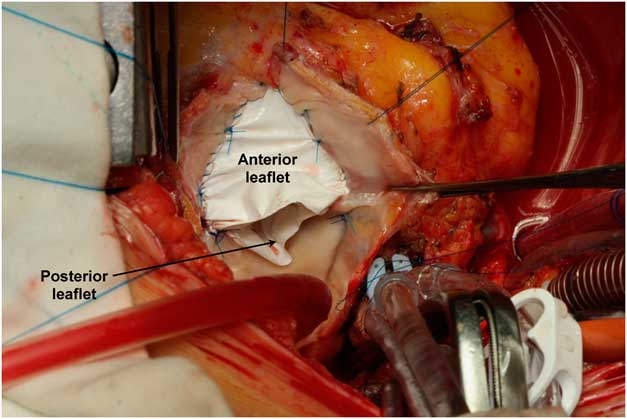
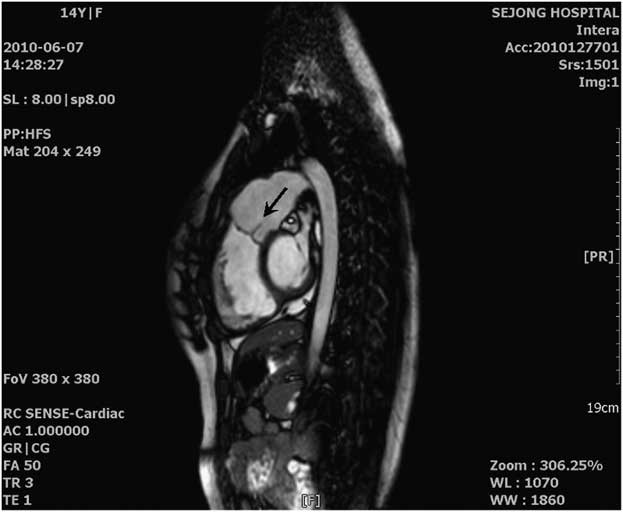
Recently, Lee et alReference Lee, Lee and Kwak 39 also started to put this bicuspid valve made of polytetrafluoroethylene membrane with 0.1 mm thickness in the pulmonary position (Fig 2) and reported promising early results of this technique. In our experience (Lee et al), this valve demonstrated excellent performance for the short term as evidenced by echocardiography and magnetic resonance imaging (Fig 3). Certainly, long-term follow-up of this valve is mandatory to determine the true value of this new technique.
Implanted bicuspid pulmonary valve made of polytetrafluoroethylene membrane with 0.1 mm thickness.

Magnetic resonance image showing good coaptation (arrow) of the polytetrafluoroethylene bicuspid pulmonary valve. The pulmonary regurgitation fraction of this valve was 7%.

Timing of pulmonary valve replacement
Pulmonary valve replacement is clearly indicated when symptoms or decreased exercise tolerance attributable to pulmonary regurgitation are present. However, there is no detailed consensus to guide optimal timing of pulmonary valve replacement in the asymptomatic patients with repaired tetralogy of Fallot and significant pulmonary regurgitation. The guidelines from the American College of Cardiology/American Heart Association state that pulmonary valve replacement is reasonable in patients with severe pulmonary regurgitation in association with moderate to severe right ventricular dysfunction or enlargement.Reference Warnes, Williams and Bashore 40 However, the specific thresholds for “moderate to severe right ventricular dysfunction or enlargement” have not been defined.
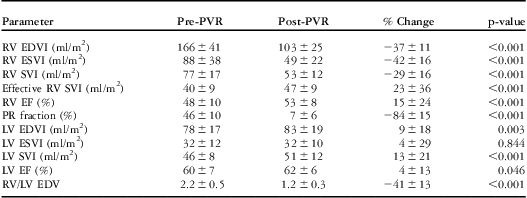
If pulmonary valve replacement can be performed with negligible mortality and morbidity, and durable prosthetic valves are available, pulmonary valve replacement should be recommended as early as possible for all patients with dilated right ventricle. However, because this is not the case, we should decide the “upper threshold” or “point of no return” to which point we can delay pulmonary valve replacement and above which optimal outcome cannot be expected after pulmonary valve replacement. Therrien et alReference Therrien, Provost, Merchant, Williams, Colman and Webb 14 reported this “point of no return” for the first time. They found that in no patients with a right ventricular end-diastolic volume index exceeding 170 ml/m2 or a right ventricular end-systolic volume index exceeding 85 ml/m2 before pulmonary valve replacement were right ventricular volumes “normalised” after surgery. Oosterhof et alReference Oosterhof, van Straten and Vliegen 9 reported that normalisation of right ventricular volumes could be achieved when pre-operative right ventricular end-diastolic volume index was less than 160 ml/m2 or right ventricular end-systolic volume index was less than 82 ml/m2. Geva et alReference Geva, Gauvreau and Powell 7 reported that right ventricular end-systolic volume index of <90 ml/m2 was associated with optimal outcome – normal right ventricular size and function. Frigiola et alReference Frigiola, Tsang and Bull 10 suggested the most aggressive policy of performing pulmonary valve replacement when right ventricular end-diastolic volume index was <150 ml/m2. Recently, in a study of 170 patients who underwent pulmonary valve replacement for chronic pulmonary regurgitation, we found that optimal outcome – normalised right ventricular volumes and function – might not be achieved when pre-operative right ventricular end-diastolic volume index exceeded 163 ml/m2 or right ventricular end-systolic volume index exceeded 80 ml/m2.Reference Lee, Kim and Lee 41 In our study, post-operative magnetic resonance imaging showed significant reduction in right ventricular volumes and more importantly significant improvement in biventricular function (Table 1). What about the “lower threshold” above which we should consider pulmonary valve replacement? It definitely depends primarily upon the clinical status of an individual patient. In asymptomatic patients, Geva et alReference Geva 42 and Dave et alReference Dave, Buechel and Dodge-Khatami 8 recommended pulmonary valve replacement when right ventricular end-diastolic volume index exceeded 150 ml/m2.
Changes in magnetic resonance imaging parameters after PVR (n = 67).Reference Lee, Kim and Lee 41

EDV = end-diastolic volume; EDVI = end-diastolic volume index; EF = ejection fraction; ESVI = end-systolic volume index; LV = left ventricular; PR = pulmonary regurgitation; PVR = pulmonary valve replacement; RV = right ventricular; SVI = stroke volume index
Although many studies identified cut-off values of right ventricular end-diastolic volume index as an indication for pulmonary valve replacement, Geva et alReference Geva, Gauvreau and Powell 7 and Henkens et alReference Henkens, van Straten and Schalij 43 stressed the importance of right ventricular end-systolic volume index in determining the timing of pulmonary valve replacement. We have also found that higher pre-operative right ventricular end-systolic volume index was a sole independent risk factor for suboptimal outcome.Reference Lee, Kim and Lee 41 Other factors influencing timing of pulmonary valve replacement include moderate or severe tricuspid regurgitation, sustained tachyarrhythmia, severe branch pulmonary arterial stenosis, and large right ventricular outflow tract aneurysm.Reference Geva 42
Summary
Pulmonary valve replacement for patients with chronic pulmonary regurgitation after relief of right ventricular outflow tract obstruction can be performed safely with low operative mortality and morbidity. Pulmonary valve replacement in these patients consistently leads to improvement in functional class and a substantial decrease or normalisation of right ventricular volumes. Although currently there is no evidence showing a long-term survival benefit of pulmonary valve replacement, timely pulmonary valve replacement before severe right ventricular dilatation and/or dysfunction occurs may have a beneficial effect on right ventricular function and QRS duration, thus improving long-term survival. Suboptimal durability of currently used bioprosthetic valves is a weak facet in determining the optimal timing of pulmonary valve replacement. Although currently there is no detailed consensus to guide optimal timing of pulmonary valve replacement in asymptomatic patients, evidences that suggest the optimal timing of pulmonary valve replacement based on magnetic resonance imaging parameters are accumulating. Accordingly, the optimal timing of pulmonary valve replacement in asymptomatic patients will be further refined.