INTRODUCTION
Critically ill patients admitted to an intensive care unit (ICU) often have a prolonged hospital length of stay (LOS) and poor outcome (The SUPPORT Principal Investigators, 1995). Decisions to forgo life-sustaining treatments such as dialysis, mechanical ventilation, and use of vasopressors are among the most difficult for clinicians and surrogates to negotiate when these interventions become unlikely to succeed in reversing organ failure (The Society of Critical Care, 1992; Thelen, Reference Thelen2005; Lautrette et al., Reference Lautrette, Darmon and Megarbane2007). Many of these patients remain hospitalized and eventually die as a result of chronic critical illness, frequently with severe and undertreated pain. Those who survive often have diminished cognitive capacity and function (Selecky et al., Reference Selecky, Eliassaon and Hall2005).
When cure is no longer possible, technological interventions to extend life often serve only to prolong the dying process, resulting in suffering for patient and surrogate, and “moral distress” for staff (Elprern et al., Reference Elprern, Covert and Kleinpell2005). Cardiopulmonary resuscitation (CPR) was never intended to be used on patients dying an expected death from a terminal illness. Terminally ill patients are often subjected to non-beneficial CPR when they lack a Do Not Resuscitate (DNR) order (see Appendix). The “code” becomes a futile exercise, which often does not restore spontaneous circulation and serves only to prolong dying (Landry et al., Reference Landry, Parker and Phillips1992; Schultz et al., Reference Schultz, Cullinane and Pasquale1996). When the expected survival is measured in days to months, it may be appropriate to prioritize the quality of the patient's remaining time, to tend to relationships, and to provide treatment focused on the relief of pain and symptoms related to dying (Mularski et al., Reference Mularski, Heine and Osborne2005).
Specialized palliative medicine teams, in addition to providing expert symptom control, are particularly skillful at helping patients and families make the transition from cure to comfort. When death is the probable outcome, the palliative medicine team may clarify confusing and conflicting issues, and help patient and family establish clearer goals. Although palliative medicine teams appear to prove their value clinically, their effectiveness has not been well studied, especially in the MICU setting (Gruenberg et al., Reference Gruenberg, Shelton and Rose2006).
We evaluated the effect of a full-time palliative medicine consultation team on a group of patients in the MICU in comparison to a control group that did not receive a palliative medicine consultation on overall hospital LOS (time until death), DNR designation at death, withdrawal of mechanical ventilation (terminal wean), as well as patient demographics. For critically ill MICU patients, these parameters may be surrogates for better care of the dying patient.
METHOD
The study population consisted of two retrospective cohorts of patients admitted to the North Shore University Hospital, Manhasset Medical ICU (MICU). North Shore University Hospital (NSUH), in Manhasset, New York, is an 849-bed academic tertiary care hospital in a 15-hospital healthcare system. There are 85 adult ICU beds. Approximately 1,200 patients are admitted annually to the 17-bed MICU.
The historical control group, composed of patients admitted to the MICU between January 1, 2003 and June 30, 2004 (prior to the existence of a Palliative Medicine Consultation Service) were compared to MICU patients who received a palliative consultation from January 1, 2005 through June 1, 2009. Only patients in both cohorts who died during their hospitalization were considered for this study. The Palliative Medicine Service began providing consultations for MICU patients as of January 1, 2005. Therefore, the time span for the intervention group coincided with the introduction of palliative medicine consultation in the MICU. As the implementation of the consultative protocol did not change routine practice, and the study merely involved collection of retrospective data without compromise of patient confidentiality, the requirement for informed consent was waived by the Institutional Review Board (IRB).
Study Design
Following IRB approval, data were analyzed for both groups regarding the following: (1) patients' time until death (LOS) from time of hospital admission and MICU admission; (2) Acute Physiology and Chronic Health Evaluation III (APACHE III) score; (3) DNR designation at death; (4) respiratory failure requiring mechanical and ventilator withdrawal (terminal wean); and (5) location of death.
The control and intervention groups had clinically comparable APACHE III characteristics, with the intervention median score equal to 94, and the control median score equal to 98. To attempt to “match” severity, only patients in both groups who died in hospital were studied in both groups. The intervention group received a palliative care consultation at any point during their MICU stay.
Consultation was requested for patients deemed likely to benefit from palliative care by members of the MICU interdisciplinary team. Prior to the intervention, information was gathered from the medical record, laboratory review of radiographic findings, and collaboration with the MICU team. The setting in which the intervention took place was a private family conference room located immediately outside the MICU, where members of the palliative care team, led by the palliative medicine attending physician, and the MICU bedside nurse and medical resident, were introduced to the legal surrogates. Occasionally, the MICU social worker would join the meeting. The primary intervention is a structured consultation with the patient's family or other surrogate (and with the patient, when possible) regarding history, diagnosis, prognosis, treatment options, and patient preferences for end-of-life care. Scripted discussions, which generally lasted 30 minutes, were opened by greetings and introductions, followed by an open-ended conversation with the family about what they had been previously told about the patient's situation. Medical facts and treatment options were discussed in light of patient preferences and goals of care. Advanced directives, including DNR status, were clarified to reflect patient or legal surrogate wishes. The meetings concluded with a summary of the plan of care and scheduling of the next follow-up meeting.
Statistical Methods
Continuous variables (age, APACHE III) were compared between the two groups using the Mann–Whitney test (a nonparametric counterpart to the two sample t test). Categorical variables, such as gender, DNR status at death, and the request to forgo mechanical ventilation were compared with the χ2 test.
The distribution of “time until death” and hospital and MICU LOS were estimated using the Kaplan–Meier product-limit method, and were compared using the log-rank test. In addition to this univariate description of the survival data, a multivariable survival model in the form of the Cox proportional hazards regression model was used to detect differences between the two interventions. Accordingly, the two groups were compared with respect to their interquartile range (IQR), a nonparametric counterpart to the standard deviation (measuring variability in data distribution). In order to test whether the “spread” of the LOS distribution for the palliative care group was different from that of the control group, the ratio (R) of the IQRs was computed using the bootstrap method with 1000 replications (Efron & Tibshirani, Reference Efron and Tibshirani1994).
RESULTS
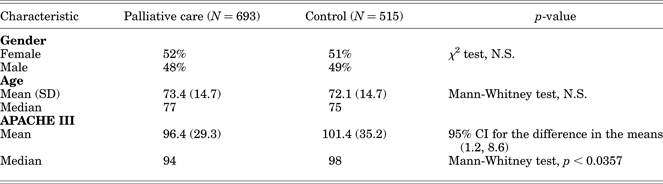
As can be seen in Table 1, the two intervention groups were comparable in age and gender; however, APACHE III scores, which range from 0 to 299, were significantly higher for the control group (96.4 vs. 101.4, Mann–Whitney test, p < 0.04). This difference, however, was not clinically significant, as evidenced by the 95% Confidence Interval (CI) for the difference in the means between the two groups.
Patient characteristics of palliative care vs. control group

LOS and Mortality
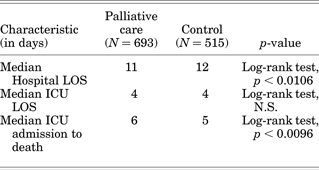
Median hospital LOS for the control group was 12 days; the palliative care group had a similar LOS of 11 days (Table 2). However, the IQR for the control group was 22 days, whereas the IQR of the palliative care intervention group was 16 days, demonstrating a “tightening” of the hospital LOS distribution in the palliative care group. The mean value of R (ratio of IQRs, 0.74 ± 0.07 SD) was <1 (bootstrap z test, p < 0.0003), meaning that the LOS variability for the palliative care group was significantly smaller than for the control group.
Length of stay (LOS) characteristics of palliative care vs. control group

As can be seen from Table 2, the distribution of time until death, as measured from hospital admission to discharge (i.e., hospital LOS) was significantly lower for the palliative care group (log-rank test, p < 0.0106). This demonstrates that dying is prolonged in the control group as compared to the palliative care group.
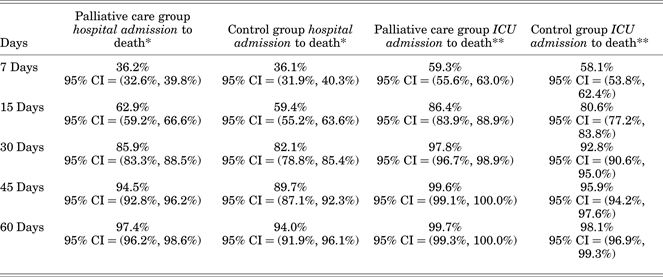
Table 3 displays mortality rate estimates, along with their respective 95% CIs, across five selected time periods: 7, 15, 30, 45, and 60 days. The median time from MICU admission to death for the control group was 5 days; the palliative care group had a similar median time until death of 6 days. However, when examining the time from MICU admission to death (i.e., hospital discharge), significant differences were found between palliative care and control groups (log-rank test, p < 0.0096), once again demonstrating that the palliative care group had a higher probability of mortality (as can be seen from Table 3). Even after adjusting for APACHE III score, the Cox model for hospital LOS continued to show a higher probability of mortality over time in the palliative care group than in the control group (p < 0.013, Hazard Ratio = 1.163, 95% CI = 1.035, 1.306), consistent with the unadjusted analysis.
Estimated mortality rate over time

Location and DNR Designation at Death
Significantly more patients in the palliative care group were protected from an MICU death and were transferred to a medical floor for end-of-life care than were controls (38.4% palliative care group vs. 28.7% control group, p < 0.0005).
The palliative medicine group contained a significantly higher proportion of patients with a DNR designation at death than did the control group (86% vs. 68%, χ2 test, p < 0.0001). This group also contained a significantly higher percentage of patients with respiratory failure requiring mechanical ventilation, as compared to control (87% vs. 80%, χ2 test, p < 0.0006). Despite this, there was no difference between the two groups in forgoing unwanted mechanical ventilation (as can be seen from Table 4).
Comparing DNR, respiratory failure requiring mechanical ventilation and withdrawing mechanical ventilation

DISCUSSION
We demonstrated that a focused palliative care intervention in an MICU can result in significant differences in outcomes that influence quality of care for dying patients. Some may argue that palliative medicine teams reduce hospital LOS by forgoing mechanical ventilation from patients, thereby allowing death to occur sooner. Interestingly, our data did not show a statistically significant difference in rate of ventilator withdrawal in our two groups.
Dying in an MICU is associated with inadequate pain control, loneliness, and noise. Restricted visiting hours creates further isolation. Families report that less than half of dying MICU patients receive adequate analgesia (Mularski et al., Reference Mularski, Heine and Osborne2005). Our study demonstrated that palliative care consultation protected a greater number of terminally ill patients from an MICU death through earlier transition to a more appropriate location such as a medical floor for ongoing end-of-life care. When death is certain, rescuing patients from an MICU death and providing appropriate palliative care on a medical floor is not only more cost effective, but associated with less unwanted and costly therapies. A typical MICU patient will endure invasive monitoring, daily chest radiographs, multiple blood tests, pulse oximetry, and vital sign measurements every 15 minutes. This translates to 100 blood pressure readings, heart rate assessments, and respiratory rate measurements every day, even on the day of death. At our institution, the direct variable cost of deceased patients in the MICU is $1,806 per day, as compared to a medical floor with a direct variable cost of $522 per day (North Shore University Hospital).
An interesting result of this study was that, while “average” LOS (as measured by mean or median) did not differ between groups, the degree of variation in LOS did differ, as demonstrated by the difference in IQRs. In other words, patients in the palliative care group had LOS that was more consistent, or predictable, than those in the control group. Although this was not an a priori hypothesis, it suggests that both average and spread should be considered when evaluating the impact of interventions such as these.
Our data showed that palliative medicine consultation in the MICU impacted length of stay, and increased DNR designation rate, thereby protecting patients from non-beneficial CPR at death. Additionally, palliative medicine consultation rescued more patients from an MICU death by offering palliative options on a medical floor, when death was certain.
LIMITATIONS
Our study design was limited to a retrospective comparison of two cohorts rather than a prospective randomized method. There were reasons why a prospective trial comparing palliative care patients to controls was not possible at our institution. First, intensivists felt it would be unethical to withhold palliative medicine consultation from patients who could benefit. Given that randomization was simply not feasible, the use of a historical (rather than concurrent) control was the best possible study design. Second, our team's presence in the MICU may have created a “halo” effect on the control group, because the palliative medicine team is involved both in direct patient care, and in teaching the MICU residents.
Discontinuing unwanted life extending-therapies occurs in more than half of all MICU deaths (Cook et al., Reference Cook, Rocker and Marshal2003). One in five people in the United States die in an MICU (Angus et al., Reference Angus, Barnato and Linde-Zwirble2004). Because of the inherent barriers to discussing death, physicians often avoid these conversations, even when death is certain (Keating et al., Reference Keating, Landrum and Rogers2010). Proactive MICU communication strategies have been shown to reduce the use of non-beneficial treatments (Campbell & Guzman, Reference Campbell and Guzman2003). Improved communication has been shown to lessen the burden of bereavement for family members. Lautrette and colleagues demonstrated that providing the relatives of patients who are dying in the MICU with a bereavement brochure and using a proactive communications strategy that included longer family conferences resulted in reduced symptoms of anxiety, depression, and post-traumatic stress disorder for family members, 90 days after the patient's death (Lautrette et al., Reference Lautrette, Darmon and Megarbane2007).
Few physicians have been effectively taught the communication skills to address issues related to death and dying (Campbell, Reference Campbell2006). As a result, “ICU care as usual” is pursued as the standard default path, even when such care is fruitless. Our study shows that proactive communication in the MICU can result in a better death for patients and their loved ones.
APPENDIX A