Introduction
Definitive radiotherapy (RT) stands as a primary treatment modality for early-stage glottic carcinoma, particularly for T1–T2N0 lesions. It offers exceptional local control rates, ranging from 83 per cent to 95 per cent for T1 lesions and 70 per cent to 80 per cent for T2 lesions, achieving a robust 5-year disease-free survival rate of 84.3 per cent.Reference Jones, Vinin, Sebastian, Muttath, Narendran and Yahiya1 In the clinical decision-making process between RT and transoral laser microsurgery, RT is frequently favoured for its superior functional outcomes, specifically its ability to maintain the anatomical integrity of the larynx and optimise long-term voice quality.Reference Baig, Shahid, Sadiq and Khan2–Reference Rydell, Andreasson, Gustafsson and Clarhed5
However, this high efficacy is not without consequence. The therapeutic benefits of radiation are frequently accompanied by a spectrum of acute and late complications that significantly impact a patient’s quality of life.Reference Purohit, Harsh, Tawri, Kumar, Sharma and Jakhar4 Post-irradiation tissue responses, including mucositis, dermatitis, persistent laryngeal oedema and broader functional impairments, can fundamentally alter vocal fold vibratory dynamics and overall laryngeal competence.Reference Lee, Lee, Kwon, Chung and Wu6
The severity of these acute-on-chronic changes is heavily influenced by the initial biological burden of the disease. The transition from T1 to T2 staging represents a critical anatomical shift characterised by larger tumour volumes and a greater extent of vocal fold involvement. Literature suggests that while objective baseline metrics (such as pre-RT jitter and shimmer) may not always capture significant differences between T1 and T2 lesions,Reference Hočevar-Boltežar and Žargi7–Reference Franz, Pessot, Gallo, Tundo, Spinato and Marioni9 the subjective patient experience may differ. Patients with T2 carcinoma often present with greater pre-treatment vocal fatigue, hoarseness and higher overall voice handicap scores.Reference Shenoy, Sharma, Chavan, Halkud, Ranganath and Pasha10 Furthermore, this stage distinction carries documented prognostic weight in oncological terms.Reference Choi, Chung, Ahn, Oh and Son11
Despite these recognised differences, clinical outcomes are often reported by aggregating T1 and T2 cases, thereby potentially masking stage-specific differences in the pace of recovery. To establish a more comprehensive clinical picture, it is essential to integrate patient-reported subjective experiences (such as the Voice Handicap Index-10) with objective acoustic and stroboscopic metrics.Reference Marciscano, Charu, Starmer, Best, Quon and Hillel12–Reference Hasanvand, Darouie, Aghadoost, Dabirmoghaddam and Bakhshi14
Building on previous longitudinal frameworks,Reference AL-Rashidi, El Dessouky, ELdemerdash, Abdel-Hady and Shohdi15 this study aimed to explore the trajectory of vocal restoration. By comparing the subjective and objective recovery pacing of T1 versus T2 patients over a six-month post-RT window, we sought to determine whether initial tumour stage is associated with a distinct, more protracted recovery trajectory. Given the exploratory nature of the stage comparison, the total Arabic Voice Handicap Index-10 score was adopted as the primary patient-reported measure, with the aim of informing more targeted, stage-specific rehabilitative strategies.
Materials and methods
Study design and participants
This prospective, longitudinal cohort study was conducted following ethical approval from the Institutional Review Board of the Faculty of Medicine, Cairo University (Ref: MD-88-2024). Written informed consent was obtained from all participants prior to enrolment. The study met all criteria established by the Declaration of Helsinki.
The study cohort comprised 37 patients newly diagnosed with early-stage (T1–T2N0M0) glottic squamous cell carcinoma who were scheduled for definitive RT. To investigate stage-specific recovery trajectories, participants were stratified into two subgroups based on their initial tumour–node–metastasis staging: Group A consisted of patients with T1 lesions (n = 27) and Group B comprised patients with T2 lesions (n = 10). This report constitutes a secondary, stage-focused analysis of the same 37-patient cohort whose overall cross-parametric voice correlations have been reported separately.Reference AL-Rashidi, El Dessouky, ELdemerdash, Abdel-Hady and Shohdi15 Whereas that earlier work analysed correlations among subjective, functional and objective measures across the full cohort, the present study addresses a distinct question not previously examined: whether initial T stage (T1 vs T2) is associated with different voice-recovery trajectories. The demographic and baseline clinical characteristics of this cohort have been detailed previously.Reference AL-Rashidi, El Dessouky, ELdemerdash, Abdel-Hady and Shohdi15 All 37 patients included in the analysis completed the full assessment protocol at all three time points (baseline, 3 months and 6 months); no data were missing for any outcome measure.
Radiotherapy protocol
All enrolled patients were treated with primary intensity-modulated radiation therapy. The prescribed cumulative radiation dose ranged from 60 to 70 Gy, delivered in daily fractions over a period of 6 to 7 weeks. This highly conformal technique was utilised to ensure precise target volume coverage while maximally sparing adjacent, non-involved laryngeal and pharyngeal tissues.
Multidimensional assessment triad
To capture the trajectory of vocal restoration, patients were evaluated at three critical junctures: pre-treatment baseline, three months post-RT and six months post-RT. The assessment protocol utilised a multidimensional battery as described in the following sections.
Subjective perception
The Arabic version of the Voice Handicap Index-10 – the validated Arabic adaptation of the original Voice Handicap Index-10 – was administered to quantify the patients’ self-perceived vocal handicap and their functional, physical and emotional distress.Reference Farahat16 Throughout this report, Arabic Voice Handicap Index-10 refers to the instrument administered to our cohort, whereas Voice Handicap Index-10 refers to the original instrument and its psychometric properties.
Functional dynamics
Laryngeal videostroboscopy was performed utilising the standardised visual-perceptual assessment scale formulated and validated by the authors.Reference AL-Rashidi, El Dessouky, Shohdi, ELdemerdash and Abdel-Hady17 Amplitude and mucosal wave vibration were rated as closely related aspects of vibratory behaviour; because both reflect the oscillatory movement of the superficial layer of the lamina propria, they commonly covary and on the ordinal 0–3 scale their scores may coincide, particularly as vibratory function normalises following resolution of the tumour mass.Reference Hirano and Bless18
Objective acoustic analysis
Acoustic signals were recorded and analysed using the Computerized Speech Lab (model 4300B) and the Multi-Dimensional Voice Program. Recordings were captured in a sound-treated environment using a sustained /a/ vowel at a comfortable pitch and loudness. Analysis followed standard clinical acoustic protocols, strictly adhering to the environmental controls and calibration detailed in a previous cohort evaluation.Reference AL-Rashidi, El Dessouky, Shohdi, ELdemerdash and Abdel-Hady17 Normal values were taken as jitter below 1 per cent and shimmer below 3 per cent,Reference Brockmann, Drinnan, Storck and Carding19 and a harmonics-to-noise ratio of at least 12 dB.Reference Shama, Krishna and Cholayya20 Maximum phonation time was also measured to assess aerodynamic efficiency; values below 15 seconds for males (norm, 30 seconds) and below 10 seconds for females (norm, 20 seconds) were classified as pathological.Reference Sawashima21
Statistical analysis
Statistical computations were performed using SPSS software version 28 (IBM Corp., Armonk, NY, USA). Given the sample sizes and data distribution patterns, non-parametric tests were employed. The Mann–Whitney U test was utilised for all inter-group comparisons (T1 vs T2) at each temporal interval to identify stage-specific differences. To track the longitudinal recovery within each specific group over time, the Wilcoxon signed-rank test was applied. A p value of less than 0.05 was established as the threshold for statistical significance.
The total Arabic Voice Handicap Index-10 score was pre-specified as the primary patient-reported outcome measure, consistent with its validation as a unidimensional instrument.Reference Farahat16 Individual domain scores (functional, physical, emotional) were analysed as secondary, exploratory measures and interpreted with caution, given that the Voice Handicap Index-10 was not originally validated for independent subscale use. To contextualise statistical findings against clinical relevance, between-group differences in total Arabic Voice Handicap Index-10 were interpreted with reference to the established minimal important difference of six points.Reference Misono, Yueh, Stockness, House and Marmor22 Given the exploratory nature of this secondary, stage-focused analysis, no formal correction for multiple comparisons was applied; the analyses were intended to generate rather than confirm hypotheses. Consequently, isolated significant findings should be interpreted with caution, and interpretative emphasis was placed on the pre-specified primary outcome (total Arabic Voice Handicap Index-10) and on the consistency of effects across parameters rather than on individual p values.
Results and analysis
Baseline comparisons (pre-treatment)
The cohort comprised 37 patients (35 men, 2 women) with a mean age of 52.45 ± 8.0 years (range, 40–69 years). Regarding tumour distribution, unilateral presentation predominated, observed in 28 cases (75.7 per cent), with 40.5 per cent localised to the right vocal fold and 35.2 per cent to the left; the remaining 9 cases (24.3 per cent) presented with synchronous bilateral involvement. All patients who were active smokers at baseline achieved smoking cessation following diagnosis and treatment initiation, representing a 100 per cent cessation rate.
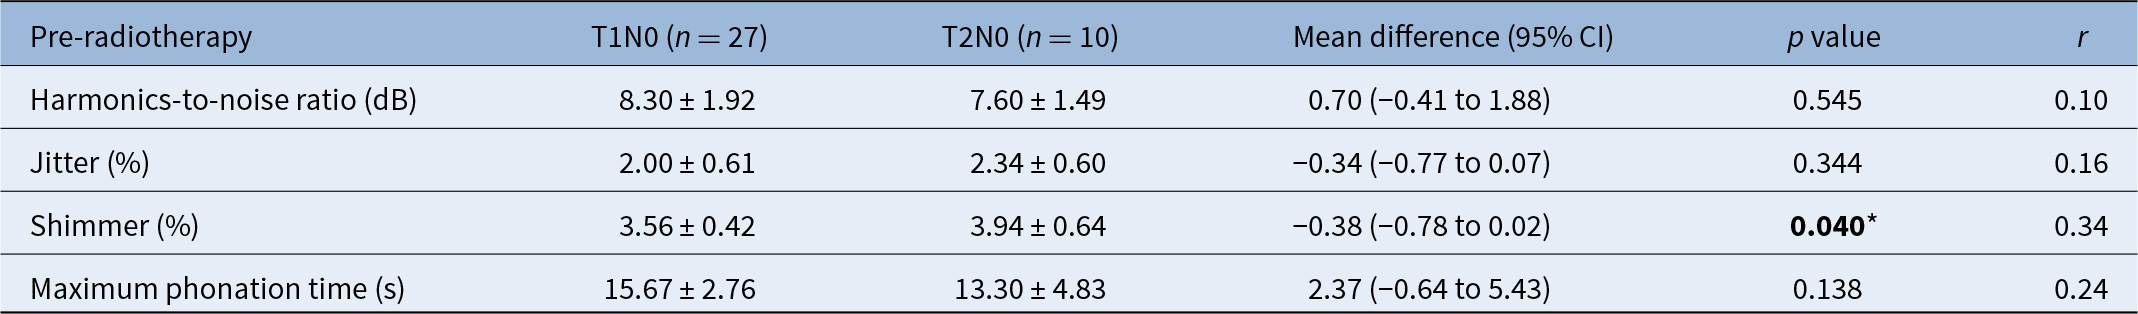
At baseline, self-reported handicap was comparable between groups: total Arabic Voice Handicap Index-10 scores did not differ significantly (28.41 ± 6.33 in T1 vs 31.50 ± 5.32 in T2; p = 0.249; r = 0.19) and the 95 per cent CI for the difference included zero (−7.00 to 0.76) (Table 1). Objective acoustic measures were likewise similar for harmonics-to-noise ratio, jitter and maximum phonation time (all p > 0.05), although shimmer reached borderline significance (3.56 ± 0.42 vs 3.94 ± 0.64; p = 0.040; r = 0.34), with a CI approaching zero (−0.78 to 0.02) (Table 2).
Baseline (pre-radiotherapy) Total Arabic Voice Handicap Index-10 scores: T1 versus T2 comparison

Table 1 Long description
Baseline, pre-radiotherapy Arabic Voice Handicap Index-10 total scores are reported for two tumor stage groups. T1N0 (27 people) had a mean score of 28.41 with a standard deviation of 6.33. T2N0 (10 people) had a mean score of 31.50 with a standard deviation of 5.32. The average difference favored higher scores in T2N0 by about 3 points, and the confidence interval ranged from about 7 points lower to about 1 point higher for T2N0 relative to T1N0. The p value was 0.249, indicating no statistically significant difference between groups. The effect size r was 0.19, suggesting a small difference. Results should be interpreted cautiously because the T2N0 group is much smaller than the T1N0 group.
Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N (0.1 small, 0.3 medium, 0.5 large). 95% confidence interval (CI) for the mean difference obtained by bootstrap resampling (10 000 replicates). *p < 0.05 considered significant.
Baseline (pre-radiotherapy) acoustic and aerodynamic metrics: T1 versus T2 comparison

Table 2 Long description
Baseline pre-radiotherapy voice and breathing-related measures are compared between T1N0 (27 people) and T2N0 (10 people), reporting group averages with variability, mean differences with confidence intervals, p values, and effect sizes. Harmonics-to-noise ratio is similar: 8.30 dB in T1N0 versus 7.60 dB in T2N0, with a non-significant p value and a small effect. Jitter is also similar: 2.00 percent in T1N0 versus 2.34 percent in T2N0, not statistically significant. Shimmer is higher in T2N0 (3.94 percent) than T1N0 (3.56 percent) and is the only measure marked statistically significant (p 0.040), with a small to moderate effect size. Maximum phonation time is longer in T1N0 (15.67 seconds) than T2N0 (13.30 seconds), but the difference is not statistically significant. Confidence intervals for the mean differences include zero for all measures, so results should be interpreted cautiously, especially given the smaller T2N0 sample.
Acoustic analysis performed using the Computerized Speech Lab (model 4300B) with the Multi-Dimensional Voice Program. Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. 95% confidence interval (CI) for the mean difference obtained by bootstrap resampling (10 000 replicates). *p < 0.05. Significant values are shown in bold
Videostroboscopy, by contrast, detected early stage-related structural differences (Table 3). T2 patients showed greater phase asymmetry (p = 0.045; r = 0.33), and greater impairment of left-fold periodicity (p = 0.031; r = 0.35) and left-fold mucosal wave vibration (p = 0.035; r = 0.35). These differences were of small-to-moderate magnitude and are consistent with the larger tumour volume and wider mucosal involvement expected in T2 lesions.
Baseline (pre-radiotherapy) videostroboscopic findings: T1 versus T2 comparison

Table 3 Long description
Baseline videostroboscopy impairment scores on a 0 to 3 severity scale are compared between T1N0 (27 people) and T2N0 (10 people), reported as mean with standard deviation, along with p values and effect size r. T2N0 has higher, worse phase symmetry impairment than T1N0 (2.70 versus 1.56), and this difference is statistically significant with a moderate effect size (r 0.33). Left vocal fold periodicity is also worse in T2N0 (2.10 versus 0.93) and statistically significant (r 0.35). Left vocal fold mucosal wave vibration is worse in T2N0 as well (2.10 versus 1.15) and statistically significant (r 0.35). Other measures do not reach statistical significance: right and left amplitude, right mucosal wave vibration, right periodicity, and glottic closure, although several show moderate effect sizes despite non-significant p values. Because these are ordinal ratings summarized with means, interpret small numeric differences cautiously and focus on the direction of change and the reported significance and effect sizes.
Parameters graded on a validated 0–3 ordinal scale (0 = normal; 3 = severe deficit). Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. *p < 0.05. Significant values are shown in bold. Confidence intervals are not reported for these ordinal grades, for which a mean-difference interval is not readily interpretable; effect size r is given instead
Taken together, the two groups began with comparable patient-perceived handicap and largely comparable acoustic output, despite detectable stage-related differences in laryngeal vibratory structure.
Three-month follow up: the ‘recovery lag’
The three-month assessment marked the point of greatest divergence between stages, with a consistent recovery lag evident in the T2 group across all three assessment domains.
Self-reported handicap differed significantly: total Arabic Voice Handicap Index-10 was higher in T2 patients (28.40 ± 5.85) than in T1 patients (22.67 ± 4.06), a mean difference of 5.73 points (95 per cent CI = −9.57 to −2.03; p = 0.012; r = 0.41). This difference approaches the established minimal important difference of six pointsReference Misono, Yueh, Stockness, House and Marmor22 and the CI indicates that the true difference may be considerably larger, supporting a clinically relevant gap at this stage (Table 4).
Total Arabic Voice Handicap Index-10 scores at three months post-radiotherapy: T1 versus T2 comparison

Table 4 Long description
Mean Arabic Voice Handicap Index-10 scores three months after radiotherapy are reported for two tumor stage groups, T1N0 and T2N0. T1N0 (27 people) had a mean total score of 22.67 with a standard deviation of 4.06. T2N0 (10 people) had a higher mean total score of 28.40 with a standard deviation of 5.85. The average difference favored T1N0 by 5.73 points, and the confidence interval for this difference ranged from 9.57 to 2.03 points in favor of T1N0. The between-group comparison was statistically significant with a p value of 0.012. The reported effect size r was 0.41, indicating a moderate difference between groups. Results should be interpreted with caution because the T2N0 group is much smaller than the T1N0 group.
Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. 95% confidence interval (CI) for the mean difference obtained by bootstrap resampling (10 000 replicates). *p < 0.05. Significant values are shown in bold
Objective acoustic measures mirrored this pattern (Table 5). T2 patients showed greater perturbation (shimmer 3.43 ± 0.14 vs 3.16 ± 0.19; p = 0.001; r = 0.55, a large effect; jitter 1.88 ± 0.37 vs 1.53 ± 0.34; p = 0.018; r = 0.39), lower spectral purity (harmonics-to-noise ratio 9.10 ± 1.60 vs 10.50 ± 1.30; p = 0.029; r = 0.35) and reduced aerodynamic efficiency (maximum phonation time 14.40 ± 0.84 vs 16.30 ± 2.89; p = 0.005; r = 0.46). All CIs excluded zero.
Acoustic and aerodynamic metrics at three months post-radiotherapy: T1 versus T2 comparison

Table 5 Long description
Acoustic and aerodynamic voice outcomes at three months after radiotherapy are compared between T1N0 (27 people) and T2N0 (10 people). T1N0 shows a higher harmonics-to-noise ratio, averaging 10.50 dB versus 9.10 dB in T2N0, with a mean difference of 1.40 dB and a statistically significant p value of 0.029. Measures of instability are lower in T1N0: jitter averages 1.53 percent versus 1.88 percent (mean difference minus 0.35; p value 0.018) and shimmer averages 3.16 percent versus 3.43 percent (mean difference minus 0.27; p value 0.001). Maximum phonation time is longer in T1N0, averaging 16.30 seconds versus 14.40 seconds (mean difference 1.90 seconds; p value 0.005). Effect sizes range from 0.35 to 0.55, indicating small to moderate group separation, with the largest effect for shimmer. Results reflect group averages with variability and should be interpreted with caution because the T2N0 group is smaller.
Acoustic analysis performed using the Computerized Speech Lab (model 4300B) with the Multi-Dimensional Voice Program. Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. 95% confidence interval (CI) for the mean difference obtained by bootstrap resampling (10 000 replicates). *p < 0.05. Significant values are shown in bold
Videostroboscopy showed the same directional pattern (Table 6), with markedly greater phase asymmetry in T2 patients (2.10 ± 0.74 vs 0.78 ± 0.85; p = 0.001; r = 0.57) and significant impairment of left-fold periodicity, amplitude, mucosal wave vibration and glottic closure (all p < 0.05).
Videostroboscopic findings at three months post-radiotherapy: T1 versus T2 comparison

Table 6 Long description
Mean impairment grades for videostroboscopic voice measures three months after radiotherapy are reported, comparing T1N0 (27 patients) with T2N0 (10 patients) on a 0 to 3 severity scale. T2N0 has higher (worse) phase symmetry impairment than T1N0 (about 2.10 versus 0.78), with a statistically significant difference and a large effect size. Left vocal fold periodicity is also worse in T2N0 (about 1.70 versus 0.44), again statistically significant with a large effect size, while right vocal fold periodicity does not differ significantly between groups. For right vocal fold amplitude and right mucosal wave vibration, T1N0 shows higher impairment than T2N0 (about 1.11 versus 0.40), with statistically significant differences and moderate effect sizes. For left vocal fold amplitude and left mucosal wave vibration, T2N0 shows higher impairment than T1N0 (about 1.70 versus 0.89), with statistically significant differences and small to moderate effect sizes. Glottic closure impairment is slightly higher in T2N0 than T1N0 (about 1.30 versus 0.85) and is statistically significant with a small to moderate effect size. Results are based on ordinal ratings summarized as means and standard deviations, so differences indicate shifts in typical severity rather than precise interval changes.
Parameters graded on a validated 0–3 ordinal scale (0 = normal; 3 = severe deficit). Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. *p < 0.05. Significant values are shown in bold. Confidence intervals are not reported for these ordinal grades, for which a mean-difference interval is not readily interpretable; effect size r is given instead. Amplitude and mucosal wave vibration received identical grades in all patients at this assessment, as both reflect oscillation of the superficial layer of the lamina propria (see Materials and methods).
Six-month endpoint: clinical convergence
By six months, both groups had improved substantially and the between-stage gap had narrowed markedly, although several parameters remained statistically distinguishable.
Total Arabic Voice Handicap Index-10 remained significantly higher in T2 patients (17.20 ± 1.69 vs 14.56 ± 5.73; p = 0.002; r = 0.50). However, the magnitude of this difference had fallen to 2.64 points, less than half the value observed at 3 months, and the 95 per cent CI (−4.92 to −0.29) lay entirely below the established minimal important difference of 6 points.Reference Misono, Yueh, Stockness, House and Marmor22 The residual difference was therefore statistically detectable but of limited clinical relevance (Table 7).
Total Arabic Voice Handicap Index-10 scores at six months post-radiotherapy: T1 versus T2 comparison

Table 7 Long description
Total Arabic Voice Handicap Index-10 scores measured six months after radiotherapy are reported, comparing T1N0 and T2N0 groups. The T1N0 group of 27 patients had a mean score of 14.56 with a standard deviation of 5.73. The T2N0 group of 10 patients had a mean score of 17.20 with a standard deviation of 1.69. The average difference indicates higher scores in T2N0 by 2.64 points, and the confidence interval for this difference ranges from 4.92 points higher to 0.29 points higher. The p value of 0.002 indicates the between-group difference is statistically significant. The reported effect size r of 0.50 suggests a moderate magnitude difference. Interpretation should consider the smaller sample size in the T2N0 group and that results reflect a single follow-up time point.
Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. 95% confidence interval (CI) for the mean difference obtained by bootstrap resampling (10 000 replicates). *p < 0.05. Significant values are shown in bold
The same pattern was evident in the objective measures (Table 8). Although the harmonics-to-noise ratio (p = 0.003; r = 0.47), jitter (p = 0.018; r = 0.38) and maximum phonation time (p = 0.004; r = 0.46) remained significantly different, both groups had reached values within or approaching accepted reference values: shimmer no longer differed significantly (2.73 ± 0.34 vs 2.92 ± 0.26; p = 0.109) and lay below the 3 per cent threshold in both groups,Reference Brockmann, Drinnan, Storck and Carding19 and mean maximum phonation time exceeded the 15-second pathological threshold in both groups.Reference Sawashima21
Acoustic and aerodynamic metrics at six months post-radiotherapy: T1 versus T2 comparison

Table 8 Long description
Acoustic voice measures and maximum phonation time at six months after radiotherapy are compared between T1N0 (27 people) and T2N0 (10 people). Harmonics-to-noise ratio averaged 12.81 dB in T1N0 versus 11.70 dB in T2N0, a statistically significant difference with a moderate effect size. Jitter averaged 1.01 percent in T1N0 versus 1.23 percent in T2N0, also statistically significant with a moderate effect size, indicating lower jitter in T1N0. Shimmer was similar between groups, 2.73 percent in T1N0 and 2.92 percent in T2N0, and the difference was not statistically significant. Maximum phonation time averaged 19.59 seconds in T1N0 versus 18.30 seconds in T2N0, statistically significant with a moderate effect size. Mean differences are reported with confidence intervals, and results should be interpreted cautiously because the T2N0 group is small.
Acoustic analysis performed using the Computerized Speech Lab (model 4300B) with the Multi-Dimensional Voice Program. Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. 95% confidence interval (CI) for the mean difference obtained by bootstrap resampling (10 000 replicates). *p < 0.05. Significant values are shown in bold
Videostroboscopic recovery was similarly pronounced (Table 9). Phase symmetry – the parameter showing the largest between-stage difference at 3 months (r = 0.57) – was identical in both groups at 6 months (0.30 ± 0.82 vs 0.30 ± 0.48; p = 0.394). Residual differences persisted in left-fold amplitude and mucosal wave vibration (both p < 0.001) and glottic closure (p = 0.016), but all mean scores were no higher than 0.60 on the 0–3 scale, indicating near-normal vibratory function in both groups.
Videostroboscopic findings at six months post-radiotherapy: T1 versus T2 comparison

Table 9 Long description
Videostroboscopic impairment scores at six months after radiotherapy are compared between T1N0 (27 people) and T2N0 (10 people) using a 0 to 3 severity scale, reported as mean with standard deviation. Most measures are low on average in both groups, but several left sided measures are worse in T2N0. Left vocal fold periodicity is 0.00 in T1N0 versus 0.30 in T2N0, with a statistically significant difference and a moderate effect size (r 0.48). Left vocal fold amplitude and left mucosal wave are 0.00 in T1N0 versus 0.60 in T2N0, both statistically significant with large effect sizes (r 0.71 for each). Glottic closure is 0.22 in T1N0 versus 0.60 in T2N0, statistically significant with a moderate effect size (r 0.40). Phase symmetry and right sided periodicity, amplitude, and mucosal wave do not show statistically significant differences between groups. Because these are ordinal ratings summarized with means, interpret the averages as overall severity tendencies rather than precise interval changes.
Parameters graded on a validated 0–3 ordinal scale (0 = normal; 3 = severe deficit). Data are mean ± standard deviation. Between-group comparison by Mann–Whitney U test. Effect size r = |Z|/√N. *p < 0.05. Significant values are shown in bold. Confidence intervals are not reported for these ordinal grades, for which a mean-difference interval is not readily interpretable; effect size r is given instead. Amplitude and mucosal wave vibration received identical grades in all patients at this assessment, as both reflect oscillation of the superficial layer of the lamina propria (see Materials and methods).
Discussion
This longitudinal analysis indicates that initial T stage is associated primarily with the pace of vocal recovery after RT, rather than its eventual extent. Although T1 and T2 groups began with comparable objective voice profiles and converged again by six months, the T2 group followed a measurably slower early trajectory, most evident at the three-month interval. The following sections consider the possible mechanisms underlying this pattern and its clinical relevance.
Baseline voice profiles
At diagnosis, the two groups were comparable in the domain that matters most to patients: self-reported handicap did not differ (p = 0.249) and the CI for the difference included zero. Objective acoustic output was similarly comparable for harmonics-to-noise ratio, jitter and maximum phonation time, with only a borderline difference in shimmer (p = 0.040), whose CI approached 0.
Videostroboscopy, by contrast, detected stage-related differences from the outset, with greater phase asymmetry and greater left-fold vibratory impairment in T2 patients. This divergence between modalities is itself informative. It suggests that the structural burden of a larger lesion is visible endoscopically before it translates into a proportionate acoustic or perceptual penalty, consistent with prior reports that pre-treatment perturbation metrics discriminate poorly between early stages.Reference Hočevar-Boltežar and Žargi7–Reference Franz, Pessot, Gallo, Tundo, Spinato and Marioni9 Patients with T1 and T2 lesions may therefore present with similar complaints despite measurably different vibratory anatomy.
This baseline configuration also frames the subsequent trajectories: because perceived handicap and acoustic output began at comparable levels, the divergence that emerged at three months is unlikely to be an artefact of unequal starting points.
Three-month recovery lag: a possible radiobiological basis
The clearest divergence emerged at 3 months, when T2 patients showed a disadvantage across all three assessment domains: greater acoustic perturbation (shimmer, r = 0.55, a large effect; jitter, r = 0.39), lower spectral purity (harmonics-to-noise ratio, r = 0.35), reduced aerodynamic efficiency (maximum phonation time, r = 0.46), markedly greater phase asymmetry on stroboscopy (r = 0.57) and a total Arabic Voice Handicap Index-10 difference of 5.73 points that approached the minimal important difference.Reference Misono, Yueh, Stockness, House and Marmor22 Rather than a discrete new deficit, this pattern is most plausibly understood as a difference in recovery kinetics: both groups improve, but T2 patients improve more slowly through the early post-RT window.
The concordance of subjective, acoustic, aerodynamic and stroboscopic findings – phase symmetry, glottic closure and all left-fold vibratory parameters, all in the same direction and of moderate-to-large magnitude – argues against a chance finding. Not all vibratory parameters followed this direction: right-fold amplitude and mucosal wave scores were poorer in the T1 group. Because stroboscopic parameters were recorded by anatomical side rather than relative to the tumour-bearing fold, and lesion laterality was unevenly distributed across the cohort, these right-sided findings most likely reflect the distribution of tumour side rather than a stage effect.
A radiobiological explanation is consistent with this timing. Larger T2 lesions require larger high-dose treatment volumes, exposing a greater extent of the vocal fold and paraglottic tissue to radiation. The three-month interval coincides with the peak of acute and early-subacute radiation effects – mucosal inflammation, laryngeal oedema and the onset of submucosal remodelling – which are volume-dependent and would therefore be expected to weigh more heavily on the T2 group. Because acoustic perturbation measures are highly sensitive to exactly these changes in mucosal mass and pliability, the acoustic signal plausibly registers this transient burden before it resolves. The concordant between-stage difference in phase symmetry on videostroboscopy (Table 6) supports a shared structural basis for the acoustic and perceptual findings at this stage, rather than three independent signals.
This interpretation aligns broadly with prior observations that larger early glottic lesions tend to recover more slowly and that acoustic and stroboscopic parameters continue to improve over the months following RT.Reference Tripathi, Verma, Panda, Ghosal and Sharma23, Reference Mekiš, Strojan, Mekiš and Hočevar Boltežar24 However, most of these reports pooled early-stage lesions or tracked recovery without stratifying by T stage; direct T1-versus-T2 comparison across sequential recovery intervals remains scarce, which is the specific gap this analysis addresses.
Six-month clinical convergence
By six months, the between-stage gap had narrowed substantially, although it did not close entirely in statistical terms. Total Arabic Voice Handicap Index-10 remained significantly higher in T2 patients (p = 0.002), yet the magnitude of the difference had fallen from 5.73 to 2.64 points, and its 95 per cent CI (−4.92 to −0.29) lay wholly below the minimal important difference of 6 points.Reference Misono, Yueh, Stockness, House and Marmor22 This dissociation between statistical detectability and clinical relevance is the central interpretative point of the six-month data: a difference that remains measurable is not necessarily a difference that patients experience.
Three observations support this reading. First, phase symmetry, the parameter with the largest between-stage effect at 3 months (r = 0.57), was identical in both groups at 6 months, indicating restoration of the fundamental vibratory pattern. Second, shimmer fell below 3 per cent in both groups and no longer differed significantly, and mean maximum phonation time rose above the pathological threshold of 15 seconds in both groups. Third, all residual stroboscopic differences occurred between mean scores no higher than 0.60 on a 0–3 scale, that is, between ‘normal’ and ‘near-normal’, rather than between impairment and health. Where these residual differences reached a large effect size, this reflects the consistency of a small absolute difference across a narrow range of near-normal scores, rather than a clinically meaningful deficit; effect size and clinical relevance are therefore not interchangeable here.
The residual differences that persisted (harmonics-to-noise ratio, jitter, maximum phonation time and left-fold vibratory parameters) were consistently in the direction of poorer function in the T2 group and are compatible with a modest degree of ongoing submucosal remodelling in the larger treated volume. Whether these subtle residua resolve further beyond six months or represent a durable ceiling on recovery in T2 lesions cannot be determined from the present follow up and merits longer-term study.
Clinical implications
Interpreted cautiously, these findings support a stage-aware approach to post-RT counselling and rehabilitation. Because T2 patients experience a slower recovery over the first three months before reaching a clinically comparable outcome, anticipatory counselling that frames the early period as a temporary plateau, rather than treatment failure, may help manage expectations and reduce distress during the phase when the gap is widest. The narrowing of the difference to below the minimal important difference by six months provides a concrete and encouraging endpoint to communicate: patients can be told that, although recovery may feel slower initially, the voice-related handicap they ultimately experience is unlikely to differ meaningfully from that of T1 patients.
The data also offer a rationale for considering earlier, stage-tailored voice therapy in T2 patients, targeting the early window in which perturbation and perceived handicap are greatest. However, because this study did not evaluate any therapeutic intervention, this remains a reasonable inference rather than a demonstrated benefit, and the specific timing and content of such therapy would need to be established prospectively.
These trajectories should also be viewed against the wider literature comparing organ-preserving modalities. Meta-analytic and population-based comparisons of transoral laser microsurgery and definitive RT in early glottic carcinoma have generally reported broadly comparable long-term voice outcomes, with differences that are often modality- and stage-dependent rather than uniform.Reference Rydell, Andreasson, Gustafsson and Clarhed5, Reference Du, Liu, Yu, Li, Li and Wang8, Reference Franz, Pessot, Gallo, Tundo, Spinato and Marioni9
Radiotherapy has been associated with more favourable outcomes in lesions requiring wider resection margins, whereas surgery may permit faster early recovery in more limited lesions. Our findings add a temporal dimension to this comparison: within RT alone, the recovery trajectory itself varies by stage, with T2 lesions lagging through the first three months before the gap narrows below clinical relevance. This suggests that cross-modality comparisons conducted at a single early time point may be sensitive to when the assessment is made, and that stage stratification is relevant when interpreting functional outcomes across treatment modalities.
These considerations sit within a wider shift in how organ-preserving treatment of laryngeal cancer is evaluated. Across subsites and modalities, functional recovery is increasingly regarded as a co-primary endpoint alongside oncological control: a recent systematic review of transoral robotic surgery for supraglottic carcinoma, for example, judged the approach principally by airway and swallowing recovery rather than by tumour clearance alone.Reference Chiari, Cordeschi, Ingelido, Motta, Caporale and Guarino25 Our data extend this principle to the glottis and to the voice domain, and add a temporal dimension: that the pace of functional recovery, not only its endpoint, differs by stage and may itself warrant clinical attention.
The temporal patterning we observed also echoes findings from other domains of laryngeal functional recovery. A recent systematic review and meta-analysis of laryngeal reinnervation for unilateral vocal fold paralysis, which, like the present study, used the Voice Handicap Index and maximum phonation time as principal endpoints, reported that the greatest gains occurred within the first six months, with values thereafter stabilising rather than continuing to improve.Reference Guarino, Russo, Chiari, Barillari, Camesasca and Carobbio26 That work also highlighted the interpretative difficulty created by heterogeneous outcome reporting and argued for standardised measures paired with anchor-based interpretation. Our findings reinforce both points: the first six months appear to be the decisive window for functional recovery in the larynx across aetiologies and interpreting handicap scores against an established minimal important difference – rather than statistical significance alone – materially changes what the data are taken to mean.
Limitations
Several limitations should be considered when interpreting these findings. First, no formal a priori sample size or power calculation was performed; the cohort size was determined by the number of consecutively eligible patients presenting during the study period. The T2 subgroup was correspondingly small (n = 10), which limits statistical power and increases susceptibility to selection bias and to the influence of individual variation. All stage-based analyses should therefore be regarded as exploratory and hypothesis-generating.
Second, although effect sizes are reported throughout and CIs are reported for all continuous outcomes, several parameters differed at baseline on videostroboscopy, and the analyses were not adjusted for these differences; the trajectories described are therefore descriptive rather than causal.
Third, the follow up was limited to six months, which captures the most dynamic phase of recovery but cannot characterise the very late effects of radiation-induced fibrosis; longer follow up of 12–24 months would be valuable to determine whether the subtle residual differences observed resolve further.
Fourth, as this analysis draws on the same prospective cohort as an earlier correlational study,Reference AL-Rashidi, El Dessouky, ELdemerdash, Abdel-Hady and Shohdi15 the two reports should be regarded as complementary analyses of a single patient population rather than independent samples.
Fifth, videostroboscopic parameters were recorded by anatomical side rather than relative to the tumour-bearing fold. Because lesion laterality was unevenly distributed across the cohort, side-specific comparisons should be interpreted with caution.
Several potential modifiers of vocal recovery also warrant comment. All baseline smokers achieved complete cessation following diagnosis, yielding a 100 per cent cessation rate; active smoking was therefore not a differential confounder between stages during follow up. No patient underwent formal voice therapy during the six-month observation period; the observed trajectories therefore reflect spontaneous recovery rather than rehabilitative intervention. Laryngopharyngeal reflux was not systematically assessed and its potential contribution cannot be excluded.
Finally, the absence of a comparator treatment arm precludes conclusions about voice recovery relative to other modalities such as transoral laser microsurgery.
• Definitive radiotherapy (RT) achieves high local control and larynx preservation in T1–T2N0 glottic carcinoma and is frequently preferred for its functional voice outcomes
• Post-RT voice outcomes are commonly reported with T1 and T2 lesions pooled together, which may conceal stage-specific differences in recovery
• Pre-treatment acoustic perturbation measures discriminate poorly between T1 and T2 lesions, and direct stage-stratified comparison across sequential recovery intervals is scarce
• T1 and T2 patients began with comparable self-reported handicap and acoustic output, although videostroboscopy already detected stage-related vibratory differences at baseline
• At 3 months, T2 patients showed a concordant recovery lag across patient-reported, acoustic, aerodynamic and stroboscopic domains, with a total Arabic Voice Handicap Index-10 difference of 5.73 points, approaching the minimal important difference, but by 6 months this difference had narrowed to 2.64 points, with a confidence interval lying wholly below the minimal important difference, and both groups reached near-normative acoustic values
• Initial T stage therefore influences the pace of voice recovery rather than its eventual extent, supporting stage-aware counselling and consideration of earlier voice therapy in T2 patients
Conclusion
This study indicates that in early glottic carcinoma treated with intensity-modulated radiation therapy, initial T stage is associated primarily with the pace of vocal recovery rather than its eventual extent. Although patient-reported handicap and acoustic output were comparable at diagnosis, T2 patients experienced a distinct recovery lag at 3 months, with a total Arabic Voice Handicap Index-10 difference of 5.73 points, approaching the minimal important difference, and concordant deficits across acoustic, aerodynamic and stroboscopic measures.
By 6 months this gap had narrowed to 2.64 points, with a CI lying entirely below the minimal important difference, and both groups reached near-normative acoustic values. The residual between-stage differences that remained statistically detectable were therefore of limited clinical relevance, a distinction that would have been obscured by significance testing alone.
These findings, although preliminary given the modest sample size, support a stage-aware approach to post-RT care: anticipatory counselling that frames the early period as a temporary plateau rather than treatment failure and consideration of earlier voice therapy for T2 patients during the window in which handicap is greatest. Larger, longer-term studies are warranted to confirm these trajectories and to determine whether the subtle residual differences observed at six months resolve further with time.
Acknowledgements
The authors used an artificial intelligence-based large language model for language editing. The authors take full responsibility for the content.
Data availability statement
The datasets generated and analysed during the current study are not publicly available because of patient confidentiality but are available from the corresponding author on reasonable request.
Funding statement
This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Competing interests
None declared