Clinical Implications
-
• One of the unmet needs in the current approach to neuropsychiatric disturbances after penetrating traumatic brain injury is the lack of para-clinical indexes to guide individualized therapy.
-
• Here we showed that lesion localization modulates the relationship between aggression and the dopaminergic system, which we propose can be conceptualized as a “U” curve. Our observations seem to confirm animal and basic human neurophysiology studies, which seem to suggest that medial prefrontal lesions and lateral prefrontal lesions might respectively increase and decrease striatal dopaminergic tone.
-
• According to our data, lPFC lesions seem to be associated with more aggressive behaviors in subjects with a lower baseline transcriptional activity of the DRD1 gene, while mPFC lesions seem to be associated with aggressive behaviors in subjects with a higher baseline transcriptional activity of the DRD1 gene.
Introduction and Aim
Pathological chronic aggressive behavior has been reported in up to 33% of patients with a traumatic brain injury (TBI).Reference Tateno, Jorge and Robinson 1 A number of different factors, including genetic predisposition, mono-aminergic system activity, and brain lesion location, are all thought to play a significant role in the development and maintenance of TBI-related aggression.Reference Pardini, Krueger and Hodgkinson 2 Regarding the symptomatic treatment options for aggression in TBI, to date most attention has been focused on the dopaminergic system.Reference Comai, Tau and Gobbi 3
Despite the widespread use of anti-dopaminergic drugs to treat aggression,Reference Goedhard, Stolker and Heerdink 4 converging evidence suggests that the relationship between dopamine and aggression is more complex than previously thought. In experimental models, for example, both D2 agonist and antagonists as well as D1 partial agonists and antagonists have been shown to reduce aggressive behaviors,Reference Tidey and Miczek 5 – Reference Aguilar, Miñarro, Pérez-Iranzo and Simón 7 while the classic pro-dopaminergic amphetamine has been shown to increase, decrease, or fail to change aggressive behavior levels depending on various factors, such as context and type of aggression.Reference Miczek and Tidey 8
Moreover, in humans, despite the consensus on the role of antipsychotics to treat aggression, pro-dopaminergic stimulants drugs have also been proposed as a possible pharmacological treatment for aggressive behaviors in specific patient groups. In attention deficit hyperactivity disorder (ADHD) patients, for example, stimulants have been shown to reduce aggressive behavior by remodulating to prefrontal cortex (PFC) dopamine levels,Reference Blader, Pliszka, Jensen, Schooler and Kafantaris 9 while pro-dopaminergic compounds have been proposed as a possible treatment for aggressive behavior in different dementing illnesses, such as frontotemporal dementia (FTD).Reference Huey, Putnam and Grafman 10 , Reference Huey, Garcia, Wassermann, Tierney and Grafman 11
Compared to the aforementioned clinical populations, the study of the biological basis of aggressive behavior in penetrating TBI (pTBI) presents another confounding factor, ie, the presence of focal brain lesions, which could modulate the relationship between the dopaminergic system and aggression. Indeed, transcranial magnetic stimulation (TMS) experiments have shown that dorsolateral PFC inhibition reduces dopamine release in deep gray matter,Reference Ko, Monchi and Ptito 12 while dorsolateral PFC stimulation increases striatal dopaminergic activity.Reference Strafella, Paus, Barrett and Dagher 13 In animal models, medial frontal lesions have been found to increase deep gray matter dopaminergic activity,Reference Jaskiw, Karoum and Weinberger 14 possibly through modulation of ventrotegmental area activity.
In this study, we explored the relationship between lesion location, pTBI-related aggressive behaviors, and dopaminergic tone. Based on the aforementioned literature and previous studies that have shown a significant role of PFC in aggressive behaviors,Reference Pardini, Krueger and Hodgkinson 2 we hypothesized that PFC lesion location significantly impacts the interaction between dopaminergic activity and aggression in pTBI. Given the key nature of PFC territories in pTBI-related aggression, we predicted a significant modulatory effect on the dopaminergic system/aggression interaction only by PFC but not non-PFC damage, and potentially a regional specificity of lesion location inside the PFC.
To test our hypotheses, we investigated, in a group of Vietnam War Veterans, the interaction between long-term pathological aggression, lesion location, and inter-individual differences in endogenous dopaminergic tone due to functional single nucleotide polymorphic (SNP) differences in the main components of the dopaminergic system,Reference Seeman and Van Tol 15 , Reference Volavka, Bilder and Nolan 16 ie, the dopamine receptor D1 (DRD1), the dopamine receptor D2 (DRD2), and the dopamine-degrading enzyme catechol-O-methyltransferase (COMT).
We decided to focus on these components of the dopaminergic system, as DRD1 and DRD2 represent the prototypical members of the 2 groups of dopamine receptors (ie, the DRD1-like and DRD2-like families),Reference Seeman and Van Tol 15 while COMT is thought to represent the major dopamine-degrading enzyme in the synaptic cleft.Reference Volavka, Bilder and Nolan 16 Evaluation of functional SNPs has been shown to be a useful tool to study the relationship between aggressive behaviors and mono-aminergic systems, both in healthy subjects and neuropsychiatric conditions,Reference Seeman and Van Tol 15 , Reference Volavka, Bilder and Nolan 16 as well as a proxy-marker of baseline dopaminergic tone in pharmacological challenges studies.Reference Cohen, Krohn-Grimberghe, Elger and Weber 17
Methods
Patient selection
Patients were drawn from Phase 3 of the Vietnam Head Injury Study (VHIS),Reference Raymont, Greathouse and Reding 18 which was conducted between 2003 and 2006 (36–39 years post-injury) at the Bethesda National Naval Medical Center (Bethesda, MD, USA). Pre-injury characteristics and follow-up data of the participants (n = 189) were available from military and Veterans Administration records. Inclusion criteria were the availability of SNP data and a negative history for treatments with drugs acting on the dopaminergic or serotoninergic system and for alcohol dependence. Eight subjects were removed due to the lack of SNP data, 9 subjects due to alcohol dependence, and 2 subjects were excluded on the basis of previous pharmacological treatments. We thus included 141 Caucasian male veterans who suffered pTBI during their service in Vietnam and 29 healthy Caucasians male Vietnam veterans. Each subject underwent neurologic and psychiatric examinations, and pTBI subjects received a noncontrast brain CT scan.
Standard protocol approvals, registrations, and patient consents
All subjects gave informed written consent before enrollment in the study. The National Naval Medical Center and the National Institutes of Health (NIH) Institutional Review Boards approved all the study procedures.
Behavioral evaluation
Long-term aggression levels were evaluated with the agitation/aggression subscale of the Neuropsychiatric Inventory (NPI-a),Reference Cummings, Mega and Gray 19 which was completed by the patients’ caregivers. The NPI-a is based on a semistructured interview and grades aggressive behaviors from 0 to 12, with higher values indicating more severe levels of aggression. The NPI-a has been used in clinical studies on aggression in brain injuryReference Pardini, Krueger and Hodgkinson 2 and other neurological conditions.Reference Cummings, Mega and Gray 19 Moreover, we also used the total NPI (NPI-t) score as a global index of psychopathology. Last, we evaluated early psychological trauma by administering the Early Trauma Inventory (ETI), a validated 56-item interview that was designed for the assessment of childhood negative experiences.Reference Bremner, Vermetten and Mazure 20
Computed tomography (CT) scans
Axial noncontrast CT scans were acquired on a GE Medical Systems Light Speed Plus CT-scanner in helical mode as described elsewhere.Reference Raymont, Greathouse and Reding 18 Briefly, images were reconstructed with an in-plane voxel size of 0.4 mm × 0.4 mm, overlapping slice thickness of 2.5 mm, and a 1-mm slice interval. Lesion location and volume were determined from CT images by manual tracing using the Analysis of Brain Lesion (ABLe)Reference Solomon, Raymont, Braun, Butman and Grafman 21 software implemented in MEDx v3.44 (Medical Numerics) with enhancements to support the Automated Anatomical Labeling (AAL) atlas.Reference Tzourio-Mazoyer, Landeau and Papathanassiou 22 A trained neuropsychiatrist (V.R.) performed the tracings, which were then reviewed by an experienced observer (J.G.) who was blind to the results of the clinical evaluations. The skull and scalp were then removed from the CT images; each volume was spatially normalized to a de-skulled CT scan, which was previously spatially normalized to the T1 MNI brain (standard of the International Consortium for Brain Mapping). The ABLe software was used to exclude the manually delineated lesion from the spatial normalization process to improve registration accuracy. Spatial normalization was performed using an automated image registration algorithm using a 12-parameter affine model. The medial PFC (mPFC) region of interest was defined as those areas of the PFC medial to x = –20 and to x = 20 in the Montreal Neurological Institute (MNI) space as previously described.Reference Koenigs, Huey, Calamia, Raymont, Tranel and Grafman 23 Subjects with a PFC lesion encompassing or partially encompassing the mPFC were included in the “mPFC group,” while all other subjects with PFC lesions were included in the “lateral PFC (lPFC) group.” Subjects with non-PFC lesions were included in the “non-PFC group.”
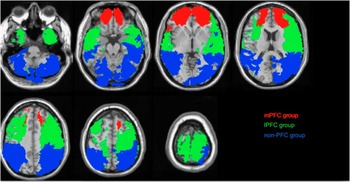
Differences in lesion localization among the 3 groups are reported in Figure 1 using lesion subtraction maps that have been previously used in pTBI research to characterize differences in lesion localization among groups.Reference Pardini, Krueger and Hodgkinson 2
Subtraction lesions maps for the mPFC group (red), lPFC group (green), and non-PFC group (blue). For each group, the subtraction lesion map shows those brain areas that were more lesioned in 1 group compared to the other groups. Note that each subject was only included in 1 group.

Genetic analysis
From a published SNP array,Reference Hodgkinson, Yuan and Xu 24 we selected the following functional SNPs: DRD1 rs686 (A-to-G), DRD2 rs4648317 (C-to-T), and COMT Val158Met rs4680 (G-to-A). Rs686 is a functional SNP located in the promoter region of the DRD1 gene; its A allele is linked with increased transcriptional activity compared to the G allele.Reference Huang, Ma and Payne 25 Rs4274224 is located in the first intronic region of the DRD2 gene; the minor allele has been linked with reduced D2 expression in healthy controls compared to the major allele.Reference Fukui, Suzuki and Sugai 26 Moreover, this SNP has been shown to impact behavioral inhibition.Reference Hamidovic, Dlugos, Skol, Palmer and de Wit 27 COMT Val158Met rs4680 is a widely studied SNP in neuropsychiatry, and the Val allele is thought to be linked with a reduced efficiency in the degradation of dopamine.Reference Volavka, Bilder and Nolan 16 Last, we decided to control for possible differences among subjects for the monoamine oxidase A (MAO-A) genotype, one of the genes more commonly linked to pathological aggression.Reference Pardini, Krueger and Hodgkinson 2 , Reference Shih, Chen and Ridd 28 While the main role of the MAO-A is serotonin metabolism rather than dopamine, we decided to include it as a confounding factor since the common variable number tandem repeat (VNTR) polymorphism is known to impact aggression levels in the general population.Reference Shih, Chen and Ridd 28 VNTR MAO-A polymorphisms are thought to modulate MAO-A activity with the 3.5 and 4 repeats linked with MAO-A high-activity and 2, 3, and 5 repeats linked with low MAO-A activity. Genotyping for the those SNPs was performed as described elsewhere.Reference Pardini, Krueger and Hodgkinson 2 , Reference Raymont, Greathouse and Reding 18 , Reference Hodgkinson, Yuan and Xu 24
Statistical analysis
Statistical threshold was set at 0.05 (2-tailed) for all first-level analyses. For each of our target SNPs (DRD1 rs686, DRD2 rs4648317, and COMT Val158Met rs4680), a mixed 2 × 4 analysis of covariance (ANCOVA) on NPI-a (and NPI-t as a control measure) was performed with Genotype (major allele/–, minor allele/minor allele) and Group (mPFC, lPFC, non-PFC, control) as between-subjects factors and the other target genes as covariates. Based on our DRD1 results (see below), we also performed a 2 × 4 ANCOVA on NPI-a scores (and NPI-t scores) with DRD1 Genotype and Group as between-subjects factors and DRD2, COMT, and MAO VNTR genotype as covariates. Follow-up independent t-tests (Bonferroni corrected for multiple comparisons) were performed for the rs686 genotypes within each lesion group.
Results
Group characteristics
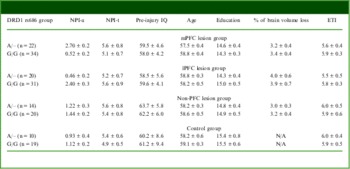
All four groups did not present with significant differences in pre-injury intelligence (F(3,165) = 1.2, p = 0.31), early life negative experiences (F(3,165) = 0.7, p = 0.55), education level (F(3,165) = 0.8, p = 0.50), and age (F(3,165) = 0.4, p = 0.75), and the lesion groups were matched on percentage of brain tissue loss due to pTBI (F(2,137) = 0.9, p = 0.41) (Table 1). Lesion subtraction maps are reported in Figure 1. Frequency distributions for the genotyping results were as follows: DRD1: 97 A/– vs 73 G/G subjects; DRD2: 117 C/– vs C/– subjects vs 53 T/T; COMT: 107 Val/– vs 63 Met/Met subjects; MAO-A: 59 low-activity vs 111 high-activity subjects.
Demographic and clinical data for the experimental DRD1 rs686 groups

Note: NPI-a: Neuropsychiatric Inventory Aggression sub-score; NPI-t: Neuropsychiatric Inventory Total score; ETI: Early Trauma Inventory Score.
DRD1
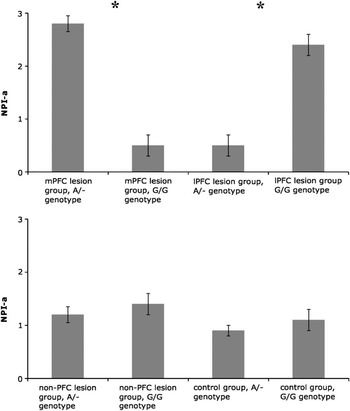
The ANCOVA on NPI-a revealed a significant interaction effect for DRD1 Genotype × Group (F(3,159) = 9.5, p = 0.001), but no significant main effects were found for DRD1 Genotype (F(1,159) = 0.4, p = 0.58) and Group (F(3,159) = 1.2, p = 0.35) and no covariate effect was found for COMT (F(1,159) = 0.45, p = 0.55), DRD2 (F(1,159) = 0.60, p = 0.4) or MAO-A (F(1,159) = 0.35, p = 0.35). Planned follow-up analyses showed that DRD1 A/– carriers had higher NPI-a scores than G/G carriers in the mPFC group (t = 2.99, p = 0.004; Cohen's d = 1.9), whereas DRD1 A/– carriers had lower NPI-a scores than G/G carriers in the lPFC group (t = 3.82, p = 0.002; Cohen's d = 1.89) (Figure 2). No significant differences were found between genotypes in the non-PFC (t = 0.92, p = 0.36) and control (t = 0.72, p = 0.48) groups.
NPI-a scores (mean ± s.e.m.) for the lesion groups divided according to the functional SNP DRD1 rs686. *Indicates a significant difference between the 2 genotype groups at p < 0.05 (Bonferroni correction).

The ANCOVA on NPI-t revealed no significant main effects (DRD1 Genotype: F(1,159) = 1.5, p = 0.25; Group: F(3,159) = 0.85, p = 0.38); interaction effect (F(3,159) = 1.1, p = 0.37); or COMT, DRD2, and MAO-A covariate effects.
DRD2
The DRD2 × Group ANCOVA performed on NPI-a scores revealed no significant main effects (DRD2 genotype: F(1,159) = 1.7, p = 0.52; Group: F(3,159) = 0.5, p = 0.80); interaction effect (F(3,159) = 0.15, p = 0.92); or DRD1, COMT, and MAO-A covariate effects.
COMT
The COMT Genotype × Group ANCOVA performed on NPI-a scores revealed no significant main effects (COMT genotype: F(1,159) = 0.7, p = 0.40; Group: F(3,159) = 0.2, p = 0.89); interaction effect (F(3,159) = 0.15, p = 0.92); or DRD1, DRD2, and MAO-A covariate effects.
Discussion
In this study, we studied the relationship between TBI-related aggression and the dopaminergic system and its modulation by lesion location. Our results revealed a significant interaction between aggressive behavior and the DRD1 rs686 SNP depending upon PFC lesion location. We showed that carriers of the major and more transcriptionally active allele of DRD1 were more aggressive compared to the minor allele homozygotes in the mPFC group, while conversely, DRD1 major allele carriers were less aggressive than minor allele homozygotes in the lPFC group.
Moreover, we did not observe any significant interactions between lesion location and genotype for DRD2 or COMT functional SNPs, thus suggesting a possible specificity of this effect to DRD1 receptors. Last, no genotype effects were observed in the non-PFC and control groups or when taking into account the global index of psychopathology.
We propose that our observation of high aggression levels in 2 specific subsets of pTBI patients—(1) subjects with mPFC lesions and more expressed DRD1 receptors and (2) subjects with lPFC lesions and less expressed DRD1 receptors—can be explained by analogy to the known relationship between impaired cognitive performance and excessively high or low levels of dopamine (ie, the observed “U-curve” relationship between cognitive performance and dopaminergic tone).Reference Vijayraghavan, Wang, Birnbaum, Williams and Arnsten 29
While the “U-shaped curve” relationship between function and dopamine levels was first observed at the neural level, recent years have seen its generalization to the behavioral, whole-organism setting. In rats, for example, both D1 agonists and antagonists have been shown to impair working memory performance in a dose-dependent function, leading to a U-shaped curve–like relationship (ie, rats presented an equally pathological performance both during excessive inhibition and excessive stimulation of the D1 receptors).Reference Floresco 30 Moreover, in line with the proposed U-shaped curve relationship between dopamine tone and performance, a DRD2 agonist, cabergoline, increased neural reward responses during a feedback-based reversal learning fMRI task in healthy subjects with low DRD2 receptor density due to the A1+ Taq1A SNP, while it reduced reward responses in those subjects with higher DRD2 receptor density due to the A– Taq1A SNP.Reference Cohen, Krohn-Grimberghe, Elger and Weber 17 Last, a dopamine agonist, bromocriptine, has been shown to increase cognitive performance in healthy subjects with lower baseline dopamine synthesis—as quantified with fluoro-L-m-tyrosine PET scans, but showed an opposite effect (ie, a performance reduction) in subjects with higher baseline dopaminergic tone.Reference Cools, Frank and Gibbs 31
Our findings suggest that subjects with lPFC lesions and less expressed DRD1 represent the other extreme of the proposed “U-shaped curve” relationship between dopaminergic tone and aggression (ie, association of high levels of aggression with reduced D1 signaling). This proposal is in line with the observed reduction of deep brain dopaminergic activity in lPFC virtual-lesion studies based on theta-burst TMSReference Strafella, Paus, Barrett and Dagher 13 and an increased striatal dopaminergic tone after lPFC activation.Reference Jaskiw, Karoum and Weinberger 14
Thus, the combination of reduced dopaminergic activity with low DRD1 expression could lead to low D1 tone in different subcortical areas linked with aggression, such as the nucleus accumbens (NA). According to pharmaco-fMRI studies, low D1 activity is linked with blunted NA responses to environmental stimuli.Reference Knutson and Gibbs 32 A similar blunted NA response to environmental stimuli has been shown in subjects with ADHD, and it has been correlated with the extent of externalizing symptoms, which include aggressive conduct.Reference Scheres, Milham, Knutson and Castellanos 33 Interestingly, pro-dopaminergic stimulants are widely used to control externalizing aggressive behaviors in ADHD,Reference Blader, Pliszka, Jensen, Schooler and Kafantaris 9 as well as in some experimental models of aggression.Reference Couppis and Kennedy 34 Last, a relationship between NA neurodegeneration and disinhibited behavior has been shown in FTD in which pro-dopaminergic stimulants are used to treat aggression.Reference Zamboni, Huey, Krueger, Nichelli and Grafman 35
Our findings also indicate that subjects with mPFC lesions and more expressed DRD1 represent the “high dopamine” end of the proposed “U-shaped curve.” The mPFC territories are richly interconnected with the ventrotegmental area (the origin of the mesolimbic dopaminergic pathway to the NA), which suggests a modulatory effect of mPFC on the dopaminergic system,Reference Takahata and Moghaddam 36 as shown in animal lesion models in which the structural lesion of medial PFC territories was linked with an increase in NA dopaminergic activity.Reference Seeman and Van Tol 15 These observations are in line with the observed activation by mPFC projections of inhibitory GABA-ergic inter-neurons in the dopaminergic mesolimbic pathway,Reference Takahata and Moghaddam 36 as well as with the reported inverse correlation between mPFC and NA activity during immediate reward evaluation in impulsive subjects.Reference Diekhof, Nerenberg and Falkai 37 Given the relationship between D1 signaling and NA activity, the presence of mPFC lesions in subjects with highly expressed DRD1 could lead to an excessively active NA, especially in behaviorally relevant impulsive decision-making settings, and possibly to heightened aggressive behaviors.Reference Buckholtz, Treadway and Cowan 38
We propose that our finding of high aggression levels in pTBI subjects with mPFC lesions and more expressed DRD1 and in subjects with lPFC lesions and less expressed DRD1 supports a U-shaped curve modulation of the function of the mesolimbic dopaminergic system. Coincidentally, in a recent meta-analysis of striatal activation during reward anticipation tasks, a similar U-shaped curve paradigm has been proposed to link the reduced reward responsiveness of mesolimbic striatal structures observed in subjects with extremely high or extremely low impulsivity observed in ADHD and healthy control group.Reference Plichta and Scheres 39 Our findings have a potential translational application in the pharmacological treatment of behavioral disturbances in pTBI patients.Reference Wong 40 Lesion location could represent a low-cost, easy-to-use, para-clinical marker to help, among other factors, in the development of individualized treatment protocols.
Indeed, our findings seem to suggest that in subjects with isolated lPFC lesions D1-agonists could represent the treatment of choice for aggressive behaviors, while the compounds in this class should be avoided in subjects with isolated mPFC lesions.
Albeit indirectly, moreover, our data also advise prudence in the use of D1-active drugs in subjects with mixed mPFC/lPFC, even if our study did not directly investigate this patient group. However, while this proof-of-concept study suggests the importance of a personalized approach to aggression treatment in pTBI, future studies are needed to explore its relevance in day-to-day clinical care.
Interestingly (but unexpectedly), given the widespread use of D2-antagonists to treat behavioral disturbances in pTBI,Reference Fowler, Hertzog and Wagner 41 we did not find any effect of the DRD2 SNP on aggression in our target populations. We argue that this observation, while it needs to be interpreted with caution, is in line with the growing evidence of the difficulties in generalizing findings from general psychiatry to neuropsychiatry. Indeed, different studies showed that chronic reduction of D2 tone using DRD2 inhibitors after TBIs increases the risk of stable cognitive deficits,Reference Kline, Massucci and Zafonte 42 , Reference Hoffman, Cheng, Zafonte and Kline 43 which, given the relationship between cognitive deficits and behavioral disturbances in pTBI, could counter the potentially positive effect of D2 inhibition on aggressive behaviors in this population.
One of the key aspects of our study is the composition of our patient group. Our experimental group is highly homogeneous regarding pTBI (all subjects suffered combat-related pTBI during their service in Vietnam), their demographic characteristics (all subjects suffered pTBI during their early adulthood), and their pre-injury cognitive levels. Moreover, all subjects were matched for their early negative experience burden and their exposure to aggressive environments (ie, all of them were exposed to infantry warfare and suffered a major injury). While this homogeneity allowed us to control for possible confounding factors (eg, pre-injury characteristics, TBI dynamics, and exposure to significant aggressive behaviors), it also represents the main limitation of this study, which prompts the need to also evaluate our findings in non-military heterogeneous populations. Another limitation of this study is the lack of anatomical information on pTBI-related white matter damage, since retained metal fragments in the brain preclude high resolution structural MRI studies.
Moreover, in this study we focused on DRD1 and DRD2, as they represent the prototypical members of the 2 families of dopamine receptors (ie, the DRD1-like and the DRD2-like families).Reference Seeman and Van Tol 15 Future studies, however, are warranted to explore the role of other dopaminergic receptors in behavioral disturbances in pTBI, especially taking into account the differences in the anatomical localization of the different receptors. DRD4, for example, seems to be of particular interest, as it is widely expressed in the PFCReference de Almeida, Palacios and Mengod 44 and been associated with inter-individual differences in externalizing behaviors,Reference DeYoung, Peterson and Séguin 45 as well as with resilience after negative life experiences.Reference Bakermans-Kranenburg, van Ijzendoorn, Caspers and Philibert 46
The longitudinal aspect of our study allowed us to evaluate the behavioral consequences of pTBI across the patients’ lifetime, which are a major determinant of quality of life levels both for our patients and their caregivers. Furthermore, the length of our follow-up suggests caution in the interpretation of our data, especially regarding their generalizability to the acute and sub-acute settings.
Conclusions
Our results suggest that pTBI modulates the relationship between pTBI-related aggression and the dopaminergic system in a lesion-location dependent way; potentially, lesion location could help in the development of individualized therapies for treatment-resistant aggression, for example, suggesting prudence in the use of D1-antagonists in subjects with lPFC lesions or of D1-agonists in subjects with mPFC damage. Pharmacological studies are warranted to explore the translational relevance of our findings.
Disclosures
Dr. Pardini received an educational grant from the nonprofit association AKWO, Lavagna (Genoa, Italy). Dr. Krueger, Dr. Hodgkinson, Dr. Raymont, Dr. Strenziok, Dr. Wassermann, and Dr. Amore report no disclosures. Dr. Goldman serves on the editorial boards of Biological Psychiatry and Addictions Biology. Dr. Grafman was supported by the U.S. National Institute of Neurological Disorders and Stroke intramural research program and a project grant from the U.S. Army Medical Research and Material Command administrated by the Henry M Jackson Foundation (Vietnam Head Injury Study Phase III: a 30-year post-injury follow-up study) and serves as co-editor of Cortex.