Introduction
Pulmonary veno-occlusive disease is a very rare and life-threatening form of pulmonary hypertension characterised by obliterative fibrotic vasculopathy of the small branches of the pulmonary venous tree.Reference Lantuéjoul, Sheppard, Corrin, Burke and Nicholson1–Reference Mandel, Mark and Hales4 This obstructive and progressive disorder of the pulmonary veins and capillaries has no known cure and is not amenable to standard pulmonary artery hypertension strategies. Medical pulmonary hypertension therapies and diuretics are used to palliatively reduce pulmonary arterial pressure and augment right heart function until lung transplantation, without which survival is estimated at 14–24 months.Reference Montani, Achouh and Dorfmüller2,Reference Woerner, Cutz, Yoo, Grasemann and Humpl3
In severe pulmonary hypertension, a restrictive atrial septal defect with a right-to-left shunt can decompress suprasystemic right ventricular pressure and enhance left ventricular filling, but permits global hypoxaemia and relies on high diastolic pressures. A more recent alternative is creation of a reverse Potts shunt between the left pulmonary artery and the descending aorta. Unlike the atrial septostomy, the reverse Potts shunt immediately reduces right ventricular afterload and equalises systemic and pulmonary pressures. A right-to-left shunt beginning after the take-off of the left subclavian artery also limits hypoxaemia to the lower body, allowing optimal oxygenation of myocardial and cerebral tissue. Current data suggest comparable survival rates for reverse Potts shunt and lung transplantation in severe refractory pulmonary hypertension. Critically ill patients who are precluded from listing for transplantation due to their tenuous clinical status pose a significant clinical challenge. In centres equipped with a dedicated pulmonary hypertension team and advanced surgical capabilities, reverse Potts shunt may be considered despite the historically recognised increased mortality in patients undergoing reverse Potts shunt in conjunction with mechanical ventilation and extracorporeal membrane oxygenation.Reference Grady, Canter and Wan5,Reference Hayes, Jennerich and Coleman6 Herein, we report the surgical creation of a reverse Potts shunt with an 8 mm Gore-tex tube graft in a patient on extracorporeal membrane oxygenation with pulmonary veno-occlusive disease who was successfully decannulated and later underwent lung transplantation.
Case
The following case is presented with written permission from the patient and the patient’s legal guardian. A 14-year-old male with asthma and epilepsy presented to a cardiology clinic with chest pain, lightheadedness, syncope, and exercise intolerance attributed to new seizure semiology. Electrocardiography revealed right ventricular hypertrophy and prolonged corrected QT interval.. Echocardiography revealed severely decreased right ventricle function, severe right ventricle dilation, and supra-systemic right ventricle pressure. Physical exam was remarkable for a malnourished teenager with an increased right ventricle impulse, hepatomegaly, and a cyanotic appearance. He was admitted for management of newly diagnosed severe pulmonary hypertension.
Chest CT with angiography revealed diffuse centrilobular ground-glass airspace opacities, peribronchial thickening, septal thickening, and right ventricle enlargement suggestive of pulmonary veno-occlusive disease. Lung biopsy confirmed the diagnosis with demonstrated severe occlusion of pulmonary vein branches, capillary proliferation, haemorrhagic oedema, hemosiderin laden macrophages, and moderate to severe pulmonary arteriopathy. The patient was discharged after stabilisation with milrinone, treprostinil, and nighttime oxygen supplementation.
One month later, he was readmitted with acutely worsening right ventricle function and progressed to bradycardic arrest. During cardiopulmonary resuscitation, he was intubated and rapidly cannulated onto veno-arterial extracorporeal membrane oxygenation via neck vessels. Atrial septostomy was performed on extracorporeal membrane oxygenation day 2 with serial dilations with the final catheter being a 13.5 mm B. Braun septostomy balloon. After 4 days, he was decannulated from veno-arterial-extracorporeal membrane oxygenation support, but then developed refractory hypotension and was re-cannulated.
Due to failed attempts at weaning from extracorporeal membrane oxygenation and poor haemodynamic suitability for lung transplantation, reverse Potts shunt was performed five days after his second cannulation. While on extracorporeal membrane oxygenation, through a left posterior thoracotomy in the fourth intercostal space, the ligamentum arteriosum was divided and the left pulmonary artery and descending aorta were dissected free. After systemic heparinization, side-biting clamps were applied, and the valveless reverse Potts shunt was created between the left pulmonary artery and descending aorta using an 8 mm Gore-Tex tube graft trimmed to 2 cm in length.
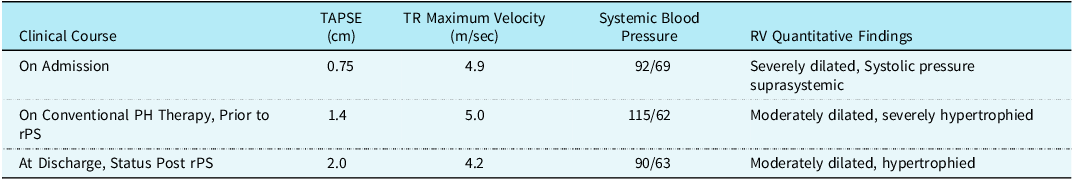
The patient was decannulated from extracorporeal membrane oxygenation in the operating room. Transthoracic echocardiogram 24 hours later revealed normal right ventricle and left ventricle systolic function. The patient was discharged after four weeks. Tricuspid annular plane systolic excursion increased from 0.75 cm to 2.0 cm from the day of admission to date of discharge (Table 1). Flow across the shunt was bidirectional at discharge. He received a lung transplant a year later. The reverse Potts shunt was taken down during the transplant surgery. There were no bleeding complications. He is now at home and doing well.
Echocardiogram findings. TAPSE: tricuspid annular plane systolic excursion; TR = tricuspid valve; RV = right ventricle; PH = pulmonary hypertension; rPS = reverse Potts shunt

Discussion
Utilisation of the reverse Potts shunt in this case emphasises the viability of veno-arterial-extracorporeal membrane oxygenation as a lifesaving manoeuvre in severe pulmonary hypertension crises. Reverse Potts shunt is not typically offered to patients with acute right heart failure due to concerns regarding high mortality in this group.Reference Grady, Canter and Wan5,Reference Hayes, Jennerich and Coleman6 However, in a subset of patients already cannulated to extracorporeal membrane oxygenation, consideration of reverse Potts shunt to facilitate decannulation is reasonable to preserve the option for future transplant especially when the potential for candidacy is uncertain.
As the experience with reverse Potts shunt for palliation of drug-refractory pulmonary hypertension evolves, specific attention is being paid to higher-risk patients with poor right ventricle function. The addition of a unidirectional-valved shunt to the reverse Potts shunt conduit has been described by Rosenzweig et al.Reference Rosenzweig, Ankola and Krishnan7 to prevent backflow during episodes of supra-pulmonary systemic pressure. This adaptation may further expand the use of reverse Potts shunt in high-risk patients.
For many patients with severe pulmonary hypertension due to pulmonary vascular disease, a lung transplant may become inevitable. In cardiorespiratory failure requiring extracorporeal membrane oxygenation support, creation of a reverse Potts l shunt is a high-risk procedure.Reference Grady, Canter and Wan5,Reference Hayes, Jennerich and Coleman6 Reverse Potts shunt can be cautiously considered as an alternative to long term extracorporeal membrane oxygenation as a bridge to transplantation.
Financial support
This research received no specific grant from any funding agency, commercial, or not-for-profit sectors.
Competing interests
None.
Ethical standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national guidelines and with the Helsinki Declaration of 1975, as revised in 2008, and has been approved by The Institutional Review Board of Children’s National Hospital. The patient provided informed written consent for the publication of the study data.