Introduction
Nursing home residents have very high rates of anxiety, depression and the behavioral symptoms associated with dementia. In an Australian survey, 24% of newly admitted residents met criteria for major depression (McSweeney and O'Connor, Reference McSweeney and O'Connor2008). All were cognitively impaired and might have been missed had residents with dementia been excluded from consideration. In another Australian study, nursing home staff rated 82% of residents positively on the BEHAVE-AD scale for activity disturbance or aggression (Brodaty et al., Reference Brodaty2001). Comparable findings emerged from studies in Hong Kong and the Netherlands (Chow et al., Reference Chow2004; Smalbrugge et al., Reference Smalbrugge, Jongenelis, Pot, Eefsting, Ribbe and Beekman2006).
These various symptoms and behaviors are often treated using anxiolytic, antidepressant or antipsychotic medications. Antidepressant use has risen in Australian and Swedish nursing homes over the last twenty years or so as newer, safer medications have supplanted older, more toxic ones (Snowdon et al., Reference Snowdon, Day and Baker2006; Lövheim et al., Reference Lövheim, Sandman, Kallin, Karlsson and Gustafson2008). Similarly, second generation antipsychotics are now preferred to first generation preparations (Greve and O'Connor, Reference Greve and O'Connor2005). In line with these changes, half or more of nursing home residents in Australia, Canada, Europe and Scandinavia were prescribed a psychotropic medication, most commonly an antidepressant or antipsychotic (Draper et al., Reference Draper2001; Sørensen et al., Reference Sørensen, Foldspang, Gulmann and Munk-Jørgensen2001; Gobert and D'hoore, Reference Gobert and D'hoore2005; Hosia-Randell and Pitkälä, Reference Hosia-Randell and Pitkälä2005; Lövheim et al., Reference Lövheim, Sandman, Kallin, Karlsson and Gustafson2008; Mann et al., Reference Mann, Köpke, Haastert, Pitkäla and Meyer2009; Nijk et al., Reference Nijk, Zuidema and Koopmans2009). In general, antipsychotic use was correlated with psychosis, agitation and night-time disturbance while antidepressant use was correlated with depressive symptoms (Draper et al., Reference Draper2001; Mann et al., Reference Mann, Köpke, Haastert, Pitkäla and Meyer2009; Nijk et al., Reference Nijk, Zuidema and Koopmans2009). In one Canadian study, only 14% of residents started on an antipsychotic had been reviewed by a geriatrician or psychiatrist in the previous 60 days (Bronskill et al., Reference Bronskill2004).
It is striking that rates of depression and agitation are so high while antidepressant and antipsychotic medications are dispensed so liberally. One explanation is that surveys exaggerate levels of psychopathology. Depending on the choice of measurement tool, nursing staff might rate agitated behaviors as “present” when, in reality, they occur only occasionally. If true, this might explain why antipsychotic medications can often be withdrawn without ill effects (Cohen-Mansfield et al., Reference Cohen-Mansfield1999; Ballard et al., Reference Ballard2004).
Another explanation is that treatments work less well in settings where large numbers of residents have an organic mental disorder, multiple medical comorbidities and limited psychosocial supports (Ryan et al., Reference Ryan, Kidder, Daiello and Tariot2002; Snowden et al., Reference Snowden, Sato and Roy-Byrne2003). Most pharmacological trials exclude nursing home residents, resulting in a dearth of evidence to guide clinicians in their choice of treatments. Experience suggests that effective therapy is often hard won, requiring serial trials of medications in a range of doses. Larger, more inclusive studies of efficacy, effectiveness and safety are required.
A third reason for the seeming mismatch between treatment and clinical outcome might be a failure by nursing home staff and attending medical practitioners to follow current practice guidelines. These stipulate that residents’ mental state and behavior are checked regularly and that treatment modalities and doses are changed accordingly (American Geriatrics Society and American Association for Geriatric Psychiatry, 2003; Nakajima and Wenger, Reference Nakajima and Wenger2007). In our study of depression in newly admitted nursing home residents, antidepressant medications were rarely reviewed, even when residents were so severely depressed that we were obliged to tell doctors of our concerns (McSweeney and O'Connor, Reference McSweeney and O'Connor2008).
As a result of these observations, we considered a range of interventions to encourage doctors and nursing home staff to attend better to residents’ mood and to monitor treatment more rigorously. As part of our quest for research funding, we gathered data on the changes made by doctors to psychotropic medications over a six-month period following residents’ admission to seven nursing homes in Melbourne, Australia. We anticipated that medications would be started more often than stopped and that few residents would be switched from one type of antidepressant or antipsychotic to another. Our findings, while modest, might still be of interest since, to our knowledge, only Selbæk et al. (Reference Selbæk, Kirkevold and Engedal2008) have tracked naturalistic prescribing practices within a single nursing home cohort.
Methods
Following approval by a research ethics committee, we approached a convenience sample of seven nursing homes in Melbourne's south-eastern suburbs. Six were private facilities and one was private-not-for-profit. Their bed numbers ranged from 45 to 99 (mean 71). All agreed to participate though two withdrew later following changes to senior personnel. The homes were sufficiently dispersed to be served by three aged psychiatry services. It is unlikely that any medical practitioners visited more than one facility.
The medication sheets of newly admitted residents were monitored over a six-month period, noting regular daily prescriptions of antidepressant, antipsychotic, anxiolytic and hypnotic medications. In line with our tightly circumscribed goals, we gathered no other information on residents’ mental or physical status.
Results
Complete data were obtained for 166 of the 223 persons (74%) admitted to the seven facilities over the audit period. Records were incomplete for 57 residents because of death or transfer (32 cases) and withdrawal from the study (25 cases). Of the 166 residents described below, most were female (66.9%). Ages ranged from 49 to 105 years (mean 84.9).
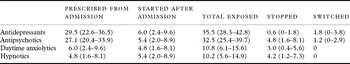
The numbers and types of prescribed psychotropic medications are listed in Table 1. Overall, 64 residents (38.6%) took one of the four medication classes, 17 (10.2%) took two classes and four (2.4%) took three.
Percentage (with 95% confidence intervals) of residents regularly prescribed medication classes from or after admission with subsequent stops and switches within the same class (N = 166).

Antidepressants were prescribed commonly at admission with serotonin re-uptake inhibitors accounting for the majority (63.2%). Only one person took a tricyclic antidepressant. Antipsychotic medications were dispensed almost as frequently though only three of the residents concerned had a chart diagnosis of schizophrenia. Second generation antipsychotics accounted for 89.1% of prescriptions. Anxiolytics and hypnotics (all benzodiazepines) were used much less often. At the time of admission, only one resident took both a daytime anxiolytic and a hypnotic. Six months later, the number had increased just to three meaning that only 12.6% of residents took any sort of benzodiazepine.
In the six months following admission, an antidepressant was started in ten cases (6.0%), an antipsychotic was started in nine (5.4%), an anxiolytic in eight (4.8%) and a hypnotic in nine (5.4%).
Once started, antidepressant medications were stopped over the six-month period in only one of 59 treated cases (1.7%); antipsychotics were stopped in eight of 54 treated cases (14.8%); anxiolytics were stopped in five of 18 treated cases (27.8%), and hypnotics were stopped in seven of 17 treated cases (41.1%). Switches from one to another member of the same class were rare.
Discussion
The audit was small and our findings might therefore not be representative of nursing home practice throughout Melbourne, let alone Australia. At the same time, initial prescribing rates for antidepressants and antipsychotics were broadly similar to those reported previously in Sydney, Australia (Draper et al., Reference Draper2001; Snowdon et al., Reference Snowdon, Day and Baker2006), and were close to the mid-point of rates reported over the past decade in six other countries (Gobert and D'hoore, Reference Gobert and D'hoore2005; Hosia-Randell and Pitkälä, Reference Hosia-Randell and Pitkälä2005; Lövheim et al., Reference Lövheim, Sandman, Kallin, Karlsson and Gustafson2008; Mann et al., Reference Mann, Köpke, Haastert, Pitkäla and Meyer2009; Nijk et al., Reference Nijk, Zuidema and Koopmans2009).
The point of the audit was to track changes in prescribing patterns over time. Antidepressants were started in only 6.0% of all cases. Antipsychotics were added almost as often. It was striking, though, that antidepressants were rarely stopped. Antipsychotic prescribing practice was a little more dynamic with treatments being stopped and started in almost equal numbers. Even so, most residents taking an antipsychotic on admission were still taking it six months later. Benzodiazepines were used much less often and were stopped quite frequently.
While our capacity to comment on doctors’ prescribing practices is limited by the lack of contemporaneous measures of residents’ mental status and behavior, evidence from previous studies suggests that treatment revisions were almost certainly insufficient to address the proven high rates of treatment-resistant major depression on the one hand and the needlessly high use of antipsychotics on the other (Cohen-Mansfield et al., Reference Cohen-Mansfield1999; Ballard et al., Reference Ballard2004; McSweeney and O'Connor, Reference McSweeney and O'Connor2008).
Ideally, admission to a nursing home should prompt a review of medications with a view to promoting quality of life, palliating distress and minimizing polypharmacy (Shrank et al., Reference Shrank, Polinski and Avorn2007). This requires, though, that staff have access to accurate, detailed background information. It is helpful to know who prescribed a medication, for what reason and with what success. Some residents, for example, will have experienced recurrent, severe depressive episodes that relapsed when treatment was stopped. Others, by contrast, will have taken an antidepressant for uncertain reasons with dubious benefit. The problem for medical practitioners is that few nursing home residents can give an accurate history; documentation is typically sparse; the symptoms of depression and dementia overlap; and nursing staff are loathe to destabilize treatment, especially when residents are not overtly disturbed. These are all barriers to change.
In theory, nursing homes provide an ideal venue for mental health care. Residents are always available; they interact constantly with staff; treatment compliance is virtually assured, and adverse effects can be monitored closely (Carlson and Snowden, Reference Carlson and Snowden2007). Evidence-based protocols for antidepressant use in aged primary care patients can be readily adapted to residential settings and guidelines for antipsychotic use are easily accessed (Mulsant et al., Reference Mulsant2001; International Psychogeriatric Association, 2003). In reality, efforts to persuade primary care physicians to review and revise psychotropic medications more assertively, and to create a more critical mindset on the part of nursing staff, are likely to fail without additional support.
Individualized, multifaceted treatment plans implemented by nursing and allied health staff together with medical practitioners have significantly reduced late-life depressive symptoms in community-based research projects in the U.K. (Blanchard et al., Reference Blanchard, Waterreus and Mann1995; Banerjee et al., Reference Banerjee, Shamash, Macdonald and Mann1996) and the U.S.A. (Unützer et al., Reference Unützer2002; Bruce et al., Reference Bruce2004). A similar approach proved successful, albeit to a modest degree, in an Australian residential community (Llewellyn-Jones et al., Reference Llewellyn-Jones, Baikie, Smithers, Cohen and Snowdon1999). Transplanting these initiatives into routine residential care, where staffing levels and budgets are strictly rationed, is challenging.
In Australia, new residents of aged care facilities must now be rated by staff on mood and behavior scales to better inform comprehensive, multidisciplinary care plans. It remains to be seen if scores are valid and reliable and if high or low ratings lead to changes in management strategies. Medical practitioners now receive a written medication review prepared by a pharmacist shortly after admission and then annually and they can access government rebates for participating in clinical review meetings with residential staff, family members and pharmacists.
In Sweden and Australia. structured pharmacist reviews reduced inappropriate prescribing (Schmidt et al., Reference Schmidt1998; Roberts et al., Reference Roberts2001) suggesting that pharmacists play a useful role in triggering reviews by nursing and medical staff of residents’ mental state and behavior with a view to reducing or ceasing medications, most notably antipsychotics.
While pharmacists’ reviews of current medications help curb over-prescribing, they cannot address under-prescribing, most notably of antidepressants. One solution might be appoint a mental health nursing specialist or “champion” to screen new residents, gather information, liaise with primary care physicians, promote pharmacological and psychosocial care pathways, engage residents in activity programs, make referrals to aged psychiatry services and educate staff (Carlson and Snowden, Reference Carlson and Snowden2007). Such positions exist already in the fields of wound care and diabetes and warrant careful study.
In summary, we found that antidepressant medications were rarely stopped or switched. Residents who remained depressed, despite taking an antidepressant, might therefore have been deprived of treatment opportunities. While antipsychotics were stopped more often, most prescriptions remained unchanged over the six-month period. Benzodiazepine use was very much lower than in surveys conducted over a decade ago in Australia (Snowdon et al., Reference Snowdon, Vaughan, Miller, Burgess and Tremlett1995), Canada (Conn et al., Reference Conn, Ferguson, Mandelman and Ward1999) and Denmark (Sørensen et al., Reference Sørensen, Foldspang, Gulmann and Munk-Jørgensen2001), pointing to notable improvements in practice over time.
Conflict of interest
None.
Description of authors’ roles
KM and DO'C secured the research grant. JG collected and analyzed data. All authors helped write the paper.
Acknowledgments
The study was supported by the L.E.W. Carty Charitable Fund and the Helen MacPherson Smith Trust. We are grateful to staff of participating nursing homes for their assistance.