Clostridioides difficile infection (CDI) is the most common healthcare-associated infection in the United States,Reference Magill, Edwards and Bamberg 1 with >450,000 cases and close to 30,000 deaths per year.Reference Lessa, Mu and Bamberg 2 The rate of relapse is ∼25%,Reference Cornely, Crook and Esposito 3 , Reference Louie, Miller and Mullane 4 and 58% of the $4.8 billion in annual healthcare costs attributable to C. difficile is linked to recurrent disease.Reference Lessa, Mu and Bamberg 2 Recurrent infection also causes significant morbidity due to repeat testing and treatment, rehospitalization, and possible colectomy.Reference Rodrigues, Barber and Ananthakrishnan 5 Thus, there is a need to identify practical ways of reducing the risk of CDI relapse, especially during times of heightened risk such as exposure to systemic antibiotics.
One strategy to prevent relapse is the prophylactic use of oral antibiotics with activity against C. difficile in patients with a history of CDI who require systemic antibiotics for other indications. Two retrospective analyses of the impact of prophylactic vancomycin have suggested that this strategy may be protective against CDI relapseReference Van Hise, Bryant, Hennessey, Crannage, Khoury and Manian 6 , Reference Carignan, Poulin and Martin 7 ; however, these analyses did not adjust for some confounders associated with CDI risk, including the numberReference Stevens, Dumyati, Fine, Fisher and van Wijngaarden 8 , Reference Nelson, Auerbach and Baltch 9 and risk classReference Bignardi 10 of systemic antibiotics given, severity of illness,Reference McFarland, Surawicz and Stamm 11 and use of gastric acid suppressants.Reference Zacharioudakis, Zervou, Pliakos, Ziakas and Mylonakis 12 , Reference Loo, Bourgault and Poirier 13 Therefore, we conducted a retrospective analysis of the impact of prophylactic oral vancomycin on the incidence of CDI relapse, using detailed electronic health record data to account for differences between patients who did and did not receive prophylaxis.
Methods
Study design
We conducted a retrospective cohort study of adults hospitalized at 2 academic medical centers in Boston, Brigham and Women’s Hospital (BWH) and Massachusetts General Hospital (MGH). We identified all patients from January 1, 2009, through June 30, 2015, who tested positive for toxigenic C. difficile by either stool toxin enzyme immunosorbent assay (ELISA, formerly Alere, subsequently acquired by Abbott Laboratories, Chicago, IL) or nucleic acid amplification testing (NAAT, Cepheid, Sunneyvale, CA). The testing algorithm included a dual toxin and glutamate dehydrogenase (GDH) antigen test with NAAT used in the case of indeterminate results. Test results from either hospital, or outpatient primary care and specialty practices affiliated with either hospital, were eligible. Patients were included if they had any hospitalizations at BWH or MGH within the subsequent 150 days after a positive test during which at least 1 dose of a systemic antibiotic was administered. We chose 150 days to allow for a large sample of eligible patients while limiting patients with very remote infections who may not hve been considered candidates for prophylaxis. When multiple hospitalizations were eligible, only the first hospitalization was included. Patients with positive C. difficile testing within 30 days before or 2 days after admission were excluded to omit patients with active CDI.
Group assignment
Patients who received oral vancomycin within 1 calendar day before or after starting systemic antibiotics were included in the vancomycin exposure (exposed) group. Patients who began oral vancomycin on day 2 after systemic antibiotic exposure underwent chart review by 1 study physician (D.A.C.) to determine whether the intent was prophylaxis or active treatment for recurrent CDI. Cases in which documentation indicated prophylactic intent were included as part of the exposed group. Cases in which the treatment intent was therapeutic were included in the unexposed group and classified as instances of CDI relapse. In addition, all patients who did not receive oral vancomycin within 2 days of starting systemic antibiotics were included in the unexposed group.
Outcomes and subgroups
The primary outcome was positive C. difficile testing within 90 days after systemic antibiotic exposure by either toxin assay or NAAT. Secondary outcomes included CDI relapse within 180 days and toxin-positive CDI only. We performed a stratified analysis among patients with 1 versus 2 or more positive C. difficile tests within the previous 12 months based on a previous trial;Reference Carignan, Poulin and Martin 7 patients enrolled during calendar year 2009 were excluded from this analysis to ensure complete data. Finally, we analyzed rates of relapse after limiting the exposed group to those who received oral vancomycin on all systemic antibiotic days, and separately after excluding unexposed patients who received oral vancomycin after day 2 in the absence of a positive C. difficile test.
Data collection
We collected the following data from an institutional electronic database: age, sex, race, hospital admission and discharge dates, vital status upon discharge, hospital length of stay, patient comorbidities derived from diagnosis codes using the method of Elixhauser et al,Reference Elixhauser, Steiner, Harris and Coffey 14 ICU utilization, C. difficile test results, daily inpatient medication administration records, and all outpatient prescriptions. The most abnormal serum laboratory values within 1 day of study inclusion were collected for hematocrit, albumin, creatinine, lactate, and total bilirubin; missing values were imputed with the mean for each group. White blood cell count was treated as a categorical variable (Table 1). Antibiotic risk was classified as high, medium, or low risk based on published data (Appendix 1 online).Reference Bignardi 10 , Reference Brown, Khanafer, Daneman and Fisman 15 The study was reviewed and approved by the Partners Healthcare Institutional Review Board.
Baseline Characteristics

Note. IPTW, inverse probability weighting; SD, standard deviation; BWH, Brigham and Women’s Hospital; LOS, length of stay; CPT, current procedural terminology; PPI, proton pump inhibitor.
a See Appendix 1 for antibiotic risk class assignments.
Statistical analysis
Data were analyzed using R statistical software version 3.5.0 (R Foundation for Statistical Computing, Vienna, Austria). Baseline covariates were compared between groups using univariate logistic regression. We estimated the average effect of treatment using inverse probability weighting for each comparison. Inverse probability weights incorporate a propensity score for treatment and the probability of missing data using Super Learner, an ensemble machine-learning algorithm that assesses multiple machine-learning methods and then uses cross validation to select the most accurate method or combination of methods in the algorithm library specified by users.Reference Pirracchio, Petersen and van der Laan 16 , Reference Gruber and van der Laan 17 Super Learner combines propensity score predictions from multiple algorithms; our analysis used Lasso, elastic-net regularized generalized linear models, classification and regression tree (CART), and random forest. Super Learner optimally combines the predicted values from each candidate learner through a weighted average and computes estimated predicted values that asymptotically outperform each of the candidate estimators in the library even if the “correct” parametric model is not included in the candidate library. Super Learner has been shown to reduce bias and improve propensity score prediction compared with traditional logistic regression.Reference Lee, Lessler and Stuart 18
We assessed all available covariates, as well as a set of covariates proposed by the authors based on clinical experience, to calculate propensity score and conditional probability. The covariate set proposed by the authors included age, Elixhauser score, antibiotic risk class, days since most recent positive C. difficile test, number of prior positive C. difficile tests, and ICU admission.
Using these propensity scores, we calculated the estimated treatment effect of oral vancomycin using a weighted logistic regression model, with the inverse probability weights calculated as: Itrt ×[Δ/missingness probability) + (1 − Itrt )×(PS/(1 − PS)]×Δ/missingness probability, where Δ = 0 indicates death before relapse, otherwise Δ = 1. We truncated the inverse probability weights at the 99th percentile. A robust standard error estimate was used to calculate 95% confidence intervals on the log scale.
Results
In total, 760 patients met inclusion criteria. Of these, 193 of 760 (25%) received oral vancomycin within 1 calendar day of starting systemic antibiotics and 567 of 760 (75%) did not. (Table 1).
The mean duration of systemic antibiotic exposure was 5.99 days (SD, 6.29) for the exposed group versus 5.41 days (SD, 6.65) for the unexposed group (P = .27). Within the exposed group, oral vancomycin was administered on all systemic antibiotic days in 118 patients (61%) and on at least half of all antibiotic days in 152 patients (79%). The mean duration of oral vancomycin was 2.29 days (SD, 5.77). Outpatient antibiotic prescriptions (other than oral vancomycin) were given at discharge to 54.4% and 50.6% of patients in the exposed and unexposed groups, respectively (P = .41). Also, 78 patients in the unexposed group received oral vancomycin 3 or more days after antibiotic exposure, either preceding or in the absence of a positive C. difficile test. No patients began oral vancomycin on day 2, so no chart reviews were performed.
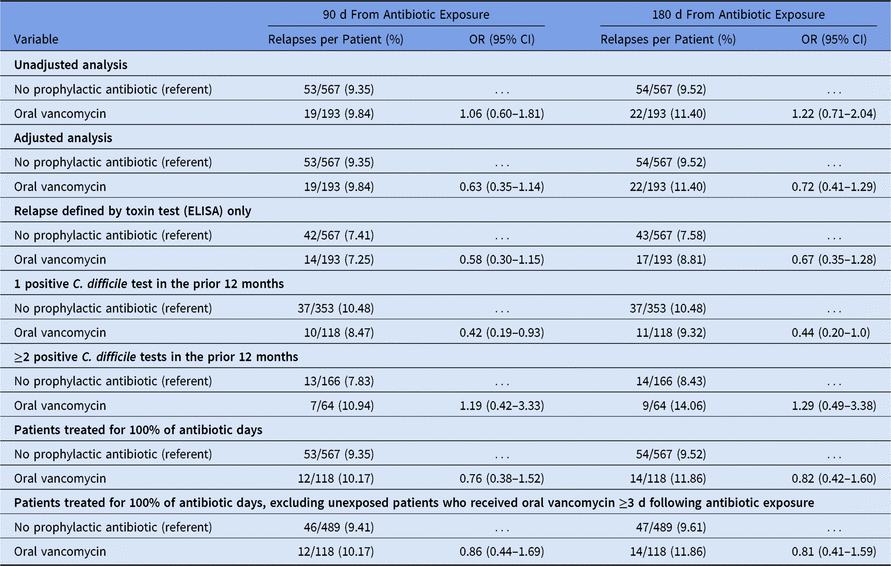
Overall, CDI relapse occurred in 76 of 760 patients (10%); at 90 days, there were 19 relapses among 193 patients (9.8%) in the exposed group and 53 relapses among 567 patients (9.4%) in the unexposed group (Table 2). At 180 days, there were 3 additional positive assays in the exposed group (total 22, 11.4%) and 1 additional positive assay in the unexposed group (total 54, 9.5%). At 90 days, there were 14 positive toxin assays in the exposed group (7.3%) and 42 in the unexposed group (7.4%). Mean days between antibiotic exposure and relapse were 34.47 days (SD, 28.64) in the exposed group and 29.40 days (SD, 28.70) in the unexposed group. At 90 days of follow-up, 31 of 193 (16.1%) patients in the exposed group had died and 99 of 567 (17.5%) in the unexposed group had died. At 180 days of follow-up, 42 of 193 (21.8%) patients in the exposed group had died and 130 of 567 (22.9%) in the unexposed group had died.
Unadjusted and Adjusted Results

Note. OR, odds ratio; CI, confidence interval; ELISA, enzyme-linked immunosorbent assay.
The unadjusted odds ratio (OR) for the primary outcome at 90 days was 1.06 (95% confidence interval [CI], 0.60–1.81) for the exposed versus unexposed group (Table 2). After inverse weighting, the adjusted odds ratio for relapse at 90 days was 0.63 (95% CI, 0.35–1.14) for the exposed versus unexposed group. The adjusted odds ratios were similar for risk of relapse within 180 days and when restricting the analysis to patients with toxin-positive CDI relapse (Table 2). For patients with only 1 prior positive C. difficile test in the preceding 12 months, the odds of relapse at 90 days were 0.42 (95% CI, 0.19–0.93) for the exposed versus unexposed group. For patients with 2 or more positive C. difficile tests in the preceding 12 months, the odds of relapse at 90 days were 1.19 (95% CI, 0.42–3.33) for the exposed versus unexposed group. Among patients in the exposed group who received oral vancomycin on all systemic antibiotic days, the odds of relapse were 0.76 (95% CI, 0.38–1.52) at 90 days and 0.82 (95% CI, 0.42–1.60) at 180 days versus the unexposed group. After excluding the 78 patients in the unexposed group who received oral vancomycin 3 or more days after antibiotic exposure, the odds of relapse at 90 days were 0.86 (95% CI, 0.44–1.69) and at 180 days were 0.81 (95% CI, 0.41–1.59) in the exposed versus unexposed group.
Discussion
Effective strategies are needed to prevent CDI, particularly in patients at high risk for recurrent disease. Oral antibiotic prophylaxis with vancomycin has gained attention in recent years, specifically in patients with a history of C. difficile who require systemic antibiotics for another infection. In this study, however, we found inconsistent short- and long-term benefits of prophylactic oral vancomycin for reducing the risk of CDI relapse when given alongside systemic antibiotics in hospitalized patients with a history of CDI. Although a potential protective effect of oral vancomcyin was seen in patients with only 1 previous CDI, we did not find any benefit among the full study population or in those with >1 prior episode of CDI.
Other investigators have reported more success with oral vancomycin for prevention of CDI relapse. In a retrospective study of 203 inpatients, Van Hise et alReference Van Hise, Bryant, Hennessey, Crannage, Khoury and Manian 6 reported an 88% reduced odds of CDI relapse within 4 weeks of antibiotic exposure in patients who received oral vancomycin alongside systemic antibiotics (OR, 0.12; 95% CI, 0.04–0.4).Reference Van Hise, Bryant, Hennessey, Crannage, Khoury and Manian 6 This study did not include a multivariate analysis, and although both study groups were similar in distribution of certain CDI risk factors, the analysis did not include measures of comorbidities, severity of illness, number of previous CDIs, or number of systemic antibiotics given.
A second retrospective study by Carignan et alReference Carignan, Poulin and Martin 7 evaluated 551 patients who received systemic antibiotics within 90 days following an initial or recurrent episode of CDI and followed them for relapse for 90 days after systemic antibiotic exposure. Overall, they reported a protective effect of oral vancomycin against relapse (adjusted hazard ratio [aHR], 0.59; 95% CI, 0.43–0.80), but the effect was limited to patients with ≥2 prior CDI episodes. They did not detect an effect among patients with only 1 previous CDI episode (aHR, 0.91; 95% CI, 0.57–1.45). This result contrasts with our findings, which only showed possible benefit in patients with 1 previous CDI and no benefit in those with ≥2 episodes. Our analysis included adjustments for several potential confounders that were not included in the prior study including gastric acid suppressants, antibiotic risk class, number of systemic antibiotics given, comorbid illness, and severity of illness. These factors may explain some of the differences in our findings.
Our study raises questions about the benefits of prophylactic oral vancomycin to prevent recurrent CDI in hospitalized patients receiving systemic antibiotics. This strategy might benefit patients with only 1 previous CDI, but the magnitude of this benefit is uncertain and contradicts results from a previous study. The rationale for oral prophylactic antibiotics in patients with a history of CDI seems intuitive and reflects extensive clinical experience using antibiotics to prevent infection in other circumstances such as severe immunosuppression and perioperative care, so it is understandable that this practice has become commonplace despite a lack of strong evidence. Importantly, however, the mechanism of CDI is unique compared to most other infections in that it requires a disturbed intestinal microbiome, a precondition which may be induced by antibiotics, including those with anti–C. difficile activity such as oral vancomycin. This concept is supported by a small randomized controlled trial of C. difficile decolonization in which use of oral vancomycin led to a significantly higher rate of recolonization after 2 months versus placebo.Reference Johnson, Homann and Bettin 19 Therefore, it is plausible that any prophylactic effect of oral vancomycin against C. difficile is counterbalanced by an adverse effect on other gut commensals and, thus, confers no long-term benefit against relapse.
This study has several limitations. As with all retrospective studies, our results could be affected by residual confounding; we attempted to mitigate this by including an extensive array of clinical variables and using a machine learning algorithm to identify the most consequential covariates, along with inverse probability weighting with propensity scoring to make robust estimates of treatment effect. These adjustments eliminated known differences between groups but unmeasured residual confounding could have remained. There was a slightly longer duration of antibiotic exposure in the exposed group (5.99 vs 5.41 days; P = .27), which could have biased results in favor of the unexposed group, although this difference was small and nonsignificant. We used laboratory testing alone to diagnose CDI relapse, leaving open the possibility that some positive C. difficile assays (ie, NAAT) may have merely represented colonization.Reference Polage, Gyorke and Kennedy 20 To address this possibility, we conducted a secondary analysis of relapse by toxin testing that yielded very similar results. Also, we could not determine the exact duration of antibiotic exposure after hospital discharge nor postdischarge antibiotic prescriptions due to the limitations of our institutional database. We did, however, show that rates of outpatient antibiotic prescriptions were similar across groups at discharge. We were only able to identify CDI relapse that was captured by laboratory testing at the 2 study hospital systems. Both study hospitals are large, academic medical centers, so our results may not be generalizable to other settings. Finally, confidence intervals for all effect estimates were wide and do not preclude the possibility that a study with more power could detect a positive effect of prophylaxis.
In conclusion, we found an inconsistent benefit of oral vancomycin for prevention of CDI relapse in patients with prior CDI and subsequent exposure to systemic antibiotics while hospitalized. Patients with only 1 prior CDI episode may have a reduced risk of CDI relapse from prophylactic oral vancomycin but there was no apparent benefit for patients with a history of ≥2 prior episodes of CDI. Prospective randomized trials are needed to determine whether this practice is truly beneficial.
Supplementary Material
To view supplementary material for this article, please visit https://doi.org/10.1017/ice.2019.88
Acknowledgments
The content is solely the responsibility of the authors and does not necessarily represent the official view of the Agency for Healthcare Research and Quality.
Financial support
Dr Rhee received support from the Agency for Healthcare Research and Quality for this study (grant no. K08HS025008).
Conflicts of interest
All authors report no conflicts of interest relevant to this article.