Universal gloving (UG), the use of gloves with every patient contact, has been suggested as an infection prevention adjunct and as an alternative to contact precautions. Studies demonstrate mixed effectiveness of UG as an infection prevention strategy.Reference Yin, Schweizer, Herwaldt, Pottinger and Perencevich 1 – Reference Bearman 4 Concerns exist about both the feasibility and acceptability of adopting UG. No studies have addressed attitudes toward UG by healthcare workers (HCWs) and patients, which could be an important step in the process of implementing this practice. Therefore, we assessed HCW and patient perceptions and barriers to UG.
MATERIAL AND METHODS
This survey-based study was conducted at a large tertiary care, 900-bed, academic hospital. Institutional Review Board–approved surveys were distributed by convenience sample; 12-item HCW surveys were distributed to HCWs in inpatient and outpatient settings, and 10-item patient surveys were distributed to adult patients attending outpatient clinics. Surveys were Likert-scale–based, anonymous, and voluntary. Pearson’s χ2 and Fisher’s exact tests were used to compare responses. A 2-way comparison of HCW vs patient responses and a 3-way comparison of nurse vs physician vs other HCW (medical/nursing student/nurse assistant) responses were conducted. Responses were analyzed using Statistical Analysis System software (v9.2, SAS Institute, Cary, NC).
RESULTS
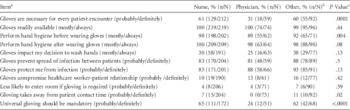
In total, 137 patient surveys and 392 HCW surveys were completed. HCWs included physicians (n=75), nurse practitioners/nurses (n=219), and others (nurse assistants and nursing/medical students, n=98). Responses are summarized in Table 1. Notably, the predominant barrier to UG for all HCWs was inconvenience (41%, 157 of 380). Although 84% (296 of 352) of all HCWs believed that UG decreases the risk of cross transmission, most physicians felt that UG was not necessary (69%, 41 of 59) and did not support the use of mandatory gloving (76%, 39 of 51). HCWs reported widespread glove availability (99.7%, 388 of 389) and self-assessed high compliance with hand hygiene (HH) both before (95%, 318 of 335) and after wearing gloves (99%, 360 of 363).
Perceptions of Universal Gloving and Hand Hygiene Practices by Healthcare Worker (HCW) Class

a Item 12 of the HCW survey did not use Likert-type scale answers and is not included in this table.
b Other includes assistant nurses and medical/nursing students.
c P values were obtained using a 3-way test of comparison.
HCW vs patient responses were also compared. Neither HCWs nor patients felt that UG compromises the HCW–patient relationship (88% vs 82%, P=.08). Patients and HCWs agreed that gloves prevent the spread of infection (88% vs 79%, P=.26). More HCWs claimed to perform HH after doffing gloves than was reported by patients (99% vs. 88%, P<.001). Patients were more enthusiastic about mandating UG than were HCWs (93% vs 57%, P<.001).
DISCUSSION
Even though the majority of nurses, medical students, and nursing students in our study agreed that gloves should be donned universally, only 31% of physicians concurred. Yet, when asked about the benefits of UG, almost 90% of all HCWs, including physicians, believed that gloves prevent the spread of infection. Despite the perceived infection prevention benefits, widespread glove availability, and self-reported high rates of hand hygiene (HH) compliance, HCWs perceived UG as an inconvenience. HCW barriers such as the belief that UG is unnecessary, coupled with its perceived inconvenience may pose implementation challenges, particularly among physicians. Patients reported that HCW HH compliance, specifically after wearing gloves, was less than compliance reported by HCWs. This is an important finding because HH overestimation by HCWs may compromise patient safety. Our findings agree with previous studies demonstrating that HCWs frequently fail to wash their hands after doffing gloves.Reference Loveday, Lynam, Singleton and Wilson 5 , Reference Girou, Chai and Oppein 6
Whereas some studies have demonstrated increased HH rates with UG, others have demonstrated that HH decreases with routine glove use.Reference Kim, Roghmann, Perencevich and Harris 7 – Reference Bearman, Marra and Sessler 9 Girou et alReference Girou, Chai and Oppein 6 reported that the failure to change or remove contaminated gloves between patient contacts accounted for 64% of missed HH opportunities.Reference Girou, Chai and Oppein 6 Although both HCW and patient respondents did not perceive a detrimental HH effect with UG, based on prior observations, the risk of negatively impacting HH remains a concern. UG should not be a substitution for HH. For programs advocating UG as an infection prevention adjunct, it is essential that UG be accompanied by robust HH promotion and assessment strategies for maximal benefit.
This report adds to the body of literature on UG and, to our knowledge, provides the only data evaluating patient and HCW perceptions and barriers to UG. Our study has several limitations. The use of convenience sampling methodology has the potential to introduce interviewer and response bias. The application of our questionnaires in a single institution may preclude our results from being generalized. The survey responses may also be subject to recall bias. Questions that were not addressed in this study include concerns related to the cost of UG and adverse events (eg, latex allergy, adverse patient outcomes, etc.).
Our findings suggest that UG is an infection prevention adjunct favored by most HCWs and patients, with little perception of harm for the patient–provider relationship. Mandatory UG, however, is not supported by most physicians, and many HCWs perceive UG as an inconvenience despite widespread glove availability. Even though HH compliance differs by HCW self-report and patient observation, both HCWs and patients feel that UG enhances safety. As HH remains a critical infection prevention strategy, facilities implementing UG as an infection prevention adjunct must have sustained HH education, monitoring, and feedback. In addition, programs instituting UG for patient care must target the perception of inconvenience and potential noncompliance by physicians. Infection prevention programs advocating the use of UG, particularly during outbreak conditions or during heightened respiratory virus activity, should aggressively educate providers on the potential benefits of UG to maximize compliance and acceptability.
ACKNOWLEDGMENTS
Financial support: None reported.
Potential conflicts of interest: All authors report no conflicts of interest relevant to this article.