Introduction
The developing fetus responds to stress in the intrauterine environment; this adaptation is an important contributor to the predisposition of adult-onset disease. Within the maternal-fetal unit, the placenta has increasingly been recognized as a major programming agent in the development of heart disease, hypertension, Type 2 diabetes, obesity and lung cancer.Reference Thornburg, O'Tierney and Louey1–Reference Kajantie, Thornburg, Eriksson, Osmond and Barker4 Yet, placental studies in the developmental origins of disease have been limited to those pregnancies complicated by intrauterine growth restriction and/or preeclampsia, or otherwise normal term pregnancies. Preterm premature rupture of membranes (PPROM) is associated with a stressful intrauterine environment, but is understudied in its relation to the developmental origins of disease. Intrauterine infection is thought to be a major contributor to PPROM, as well as the main risk factor for adverse neonatal outcomes, including cerebral palsy.Reference Grether, Nelson, Walsh, Willoughby and Redline5–Reference Yoon, Park and Chaiworapongsa12 Furthermore, it makes intuitive sense that the hostile fetal environment associated with PPROM may be an important modulator in the programming of adult metabolic syndrome.
Although PPROM accounts for ∼30–40% of preterm deliveries,Reference Ananth and Vintzileos13 the pathological findings in PPROM placentas are not well characterized. Prior studies of placental pathology have focused on preterm birth in the context of other complications.Reference Dammann, Allred and Leviton14–Reference Rana, Sawhney, Gopalan, Panigrahi and Nijhawan19 In those studies that have examined the PPROM subset, definitions of PPROM are not uniform, making generalizability difficult. Additionally, pathological studies of preterm placentas have focused on intrauterine inflammation, primarily chorioamnionitis and fetal vasculitis. However, histologic evidence of inflammation is not present in the majority of these placentas, nor is there necessarily a strict progression from chorioamnionitis to fetal vasculitis, as conventionally imparted.Reference Hecht, Allred and Kliman16, Reference Guzick and Winn20–Reference Redline24 Furthermore, studies of placental pathology in PPROM have been conducted in populations residing at sea level, calling to question whether different patterns exist at altitude.
We postulate that (1) there are unrecognized contributors to PPROM; (2) these non-inflammatory contributors may sometimes be found in association with inflammation; and (3) isolated fetal-derived inflammation may also contribute to PPROM. We further hypothesize that no differences in inflammatory patterns exist – but thrombotic findings may be more apparent – between our high altitude cohort (1600 m/5280 ft) and findings published from sea-level populations. Therefore, the goal of this study was to comprehensively characterize inflammatory and thrombotic histologic findings in placentas from pregnancies complicated by PPROM in a high-altitude population. Uncovering patterns of placental pathology in PPROM may reveal clues to the development of adult-onset disease, give insight into the variation of neonatal outcomes associated with PPROM, and ultimately aid in developing targeted interventions to prevent PPROM and its adverse consequences.
Methods
Placentas from PPROM pregnancies (>24 or <34 weeks at PPROM) were collected from women enrolled in a prospective cohort at the University of Colorado Hospital from July 1, 2010 to June 30, 2012. PPROM was confirmed by standard clinical characteristics of alkaline pH, ferning and pooling of amniotic fluid in the vagina on speculum examination in women >24 weeks or <34 weeks of gestation before the onset of labor. Clinical chorioamnionitis was defined as two or more of the following clinical criteria: maternal fever >38.0°C, maternal tachycardia (>100 beats/min), fetal tachycardia (>160 beats/min), maternal fundal tenderness, maternal leukocytosis (WBC > 15,000) and maternal purulent vaginal discharge odd ratio (OR) amniocentesis with findings consistent with chorioamnionitis.
Subjects with multiple gestation, hypertensive diseases of pregnancy or non-viable pregnancy were excluded. This research was conducted in accordance with the 2004 Declaration of Helsinki, with signed informed consent required for study participation (Colorado Multiple Institutional Review Board study 09-1107).
Demographic and pregnancy data were abstracted from the Perinatal Database of the Department of Obstetrics and Gynecology at the University of Colorado School of Medicine. Data abstraction was performed by a trained research assistant using a standardized protocol and verified by the principal investigator for PPROM subjects (J.A.W.). Ambiguity of clinical data was clarified by a senior maternal-fetal medicine specialist (V.D.W.).
Placenta analysis
Placentas were placed in formalin following delivery and then grossly examined within 72 h to assess for umbilical cord length and insertion, number of vessels, membrane insertion, trimmed weight, appearance of maternal and fetal surfaces, and the parenchyma. A minimum of four formalin-fixed paraffin-embedded blocks were generated, including cross-sections of umbilical cord, free fetal membranes and full-thickness placental parenchyma. At least one 5-μ section from each block was stained with hematoxylin and eosin and then examined by a placental pathologist (M.D.P.) to evaluate for the presence of any microscopic lesions.
Histologic acute chorioamnionitis (HCA) was defined as the presence of polymorphonuclear cells within the amnion or chorion (Fig. 1a). Fetal-derived inflammation was defined as the presence of an inflammatory infiltrate (polymorphonuclear cells) emanating from the fetal vessels of the umbilical cord (vasculitis or phlebitis) or chorionic plate (chorionic plate vasculitis), or funisitis – fetal inflammatory cells extending into Wharton's jelly (Fig. 1b and 1c). Maternal-derived inflammation was defined as chronic villitis (maternal lymphocytes infiltrating and destroying villi, Fig. 1d). Additional findings recorded included fetal thrombotic events such as intimal fibrin cushions (remote non-occlusive mural thrombi of stem villous or chorionic plate vessels as evidenced by intramural fibrin aggregates and intimal hyperplasia), hemorrhagic endovasculitis (non-inflammatory necrosis of villous vessels leading to red blood cell extravasation) and intervillous thrombi (leakage of villous capillaries causing slow feto-maternal hemorrhage). Presence of subchorionic thrombi (blood clots below the chorionic plate from maternal malperfusion, Fig. 1e) and placental infarcts (representing cessation of maternal blood flow) were also recorded.
Placental membranes were evaluated for the presence of acute inflammatory cells (arrows) extending through the decidua (the endometrium of the pregnant uterus) into the chorion (the membrane between the fetus and mother) or amnion (the membrane that encloses the fetus) (a, b). Inflammation of the umbilical cord (c) was classified as vasculitis if the inflammatory cells infiltrated through the umbilical cord vessel walls (arrow) or funisitis if they extended into the surrounding Wharton's jelly (asterisk). In some cases, there was inflammation of the chorionic plate (the fetal side of the placental disc) (d) emanating from fetal vessels and extending toward the amniotic cavity (arrow). Chronic villitis (e) is characterized by maternal lymphocytes encasing and invading the chorionic villi (asterisks). Some placentas showed subchorionic thrombi (f), a laminated clot formed below the chorionic plate because of slow/absent maternal blood flow.

Statistical analysis
Dichotomous variables were compared using χ 2 analysis (or Fisher's exact test) and continuous variables using Student's t-test or Mann–Whitney U-test when appropriate. Correlation coefficient was assessed using mean square contingency (ϕ) for dichotomous variables. To assess predictors of placental inflammation or thrombosis, we calculated ORs and 95% confidence intervals (CIs) using logistic regression. Univariate predictors included maternal age, race (Caucasian/non-Caucasian), ethnicity (Caucasian not of Hispanic origin, Caucasian of Hispanic origin, other), diagnosis of clinical chorioamnionitis, nulliparity, cesarean section, gestational age at rupture, gestational age at delivery, and membrane rupture interval from PPROM to delivery, and histologic chorioamnionitis; although smoking during pregnancy, auto-immune disease, and non-gestational diabetes were also predictors of interest, there were no cases within our cohort. Gestational age at delivery was treated as both continuous and trichotomous variables of <28, 28–32 and >32 weeks. To determine independent predictors of placental pathological patterns, we created multivariate models; on multivariate analysis, the model corrected for gestational age at delivery and included all covariates with a P-value of ⩽0.10 in the initial analysis. Stata 12.0 (Stata Corp, College Station, TX) was used for all statistical analysis. All tests were two-sided and P < 0.05 was considered significant.
Results
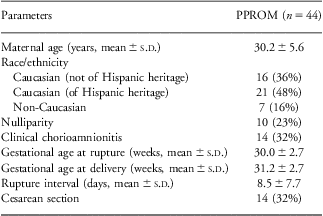
Demographics (Table 1)
Placentas from 44 pregnant women with PPROM were examined. Mean gestational age at membrane rupture was 30.0 ± 2.7 weeks (range 23 3/7–33 4/7 weeks). Mean gestational age at delivery was 31.2 ± 2.7 weeks (range 24 5/7–34 1/7 weeks). Average interval between PPROM and delivery was 8.5 days (range 0–36 days). All pregnant women were treated with antibiotics and betamethasone as per standard of care within our institution. Clinical chorioamnionitis was diagnosed in 32% (n = 14) of all PPROM pregnancies.
Clinical characteristics of patients with PPROM
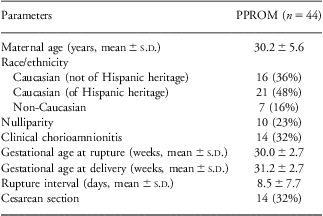
PPROM, preterm premature rupture of membranes; s.d., standard deviation.
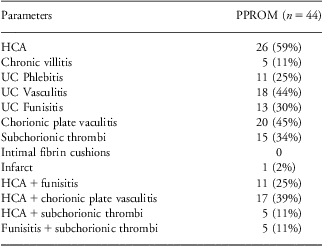
Patterns of inflammation and thrombosis (Table 2)
The overall prevalence of HCA was 59% (n = 26). HCA was poorly correlated with clinical chorioamnionitis diagnosis (11/26; 42%; ϕ = 0.27), although when clinical chorioamnionitis was diagnosed, HCA was often present (11/14; 79%).
Patterns of inflammation and thrombosis in PPROM placentas
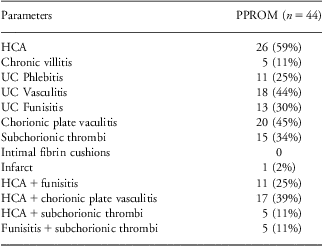
PPROM, preterm premature rupture of membranes; HCA, histologic chorioamnionitis; UC, umbilical cord.
Funisitis was seen in 30% of PPROM placentas. Eighty-five percent (11/13) of all PPROM placentas with funisitis also had HCA (ϕ = 0.34), but clinical chorioamnionitis was poorly correlated with funisitis (ϕ = 0.09).
Chorionic plate vasculitis was seen in 45% of PPROM placentas (n = 20). Chorionic plate vasculitis typically also had HCA (17/20; 85%; ϕ = 0.48), although chorionic plate vasculitis had less correlation with clinical chorioamnionitis (9/20; 45%; ϕ = 0.29). Chorionic plate vasculitis and funisitis were often seen together (ϕ = 0.30), yet one-third of funisitis cases did not have associated chorionic plate vasculitis.
Chronic villitis was present in only 11% of all PPROM placentas (n = 5), with the majority seen in >32 weeks of gestational age placentas (4/5; 80%). Chronic villitis was uncommonly seen with clinical chorioamnionitis (1/14; 7; ϕ = –0.09) or HCA (1/26; 4%; ϕ = –0.29). Chronic villitis was never seen with funisitis or chorionic plate vasculitis.
Subchorionic thrombi were seen in 34% of the placentas (n = 15). Subchorionic thrombi were more frequent in the absence of clinical chorioamnionitis (4/15; 27%; ϕ = −0.07) or HCA (5/15; 30%; ϕ = –0.38). Subchorionic thrombi and funisitis were both present in 11% of placentas (n = 5; ϕ = 0.05). Similarly, subchorionic thrombi and chorionic plate vasculitis were infrequently seen together (n = 8; 18%; ϕ = 0.11). Only one case of subchorionic thrombi also had chronic villitis.
Inflammation, thrombosis and gestational age (Fig. 2)
There was no difference in the diagnosis of clinical chorioamnionitis with gestational age at PPROM, gestational age at delivery or rupture-to-delivery interval. HCA was equally prevalent in placentas delivered at <28 weeks and 28–32 weeks (88% v. 71%; P = 0.62). However, HCA was less common in placentas delivered >32 weeks (37%; P = 0.02). There was no difference in mean rupture-to-delivery interval between PPROM placentas with and without HCA (7 v. 10 days; P = 0.26).
Patterns of inflammation and thrombosis in preterm premature rupture of membranes (PPROM) placentas in relation to gestational age. GA, gestational age; HCA, histologic acute chorioamnionitis; FUN, funisitis; CPV, chorionic plate vasculitis; THR, subchorionic thrombi.
Funisitis was equally prevalent in placentas delivered at <28 weeks (38%; P = 0.58) and 28–32 weeks (35%; P = 0.51). Although funisitis was seen less frequently in placentas delivered >32 weeks (21%), this finding was not statistically significant (P = 0.34). Chorionic plate vasculitis was more common in placentas delivered <28 weeks of gestational age (88%; P = 0.02) compared with those delivered at 28–32 weeks (41%; P = 0.04) and >32 weeks (31%; P = 0.01). Although gestational age at time of delivery was not significantly associated with funisitis (P = 0.13), the presence of chorionic plate vasculitis was inversely proportional to gestational age at delivery (P = 0.004; ϕ = −0.42). There was no difference in mean rupture-to-delivery interval between PPROM cases with and without funisitis (9 v. 8 days; P = 0.73), nor chorionic plate vasculitis (8 v. 9 days; P = 0.53).
There was no difference in subchorionic thrombi and gestational age at delivery (P = 0.49), nor was there an association with rupture-to-delivery interval with presence or absence of thrombi (10 v. 8 days; P = 0.32).
Predictors of inflammation and thrombosis
There were no independent predictors of clinical chorioamnionitis or HCA on multivariate analysis. On univariate analysis, HCA was a predictor of funisitis (OR = 5.9; CI =1.1–31.0; P = 0.04), but was not an independent predictor on multivariate analysis. However, there was a trend for Hispanic women to have higher odds of funisitis compared with non-Hispanic women (OR = 5.4; CI = 1.01–28.2; P = 0.05). Earlier gestational age at rupture and HCA were univariate predictors of chorionic plate vasculitis, but were not independent predictors on multivariate analysis. When adjusted for gestational age at delivery, the odds of subchorionic thrombi without HCA was 6.3 times greater that the odds of subchorionic thrombi with HCA (CI = 1.3–33.3; P = 0.02), regardless of maternal ethnicity.
Discussion
Overall, distinct patterns of placental pathology exist in PPROM. As expected, chorioamnionitis was common in PPROMReference Redline24–Reference Aziz, Cheng and Caughey27; at our institution, there was a moderate concordance of HCA with clinical chorioamnionitis. Yet, almost 40% of the PPROM placentas did not have HCA, suggesting a non-inflammatory mechanism for premature rupture. Although fetal-derived inflammation (funisitis and chorionic plate vasculitis) is a central pathological finding in PPROM, we determined that subchorionic thrombi may also be important. These findings suggest that PPROM may be triggered by separate mechanisms (inflammation and/or thrombosis).
Funisitis is recognized as the histologic manifestation of the fetal inflammatory response, and has been associated with adverse neurological outcomes.Reference Wu, Escobar and Grether11, Reference Pacora, Chaiworapongsa and Maymon28, Reference Yoon, Romero and Yang29 Funisitis has also been postulated to be the essential indicator of the fetal inflammatory response in preterm, but not term deliveries.Reference Kim, Yoon, Park, Kim and Chi30 Our prevalence of PPROM funisitis (30%) is consistent with most studies of PPROM as well as all preterm deliveries.Reference Pacora, Chaiworapongsa and Maymon28, Reference Kim, Yoon, Park, Kim and Chi30–Reference Germain, Carvajal and Sanchez33 In our cohort, funisitis had higher correlation with HCA than clinical chorioamnionitis. Our data suggest that funisitis – as a marker for the fetal inflammatory response – may not manifest with clinically evident symptoms in the pregnant woman. Additionally, we found a trend for Hispanic women to have higher odds of funisitis compared with non-Hispanic women regardless of maternal age, parity, gestational age, rupture interval or presence of HCA. Although Hispanic infants have been shown to have lower risk of perinatal morbidity and mortality,Reference Hessol and Fuentes-Afflick34 a recent large retrospective cohort study in California found slightly increased risk of spastic or dyskinetic cerebral palsy in normal birth weight Hispanic infants compared with Caucasian infants not of Hispanic origin.Reference Wu, Xing and Fuentes-Afflick35 Interestingly, concentrations of umbilical plasma IL-6 (as a serum correlate of the fetal inflammatory response) was elevated in a predominately Hispanic population, suggesting a genetic component of inflammatory response.Reference Chaiworapongsa, Romero and Kim36 Funisitis and the fetal inflammatory response could be a mechanistically plausible explanation for this increased risk for cerebral palsy. Although beyond the scope of this study, future exploration into the effect of race/ethnicity, PPROM placental pathology and offspring neurological outcomes may be informative.
In their study of extremely low gestational age newborns (23–27 weeks of gestation), Hecht et al.Reference Hecht, Allred and Kliman16 noted that funisitis did not vary with gestational age, whereas chorionic plate vasculitis was inversely proportional to gestational age. Within our group of slightly older preterm newborns (25–33 weeks of gestation), we saw similar findings. Interestingly, in both studies, funisitis did not necessarily accompany chorionic plate vasculitis or HCA. These data would argue against the concept of funisitis as strictly a progression of inflammation from the chorionic plate after HCA exposure, but support the concept that funisitis may be (in some instances) a response to another unidentified insult, or a de novo fetal inflammatory response.Reference Redline24, Reference Chaiworapongsa, Romero and Kim36, Reference van Hoeven, Anyaegbunam and Hochster37 Although the mechanism remains unclear, genetic determinants of inflammation may help to explain these findings.Reference Chaiworapongsa, Romero and Kim36 Nonetheless, most pathologists agree that these findings most likely reflect sampling error,Reference Redline24, Reference Katzman and Metlay38, Reference Machin39 or likewise represent differences in pathological interpretation.Reference Salafia, Misra and Miles40
Similar to prior studies,Reference Hillier, Martius and Krohn17, Reference Sebire, Goldin and Regan41 we found that HCA was less prevalent with later gestational age at delivery after PPROM. Yet, rupture-to-delivery interval was not associated with increased prevalence of HCA or fetal inflammation, suggesting that there is no increased inflammation with longer rupture length. In a similar gestational age and birth weight cohort to ours, Ghidini et al.Reference Ghidini, Salafia and Minior22 showed a lack of relationship between HCA and latency duration in PPROM, even with prolonged (>7 days) rupture interval. Although our cohort is small, we suspect that inflammation, when apparent, is present at time of rupture, given that overall rupture-to-delivery interval did not change inflammatory patterns. Alternatively, these findings may indicate that those women who develop significant placental inflammation may go into labor sooner than those without inflammation.
Distinct clustering of inflammatory patterns v. placental perfusion abnormalities have been found with other mechanisms of preterm delivery such as preterm labor without premature rupture, and preterm preeclampsia, as well as in extremely low gestational age newborns.Reference Hecht, Allred and Kliman16, Reference Kramer, Chen and Roy26, Reference Arias, Rodriquez, Rayne and Kraus32, Reference Harteman, Nikkels, Kwee, Groenendaal and de Vries42 We found a similar prevalence of subchorionic thrombi and funisitis in our cohort. Similar to previous studies, it was uncommon to see inflammation with thrombosis. In fact, the presence of subchorionic thrombi appears to be inversely correlated with inflammation. Despite this inverse correlation, 11% of the PPROM group had both umbilical cord inflammation and subchorionic thrombi present, suggesting a potential relationship between insufficient maternal placental perfusion and the fetal inflammatory response.Reference Koeppen, Eckle and Eltzschig43, Reference Kovo, Schreiber and Ben-Haroush44 Our data suggest that inflammation alone is not the sole trigger of PPROM. Furthermore, indicators of placental perfusion abnormalities such as subchorionic thrombi may be important in the pathogenesis of neonatal outcomes, such as in infants with atypical timing and presentation of periventricular hemorrhagic infarction.Reference Harteman, Nikkels, Kwee, Groenendaal and de Vries42 Our findings highlight the importance of needed studies dissecting the mechanisms of PPROM to properly inform interventions to prevent PPROM or the adverse associated sequelae. Therapeutic targets have traditionally focused on inflammation, but anti-inflammatory agents alone may not be adequate.
This study is unique in exclusively focusing on PPROM, rather than grouping preterm placentas of varying etiologies together. This study also examined the effect of ethnicity in patterns of PPROM placental pathology. A limitation of the study is that placentas were not matched on gestational age from other preterm cohorts. Additionally, maternal systemic vascular and/or autoimmune disease is underrepresented in our population. These factors may indeed predispose to increased risk of PPROM because of global inflammation and/or hypercoagulability that cannot be fully assessed within our present cohort. Finally, our cohort of pregnant women reside and deliver at altitude (1600 m/5280 ft), which may contribute to our increased prevalence of placental perfusion abnormalities (subchorionic thrombi), although our pathological findings differ from very high-altitude series.Reference Khalid, Ali and Ali45 In fact, our thrombotic and inflammatory findings are similar to others cited in this manuscript, all at sea level, suggesting generalizability of our findings. These findings do suggest that PPROM is either caused by or can result in inflammation in the fetal compartment, insufficient maternal placental perfusion or both. Whether a multi-hit phenomenon of fetal inflammation combined with maternal malperfusion may portend poor neonatal outcomes is not known. Furthermore, maternal ethnicity may impart unknown genetic modifiers on placental inflammation, thrombosis, newborn disability and chronic disease. Future studies focused on this constellation of PPROM placental findings, genetic polymorphisms, neonatal outcomes and adult-onset diseases are needed.
Acknowledgment
The authors would like to thank Dr Anne Lynch for access to the Perinatal Research Database, Dr David Weitzenkamp for statistical support, Ms Lisa Litzenberger for photo preparation and Ms Whitney Hoover for aid in manuscript preparation.
Financial support
This research was funded by NIH BIRCWH K12 KD HDO57022 (J.A.W.), American Heart Association SouthWest Affiliates Clinical Research Grant 10CRP3670014 (J.A.W.), Colorado CCTSA Grant 5UL1RR025780 (J.A.W.) and CU Center for Women's Health Research Junior Researcher Grant (J.A.W.).
Conflicts of interest
None.
Ethical Standards
This research was conducted in accordance with the 2004 Declaration of Helsinki, with signed informed consent required for study participation (Colorado Multiple Institution Review Board study 09-1107).