Background and introduction
Percutaneous balloon dilation is the gold standard therapy for severe pulmonary valve stenosis and pulmonary atresia with intact ventricular septum in infants with well-developed right ventricular cavity and tricuspid valve annulus (z-score value above −2).Reference Gournay, Piéchaud, Delogu, Sidi and Kachaner 1 , Reference El Louali, Villacampa, Aldebert, Dragulescu and Fraisse 2 The procedure is usually effective in relieving pulmonary valve gradient, but many patients remain oxygen or prostaglandin dependent despite intervention.
We previously reported that alpha adrenoceptors are elevated in patients with pulmonary valve stenosis and in patients with hypoxia.Reference Galal, Dzimiri, Bakr, Moorji and Almotrefi 3 , Reference Dzimiri, Galal and Moorji 4 These receptors normalised as soon as the pulmonary valve stenosis was relieved.Reference Galal, Dzimiri, Bakr, Moorji and Almotrefi 3 In neonates with severe pulmonary valve stenosis who remained oxygen or prostaglandin dependent after effective balloon dilation, we hypothesised that the alpha adrenoceptor’s activity remained high due to associated hypoxia. We treated these neonates successfully, reducing ICU hospitalisation, with alpha 2 blockers, and in some cases associated with angiotensin-converting enzyme inhibitors.Reference Galal, Kalloghlian, Pittappilly and Dzimiri 5 – Reference Galal, Alzahrani and Elhoury 7
We believe that alpha adrenoceptor blockers and angiotensin-converting enzyme inhibitors improve forward flow as a result of vasodilation of the pulmonary and systemic beds. This seems to increase flow through the tricuspid valve, reducing right-to-left shunt across the patent foramen ovale or the atrial septal defect. This approach seems to reduce significantly the time required to improve right ventricular compliance in such patients.Reference Sommer, Rhodes and Parness 8
The present study aimed to evaluate the role of alpha blockers and/or angiotensin-converting enzyme inhibitors in newborns and infants submitted to balloon valvuloplasty for severe pulmonary stenosis. We were particularly interested in assessing the effects of these drugs on post-intervention oxygen requirements and the length of hospital stay.
Patients and methods
We studied, retrospectively, 28 patients below 6 months of age with pulmonary valve stenosis, who presented with right-sided heart failure, or desaturation, and were dependent on prostaglandin or oxygen. These patients underwent effective balloon valvuloplasty between January, 2009 and January, 2014, at a single tertiary-care institution.
Out of the 28 patients, 20 remained oxygen or prostaglandin dependent after effective balloon valvuloplasty and were treated with alpha blocker – phentolamine – or angiotensin-converting enzyme inhibitor – captopril. The study population consisted of these 20 patients.
Neonates were usually duct – that is, prostaglandin – dependent, with either a right-to-left or a bidirectional shunt across the patent foramen ovale or an atrial septal defect. Infants had systemic or suprasystemic right ventricular pressure and right-sided failure with low oxygen saturation. All patients had tricuspid valve diameter z-scores above −2 and tripartite right ventricles.
Patients older than 6 months with pneumothorax or chest infection were excluded from the study.
Demographic data, heart rate, respiratory rate, blood pressure, and oxygen saturation were recorded before and after balloon valvuloplasty and following treatment with either phentolamine or captopril. Duration of ventilator dependency, prostaglandin, phentolamine, captopril, and oxygen administrations, and the ICU and hospital length of stay were registered.
A transthoracic echocardiogram, including Doppler evaluation, was documented before and after treatment in every patient. Transthoracic echocardiograms were performed using a Phillips IE33 (United Medical Instruments Inc., UMI San Jose, California, United States of America), and the following data were evaluated: presence of a patent foramen ovale or atrial septal defect, direction of shunting, grade of tricuspid regurgitation, tricuspid and pulmonary valve diameters, peak gradient across the pulmonary valve, and the presence of a patent ductus arteriosus. After discharge, patients were followed-up clinically and underwent repeat echocardiographic studies. Cardiac catheterisation was performed as described previously (see referenceReference Rao, Galal, Patnana, Bock and Wilson 9 for details).
After establishing venous access, using a 4 or a 5 Fr sheath, a 4 Fr Judkins right coronary catheter was used to record haemodynamic data in the right side of the heart and access the pulmonary artery. A hand injection was performed in the right ventricle, just underneath the pulmonary valve. The pulmonary valve was crossed with a 0.014″ PTCA guide wire (Medtronic Inc., Minneapolis, United States of America) or a 0.018″ Terumo wire (Terumo Corporation, Tokyo, Japan). A balloon – when feasible, with a diameter selected to obtain balloon-to-annulus ratio lower than 1.2/1 – was advanced over the wire, positioned across the pulmonary valve, and inflated. On rare occasions, a right ventricular angiography after the procedure was performed. An echocardiogram was performed in the cardiac catheterisation laboratory to assess the residual gradient and degree of pulmonary regurgitation after the procedure.
Patients with oxygen saturations under 85% and oxygen- or prostaglandin-dependent patients were started on either phentolamine or captopril. Patients who were unstable were started on alpha blocker, phentolamine, and later switched to oral captopril.
Phentolamine was administered as a continuous infusion, at 5 μg/kg/min. When transcutaneous oxygen saturations were stable and above 90%, oral captopril was started at 0.15 mg/kg every 8 hours, and phentolamine was discontinued. This was followed by oxygen weaning, aiming to maintain oxygen saturations above 90%. Clinically stable patients were started on oral captopril treatment.
When patient saturation improved to above 90%, repeat transthoracic echocardiograms were performed. Both the groups of patients – that is, phentolamine and captopril treatment groups – were discharged on captopril at a dose of 0.15 mg/kg/day Q-8 hourly. Outpatient follow-up included clinical and echocardiographic evaluations at 1, 3, 6, and 12 months after discharge.
Statistical analysis
Data were analysed using SPSS version 16. Pre- and post-intervention gradients as well as pre- and post-captopril and phentolamine saturations, oxygen-dependency duration, and length of ICU and hospital stay were compared using the t-test, and p-values were calculated.
Results
A total of 20 patients were studied, with a female:male ratio of 3:1. Their mean age was 25.2±46.4 days (±SD; range 1–169 days), with a mean weight at cardiac catheterisation of 3.1±1.25 kg (range 1.9–6.7 kg). Among the study population, 18/20 (90%) patients were neonates, and two patients were 150 and 169 days of age, weighing 6.7 and 6.5 kg, respectively.
All 20 patients required oxygen before catheterisation. Among them, 18 (90%) patients were on prostaglandin infusion and 4/20 (20%) were ventilated. Mean pre-catheterisation oxygen saturation was −76.55±7.11% (range 50–84%). At cardiac catheterisation, mean pulmonary valve diameter was 6.86±1.2 mm, and mean pulmonary valve gradient was 87.2±15.4 mmHg. Mean balloon-to-pulmonary valve ratio was 1.2. Only one patient developed significant infundibular stenosis and was referred for surgical valvotomy after failed phentolamine treatment (see Table 1). There was no mortality.
Trans-pulmonary Doppler gradient and oxygen saturation before and after balloon valvuloplasty.

SD=standard deviation
There was a significant drop in mean trans-pulmonary valvar gradient after balloon valvuloplasty, while oxygen saturation did not differ
All patients required oxygen after pulmonary valvuloplasty. Only six of the 18 patients who were on prostaglandin before intervention needed to continue prostaglandin for a mean duration of 15.86±0.69 hours (range 10–32 hours). Out of the four ventilated newborns, three remained intubated after balloon dilation and were extubated at a mean time of 1.92±0.28 days (range 1–2 days) after starting phentolamine treatment.
After a mean time of 15±6.9 hours, nine (45%) patients were started on intravenous phentolamine and 11 (55%) on oral captopril. Of the nine patients on phentolamine treatment, one did not respond to therapy. This was an infant who was found to have a significant infundibular stenosis with a peak gradient of 56 mmHg and was started on beta blockers and later underwent elective surgical resection of the obstruction.
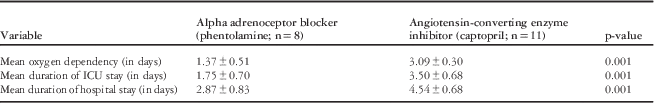
In the remaining eight patients, because of improvement in oxygen saturation, the alpha blocker was discontinued after a mean time of 1.37±0.51 days (range 1–2 days). In these eight patients, oral captopril was started before discontinuation of intravenous phentolamine. Mean duration of hospital stay for this group was 2.8±0.8 days (range 1.9–3.6 days; Table 2). The remaining 11 patients (55%) were started directly on oral captopril. Oxygen saturation for all 19 patients who benefited from this therapeutic approach improved significantly from a mean of 76.55±7.11 to 93±1.66%; p-value=0.001.
Oxygen dependency, ICU and hospital length of stay in patients treated with alpha adrenoceptor blocker or angiotensin-converting enzyme inhibitor.

Patients who received alpha adrenoceptor blocker could be weaned off oxygen earlier than the group treated with captopril. ICU and hospital stay were also shorter for the alpha adrenoceptor blocker group
Mean oxygen dependency after balloon dilation for patients on phentolamine treatment was significantly shorter than that for captopril patients (Table 2). None of the patients developed hypotension or renal failure, which have been reported occasionally with phentolamine and captopril treatment.
The mean ICU and hospital length of stay after balloon dilation for patients on phentolamine was significantly lower than that for those treated with captopril (Table 2).
Repeat echocardiogram 48 hours after phentolamine or captopril treatment showed patent foramen ovale/atrial septal defect shunting, predominantly left-to-right and mild tricuspid regurgitation, with a mean gradient between the right ventricle and the right atrium of 25 mmHg. The ductus arteriosus was closed in 16/18 patients, whereas a mild left-to-right shunt was seen in two patients. We elected to discharge all 19 patients on captopril to sustain the beneficial effect of this new treatment.
All 19 patients were followed-up clinically and echocardiographically. Mean duration of follow-up was 23±17.8 months (range 5–60 months). Mean weight at last follow-up was 11.56±5.5 kg (range 2–16.5 kg). Mean oxygen saturation was 98.9±2.3% (range 91–99%), and the mean Doppler gradient by echocardiography was 26.5±16 mmHg. The atrial septal defect or patent foramen ovale was closed in 11 patients, whereas a small left-to-right shunt persisted in 8 patients. The ductus arteriosus was closed in all patients at follow-up. Captopril treatment was discontinued after a mean of 70.2±25.73 days.
Discussion
Sommer et al suggested a multitude of factors leading to desaturation, despite successful balloon dilation of severe pulmonary valve stenosis. Poor compliance of the hypertrophied right ventricle and tricuspid regurgitation can contribute to right-heart failure and facilitate right-to-left shunt across the patent foramen ovale. Therefore, many patients will remain hypoxic.Reference Sommer, Rhodes and Parness 8 They also pointed that with reduced ventricular afterload right ventricular hypertrophy would resolve, leading to improvement in compliance and increase in right ventricular inflow.Reference Sommer, Rhodes and Parness 8
Patients with valvar pulmonary stenosis have increased density of alpha 2 adrenoceptors on circulating cells that can normalise within 10 minutes with balloon valvuloplasty.Reference Galal, Dzimiri, Bakr, Moorji and Almotrefi 3 We speculated that alpha 2 adrenoceptors do not normalise in newborns with severe pulmonary valve stenosis, presenting desaturation despite intervention. Assuming alpha 2 adrenoceptors on circulating cells represent the distribution of these receptors in the vascular system, we hypothesised that blocking alpha 2 adrenoceptors and/or inhibiting angiotensin-converting enzyme might aid in the treatment of severe pulmonary valve stenosis and pulmonary atresia with intact ventricular septum.Reference Galal, Dzimiri, Bakr, Moorji and Almotrefi 3 , Reference Galal, Arfi, Ata, Hussain and Kouatli 6 , Reference Galal, Alzahrani and Elhoury 7
How do alpha blocker and angiotensin-converting enzyme inhibitor work?
Blocking the aforementioned receptors with phentolamine leads to vasodilation. We also believe that alpha-blocker improves right ventricular compliance. This effect, along with vasodilation, would explain the improvement of oxygen saturation for newborns, within few hours, in response to phentolamine.
Angiotensin-converting enzyme inhibitor blocks conversion of angiotensin I to angiotensin II. This lowers arteriolar resistance, increases venous capacity, and can lower the resistance in the pulmonary vasculature. In the rat model, angiotensin-converting enzyme inhibitor decreases pulmonary arterial pressure through preservation of endothelial nitric oxide synthase.Reference Ng and Vane 10 , Reference Laursen and Harrison 11 It has been shown that angiotensin-converting enzyme inhibitor increases bradykinin, an agonist of nitric oxide synthase, a well-known vasodilator of the pulmonary vascularity.Reference Ignjatovic, Stanisavljevic, Brovkovych, Skidgel and Erdos 12 – Reference Jiang, Hess, Matter, Mandinov, Kaufmann and Vasalli 15
Vasodilation facilitates forward flow into the lungs and increases cardiac output, improving oxygenation. Nitric oxide modulates cardiac function by abbreviating systolic contraction and prolonging diastolic relaxation. Nitric oxide also exerts a decrease in left ventricular end-diastolic pressure without affecting left ventricular systolic pump function.Reference Laursen and Harrison 11 Assuming that this mechanism is effective in the right ventricle, it would further facilitate right ventricular inflow, leading to improved oxygenation.
Based on this background, we introduced phentolamine in two neonates with severe pulmonary valve stenosis who failed to respond to balloon dilation. Phentolamine improved their clinical status dramatically.Reference Galal, Kalloghlian, Pittappilly and Dzimiri 5 Alpha 2 blocker also showed effectiveness in a patient who remained prostaglandin and oxygen dependent for 2 weeks after successful pulmonary valvuloplasty.Reference Galal, Arfi, Ata, Hussain and Kouatli 6 Before discontinuing phentolamine, angiotensin-converting enzyme inhibitor was administered orally, improving right ventricular compliance. Encouraged by this experience,Reference Galal, Arfi, Ata, Hussain and Kouatli 6 a patient with oxygen dependency, without major clinical distress, was administered an oral angiotensin-converting enzyme inhibitor. Within 12 hours, the patient was weaned off oxygen completely.Reference Galal, Alzahrani and Elhoury 7
A 2012 paper regarding management of pulmonary atresia with intact ventricular septum suggested that a Blalock Taussig shunt or duct stenting should be considered, if prostaglandin infusion could not be discontinued in ∼1–2 weeks.Reference Burkholder and Balaguru 16 It may require as long as 4–6 weeks for oxygen saturation to improve to satisfactory levels.Reference Burkholder and Balaguru 16
Our study showed that in spite of effective balloon dilation, 20/28 infants (71%) with severe pulmonary valve stenosis remained oxygen or prostaglandin E dependent.
In contrast to the proposed management by other authors,Reference Burkholder and Balaguru 16 only one of our patients did not respond positively to our new therapeutic management and had severe infundibular stenosis. The remaining 19 patients either responded within hours to the administration of phentolamine or within days to captopril, proving the efficacy of this therapeutic strategy. Therefore, our patients had a very short ICU stay and prostaglandin E and oxygen dependency. Their hospital stay was shorter and oxygen supply at home was not required. In addition, our new regimen of adding either phentolamine or angiotensin-converting enzyme inhibitor proved to be safe.
Weakness of the study
The main limitation of this study is its retrospective design. Although this type of treatment started in 1996, its limitations still need to be defined and understood further. We have already identified significant infundibular stenosis as a contraindication for this approach.
Conclusion
This study showed that angiotensin-converting enzyme inhibitor – captopril – and alpha 2 blocker – phentolamine – have important therapeutic roles in patients who remain oxygen and prostaglandin dependent after balloon dilation for severe pulmonary valve stenosis and pulmonary atresia with intact ventricular septum. These medications may reduce the cost and length of hospital stay of such patients. No patient required oxygen supply at home, reducing stress on families. The use of this approach may shorten ventilator, prostaglandin E, and oxygen dependency, and prevent further interventions. Unfortunately, conducting a controlled study may prove very difficult, as this is a very rare disease.
Acknowledgements
The authors thank Mr S.K. Galal and Mr K.R. Galal for the extensive English corrections. The authors thank Prof. Omar Kasule for helping in statistical analysis.
Financial Support
The research received no specific grant from any funding agency, commercial, or not-for-profit sector.
Conflicts of Interest
None.
Ethical Standards
The authors hereby declare that the research documented in the submitted manuscript has been carried out with the approval of the Hospital Institutional Review Board.