Introduction
Income inequality is associated with increased suicide rates in men over the age of 55 years (Cutright and Fernquist, Reference Cutright and Fernquist2000), in those up to the age 75 years (Fukuda et al., Reference Fukuda, Nakamura and Takano2005), in those over the age of 65 years (Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a), and in the general population (Kowalski et al., Reference Kowalski, Faupel and Starr1987; Lorant et al., Reference Lorant, Kunst, Huisman, Costa and Mackenbach2005). Gross national domestic product (GDP) is positively correlated with suicide rates in the general population (Zhang, Reference Zhang1998) and in men aged 75+ years (Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). However, in a study of 47 medium and high income countries, elderly suicide rates were negatively correlated with GDP (Kiemo, Reference Kiemo2004). A decline in elderly suicide rates over time in England and Wales was associated with an increase in GDP (Gunnell et al., Reference Gunnell, Middleston, Whitley, Dorling and Frankel2003). These observations collectively suggest that socioeconomic status may differentially influence suicide rates in different age and sex groups in different countries. Life expectancy was positively correlated with suicide rates in the elderly (Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a) and the general population (Zhang, Reference Zhang1998). Life expectancy and GDP have a highly significant strong inter-correlation (Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). However, due to difficulties with multiple collineality, it has not been possible to determine the independent effects of these two variables on elderly suicide rates using multiple regression techniques (Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). Moreover, previous studies have developed sequential models whereby increased GDP leads to increased life expectancy and increased life expectancy, in turn, leads to a greater number of people reaching old age, where the risk of suicide is the highest (Shah, Reference Shah2007a; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). However, other factors, including income inequality and education, may also influence life expectancy independent of GDP (Shah, Reference Shah2007a; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a), and it is also possible that both GDP and life expectancy may have an independent and cumulative effect on elderly suicide rates.
Elderly suicide victims have poor educational attainment (Rubenowitz et al., Reference Rubenowitz, Waern, Wilhelmson and Allebeck2001). However, male African American suicide victims aged 55+ years had higher levels of educational attainment (Fernquist, Reference Fernquist2001). General population suicide rates in the U.S.A., including those among African Americans, have been both positively (Kowalski et al., Reference Kowalski, Faupel and Starr1987; Stack, Reference Stack1998) and negatively (Willis et al., Reference Willis, Coombs, Drentea and Cockerham2003; Abel and Kruger, Reference Abel and Kruger2005) correlated with educational attainment. Also, general population suicide rates in Japan (Otsu et al., Reference Otsu, Araki, Sakai, Yokoyama and Voorhees2004) and in men in ten European countries (Lorant et al., Reference Lorant, Kunst, Huisman, Costa and Mackenbach2005) were negatively correlated with educational attainment. These findings collectively suggest that educational attainment may differentially influence suicide rates in different age and ethnic groups in different countries.
The Human Development Index (HDI), developed by the United Nations, is a composite index measuring the average achievements in a given country on three basic dimensions of human development: a long and healthy life, as measured by life expectancy; educational attainment, as measured by the adult literacy rate and the combined gross enrolment ratio for primary, secondary and tertiary schools; and, a decent standard of living, as measured by GDP. A recent cross-national study examining the relationship between the composite and cumulative effect of these three variables, measured by the HDI, and suicide rates in both sexes, in the age-bands 65–74 years and 75+ age-band, demonstrated a curvilinear (inverted U-shaped curve) relationship between elderly male suicide rates and the HDI fitting the quadratic equation y = a + bx − cx2 (where y is the elderly male suicide rate, x is the HDI and a, b and c are constants) (Shah, Reference Shah2009a). A similar relationship was observed in females, but only approached statistical significance. These findings, including the composite effect of life expectancy, education and socioeconomic status, were explained by the development of a hypothetical sequential four-stage model adapted from similar models that have been proposed to explain the relationship between socioeconomic status and cross-national variations in the prevalence of dementia (Suh and Shah, Reference Suh and Shah2001), other mental disorders in old age (Shah, Reference Shah2007b) and elderly suicides (Shah, Reference Shah2010).
Low elderly suicide rate – low human development society stage
Low elderly suicide rates are associated with poor socioeconomic status and greater income inequality in cross-national studies (Simpson and Conklin, Reference Simpson and Conklin1989; Zhang, Reference Zhang1998; Vijaykumar et al., Reference Vijayakumar, Nagaraj, Pirkis and Whiteford2005; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a) and within-country studies (Kowlaski et al., Reference Kowalski, Faupel and Starr1987). Societies with low socioeconomic status and greater income inequality have poorly developed healthcare services (Shah, Reference Shah2007b; Reference Shah2009b; Jacob et al., Reference Jacob, Sharan, Mirza, Garrido-Cumbrera, Seedat, Mari and Sreen2007; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah and Bhat, Reference Shah and Bhat2008a; Reference Shah and Bhat2008b). Poorly developed healthcare services will increase child mortality rates (Suh and Shah, Reference Suh and Shah2001; Shah, Reference Shah2007b; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a), which leads to reduced life expectancy (Zhang, Reference Zhang1998; Shah, Reference Shah2007b; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). Given that suicide rates generally increase with age (Shah and De, Reference Shah and De1998; Shah, Reference Shah2007c), reduced life expectancy will result in fewer people reaching the age of increased risk for suicide in countries with low socioeconomic status, and result in a reduced number of elderly suicides in such countries (Zhang, Reference Zhang1998; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). Moreover, in societies with low socioeconomic status, the elderly may be at reduced risk of suicide because they may have greater tolerance of additional hardship in old age due to life-long exposure to adversity (Seiden, Reference Seiden1981; McIntosh, Reference McIntosh1984; Lindesay, Reference Lindesay1991; Shah and Bhat, Reference Shah and Bhat2009).
In addition, poor socioeconomic status may be associated with poor educational attainment. Low suicide rates were positively correlated with poor educational attainment in individual-level studies (Fernquist, Reference Fernquist2001; Kung et al., Reference Kung, Liu and Juon2004) and aggregate-level studies (Kowalski et al., Reference Kowalski, Faupel and Starr1987; Gillis, Reference Gillis1994; Lester Reference Lester1990–1991; Stack, Reference Stack1998), but they were from socioeconomically well-developed countries and of younger age groups.
High elderly suicide rate – low human development society stage
The improvement in the socioeconomic status of countries will improve the development of healthcare services (Zhang, Reference Zhang1998; Shah, Reference Shah2007b; Reference Shah2009b; Jacob et al., Reference Jacob, Sharan, Mirza, Garrido-Cumbrera, Seedat, Mari and Sreen2007; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah and Bhat, Reference Shah and Bhat2008a; Reference Shah and Bhat2008b) leading to reduced child mortality rates (Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah, Reference Shah2007b) and increased life expectancy (Zhang, Reference Zhang1998; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). This, in turn, will result in a greater number of subjects reaching the age of increased risk of suicide and an increase in elderly suicide rates. This is supported by positive correlations between life expectancy and suicide rates in the elderly (Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a) and general population (Zhang, Reference Zhang1998). This will lead to a gradual transition from low elderly suicide rate–low human development society stage to a high elderly suicide rate–low human development society stage.
High elderly suicide rate – high human development society stage
As societies develop, a change from lower to higher human development status will occur. Further improvements in the development of healthcare services as observed by positive correlations between GDP and markers of development of healthcare, and negative correlations between the Gini coefficient and these variables (Shah, Reference Shah2007b, Reference Shah2009b; Jacob et al., Reference Jacob, Sharan, Mirza, Garrido-Cumbrera, Seedat, Mari and Sreen2007; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah and Bhat, Reference Shah and Bhat2008a; Reference Shah and Bhat2008b). Such improvement will further reduce child mortality rates (Zhang, Reference Zhang1998; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah, Reference Shah2007b) and further increase the life expectancy (Zhang, Reference Zhang1998; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah, Reference Shah2007b). This, in turn, will increase the number of subjects reaching the age of increased risk of suicide (Zhang, Reference Zhang1998; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a). Moreover, the protective effects of life-long adversity on elderly suicide rates (Seiden, Reference Seiden1981; Lindesay, Reference Lindesay1991; McIntosh, Reference McIntosh1984) are likely to be less prevalent in countries with higher socioeconomic status. The composite effect of these changes will increase the number of individuals at increased risk of suicide in old age in socioeconomically more developed countries. This will lead to a gradual transition from the high elderly suicide rate–low human development society stage to a high elderly suicide rate–high human development society stage.
Low elderly suicide rate – high human development society stage
Theoretically, in socioeconomically well-developed countries, due to further reduction in child mortality rates and increase in life expectancy, a greater number of people would reach the age of increased of suicide, and consequently lead to higher elderly suicide rates. However, in socioeconomically well developed countries, including Italy, Netherlands, Norway, U.K. and U.S.A., elderly suicide rates are comparatively low (Shah et al., Reference Shah, Bhat, MacKenzie and Koen2007) and have declined over time (Shah et al., Reference Shah, Bhat, MacKenzie and Koen2008b). In socioeconomically very well-developed societies, elderly suicide rates may progressively decline over many years due to improved efforts to control the risk factors for elderly suicides, enhance protective factors for elderly suicides, advances in medical care, prompt resuscitation of those who attempt suicide, better provision of healthcare (including mental health) services and public health initiatives to reduce suicide rates (Gunnell et al., Reference Gunnell, Middleston, Whitley, Dorling and Frankel2003; Kua et al., Reference Kua, Ko and Ng2003; Lodhi and Shah, Reference Lodhi and Shah2004; Reference Lodhi and Shah2005; Yip et al., Reference Yip, Liu, Hu and Song2005; Shah and Coupe, Reference Shah and Coupe2009; Shah, Reference Shah2009c). Ultimately, this will lead to a gradual transition from a high elderly suicide rate–high human development society stage to a low elderly suicide rate–high human development society stage.
Also higher socioeconomic status is likely to be associated with higher educational attainment. There is evidence that low suicide rates are associated with higher educational attainment in individual-level (Fernquist, Reference Fernquist2001) and aggregate-level studies (Willis et al., Reference Willis, Coombs, Drentea and Cockerham2003; Abel and Kruger, Reference Abel and Kruger2005; Otsu et al., 2005; Lorant et al., Reference Lorant, Kunst, Huisman, Costa and Mackenbach2005) from socioeconomically well-developed countries, although they are mainly of younger age groups.
The earlier study (Shah, Reference Shah2009a) demonstrating a curvilinear relationship between elderly suicide rates and the HDI used only one-year cross-sectional data on elderly suicide rates, and suicide rates can randomly fluctuate year on year (Shah and Coupe, Reference Shah and Coupe2009). Therefore, in order to replicate the findings of this earlier study, the relationship between elderly suicide rates and the HDI was examined: (i) by using a one-year average of five years data on elderly suicide rates; and (ii) using the latest available (and, therefore, a more recent) data set on elderly suicide rates.
Methods
Data on elderly suicide rates for males and females in the age-bands 65–74 years and 75+ years were ascertained from the World Health Organization (WHO) website (http://www.who.int/whosis/database/mort/table1.cfm). For a small number of countries only the raw figures for the number of suicides were available from the WHO website. Suicide rates for these countries were calculated by dividing the number of reported suicides by the population size in the relevant age-band and sex group available on the same website. Data were ascertained for the latest five consecutive years. The one-year average suicide rate was calculated by dividing the sum of suicide rates for the latest five consecutive years by five. The median (range) for the latest year for the suicide rate data was 2005 (1983–2007).
The HDI, developed by the United Nations, is a composite index measuring the average achievements in a given country on three basic dimensions of human development: a long and healthy life, as measured by life expectancy; educational attainment, as measured by the adult literacy rate and the combined gross enrolment ratio for primary, secondary and tertiary schools; and, a decent standard of living, as measured by the GDP. The United Nations Development Programme website provided data on the HDI for the year 2004 (http://hdr.undp.org/en/media/HDI_2008_EN_Tables.pdf). The HDI is scored on a scale of 0 to 1 (given up to three decimal points), with higher scores reflecting higher degree of human development on measures of life expectancy, educational attainment and socioeconomic status.
The relationship between elderly suicide rates, in both sexes and both elderly age-bands, and the HDI was examined with curve estimation regression model to test the previously observed inverted U-shaped curvilinear relationship fitting the quadratic equation y = a + bx − cx2 (where y is the elderly suicide rate, x is the HDI and a, b and c are constants) (Shah, 2009).
Results
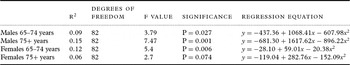
Data on elderly suicide rates and the HDI were available for 85 countries. Table 1 illustrates the characteristics of the curve regression models. The relationship between suicide rates in males aged 65–74 years, males aged 75+ years and females aged 65–74 years and the HDI was curvilinear (inverted U-shaped curve) and fitted the quadratic equation y = a + bx − cx2 ; the significance level was at least at the 0.05 level. A similar curvilinear relationship was observed in females aged 75+ years, but the significance level only approached the 0.05 level.
Curve estimation regression models for the relationship between elderly suicide rates and the HDI

y = Suicide rates.
x = HDI.
a, b and c are constants.
Discussion
Some methodological issues need consideration. Cross-national data on suicide rates should be viewed cautiously because: data are not available from all countries (Moscicki, Reference Moscicki1995; Wasserman et al., Reference Wasserman, Cheng and Jiang2005); the validity of this data is unclear (Diekstra, Reference Diekstra1989; Wasserman et al., Reference Wasserman, Cheng and Jiang2005); the legal criteria for the proof of suicide vary between countries (Shah and Ganesvaran, Reference Shah, Ganesvaran, Chiu and Ames1994; Wasserman et al., Reference Wasserman, Cheng and Jiang2005); some countries have poor death registration facilities (Shah and Ganesvaran, Reference Shah, Ganesvaran, Chiu and Ames1994); and, cultural and religious factors and stigma attached to suicide may lead to under-reporting (Wasserman et al., Reference Wasserman, Cheng and Jiang2005; Abrahams et al., Reference Abrahams, Abrahams and Jacob2005). Data on life expectancy, health-related measures, educational attainment and socioeconomic status should also be viewed cautiously because: the validity of these data is unclear; and, some countries have poor infrastructure to collect data on health-related measures and finances. There are no specific data on the reliability of the HDI, although it has previously been examined as a potential protective and risk factor for elderly suicides (Shah, Reference Shah2009a). However, the best and the latest available data set were obtained from the WHO and the UN and a one-year average of five years’ data on suicide rates was used.
The curvilinear (inverted U-shaped curve) relationship between elderly suicide rates and the HDI, using one-year average of five years’ data on suicide rates and the latest available data set (different from the earlier study), confirmed the findings of the earlier study using only one-year cross-sectional data on suicide rates (Shah, Reference Shah2009a). This suggests that this relationship is robust and accurate. These findings, including the composite effect of life expectancy, education and socioeconomic status, may be explained by the four sequential stage model described in the Introduction, which was developed following the earlier study with similar findings (Shah, Reference Shah2009a). This developmental model has the following four sequential stages: (i) low elderly suicide rate–low human development society; (ii) high elderly suicide rate–low human development society; (iii) high elderly suicide rate-high human development society; and (iv) low elderly suicide rate–high human development society. This model relies on several previous observations: (i) low socioeconomic countries have poorly developed healthcare services (Shah, Reference Shah2007b, Reference Shah2009b; Jacob et al., Reference Jacob, Sharan, Mirza, Garrido-Cumbrera, Seedat, Mari and Sreen2007; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah and Bhat, Reference Shah and Bhat2008a; Reference Shah and Bhat2008b); (ii) poorly developed healthcare services lead to increased child mortality rates (Suh and Shah, Reference Suh and Shah2001; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah, Reference Shah2007b); (iii) increased child mortality will lead to reduced life expectancy (Zhang, Reference Zhang1998; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a; Shah, Reference Shah2007b); reduced life expectancy will result in fewer people reaching the age of increased risk of suicide (Zhang, Reference Zhang1998; Shah et al., Reference Shah, Bhatt, MacKenzie and Koen2008a); and (v) elderly suicide rates may progressively decline over many years due to improved efforts to control the risk factors for elderly suicides, enhance protective factors for elderly suicides, advances in medical care, prompt resuscitation of those who attempt suicide, better provision of healthcare (including mental health) services and public health initiatives to reduce suicide rates in socioeconomically very well-developed countries (Gunnell et al., Reference Gunnell, Middleston, Whitley, Dorling and Frankel2003; Kua et al., Reference Kua, Ko and Ng2003; Lodhi and Shah, Reference Lodhi and Shah2004; Reference Lodhi and Shah2005; Yip et al., Reference Yip, Liu, Hu and Song2005; Shah and Coupe, Reference Shah and Coupe2009; Shah, Reference Shah2009c). The findings of this study and the previously proposed four-stage model are both consistent with these observations.
Caution should be exercised in the application of this model because of the cross-sectional and ecological study design whereby the findings are subject to ecological fallacy and require rigorous testing in within-country longitudinal studies over time. It is likely that different countries will be at different stages of development, and each country would progress through each of these four developmental stages over time. This model can be formally tested by following up countries that are currently at the low elderly suicide rates – low human development society stage over time to observe if they progress through the four developmental stages of the proposed model. This model is complimentary to, and does not preclude, other proximal and distal etiological risk factors for elderly suicides including economic growth, health and welfare services for the elderly, psychosocial environment and religion – although some of these factors are discussed under subheadings of the four stages of the model above.
Conflict of interest
None.