Introduction
In the surgical management of chronic laryngotracheal stenosis, cases with subglottic stenosis pose special challenges. The lower subglottis houses the cricoid ring – the only complete ring in the airway – and is believed to be especially prone to stenosis. The upper subglottis houses the vocal fold muscles, the scarring of which has implications for vocal fold mobility and additional glottic stenosis.Reference Pradhan, Sikka and Thakar1
Most large series pertain to paediatric or congenital stenosis. Reports on acquired subglottic stenosis are fewer and are based on small numbers of patients.Reference Pradhan, Sikka and Thakar1–Reference Kelkar, Shah, Mahandru and Kasbekar5 A wide variety of surgical techniques has been advocated. Techniques used include endoscopic techniques, such as dilatation, laser vaporisation of the scarred tissues and luminal stenting, and external techniques, such as laryngofissure, stenting, cricotracheal resection with end-to-end anastomosis, and laryngotracheal reconstruction with an anterior and/or posterior cricoid split procedure and costal cartilage grafts.Reference Pradhan, Sikka and Thakar1–Reference George, Jaquet, Ikonomidis and Monnier6 Although a large variety of surgical techniques have been described, the specific indications and effectiveness of each procedure are unclear, especially those for acquired stenosis and for stenosis extending beyond the subglottis.Reference Jović, Dragičević, Komazec, Mitrović, Janjević and Gašić4
Distinguishing between isolated ‘mucosal involvement or soft stenosis,’ and ‘cartilaginous or framework involvement, or hard stenosis’, is considered critical to the choice between an endoluminal and external surgical procedure. However, such differentiation is currently imprecise,Reference Roediger, Orloff and Courey2 and is based on subjective and multifactorial assessments that include patient history (aetiology, time since injury), endoscopic evaluation (grade of stenosis, distensibility of the stenosis) and radiology.
This report details a single-institution, multi-surgeon experience of the surgical treatment of subglottic stenosis in a cohort of 30 consecutive cases treated over a 6-year period. The differences in injury and stenosis patterns between major aetiological groups are presented. The results of a spectrum of recommended external and endoscopic surgical procedures are presented and compared. Based on these results, recommendations are made with regard to the selection of appropriate surgical procedures for different clinical situations.
Materials and methods
The study included 30 patients treated for acquired subglottic stenosis at a tertiary care academic institution from 2004 to 2009. Institutional ethical clearance was obtained. Seventeen patients were treated in the period from January 2004 to December 2006, and data pertaining to them were procured by an initial retrospective evaluation of hospital in-patient case records (in-patient physician investigation, radiology and surgical notes) and subsequent follow-up visits. Thirteen patients were treated in the period from January 2007 to December 2009, and data pertaining to them were recorded prospectively. In that same six-year period, four other patients with subglottic stenosis were advised against surgical correction in view of co-morbidities (i.e. severe bronchial asthma, chronic obstructive pulmonary disease and significant post-corrosive hypopharyngeal stenosis), as surgery may have increased the risk of aspiration and pulmonary complications.
Aetiological information, details of previous interventions prior to referral, and any co-morbidities were noted. Stenosis was assessed by flexible laryngoscopy, radiology (computed tomography scan and soft tissue neck X-ray) and rigid endoscopy under anaesthesia. The specific parameters assessed included: grade of stenosis (using the Myer–Cotton classification),Reference Myer, O'Connor and Cotton7 length of stenosis, extension to the glottis or the trachea, and vocal fold mobility. Examination of whether stenosis is primarily mucosal or includes involvement of the cartilaginous framework remains imprecise. Such assessments were based on a multifactorial evaluation of radiology and endoscopy findings (e.g. consistency of stenosis – soft or hard), and patient history (aetiology and time lapse since injury).
Cases were classified into three subtypes: isolated subglottic stenosis, combined subglottic and tracheal stenosis, and combined subglottic and glottic stenosis.
Surgical interventions ranged between endoscopic and external, as indicated by the length, grade and consistency of stenosis (soft or hard). Patients were treated under the clinical care of one of three separate clinical teams led by three individual, experienced consultant surgeons (AT, RK and SCS). The choice of surgical procedures was affected by individual assessments and preferences.
Endoscopic interventions were generally restricted to cases with short-segment (1–2 cm) stenosis, which were judged to be primarily mucosal with no or minimal loss of cartilaginous support. These interventions included balloon dilatation, carbon dioxide laser excision, adjuvant mitomycin C applications and Montgomery tracheal T-tube stenting. External interventions included laryngotracheal reconstruction (anterior cricoid split, or combined anterior and posterior cricoid split with costal cartilage augmentation), cricotracheal resection and anastomosis, laryngofissure with keel insertion, and an anterior cricoid split or anterior cricotracheal split with stenting (Shiann Yann Lee procedureReference Kelkar, Shah, Mahandru and Kasbekar5). In patients who underwent cricotracheal resection with anastomosis, the resection was extended to include the cricoid ring superiorly and the tracheostoma inferiorly, with the anastomosis performed between the cricoid lamina or thyroid lamina superiorly and the tracheal ring inferiorly. The length of resected trachea varied from 3 to 6.5 cm.
A temporary Silastic® tube stent (Montgomery tracheal T-tube) was used in the post-operative period for the majority of open surgical procedures (32 out of 34 procedures). Tracheal T-tube stenting was undertaken so as to: provide for a stable airway in the immediate post-operative period, minimise demands on the intensive care unit and provide support to the surgical repair. Tracheal T-tube stents were kept for a period of 6–12 weeks in patients who underwent cricotracheal resection and anastomosis, and for a period of 12–40 weeks (mean of 20 weeks) in those who underwent cricotracheal reconstruction with a cricoid split procedure and costal cartilage wedge grafts.
In accordance with the literature indicating that gastroesophageal reflux disease may compromise surgical success,Reference Little, Koufman, Kohut and Marshall8 all patients received peri-operative proton pump inhibitors for four weeks.
Outcome was assessed in terms of the establishment of a tracheotomy-free airway.
Results
Case descriptions
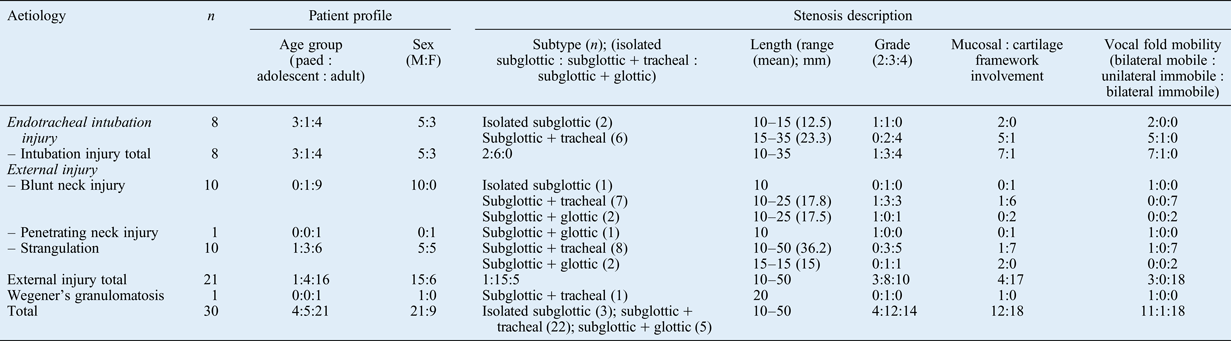
The aetiological profile is listed in Table I, as are the descriptions of the stenoses for each aetiological group. Two major aetiological groups were identified: endotracheal intubation injury and external neck injury (i.e. blunt neck injury, penetrating injury and strangulation). All cases of neck strangulation were accidental.
Aetiological profile and stenosis description

Paed = paediatric; M = male; F = female
The case group included 4 paediatric patients (less than 12 years old), 5 adolescents (12–18 years old) and 21 adults (over 18 years old). Patient age ranged from 2.5 to 35 years (mean of 21 years). There were 21 males and 9 females. The blunt neck injury group consisted exclusively of males (n = 10), with the other aetiological groups having a near equal sex distribution.
All patients had a diagnosis of stenosis established, and all had been tracheotomised at various other centres prior to referral to our tertiary care service. The time from tracheotomy to referral ranged from 1 to 18 months (mean of 4 months). Six patients had undergone unsuccessful surgical interventions prior to referral.
The majority of patients (26 out of 30) had grade III–IV stenosis. The length of the stenosis varied from 10 to 50 mm.
Acquired stenosis limited to the subglottis was unusual (affecting 3 out of 30 patients), and most patients had contiguous involvement of the trachea or glottis. Isolated subglottic stenosis was more frequent in the paediatric population (2 out of 4 paediatric patients had isolated subglottic stenosis compared with 1 out of 26 adults; p < 0.05, Fisher's exact test).
Combined subglottic and tracheal stenosis was the most common clinical situation in all aetiological groups. Combined subglottic and glottic stenosis was noted in the strangulation and blunt neck injury groups, but not in the post-intubation injury group.
Vocal fold fixation was unusual in the endotracheal intubation injury group (1 out of 8 patients (12.5 per cent) suffered unilateral fixation), but was frequent and bilateral in the external injury group (18 out of 21 patients (86 per cent) suffered bilateral fixation) (p < 0.01, Fisher's exact test).
On initial evaluation, the majority of patients in the external injury group (17 out of 21) were judged to have cartilaginous framework injury rather than isolated mucosal injury. In contrast, the signs of cartilaginous framework involvement were rare in the endotracheal intubation injury group (one out of eight patients) (p < 0.01, Fisher's exact test).
Surgical treatment
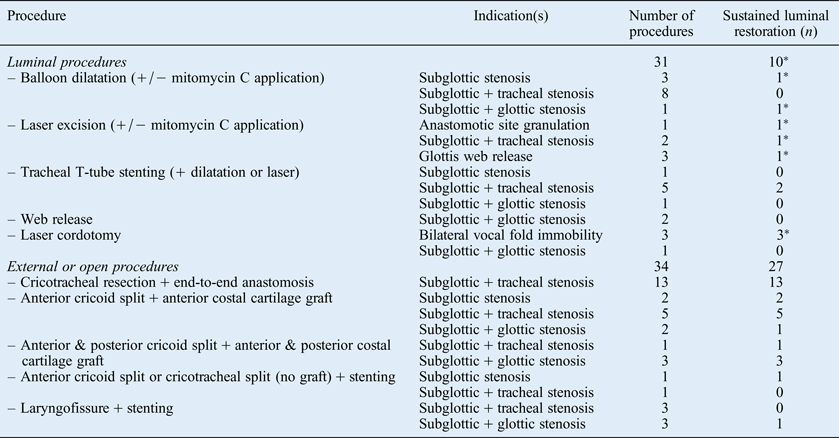
Surgical intervention varied depending upon the site of involvement, the grade and length of stenosis, the time since injury, and indications that stenosis was consequent to mucosal oedema or involved the cartilaginous framework. A total of 65 procedures were undertaken in 30 patients, consisting of 31 intraluminal procedures and 34 external procedures. Luminal restoration was achieved in 29 out of 30 patients (96.6 per cent). The various surgical procedures undertaken and their efficacy in terms of luminal restoration are shown in Table II.
Surgical procedures, indications and outcome
*In 8 of the 10 successful endoscopic procedures, the endoscopic procedure was undertaken to supplement a previous external or open procedure.
Not accounting for the surgical interventions undertaken prior to referral to our facility, luminal restoration was attained with 1 single procedure in 11 cases, 2 procedures in 6 cases, 3 procedures in 6 cases, and more than 3 procedures in 5 cases. Three patients required additional surgery (laser posterior cordotomy, also known as Kashima's cordotomy) for vocal fold immobility prior to decannulation.
Initial endoscopic treatments were attempted in 9 out of 30 patients. Of 12 patients judged to have isolated mucosal involvement, 6 had initial endoscopic treatment (stenosis length 1–2 cm, grade II–IV), with successful decannulation achieved in 2 out of the 6 patients. This included patients from the post-intubation injury group, wherein seven of eight patients were initially considered to have no significant cartilaginous involvement, but only one such patient was successfully treated by endoscopic procedures. In the two patients in whom endoscopic treatments were successful, stenosis was consequent to either recent endotracheal intubation (an adult, with a time from tracheotomy to treatment of four weeks) or Wegener's granulomatosis. In the four patients in whom endoscopic treatments failed, stenosis was consequent to intubation injury (n = 2) and strangulation injury (n = 2). No significant differences in the grade or length of stenosis were noted among the successful and unsuccessful cases. Paediatric patients had less success than adults (zero out of three children vs two out of three adults – a non-significant finding).
Of the 18 patients found (in the initial assessment) to have cartilaginous involvement, 3 with short-segment stenosis (1 cm) underwent attempts at endoscopic treatment, but all 3 attempts were unsuccessful.
Among the external procedure cases, greater success was achieved with cricotracheal resection and anastomosis (13 out of 13), and with laryngotracheal reconstruction (anterior with or without posterior cricoid split, with costal cartilage grafting (12 out of 13)), while other procedures proved less successful (Table II).
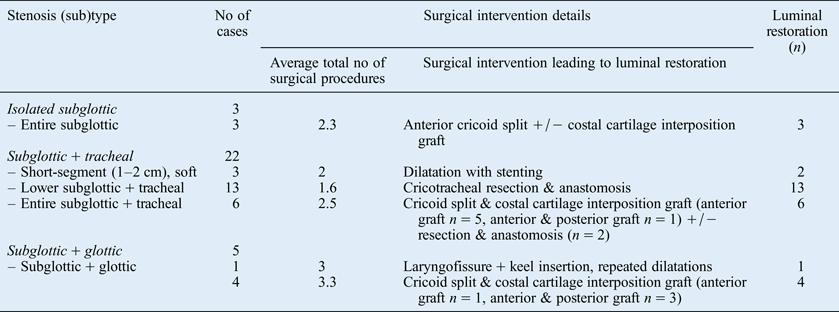
The details of the surgical treatment according to different sites are detailed below and are summarised in Table III.
Treatment summary for stenosis subtypes
No = number
Isolated subglottic stenosis
In all three affected patients, the stenosis involved the entire length of the subglottis (grades II–III). Luminal restoration was achieved in all patients using an anterior cricoid split procedure with or without costal cartilage grafting and stenting. One of these patients had been initially managed with repeated dilatations which had proved unsuccessful. An additional subsequent endoscopic dilatation was required in one patient.
Combined subglottic and tracheal stenosis
Of the 22 patients affected, 3 had short-segment, soft stenosis, 2 of whom developed an adequate lumen with endoscopic dilatation or laser excision along with long-term stenting. In other clinical situations, the endoscopic procedures proved disappointing, and patients required external surgery for restoration of the cartilaginous framework and lumen.
Thirteen patients had stenosis extending from the lower half of the subglottis to the upper tracheal rings. They were all successfully managed with cricoid ring and upper tracheal resection with end-to-end anastomosis. Four of these patients needed additional endoscopic procedures prior to decannulation (laser cordotomy (n = 2), laser excision of anastomotic site granulations (n = 1) and repeat dilatations (n = 1)).
Six patients had stenosis involving the entire subglottis and the upper tracheal rings. These patients underwent a cricoid split procedure with costal cartilage graft augmentation for expansion of the subglottis and upper trachea (laryngotracheal reconstruction). Two of these six patients had a simultaneous cricoid ring and upper tracheal resection with anastomosis. One of the six patients required an additional laser cordotomy prior to decannulation.
Of the 22 patients in this group, 21 were decannulated. Endoscopic surgery failed in one patient; this patient was scheduled for subsequent open surgery, but has since been lost to follow up.
Combined subglottic and glottic stenosis
Initial endoscopic procedures in three of five patients proved unsuccessful. All needed an external procedure to achieve luminal restoration.
One patient was successfully managed by laryngofissure with stenting, followed by repeated dilatations. The same procedure proved unsuccessful in two others.
The four other cases required a cricoid split (anterior or posterior) procedure with costal cartilage grafting to achieve adequate luminal restoration. One of these four patients required three additional endoluminal procedures (laser excision of the glottic web and balloon dilatations) prior to decannulation.
Overall treatment results
Luminal restoration with removal of the tracheotomy tube was achieved in 29 out of 30 patients, with an overall success rate of 96.6 per cent. The remaining patient had persistent stenosis following an endoscopic procedure and has since been lost to follow up.
Of the 31 endoscopic procedures performed, 18 were undertaken on initial presentation or prior to an open procedure, and 13 procedures (in 8 patients) were carried out subsequent to and adjunctive to an open or external procedure. Success in the primary setting was only noted in two patients, while all eight patients that required endoscopic procedures following the external procedures could be decannulated.
Open or external surgical procedures were the prime contributors to surgical success in 27 of 30 patients. An evaluation of the efficacy of surgical procedures according to the site(s) of stenosis (Table III and Table II) indicated the most effective surgical options for various sites. In patients with isolated subglottic stenosis, an anterior cricoid split procedure with costal cartilage grafting (laryngotracheal reconstruction) proved adequate. In patients with subglottic and additional glottic involvement, supplementing the anterior costal graft with a posterior cricoid split procedure and graft proved efficacious. A lower subglottic and tracheal stenosis was best treated by cricotracheal resection and end-to-end anastomosis, with universal efficacy. Simple laryngofissure, anterior cricoid split or cricotracheal split with stenting, but without the use of costal cartilage grafts, proved extremely disappointing (Table III).
Discussion
The present paper, which describes 30 cases, represents one of the largest series of patients with acquired subglottic stenosis published to date in the English-language literature.Reference Pradhan, Sikka and Thakar1–Reference Kelkar, Shah, Mahandru and Kasbekar5 Isolated subglottic stenosis was found to be unusual in non-paediatric patients and in acquired situations, with most cases demonstrating additional contiguous involvement of the trachea or glottis. Furthermore, in contrast to previous reports wherein the primary aetiological factor has been endotracheal intubation related injury,Reference Roediger, Orloff and Courey2–Reference Kelkar, Shah, Mahandru and Kasbekar5, Reference Amoros, Ramos, Villalonga, Morera, Ferrer and Diaz9, Reference Ciccone, De Giacomo, Venuta, Ibrahim, Diso and Coloni10 the experience as noted here differs in having a large number of cases caused by strangulation or blunt neck injuries. Although the eventual decannulation rate of 29 out of 30 cases indicates an excellent overall result, many initial procedures proved unsuccessful. This report audits the results of various surgical procedures and identifies the most effective surgical procedures for various clinical situations.
The commonest anatomical pattern in all three major aetiological groups (blunt neck injury, strangulation injury and endotracheal intubation injury) was combined subglottic and tracheal stenosis. Isolated subglottic stenosis was noted in only 3 of the 30 cases (2 paediatric).
The different aetiological profile in this report, wherein the majority of stenosis cases were caused by external neck injury, posed special challenges, with such cases demonstrating near universal involvement of the cartilaginous framework and bilateral vocal fold immobility. Eighteen of 21 cases in the external injury group demonstrated vocal fold immobility, while this was unusual in the endotracheal intubation injury group (1 out of 8 cases). A high prevalence of vocal fold immobility in association with blunt neck injury has been previously noted.Reference Wu, Tsai, Lin, Hsu and Fong11 The common acute injury patterns for blunt neck injury and strangulation injury are cricotracheal separation and cricoid ring fracture,Reference Ford, Gardner and Lynch12 and it is conceivable that the recurrent laryngeal nerve would be damaged with such injuries. Vocal fold immobility in strangulation injury may also be consequent to upper subglottic or glottic scarring.
Initial evaluation also indicated a much greater incidence of cartilaginous framework involvement in the external injury group (17 out of 21 cases) compared with the endotracheal intubation injury group (1 out of 8 cases). The method of determining cartilaginous framework involvement is imprecise however, and despite the multifactorial assessment used for such a determination (radiological, endoscopic and stenosis consistency (soft or hard) evaluations), it is plausible that early chondritis would go undetected.Reference Roediger, Orloff and Courey2 The overall lack of treatment response to endoluminal surgical procedures, as well as the significant time lapse between injury and treatment, and the universal presence of a tracheotomy and associated inflammation in all patients, indicates that many such patients harbour incipient and undetected cartilage involvement.
The lack of clear guidelines in the literature with regard to the surgical treatment of acquired subglottic stenosis,Reference Jović, Dragičević, Komazec, Mitrović, Janjević and Gašić4 especially when accompanied by contiguous tracheal or glottic involvement, led to a multitude of procedures being undertaken. The variations in approach of the three individual surgeons also contributed to the wide variety of surgical procedures. An average of 2.2 procedures were undertaken per case, with many of the initial surgical procedures proving unsuccessful. The compiled dataset of all three surgeons as reported here provides a unique opportunity to assess the effectiveness or lack of effectiveness of various surgical procedures, and to frame guidelines on the most appropriate surgical procedures for different clinical situations.
Table II illustrates the surgical procedures attempted and the effectiveness of each. It indicates the lack of efficacy of an exclusive endoluminal approach, except in very specific situations. The lack of efficacy of endoscopic procedures indicates incipient and undetected cartilage involvement in cases thought to have isolated ‘mucosal’ stenosis, and therefore considered to be appropriate for endoscopic procedures. It is plausible that the universal prevalence of tracheotomy in all cases, as well as the large time period between injury and surgery in this study (mean of 4.0 months), may have contributed to such incipient cartilage involvement. It is our impression that if acute injury is not initially treated and is allowed to linger to a chronic stage, development of near universal involvement of the cartilaginous framework can occur over time and go against success with endoscopic techniques. Such cartilage involvement may be related to ongoing chondritis, hyperaemia-related resorption or perhaps cartilage ischaemia. Other studies of similar case groups have reported disappointment with endoscopic techniques in chronic stenosis.Reference Jović, Dragičević, Komazec, Mitrović, Janjević and Gašić4 Nevertheless, endoluminal procedures were found to be useful adjunctive procedures to supplement external open procedures.
Among the external surgical procedures, cricotracheal resection with anastomosis, and anterior or posterior cricoid split procedures with costal cartilage augmentation (laryngotracheal reconstruction), proved to be consistently reliable techniques for specific indications. Other open procedures were almost always disappointing.
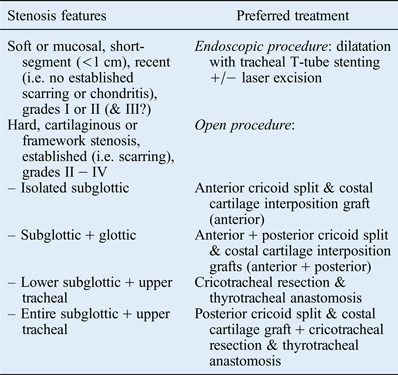
Based on this experience, a surgical scheme has been formulated for subglottic stenosis cases (Table IV). This forms the basis for our current practice. Case categorisation into the three subgroups of isolated subglottic stenosis, combined subglottic and tracheal stenosis, and combined subglottic and glottic stenosis has proved useful for selection of the most appropriate surgical procedure. A primary endoscopic luminal procedure is considered useful mainly in cases with soft, short-segment, recent (i.e. no established scarring), grade I or II stenosis. For other clinical situations, an open procedure is recommended.
Suggested treatment scheme for surgical treatment of subglottic stenosis
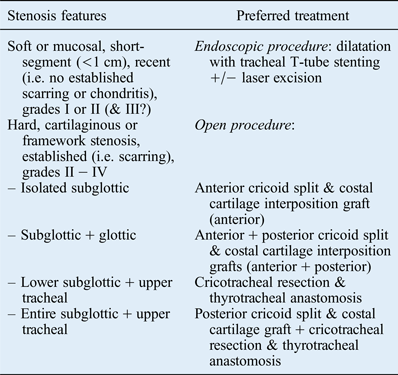
Among the open procedures, isolated subglottic stenosis is adequately treated with an anterior cricoid split procedure and a costal cartilage interposition graft. Cases of superior extension to the glottis (combined subglottic and glottic stenosis) proved especially challenging to treat, with a larger number of unsuccessful procedures than in the other groups (Table III). However, the combination of anterior or posterior cricoid split procedures with anterior or posterior cartilage grafts was effective for this clinical situation. Furthermore, this technique simultaneously divides and separates scar tissue in the glottic posterior commissure, leading to additional glottic expansion,Reference Pradhan, Sikka and Thakar1, Reference Zalzal13 and in some situations it also restores any limitation of arytenoid mobility associated with such scar tissue.Reference Pradhan, Sikka and Thakar1
Stenosis involving the subglottis and trachea is effectively treated using combined cricotracheal resection with end-to-end anastomosis. The procedure proved to be uniformly successful in clinical situations of lower subglottic and tracheal stenosis. However, it may be inappropriate for situations of stenosis extension to the upper subglottis or glottis; resection of these areas could jeopardise the vocal folds, or the upper reaches of the cricoid lamina or cricoarytenoid joint. For cases of tracheal and high subglottic, or subglottic plus glottic stenosis, cricotracheal resection with anastomosis is supplemented with an additional cricoid split procedure and posterior cartilage graft so as to expand the superior subglottis.
• The indications and effectiveness of advocated surgical procedures for acquired subglottic stenosis are unclear
• Surgical selection is guided by categorisation of stenosis into ‘mucosal or soft stenosis’ or ‘cartilaginous framework involvement or hard stenosis’
• Such categorisation is imprecise, and based on subjective and multifactorial assessment
• Acquired subglottic stenosis is rarely limited to the subglottis; most show contiguous involvement of trachea or glottis
• External injury stenosis cases have a worse profile than intubation-related cases
• Tracheostomy, and chronicity of stenosis, may predispose to chondritis and compromise the cartilaginous framework, limiting endoscopic treatment efficacy
The use of temporary luminal stents in association with external procedures, as practised in this report, is not universally supported by the contemporary literature.Reference Jović, Dragičević, Komazec, Mitrović, Janjević and Gašić4, Reference Cotton, Myer, O'Connor and Smith14 Tracheal T-tube stenting has been perceived to be unnecessary and to prolong morbidity by virtue of the accompanying tracheotomy.Reference Smith, Zur and Jacobs15 The prime reasons for tracheal T-tube stenting in our practice are to ensure a patent and safe post-operative airway, and to eliminate the risk of immediate post-operative airway compromise that is inherent to single-stage reconstruction procedures.Reference Smith, Zur and Jacobs15 Some possible benefits of stenting regarding shaping the luminal contour in laryngotracheal reconstruction have been reported, and stents have been proposed to enhance tracheal re-epithelisation and so aid anastomotic suture line healing.Reference Puma, Ragusa, Avenia, Urbani, Droghetti and Daddi16
Tracheal T-tube stenting is not part of our current practice for acute airway injury tracheal restoration, or for tumour-related tracheal resections. However, we consider tracheal T-tube stenting prudent for the patient group reported here as they demonstrate a high prevalence of identified poor prognostic factors by virtue of prior tracheotomies. These include consequent contamination or infection, delays in the time from injury to surgery and consequent scarring, grades III or IV stenosis, and posterior laryngeal inlet scarring with arytenoid fixation.Reference Simpson, Strong, Healy, Shapshay and Vaughan17, Reference Monnier, George, Monod and Lang18 All these factors may compromise and delay healing at the anastomotic suture line or the cartilage graft junction. Furthermore, most of the patients in the current study lived a long geographical distance from the surgical centre, and had limited access to the centre after discharge. Tracheal T-tube stenting in our practice limits the demand for immediate post-operative intensive care, facilitates early discharge from hospital and increases the chance of a patent airway in the first few months after discharge.