During the past decade, healthcare-associated infection rates have become closely scrutinized by federal agencies, such as the Centers for Disease Prevention and Control, and Medicare and Medicaid Services. 1 , 2 Furthermore, national quality rankings of healthcare facilities take into consideration the incidence of healthcare-associated infections (eg, Vizient). 3 Even though device-related infections are most frequently diagnosed in the inpatient setting, acquisition of multidrug-resistant organisms (eg, methicillin-resistant Staphylococcus aureus) might occur outside the acute inpatient arena.Reference Flanagan, Cassone, Montoya and Mody 4 , Reference Won, Munoz-Price, Lolans, Hota, Weinstein and Hayden 5
During the past few years, the infection control community has become more aware of the relevance of facilities within the continuum of care on not only the transmission of multidrug resistant organisms but also on shaping the regional epidemiology of antimicrobial resistance.Reference Flanagan, Cassone, Montoya and Mody 4 , Reference Won, Munoz-Price, Lolans, Hota, Weinstein and Hayden 5 Facilities outside inpatient settings that have proven to be of major significance include long-term acute-care hospitals and nursing homes.Reference Won, Munoz-Price, Lolans, Hota, Weinstein and Hayden 5 However, little is known about ambulatory settings, especially with the increasing complexity of care and severity of illness being seen in clinics.Reference Hefzy, Wegdan and Abdel Wahed 6 , Reference Bingham, Abell and Kienast 7 One study from 2014 showed that methicillin susceptible Staphylococcus aureus was present on 24% of surfaces, including doorknobs, slit-lamps, and computer keyboards.Reference Reem, Van Balen, Hoet and Cebulla 8 This finding is a cause for concern given that the number of outpatient care visits reached almost a billion visits in 2007. 9 Even though the relevance of environmental cleaning and disinfection in the inpatient area is well established, it is unclear how frequently this practice should be performed in outpatient settings. 9 To inform potential areas of improvement, we aimed to assess the quality of terminal cleaning practices in our outpatient clinics.
We performed this pilot study in the ambulatory clinics of a 700-bed, academic teaching hospital in the greater Milwaukee area. In 2016, 3 ambulatory areas within the main hospital were evaluated: primary care, gastroenterology, and obstetrics and gynecology clinics. These areas have annual patient volumes of 22,214, 7,882, and 49,922, respectively. According to hospital policy, high-touch horizontal surfaces (eg, exam bed, desk) are supposed to be disinfected in between patients by medical assistants with a quaternary ammonium mixed with 55% alcohol (Super Sani-Cloth, PDI, New York, NY). Terminal cleaning is supposed to be performed at the end of the day by Environmental Services using Oxycide (Ecolab, St Paul, MN). Fluorescent markers (Dazo, Ecolab) were placed on keyboards, computer mice, chairs, beds, steel tables, sinks, tables, vitals monitors, blood-pressure cuffs, and manometers. After 24 hours, markers were evaluated using ultraviolet lights to determine their presence. Although the manufacturer of the fluorescent markers recommends to only count fully removed marks as “cleaned,” we opted to include as “cleaned” both marks completely and partially removed. We chose the latter because we were evaluating any effort made by providers to wipe the areas rather than the quality of the cleaning. Surfaces with marks untouched were considered not cleaned. As quality control, we marked 10 areas using the fluorescent marker; once dried, half of the markers were subjected to the Super Sani-Cloth wipes and half to an aqueous solution. After 3 strokes, all marks were partially removed.
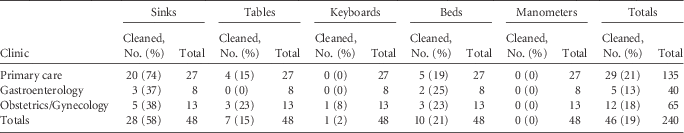
A total of 240 objects across 48 rooms were observed: 27 rooms were located in the primary care clinic, 8 in gastroenterology, and 13 in obstetrics and gynecology. Of the 240 objects, 46 (19%) were cleaned and 194 (80.8%) were not cleaned (Table 1). The objects least cleaned were the manometers (0%) and the keyboards (2%).
Distribution of Fluorescent Marker Results by Object and Clinic Observed

During our relatively short project, we found that only 19% of objects tested in the ambulatory setting were cleaned over a 24-hour period. The authors would like to emphasize that high-alcohol disinfectants, like the one we used in the clinics observed, could fail to completely remove the fluorescent markers; however, given that we considered partially removed sites as “cleaned,” this should not have influenced our results. Our findings represent a particularly low compliance with cleaning considering that each exam room is used for multiple patients during a 24-hour period. Nonetheless, at this time there are no clear recommendations on how frequently surfaces should be disinfected in the ambulatory setting. 9 A position paper by the Canadian Paediatric Society recommends cleaning frequently touched surfaces, such as tables, treatment chairs, and sinks on a daily basis. 10 Furthermore, this Canadian paper recommends that noncritical items that touch only intact skin such as blood pressure cuffs should be disinfected ideally after each use. The Centers for Disease Control and Prevention and Healthcare Infection Control Practices 2016 Guide for Infection Prevention for Outpatient Settings recommends establishing policies and procedures for environmental cleaning including, selecting EPA registered disinfectants, and following manufacturer’s recommendations; however, it does not specify the frequency of cleaning. 9 A potential reason for the lack of standardization on recommendations is the paucity of data showing horizontal transmission of pathogens occurs in the ambulatory areas. Additionally, patients tend to stay only for a limited time in the ambulatory environment and thus have limited interaction with their surroundings.
Hospital-based outpatient clinics frequently share environmental service personnel with the inpatient areas. Thus, increasing cleaning in the outpatient areas could negatively impact the coverage of inpatient areas. Given that we do not know the clinical implications of reduced environmental disinfection in the outpatient setting it is difficult to justify shifts in coverage—or adding environmental service personnel—to hospital administrators. Future research should aim at better understanding the clinical implications of lack of proper environmental disinfection in the ambulatory setting. Finally, guidelines for the frequency of cleaning and disinfection within the ambulatory care areas are needed.
ACKNOWLEDGMENTS
Ecolab provided the product used for this study. However, the company was not aware of the results of this project and did not participate in the interpretation of the findings.
Financial support: No financial support was provided relevant to this article.
Potential conflicts of interest: All authors report no conflicts of interest relevant to this article.