Introduction
The restricted and repetitive behaviors characteristic of autism spectrum disorders (ASD) can be the most disabling feature of the disorder (Bishop et al. Reference Bishop, Richler, Cain and Lord2007), although they have received far less research attention than social and communication impairments. Neurocognitive impairments affecting the voluntary control of behavior may contribute to repetitive behaviors in ASD. Successful voluntary behavioral inhibition is supported by frontostriatal systems (Sweeney et al. Reference Sweeney, Mintum, Kwee, Wiseman, Brown, Rosenberg and Carl1996; Kelly et al. Reference Kelly, Hester, Murphy, Javitt, Foxe and Garavan2004; Rubia et al. Reference Rubia, Smith, Taylor and Brammer2007) and disruption of this circuitry can impede the ability to suppress repetitive responses (Suvorov et al. Reference Suvorov, Shuvaev, Voilokova, Chivileva and Shefer1997; Christ et al. Reference Christ, White, Brunstrom and Abrams2003). Thus, reduced inhibitory control, mediated by alterations in frontostriatal systems, may contribute to rigid stereotypic preferences in ASD.
Eye movement studies offer a translational approach for examining disturbances in frontostriatal systems that support the ability to voluntarily suppress context-inappropriate responses. Studies applying antisaccade (ANTI) paradigms, in which individuals are instructed to generate eye movements away from rather than toward novel targets, have demonstrated deficits in ASD participants' ability to inhibit prepotent responses (Minshew et al. Reference Minshew, Luna and Sweeney1999; Goldberg et al. Reference Goldberg, Lasker, Zee, Garth, Tien and Landa2002; Manoach et al. Reference Manoach, Lindgren and Barton2004; Luna et al. Reference Luna, Doll, Hegedus, Minshew and Sweeney2007). These results are consistent with functional magnetic resonance imaging (fMRI) findings of atypical frontostriatal activation in ASD during visually guided saccade (Takarae et al. Reference Takarae, Minshew, Luna and Sweeney2007) and ANTI paradigms (Liu et al. Reference Liu, Sweeney, Minshew, Geier, Garver and Luna2007; Thakkar et al. Reference Thakkar, Polli, Joseph, Tuch, Hadjikhani, Barton and Manoach2008), and suggest that oculomotor tasks may be useful paradigms for investigating response inhibition disturbances in ASD.
Lopez et al. (Reference Lopez, Lincoln, Ozonoff and Lai2005) and South et al. (Reference South, Ozonoff and McMahon2007) reported relationships between performance on neuropsychological tests of executive function and repetitive behaviors in autism, suggesting an involvement of impaired response inhibition and cognitive flexibility in the repetitive behaviors associated with ASD. Although executive dysfunction has been shown to be associated with social-communication impairments as well (McEvoy et al. Reference McEvoy, Rogers and Pennington1993; Russell et al. Reference Russell, Saltmarsh and Hill1999), no studies to date have indicated that atypical cognitive/behavioral inhibition is associated with the core social and communication abnormalities in ASD. Translational research examining potential causes of restricted and repetitive behaviors in ASD, including impaired inhibitory control supported by dorsolateral prefrontal cortical (DLPFC) and frontal eye field connections with the anterior cingulate cortex (Taylor et al. Reference Taylor, Stern and Gehring2007) and striatum (Everling et al. Reference Everling, Dorris, Klein and Munoz1999, Reference Everling and Munoz2000), can help to clarify specific cognitive mechanisms and the pathophysiology of this relatively underexplored dimension of ASD. Consistent with this hypothesis, Thakkar et al. (Reference Thakkar, Polli, Joseph, Tuch, Hadjikhani, Barton and Manoach2008) recently reported that participants with ASD exhibit abnormally increased activation of rostral anterior cingulate cortex relative to healthy controls during correct antisaccade responses. This hyperactivation was associated with the level to which affected individuals exhibited repetitive behaviors, suggesting that anterior cingulate dysfunction during response monitoring may contribute to restricted and stereotyped behaviors in ASD.
In the present study, individuals with ASD (autistic disorder or Asperger's syndrome) and age- and IQ-matched healthy control participants performed an ANTI task. A visually guided saccade control task was also administered to assess automatic visual attention and sensorimotor components of voluntary saccades. We hypothesized that individuals with higher clinical ratings of repetitive behavior would have higher error rates on the ANTI task (as indexed by saccades toward rather than away from peripheral targets).
Method
Subjects
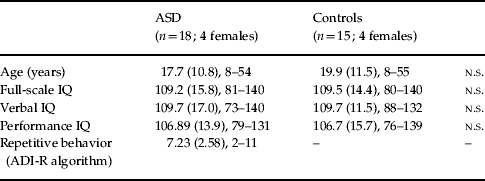
Participants included 18 individuals with autism (n=13) or Asperger's syndrome (n=5) (four females) and 15 healthy control individuals (four females) who were matched on age and IQ (Table 1). Because of the known association between age and ANTI performance (Luna et al. Reference Luna, Doll, Hegedus, Minshew and Sweeney2007), we ensured that groups did not differ in the proportion of children aged 8–12 years [ASD: 39% (7); controls: 40% (6)], adolescents aged 13–17 years [ASD: 17% (3); controls: 20% (3)], or adults aged 18–55 years [ASD: 44% (8); controls: 40% (6)]. Diagnoses were established according to DSM-IV criteria using two structured research diagnostic instruments, the Autism Diagnostic Inventory – Revised (ADI-R; Lord et al. Reference Lord, Rutter and Le Couteur1994) and the Autism Diagnostic Observation Schedule – Generic (ADOS-G; Lord et al. Reference Lord, Risi, Lambrecht, Cook, Leventhal, DiLavore, Pickles and Rutter2000). Individuals were excluded if they had a disorder with known etiology associated with ASD, including Fragile X syndrome and tuberous sclerosis.
Demographic, intellectual and clinical characteristics of autism spectrum disorder (ASD) and healthy control subjects

ADI-R, Autism Diagnostic Inventory – Revised; n.s., not significant.
Values are given as mean (standard deviation), range.
Potential control participants were excluded for a personal history of psychiatric or neurological disorders, a family history of an ASD, or a first-degree relative with a history of severe psychopathology or developmental disorders, including schizophrenia, bipolar disorder, obsessive–compulsive disorder (OCD), attention deficit hyperactivity disorder or substance abuse. Both healthy control participants and individuals with ASD were excluded for a history of head injury, birth injury or seizure disorder. Individuals in both groups had full-scale IQs >80, and disparities between verbal and non-verbal IQs <20 points. Individuals were excluded if they reported taking medications known to affect eye movements or performance on cognitive tasks, including antipsychotics, methylphenidate, amphetamines or anticonvulsants. Far visual acuity was normal or corrected to at least 20/40. Informed consent was obtained from all adult participants; children and adolescents provided assent, and their parents provided consent. All study procedures were approved by the Institutional Review Board of the University of Illinois at Chicago.
Procedures
Participants were tested in a darkened black room and positioned in a chin and forehead rest with head strap and occipital restraints to minimize head movement. An examiner in an adjacent room provided instructions using an intercom and monitored eye movement activity during testing to ensure that participants were alert and performing tasks according to instructions. Visual stimuli subtending 1° of visual angle were presented in the horizontal plane at eye level on a 72′×96′ seamless rear projection screen (Stewart Techplex 150) using a high-resolution projector (Christie Digital Systems Marquee 8500 Ultra projector with 2500×2000 resolution and 120 Hz refresh rate). Participants were seated 55 inches from the screen.
Electrodes were placed at the lateral and nasal canthi of each eye to obtain direct current electro-oculography (EOG) recordings (Grass Neurodata 12 Acquisition System, Astro-Med, Inc., West Warwick, RI, USA). EOG was selected over infrared (IR) recordings because of limitations in IR methods for measuring eye movements exceeding 12–15° from center. Blinks were monitored using electrodes placed above and below the left eye linked to an AC-coupled bioamplifier. Data from the right eye were scored unless prevented by signal clipping or high noise artifact; in these cases, recordings from the left eye were examined.
Visually guided saccade task
Subjects fixated a central target that was presented for a variable period (1500–2500 ms) prior to being extinguished and replaced by a peripheral target appearing for 2 s at 10°, 20° or 30° to the right or left of center. Multiple target locations were included to ensure that locations could not be anticipated. Target location was counterbalanced across hemifield and visual angle. Subjects were instructed to look at peripheral targets as soon as they appeared. Subjects understood the verbal instructions for the visually guided saccade task, so no practice trials were administered. Two conditions, gap and overlap, were presented to examine whether individuals with ASD are selectively impaired in conditions in which their attention is released prior to the appearance of a novel stimulus (gap trials) or during conditions in which they must disengage attention from a central stimulus (overlap trials). In gap trials, the central fixation target was extinguished 200 ms before the peripheral target appeared. In overlap trials, the central fixation remained illuminated for 200 ms after the appearance of the peripheral target. A temporal gap between the offset of the initial cue and the presentation of a novel peripheral stimulus allows the visual fixation system to be released, reducing the latency of shifts of attention and gaze. By contrast, overlap effects occur when the central target persists after the appearance of the peripheral cue, prolonging activity in visual fixation systems, and to the extent attention is engaged at central fixation there is a parallel increase in response latencies. Thirty-six trials of each condition (72 total trials) were interleaved and presented in a fixed pseudo-random order. Saccade latencies were measured.
ANTI trials
Stimulus parameters, including an interleaving of gap and overlap trials, were identical to those used in the visually guided saccade task. However, subjects were instructed to inhibit saccades toward the peripheral targets, and instead to look immediately to the mirror location of the targets in the opposite hemifield. To ensure that poor performance did not reflect inattention or confusion about task demands, subjects were reminded of task instructions if two consecutive prosaccade errors were made. Each subject also participated in 10 practice trials that were repeated if subjects did not perform two consecutive successful trials. Testing was discontinued if subjects were not able to successfully complete the practice session. Three participants with ASD were not able to successfully complete practice trials and are not included in the present study. The percentage of trials with prosaccade errors (trials in which subjects look toward rather than away from targets) and the latency of correct antisaccade responses were measured. ANTI trials were always presented following visually guided saccade trials.
ADI-R
The ADI-R is a semi-structured interview administered to parents or caregivers. The interview includes items related to early development, social behavior, communication skill, and repetitive behaviors. Algorithms for social, communication and repetitive behavior domains have been validated (Lord et al. Reference Lord, Risi, Lambrecht, Cook, Leventhal, DiLavore, Pickles and Rutter2000) and were examined in the present study. Based on prior work, repetitive behaviors were subdivided into ‘higher-order’ and ‘sensorimotor’ categories (see Turner, Reference Turner1999 for a review). Higher-order repetitive behavior included algorithm items C1 (encompassing preoccupation or circumscribed pattern of interest) and C2 (apparently compulsive adherence to non-functional routines or rituals). Sensorimotor repetitive behaviors included algorithm items C3 (stereotyped and repetitive motor mannerisms) and C4 (preoccupations with parts of objects or non-functional elements of materials).
Analysis of oculomotor recordings
Recordings were digitized at 500 Hz (DI-210 16-bit A/D, DATAQ Instruments) and analyzed off-line using custom software developed in our laboratory. An algorithm identified saccade initiation when eye velocity rose above 30°/s, and saccade termination when eye velocity returned below that level. Trials were rejected if a blink occurred in the interval between 100 ms prior to presentation of peripheral targets and the end of primary saccades. Data were scored without knowledge of diagnostic or demographic participant characteristics.
Statistical analysis
Repeated-measures ANOVAs were used to compare ASD and control groups. The interactions of diagnostic group with target location (10°, 20° or 30° from center), visual hemifield (right versus left) and condition (gap versus overlap) were examined. There were no significant hemifield effects, or group by hemifield interactions, so data were pooled across hemifield for hypothesis testing. For analyses in which significant group interactions with target location or task condition were not significant, performance was pooled across locations and/or conditions. Because ANTI performance is known to improve with age (Luna et al. Reference Luna, Garver, Urban, Lazar and Sweeney2004), age was included as a covariate in all analyses.
Results
Visually guided saccades
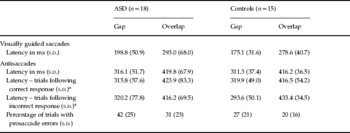
ASD subjects and healthy controls did not differ in the latency of visually guided saccades [F(1, 31)=1.22, p=0.29; see Table 2]. Latencies were shorter in the gap than the overlap condition [F(1, 31)=244.60, p<0.001] but there was no group difference in gap and overlap trials [F(1, 31)=0.37, p=0.55].
Performance of autism spectrum disorder (ASD) and healthy subjects on visually guided saccade and antisaccade tasks

s.d., Standard deviation.
a The condition of the preceding trial is not indicated.
Antisaccades
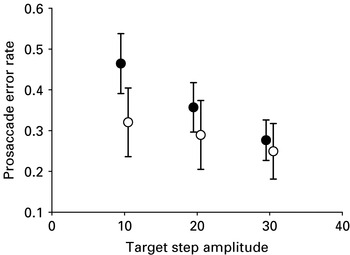
ASD subjects made more prosaccade errors than healthy individuals on the ANTI task [F(1, 30)=4.12, p=0.05]. For both groups, a greater number of prosaccade errors occurred on gap than overlap trials [F(1, 30)=11.42, p<0.01] and on trials with smaller target displacement [F(1, 30)=9.66, p=0.001]. No differential effect of gap versus overlap trials was observed between groups [F(1, 30)=0.49, p=0.49], but an interaction between location and group was observed as ASD subjects had disproportionately increased error rates on trials where targets were presented closer to central fixation [F(2, 29)=7.65, p=0.01; Fig. 1]. Differences between groups in error rates were significant [t(30)=2.54, p=0.03] at 10° of visual angle and approached significance at 20° of visual angle [t(30)=1.77, p=0.08]. Increased age was associated with fewer prosaccade errors (r=−0.45, p<0.001), but no age by group interactions were observed [F(2, 29)=0.73, p=0.49].
Mean rate of prosaccade errors for autism spectrum disorder (ASD, •) and healthy participants (○) across various target step amplitudes from center fixation in degrees of visual angle on an antisaccade task. ASD participants made more prosaccade errors than healthy participants, and the magnitude of this effect was greater when targets were presented closer to center fixation. Error bars show standard error.

There were no group differences in response latencies for correctly performed ANTI trials [F(1, 31)=0.01, p=0.94]. Shorter latencies for gap relative to overlap trials were observed across groups [F(1, 31)=13.67, p=0.001] but the interaction of group and condition for latency data was not significant [F(1, 31)=0.20, p=0.66]. To examine whether participants adjusted their response timing following antisaccade errors, response latencies for correct responses following antisaccade errors were compared with response latencies for correct responses following a correct response. Overall, participants did not adjust their response rates following antisaccade errors [F(1, 28)=0.28, p=0.60; see Table 2]. The group by trial type (post-error versus post-correct) latency interaction was not significant [F(1, 28)=0.02, p=0.89].
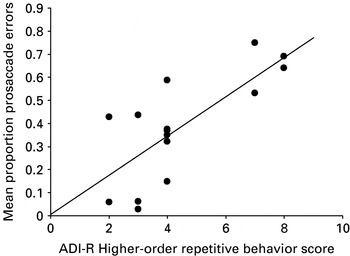
Relationship between ANTI performance and repetitive behaviors (Fig. 2)
Prosaccade errors were related to higher-order repetitive behaviors both before (r=0.65, p=0.01) and after controlling for age (partial r=0.73, p=0.004). Prosaccade errors were not associated with sensorimotor repetitive behaviors (r=0.11, p=0.62; partial r=0.08, p=0.79). The relationship between prosaccade errors on the ANTI task and social and communication scores from the ADI-R were not significant (r's <0.2). The relationship between ADI-R ratings of repetitive behaviors and age was not significant (r=0.04, p=0.86).
Relationship between prosaccade error rates and scores on algorithm items C1 and C2 on the restricted, repetitive behavior domain of the Autism Diagnostic Inventory – Revised (ADI-R) for autism spectrum disorder (ASD) participants. This relationship was significant both before and after controlling for age and IQ (r=0.65, p=0.01).

Discussion
The current study provides evidence that impairments in inhibitory control are associated with an increased severity of higher-order repetitive behaviors in ASD patients but not with sensorimotor repetitive behaviors or communication and social disturbances. These findings highlight a distinct pattern of neurocognitive dysfunction associated with behavioral inflexibility involving preoccupations or compulsions in ASD. Specifically, these data suggest that higher-order repetitive behaviors in ASD are not exclusively a result of intense emotional attachment to an object or activity of interest, but also involve fundamental problems in behavioral flexibility. In the context of previous findings from non-human primate neurophysiology (Schlag-Rey et al. Reference Schlag-Rey, Amador, Sanchez and Schlag1997; Johnston & Everling, Reference Johnston and Everling2006) and human fMRI studies (Sweeney et al. Reference Sweeney, Levy and Harris2002; Manoach et al. Reference Manoach, Thakkar, Cain, Polli, Edelman, Fischl and Barton2007; Polli et al. 2007) with the ANTI task, the present findings suggest that deficits in inhibitory control mediated by alterations in frontostriatal systems may have an important role in the pathophysiology of higher-order restricted and repetitive behaviors in ASD.
Inhibitory control in ASD
Participants with ASD made a greater number of prosaccade errors on an ANTI task than healthy control participants. The rate of response inhibition failures varied as a function of target location for both participants with ASD and healthy controls. However, the effect of target location was disproportionate for the ASD participants, who made increased errors relative to controls at the two locations closest to center, but not at the location furthest from center. These findings are similar to those reported on children with OCD (Rosenberg et al. Reference Rosenberg, Averbach, O'Hearn, Seymour, Birmaher and Sweeney1997) and suggest that inhibitory control networks are more susceptible to perturbations when visual information that should be ignored appears closer to the preceding focus of attention and fixation.
The finding of increased prosaccade errors on an ANTI task in ASD is consistent with prior work from our laboratory with independent samples (Minshew et al. Reference Minshew, Luna and Sweeney1999; Luna et al. Reference Luna, Doll, Hegedus, Minshew and Sweeney2007) and with other published work (Goldberg et al. Reference Goldberg, Lasker, Zee, Garth, Tien and Landa2002; Manoach et al. Reference Manoach, Lindgren and Barton2004; Thakkar et al. Reference Thakkar, Polli, Joseph, Tuch, Hadjikhani, Barton and Manoach2008). The mechanistic understanding of this pattern of deficits involves an alteration in top-down signals from DLPFC to frontal eye fields, striatum and superior colliculus that enable steady fixation on objects of interest as relevant to ongoing behavioral plans, and the ability to override effects of novel sensory events that tend to automatically elicit shifts of gaze toward them (Everling et al. Reference Everling, Dorris, Klein and Munoz1999, Reference Everling and Munoz2000). Impaired inhibitory control on the ANTI task implicates this specific frontostriatal system in ASD, and parallels previous fMRI findings of DLPFC and anterior cingulate alterations during tasks requiring a voluntary suppression of prepotent behavioral responses in individuals with ASD (Schmitz et al. Reference Schmitz, Rubia, Daly, Smith, Williams and Murphy2006; Liu et al. Reference Liu, Sweeney, Minshew, Geier, Garver and Luna2007). Consistent with this hypothesis, Thakkar et al. (Reference Thakkar, Polli, Joseph, Tuch, Hadjikhani, Barton and Manoach2008) recently reported associations in individuals with ASD between anterior cingulate cortical hyperactivation during antisaccade trials, decreased white matter microstructural integrity in right rostral anterior cingulate cortex, and repetitive behavior.
Frontostriatal dysfunction and repetitive behaviors
ASD participants' response inhibition errors were related to clinically rated severity of higher-order, but not sensorimotor, repetitive behaviors. Higher-order repetitive behaviors involve a disturbance in context-dependent behavioral flexibility whereas sensorimotor stereotypies involve repetitive motor actions or sensory behaviors (Cuccaro et al. Reference Cuccaro, Shao, Grubber, Slifer, Wolpert, Donnelly, Abramson, Ravan, Wright, DeLong and Pericak-Vance2003). Moreover, higher-order behavioral inflexibility is unique to ASD in that it is not typically observed in other developmental disorders, whereas sensorimotor repetitive behaviors are evident in many developmental disorders. Previous findings (Lopez et al. Reference Lopez, Lincoln, Ozonoff and Lai2005; South et al. Reference South, Ozonoff and McMahon2007) and the present data indicate that inhibitory control deficits are associated with a resistance to change behavior according to dynamic environmental demands. Previous visually guided saccade studies (Minshew et al. Reference Minshew, Luna and Sweeney1999; Takarae et al. Reference Takarae, Minshew, Luna and Sweeney2004), and the present study, each failed to find disturbances in the ability to automatically redirect visual attention in ASD. This consistent pattern of impaired performance on ANTI but not visually guided saccade tasks suggests a deficit that is specific to situations that require voluntary inhibitory control and, by inference, that engage rostral frontostriatal systems. These mechanisms associated with higher-order repetitive behaviors are distinct from those involved in sensorimotor stereotypies.
Clinical observations suggest that intense emotional attachment to specific stimuli or activities also contributes to repetitive behaviors in ASD. In this regard, it is important to note that the results of the present study were obtained in a laboratory setting with simple ‘dot’ targets having little emotional salience. It is possible that reduced cognitive flexibility may prove to have a greater behavioral impact during situations with high emotional or motivational salience. However, its manifestation in situations with modest motivational considerations, as in the context of the current laboratory studies, points to a fundamental deficit in inhibitory control supporting behavioral flexibility as a significant contributing factor. Thus, the phenomenon of higher-order repetitive behaviors in ASD seems to result not only from issues related to intense emotional engagement but also to a fundamental neurocognitive alteration in the dynamic control of behavioral flexibility that implicates prefrontal systems.
The observed connection between inhibitory control deficits and repetitive behaviors is consistent with studies of individuals with OCD, a disorder that, like ASD, is characterized by compulsive and rigid behaviors (APA, 2000). Tien et al. (Reference Tien, Pearlson, Machlin, Bylsma and Hoehn-Saric1992) and Rosenberg et al. (Reference Rosenberg, Averbach, O'Hearn, Seymour, Birmaher and Sweeney1997) observed deficits in response inhibition on an ANTI task among individuals with OCD. Although both groups seem to have inhibitory control deficits, OCD patients also have been noted to have increased antisaccade latencies (Maruff et al. Reference Maruff, Purcell, Tyler, Pantellis and Currie1999; van der Wee et al. Reference van der Wee, Hardeman, Ramsey, Raemakers, Van Megen, Denys, Westenberg and Kahn2006). This suggests that patients with OCD show either a slowing of psychomotor function or an attempt to compensate for inhibitory deficits by slowing reaction times to better inhibit reflexive responses. The degree of similarity in the causes of inflexible behavior in ASD and OCD remains to be established, but observations that inhibitory control deficits are evident in both groups and are reduced by serotonergic drugs in neuropsychiatric disorders (Rosenberg et al. Reference Rosenberg, McMaster, Keshavan, Fitzgerald, Stewart and Moore2000; Moresco et al. Reference Moresco, Pietra, Henin, Panzacchi, Locatelli, Bonaldi, Carinelli, Gobbo, Bellodi, Perani and Fazio2007) suggest that frontostriatal disruption is one commonality in these behavioral disturbances.
Frontostriatal alterations and repetitive behaviors in ASD and OCD may be related to alterations in brain serotonin systems. Whitaker-Azmitia (Reference Whitaker-Azmitia2005) and Boylan et al. (Reference Boylan, Blue and Hohmann2007) have argued that a loss of 5-hydroxytryptamine (5-HT) terminals in cerebral cortex, especially in forebrain regions, may result in social, repetitive and sensorimotor behaviors that parallel those seen in individuals with ASD. Studying rat pups injected with a 5-HT neurotoxin in the major afferent pathway to the forebrain, Boylan et al. (Reference Boylan, Blue and Hohmann2007) showed that neonatal 5-HT depletion results in increased repetitive behaviors. A role for serotonergic alterations in frontostriatal system disturbances in ASD is also suggested by reports of decreased serotonin synthesis within frontostriatal circuitry in ASD (Chugani et al. Reference Chugani, Muzik, Rothermel, Behen, Chakraborty, Mangner, da Silva and Chugani1997), elevated whole-blood serotonin levels (Cook et al. Reference Cook, Leventhal and Freedman1988), and reduced repetitive behaviors in ASD following therapy with selective serotonin reuptake inhibitors (DeLong et al. Reference DeLong, Teague and McSwain1998; Moore et al. Reference Moore, Eichner and Jones2004; Owley et al. Reference Owley, Walton, Salt, Guter, Winnega, Leventhal and Cook2005). Investigating the effects of serotonin alterations on voluntary inhibitory control deficits in ASD is therefore a strategy that may be important both for developing models of the pathophysiology of repetitive behaviors in ASD and for new treatments targeting these behaviors.
Conclusions
The present study has demonstrated that individuals with ASD show deficits in inhibitory control that are associated with the clinically rated intensity of higher-order repetitive behaviors. Deficits in inhibitory control were not associated with other core features of ASD, indicating that the reported relationship is specific to a subset of repetitive behaviors. These findings implicate disturbances in frontostriatal circuitry as a cause of reduced behavioral flexibility in ASD.
Acknowledgments
This study was supported by the NICHD Collaborative Program of Excellence in Autism HD35469, the NIH Autism Center of Excellence Project award HD055751, and the National Alliance for Autism Research. We also gratefully acknowledge the participation of the individual subjects and their families in these studies.
Declaration of Interest
None.