Background
An increased mortality risk associated with mental disorder has been reported for several decades, but surprisingly few studies are based on random samples with interview-based psychiatric diagnoses (Eaton et al. Reference Eaton, Martins, Nestadt, Bienvenu, Clarke and Alexandre2008). The ascertainment of mental disorder is difficult and cumbersome, and psychiatric epidemiology has, partly due to practical necessity, evolved from being dependent on psychiatric expertise towards standardised interview schedules. Validation studies of the diagnoses generated from such schedules have shown that many, but not all of these diagnoses have good agreement with what is regarded as criterion standard – psychiatric interview-based diagnoses (Anthony et al. Reference Anthony, Folstein, Romanowski, Korff, Nestadt, Charal, Merchant, Brown, Shapiro, Kramer and Gruenberg1985; Helzer et al. Reference Helzer, Robins and Mcevoy1985; Lehtinen et al. Reference Lehtinen, Joukamaa, Lahtela, Raitasalo, Jyrkinen, Maatela and Aromaa1990; Wittchen, Reference Wittchen1994). Longer-follow ups (i.e. based on older cohorts) have shown increased long-term mortality associated with depression (Murphy et al. Reference Murphy, Monson, Olivier, Sobol and Leighton1987, Reference Murphy, Monson, Olivier, Sobol, Pratt and Leighton1989, Reference Murphy, Burke, Monson, Horton, Laird, Lesage, Sobol and Leighton2008), anxiety (Grasbeck et al. Reference Grasbeck, Rorsman, Hagnell and Isberg1996) and alcohol use disorder (Murphy et al. Reference Murphy, Monson, Olivier, Sobol, Pratt and Leighton1989; Grasbeck et al. Reference Grasbeck, Rorsman, Hagnell and Isberg1996; Mattisson et al. Reference Mattisson, Bogren, Öjehagen, Nordström and Horstmann2011). More contemporary samples, which are larger, based on stratified random sampling and use standardised interview schedules on the other hand show increased mortality for DSM/International Classification of Disease (ICD) depression (Bruce et al. Reference Bruce, Leaf, Rozal, Florio and Hoff1994; Kouzis et al. Reference Kouzis, Eaton and Leaf1995; Joukamaa et al. Reference Joukamaa, Heliövaara, Knekt, Aromaa, Raitasalo and Lehtinen2001; Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012), phobia (but not other anxiety), alcohol use disorder (Bruce et al. Reference Bruce, Leaf, Rozal, Florio and Hoff1994; Badawi et al. Reference Badawi, Eaton, Myllulouma, Weimer and Gallo1999; Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012; Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013), drug use (Kouzis et al. Reference Kouzis, Eaton and Leaf1995; Badawi et al. Reference Badawi, Eaton, Myllulouma, Weimer and Gallo1999), functional psychosis/schizophrenia (Bruce et al. Reference Bruce, Leaf, Rozal, Florio and Hoff1994; Joukamaa et al. Reference Joukamaa, Heliövaara, Knekt, Aromaa, Raitasalo and Lehtinen2001; Suvisaari et al. Reference Suvisaari, Partti, Perälä, Viertiö, Saarni, Lönnqvist, Saarni and Härkänen2013) and antisocial personality disorder (Eaton et al. Reference Eaton, Kalaydjian, Scharfstein, Mezuk and Ding2007, Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013). Few studies have long follow-up periods and most of them are based on the American Epidemiologic Catchment Area (ECA) samples. Only one previous study exists where diagnosis was set by interviewing psychiatrist, the older Swedish Lundby study (Rorsman et al. Reference Rorsman, Hagnell and Lanke1982; Grasbeck et al. Reference Grasbeck, Rorsman, Hagnell and Isberg1996; Mattisson et al. Reference Mattisson, Bogren, Öjehagen, Nordström and Horstmann2011) where self-defined criteria diagnoses were used. Moreover, even though worse somatic health is repeatedly suggested as a mechanism behind the increased mortality in those with mental disorders there are few psychiatric samples having such information (Henderson et al. Reference Henderson, Hothopf, Shah, Hayes and Kuh2011; Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012; Suvisaari et al. Reference Suvisaari, Partti, Perälä, Viertiö, Saarni, Lönnqvist, Saarni and Härkänen2013). We present findings on long-term mortality in a large population-based sample with psychiatric diagnoses from semi-structured interview with a psychiatrist and information on health status collected at a clinical examination.
Method
Participants
The Rehabilitation Needs Survey (with Swedish acronym REBUS) was collected to identify unmet somatic, psychiatric and social needs in Sweden. A two-phase sampling procedure was employed (a detailed figure of the sampling procedure is found in table 5 in Appendix). First, four samples were drawn from the Stockholm County Population Register (frame population) in November 1969, March 1970, August 1970 and October 1970, stratified by age (18–25, 26–46 and 46–65). To members of these samples (total n = 32 186), a screening questionnaire was sent with items on somatic and psychiatric symptoms and social circumstances. At the second phase, subsamples were drawn from these samples (and from non-respondents). These subsamples were, based on screening questionnaire information and hospital registers, stratified according to potential illness: high likelihood, moderate likelihood, likely healthy and screening questionnaire non-responders (Halldin, Reference Halldin1984b ). All individuals in the four subsamples were invited to participate in rigorous health examinations at a hospital over a whole day. Subsamples 1–3 were also asked to take part in a psychiatric examination. Subsamples 1 and 2 participated in a dental examination, where smoking information was collected. Of the 2283 individuals in the subsamples 1–3, 1896 participated in psychiatric examination in 1970–1971 (subsample 1 summer–autumn 1970, 2 autumn–winter 1970 and 3 winter–spring 1971), which was 80% of those in the frame and 88% of the weighted population. In the three age groups (18–25, 26–45 and 46–65), there are 651, 715 and 552 individuals. First and second stage samples are compared in table 6 in appendix, showing that age and selected questionnaire responses are similar after applying weights. Non-participation has been examined elsewhere (Halldin, Reference Halldin1984a ), and showed that 6% was from refusal, 3% from migration (returning primarily to Finland) and the rest were unreachable or dead. Non-participants were more often working class, while there was no difference in levels of registered sickness absence or penal offences between participants and non-participants. All of those showing up for medical examination participated in the psychiatric examination.
Instruments
Psychiatric examination
The psychiatric interview was conducted by two psychiatrists, Jan Halldin and Karin Björk at Danderyd hospital during the same day as somatic health examinations and interview by health care worker. The interview was semi-structured covering four sections: (1) medical history of psychiatric care and use of psychotropic medicine, (2) psychiatric symptoms in the last 12 months or lifetime (a checklist of 30 symptoms, e.g. worrying, tension, panic, anxiety and phobias, obsessional symptoms, depressed mood and ideation, delusions) and questions on traumatic head injuries, (3) biographical information on circumstances in family, school, work and childhood and (4) alcohol and substance use and their consequences. Mental status examination was recorded during the interview with ratings on 15 observational variables regarding emotional and cognitive deficits. Diagnoses were set according to 8th version of the ICD (ICD-8) following a list of 36 diagnoses, with pre-established definitions and refer to the last 12 months (Halldin, Reference Halldin1984b ). Inter-rater comparisons showed no statistical difference between the prevalence of severe or moderate disorders between the two psychiatrists (Halldin, Reference Halldin1984b ).
Mortality
Date of death was obtained from the Total Population Register maintained by Statistics Sweden. The Total Population Register was set up in 1968, is based on the Swedish Tax Register, and encompasses all residents in Sweden and Swedish citizens. In the event of a death in Sweden, a physician has to submit a death certificate to the Tax Agency. When a Swedish citizen dies abroad, the Tax Agency is informed by the appropriate embassy or consulate. Linkage of REBUS participants and non-participants to entries in the Total Population Register was enabled by the ten-digit personal identity numbers under the administration of the National Tax Board, which is assigned to all individuals who have resided in Sweden. We had information on all deaths up to and including September 2011.
Somatic health
Six potential mediating factors measured at baseline medical examination were examined: Body composition was computed as BMI (kg/m2) from weight and height measurements grouped as overweight (BMI 25–29), obesity (BMI 30 or more) and underweight (BMI less than 18.5). Hypertension was defined as systolic blood pressure ≥140 mm Hg and/or diastolic blood pressure ≥90 mm Hg. Fasting blood glucose (FBG) values were grouped as low (<3.0 mmol/l), normal (3.0–6.9 mmol/l), high (7.0–7.7 mmol/l) or very high (>7.7 mmol/l) where the two latter is the WHO 1985 definition of diabetes. Pulmonary function, forced vital capacity (FVC) and forced expiratory volume in 1 s (FEV1) was examined with spirometer. A FEV1/FVC ratio (FEV1%) <0.70 was defined as poor lung function. Information on daily smoking came from interview on tobacco consumption which was grouped as 1–10, 11–20 and 21 g or more of tobacco (1 cigarette = 1 g, 1 pipe = 1 g and 1 cigar = 5 g).
Statistical analyses
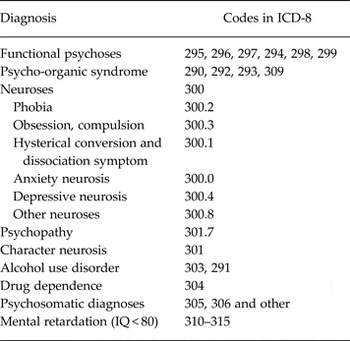
All analyses were conducted in SAS 9.3 (SAS Institute Inc., Cary, NC, USA). We examined associations between each of the ICD-8 diagnoses in Table 1 and mortality by Cox proportional hazard regression models using SURVEYPHREG and report associations as mortality hazard ratios (HRs) with 95% confidence intervals (CI). We computed person-years from time of examination until date of death or 30 September 2011, whichever came first. We controlled for age in five age groups (18–25, 26–35, 36–45, 46–55 and 56–65) and sex. Sample selection bias was assessed by comparing mortality rates between the 1896 participants and the 394 non-participants. All estimates were computed using sample weights. 95% CI are based on standard errors from Taylor linearisation computed on the 36 sample strata (3 subsamples × 3 age groups × 4 screening groups). Mediation by health status was examined for three larger diagnostic groups by including variables associated to the exposure (diagnosis) that was also a significant risk predictor for mortality in the multivariate regression model, and kept if changing the estimate >10%. Proportion explained was computed as [(HRcrude–HRmediator adjusted/HRcrude–1) × 100] and interpreted as % excess risk explained by the mediator (Richiardi et al. Reference Richiardi, Bellocco and Zugna2013). Since information on smoking was available only for those in subsamples 1 and 2, mediation analysis was carried out only in 1135 individuals.
Diagnostic groups and 8th version of the International Classification of Disease (ICD-8) codes

Results
Mental disorder
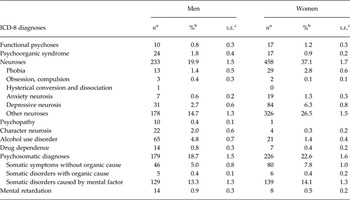
Of the 1896 individuals, a total of 1063 (47% weighted prevalence) had at least one psychiatric diagnosis. Not counting the psychosomatic diagnoses, weighted prevalence was 34%. Prevalence for the different psychiatric disorders is shown in Table 2. The largest subgroup in neurosis is other neurosis, because a specific neurosis was made only when there was a dominating symptom. Women had more neuroses and functional psychoses, other diagnoses were more common among men. There were no affective disorders or sexual deviations, only one individual with obsessive–compulsive disorder and one with hysterical conversions/dissociation symptoms. About 10% (n = 271) had more than one diagnosis. Comorbidity was most commonly found in drug disorder (20 of 21 individuals, mainly with neurosis), psychopathy (10 of 11 individuals, mainly with alcohol use disorder), mental retardation (18 of 22 individuals, mainly with neurosis) and alcohol use disorder (67 of 86 individual, mainly with neurosis).
Prevalence of psychiatric diagnoses at psychiatric examination 1970, men and women

Notes. aUnweighted number of individuals with disorder.
b Weighted prevalence.
c Standard error from Taylor approximation. n = 1896, men: n = 920, 50.2%b, women: n = 976, 49.8%b.
Mortality
The date of completion of follow-up was 30 September 2011. Of the 1896 individuals, 883 died. In total, there were 65 807 person-years of follow-up (weighted mean 34.7 years). Since we had information on mortality not only for the 1896 who participated in the baseline examination but also on the 394 non-participants we compared the mortality risk between the two. There were no significant differences between participants and non-participants, HR = 0.98 (0.81–1.18) for non-participants compared with participants (HRs computed without weights, adjusted for sex and age, n = 2283).
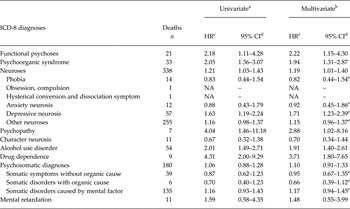
Table 3 shows the associations between the psychiatric diagnosis and mortality, for each diagnosis and taking into account a potential second diagnosis. Except for the HRs for psychopathy and drug use disorder no important difference in HRs was found taking into account second diagnosis. Statistically significant increased mortality was found for: functional psychoses, depressive neuroses, psycho-organic syndrome, psychopathy, alcohol use disorder and drug abuse.
Mortality according to psychiatric diagnosis at examination, with and without considering comorbidity

Notes: aAdjusted for age and sex.
b Adjusted for age and sex and other psychiatric diagnoses.
c Hazard ratio.
d 95% confidence intervals from Taylor approximation.
e Regression estimates excluding higher-order variables neuroses and psychosomatic diagnoses. n = 1896.
Mediation by somatic health status
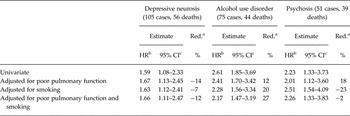
Body composition, hypertension, FBG, pulmonary function and smoking were all found more often in depressive neurosis, alcohol use disorder and psychosis than among those without these disorders (web appendix). Three of these were also statistically significant predictors of mortality: hypertension to non-hypertension HR = 1.37 (1.15–1.63); high to normal glucose HR = 2.90 (1.79–4.71), poor lung function to non-poor HR = 1.38 (1.11–1.73) and; smoking heavily HR = 1.85 (1.38–2.44), moderately HR = 1.63 (1.22–2.17) and light HR = 1.19 (0.88–1.62) to non-smoking. In multivariate analysis only two risk factors, smoking and pulmonary function had a reducing effect on the association between any of diagnoses and mortality. Table 4 shows the mediation of these two variables on the association between psychiatric diagnosis and mortality. There was a tendency in change of the estimates, both positive and negative, but not in a uniform manner and not dramatically. Also, the CI include all estimates.
Mediation by low pulmonary function and smoking on the association between three psychiatric diagnoses and mortality

Notes: All estimates are adjusted for age, sex and the two other disorders in the table. The analysis is based on subsamples 1 and 2 because they had odontological examination/smoking status.
a Reduction, proportion explained. n = 1135, 535 deaths.
b Hazard ratio.
c 95% confidence intervals from Taylor approximation.
Discussion
Summary of the findings
In this study based on 1896 individuals in the general population, we examined the association between clinical ICD-8 psychiatric diagnoses from interview and mortality during up to 41 years of follow-up. Those who were diagnosed with functional psychoses, psycho-organic syndromes, depressive neurosis, psychopathy, alcohol use disorder and drug abuse had significantly increased risks of death that was approximately two to five times increased. We found little evidence of mediation by health status measured at baseline.
Comparison with previous studies
Depression
The mortality HR of 1.7 for depressive neurosis found in our study is very similar to estimates reported in previous studies based on psychiatric interview schedules, despite different conceptualisations and length of follow-up. A 1.7-fold mortality was found for ICD-8 depressive neurosis in the Mini-Finland study (Joukamaa et al. Reference Joukamaa, Heliövaara, Knekt, Aromaa, Raitasalo and Lehtinen2001) as well as for any DSM-IV depressive disorder in the Health 2000 Study (Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012). In the Stirling study, which use their own criteria of depression, mortality HRs also ranged between HR 2.1 and 2.7 (Murphy et al. Reference Murphy, Burke, Monson, Horton, Laird, Lesage, Sobol and Leighton2008), and in the New Haven ECA study DSM-III major depression (which excludes milder depressions included in the above-mentioned studies) had a 1.5–2.9-fold increased mortality (Bruce et al. Reference Bruce, Leaf, Rozal, Florio and Hoff1994). In contrast, in a recent 27-year follow-up of four ECA samples, the authors found no association between depression and mortality, an unexpected finding to which the authors offered two potential explanations; that the instrument (the Diagnostic Interview Schedule (DIS)) was imprecise and lacked predicative ability, or that symptoms of somatic illness was mistaken for depression and that those with depression were not under long-term risk of mortality (Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013).
Anxiety
We found no significant increased risk for mortality associated with anxiety, phobia, character neurosis or other neurosis. This is also in line with results from Mini-Finland (ICD-8 anxiety neuroses, phobic neurosis, obsessive neurosis and other neurosis) (Joukamaa et al. Reference Joukamaa, Heliövaara, Knekt, Aromaa, Raitasalo and Lehtinen2001), ECA samples (DSM-III panic, obsessive–compulsive and phobic disorder) (Bruce et al. Reference Bruce, Leaf, Rozal, Florio and Hoff1994; Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013), the Health 2000 Study (DSM-IV anxiety disorder) (Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012) and Stirling (own criteria anxiety) (Murphy et al. Reference Murphy, Monson, Olivier, Sobol and Leighton1987, Reference Murphy, Monson, Olivier, Sobol, Pratt and Leighton1989). A small but increased mortality (RR = 1.3) has been reported for phobic disorder in the Baltimore ECA (DSM-III) (Badawi et al. Reference Badawi, Eaton, Myllulouma, Weimer and Gallo1999), and also in Lundby, where own criteria anxiety and reassessed DSM-III-R panic disorder associations with mortality is reported (Grasbeck et al. Reference Grasbeck, Rorsman, Hagnell and Isberg1996). Further, anxiety is commonly associated with mortality in patient-based materials (Harris & Barraclough, Reference Harris and Barraclough1998) which include those severely ill, and in random samples with self-report measures, which are considered more fallible.
Psychosis
Those with functional psychoses (schizophrenia, other psychosis and paranoid conditions) had in our study a 2.3 times higher mortality. This is similar to associations in the New Haven ECA for schizophrenia and schizophreniform disorders (HR = 2.5) (Bruce et al. Reference Bruce, Leaf, Rozal, Florio and Hoff1994) and for schizophrenia and other non-affective psychosis in the Health 2000 Study (HR = 3.0 and 1.8) (Suvisaari et al. Reference Suvisaari, Partti, Perälä, Viertiö, Saarni, Lönnqvist, Saarni and Härkänen2013), where cases were identified using structured interview schedules (DIS and its successor the Composite International Diagnostic Interview), which have been criticised for low reliability for psychosis (Anthony et al. Reference Anthony, Folstein, Romanowski, Korff, Nestadt, Charal, Merchant, Brown, Shapiro, Kramer and Gruenberg1985; Wittchen, Reference Wittchen1994). Since those with psychosis or residual psychosis typically misunderstand questions, but also because non-psychotic individuals sometimes report odd but not psychotic experiences, clinical judgements is believed to be needed in order to make a valid diagnosis (Anthony et al. Reference Anthony, Folstein, Romanowski, Korff, Nestadt, Charal, Merchant, Brown, Shapiro, Kramer and Gruenberg1985; Wittchen, Reference Wittchen1994) and, e.g. the recent 27-year mortality follow-up of four of the ECA samples did not include psychoses (Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013). The Mini-Finland study did report mortality rates for functional psychosis, but they relied on patient registers and not the structural interview (Present State Examination) used for ascertaining other mental disorders. However, the mortality estimates found in that study were also comparable with ours (male HR = 2.7 and female HR = 1.6). Given the severity of psychosis, patient registers most likely have good coverage of and representation for this group. Also those with psycho-organic syndrome had high mortality risk, HR = 1.9, which is similar to risks in Lundby, where ‘organic brain disorder’ was strongly associated with mortality in the 25 year follow-up, RR = 3.4 (Rorsman et al. Reference Rorsman, Hagnell and Lanke1982).
Substance use disorder
Alcohol use disorder and drug abuse were also found to associate with mortality. Our HR of 1.9 for those with alcohol use disorder is similar to those found for alcohol use disorders in Lundby (HR = 1.5) (Mattisson et al. Reference Mattisson, Bogren, Öjehagen, Nordström and Horstmann2011), New Haven and Baltimore ECA samples (both RR = 1.8) (Bruce et al. Reference Bruce, Leaf, Rozal, Florio and Hoff1994; Badawi et al. Reference Badawi, Eaton, Myllulouma, Weimer and Gallo1999) and the Health 2000 Study (HR = 2.6) (Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012). Lower risk was reported in the recent 27-year follow-up of four ECA samples HR = 1.33 (1.21–1.47) (Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013). For drug abuse, which only ECA samples has provided population-based mortality risks, HR of mortality was 3.7 in our study. This is in line with ECA estimates which range between HR 11.0 and HR 1.44 depending on the length of the follow-up (Kouzis et al. Reference Kouzis, Eaton and Leaf1995; Badawi et al. Reference Badawi, Eaton, Myllulouma, Weimer and Gallo1999; Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013).
Personality disorder
We also found an increased risk of mortality for psychopathy, HR = 2.9, which was statistically significant despite a small number of individuals. The ECA is the only general population sample in which mortality is examined for any personality disorder – antisocial personality disorder, which overlaps with psychopathy (Eaton et al. Reference Eaton, Kalaydjian, Scharfstein, Mezuk and Ding2007). The longer follow-ups of these , 23 and 27 years, show mortality risks for this group similar to those in our study, HR = 2.8 (Eaton et al. Reference Eaton, Kalaydjian, Scharfstein, Mezuk and Ding2007) and HR = 2.0 (Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013), respectively.
Mediation by somatic health
As it has been suggested that poor somatic health among those with mental disorders contribute substantially to their increased mortality risks, we assessed mediation by five well-known risk factors, body composition, pulmonary function, hypertension, FBGs and smoking. We found indication of some mediation by smoking and low pulmonary function for those with alcohol use disorder but not depression or psychosis (except for pulmonary function). In three previous population-based studies, two based on mental disorders in the Health 2000 Study (Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012; Suvisaari et al. Reference Suvisaari, Partti, Perälä, Viertiö, Saarni, Lönnqvist, Saarni and Härkänen2013) and one on the psychiatric symptoms score index in the British 1946 birth cohort, assessments have been made as to whether physical health and health behaviours moderated the association between mental disorder and mortality. In those studies, similarly to our, there was indication of confounding by smoking (Henderson et al. Reference Henderson, Hothopf, Shah, Hayes and Kuh2011; Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012) and pulmonary disease (Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012), but not by obesity (Markkula et al. Reference Markkula, Harkanen, Perala, Patti, Pena, Koskinen, Lönnqvist, Suvisaari and Saarni2012; Suvisaari et al. Reference Suvisaari, Partti, Perälä, Viertiö, Saarni, Lönnqvist, Saarni and Härkänen2013), glucose level (Suvisaari et al. Reference Suvisaari, Partti, Perälä, Viertiö, Saarni, Lönnqvist, Saarni and Härkänen2013) or hypertension (Suvisaari et al. Reference Suvisaari, Partti, Perälä, Viertiö, Saarni, Lönnqvist, Saarni and Härkänen2013). Similarly to all these studies most of the association between mental disorder and mortality remained unexplained. Body composition and hypertension, which together with smoking and diabetes are the most important risk for cardiovascular disease (Greenland et al. Reference Greenland, Knoll, Stamler, Neaton, Dyer, Garside and Wilson2003), were after controlling for age, not statistically associated with mortality, and therefore not examined as mediators. The relatively small sample and a long follow-up might be one explanation to this lack of association, and since there was a tendency of for instance obesity among those with psychosis and hypertension among those with alcohol use disorder, we do not rule that they have a role in elevating the overall mortality rates for those with mental disorder.
Methodological considerations
The main strength of our data is the combination of a random sample and diagnosis from semi-structured interview by psychiatrists. Few studies have interview data, and while highly structured interviews are a practical necessity, interview by a psychiatrist remain criterion standard. Comparisons of clinical interviews and structured instruments in ECA subsamples (DIS) (Anthony et al. Reference Anthony, Folstein, Romanowski, Korff, Nestadt, Charal, Merchant, Brown, Shapiro, Kramer and Gruenberg1985; Helzer et al. Reference Helzer, Robins and Mcevoy1985; Eaton et al. Reference Eaton, Neufeld, Chen and Cai2000) and the Mini-Finland study (PSE) (Lehtinen et al. Reference Lehtinen, Joukamaa, Lahtela, Raitasalo, Jyrkinen, Maatela and Aromaa1990) have shown poor concordance for some diagnoses. A second strength of the REBUS study is the high participation rate. A low participation among those with mental disorder may bias estimates in an unknown direction (Lundberg et al. Reference Lundberg, Damström Thakker, Hällström and Forsell2005 ). A third strength is the highly reliable data on death, which we had information on for both participants and non-participants. Swedish population registration information has very good quality, with small under- and over-coverage (UNSTATS), whereas in some previous studies, e.g. the ECA samples, matching vital status is less than perfect for a large proportion (Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013).
A weakness of our study is that it was conducted before DSM-III, Research Diagnostic Criteria or Feigner's Criteria, and some of the diagnoses are no longer in use or have changed. For example, schizophrenia was diagnosed according to Bleuler's criteria which was more inclusive than Kraepelin's and later criteria (Modestin et al. Reference Modestin, Huber, Satirli, Malti and Hell2003) and psychopathy was based on Vanggaard's criteria which is wider than antisocial personality disorder (Halldin, Reference Halldin1984b ) (although more narrow that Schneider's psychopathy). More narrow definitions would perhaps result in higher risk estimates. The prevalence of disorder in REBUS was high, 47% (34% not counting psychosomatic disorders), which is higher than those reported in younger samples of adults, where prevalence range between 9.7 and 27.0% (Bourdon et al. Reference Bourdon, Rae, Locke, Narrow and Regier1992; Kessler et al. Reference Kessler, McGonagle, Zhao, Nelson, Huges, Eshleman, Wittchen and Kendler1994, Reference Kessler, Aguilar-Gaxiola, Alonso, Chatterji, Lee, Oromel, Üstün and Wang2009). The demarcation of mental disorder is difficult, and in REBUS a symptom-duration of at least a week and at least a minor insufficiency (Halldin, Reference Halldin1984a ) is a low threshold. Even lower thresholds were used in the older Midtown Manhattan Study and the Stirling County Study, where only 17 and 19%, respectively, were regarded as ‘probably well’ (Srole et al. Reference Srole, Langner, Mjchael, Opler and Rennie1962; Leighton et al. Reference Leighton, Harding, Macklin, Mackmillan and Leighton1963). Besides psychosomatic diagnoses and non-specific neurosis, the prevalences are quite low in comparison with population-based samples, e.g. in ECA (Eaton et al. Reference Eaton, Roth, Bruce, Cottler, Wu, Nestadt, Ford, Bienvenu, Crum, Rebok, Anthony and Munoz2013) and Swedish conscript cohorts from the same time-period (Lundin et al. Reference Lundin, Lundberg, Allebeck and Hemmingsson2011), and as we have shown the mortality HRs agree with those in previous population-based studies. Furthermore, although 1896 individuals in a stratified random sample is quite equivalent to sample sizes in, e.g. the ECA samples, some diagnoses are represented by few individuals. More modern epidemiologic samples such as the National Comorbidity Survey and the Health 2000 Study are larger but few mortality studies have been conducted using those. Hence, the relative large size of REBUS combined with the very long follow-up makes a substantial contribution to the knowledge about long-term effects of disorders. Relatedly, in this study we could only examine all-cause mortality, and cause-specific mortality would undoubtedly provide more specific knowledge on the mechanisms to the increased mortality for specific diagnoses. Lastly, another weakness is that we rely on a single interview, based partly on retrospective information. As always, failure to recall might give misleading estimates. We do not think that our study differs essentially from other studies in this respect.
Implications
Mental disorders are common, long-term and recurrent conditions which are likely to shorten your life, through death from unnatural as well as natural causes. However, the all-cause mortality risk, a central basic measure in the descriptive epidemiology of disease, is not well described in population-based research. This study showed, in a very long follow-up, that mortality was increased for several diagnostic groups, but little of this was explained by known and preventable risk factors. Few population-based epidemiologic studies have clinical somatic information and such would contribute to explain the increased mortality for those with mental disorder, and help guide clinicians and public health workers in their preventive work. In order to provide information for public health action future research should continue to track mortality and morbidity for those with mental disorder, encompassing also diagnosis-specific morbidity and mortality.
Acknowledgements
The authors appreciate the helpful contributions of Centre for epidemiology and community medicine, Stockholm county council.
Financial Support
This research received no specific grant from any funding agency, commercial or not-for-profit sectors.
Statement of interest
None.
Ethical Standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008.
Supplementary materials and methods
The supplementary material for this article can be found at http://dx.doi.org/10.1017/S2045796015000487