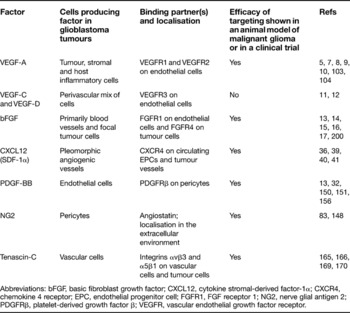
Glioblastoma tumours are the most malignant brain tumours: their aggressive nature results in a median survival of 12–15 months (Ref. Reference Nabors and Fiveash1). Notably, they also are one of the most angiogenic of the known solid malignant tumours (Ref. Reference Kleihues2). Angiogenesis, the induction and creation of a neovasculature, allows tumours to overcome the limitations in nutrient and oxygen delivery that develop when the tumour reaches a size of ∼1–2 mm in diameter (Refs Reference Hanahan and Folkman3, Reference Folkman4). The new vessel growth occurs as an expansion of the existing vasculature in response to the secretion of proangiogenic growth factors by the tumour cells, stromal cells and/or inflammatory cells. Multiple proangiogenic factors have been identified. Vascular endothelial growth factor-A (VEGF-A) is perhaps the best known of these and plays a key role in angiogenesis. VEGF-A is upregulated in glioblastoma tumours in which it is produced by tumour cells, as well as by stromal and inflammatory cells (see Table 1) (Ref. Reference Goldman5 and reviewed in Ref. Reference Hanahan and Folkman3). Once secreted by the tumour, stromal or inflammatory cells, VEGF-A can be sequestered or tethered in the extracellular matrix through interactions with proteoglycans or glycosaminoglycans (Refs Reference Whitelock, Murdoch, Iozzo and Underwood6, Reference Klagsbrun and D'Amore7). The expression of receptors for VEGF-A (VEGFR1 and VEGFR2) is upregulated on endothelial cells in glioblastoma tumours, compared with their expression on the endothelial cells in normal brain (Refs Reference Klagsbrun and D'Amore7, Reference Kukk8, Reference Stratmann, Machein and Plate9, Reference Witmer10). VEGFR3 expression was previously thought to be specific for lymphatic endothelial cells, and VEGFR3 is not expressed in the normal brain; however, VEGFR3 has now been shown to be expressed in glioblastoma tumours and has been localised to the endothelial cells despite the absence of a lymphatic system in the brain (Refs Reference Grau11, Reference Witmer12). Furthermore, the ligands for VEGFR3 (VEGF-C and VEGF-D) are expressed by multiple cell types that surround the angiogenic vessels in glioblastoma tumours (see Table 1) (Ref. Reference Grau11), suggesting that a novel proangiogenic paracrine-signalling pathway exists in these tumours. Similar observations regarding VEGFR3 expression have been made in other tumours (Ref. Reference Witmer12).
Proangiogenic molecules expressed in glioblastoma tumours: binding partner(s) and localisation

Abbreviations: bFGF, basic fibroblast growth factor; CXCL12, cytokine stromal-derived factor-1α; CXCR4, chemokine 4 receptor; EPC, endothelial progenitor cell; FGFR1, FGF receptor 1; NG2, nerve glial antigen 2; PDGFRβ, platelet-derived growth factor β; VEGFR, vascular endothelial growth factor receptor.
Another proangiogenic growth factor that is upregulated in glioblastoma tumours is basic fibroblast growth factor (bFGF). In glioblastoma tumours, bFGF is expressed by vascular cells and focally by the tumour cells (see Table 1) (Ref. Reference Karcher13). Furthermore, a neutralising antibody directed toward bFGF inhibited tumour growth in a subcutaneous xenograft model of glioblastoma tumour propagated in the nude mouse (Ref. Reference Morrison14). The receptors for bFGF include FGFR1, FGFR2 and FGFR4. FGFR1 is upregulated in glioblastoma tumours in which it is expressed both by the tumour cells and the tumour endothelial cells, FGFR4 is expressed only by the tumour cells and FGFR2 is not detected in glioblastoma tumours, although it is expressed in the normal brain (Refs Reference Morrison14, Reference Morrison15, Reference Ueba16, Reference Yamada17). Similarly to VEGF, bFGF can be tethered in the matrix via an association with proteoglycans or glycosaminoglycans. The glypican family of proteoglycans, which are expressed on the endothelial cells, serve as co-receptors for bFGF (Ref. Reference Qiao18).
The binding of VEGF or bFGF activates the existing endothelial cells. Binding of VEGF to its receptors on the endothelial cell typically results in signalling through the phosphatidylinositol 3-kinase (PI3K)/protein kinase B (Akt) pathway, whereas the bFGF receptors signal predominantly through the protein kinase Cα (PKCα) pathway (Refs Reference Pintucci19, Reference Simons20). In addition, both VEGF and bFGF stimulation can initiate signalling through the extracellular signal-regulated kinase (Erk) pathway (Refs Reference Pintucci19-Reference Gliki, Wheeler-Jones and Zachary21). The activation of the endothelial cells results in upregulation or increased expression of certain cell adhesion receptors, such as integrins αvβ3 and α5β1, respectively, and the activated endothelial cells exhibit increased cell survival, proliferation and migration responses (Refs Reference Kim22, Reference Brooks, Clark and Cheresh23, Reference Gladson24). In addition to VEGF and bFGF, other proangiogenic growth factors may also act to initiate or amplify angiogenesis in glioblastoma tumours. For example, interleukin-8 (IL-8), which is released from macrophages during a host inflammatory response, activates endothelial cells through the chemokine-1 and chemokine-2 receptors CXCR1 and CXCR2, which are expressed on endothelial cells (see Table 1) (Ref. Reference Brat, Bellail and Van Meir25). Other examples that are not discussed further in this review include hepatocyte growth factor, granulocyte-macrophage-colony-stimulating factor, granulocyte-colony-stimulating factor and urokinase (Refs Reference Karcher13, Reference Gondi26, Reference Lakka, Gondi and Rao27). In addition, microenvironmental signals can act to amplify the signals provided by the proangiogenic factors. Notably, rapid tumour growth that exceeds the oxygen supply causes a decrease in intracellular pH, leading to hypoxia-driven expression of proangiogenic growth factors, including VEGF, by both tumour cells and the host inflammatory cells (Refs Reference Kaur28, Reference Liu and Simon29).
For endothelial cells to form a neovasculature, the basement membrane that forms a ‘cage’ around the existing vasculature must be degraded (Ref. Reference Overall and Kleifeld30). The proteolytic degradation of the basement membrane is mediated by proteases, such as the matrix metalloproteinases (MMPs), that are secreted by tumour and stromal cells (Ref. Reference Overall and Kleifeld30). This exposes the endothelial cells to matrix proteins that promote pro- or antiangiogenic activity, to fragments derived from the proteolytic breakdown of matrix molecules, and to the matrix-tethered growth factors (such as tethered VEGF and bFGF) (Refs Reference Whitelock, Murdoch, Iozzo and Underwood6, Reference Belotti31). Integrins expressed on the endothelial cells play a critical role in directing the migration of the endothelial cells into the degraded basement membrane (Ref. Reference Brooks, Clark and Cheresh23). Thus, the degradation of the basement membrane creates pathways that both enable and stimulate the migration of endothelial cells from the existing vasculature, which results in the typical ‘sprouting’ of the neovasculature from the existing vasculature.
Concurrently, vascular-associated cells, including smooth muscle cells and pericytes, are recruited to the neovasculature through platelet-derived growth factor (PDGF) signalling (Ref. Reference Bergers and Song32). Endothelial cells synthesise PDGF and this enables the recruitment of pericytes to the neovessels as they express the PDGF receptor β (PDGFRβ). PDGF also acts as a proangiogenic growth factor (see Table 1) (Ref. Reference Karcher13). These vascular-associated cells serve to stabilise the neoendothelium (Ref. Reference Bergers and Song32). In normal angiogenesis, pericytes accomplish this through the angiopoietin–TIE2 (angiopoietin-1 receptor) signalling axis, but this is altered in glioblastoma tumours (see below). Pericytes also can stabilise the neoendothelium through their deposition of matrix proteins that help to form the new basement membrane (Refs Reference Metheny-Barlow and Li33, Reference Baluk34). The new basement membrane can influence endothelial cell behaviour both directly, through the engagement of specific integrin receptors, and indirectly through the modulation of growth factor signalling. For example, integrin αvβ5 can cooperate with VEGFR2 and integrin αvβ3 can cooperate with FGFR in promoting endothelial cell survival, proliferation and migration (Ref. Reference Hood35). Integrin αvβ3 expression is upregulated on the endothelial cells in glioblastoma tumours (Ref. Reference Gladson24). Bone-marrow-derived progenitor cells, such as endothelial progenitor cells (EPCs), may also assist in vascular remodelling and are mobilised from the bone marrow by the cytokine stromal-derived factor-1α (SDF-1α), also known as CXCL12 (see Table 1) (Refs Reference Ceradini36, Reference Annabi37, Reference Aghi38). CXCL12 is expressed by the pleomorphic angiogenic vessels in glioblastoma tumours and binds to the G-protein-coupled chemokine 4 receptor (CXCR4) expressed on circulating EPCs and on tumour vessels (Refs Reference Ceradini36, Reference Salvucci39, Reference Rempel40). Furthermore, targeting of this pathway with a CXCR4 antagonist in an orthotopic xenograft model of glioblastoma tumour propagated in the nude mouse resulted in an inhibition of tumour growth (Ref. Reference Rubin41).
Unlike the blood vessels in normal tissue, the neovasculature in glioblastoma tumours never fully develops into mature vessels, due in part, to an imbalance of pro- and antiangiogenic growth factors in the tumour. This leads to an atypical and constantly remodelling tumour vasculature.
Angiogenesis in glioblastoma tumours is characterised by a neovasculature that has a glomeruloid-like histology and exhibits an erratic basement membrane, reduced pericyte coverage, decreased astrocytic endfoot association with blood vessels and altered expression of endothelial cell adhesion molecules (Refs Reference Kleihues2, Reference Gladson24, Reference Baluk34, Reference Vitolo42, Reference Lossinsky43). These abnormalities result in excessive leakiness of the neovasculature. Typically, there is an increase in microvessel density and in the number of dilated large tortuous vessels in glioblastoma tumour biopsies.
This excessive leakiness is of particular importance in the expansion and spread of glioblastoma tumours throughout the normal brain and in the treatment of these tumours. The abnormal neovasculature associated with the tumours lacks a normal blood–brain barrier (BBB). This is thought to lead to a decrease in the osmotic gradient between the vasculature and interstitium, and to an elevation of the interstitial fluid pressure in the tumour (Ref. Reference Boucher, Leunig and Jain44). The elevated interstitial fluid pressure, together with the frequent reversions and stalling of the blood flow in the contorted neovasculature, can compromise drug delivery to the glioblastoma tumours (see below). The abnormal vasculature may also result in enhanced tumour cell access to the vasculature, which probably enables tumour cell migration and invasion throughout the previously uninvolved brain tissue. This may be of considerable importance, as it may contribute to the aggressive behaviour of the glioblastoma tumour by overcoming the limitation on tumour invasion and local migration in the brain that is imposed by the absence of a lymphatic system. The lack of a lymphatic system has been purported to be one reason for the lack of identified extracranial metastases in the vast majority of glioblastoma tumours. Finally, the leaky tumour vasculature amplifies the effects of the tumour mass on the generation of an increased interstitial pressure, measured as increased intracranial pressure. In the enclosed cranium, this has very negative effects on uninvolved brain tissue. Again, this effect is exacerbated by the lack of a lymphatic system, which limits the ability of the brain to relieve the pressure.
Glioblastoma tumours frequently exhibit extensive necrotic cores. This exacerbates hypoxia, which can promote tumour angiogenesis by enhancing the production of proangiogenic factors. Hypoxia destabilises the von Hippel Landau (VHL) molecule, and the VHL molecule inhibits the function of hypoxia-inducible factor-1α (HIF-1α) by targeting it for proteasome degradation; HIF-1α is a transcription factor promoting the transcription of several proangiogenic growth factors (Ref. Reference Kaur28). Hypoxia-driven VHL molecule dissociation from HIF-1α causes HIF-1α to bind the promoter of the hypoxia-response element (HRE) in several proangiogenic factors, including VEGF and CXCL12, resulting in their transcription (Refs Reference Kaur28, Reference Ceradini36).
Opposing angiogenic factors in glioblastoma tumours
Thrombospondin-1 and Thrombospondin-2
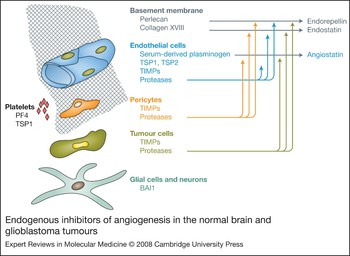
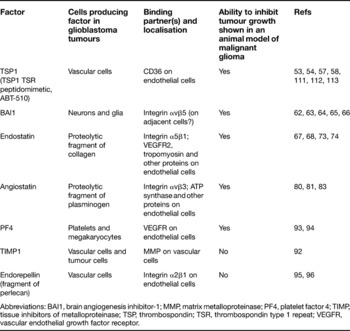
In normal tissues, the balance of pro- and antiangiogenic factors is in equilibrium. In glioblastoma tumours, the balance of pro- and antiangiogenic growth factors is skewed to favour proangiogenic factors, which favours neovascularisation. Several antiangiogenic factors have been described. Thrombospondin-1 (TSP1) is an extracellular antiangiogenic factor that is synthesised and secreted by multiple normal cells and tissues, such as platelets, endothelial cells, and smooth muscle cells (see Fig. 1 and Table 2) (reviewed by Refs Reference Adams and Lawler45, Reference Lawler46). The antiangiogenic effects of TSP1 treatment have been studied extensively in dermal microvessel endothelial cells propagated in vitro; TSP1 inhibits the migration and proliferation of these cells, and also induces apoptosis (Refs Reference Jimenez47, Reference Volpert48, Reference Nor49). The most potent antiangiogenic effects of TSP1 are induced through the binding of TSP1 to CD36, which is expressed on the surface of microvessel endothelial cells. This interaction is mediated by the type 1 repeat domain (TSR) of TSP1 and the CLESH1 domain of CD36 (Ref. Reference Simantov and Silverstein50). Other proteins can modify the TSP1 response by cooperating with or modulating CD36 function; for example, integrin αvβ3 modulates CD36 function in macrophages (Ref. Reference Bottcher51). In addition, TSP1 also can promote an antiangiogenic effect that is mediated through other domains of TSP1, or is caspase independent (Refs Reference Adams and Lawler45, Reference Elzie and Murphy-Ullrich52, Reference Armstrong53). Peptides derived from the TSP1 TSRs have been administered to mice bearing malignant glioma tumours and have been shown to inhibit tumour angiogenesis and tumour growth, as discussed in more detail later in this review (Ref. Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54). TSP1 has been shown to act downstream of the tumour suppressor p53 in cells propagated in vitro (Refs Reference Tenan55, Reference Harada56). Loss of p53 function is found in some glioblastoma tumours, yet TSP1 levels are increased in the tumour vasculature, probably because of a host stromal antitumour and antiangiogenesis response (See Table 2 and Fig. 1) (Refs Reference Pijuan-Thompson57, Reference Kawataki58).
Endogenous inhibitors of angiogenesis in the normal brain and glioblastoma tumours. The cell of origin or cellular localisation. Angiostatin, endorepellin and endostatin are proteolytic cleavage products. Various cell types produce proteases but the relative contribution of each of these cellular sources of proteases to the generation of these cleavage products has not yet been defined. Abbreviations: BAI1, brain angiogenesis inhibitor-1; PF4, platelet factor 4; TIMP, tissue inhibitors of metalloproteinase; TSP, thrombospondin.

Antiangiogenic molecules expressed in glioblastoma tumours: binding partner(s) and localisation

Abbreviations: BAI1, brain angiogenesis inhibitor-1; MMP, matrix metalloproteinase; PF4, platelet factor 4; TIMP, tissue inhibitors of metalloproteinase; TSP, thrombospondin; TSR, thrombospondin type 1 repeat; VEGFR, vascular endothelial growth factor receptor.
TSP2 is highly homologous to TSP1 and also exhibits antiangiogenic properties that are due in part to the TSRs (Refs Reference Adams and Lawler45, Reference Simantov and Silverstein50, Reference Streit59). TSP2 is expressed by endothelial cells and other cells in the normal mouse brain (Ref. Reference Fears60), and its expression is downregulated in glioblastoma tumours compared with levels in the normal brain (see Fig. 1) (Ref. Reference Kazuno61). Furthermore, mouse malignant glioma tumours propagated orthotopically in the TSP2-null mouse showed an increased tumour size and an increased microvessel density compared with tumours propagated in the wild-type mouse (Ref. Reference Fears60), supporting a host antitumour and antiangiogenesis role for TSP2 in the brain.
Brain angiogenesis inhibitor-1
Brain angiogenesis inhibitor-1 (BAI1) is a brain-specific antiangiogenic molecule (see Table 2 and Fig. 1) (Ref. Reference Nishimori62). It is a cell membrane protein that can be cleaved, releasing the extracellular domain, which contains five TSRs and is known as vasculostatin (Refs Reference Nishimori62, Reference Kaur63). In certain experimental conditions, BAI1 may be a p53 target gene (Refs Reference Nishimori62, Reference Kaur64). However, BAI1 expression in glioblastoma tumours is independent of p53 (Ref. Reference Kaur64). BAI1 is expressed differentially in normal brain and glioblastoma tumours. In the normal brain, there is a high expression of BAI1 in normal glia and neurons but no expression in blood vessels. In glioblastoma tumours, BAI1 expression is decreased, probably because of the loss of neurons and normal glia (Ref. Reference Kaur64). Despite the TSR domains, BAI1 functions independently of CD36 expressed on the endothelial cells and it appears to inhibit cell survival through an interaction of the TSRs with integrin αvβ5 (Ref. Reference Koh65). Expression of either full-length BAI1, or the extracellular domain of BAI1, in human glioma cells that were propagated in nude mice resulted in a significant inhibition of tumour growth and tumour angiogenesis compared with similarly propagated control glioma cells (Refs Reference Kaur63, Reference Kang66). This suggests that BAI1 has an antiangiogenic effect in vivo, and that the TSRs of BAI1 are probably necessary for this antiangiogenic effect.
Endostatin and tumstatin
Antiangiogenic molecules, including endostatin, can be produced during the proteolytic cleavage of the basement membrane in glioblastoma tumours (see Table 2 and Fig. 1) (Refs Reference Strik67, Reference Morimoto68). Endostatin is a C-terminal cleavage product of collagen type XVIII by elastase, cathepsin-L and an MMP (Refs Reference Folkman69, Reference Heljasvaara70). Endostatin appears to be capable of interacting with several different receptors or binding partners on the endothelial cells and to inhibit angiogenesis through multiple mechanisms, including: blockade of VEGFR2; binding to integrin α5β1; blockade of focal adhesion kinase (FAK)-mediated endothelial cell migration and survival; binding to tropomyosin; and altered regulation of multiple other targets (such as through the nucleolin receptor) (Refs Reference Folkman69, Reference Shi71, Reference Sudhakar72). Endostatin also can reduce expression of anti-apoptotic Bcl2 family members (Ref. Reference Folkman69). In addition, endostatin binds the proangiogenic protease MMP2 and blocks its activation and catalytic activity (Ref. Reference Folkman69). Endostatin is expressed in glioblastoma tumours (Refs Reference Strik67, Reference Morimoto68), and a higher level of endostatin expression was found in glioblastoma tumours than in lower grade glioma tumour biopsies upon examination by immunoblotting and immunohistochemistry (Ref. Reference Morimoto68). This suggests that endostatin expression is part of a host antitumour response. Several studies have shown that endostatin inhibits malignant glioma growth in rodent models, for example, when recombinant endostatin is delivered to tumours propagated in an ectopic or an orthotopic manner, or when the endostatin gene is delivered to orthotopic tumours (Refs Reference Barnett73, Reference Sorensen74).
Another antiangiogenic molecule derived from the proteolytic cleavage of the basement membrane is tumstatin. Tumstatin is generated by the cleavage of collagen type IV by MMPs, and is thought to inhibit neovessel formation through an interaction with integrin αvβ3 resulting in blockade of FAK, and the PI3K signalling pathway (Refs Reference Sudhakar72, Reference Maeshima75, Reference Maeshima, Colorado and Kalluri76, Reference Mundel and Kalluri77).
Angiostatin
One of the best known of the endogenous antiangiogenic proteins is angiostatin (see Table 2 and Fig. 1). Angiostatin is made up of the first four kringle domains (K1–K4) of plasminogen (Ref. Reference O'Reilly78). Plasminogen is primarily synthesised and secreted by the liver and is present at high concentrations in the plasma; it can be proteolytically digested by proteases, such as cathepsin D and MMPs, to generate angiostatin (Ref. Reference Wahl79). The antiangiogenic activity of angiostatin was first demonstrated in mice bearing subcutaneous Lewis lung carcinoma tumours (Ref. Reference O'Reilly78). A number of studies have now shown that angiostatin inhibits malignant glioma growth in rodent models, for example, when angiostatin is administered to ectopic or orthotopic tumours propagated in immunodeficient mice (Refs Reference Kirsch80, Reference Joe81). Angiostatin appears to mediate its antiangiogenic effects through binding to several different receptors or binding partners on the endothelial cell, including binding to integrin αvβ3, and ATP synthase (Refs Reference Wahl79, Reference Tarui, Miles and Takada82, Reference Chekenya83). Angiostatin has also been shown to upregulate proapoptotic proteins in activated or proliferating endothelial cells (Ref. Reference Wahl79).
The fifth kringle domain (K5) of plasminogen has also been reported to have antiangiogenic activity (Ref. Reference Cao84); however, generation of K5 in vivo through the proteolytic cleavage of plasminogen has not been reported. K5 has been shown to promote several antiangiogenic effects, such as cell-cycle arrest, inhibition of migration and induction of apoptosis, in non-brain endothelial cells propagated in vitro (Refs Reference Cao84, Reference Davidson85, Reference Lu86, Reference Zhang87). The antiangiogenic effects of K5 appear to require binding to cell-surface glucose-regulated protein 78 (GRP78), a heat shock protein family member (Ref. Reference Davidson85). When glioma cells stably expressing K5 are propagated in nude mice the tumours are smaller and demonstrate a reduced angiogenic response (Ref. Reference Perri88).
Angiopoietins
The angiopoietins can exhibit pro- or antiangiogenic activities and have diverse roles in the brain and in the neovasculature of glioblastoma tumours. In normal blood vessels angiopoietin-1 is expressed primarily by pericytes and binds the TIE2 receptor expressed on endothelial cells, leading to an increased association of pericytes with endothelial cells, and to a less leaky, normalised vasculature (Refs Reference Bergers and Song32, Reference Eklund and Olsen89). If this occurred in glioblastoma tumours it could be of importance therapeutically because normalisation of the vasculature may improve antitumour drug delivery and radiation effectiveness. However, in glioblastoma tumours, there is increased expression of both angiopoietin-1 and -2, and angiopoietin-2 is expressed by endothelial cells, whereas angiopoietin-1 is expressed by the tumour cells and is not expressed at the blood vessels (Ref. Reference Zagzag90). Angiopoietin-2 is thought to serve as a TIE2-receptor antagonist (Refs Reference Metheny-Barlow and Li33, Reference Zagzag90, Reference Stratmann, Risau and Plate91). These observations have led investigators to hypothesise that angiopoietin-2 may have a proangiogenic function in the presence of VEGF, such as in angiogenic vessels in which VEGF and angiopoietin-2 are both expressed.
Other antiangiogenic proteins expressed in the brain or glioblastoma tumours, which are not discussed here, include tissue inhibitors of matrix metalloproteinases (TIMPs), such as TIMP1 (Ref. Reference Groft92), platelet factor 4 (Refs Reference Tanaka93, Reference Bikfalvi94); endorepellin, a fragment of perlecan (Refs Reference Mongiat95, Reference Bix96); PEX, a fragment of MMP2 (Ref. Reference Brooks97); and pigment-epithelium-derived factor (Refs Reference Guan98, Reference Zhang99) (see Table 2 and Fig. 1).
Targets for antiangiogenic therapy
Endothelial cells
VEGF/VEGFR
Endothelial cells offer the most logical target for antiangiogenic therapy owing to their relative genetic stability compared with tumour cells, and their direct contact with blood, which could facilitate drug delivery. VEGF-A and the VEGFR2 receptor are the targets of multiple new antiangiogenic drugs, including antibodies directed toward VEGF-A, the targeting of active VEGFR2 with blocking antibodies or small-molecule tyrosine kinase inhibitors, and chimaeric VEGFR2-like molecules or Traps (see Fig. 2 and Table 3) (Refs Reference Willett100, Reference Jain101, Reference Jain102). Antiangiogenic drugs targeting this pathway in a mouse model of glioblastoma tumour and in patients with recurrent glioblastoma tumour decrease the diameter of enlarged tumour vessels and the overall blood vessel size, decrease the thickness of the basement membrane and increase pericyte coverage, resulting in decreased tumour oedema (Refs Reference Jain101, Reference Jain102, Reference Batchelor103, Reference Winkler104). These data suggest that inhibition of the VEGF/VEGFR pathway has a more pronounced effect on the large or dilated vessels in glioblastoma tumours. As inhibition of the VEGF/VEGFR signalling axis in glioblastoma tumours has been reviewed recently (Ref. Reference Jain102), we will not discuss this approach further here. Therapeutic inhibition of VEGFR2 also may be achieved, in part, through the administration of endostatin, which interferes with VEGFR2 signalling (reviewed in Ref. Reference Folkman69). The FGFR1 receptor and IL-8 receptors (CXCR1 and CXCR2) offer similar opportunities for therapeutic targeting, although the specificity of such targeting to angiogenic endothelial cells in glioblastoma tumours has yet to be thoroughly explored (Refs Reference Morrison14, Reference Brat, Bellail and Van Meir25, Reference Stefanik105).
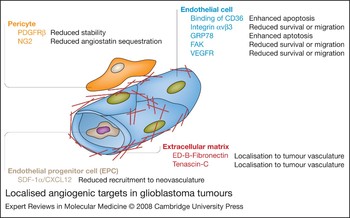
Localised angiogenic targets in glioblastoma tumours. A schematic of the new targets of antiangiogenic therapy, as discussed in the text, in the neovasculature of glioblastoma tumours. Abbreviations: FAK, focal adhesion kinase; GRP78, glucose-regulated protein 78 kDa; NG2, nerve glial antigen 2; PDGFRβ, platelet-derived growth factor β; SDF-1α/CXCL12, cylokine stromal-derived factor-1α; VEGFR, vascular endothelial growth factor receptor.

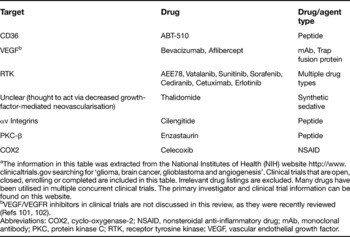
Clinical trials with antiangiogenic agents targeting malignant gliomasa

aThe information in this table was extracted from the National Institutes of Health (NIH) website http://www.clinicaltrials.gov searching for ‘glioma, brain cancer, glioblastoma and angiogenesis’. Clinical trials that are open, closed, enrolling or completed are included in this table. Irrelevant drug listings are excluded. Many drugs have been utilised in multiple concurrent clinical trials. The primary investigator and clinical trial information can be found on this website.
bVEGF/VEGFR inhibitors in clinical trials are not discussed in this review, as they were recently reviewed (Refs 101, 102).
Abbreviations: COX2, cyclo-oxygenase-2; NSAID, nonsteroidal anti-inflammatory drug; mAb, monoclonal antibody; PKC, protein kinase C; RTK, receptor tyrosine kinase; VEGF, vascular endothelial growth factor.
Binding or activating CD36 using TSR peptides derived from TSP1
Binding or activating CD36 is another possible therapeutic target on angiogenic endothelial cells (see Fig. 2 and Table 3) (Ref. Reference Simantov and Silverstein50). TSP1 binds CD36, resulting in potent antiangiogenic effects on microvessel endothelial cells. Full-length TSP1 is an improbable therapeutic agent owing to its size, complex domain structure and multiple biological activities (Refs Reference Adams and Lawler45, Reference Lawler46); however, peptides derived from the TSRs of TSP1 have proven to be an effective antiangiogenic therapy in several mouse models of malignant tumours (Refs Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54, Reference Reiher106, Reference Haviv107). Peptidomimetics from the TSRs of TSP1, such as ABT-510 (NAcSarGlyValDalloIleThrNvaIleArgProNHE), induce apoptosis of human brain microvascular endothelial cells propagated in vitro, and inhibit bFGF-stimulated tubulomorphogenesis of these cells when propagated in collagen gels (Ref. Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54). CD36 was required for the inhibition of tubulomorphogenesis by ABT-510. Furthermore, ABT-510 inhibits malignant glioma growth in two orthotopic intracerebral mouse models of malignant glioma, and this was shown to be mediated through an induction of apoptosis in the tumour endothelial cells (see Fig. 2) (Ref. Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54). The latter observations were made in a syngeneic mouse model of malignant glioma, in which GL261 mouse malignant glioma cells were propagated in the brains of C57BL/6 mice, and in a xenograft model, in which U-251MG human malignant glioma cells were propagated in the nude mouse brain. The endothelial cell death in tumours observed after ABT-510 administration results in a decreased tumour microvessel density, and thus nutrient deprivation of the tumour. It is important to note that although ABT-510 induces apoptosis of primary human brain endothelial cells propagated in vitro, its effects in vivo appear to be specific for tumour endothelial cells, because we have not detected changes in normal brain endothelial cells (Ref. Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54). CD36 is expressed on the microvessel endothelial cells in the normal brain (Refs Reference Barnwell108, Reference Husemann109, Reference Febbraio, Hajjar and Silverstein110); however, the activation of CD36, the conformation of CD36, the binding partner(s) for CD36 or the conformation of its binding partners may be different in the tumour-associated endothelial cells, thereby promoting the tumour-specific effect of ABT-510. Our results regarding the specificity of ABT-510 are consistent with those reported by other investigators concerning the effects of ABT-510 on bladder and Lewis lung carcinoma tumours propagated in mice. All of these studies indicate that ABT-510 inhibits angiogenesis (measured as microvessel density) and tumour growth, but does not affect endothelial cells in normal tissues (Refs Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54, Reference Reiher106, Reference Haviv107).
The effects of expression of TSR-containing fragments of TSP1 that do not bind CD36 and the expression of intact TSP1 on glioma growth in vivo have also been reported. In one study, a peptide from a different region of the TSR that does not bind CD36 was found to inhibit the growth of C6 and 9L gliomas propagated in rats (Ref. Reference Bogdanov111). In another study, expression of an N-terminal TSP1 construct (containing the two cysteine residues involved in disulphide bridging, the procollagen-homology domain and the three TSRs) in rat C6 glioma cells resulted in an increase in the growth of the tumours when the cells were propagated in nude mice (Ref. Reference de Fraipont112), suggesting that the procollagen-homology domain may have unexpected protumour effects. Finally, in support of our study (Ref. Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54), investigators propagated human LN-229 malignant glioma cells overexpressing intact TSP1 subcutaneously in nude mice and found a significant reduction in tumour size and vascular density (Ref. Reference Kragh113).
Combining ABT-510 with valproic acid or with metronomic doxorubicin treatment has been shown to increase the effectiveness of ABT-510 therapy, and results in an enhanced antitumour effect on neuroblastoma cells as well as on other carcinoma cells (Lewis lung, bladder, and prostate) propagated in mouse models (Refs Reference Yang114, Reference Quesada115). The mechanism by which valproic acid, a histone deacetylase inhibitor, enhanced the antiangiogenic and antitumour effect of ABT-510 was not examined in the above studies. Other investigators have shown recently that the histone deacetylase inhibitor trichostatin A increases TSP1 expression in cells propagated in vitro (Ref. Reference Kang116). This suggests the possibility that the increased effectiveness of ABT-510 administered with valproic acid in the above mouse models of cancer could be due to an increased expression of TSP1 in the tumour vascular cells induced by valproic acid. These results highlight the need to combine antiangiogenic therapies.
A Phase I clinical trial with ABT-510 monotherapy in 39 patients with advanced solid malignancy that were refractory to standard therapy, excluding primary brain tumours and metastases to the brain, has been performed (Ref. Reference Hoekstra117). In this study, six patients had stable disease lasting for six cycles or more of ABT-510 therapy. Also, the median serum level of bFGF for all patients decreased from 14.1 pg/ml to 3.2 pg/ml after 56 days of treatment, supporting the antiangiogenic effect of ABT-510. Importantly, as reported for animal studies with ABT-510, no indication of toxicity or damage to normal endothelial cells was observed. Toxicity due to repeated subcutaneous injection of ABT-510 at the same site was reported, and upon skin biopsy of one patient, a perivascular inflammatory cell infiltrate was seen but there was no vasculitis or endothelial cell death. Recently, the results of a Phase II clinical trial with ABT-510 monotherapy were reported. In 21 patients with metastatic melanoma treated with ABT-510, three patients appeared to have a partial response at 18 weeks (Ref. Reference Markovic118). Importantly, eight of 11 patients who had received six cycles of ABT-510 monotherapy had decreased numbers of circulating EPCs and six patients had decreased plasma levels of VEGF-A, supporting the antiangiogenic effects of ABT-510 therapy. These data support the contention that antiangiogenic therapy should be combined with a cytotoxic therapy and/or a secondary antiangiogenic therapy.
Integrin αvβ3
The expression of matrix-binding adhesion molecules on the endothelial cell surface is altered in glioblastoma tumours. The expression of the integrin family of cell adhesion receptors has been characterised on endothelial cells in these tumours. Targeting the tumour-associated upregulation of an integrin on endothelial cells, such as the upregulation of integrin αvβ3 on the endothelial cells in glioblastoma tumours (Refs Reference Gladson24, Reference Gingras119), would probably serve to block the pro-survival signal transmitted to basement-membrane-bound endothelial cells, as well as to inhibit signalling that promotes endothelial cell migration and proliferation (see Fig. 2 and Table 3). This could effectively inhibit angiogenesis. The integrin αvβ3-binding molecule cyclic-RGD-based peptide (Cilengitide) has been used for this purpose in a Phase I clinical trial and has shown no significant toxicity when administered to 37 patients with surgically resected and radiated glioblastoma tumours and to 11 patients with anaplastic astrocytoma tumours that were also surgically resected and radiated (Ref. Reference Nabors120). In this study, there were two complete responses, one in a patient with a glioblastoma tumour and one in a patient with an anaplastic astrocytoma tumour, and three patients demonstrated a partial response, suggesting that a subpopulation of patients with malignant glioma tumours respond favourably to the cyclic RGD peptide. The administration of RGD peptide has also been shown to inhibit human malignant glioma growth in mice (Refs Reference Chatterjee121, Reference Yamada122). Supporting the above results, the targeting of integrin αvβ3 in other types of cancer has proven effective in inhibiting tumour growth in mouse models (Refs Reference Reinmuth123, Reference Janssen124). Integrin αvβ3 may also be targeted by therapy with angiostatin, because angiostatin inhibits angiogenesis in part by binding to integrin αvβ3 (Ref. Reference Tarui, Miles and Takada82). Finally, integrin αvβ3 may be targeted by tumstatin, which binds integrin αvβ3 and induces endothelial cell death (Refs Reference Sudhakar72, Reference Maeshima, Colorado and Kalluri76).
Glucose-regulated protein 78
Recently, it has been shown that GRP78 is a cell-surface binding protein for K5 on non-brain microvessel endothelial cells, and is necessary for the proapoptotic effect of K5 in these cells (Ref. Reference Davidson85). GRP78 is a member of the heat shock protein 70 (HSP70) family and normally functions as an endoplasmic reticulum (ER)-resident chaperone protein (Ref. Reference Li and Lee125). Stress, such as hypoxia, can cause an upregulation of GRP78 via the unfolded protein response, which is part of the general cellular defence mechanism of stressed cells (Ref. Reference Li and Lee125). It has been shown that GRP78 is upregulated and expressed on the surface of tumour cells in patient biopsies, including biopsies of lung, breast, colon and prostate cancers (Refs Reference Li and Lee125, Reference Shin126, Reference Arap127, Reference Bini128). The expression of GRP78 and other ER chaperone proteins on the surface of tumour cells and potentially on tumour endothelial cells could be used as a novel target for therapy (see Fig. 2). Also, because a hypoxic environment is found in glioblastoma tumours, the targeting of GPR78 in these tumours with K5 could be efficacious.
Focal adhesion kinase
A potential intracellular target in the endothelial cell is FAK (see Fig. 2). FAK is a cytoplasmic nonreceptor tyrosine kinase that is necessary for vasculogenesis (Ref. Reference Ilic129). The embryos of FAK-null mice are not viable because of severe cardiovascular anomalies (Ref. Reference Ilic129). Additional evidence supporting a role for FAK in angiogenesis is the observation that dominant-negative FAK constructs, such as the FAK-related non-tyrosine kinase construct (FRNK), which corresponds to the C-terminus of the FAK protein, inhibits endothelial cell tube formation and branching in tubulomorphogenesis assays (Ref. Reference Haskell130). FAK promotes two functions essential for neovascularisation: cell proliferation and migration (reviewed in Refs Reference Cox131, Reference Parsons132). It promotes cell-cycle progression by activating Erk, and inducing expression of the transcription factor krupple-like factor 8 (KLF8), which binds and promotes cyclin D1 transcription (Refs Reference Zhao, Zheng and Guan133, Reference Zhao134, Reference Ding135). Evidence that FAK promotes cell migration is abundant and includes studies using FAK-null mouse embryo fibroblasts that demonstrated reduced cell motility (Ref. Reference Ilic129), which was rescued by the re-expression of FAK (Ref. Reference Owen136). In multiple cell types, including brain endothelial cells and glioblastoma tumour cells, dominant-negative FAK constructs inhibit cell migration whereas wild-type FAK constructs promote cell migration (Refs Reference Haskell130, Reference Cox131, Reference Parsons132, Reference Natarajan137). Small-molecule inhibitors of FAK, such as TAE226 (Ref. Reference Shi138) and PF-573,228 (Ref. Reference Slack-Davis139), are now available, and both of these inhibitors significantly block the migration and invasion of cells propagated in vitro. The TAE226 inhibitor also blocks cell proliferation in vitro. A FAK family member, PYK2, has also been shown to promote migration and invasion of glioblastoma tumour cells propagated in vitro (Refs Reference Lipinski140, Reference Lipinski141). It is worth noting that different experimental conditions were used for the PYK2 studies compared with those used to test the necessity of FAK for glioblastoma cell migration (Refs Reference Natarajan137, Reference Lipinski140, Reference Lipinski141). The FAK inhibitor PF-573,228 appears to be specific for FAK because it is 250 times more sensitive to FAK (IC50 = 4 nM) compared with PYK2 (IC50 = 1 µM) (Ref. Reference Slack-Davis139). The effect of the FAK inhibitor TAE226 on PYK2 has not been reported. These inhibitors offer promise for future animal studies and clinical trials, and suggest that the targeting of FAK in the tumour endothelial cells could be an effective antiangiogenic therapy (see Fig. 2).
Angiopoietin-1 receptor
Specific inhibition of the pericyte signalling, which supports endothelial cell survival in the glioblastoma neovasculature, through targeting of the angiopoietin–TIE2 signalling axis is another potential therapy (Ref. Reference Bach, Uddin and Burke142). However, the neovasculature in glioblastoma tumours has significantly reduced pericyte coverage, thus the effectiveness of this approach in glioblastoma tumours must be determined. TIE2 expression in glioblastoma tumours is upregulated on the endothelial cells (Ref. Reference Stratmann, Risau and Plate91), and the increased angiopoietin-2 found in glioblastoma tumours is localised to endothelial cells and associated with angiogenesis; thus, investigators have hypothesised that angiopoietin-2 promotes angiogenesis in the presence of VEGF (Refs Reference Stratmann, Risau and Plate91, Reference Lobov, Brooks and Lang143, Reference Holash144). The angiopoietin-1 expressed by tumour cells, but not by the endothelial cells, in glioblastoma biopsies may act to promote cell adhesion because angiopoietin-1 and -2 can promote adhesion mediated by integrin α5β1, independently of TIE2 expression (Ref. Reference Carlson145). Thus, potential therapies that block TIE2 signalling in glioblastoma tumours require further investigation.
Pericytes
NG2 chondroitin sulphate proteoglycan
A possible target on pericytes is NG2 (also known as CSPG4), which is a transmembrane protein and a marker of pericytes in angiogenic vessels (see Table 1 and Fig. 2) (Refs 146, 147; reviewed in Ref. Reference Bergers and Song32). Expression of NG2 is upregulated on pericytes in glioblastoma tumours compared with the expression on pericytes in normal brain (Ref. Reference Schrappe148). NG2 appears to promote a proangiogenic effect through its binding and sequestration of angiostatin (Ref. Reference Chekenya83). Human U-251MG malignant glioma cells overexpressing NG2 and propagated in nude rats exhibited increased tumour growth and increased tumour angiogenesis compared with similarly propagated wild-type tumour cells (Ref. Reference Chekenya83), supporting the potential proangiogenic role of NG2 in glioblastoma tumours. This suggests that the vascular supporting cells in glioblastoma tumours may be induced by the tumour to upregulate expression of the proangiogenic proteoglycan NG2.
Platelet-derived growth factor β receptor
Another target on pericytes is PDGFRβ, the receptor for PDGF (see Fig. 2). Expression of PDGFRβ on pericytes is responsible for pericyte recruitment to blood vessels (Refs Reference Hellstrom149, Reference Guo150). PDGFRβ is also expressed on some tumour cells in glioblastoma tumours and it can cooperate with integrin αvβ3 in promoting the migration of glioblastoma cells (Refs Reference Hermanson151, Reference Ding152). PDGFRβ can be targeted through specific tyrosine kinase inhibitors, or through antibodies directed toward PDGF-BB or PDGFRβ. Blocking either the receptor or ligand could theoretically inhibit other key downstream signalling events that promote endothelial cell survival as well as inhibit tumour cell migration (Refs Reference Guo150, Reference Ding152). In a study of pancreatic islet cell carcinoma, the investigators found an enhanced antiangiogenic effect when combining VEGF and PDGF antagonists that resulted in anti-endothelial cell and anti-pericyte effects (Ref. Reference Bergers153). In another study, investigators also targeted the PDGF and VEGF signalling pathways simultaneously in B16 melanoma tumours propagated in C57BL/6 mice with a small-molecule inhibitor of VEGFR (PTK787) and of PDGFR (STI576) (Ref. Reference Hasumi154). In this study, a reduction in tumour size was found (probably because of a reduction in tumour vessel density and tumour vessel size), as well as a reduction in pericytes that were loosely attached to the tumour vessels; however, no change in the number of pericytes tightly associated with the vessels was observed. Consistent with the above animal studies, in a Phase I/II clinical study of patients with recurrent malignant glioma, a PDGFR inhibitor (imatinib) administered alone did not appear to be effective (Ref. Reference Wen155); however, when imatinib was combined with hydroxyurea in a Phase II clinical study of patients with recurrent malignant glioma, the results were encouraging (Ref. Reference Reardon156). Collectively, these studies underscore the importance of evaluation of antiangiogenesis therapy as a component of multimodality strategies.
Circulating progenitor cells – CXCR4
The circulating progenitor cells that are recruited to angiogenic vessels and may promote angiogenesis are of great interest (Refs Reference Shaked157, Reference Dome158, Reference Jain and Duda159). Whether the recruited progenitor cells are solely endothelial progenitors or are also progenitors of supportive smooth muscle cells and pericytes is an area of active research. The CXCR4 receptor expressed on circulating EPCs is recognised by chemokine CXCL12/SDF-1α; thus, the CXCR4 on these EPCs could be targeted therapeutically with the goal of inhibiting EPC mobilisation from the bone marrow (see Fig. 2) (Ref. Reference Zernecke160). As CXCR4 is expressed on smooth muscle cell progenitors, this approach could also be used to target the recruitment of these cells to angiogenic vessels (Ref. Reference Zernecke160). Inhibition of CXCL12 signalling is likely to have multiple effects; for example, circulating EPCs also can express CXCL12 and can therefore recruit additional EPCs from the bone marrow. The importance of this signalling pathway in vasculogenesis is suggested by the severe vascular abnormalities and associated embryonic lethality exhibited by both CXCL12- and CXCR4-knockout mice (Ref. Reference Tachibana161). Interestingly, CXCL12 is expressed by the pleomorphic angiogenic vessels in the glioblastoma tumours (Refs Reference Salvucci39, Reference Rempel40), suggesting that this neovasculature may recruit circulating EPCs, which would support the continued neovascularisation described above (see Table 1). When mice bearing grafted Lewis lung carcinoma tumours were treated with the TSP1 TSR mimetic ABT-510 or with a monoclonal antibody to VEGFR2, there was a reduction in the number of circulating EPCs and circulating endothelial cells (CECs); in this study the antitumour therapeutic activity of the VEGFR2 antibody was verified by a reduced tumour volume (Ref. 157). These results support the concept that circulating EPCs contribute to angiogenesis in tumours. Thus, further investigation of the relative numbers of circulating EPCs, their biological role in angiogenesis, and the potential efficacy of agents that target these cells in glioblastoma tumours is warranted.
Endothelial cell matrix and basement membrane of the glioblastoma tumour vasculature
ED-B isoform of fibronectin
Matrix proteins and fragments of matrix proteins that regulate angiogenesis are expressed differentially in the neovasculature of glioblastoma tumours compared with expression in the normal brain (Ref. 162; reviewed in Ref. Reference Wang, Anderson and Gladson147). Thus, these matrix proteins and fragments may be extremely useful in the directed delivery of therapies. For example, the oncofetal isoform of fibronectin (the ED-B isoform) is expressed only during embryogenesis and angiogenesis, and is a clear marker of the angiogenic vasculature in glioblastoma tumours (Ref. Reference Castellani162). An antibody to such a matrix molecule could be used to deliver a cytotoxic conjugate to the glioblastoma tumour vasculature (see Fig. 2) (Refs Reference Mariani163, Reference Tarli164). This could be a highly effective therapeutic approach because immunorecognition of proteins in the endothelial cell basement membrane is probably increased by the exposure of the endothelial cell basement membrane that occurs during degradation by proteases prior to endothelial cell sprouting and by the erratic coverage of the basement membrane by endothelial cells in angiogenic vessels.
Tenascin-C
The matrix protein tenascin-C appears to play an important role in angiogenesis (see Table 1 and Fig. 2). In glioblastoma tumours, tenascin-C is expressed at sites of neovascularisation by vascular cells, including those at the invasive edge of the tumour, but it is not expressed in the normal brain (Ref. Reference Zagzag165). Tenascin-C promotes brain microvascular endothelial cell migration and it is synthesised by migrating brain microvascular endothelial cells, suggesting that endothelial cells can promote their own migration through this autocrine loop (Ref. Reference ZagZag166). In addition, tenascin-C can promote FAK phosphorylation and upregulate VEGF expression (Refs Reference ZagZag166, Reference Huang167, Reference Orend168), as well as induce proliferative signals that appear to be mediated through its interactions with integrin α5β1 and syndecan-4 (Ref. Reference Huang167). These data suggest that the vascular cells in glioblastoma tumours and in other malignant tumours are induced or co-opted by the tumour to synthesise and secrete proangiogenic tenascin-C.
In a Phase II clinical trial, a 131I-labelled antitenascin-C monoclonal antibody (81C6) was injected into the surgical resection cavity of newly diagnosed glioblastoma patients, followed by conventional radiotherapy and chemotherapy. This treatment significantly increased the median survival of the glioblastoma patients (Ref. Reference Akabani169). In a Phase II study, intracavitary administration of 131I-labelled 81C6 to patients with recurrent malignant glioma followed by chemotherapy, also resulted in a median survival that was greater than that of historical controls treated with surgery and 125I-brachytherapy (Ref. Reference Reardon170). As tenascin-C has multiple functional domains (Ref. Reference Jones and Jones171), the physiological implications of targeting tenascin-C in glioblastoma tumours are probably multifactorial and are not completely understood. Nevertheless, the current and potential future use of tenascin-C, as a homing signal for conjugated cytotoxic agents or antiangiogenic agents for radiotherapy or for radioimaging, offers intriguing possibilities (see Fig. 2). The above data suggest that the targeting of matrix proteins associated with the angiogenic vasculature in glioblastoma tumours is feasible and can be therapeutically useful.
Clinical implications
Quantitative measures of angiogenesis
The monitoring of antiangiogenic therapeutic agents and delineation of their mechanism of action requires assays that can be used to accurately quantify changes in the tumour neovasculature. Angiogenesis can be quantified in biopsies of tumour tissue using direct counts of the vessel surface area, including small and large vessels, or counts of microvessel density after immunostaining the tissue section with an antibody directed toward von Willebrand factor, CD31 or factor VIII (Refs Reference Folkman4, Reference Anderson, Grammer, Wang, Nabors, Henkin, Stewart and Gladson54, Reference Perri88, Reference Reiher106, Reference Haviv107). Angiogenesis can also be assessed in biopsies of glioblastoma tumour tissue by visualising the decreased pericyte coverage or decreased pericyte density after immunostaining the tissue section with an antibody directed toward NG2, desmin or smooth muscle actin, all of which are markers of pericytes (Ref. Reference Bergers and Song32). Methods for the assessment of angiogenesis in the tumour when biopsy tissue is not available are still under development and this complicates the assessment of the clinical efficacy of antiangiogenic therapy. A radiolabelled anti-fibronectin ED-B isoform antibody (Refs Reference Mariani163, Reference Tarli164) and a radiolabelled RGD peptide (Ref. Reference Janssen124) have been tested as in vivo markers of the neovasculature. A promising approach is the quantification of indirect markers of tumour angiogenesis that can be assessed noninvasively, such as the quantification of CECs and circulating EPCs (Refs Reference Shaked157, Reference Duda172). However, the criteria for the identification of CECs and circulating EPCs are still being standardised. CECs are thought to reflect endothelial cell damage and increased numbers are seen with tumour angiogenesis. The number of circulating EPCs is thought to correlate with ongoing angiogenesis and recruitment from the bone marrow. Currently, multichannel flow cytometry analysing a combination of markers (CD45–, CD34+, CD133+ and VEGFR2+) is used to identify circulating EPCs (Refs Reference Shaked157, Reference Dome158, Reference Duda172, Reference Mancuso173, Reference Mancuso174). Some investigators include the expression of c-kit (CD117+) and CD13 to identify circulating EPCs (Ref. Reference Shaked157). Alteration of the number of circulating EPCs has been used with some success to measure the vascular response to treatment with the TSP1 TSR mimetic ABT-510, a monoclonal antibody to VEGFR2 and a monoclonal antibody to VEGF-A (Refs Reference Willett100, Reference Markovic118, Reference Shaked157). Quantification of circulating EPCs and CECs also may offer a measure of the direct effect of antiangiogenic agents on the mobilisation of EPCs from the bone marrow and the sloughing of endothelial cells from angiogenic tumour vessels, respectively.
Serum or plasma levels of certain proangiogenic factors, such as bFGF and CXCL12, could also potentially be useful markers of angiogenesis. Antiangiogenic therapy with AZD2171, a pan-VEGFR tyrosine kinase inhibitor, results in a decrease in the levels of bFGF and CXCL12 (Ref. Reference Batchelor103). The expression of these two proangiogenic growth factors is upregulated on the vessels or on the pleomorphic angiogenic vessels in glioblastoma tumours (Refs Reference Karcher13, Reference Salvucci39, Reference Rempel40).
Perfusion MRI, also known as dynamic contrast-enhanced MRI, is a relatively new imaging technique that can be used for the assessment of tumour angiogenesis (reviewed in Ref. Reference Barrett175). Using this technique, images can be acquired in a relatively short period of time when a patient presents for a standard contrast-enhanced MRI. Recent reports suggest this technique may be useful in monitoring neovascularisation, because altered perfusion parameters have been demonstrated in brain tumours after antiangiogenic therapy with the RGD-peptide Cilengitide (Refs Reference Nabors120, Reference Akella176).
The blood–brain barrier and antiangiogenic therapy
The BBB is a unique functional unit that limits passive, active and facilitated transport of molecules between the blood and the brain (Refs Reference Hawkins and Egleton177, Reference Ballabh, Braun and Nedergaard178). Key components of the BBB include: tight junctions between endothelial cells, pericytes in the basement membrane and astrocyte endfoot processes (Refs Reference Hawkins and Egleton177, Reference Ballabh, Braun and Nedergaard178). There is a reduced number of fenestrations in brain capillaries compared with capillaries in other organs that are responsible for uptake of molecules, and this limits transport across the BBB (Ref. Reference Hawkins and Egleton177). In addition, brain endothelial cells express relatively high levels of the P-glycoprotein (Pgp/MDR1) drug efflux pump that controls the transport of many chemotherapeutic agents, and this limits active transport across the BBB (Ref. Reference Pardridge179).
In glioblastoma tumours, the BBB is either intact or disrupted depending on whether the vessels are part of the tumour neovasculature or are co-opted vessels (Refs Reference Ballabh, Braun and Nedergaard178, Reference Claes180). The status of the BBB may also be dependent on the spatial localisation of the vessels in the tumour, in areas lacking a neovasculature (for example, some areas of the invasive margin) the BBB is intact; whereas in areas of the tumour where there is a neovasculature, the vessels are leaky (disrupted BBB) (Ref. Reference Muldoon181). A disrupted BBB probably promotes access of large molecules to the tumour. Disruption of the BBB should also result in an initial increase in passive transport of small molecules to the tumour; however, passive transport is probably diminished, because the disrupted BBB becomes chronic owing to an equalisation of the osmotic gradient. These observations result in difficulty in targeting the entire tumour with one drug at any given time, because different properties are required for the drug to gain access to the tumour depending on whether there is a disrupted or intact BBB.
Certain antiangiogenic agents, such as inhibitors of the VEGF/VEGFR signalling pathway, cause a ‘normalisation’ of the BBB; normalisation is defined as a reduction of vessel leakage and a concomitant reduction of interstitial fluid pressure in the brain parenchyma as assessed by perfusion or contrast-enhanced MRI (Ref. Reference Batchelor103). In a recent study, normalisation of the neovasculature occurred post therapy with a VEGFR inhibitor and correlated with an increased pericyte recruitment to neovessels in the tumour, suggesting that pericyte coverage could be an anatomical correlate of vascular normalisation in glioblastoma tumours (Ref. Reference Batchelor103). Other antiangiogenic agents have been shown to reduce vascular permeability associated with disruption of the BBB. For example, endostatin therapy reduced vessel density, vessel diameter and vessel permeability in malignant glioma tumours, as well as inducing a collapse of tumour vessels in a syngeneic intracerebral rat model of malignant glioma (Ref. Reference Barnett73). This reduction in vessel permeability may have been due to an increase in pericyte coverage of tumour vessels because the authors reported an increase in pericyte number with endostatin therapy; however, pericyte coverage was not shown and the quantification of pericytes was not described. Also, the antiangiogenic compound thalidomide administered at teratogenic doses that inhibit angiogenesis (Ref. Reference D'Amato182) may decrease brain vessel permeability induced by stimulation with a β-amyloid peptide (Ref. Reference Ryu and McLarnon183). However, thalidomide used at a similar teratogenic dose was reported to induce increased endothelial cell fenestrations and thinned endothelial cell processes, which correlated with inhibition of bFGF-induced neovascularisation in the rabbit corneal micropocket model of angiogenesis (Ref. Reference D'Amato182).
Normalisation of the tumour neovasculature with VEGF or VEGFR inhibitors may potentially alter the effectiveness of certain chemotherapeutic agents. Recently, a decreased tumour response to temozolomide therapy was observed when temozolomide was administered simultaneously with a VEGFR2 inhibitor in an intracerebral xenograft model of malignant glioma (Ref. Reference Claes180). This was interpreted to be due to a decreased localisation of temozolomide to the tumour, although temozolomide levels in the tumour were not measured. Also, the antiangiogenic compound O-(N-chloroacetyl-carbamoyl)-funagillol (TNP-470) may affect the BBB, because a decreased concentration of temozolomide in the tumour was reported when TNP-470 was administered to an orthotopic mouse model of malignant glioma followed by temozolomide therapy (Ref. Reference Ma184). However, other reports indicate that simultaneous administration of an antiangiogenic agent and a chemotherapeutic agent has beneficial results in orthotopic rodent models of malignant glioma. For example, thalidomide and cisplatin combination therapy resulted in a greater inhibition of tumour growth than that seen with either agent alone (Ref. Reference Murphy185), a synthetic fragment of endostatin and carmustine combination therapy increased survival in a synergistic manner (Ref. Reference Pradilla186) and a novel small-molecule tyrosine kinase inhibitor (AEE788), which blocks the activity of VEGFR2 and EGFR, combined with a mTOR inhibitor (RAD001) yielded greater increases in mouse survival than either agent alone (Ref. Reference Goudar187). Also, some clinical trials of combination therapy with an antiangiogenic agent and a chemotherapeutic agent in patients with malignant glioma or glioblastoma tumours yield promising results, including for example, a study utilising a monoclonal antibody to VEGF-A (bevacizumab) and irinotecan (Ref. Reference Vredenburgh188); a study utilising thalidomide and temozolomide (Ref. Reference Baumann189); and a study utilising thalidomide and carmustine (Ref. Reference Fine190). Therefore, the potential of certain antiangiogenic agents to restore the BBB and reduce the tumour localisation of certain chemotherapeutic agents suggests that the target of specific antiangiogenic therapy, the effects of different antiangiogenic therapies on the BBB and the time course of these effects must be determined to optimally combine antiangiogenic therapy with chemotherapy. Agents that normalise the tumour neovasculature could be used following cytotoxic therapy, if the cytotoxic agent of choice cannot cross the BBB after antiangiogenic therapy. Also, the BBB could potentially be disrupted transiently for chemotherapeutic delivery purposes using ultrasound, convection-enhanced delivery or hypertonic solutions after antiangiogenic therapy (Ref. Reference Kemper191). One caveat of the latter approach is that there is the potential for neurotoxicity or an inflammatory response with disruption of the BBB, because it allows a broad spectrum of plasma proteins to cross into the brain.
Developed resistance to antiangiogenic therapy
Glioblastoma tumours are able to escape the effectiveness of antiangiogenic monotherapy, even though the endothelial cells are relatively genetically stable. For example, one study showed that when dermal fibroblasts overexpressing intact TSP1 were injected subcutaneously along with rat C6 glioma cells into nude mice, there was an initial inhibition of tumour growth and angiogenesis (Ref. Reference Filleur192). However, prolonged exposure of the tumours to TSP1 resulted in an increased expression of proangiogenic growth factors by the tumour that counterbalanced the inhibitory effect of TSP1 on neovascularisation (Ref. Reference Filleur192). Also, in an orthotopic model of gliosarcoma propagated in the rat, downregulation of VEGF-A resulted in an increase in the expression of VEGF-D (Ref. Reference Moffat193), and a study in patients with brain tumours treated with a VEGF inhibitor showed only a temporary normalisation of the tumour vasculature (reviewed in Ref. Reference Jain102). In addition, in a study of 16 patients with recurrent glioblastoma tumours treated with AZD2171 monotherapy (directed toward VEGFR), the 11 patients who experienced disease progression had significantly elevated levels of serum bFGF and CXCL12 (Ref. Reference Batchelor103). These reports highlight the need to move from single antiangiogenic agent therapy to combined antiangiogenic therapy. Moreover, antiangiogenic therapies should be a component of a multi-modality strategy (cytotoxic and antiangiogenic), because progressive tumour growth can occur after antiangiogenic therapy alone, despite reduced angiogenesis (Ref. Reference Leenders194). The latter observation may be due to a co-option of the existing blood vessels by the tumour. In support of this hypothesis, treatment with a monoclonal antibody toward VEGFR2 inhibited glioma angiogenesis in an orthotopic mouse model of malignant glioma; however, numerous satellite tumours arose around the primary tumour and these satellite tumours had a central vessel core (Ref. Reference Kunkel195). These data support the need to combine antiangiogenic therapy with other treatment modalities.
Possible strategies for combining antiangiogenic therapy with other treatment modalities would be to use agents that target more than one pathway (e.g. targeting the fibronectin ED-B isoform in the endothelial cell basement membrane or VEGFR2 on the endothelial cell, with an antiangiogenic or cytotoxic conjugate coupled to an antibody). Alternatively, targeting small and dilated vessels in the tumour with the concurrent use of two antiangiogenic drugs – one that targets microvessels, such as the TSP1 TSR mimetic ABT-510, and a VEGF/VEGFR inhibitor, which has a more pronounced effect on enlarged (dilated) vessels in glioblastoma tumours – could be highly effective. Targeting of both endothelial cells and circulating EPCs (e.g. an antibody directed toward CXCR4 together with a TSP1 TSR mimetic such as ABT-510) warrants consideration. Finally, two recent studies – an animal study targeting VEGF signalling and a clinical trial with AZD2171 in patients with recurrent glioblastoma tumours – suggest that antiangiogenic agents inhibit angiogenesis temporarily, but on cessation of the therapy, renewed tumour neovascularisation occurs (Refs Reference Batchelor103, Reference Casanovas196). This would indicate that cycling of administration of antiangiogenic agents may be required. In conjunction with conventional chemotherapies and surgery, combinatorial antiangiogenic therapies could prove effective, especially if used simultaneously, thereby preventing tumour adaptation and thus drug resistance.
Outstanding research questions
There are opposing actions in glioblastoma tumours, some proangiogenic and others antiangiogenic, that affect the angiogenic response. Control of the angiogenic response most likely occurs at the cellular level and thus the localisation of pro- and antiangiogenic factors is important (Tables 1 and 2; Figs 1 and 2). The tumour overcomes the influence of the antiangiogenic factors produced by the host stromal cells through multiple mechanisms that include: (1) tumour cell secretion of proangiogenic growth factors, such as VEGF; (2) tumour cell expression of proangiogenic growth factor receptors, such as PDGFR and FGFR4, which take advantage of the proangiogenic growth factors in the tumour microenvironment to promote their own proliferation and migration; (3) tumour-induced expression of proangiogenic matrix proteins by host stromal cells, such as increased pericyte expression of NG2 and vascular cell expression of tenascin-C; and (4) tumour-induced downregulation of antiangiogenic factors by stromal cells, such as the downregulation of TSP2. Thus, the mechanisms by which glioblastoma tumours ‘co-opt’ the host stromal cells and induce their expression of proangiogenic molecules or downregulate their expression of antiangiogenic molecules is of great interest. A new model of glioblastoma tumours (Ref. Reference Assanah197) derived from the PDGF-induced transformation of adult brain progenitor cells has shown that transformed progenitor cells induce proliferative changes in the resident nontransformed progenitor cells. This model could be used to study how glioblastoma tumour cells co-opt the host stromal cells to enhance tumour cell growth, survival, and invasion.
Antiangiogenic therapy appears to be an important new adjuvant therapy for glioblastoma tumours and a number of clinical trials with antiangiogenic agents are ongoing (see Table 3); however, several practical considerations must be addressed. Most investigators agree that antiangiogenic therapy should be combined with a cytotoxic agent for maximal benefit, but questions still remain regarding which cytotoxic agent to combine with which specific antiangiogenic agent and whether they should be administered concurrently or in a staggered manner if the antiangiogenic therapy restores the BBB (Refs Reference Winkler104, Reference Bello198). Similarly, questions remain concerning whether two antiangiogenic agents with different molecular targets should be administered simultaneously and which method of delivery of antiangiogenic agents is most effective (Ref. Reference Schmidt199). In addition, the most effective schedule for re-administration of antiangiogenic therapy must be determined. To address these issues effectively it will be necessary to further develop techniques for measuring the response of the neovasculature in tumours during and after antiangiogenic therapy. Re-biopsy of the tumour is costly and invasive; thus, additional assays for measurement of angiogenesis are necessary. The quantification of CECs and circulating EPCs from blood samples pre- and post-therapy are promising new assays for assessment of tumour angiogenesis or treatment response, but the markers used for identification of these cells from blood must be optimised and standardised. The recent evidence that perfusion MRI could be used as a measure of tumour angiogenesis is exciting, but could be expensive (Refs Reference Barrett175, Reference Akella176). Thus, the successful application of antiangiogenic therapies for the treatment of glioblastoma tumours will require additional translational research, including animal studies and Phase I/II clinical trials, over the next few years.
Considerable progress has been made in developing new drugs that target the known proangiogenic growth factors, their receptors and signalling molecules, as well as in the identification of endogenous inhibitors of angiogenesis that could be exploited for therapeutic purposes. Our knowledge of angiogenesis and its regulation is still in its infancy, however, especially in terms of the identification of endogenous inhibitors and their modes of action. Continued basic research is necessary and will provide valuable insights into how the tumours overcome the antiangiogenic effects of endogenous inhibitors of angiogenesis, and how they adapt to antiangiogenic therapy.
Acknowledgements
Mrs Rhonda Carr is thanked for secretarial assistance in preparing this manuscript. We apologise for not including all relevant references owing to space constraints. This work was supported by grants CA127620 and CA109748 from the National Institutes of Health, National Cancer Institute to C.L.G., and an institutional T32 grant NS048039 from the National Institute of Neurological Diseases and Stroke (J.C.A.).