INTRODUCTION
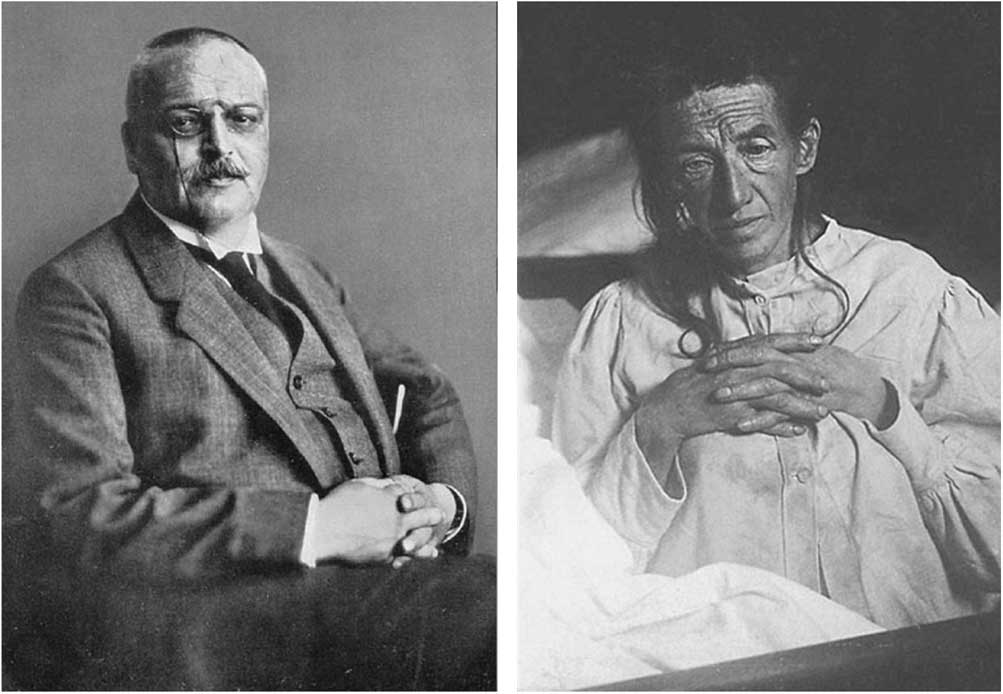
One of the great challenges faced by neuropsychologists over the past 50 years is to understand the cognitive and behavioral manifestations of dementia and their relationship to underlying brain pathology. This challenge has grown substantially over the years with the aging of the population and the age-related nature of many dementia-producing neurodegenerative diseases. Although the concept of dementia has existed for thousands of years (Mahandra, Reference Mahandra1984), it is only early in the past century that the essential clinical syndrome and associated neurodegenerative changes were first discovered. In 1907, Aloysius “Alöis” Alzheimer carefully described the symptoms of a 51-year-old woman, Auguste Deter, who was under his care at the state asylum in Frankfurt Germany (Alzheimer, Reference Alzheimer1907; for an English translation, see Stelzmann et al., Reference Stelzmann, Schnitzlein and Murtagh1995) (Figure 1). Alzheimer’s description of her symptoms is almost certainly the first neuropsychological characterization of the disease:
Photographs of Alois Alzheimer (left) and his patient Auguste Deter (right).

“Her memory is seriously impaired. If objects are shown to her, she names them correctly, but almost immediately afterwards she has forgotten everything. When reading a test, she skips from line to line or reads by spelling the words individually, or by making them meaningless through her pronunciation. In writing she repeats separate syllables many times, omits others and quickly breaks down completely. In speaking, she uses gap-fills and a few paraphrased expressions (“milk-pourer” instead of cup); sometimes it is obvious she cannot go on. Plainly, she does not understand certain questions. She does not remember the use of some objects.”
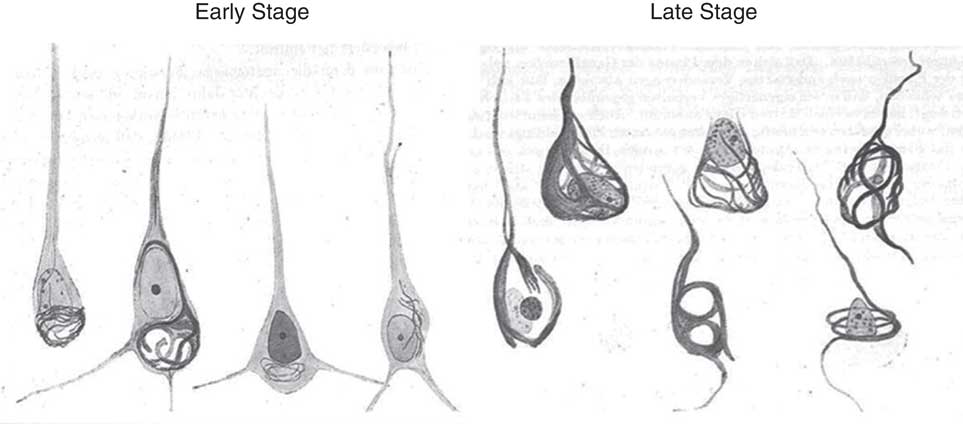
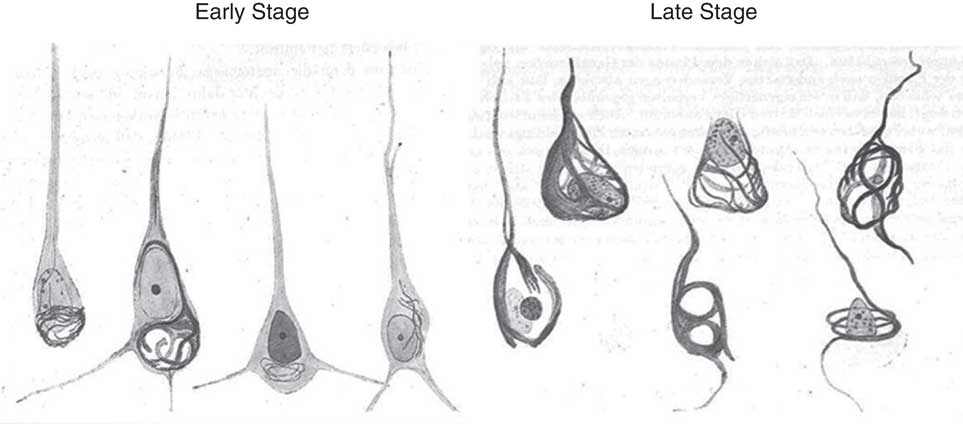
When Auguste Deter died, Alzheimer used the then-new silver staining histological technique to examine her brain microscopically. When he did so, he observed the neuritic plaques, neurofibrillary tangles, and amyloid angiopathy that were to become the hallmarks of the disease that now bears his name (as shown in Figure 2 from sketches of the histologic preparations in his 1911 paper). Alzheimer himself did not claim to have discovered “Alzheimer’s disease,” although his mentor Emil Kraepelin at the Munich Medical School rightly credited him with doing so by coining the term in his own Handbook of Psychiatry (Kraepelin, Reference Kraepelin1910). By 1911, the medical community was using Alzheimer’s depictions of the disease to diagnose patients both in Europe and the United States (Mauer & Mauer, Reference Maurer and Maurer2003).
Sketches of Auguste Deter’s histopathologic preparations of early and late stage neurofibrillary tangle pathology as drawn by Alzheimer from his Reference Alzheimer1911 paper entitled “Über eigenartige Krankheitsfälle des späteren Alters.”
It was also during this time that Eugen Blueler in his study of schizophrenia coined the term “organic psychosyndrome” to refer to decrements in memory, judgment, perceptual discrimination and attention, emotional lability, and defective impulse control associated with chronic diffuse cortical damage. This classification was essentially adopted by the American Psychiatric Association (APA) to define dementia in the first two editions of their Diagnostic and Statistical Manual of Mental Disorders (DSM). Specifically, DSM-II defined “organic brain syndrome” as a “basic mental condition characteristically resulting from diffuse impairment of brain tissue function from whatever cause,” and which is manifested behaviorally as impairment in orientation, memory, intellectual functions, judgment, and affect (APA, 1968).
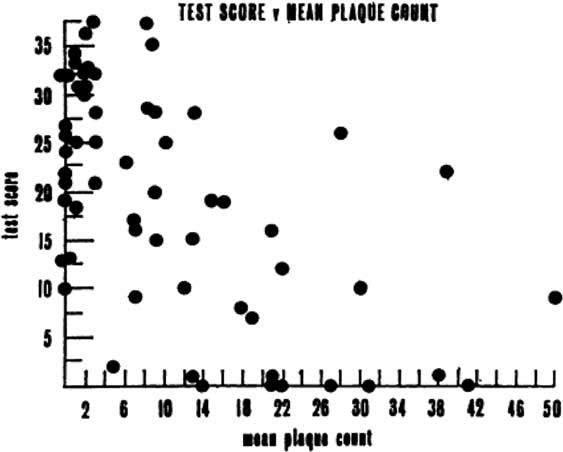
Armed with these uniform criteria and newly developed standardized bedside cognitive screening tests (Blessed, Tomlinson, & Roth, Reference Blessed, Tomlinson and Roth1968; Folstein, Folstein, & McHugh, Reference Folstein, Folstein and McHugh1975), a handful of investigators began scientific studies of dementia, particularly focusing on dementia associated with Alzheimer’s disease (AD). Although dementia is associated with more than 70 different causes of brain dysfunction, AD is the most common cause accounting for roughly half of all cases (for review, see Cummings & Benson, Reference Cummings and Benson1992). One of the most important studies during this period showed that the degree of AD pathology in the brain was significantly correlated with performance on standardized cognitive tests shortly before death (Blessed, Tomlinson, & Roth, Reference Blessed, Tomlinson and Roth1968). This was the first study to strongly link the clinical features of AD with the pathologic brain changes that Alzheimer had described (Figure 3).
Mean plaque count plotted against the summary cognitive test score constructed by Blessed, Tomlinson, & Roth (Reference Blessed, Tomlinson and Roth1968). The “Blessed” test score was computed from “a number of simple psychological tests of orientation, remote memory, recent memory, and concentration,” resulting in a total score ranging from 0 (complete failure) to 37 (perfect score). The scatterplot resulted in a highly significant correlation coefficient of −0.59 (p<.001) (from Blessed, Tomlinson, & Roth, Reference Blessed, Tomlinson and Roth1968).

Neuropsychological studies of dementia and AD during this period were rare and largely limited to presenile dementia with onset before the age of 65. A notable exception was a series of studies by Edgar Miller who showed that the main behavioral feature of presenile AD is a memory disorder in which recently acquired information fails to reach long-term memory storage due to both an abnormally rapid loss of material from short-term storage (perhaps due to encoding inefficiency) and difficulty in transferring information between short-term and long-term storage systems (Miller, Reference Miller1971, Reference Miller1973). He also suggested that inefficient retrieval of information from long-term storage may contribute to the memory deficit in presenile AD (Miller, Reference Miller1975, Reference Miller1978). These early studies set the stage for countless subsequent studies that examined the nature of memory dysfunction in AD in the decades to follow (for reviews, see Salmon & Bondi, Reference Salmon and Bondi2009; Smith & Bondi, Reference Smith and Bondi2013).
A major sea-change in the study of dementia occurred in 1976 when Robert Katzman summarized data showing that senile and presenile AD were histopathologically identical and suggested that, based on epidemiological data, AD was the fourth leading cause of death in the elderly (Katzman, Reference Katzman1976). Suddenly, AD dementia went from a relatively rare condition to a major public health issue. This led to greater attention to the disease by the public and at the National Institutes of Health, which established the National Alzheimer’s Disease Research Center program to study the cause, neuropathology, and clinical characteristics of AD. At this time, the diagnostic criteria for dementia were refined in the DSM-III (American Psychiatric Association, 1980) and International Statistical Classification of Diseases and Related Health Problems, 10th Revision (World Health Organization, 1992), and specific research diagnostic criteria for AD were established (McKhann et al., Reference McKhann, Drachman, Folstein, Katzman, Price and Stadlan1984).
Also notable at this time was a growing realization that various dementing disorders are associated with patterns of relatively preserved and impaired cognitive abilities that vary depending upon the etiology and neuropathology of the underlying disease. Martin Albert and his colleagues (Albert, Feldman, & Willis, Reference Albert, Feldman and Willis1974) referred to the pattern of cognitive dysfunction observed in patients with progressive supranuclear palsy as a “subcortical dementia” characterized by forgetfulness, slowness of thought processes, altered personality with apathy or depression, and impaired ability to manipulate acquired knowledge. Similar cognitive changes were noted in patients with Huntington’s disease (McHugh & Folstein, Reference McHugh and Folstein1975). This pattern of impairment was contrasted with the cortical dementia (e.g., frank amnesia, aphasia, and agnosia) observed in AD. Subsequent studies further delineated qualitative differences in the cognitive deficits associated with so-called “cortical” and “subcortical” dementing disorders (Huber, Shuttleworth, Paulson, Bellchambers, & Clapp, Reference Huber, Shuttleworth, Paulson, Bellchambers and Clapp1986; Salmon, Kwo-on-Yuen, Heindel, Butters, & Thal, Reference Salmon, Kwo-on-Yuen, Heindel, Butters and Thal1989), and several investigators suggested that these two forms of dementia should be recognized as distinct clinical syndromes (for reviews, see Cummings & Benson, Reference Cummings and Benson1992; Cummings, Reference Cummings1990).
THE 1990s: NEUROPSYCHOLOGICAL CHARACTERIZATION OF ALZHEIMER’S DISEASE AND RELATED DISORDERS
The new criteria for dementia and AD adopted in the 1980s improved the reliability of the clinical diagnosis and allowed group studies of mildly demented patients to be carried out with a reasonable degree of accuracy. Many of these studies applied the theories and methods of cognitive psychology to study the cognitive consequences of AD. By using this approach, these studies characterized the component cognitive processes underlying the neuropsychological deficits observed in AD, and showed that cognitive changes attributable to AD and other dementing disorders could have important implications for existing theories of brain–behavior relationships underlying normal cognition.
Several studies at this time showed that episodic memory impairment (i.e., amnesia) is usually the earliest and most salient aspect of the AD dementia syndrome. These findings were consistent with neuropathologic studies that showed extensive AD pathology occurs earliest in medial temporal lobe (MTL) structures (e.g., hippocampus, entorhinal cortex) important for episodic memory (Hyman et al., 1984). The memory deficit was shown to reflect an inability to effectively encode and store new information since patients with very early AD were particularly impaired on measures of delayed recall (i.e., have abnormally rapid forgetting), exhibited an abnormal serial position effect with attenuation of the primacy effect (i.e., recall of words from the beginning of a list), and remained impaired even if retrieval demands were reduced by the use of recognition testing (e.g., Delis et al., Reference Delis, Massman, Butters, Salmon, Cermak and Kramer1991).
Semantic encoding was found to be less effective in improving the episodic memory performance of patients with AD than normal elderly individuals (Buschke, Sliwinski, Kuslansky, & Lipton, Reference Buschke, Sliwinski, Kuslansky and Lipton1997). In addition, patients with AD more often produced intrusion errors (i.e., previously learned information is produced during the attempt to recall new material) on both verbal and non-verbal memory tests, presumably due to increased sensitivity to interference and/or decreased inhibitory processes (Butters, Granholm, Salmon, Grant, & Wolfe, Reference Butters, Granholm, Salmon, Grant and Wolfe1987; Jacobs, Salmon, Tröster, & Butters, Reference Jacobs, Salmon, Tröster and Butters1990). This pattern of memory deficits was shown to differ from the pattern exhibited by patients with subcortical dementia who had difficulty learning new information, but retained what was learned well and showed improved performance with retrieval aids (e.g., cueing or recognition formats) (Cummings, Reference Cummings1990). These findings provided evidence of differential roles of MTL and fronto-striatal brain structures in memory performance.
Studies also showed that, as the neuropathology of AD spreads beyond MTL structures to adjacent temporal, parietal, and frontal association cortices, several higher order cognitive abilities became affected. A deficit in language abilities (i.e., aphasia) was observed relatively early in the course of AD, with deficits in confrontation naming, verbal fluency (particularly from semantic categories), semantic categorization, and a reduced ability to recall over-learned facts (e.g., the number of days in a year) (Hodges & Patterson, Reference Hodges and Patterson1995; Nebes, Reference Nebes1989). Patients were highly consistent in the individual items they missed across different semantic memory tests that used unique modes of access and output (e.g., fluency versus confrontation naming; Chertkow & Bub, Reference Chertkow and Bub1990; Hodges, Salmon, & Butters, Reference Hodges, Salmon and Butters1992), or within the same test across serial evaluations (Norton, Bondi, Salmon, & Goodglass, Reference Norton, Bondi, Salmon and Goodglass1997).
These findings demonstrated that AD results in a true loss of semantic knowledge (i.e., general knowledge and the meanings of words) rather than only an impaired ability to retrieve information from intact semantic memory stores (also see Salmon, Heindel, & Lange, Reference Salmon, Heindel and Lange1999). A similar loss of knowledge was thought to contribute to the severe deficit patients with AD exhibited in the ability to remember past events that were successfully remembered before the onset of the disease (i.e., retrograde amnesia) (Squire, Reference Squire1987). Patients with subcortical dementia or fronto-temporal dementia, in contrast, retained semantic knowledge well, but had difficulty in systematic retrieval from semantic memory stores (Rosser & Hodges, Reference Rosser and Hodges1994; Rascovsky, Salmon, Hansen, Thal, & Galasko, Reference Rascovsky, Salmon, Hansen, Thal and Galasko2007).
Deficits in “executive” functions responsible for concurrent mental manipulation of information, concept formation, problem solving, and cue-directed behavior were found to develop in the course of AD (Bondi, Monsch, Butters, Salmon, & Paulsen, Reference Bondi, Monsch, Butters, Salmon and Paulsen1993; Lefleche & Albert, Reference Lefleche and Albert1995; Perry & Hodges, Reference Perry and Hodges1999). Attention deficits were also found to occur and were usually evident on dual-processing tasks, tasks that require the disengagement and shifting of attention, and working memory tasks that depend upon the control of attentional resources (for reviews, see Parasuraman & Haxby, Reference Parasuraman and Haxby1993; Perry & Hodges, Reference Perry and Hodges1999). Deficits in working memory were relatively mild and primarily characterized by disruption of the “central executive” with relative sparing of immediate memory (Baddeley, Bressi, Della Sala, Logie, Spinnler, Reference Baddeley, Bressi, Della Sala, Logie and Spinnler1991; Collette, Van der Linden, Bechet, Salmon, Reference Collette, Van der Linden, Bechet and Salmon1999). Executive dysfunction and deficits in attention played a less prominent role in the AD dementia syndrome than in the subcortical dementia syndrome associated with fronto-striatal dysfunction.
Several studies showed that visuospatial deficits occurred in patients with AD (for review, see Cronin-Golomb & Amick, Reference Cronin-Golomb and Amick2001), but these deficits were usually less salient than other cognitive deficits in the early stages of the disease (Storandt Botwinick, Danziger, Berg, Hughes, Reference Storandt, Botwinick, Danziger, Berg and Hughes1984). Visuospatial tasks that were sensitive to early AD often involved not only visuoperceptual and constructional aspects of performance, but also required conceptual knowledge (e.g., Clock Drawing; Rouleau, Salmon,, Butters, Kennedy, & McGuire, Reference Rouleau, Salmon, Butters, Kennedy and McGuire1992) or planning ability (e.g., Block Design).
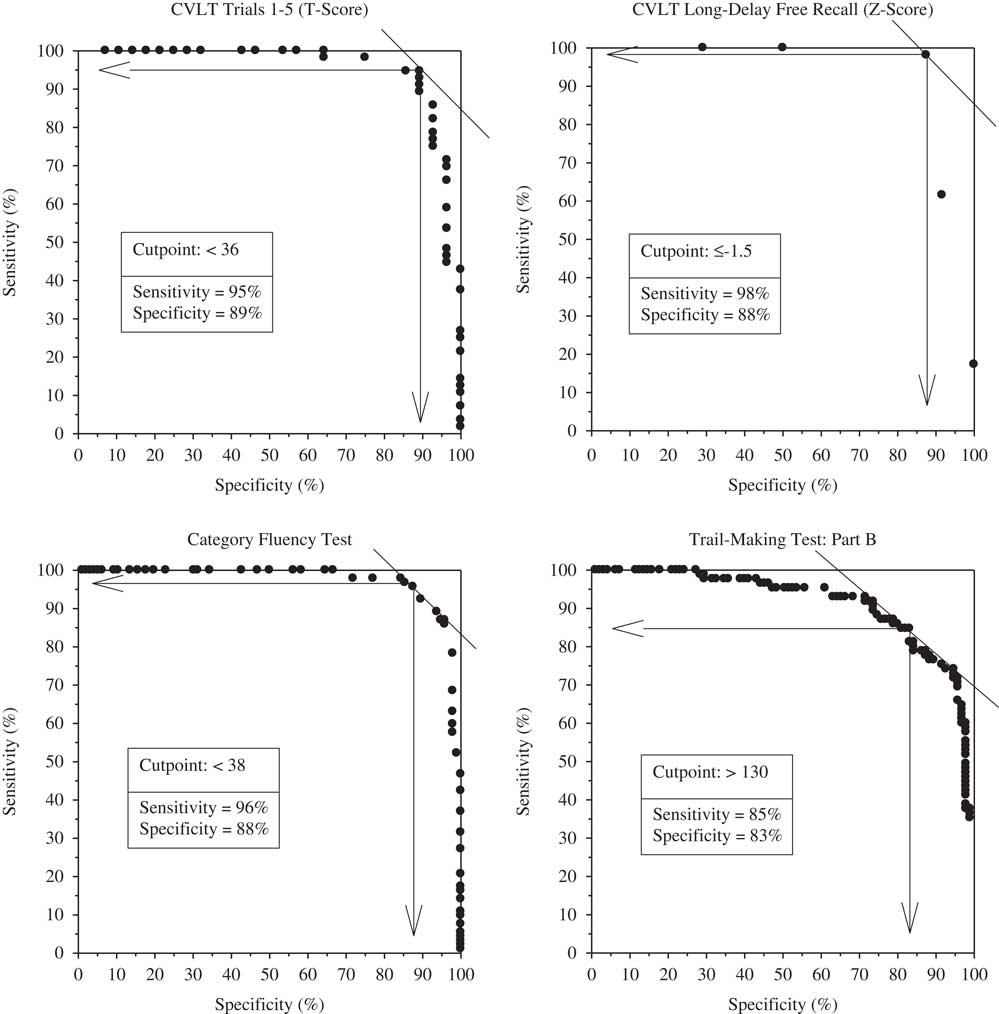
The advances made in characterizing the neuropsychological deficits associated with AD had a major impact on the ability to accurately diagnose the disease in its early stages. This clinical utility was demonstrated in a study that compared the ability of several sensitive measures of learning and memory, executive abilities, language, and visuospatial abilities to differentiate between mild AD and matched normal control subjects (Salmon et al., Reference Salmon, Thomas, Pay, Booth, Hofstetter, Thal and Kaltzman2002). Results showed excellent sensitivity and specificity for learning and delayed recall measures from the California Verbal Learning Test (CVLT) (sensitivity: 95–98%, specificity: 88–89%), category fluency (sensitivity: 96%, specificity: 88%), and Trail-Making Part B (sensitivity: 85%, specificity: 83%). The best-fitting combination of category fluency and delayed recall accurately classified 96% of the patients with AD and 93% of the control subjects (see Figure 4). This study also illustrated that the pattern of cognitive deficits typically associated with AD is characterized by prominent deficits in episodic and semantic memory, with additional, although somewhat less prominent, deficits in executive functions, visuospatial abilities, and attention.
Receiver operating characteristic curves demonstrating excellent sensitivity and specificity for the accurate diagnosis of early AD achieved with neuropsychological tests of memory (California Verbal Learning Test), language (category fluency: animals, fruits, and vegetables) and executive functions (Trail-Making Test: Part B) (adapted from Salmon et al., Reference Salmon, Thomas, Pay, Booth, Hofstetter, Thal and Kaltzman2002).

There are, however, somewhat rare instances, particularly in younger patients (e.g., less than 65 years old), where AD initially presents with dementia dominated by higher-order visual dysfunction, executive dysfunction or deficits in language. Posterior cortical atrophy (PCA) occurs when there is disproportionate atrophy and deposition of neurofibrillary tangles and neuritic plaques in the occipital cortex and posterior parietal cortex relative to other cortical association areas (Hof, Vogt, Bouras, & Morrison, Reference Hof, Vogt, Bouras and Morrison1997; Renner et al., Reference Renner, Burns, Hou, McKeel, Storandt and Morris2004). Patients with PCA usually have prominent visual agnosia (sometimes including prosopagnosia) and constructional apraxia, and exhibit many or all of the features of Balint’s syndrome, including optic ataxia, gaze apraxia, and simultanagnosia (i.e., can detect visual details of an object but cannot organize them into a meaningful whole) (Caine, Reference Caine2004; Mendez et al., Reference Mendez, Ghajarania and Perryman2002; Renner et al., Reference Renner, Burns, Hou, McKeel, Storandt and Morris2004). PCA is associated with posterior cortical hypometabolism with particular involvement of the dorsal visual stream (Nestor, Caine, Fryer, Clarke, & Hodges, Reference Nestor, Caine, Fryer, Clarke and Hodges2003), and with a posterior distribution of amyloid deposition revealed by positron emission tomography (PET) imaging using Pittsburgh compound-B ([11C]-PIB) (Tenovuo, Kemppainen, Aalto, Nagren, & Rinne, Reference Tenovuo, Kemppainen, Aalto, Nagren and Rinne2008).
A frontal variant of AD was identified in a subgroup of patients with autopsy-confirmed AD who initially presented with disproportionately severe deficits on neuropsychological tests of frontal lobe functioning (Johnson, Head, Kim, Starr, & Cotman, Reference Johnson, Head, Kim, Starr and Cotman1999). These patients had a significantly higher burden of neurofibrillary tangles, but not neuritic plaques, in the frontal cortex than a matched group of patients with a typical clinical presentation of AD. A subset of patients with primary progressive aphasia (PPA) was found to have AD pathology. These patients usually presented with logopenic PPA (PPA-L), which is characterized by hesitant, grammatically correct speech and spared language comprehension (Gorno-Tempini et al., Reference Gorno-Tempini, Dronkers, Rankin, Ogar, Phengrasamy, Rosen and Miller2004). PPA-L is most often associated with AD pathology disproportionately distributed in language-related cortical areas (Mesulam et al., Reference Mesulam, Wicklund, Johnson, Rogalski, Leger, Rademaker and Bigio2008).
The existence of these AD “variants” has complicated the clinical and neuropsychological differentiation of AD from other neurodegenerative diseases that may have a different underlying focal pathology such as frontotemporal lobe dysfunction (FTLD), dementia with Lewy bodies (DLB), or PPA. However, considerable work has been done to identify how the neuropsychological presentations of these disorders differs from that of typical AD, and this information has been incorporated into the most recent clinical diagnostic criteria for behavioral variant FTLD (Rascovsky et al., Reference Rascovsky, Hodges, Knopman, Mendez, Kramer, Neuhaus and Miller2011), DLB (McKeith et al., Reference McKeith, Boeve, Dickson, Halliday, Taylor, Weintraub and Kosaka2017), and PPA (Gorno-Tempini et al., Reference Gorno-Tempini, Hillis, Weintraub, Kertesz, Mendez, Cappa and Grossman2011).
During the 1990s and early 2000s, important advances were also made in identifying genetic risks for AD. Mutations on three separate genes were identified in large families that displayed an autosomal dominant inheritance pattern of an early-onset form of AD (i.e., onset generally before the age of 60): the amyloid precursor protein gene on chromosome 21, the presenilin 1 gene on chromosome 14, and the presenilin 2 gene on chromosome 1 (for review, see Bird, Reference Bird1999). These forms of familial AD are rare and account for only approximately 1 to 2% of all cases of the disease. A far more common genetic risk factor for sporadic, late-onset AD was identified as the type ε4 allele of the gene for apolipoprotein E (APOE), a low density lipoprotein cholesterol carrier (Strittmatter et al., Reference Strittmatter, Saunders, Schmechel, Pericak-Vance, Enghild, Salvesen and Roses1993). Located on chromosome 19, the APOE ε4 allele was found to be present in 50 to 60% of patients with AD (compared to 20 to 25% of healthy older adults), regardless of whether or not they have a family history of dementia (Strittmatter, et al., Reference Strittmatter, Saunders, Schmechel, Pericak-Vance, Enghild, Salvesen and Roses1993). Unlike the genes associated with early-onset familial AD, the APOE ε4 allele is not deterministic, but confers an approximately three-fold risk of developing AD if one copy of the ε4 allele is present, and an eight-fold risk if two copies are present (Katzman & Kawas, Reference Katzman and Kawas1994).
The identification of the APOE ε4 risk led to a new approach to examining potential decrements in learning and memory during a “preclinical” phase of AD. The performance of non-demented older adults who have an increased risk for developing the disease due to an APOE ε4 genotype could be compared to that of individuals who do not have this risk factor with the presumption that more individuals with the ε4 genotype are in a preclinical stage of the disease. In one such study, Bondi, Salmon, Galasko, Thomas, and Thal (Reference Bondi, Salmon, Galasko, Thomas and Thal1999) compared the neuropsychological test performances of non-demented elderly individuals with or without at least one APOE ε4 allele. Although the groups did not differ significantly in age, education, or global cognitive status, the ε4+ subjects performed significantly worse than the ε4− subjects on measures of delayed recall, but not on tests of other cognitive abilities.
Cox proportional hazards analysis showed that APOE ε4 status and measures of delayed recall were significant independent predictors of subsequent progression to AD, suggesting that poor recall is an early sensitive neuropsychological marker of AD and not a cognitive phenotype of the ε4 genotype (also see Bondi et al., Reference Bondi, Salmon, Monsch, Galasko, Butters, Klauber and Saitoh1995; Petersen et al., Reference Petersen, Smith, Ivnik, Tangalos, Schaid, Thibodeau and Kurland1995; Reed et al., Reference Reed, Carmelli, Swan, Breitner, Welsh, Jarvik and Auwerx1994). Although ApoE remains the most potent susceptibility gene, the advent of genome wide association studies have identified 25 loci known to associate with late-onset sporadic AD, and the advent of polygenic risk scores are now available and will further refine our understanding of genetic contributions to AD progression (for review, see Sims & Williams, Reference Sims and Williams2016).
THE 2000s: “MILD COGNITIVE IMPAIRMENT”
Although in the 1990s a few investigators had begun to systematically study individuals at risk for dementia to determine whether cognitive declines could be detected before diagnosis (Bondi et al., Reference Bondi, Monsch, Galasko, Butters, Salmon and Delis1994, Reference Bondi, Salmon, Galasko, Thomas and Thal1999; La Rue, Matsuyama, McPherson, Sherman, & Jarvik, Reference La Rue, Matsuyama, McPherson, Sherman and Jarvik1992; Small, Fratiglioni, Viitanen, Winblad, & Bäckman, Reference Small, Fratiglioni, Viitanen, Winblad and Bäckman2000; Snowdon et al., Reference Snowdon, Kemper, Mortimer, Greiner, Wekstein and Markesbery1996), following the turn of this century, the focus of the field heavily shifted to the study of prodromal stages of AD that precede the full-blown dementia syndrome. Characterization of such early phases was largely crystallized by Ron Petersen, Glenn Smith, and colleagues from the Mayo Clinic who introduced of the concept of “mild cognitive impairment” (MCI) (Petersen et al., Reference Petersen, Smith, Waring, Ivnik, Tangalos and Kokmen1999).
MCI was defined as a condition in which individuals experience memory loss to a greater extent than one would expect for age, yet do not meet criteria for dementia. The specific clinical criteria for MCI they originally put forth were: (1) subjective memory complaint, (2) objective memory impairment for age, (3) relatively preserved general cognition, (4) essentially intact activities of daily living, and (5) not demented (Petersen et al., Reference Petersen, Smith, Waring, Ivnik, Tangalos and Kokmen1999). This classification scheme was subsequently broadened to include “amnestic MCI” or “non-amnestic MCI” subtypes, and “single domain” or “multiple domain” conditions to indicate the number of cognitive domains affected (Petersen, Reference Petersen2004; Winblad et al., Reference Winblad, Palmer, Kivipelto, Jelic, Fratiglioni, Wahlund and Petersen2004). It was proposed that these MCI subtypes correspond to various etiologies, with “amnestic MCI” being most indicative of AD and “non-amnestic MCI” suggesting other neurodegenerative conditions such as FTLD or DLB (Petersen & Morris, Reference Petersen and Morris2005; see also Smith & Bondi, Reference Smith and Bondi2013, for review).
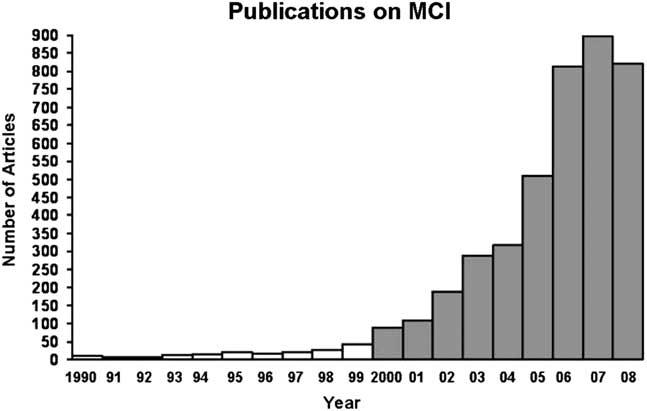
With the advent of these new criteria, the study of MCI became widespread during the 2000s. To illustrate this increasing attention and productivity, Petersen and colleagues (Reference Petersen2009) noted that in 1999 fewer than 50 papers were published in the medical literature on the topic of MCI, whereas by 2007, this number approached 900 peer-reviewed studies in that year alone (see Figure 5). He rightly concluded that the increased awareness and study of MCI had been extremely valuable for the field by enhancing our understanding of the early neuropsychological manifestations of AD and improving the ability to identify those at risk for progression to dementia.
A representative number of publications with the search term “mild cognitive impairment” in the title or abstract from 1990 through part of 2008. Note the exponential rate of increase in the numbers of publications during the 2000s (from Petersen et al., Reference Petersen, Knopman, Boeve, Geda, Ivnik, Smith and Jack2009).

Detection and characterization of prodromal AD continued to be a vibrant area of research moving into the 2010s. In 2011, the National Institute on Aging and Alzheimer’s Association (NIA-AA) published updated diagnostic guidelines for MCI (Albert et al., Reference Albert, DeKosky, Dickson, Dubois, Feldman, Fox and Phelps2011) and introduced research criteria for “preclinical” AD (Sperling et al., Reference Sperling, Aisen, Beckett, Bennett, Craft, Fagan and Phelps2011). The new guidelines for MCI largely retained the criteria developed by Petersen and colleagues, but expanded the subjective cognitive complaint criterion to allow the complaint to come from either the patient, an informant or a skilled clinician, and incorporated the use of biomarkers into the diagnosis (discussed below). Research began on the potential of subjective cognitive complaints alone to accurately signal the development of underlying AD pathology (for review, see Jessen et al., Reference Jessen, Amariglio, van Boxtel, Breteler, Ceccaldi and Chételat2014). Criteria for “preclinical” AD were developed to identify at-risk individuals at a stage of disease when they were still considered “asymptomatic” (i.e., had no significant cognitive impairment in the presence of one or more positive biomarkers for AD).
Although the criteria for MCI have been widely adopted, recent research has demonstrated limitations in the way the criteria were operationalized for clinical trials (e.g., Petersen et al., Reference Petersen, Thomas, Grundman, Bennett, Doody, Ferris and Thal2005) and large-scale natural history studies (e.g., the Alzheimer’s Disease Neuroimaging Initiative or ADNI; Weiner et al., Reference Weiner, Veitch, Aisen, Beckett, Cairns, Green and Trojanowski2013). These studies operationalized MCI as subjective complaints about memory, normal performance on simple cognitive screens, marginal memory ratings on scales based on clinical judgment, and impaired performance on a single memory test. Unfortunately, this method appears to be highly susceptible to false positive diagnostic errors (Bondi et al., Reference Bondi, Edmonds, Jak, Clark, Delano-Wood, McDonald and Salmon2014; Clark et al., Reference Clark, Delano-Wood, Libon, McDonald, Nation, Bangen and Bondi2013; Edmonds, Delano-Wood, Clark, et al., Reference Edmonds, Delano-Wood, Clark, Jak, Nation, McDonald and Bondi2015).
This susceptibility was demonstrated by Edmonds, Delano-Wood, Clark, et al. (Reference Edmonds, Delano-Wood, Clark, Jak, Nation, McDonald and Bondi2015) who applied cluster-analytic statistical techniques to the neuropsychological test scores of participants in the ADNI cohort who had been classified as MCI using the conventional criteria. Despite their MCI diagnosis, approximately one-third of these participants performed within normal limits on this more extensive cognitive testing and showed a low rate of progression to dementia. Given these limitations in the conventional diagnostic criteria, Jak, Bondi, and colleagues (Jak et al., Reference Jak, Bondi, Delano-Wood, Wierenga, Corey-Bloom, Salmon and Delis2009, Bondi et al., Reference Bondi, Edmonds, Jak, Clark, Delano-Wood, McDonald and Salmon2014) developed an actuarial neuropsychological diagnostic method to identify individuals with MCI. Rather than using a single memory test, a diagnosis of MCI is established on the basis of scores achieved on multiple objective neuropsychological tests that assess a range of cognitive domains without reference to subjective complaints or clinical judgment. This actuarial method was shown to produce greater diagnostic stability than the conventional method (i.e., individuals classified as MCI did not revert to “normal” cognition after 1 year; Jak et al., Reference Jak, Bondi, Delano-Wood, Wierenga, Corey-Bloom, Salmon and Delis2009), and revealed stronger relationships between cognition, biomarkers, and rates of progression to dementia in patients classified as MCI in this way (Bondi et al., Reference Bondi, Edmonds, Jak, Clark, Delano-Wood, McDonald and Salmon2014).
THE 2010s: THE ERA OF BIOMARKERS
Over the past 20 years great progress was made in identifying in vivo biological markers of AD. Several investigators refined the ability to detect and measure cerebrospinal fluid levels of Aβ (the main constituent of the plaque) and tau protein (a constituent of the neurofibrillary tangle) that were indicative of AD pathology in the brain. Klunk and colleagues (see Mathis et al., Reference Mathis, Wang, Holt, Huang, Debnath and Klunk2003) developed Pittsburgh compound-B ([11C]-PIB), an agent that binds to Aβ, for use with PET imaging to reveal deposition of amyloid in the brain. Tau-binding agents that can be used with PET imaging have also been recently developed (for review, see Brosch, Farlow, Risacher, & Apostolova, Reference Brosch, Farlow, Risacher and Apostolova2017).
Neuroimaging measures of hippocampal, cortical, and general brain atrophy were developed and applied to detect early neurodegenerative changes associated with AD (for review, see Frisoni, Fox, Jack, Scheltens, & Thompson, Reference Frisoni, Fox, Jack, Scheltens and Thompson2010). Other advanced structural and functional neuroimaging methodologies, including resting-state functional MRI and diffusion tensor imaging, have been used to detect pathological changes associated with AD and to create algorithms for classifying AD and MCI (for review, see Rathore, Habes, Iftikhar, Shacklett, & Davatzikos, Reference Rathore, Habes, Iftikhar, Shacklett and Davatzikos2017). All of these biomarkers have greatly increased the accuracy with which AD pathology in the brain can be detected before the onset of cognitive symptoms, and improved the ability to differentiate AD from other pathologies that lead to dementia.
In the current decade, several large-scale longitudinal studies have examined the relationship between various AD biomarkers and the development of cognitive decline and dementia (e.g., ADNI, Australian Imaging, Biomarkers, and Lifestyle study). Based on results from these studies, Jack and colleagues (Reference Jack, Knopman, Jagust, Shaw, Aisen and Weiner2010) proposed a hypothetical model of dynamic biomarker changes in the development of AD. Their model, consistent with the amyloid cascade hypothesis, proposed that amyloid deposition related to abnormal processing of the amyloid precursor protein (i.e., amyloidosis) drives the formation of abnormal tau aggregates. This in turn leads to tangle-mediated neuronal injury and neurodegeneration, which then produces cognitive and functional impairment (see Jack et al., Reference Jack, Knopman, Jagust, Shaw, Aisen and Weiner2010, Reference Jack, Knopman, Jagust, Petersen, Weiner, Aisen and Trojanowski2013, for discussion).
Many biomarker studies align with this temporal sequence of pathophysiologic changes, particularly in early-onset autosomal dominant mutation carriers (e.g., Bateman et al., Reference Bateman, Xiong, Benzinger, Fagan, Goate, Fox and Morris2012). The model has been very influential in the development of treatment strategies for AD because it posits that, if the preclinical build-up of amyloid can be blocked or built-up, amyloid can be cleared and the cascade of events that leads to cognitive decline and dementia can be prevented (for review, see Musiek & Holtzman, Reference Musiek and Holtzman2015). The hypothesis also provided the framework for revised diagnostic criteria for AD (McKhann et al., Reference McKhann, Knopman, Chertkow, Hyman, Jack, Kawas and Phelps2011), MCI (Albert et al., Reference Albert, DeKosky, Dickson, Dubois, Feldman, Fox and Phelps2011), and preclinical AD (Sperling et al., Reference Sperling, Aisen, Beckett, Bennett, Craft, Fagan and Phelps2011).
Despite its wide influence, there is increasing evidence that calls the amyloid cascade hypothesis into question, especially with regard to its invariant temporal sequence of pathological events (Drachman, Reference Drachman2014). Several studies, for example, have shown that neurodegeneration (measured by tau biomarkers or neuroimaging measures of atrophy) can occur before amyloidosis in individuals with prodromal AD (Braak, Zetterberg, Del Tredici, & Blennow, Reference Braak, Zetterberg, Del Tredici and Blennow2013; Knopman et al., Reference Knopman, Jack, Wiste, Weigand, Vemuri, Lowe and Petersen2013; Ryan et al., Reference Ryan, Keihaninejad, Shakespeare, Lehmann, Crutch, Malone and Fox2013; Sheline et al., Reference Sheline, Morris, Snyder, Price, Yan, D’Angelo and Mintun2010; Wirth et al., Reference Wirth, Madison, Rabinovici, Oh, Landau and Jagust2013). Neurodegeneration in the face of normal amyloid levels was evident in 23% of the original sample of Jack et al. (Reference Jack, Knopman, Jagust, Shaw, Aisen and Weiner2010) (and in an even higher percentage in Edmonds, Delano-Wood, Galasko, et al., Reference Edmonds, Delano-Wood, Galasko, Salmon and Bondi2015). Axonal injury (Ryan et al., Reference Ryan, Keihaninejad, Shakespeare, Lehmann, Crutch, Malone and Fox2013) and tau lesions in late-myelinating regions (Braak et al., Reference Braak, Thal, Ghebremedhin and Del Tredici2011) have been shown to predate amyloid deposition in prodromal AD.
In addition, a growing number of studies have shown that cognitive measures can be as sensitive as physical biomarkers in predicting progression to dementia (Gomar et al., Reference Gomar, Conejero-Goldberg, Davies and Goldberg2014; Heister et al., Reference Heister, Brewer, Magda, Blennow and McEvoy2011; Jedynak et al., Reference Jedynak, Lang, Liu, Katz, Zhang and Wyman2012; Landau et al., Reference Landau, Harvey, Madison, Reiman, Foster and Aisen2010; Richard, Schmand, Eikelenboom, Van Gool; Alzheimer’s Disease Neuroimaging Initiative, Reference Richard, Schmand, Eikelenboom and Van Gool2013). Taken together, these findings strongly suggest that the neurodegeneration of AD may not depend upon prior amyloidosis (Knopman et al., Reference Knopman, Jack, Wiste, Weigand, Vemuri, Lowe and Petersen2013, but cf. Jack, Knopman, et al., Reference Jack, Knopman, Chetelat, Dickson, Fagan, Frisoni and Vos2016).
Our prior work (Edmonds, Delano-Wood, Galasko, et al., Reference Edmonds, Delano-Wood, Galasko, Salmon and Bondi2015) in this area confirms that biomarker development in most individuals with preclinical/prodromal AD does not follow the temporal order proposed by the amyloid cascade hypothesis. We have shown that cognitively normal individuals who later progressed to MCI or AD, and had only one abnormal biomarker at baseline, were most likely to have neurodegeneration (i.e., P-tau positivity) as that abnormal biomarker rather than either amyloidosis alone or subtle cognitive deficit alone. In fact, neurodegeneration in isolation was 2.5 times more common than amyloidosis alone.
Jack, Bennett, and colleagues (Reference Jack, Bennett, Blennow, Carrillo, Feldman, Frisoni and Dubois2016) have recently acknowledged these and similar findings and proposed a more descriptive classification scheme for AD biomarkers that is agnostic to the temporal ordering of mechanisms underlying AD pathogenesis. This new model, known as the A/T/N system (“A” refers to Aβ, “T” to tau, and “N” to neurodegeneration), makes no assumptions about temporal ordering of biomarkers or their putative causal relationships. This “agnosticism” concurs with the notion of a simple tallying of biomarker risks as previously suggested by Edmonds, Delano-Wood, Galasko, et al. (Reference Edmonds, Delano-Wood, Galasko, Salmon and Bondi2015).
Such a dramatic shift away from the strictures of the amyloid cascade model toward a more equipotential conceptualization of AD biomarker risks espoused by our tally system and by the A/T/N classification system fits well with a continuum hypothesis proposed by Braak and colleagues. An original Braak staging theory proposed that progression of neurofibrillary tangle pathology proceeds along well-defined predilection sites beginning in the MTL and then expands to adjacent association cortices and beyond (Braak & Braak, Reference Braak and Braak1991). Amyloid plaque pathology, in contrast, accumulates more diffusely across neocortex.
This theory was recently updated to suggest that the pathogenic process actually starts with the formation of pre-tangle material in the lower brainstem with the first visible pathologic changes occurring in the locus coeruleus (Braak et al., Reference Braak, Thal, Ghebremedhin and Del Tredici2011). Tangle pathology then spreads (possibly through cell-to-cell propagation; Iba et al., Reference Iba, McBride, Guo, Zhang, Trojanowski and Lee2015) to MTL through specific projections from the locus coeruleus. It is postulated that this begins well before amyloidosis. Braak and Del Tredici (Reference Braak and Del Tredici2015) proposed that the initial tau pathology in locus coeruleus and its axonal projections may not result in outright neuronal death, but may restrict neuronal function. Thus, a central role of neuropsychology in the coming decades may be to provide sophisticated measurement of functionality of affected neural systems in preclinical/prodromal AD.
Critics of the continuum theory argue that tau aggregation confined to brainstem structures and MTL, in the context of little to no amyloid deposition, should be considered an independent pathological process that is not integral to the developmental continuum of sporadic AD. They have termed this condition primary age-related tauopathy (PART; Crary et al., Reference Crary, Trojanowski, Schneider, Abisambra, Abner, Alafuzoff and Nelson2014). In this view, the pathological diagnosis of AD requires the presence of amyloid pathology. Braak and Del Tredici (Reference Braak and Del Tredici2014) counter this argument by suggesting that amyloid plaques may develop after neurofibrillary tangle pathology develops in sites associated with AD (e.g., MTL); therefore, the “absence of Aβ deposits is not an adequate rationale for excluding tau-only cases from the developmental spectrum of the AD-related process.” They further argue that requiring a minimum threshold level of amyloid deposition for a neuropathologic diagnosis of AD (as in the PART criteria) may be justified only when applied in cases with clinically evident dementia, but not when applied to non-demented individuals.
As we move toward the end of the current decade, it is clear that the dogma that “amyloidosis is AD” is giving way to a broader conceptualization of the disease. This is evident in the adoption of biomarker staging systems that are agnostic to the temporal order of their occurrence (e.g., a tally system or the A/T/N system), and with the acceptance of new evidence that brainstem tauopathy and its propagation to the MTL may occur before amyloidosis associated with late-onset sporadic AD. This new understanding of AD may drive fundamental shifts in biomarker strategies, drug discovery, and therapeutics.
THE FUTURE
Neuropsychology has played a critical role in characterizing the cognitive changes associated with AD and related dementing disorders. This has improved the ability to accurately diagnose AD and differentiate it from other dementing disorders, to identify subtle cognitive changes that occur in the preclinical/prodromal phase of disease, and to track progression of the disease over the aging-MCI-AD continuum. Recent advances in AD biomarker development will alter this role. Increasingly, diagnosticians and investigators will be asked to use an array of available biomarkers to identify the neuropathologic determinants underlying cognitive changes within a given individual, and to detect neuropathology in its earliest stages before the onset of significant cognitive change.
That is not to say, however, that neuropsychology will cease to play an important role in dementia assessment and research. Regardless of the underlying pathology, it remains a critical function to identify the onset and nature of the earliest cognitive deficits that might impact someone’s life, to be able to predict the course of cognitive decline, and to measure the cognitive outcome of future treatments. These functions will likely be enhanced by integrating biomarker information into assessments. The use of such a “precision medicine” approach might bring increased specificity to the study of dementia in the future.
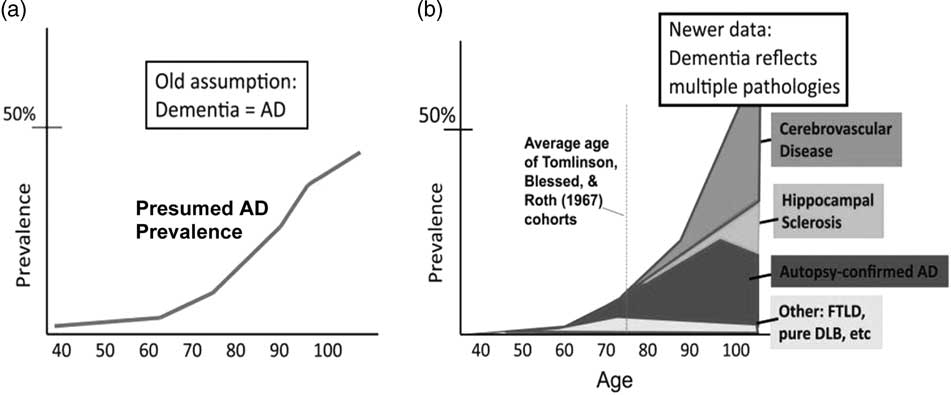
It has also become clear that, as age increases, there is increasing heterogeneity in the neuropathology underlying what is clinically diagnosed as “AD dementia.” Nelson and colleagues (Reference Nelson, Head, Schmitt, Davis, Neitner, Jicha and Scheff2011) showed that the prevalence of AD pathology increases with age but reaches a plateau at approximately age 90; however, the prevalence of dementia and other pathologies, such as cerebrovascular disease or hippocampal sclerosis (arteriolosclerosis more generally), continue to increase with age (see Figure 6). This observation suggests that, in some cases, “AD dementia” appears only following the addition of other pathologies to a sub-threshold level of AD pathology. Such pathological heterogeneity leads to neuropsychological heterogeneity, making dementia characterization and differential diagnosis more difficult.
Nelson et al.’s (Reference Nelson, Head, Schmitt, Davis, Neitner, Jicha and Scheff2011) contrasting depictions of the epidemiology of dementia. Panel (a) is the schematic representation of the prevailing view of Alzheimer neuropathology by age, whereas panel (b) depicts distinct brain diseases other than AD that may contribute to cognitive impairment in late life (adapted from Nelson et al., Reference Nelson, Head, Schmitt, Davis, Neitner, Jicha and Scheff2011).

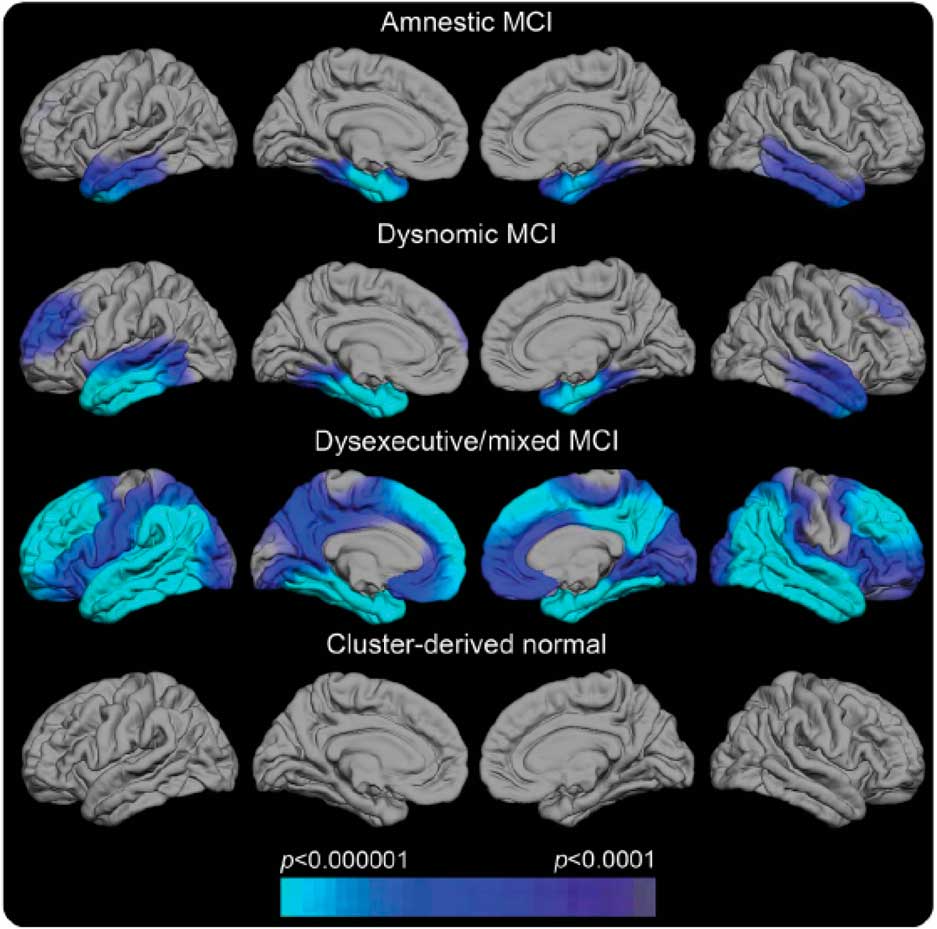
In the future, a precision medicine approach will allow multiple biomarkers to target distinct pathologies to show which pathologies are present, a genetic analysis will allow polygenic risk for various disorders to be assessed, and neuropsychological assessment will identify distinct patterns of deficits that reflect the differential impact of distinct pathologies on the dementia syndrome. Movement toward this goal is illustrated in a recent study which showed that individuals diagnosed as amnestic MCI in the ADNI cohort had great heterogeneity in the pattern of cognitive deficits they exhibited and that their deficits coincided well with specific regions of cortical thinning on neuroimaging (see Figure 7; Edmonds et al., Reference Edmonds, Eppig, Bondi, Leyden, Goodwin, Delano-Wood and McDonald2016). These results demonstrate the potential utility of a combination of neuropsychological assessment and neuroimaging biomarkers to help explain a heterogeneous presentation of prodromal AD.
Regional cortical thickness maps of the left and right lateral and medial pial surfaces for each neuropsychological MCI subtype relative to normal control (NC) participants (Edmonds et al., Reference Edmonds, Eppig, Bondi, Leyden, Goodwin, Delano-Wood and McDonald2016). The scale indicates group differences in cortical thickness at p<.0001. The cyan/blue shades represent areas where the MCI subgroup has significantly thinner cortex than the NC group. Cluster-derived normal (CDN)=those participants who performed normally across the neuropsychological tests but whom ADNI diagnosed as MCI. Their maps show no areas of cortical thinning relative to the NC group, suggesting they are false-positive diagnostic errors. Our prior work showing the CDN subgroup to have normal CSF AD biomarkers and low progression rates adds to the inference that they received false-positive MCI diagnoses (Bondi et al., Reference Bondi, Edmonds, Jak, Clark, Delano-Wood, McDonald and Salmon2014).

Neuropathological heterogeneity in AD could also have important implications for future therapeutic approaches to the disease. Given the shift away from the amyloid cascade model toward a more equipotential conceptualization of AD, it is not surprising that the recent singular focus on anti-amyloid treatments has led to disappointing results (Cummings, Morstorf, & Zhong, Reference Cummings, Morstorf and Zhong2014). In an equipotential model of AD, other aspects of AD related pathology may already exist, continue to develop, and adversely affect cognition even if amyloid pathology is removed. If patients in anti-amyloid trials are positive for significant levels of amyloid, the anti-amyloid agent engages and clears amyloid, yet there is no clinical or cognitive benefit, it is reasonable to presume that pathology other than amyloid needs to be targeted.
Since tau pathology is more firmly associated with clinical and cognitive decline than is amyloid pathology, and may accumulate in susceptible regions earlier than that of amyloid, tau-altering pharmacologic interventions would seem worthwhile. Specific therapeutics may also be needed for other underlying pathologies (e.g., arteriolosclerosis, blood–brain barrier dysfunction, α-synuclein) that could be interacting with abnormal amyloid and tau in older individuals with sporadic “AD dementia.” Such agents could be used in a “precision medicine” context, where aberrant biomarkers coupled with a specific pattern of neuropsychological deficits could specify a particular treatment regimen within a prevention framework. Such a framework would also be accommodative of the specter of multiple biomarker abnormalities occurring concurrently.
SUMMARY
Over the past century since Alzheimer’s original publication, we have witnessed an explosion of work in the neuropsychology of dementia, and we have much work yet to complete. To borrow from another prominent psychologist who spoke of his perspective to better understand schizophrenia nearly 2 decades ago, Irving Gottesman (Reference Gottesman2001) pointedly suggested that no discipline committed to understanding any of the major disorders (insert Alzheimer’s disease in this example) has a monopoly on the amounts of uncertainty that remain for current and future generations of investigators. By joining forces across disciplines and assembling the most certain and important facts, investigators can launch new initiatives not previously imagined. Such an effort will be required to solve the complex puzzle of Alzheimer’s disease.
ACKNOWLEDGMENTS
This work was supported by National Institutes of Health grants P50 AG05131 (M.W.B., D.P.S.), R01 AG049810 (M.W.B.) and K24 AG026431 (M.W.B.), and the U.S. Department of Veterans Affairs Clinical Sciences Research and Development Service (Career Development Award-2 1IK2 CX001415-01A1 to E.C.E.). Dr. Salmon serves as a consultant for Bristol-Myers Squibb. Dr. Bondi serves as a consultant for Novartis and Eisai and receives royalties from Oxford University Press. The other authors report no disclosures.