Late-onset infections continue to cause substantial morbidity and mortality in neonatal intensive care units (NICUs),Reference Kochanek, Xu, Murphy, Miniño and Kung 1 – Reference Stoll, Hansen and Adams-Chapman 3 increasing length of stay and costs.Reference Donovan, Sparling and Lake 4 Although many studies have examined the impact of environmental factors on nosocomial infections, the cornerstone of which is proper hand hygiene by healthcare workers,Reference Lankford, Zembower, Trick, Hacek, Noskin and Peterson 5 the role of room configuration is less well defined. Many pathogens are transmitted via surfaces and fomites,Reference Ulrich, Quan, Zimring, Joseph and Choudhary 6 and multipatient rooms are more difficult to decontaminate because of their greater number of surfaces and higher traffic. These concerns contributed to single-patient rooms becoming the standard design in healthcare facilities. 7 , Reference Joseph 8 Although improvements in air quality and nosocomial infections have been attributed to the change from open-unit to single-patient room facilities,Reference Joseph 8 , Reference Domanico, Davis, Coleman and Davis 9 these NICU bed configurations have not been directly compared contemporaneously. Our NICU, which has both single-patient and open-unit beds, provided an opportunity to test the hypothesis that infants in single-patient rooms have a lower risk of methicillin-resistant Staphylococcus aureus (MRSA) colonization, late-onset sepsis, and death.
METHODS
Study Location
The NICU at St. Louis Children’s Hospital has 73 beds that can flex to 81 beds during times of high census. Thirty-six beds are in single-patient rooms while 3 open-unit areas have 9 or 14 beds, with flexible beds organized in an 8-bed open-unit model.
Open-unit and single-patient rooms were staffed by the same groups of nurses, residents, nurse practitioners, fellows, and attending physicians. Patients were assigned to 1 of 4 multidisciplinary teams. Nurse-to-patient staffing ratios are 1:1–3, depending on illness severity, and all patients in a nursing assignment are in the same bed configuration. Staffing was similar across bed configurations. Bed assignment was based on staffing and bed availability without regard to diagnosis, acuity, or bed configuration.
Patients
All patients who resided in the NICU from July 1, 2009, to November 30, 2011, were included, regardless of admission or discharge date. The study was approved by the Washington University Human Research Protection Office.
Data Acquisition
Billing and coding data from the hospital management information system were retrospectively queried for the study interval to determine dates of birth, admission, discharge and death, room location, sex, race, ethnicity, insurance type (Medicaid, private, uninsured), as well as International Statistical Classification of Disease, Ninth Revision, diagnosis codes that contain gestational age and birthweight information. Additionally, data were gathered from the hospital infection control service to identify all patients colonized with MRSA during the study period and the rates of hand hygiene compliance during patient encounters. Apgar score, temperature on admission, and initial blood gas results were gathered from our NICU’s National Institute of Child Health and Human Development data set 10 and the Clinical Investigation Data Exploration Repository. 11 Finally, patient-specific information regarding all positive cerebrospinal fluid and blood cultures from NICU patients for the study interval was provided by the microbiology laboratory information system (Cerner Millennium).
Hospital management information system data included daily room assignments, allowing for each patient’s NICU room assignment and bed configuration type to be tracked on a day-by-day basis. Patients who transferred between open-unit and single-patient rooms had all data removed from the analyses.
MRSA Genotyping
Anterior nares swab specimen cultures were used to screen for MRSA colonization as part of routine infection control measures on admission and weekly thereafter, per institution protocol. The first MRSA recovered from each subject was frozen for future analysis. DNA was extracted from bacterial isolates using the BiOstic Bacteremia DNA Isolation Kit (MoBio Laboratories) according to the manufacturers’ directions. Repetitive sequence polymerase chain reaction was then performed as previously described, using approximately 100 ng of DNA, a Ready-to-go RAPD analysis bead (GE), and primer RW3A in a final reaction volume of 25 µL.Reference Church, Chow, Lloyd and Gregson 12 , Reference Kang and Dunne 13 The repetitive sequence polymerase chain reaction products were resolved using the Agilent 2100 Bioanalyzer, and banding patterns were analyzed using Diversilab software, version 3.4 (bioMérieux), to measure strain similarity. Isolates with similarity indices greater than 95% were considered identical.
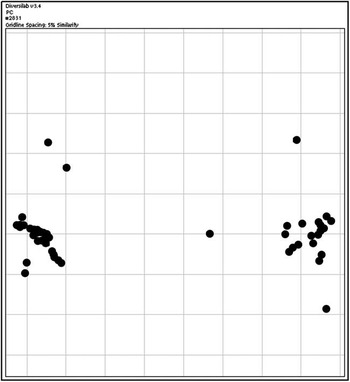
The Diversilab software compared the DNA banding pattern of each isolate to all other isolates and assembled this into a 2-dimensional scatterplot. Those with high similarity indices clustered closer than those with low similarity indices. This allowed visualization of genotype clustering within a set of isolates. 14
Barrier Precautions
All patients, regardless of MRSA colonization status, were cared for using standard precautions. In addition, infants colonized with MRSA were placed in contact isolation. These policies applied to all members of the staff, families, and visitors. No visitor restriction occurred for either group of patients. Use of alcohol foam or hand washing stations on room entry and exit is standard of care. Compliance with hand hygiene was assessed by direct observation of repeated patient encounters by members of the hospital infection control committee and included all providers. Observations of compliance occurred weekdays during the day shift and covered all areas of the NICU. A provider who exited one bed space, performed hand hygiene, and entered another bed space remained compliant as long as no other surfaces were contacted during this transition.
Definitions
Confirmed Late-Onset Sepsis
Confirmed late-onset sepsis (CLOS) was defined as a having a culture-positive bacterial infection of the blood or cerebrospinal fluid on or after 72 hours of life for which the patient was treated with antibiotics for 5 or more days.Reference Stoll, Hansen and Adams-Chapman 3 , Reference Shane, Hansen and Stoll 15 Episodes of positive bacterial cultures not meeting this definition and nonpathogenic bacteria typically considered contaminants were removed from further analysis.
Illness Severity Indices
Maximum Acuity Score
Acuity scores were based on level of care required by each patient and consisted of type and level of ventilator assistance, presence or absence of central lines, need for and frequency of laboratory draws, and patient monitoring. Scores ranged from 2 to 4 with higher scores indicating greater level of resources. For each patient, the maximum acuity score throughout his or her stay was used in the analysis.
Clinical Risk Index for Babies–II Score
The Clinical Risk Index for Babies–II (CRIB-II) score is an aggregation of clinical and laboratory data that is used to provide risk adjustment of mortality and neurologic dysfunction across institutions.Reference Gagliardi, Cavazza and Brunelli 16 – Reference Parry, Tucker and Tarnow-Mordi 18 It is a sum of scores for the combination of birthweight, gestational age, and sex; admission temperature; and base excess. Scores range from 0 to 27 with higher scores associated with higher mortality risk. For patients born after more than 32 weeks’ gestation or whose birthweights were in excess of 3,000 grams, only the temperature and base excess portions of the CRIB-II were used.Reference Filippi, la Marca and Cavallaro 19 CRIB-II scores were available for 1,128 patients. Because this was a subset of patients, multivariate regressions were performed with and without this variable, which minimally affected the significance of the models.
Mean Colonization Pressure and Average Census
Colonization pressure is the ratio of MRSA-positive patient-days to total patient-days, expressed as a percentage. The mean colonization pressure (MCP) is the arithmetic mean of this ratio over a patient’s hospitalization. The MCP was calculated for the entire unit and for the patient-specific bed configuration. Average census for the entire unit and the patient-specific bed configuration used the average census of the respective areas during the patient’s admission.
Statistical Analysis
The outcomes of time to MRSA colonization, CLOS, and combined CLOS or death were compared between patients in single-patient rooms and those in open-unit rooms. Kaplan-Meier curves yielding log-rank tests as well as univariate, bivariate, and multivariate Cox regressions were used to determine these time-dependent outcomes. Additionally, time-independent incidences of these end points were compared using χ2 tests and Fisher exact tests, where appropriate. Analysis of variance was used to determine differences between bed configurations in CRIB-II scores, 5-minute Apgar scores, average daily census, MCP, and hand hygiene compliance upon room entry and room exit. Pearson χ2 and log-rank tests with alpha values of .05 and 2-sided tests were used for statistical power calculations. Analyses were performed using SAS, version 9.3 (SAS Institute).
RESULTS
Demographic Characteristics
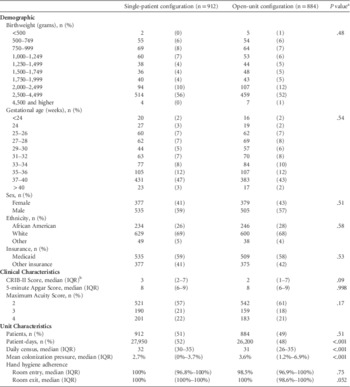
The 1,823 subjects representing 55,166 patient days were included in this analysis. Twenty-seven patients (1.5%) who transferred between single-patient and open-unit layouts were excluded from further analysis. Patients in single-patient and open-unit rooms were similar in terms of birthweight, gestational age at birth, sex, race, insurance type, and illness severity based on CRIB-II score, 5-minute Apgar score, and maximum acuity score (Table 1).
Summary of Characteristics by Bed Configuration

NOTE. CRIB-II, Clinical Risk Index for Babies; IQR, interquartile range.
a P values from χ2 and analysis of variance.
b For the CRIB-II Score, the number of patients in single-patient configuration was 563 and the number in open-unit configuration was 565.
The median daily census over the study period was significantly greater in the single-patient rooms than open-unit rooms (32 vs 31; analysis of variance P<.001). MCP was significantly smaller in the single-patient rooms (2.7% vs 3.6%; analysis of variance P<.001).
A median of 48 hand hygiene assessments upon room entry (interquartile range, 37–60) and 53 hand hygiene assessments upon room exit (42–71) per bed configuration per month were available throughout the study period. Hand hygiene compliance upon room entry did not differ significantly between staff assigned to the different bed configurations. At room exit, hand hygiene compliance was slightly higher in single-patient rooms at Q1 (100% vs 98.6%) whereas median and Q3 were 100% for both groups (analysis of variance P=.052).
MRSA
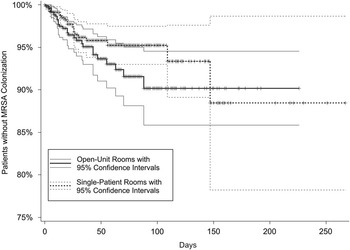
The incidence of MRSA colonization in single-patient and open-unit rooms was similar (2.1% vs 3.3%; χ2 P=.11). Figure 1 demonstrates the similarity in MRSA-free survival over time between the 2 bed configurations. Univariate Cox regression showed no difference in MRSA colonization rates between bed configurations (χ2 P=.10); this similarity persisted when controlling for demographic (birthweight, gestational age, sex, race, insurance type), patient-driven (CRIB-II score, 5-minute Apgar score, and maximum acuity), and unit-driven (average census, MCP, and hand hygiene adherence) variables (Table 2). Average daily census was the only variable to interact significantly with bed configuration in the bivariate analyses. Within the subset of patients located in single-patient rooms, each additional one patient in the average census during their hospitalization correlated with 31% greater MRSA colonization rate (hazard ratio, 1.31 [95% CI, 1.02–1.68]; P=.039). This correlation was not seen within the open-unit configuration. A Cox regression model for MRSA colonization using bed configuration and average census was not significant.
Patients without methicillin-resistant Staphylococcus aureus (MRSA) colonization by bed configuration. Data are presented as a Kaplan-Meier plot, with patients censored at death or discharge (log-rank P=.19).

Cox Proportional Hazards Model for MRSA Colonization

NOTE. Cox regression models for methicillin-resistant Staphylococcus aureus (MRSA) colonization using univariate, bivariate, and multivariate analyses of bed configuration. CRIB-II, Clinical Risk Index for Babies–II; MCP, mean colonization pressure.
a χ2 p-values are shown for bed configuration in Cox proportional hazard models.
b χ2 p-values are shown for listed covariates in bivariate Cox proportional hazard models.
c χ2 p-values are provided for bivariate model interactions, which model the effect on MRSA colonization when subgroups of 1 of the 2 covariates are selected.
The only variables to affect MRSA colonization involved hand hygiene. Lower rates of MRSA colonization of 17% (hazard ratio, 0.834 [95% CI, 0.731–0.951]; P=.0068) and 28% (hazard ratio, 0.719 [95% CI, 0.611–0.846]; P<.0001) were associated with 1% greater hand hygiene compliance on room entry or exit, respectively. This was independent of and similar across bed configurations.
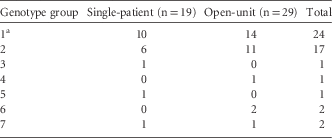
A 2-dimensional scatter plot of the MRSA genotypes (Figure 2) demonstrated that 44 (86%) of the 51 isolates clustered into 2 distinct genotypes. There was no difference in MRSA genotypes between single-patient and open-unit rooms (2-tailed Fisher exact test P=.63) (Table 3).
Scatterplot of methicillin-resistant Staphylococcus aureus (MRSA) genotype similarity plotted by Diversilab, version 3.4. Grid markings represent 5% genotypic difference. DNA banding patterns produced by repetitive sequence polymerase chain reaction are compared to construct this scatterplot, allowing visualization of genotype clustering within a set of isolates. Isolates with similar banding patterns cluster closer together than those with more divergent banding patterns.

MRSA Genotypes by Bed Configuration

NOTE. MRSA, methicillin-resistant Staphylococcus aureus.
a An additional 3 patients from genotype group 1 spent time in both bed configurations and were excluded from the analysis. Fisher exact test P=.63.
Late-onset Sepsis
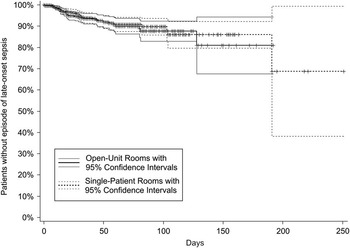
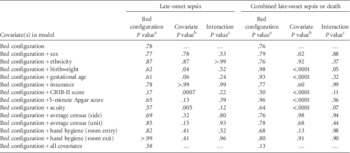
The rates of CLOS in single-patient and open-unit rooms were similar (3.9% vs 4.1%; χ2 P=.89). Coagulase-negative Staphylococcus species was the most frequent pathogen recovered from cultures in both configurations at 43% of all positive cultures. Methicillin-susceptible Staphylococcus aureus and Streptococcus agalactiae (group B streptococci) were the next most frequent gram-positive pathogens (11% and 8%, respectively) and Escherichia coli was the most frequent gram-negative pathogen (10%). Overall, 56 gram-positive and 16 gram-negative bacterial pathogens were isolated from blood and/or cerebrospinal fluid (Online Supplemental Table 1). Of the 72 patients with CLOS, 6 had more than one episode. With few patients having multiple episodes and concerns that an earlier course of sepsis and antibiotics might influence a second episode of CLOS, only the first episode was entered into the analysis. A Kaplan-Meier plot (Figure 3) demonstrates similarity of survival when controlling only for bed configuration (log-rank P=.78). This similarity holds in the univariate, bivariate, and multivariate Cox regression models when controlling for demographic, patient-driven, and unit-driven variables (Table 4). Lower birthweight and greater CRIB-II scores and acuity scores correlated with higher rates of CLOS, but only independently of bed configuration.
Patients without late-onset sepsis by bed configuration. Data are presented as a Kaplan-Meier plot, with patients censored at death or discharge (log-rank P=.78).

Cox Proportional Hazards Model for Late-Onset Sepsis and Combined Outcome of Late-Onset Sepsis or Death

NOTE. Cox regression models for late-onset sepsis and the combined outcome of late-onset sepsis or death using univariate, bivariate, and multivariate analyses of bed configuration. CRIB, Clinical Risk Index for Babies; MCP, mean colonization pressure.
a χ2 P values are shown for bed configuration in Cox proportional hazard models.
b χ2 P values are shown for listed covariates in bivariate Cox proportional hazard models.
c χ2 P values are provided for bivariate model interactions, which model the effect on outcomes when subgroups of 1 of the 2 covariates are selected.
Late-Onset Sepsis or Death
To ensure that death did not mask differences in rates of sepsis between bed configurations, a combined outcome of CLOS or death was used. The combined outcome was similar in single-patient and open-unit rooms (11.6% vs 10.8%; χ2 P=.56). This similarity also existed in the univariate, bivariate, and multivariate Cox regression models (Table 4). Lower birthweight, early gestational age, male sex, higher acuity and CRIB-II score, and lower 5-minute Apgar score correlated with greater rates of CLOS or death.
DISCUSSION
To our knowledge, this study was the first attempt to examine the association between bed configuration within a NICU and rates of MRSA colonization and CLOS using the same study period for both groups, while accounting for illness severity. Vietri et alReference Vietri, Dooley, Davis, Longfield, Meier and Whelen 20 reported similarity in MRSA colonization rates between bed configurations before and after conversion of an adult ICU from an open-unit configuration to single- or double-patient rooms. Domanico et alReference Domanico, Davis, Coleman and Davis 9 also compared intervals and found lower MRSA colonization rates in a NICU when converting from open-unit configuration to single-patient rooms. The contemporaneous comparison of the 2 bed configurations in our study minimized potential bias from changing clinical practices or practitioners.
In this analysis, single-patient rooms were not associated with reduced MRSA colonization, CLOS, or the combined outcome of CLOS or death compared with open-unit beds. The overall incidence of MRSA colonization in this study (2.7%) was similar to the 1.1%–5.6% colonization rates reported by other NICUs in the United StatesReference Gregory, Eichenwald and Puopolo 21 – Reference Song, Perencevich, Campos, Short and Singh 23 but less than the 20%–41% rates in Taiwan and Japan.Reference Huang, Chou, Su, Lien and Lin 24 , Reference Sakaki, Nishioka, Kanda and Takahashi 25 Colonization pressure was significantly higher in the open-unit configuration. Although this and insurance provider have been shown to be risk factors for MRSA colonization in and out of the NICU,Reference Fritz, Garbutt, Elward, Shannon and Storch 26 , Reference Geraci, Giuffre and Bonura 27 only the average daily census was positively associated with increasing MRSA colonization, and only in the single-patient configuration (Table 2). The only variable to significantly impact MRSA colonization rates was hand hygiene compliance upon room entry and exit; bed configuration, however, did not contribute to these models.
Rates of CLOS and the combined outcome of CLOS or death also did not differ between bed configurations. During the study, the overall rate of CLOS and the combined rate of CLOS or death were 4.0% and 11.2%, respectively. Of note, this study was performed in an era of focused efforts to decease central line–associated bloodstream infections.
The large sample size of this study and the contemporaneous housing provide the power to detect clinically significant hazard ratios for each of our outcomes. The retrospective design of this study offers perspective into the clinical impact of our results while controlling for secular changes. For all 3 of the outcomes, our sample size had greater than 80% power to detect a hazard ratio of 1.25—that is, a difference of 25% in the outcomes between bed configurations would have been detected. Although an argument can be made that any reduction in the outcomes we selected (death, sepsis) might be considered to be worth an investment in single-patient rooms, proving that room configuration plays a role in averting undesirable outcomes would require an enormous study population. For instance, a 10% reduction in MRSA colonization rates, which for this study population equates to an absolute risk reduction of 0.4% or 1 of 250 babies per month, would be detected at 80% power only with 7,984 patients studied throughout their NICU stay.
Single-patient rooms might fail to prevent MRSA colonization and CLOS for several reasons. With single-patient rooms spread further apart in space, horizontal spread of infections would seem to decrease. If, however, hand-hygiene practices are universally followed and fomites carried by healthcare workers are limited, this may reduce the effect of spreading patients out geographically. Over the course of this study, there was high hand hygiene compliance, which may have diminished the impact of bed configuration, limiting generalizability for units in which hand hygiene compliance is low. In addition, nonhorizontal spread of pathogens may contribute sufficient amounts of infectious “noise” to the data, decreasing the ability to detect the horizontal spread of infectious material. Such nonhorizontal methods include vertical transmission at birth and contact with visitors, including parents and family, which would not be expected to differ on the basis of room configuration.
Our study indicates that high census periods are positively correlated with greater MRSA colonization only in single-patient room configurations. Although bed occupancy rates have been shown to correlate positively with MRSA colonization,Reference Kaier, Meyer, Dettenkofer and Frank 28 the mechanisms leading to this configuration-specific result remain to be determined.
This study has several limitations. First, the data were collected retrospectively. However, a large prospective randomized study of this nature would be prohibitive given the constraints of patient staffing and physical space within a NICU environment. Second, although bed configuration might reduce horizontal spread of pathogens, such layouts might not mitigate other mechanisms of transfer, such as visitor-to-patient transmission or interhost transfer,Reference Carl, Ndao and Springman 29 which were not addressed. In a companion project conducted at the same time as this study, stools of 3 infants in open-unit rooms in the vicinity of 2 infants with group B streptococci sepsis, and 1 infant in the vicinity of an infant with Serratia marcescens sepsis, contained the infecting strain, suggesting that interhost spread is better detected by focusing on colonization than on culture-proven sepsis.Reference Carl, Ndao and Springman 29 Finally, our study was not designed to address culture-negative sepsis. Isolation of bona fide bloodstream pathogens is a challenge in NICUs because the volume of blood submitted for culture might be inadequate to confirm an etiologic agent.Reference Piantino, Schreiber, Alexander and Hageman 30 Identifying such cases in retrospect is difficult, and hence, we might have underestimated actionable events that occurred in either or both of the bed configurations. Using a broader definition than CLOS, however, could have overestimated sepsis events.
Considerations beyond infection have been put forth regarding choice of room configuration. Some studies demonstrate that single-patient rooms modestly improve breast-feeding initiation, are quieter, and have better air quality,Reference Domanico, Davis, Coleman and Davis 9 whereas others have highlighted the larger space requirement,Reference Shepley, Harris, White and Steinberg 31 resulting in larger NICUs, greater construction costs,Reference Chaudhury, Mahmood and Valente 32 , Reference Bartley, Olmsted and Haas 33 and longer distances traveled responding to emergencies, as well as issues with communication, patient monitoring,Reference Shepley, Harris, White and Steinberg 31 , Reference Joseph and Rashid 34 and nurse isolation.Reference Lester, Miller and Hawes 35 Although parent satisfaction scores, visitation rates, and noise levels favor single-patient rooms,Reference Shepley, Harris, White and Steinberg 31 , Reference Lester, Miller and Hawes 35 – Reference Lester, Hawes and Abar 37 parental stress and neonatal language and motor development favor open units.Reference Pineda, Neil and Dierker 38 , Reference Pineda, Stransky and Rogers 39
In conclusion, single-patient rooms did not provide protection against MRSA colonization, CLOS, and the combined outcome of CLOS or death in a NICU environment. Although single-patient rooms may have other benefits, neonates in this bed configuration were as likely as those in open-units to acquire these infections and the morbidities and mortality that come with them. In this analysis, average census positively correlated with MRSA colonization only within the single-patient room configuration. Increased vigilance is required during periods of high census, with particular attention paid to hand hygiene, the only variable that affected MRSA colonization. Further studies are warranted to assess how facility design might reduce the burden of sepsis and MRSA colonization in this high-risk population.
ACKNOWLEDGMENTS
We thank Alexis Elward, MD, and the Infection Control Committee at St. Louis Children’s Hospital for their expertise, MRSA colonization data, and hand hygiene compliance data; Rachel Frobel for the training and technical expertise in repetitive sequence polymerase chain reaction; and the St. Louis Children’s Hospital Office of Planning and Business Development for the NICU billing and coding data used in this study. Finally, none of this would be possible without the cooperation of the staff of the NICU and the families of our patients at St. Louis Children’s Hospital.
Financial support. National Institutes of Health (grant UH3 AI083265).
Potential conflicts of interest. All authors report no conflicts of interest relevant to this article.
SUPPLEMENTARY MATERIAL
To view supplementary material for this article, please visit http://dx.doi.org/10.1017/ice.2015.144