Introduction
Congenitally corrected transposition of the great arteries is a rare congenital cardiac anomaly, constituting 0.5% of all CHDs. Reference Hornung and Calder1 Congenitally corrected transposition of the great arteries is characterised by atrioventricular and ventriculoarterial discordance. Reference Kumar2 Due to its heterogeneity, management strategies for congenitally corrected transposition of the great arteries include medical management, physiologic repair, and anatomic repair. Surgical approaches can be divided into physiologic and anatomic repairs. Some patients with congenitally corrected transposition of the great arteries and without associated structural heart defects can be medically managed, avoiding surgery. Reference Van Praagh3
Anatomic repair corrects associated defects and reconfigures circulation via a double switch or Rastelli operation, positioning the morphological left ventricle as the systemic ventricle. Reference DeWeert, Lancaster and Dorfman4 This correction requires a conditioned left ventricle, which is considered present when a large ventricular septal defect or left ventricular outflow tract obstruction is present. In patients without these conditions, pulmonary artery banding may be necessary to prepare the left ventricle. Reference Kumar2 However, the double switch or atrial switch/Rastelli operation carries risks of neo-aortic dilation, coronary issues with transfer, heart block with ventricular septal defect closure, and conduit replacement or left ventricular outflow tract obstruction in the atrial switch/Rastelli. Reference Hiramatsu, Matsumura and Konuma5,Reference Imamura, Drummond-Webb and Murphy6
Physiologic repair, alternatively, addresses associated defects like ventricular septal defects or left ventricular outflow tract obstruction but maintains the morphologic right ventricle as the systemic ventricle. Reference DeWeert, Lancaster and Dorfman4 This approach can lead to systemic right ventricular dysfunction, systemic atrioventricular valve regurgitation, and eventual heart failure. Reference van Dissel, Opotowsky and Burchill7 Historically, long-term outcomes of physiologic repair have been disappointing, with progressive systemic right ventricular dysfunction, systemic atrioventricular valve regurgitation, Reference Hraska, Duncan and Mayer8–Reference McGrath, Kirklin and Blackstone11 and low survival rates. Reference Hornung and Calder1 While some advocate for anatomic repair to mitigate these risks, predicting which patients are most at risk for right ventricular dysfunction and tricuspid regurgitation is challenging. Physiologic repair may still be beneficial for older congenitally corrected transposition of the great arteries patients with well-preserved right ventricular and systemic atrioventricular valve function who are considered high-risk for anatomic repair. Reference Karl12
The initial presentation of congenitally corrected transposition of the great arteries patients often does not clearly dictate the most appropriate management strategy, partly due to the condition’s rarity and the wide range of anatomic variations. Although early intervention is crucial for some patients, others may not require any intervention throughout their lifetime. This uncertainty is especially significant in the neonate or infant congenitally corrected transposition of the great arteries patient without associated defects, where there is no consensus on the superiority of early anatomic repair over physiologic repair or a medically managed approach with regular follow-up.
Health-related quality of life is a critical factor in considering appropriate management of chronic cardiac conditions like congenitally corrected transposition of the great arteries. Treatment goals extend beyond survival to include long-term functional benefits. Health-related quality of life provides key insights into physical, emotional, and social wellbeing from the patient perspective. Data have shown that physician and patient perceptions are not always consonant. Reference Kennedy, Rehman and Johnson13–Reference Samuel, Mbah and Schaal15 Our study addresses these critical knowledge gaps by comparing health-related quality of life scores among patients undergoing anatomic repair, physiologic repair, and medical management, using a novel instrument validated at the Cleveland Clinic for adult cardiac populations. To contextualise the health-related quality of life responses, we also assessed the association between echocardiographic measures of systemic ventricular dysfunction and systemic atrioventricular valve regurgitation with patients’ perceived health-related quality of life over time.
Materials and methods
Subjects
In a previous study by Barrios and colleagues at the Cleveland Clinic, Reference Barrios, Zia and Pettersson16 a comprehensive medical review confirmed the diagnosis of 240 patients with congenitally corrected transposition of the great arteries, who were treated at our institution between 1995 and 2020. To be eligible for this study, participants had to be older than 17 years of age. Patients who had undergone a prior Fontan procedure, heart transplant, or a main procedure at another institution prior to presentation at the Cleveland Clinic were excluded from analysis. Respondents were categorised into groups according to treatment type. Medical management consisted of an expectant, non-surgical approach, which closely monitored the patient and optimised ventricular function with medications. Physiologic repair and Anatomic repair were defined following the exact criteria detailed in Barrios et al. Reference Barrios, Zia and Pettersson16 Physiologic repair was defined as any cardiac surgical operation maintaining the morphologic right ventricle as the systemic ventricle, excluding permanent pacemaker placements. Anatomic repair included either an arterial switch operation with atrial switch (double switch), arterial switch plus a hemi-Mustard/Senning procedure and bidirectional Glenn, or an atrial switch/Rastelli procedure.
Data collection and follow-up
A cross-sectional follow-up of the surviving patients from the prior 240 congenitally corrected transposition of the great arteries patient cohort was performed via patient record review and telephone follow-up using a standardised hybrid health-related quality of life questionnaire. Surviving participants were contacted by letter and followed up with between 1 to 2 weeks later by telephone. Written consent was obtained for each participant, and verbal re-consent was obtained from each subject or family during telephone follow-up. No payment or gift was provided. Responses from 50 patients were obtained.
Measurement of health-related quality of life
PROMIS-10 and MacNew are two validated questionnaires to assess health-related quality of life in patients with chronic health conditions. Reference Salim Hammoud, Gupta and McCloskey17 The PROMIS-10 is a 10-item patient-reported questionnaire assessing physical and mental health. It uses a T-score metric, where a score of 50 (out of 100) represents the average for a matched age and sex U.S. population, and scores above and below 50 represent superior or inferior mental/physical health, respectively. The MacNew questionnaire is a cardiac-specific questionnaire evaluating physical limitations, emotional function, and social function in particular cardiac disease states. A score above 5 (out of 7) signified an individual’s enhanced performance in a category, relative to peers with the same condition and age group.
Minimal clinically important difference is defined as the smallest difference in a health status measure at which patients perceive a beneficial change in their health status significant enough to influence treatment decisions or management. Reference Jaeschke, Singer and Guyatt18 Minimal clinically important difference for the PROMIS-10 has not been specifically reported in the congenitally corrected transposition of the great arteries population, but a systematic review of over 31 studies utilising PROMIS-10 found that the threshold to evaluate within-group changes or between-group changes ranges from 2 to 6 T-score points. Reference Terwee, Peipert and Chapman19 The MacNew questionnaire has been shown to have a minimal clinically important difference of 0.50 points across each scale. Reference Dixon, Lim and Oldridge20 We have previously utilised the MacNew and PROMIS-10 questionnaires in two studies examining health-related quality of life. Reference Chen, Hammoud and Ghandour21,22
To minimise overlap between the PROMIS-10 and MacNew surveys while performing a comprehensive evaluation of health-related quality of life, we utilised a novel, hybrid instrument derived from the mental and physical domains of the PROMIS-10 questionnaire and the social domain of the MacNew questionnaire. This instrument was validated at the Cleveland Clinic on multiple and different adult cardiac populations, including patients who underwent Ozaki, Ross, or mechanical aortic valve replacement procedures. Reference Salim Hammoud, Gupta and McCloskey17
Echocardiographic data collection and assessment
Echocardiographic data were obtained as described in our previous study. For each operation, perioperative echo data were obtained at all available time points, including postoperatively, prior to hospital discharge, and at the time of cross-sectional follow-up. Extent of echo follow-up varied greatly between patients (Supplementary Figure S1). Protocolized echo review was performed by American College of Graduate Medical Education-accredited fellows in paediatric cardiology and overseen by expert echocardiographic faculty. Reference Barrios, Zia and Pettersson16
Systemic atrioventricular valvular regurgitation and systemic ventricular dysfunction were assessed via a binary scoring system (none/mild = 0 and moderate/severe = 1). These echo parameters evaluate haemodynamic function and have previously been shown to indicate successful short-term and long-term durability of congenitally corrected transposition of the great arteries repair strategies. Reference Barrios, Zia and Pettersson16 Systemic atrioventricular valvular regurgitation and systemic ventricular dysfunction were assessed over time and segregated based on procedural group.
Statistical analysis
Summary statistics were presented in the form of median interquartile range (IQR) for the continuous variables and n (%) for the categorical variables. Overall p-value that tests the hypothesis that medians across three treatment groups were similar was derived using Kruskal-Wallis test, whereas pairwise p-value that tests medians for any two treatment groups was derived using Wilcoxon rank sum test. A p-value that tests the hypothesis that frequencies across three treatment groups was determined using a Chi-square test. Association of health-related quality of life with treatment assignment, as well as, in a separate model, with echo parameters, was evaluated using a time-varying coefficient model, adjusted for gender and age at the time of health-related quality of life assessment. Results were presented in the form of estimated time-varying coefficients and health-related quality of life scores.
Results
A total of 50 patients (70% male) completed the questionnaires: 20 medically managed, 17 physiological repair, and 13 anatomical repair. Table 1 presents demographics and associated lesions. The anatomic repair group was significantly younger at presentation and procedure compared to the physiologic repair and medical management groups (p < 0.001). Ventricular septal defect was more prevalent in anatomic repair than physiologic repair and medical management patients (p = 0.003). Coarctation of aorta and pulmonary valve atresia were exclusive to anatomic repair patients.
Summary statistics of the baseline characteristics, stratified by the three treatment groups. Across all groups, no patients had a diagnosis of overriding tricuspid valve, tricuspid valve stenosis, mitral valve stenosis, subvalvar aortic stenosis, or supravalvular aortic stenosis

Echocardiographic measures of systemic ventricular function and systemic atrioventricular valve function
Cross-sectional echo metrics closest to time of health-related quality of life measurement were evaluated for patients across the three treatment modalities. Normal systemic ventricular function was most prevalent in anatomic repair patients (84.6%), and least common in physiologic repair patients (35.3%). Ventricular dysfunction was observed most often in physiologic repair patients across the spectrum of severity. Mild dysfunction in physiologic repair patients (23.5%) was greater than anatomic repair (15.4%), and moderate to severe dysfunction was greatest in physiologic repair patients (41%) and absent in anatomic repair patients (p=0.093).
The severity of systemic atrioventricular valve regurgitation differed significantly among groups (p < 0.001). Most anatomic repair patients exhibited no atrioventricular valve regurgitation (69.2%), while the absence of atrioventricular valve dysfunction was rare in medical management (5%) and physiologic repair patients (0%). Mild regurgitation was most common in the medical management group (45%), followed by physiologic repair (35.3%) and anatomic repair (30.8%). Mild-to-moderate regurgitation was present in medical management (45%) and physiologic repair groups (41.2%), but absent in anatomic repair. Moderate-severe or severe regurgitation was highest in physiologic repair (23.6%), lower in medical management (5%), and absent in anatomic repair.
Health-related quality of life scores between treatment groups
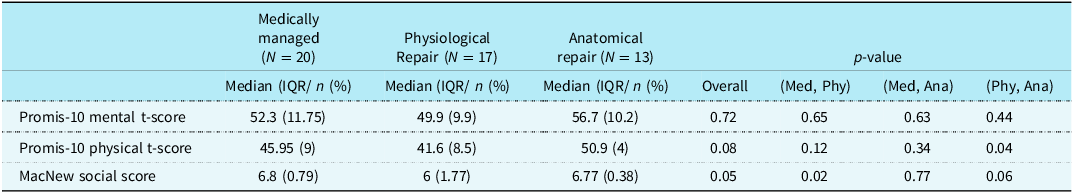
Health-related quality of life measurements were taken at a single time point for each patient. Overall median health-related quality of life scores are summarised in Table 2. MacNew Social scores of medical management patients were higher than physiologic repair patients (p < 0.05), but no significant difference was noted between physiologic repair and anatomic repair. PROMIS-10 Physical scores of anatomic repair were higher than physiologic repair (p < 0.05). PROMIS-10 Mental T-scores showed no significant differences among the groups.
Summary statistics of the three quality of life scores, stratified by treatment group

Changes in health-related quality of life, depending on time of assessment, are shown in Figure 1. Anatomic repair patients assessed within 20 years post-treatment showed higher MacNew Social and PROMIS-10 Mental T-scores than physiologic repair. MacNew Social and PROMIS-10 Mental T-scores were comparable between anatomic repair and physiologic repair for patients assessed beyond 20 years post-treatment. Anatomic repair patients showed consistently higher PROMIS-10 Physical T-scores than physiologic repair across all intervals, though this difference did not reach statistical significance.
Mean HRQoL scores stratified by treatment group and time.

Association between echocardiographic metrics and health-related quality of life is time dependent
Intervals between echo and health-related quality of life assessments were constructed to contextualise factors beyond time elapsed, offering insights into follow-up duration and post-surgical recovery (Figure 2). Patients with greater time since surgery demonstrated associations between echo and long-term health-related quality of life.
Figure shows the estimates of time-varying coefficient for systemic ventricular dysfunction (binary) on the left and systemic AV valve regurgitation (binary) on the right across HRQoL domains. The dashed green line corresponds to value = 0, indicating no effect.

In the early period, moderate or severe systemic ventricular dysfunction was positively associated with all health-related quality of life scores. In the intermediate period, moderate or severe ventricular dysfunction was negatively associated with health-related quality of life scores.
Over the long term, associations between ventricular dysfunction and health-related quality of life generally attenuated in all domains. Atrioventricular valve regurgitation demonstrated a negative association with physical scores at 6 to 10 years, though this effect gradually attenuated.
Ventricular dysfunction consistently exhibited stronger associations with health-related quality of life than atrioventricular valve regurgitation across all time periods.
Discussion
Patients with congenitally corrected transposition of the great arteries exhibit a spectrum of associated lesions and symptoms, Reference Agarwal, Samad, Kalvin, Bush and Tajik23 creating challenges for physicians in determining optimal management pathways, particularly in well-balanced congenitally corrected transposition of the great arteries cases. A key unanswered question in current clinical data is whether to pursue anatomic repair proactively in congenitally corrected transposition of the great arteries infants without associated lesions, given their potential for long-term survival without surgical intervention.
Health-related quality of life assessments can offer critical insights to guide clinical decision-making for balanced congenitally corrected transposition of the great arteries patients. Health-related quality of life is crucial because it captures patients’ perceptions on how treatment impacts their physical, psychological, and social well-being, Reference Sitlinger and Yousuf Zafar24,Reference Megari25 providing a valuable counterbalance to physician biases that may not always align with patient experiences. Reference Kennedy, Rehman and Johnson13–Reference Samuel, Mbah and Schaal15 Health-related quality of life is especially essential in chronic conditions like congenitally corrected transposition of the great arteries, where the goal of treatment extends beyond survival to include long-term well-being. Reference Kahr, Radke and Orwat26–Reference Cotts, Malviya and Goldberg28 Patients with congenitally corrected transposition of the great arteries often require lifelong follow-up, making it critical to not only evaluate their clinical outcomes but also how their treatment affects their overall quality of life. Our findings suggest that anatomic repair confers early benefits in the health-related quality of life of congenitally corrected transposition of the great arteries patients, particularly in the physical domain, though these appear to attenuate over time. In contrast, patients undergoing physiologic repair initially reported lower health-related quality of life scores but showed improvement, especially in social functioning. These trajectories reflect not only the impact of surgical strategy but also the long-term adaptation of patients.
Importantly, our study found that systemic ventricular dysfunction was more strongly associated with diminished health-related quality of life than atrioventricular valve regurgitation across time points. This finding reinforces the importance from a patient perspective of preserving ventricular function, regardless of the chosen repair pathway. The delayed negative association observed with atrioventricular valve regurgitation may reflect cumulative strain over time or its interaction with ventricular performance.
While anatomic repair offers promising early results, our data suggest that its long-term health-related quality of life advantage may converge with that of physiologic repair. This underscores the need for individualised decision-making, particularly in balanced congenitally corrected transposition of the great arteries patients, where early intervention must be weighed against surgical risk and developmental timing.
Finally, health-related quality of life expectations vary by age. Several anatomic repair patients were younger, and surveys were parent-reported. Although age-adjustment was applied, proxy response bias and developmental differences remain a limitation. Larger, prospective, age-stratified studies would be needed to further clarify these findings.
Several limitations exist in this study. First, the potential for selection bias exists with allocation of patients to treatment pathways based on anatomical considerations and candidacy. Secondly, our limited sample size may hinder the generalizability of our findings. Although repeated follow-up attempts were made to contact patients from the original congenitally corrected transposition of the great arteries cohort, we were only able to reach 50 patients. Haemodynamic data from the cohort were also limited due to variability in follow-up echocardiographic data available. Furthermore, there was variability in the age of presentation and definite operation in the treatment groups. Patients in the physiologic repair and medical management group had an older median age of presentation and definite procedure than anatomic repair patients. To address this discrepancy, we implemented age and gender adjustment in our analyses. Another limitation is inherent to the novel hybrid questionnaire instrument utilised in this study. Though this tool was previously validated in an adult cardiac population, its application to younger patients in our cohort may introduce discrepancies that impact interpretation of quality of life outcomes.
Despite these limitations, our data provide valuable insight into the long-term health-related quality of life outcomes of congenitally corrected transposition of the great arteries patients. A larger, prospective multi-centre study with standardised long-term follow-up is needed to further inform clinical decision-making and determine the optimal treatment pathway for patients with congenitally corrected transposition of the great arteries.
Supplementary material
The supplementary material for this article can be found at https://doi.org/10.1017/S104795112510142X
Acknowledgements
None
Financial support
None
Competing interests
The authors declare no conflict of interest relevant to this study.
Ethical standard
This study was approved by the Cleveland Clinic Institutional Review Board (IRB#19-935; approved 08/07/2019; last amended 1/23/2023). Informed consent was obtained from all patients or their guardians in accordance with the Declaration of Helsinki and institutional guidelines.