Introduction
First described by Minor et al.,Reference Minor, Solomon, Zinreich and Zee1 superior semicircular canal dehiscence syndrome is characterised by absence of the bone overlying the superior semicircular canal, which creates a so-called ‘third-window effect’ and causes abnormal transmission of acoustic energy within the inner ear. Patients with this defect typically present with sound- and/or pressure-induced vertigo (Tullio phenomenon) and nystagmus in a vertical-torsional plane.Reference Minor, Solomon, Zinreich and Zee1–Reference Banerjee, Whyte and Atlas3 Patients with superior semicircular canal dehiscence may have other manifestations such as low-frequency hearing loss (typically conductive), hyperacusis, autophony and other unusual auditory phenomena.
A spectrum of symptoms and signs associated with a defect involving the posterior canal (posterior semicircular canal dehiscence syndrome) has also been recently described.Reference Gopen, Zhou, Poe, Kenna and Jones4–Reference Brantberg, Bagger-Sjöbäck, Mathiesen, Witt and Pansell6
While unilateral superior semicircular canal and posterior semicircular canal dehiscences have been well-described in the literature, there are few reports of bilateral dehiscences of both the superior semicircular canal and the posterior semicircular canal. Moreover, surgical management of dehiscences of multiple semicircular canals has not been previously reported.
We present an unusual case of bilateral superior semicircular canal dehiscence and posterior semicircular canal dehiscence, causing hearing loss and problematic hyperacusis, treated surgically via a transmastoid approach to simultaneously address both bony defects on one side.
Case description
A 52-year-old man presented with progressive, right-sided hyperacusis, which interfered with his recreational and choir activities. He also described pain induced by high frequency sounds, right aural fullness, and autophony. He denied pressure- or sound-induced vertigo. However, he had experienced occasional but progressive imbalance. Previously, the patient had been exposed to substantial environmental noise and had suffered a significant head trauma while working in construction, many years preceding the development of any of the troublesome symptoms mentioned above.
His head and neck examination, including otoscopy, was normal. The fistula test was negative subjectively and objectively, bilaterally. His remaining physical examination was normal except for a broad-based gait.
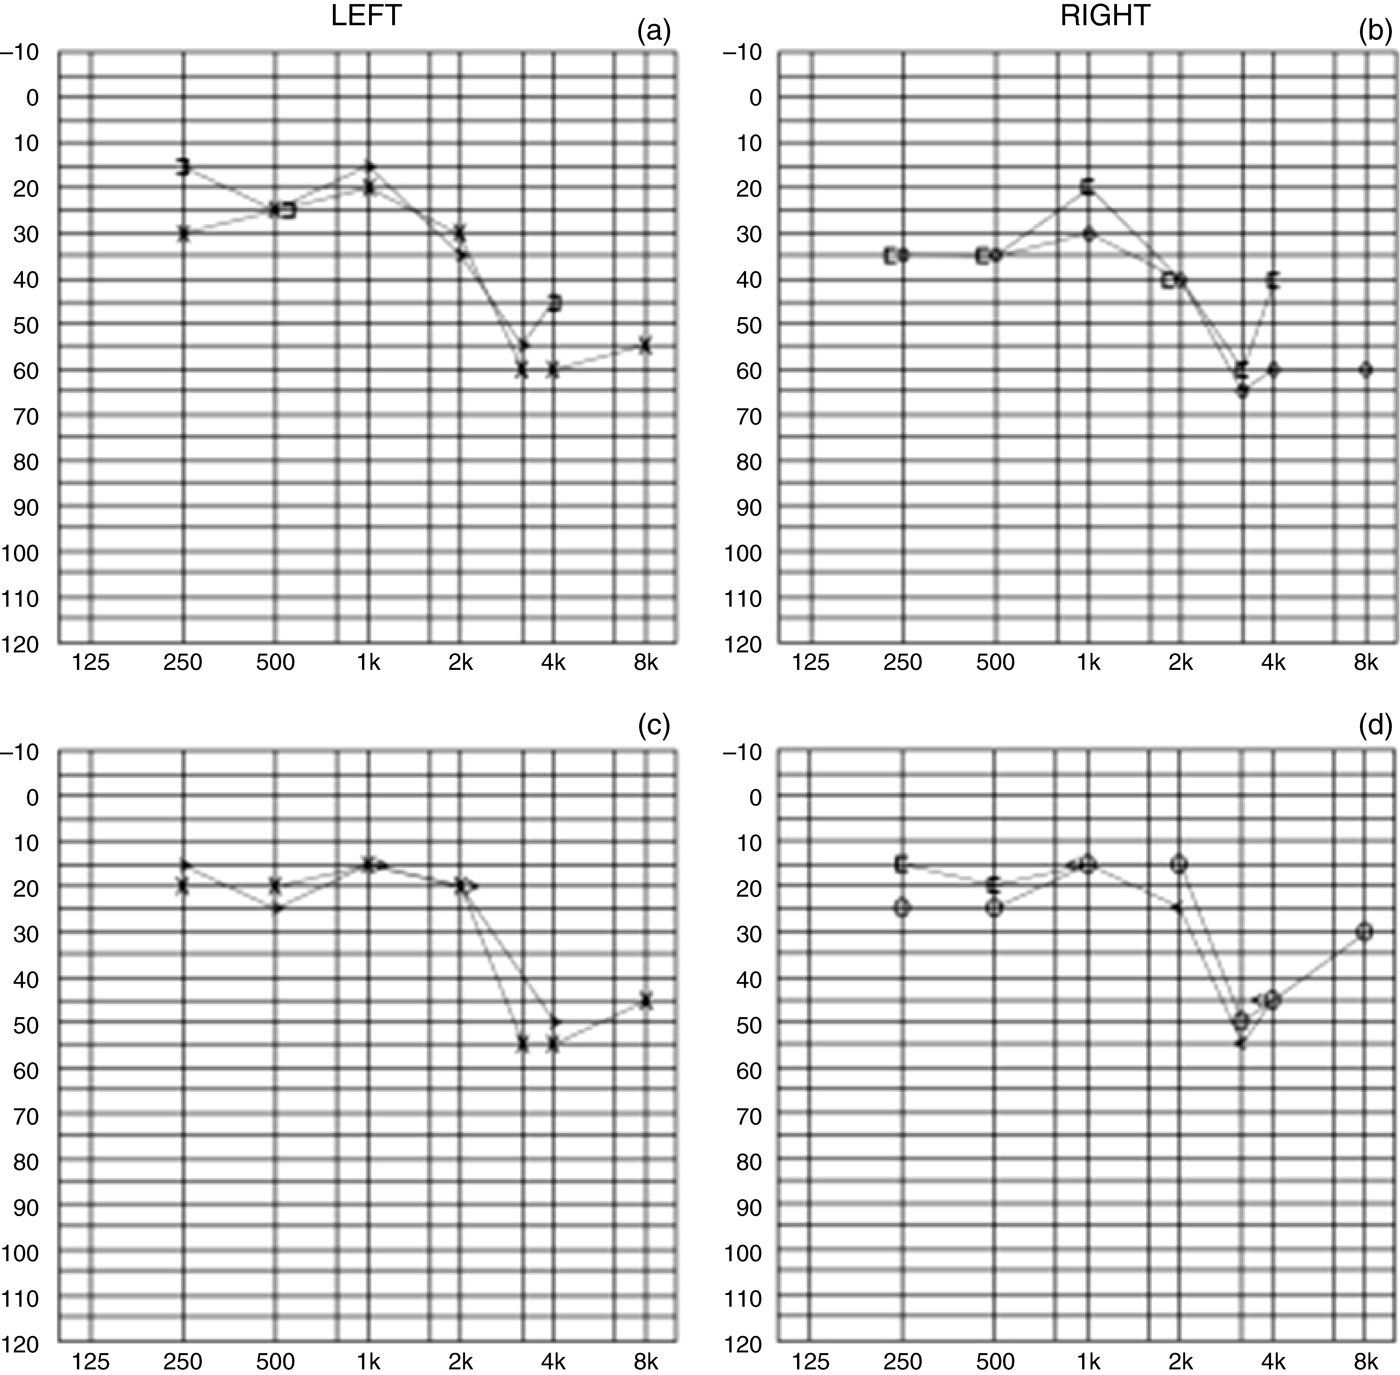
Audiometry revealed bilateral downward-sloping sensorineural hearing loss (SNHL) in a noise-induced configuration (Figure 1). Additionally, there was a 10–20 dB, low frequency SNHL in the right ear. His word recognition testing scores at 65 dB were 84 and 92 per cent on the right and left sides, respectively. Tympanometry was normal. A click-induced cervical vestibular evoked myogenic potential test demonstrated responses at 70 dB normal hearing level bilaterally (normal thresholds are approximately 95 dB normal hearing level),Reference Minor, Cremer, Carey, Della Santina, Streubel and Weg2 with an insignificant interaural amplitude difference. The patient complained of right ear discomfort and subjective nystagmus at 95 dB.
Audiograms for the (a) left and (b) right ear pre-operatively, and the (c) left and (d) right ear one-year post-operatively. Note that bone conduction thresholds from six-month post-operative audiography were used to prepare the one-year post-operative audiogram, as these thresholds were not recorded at the one-year time point. x axes represent frequency (Hz); y axes represent hearing threshold (dB).

Videonystagmography failed to elicit vertical or horizontal nystagmus with sound or pressure stimuli. The patient had a spontaneous, right-beating nystagmus and abnormal optokinetic and saccade test results, suggesting a central aetiology. Caloric test results were normal.
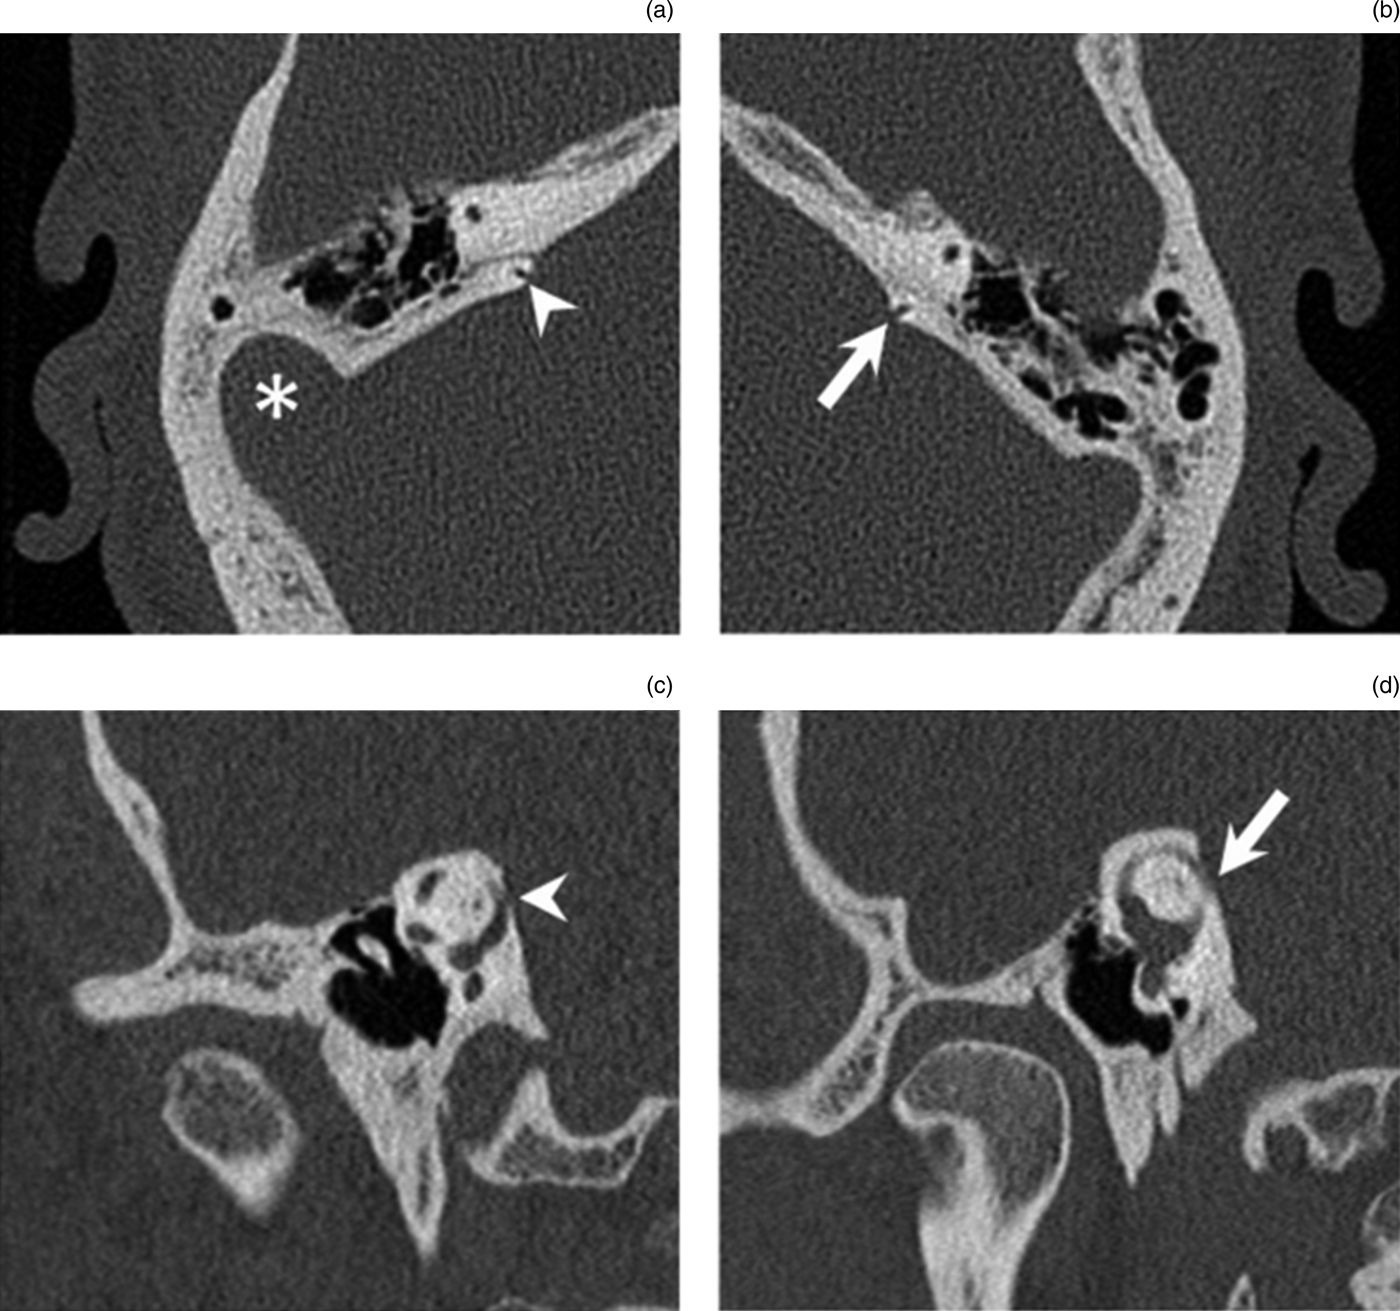
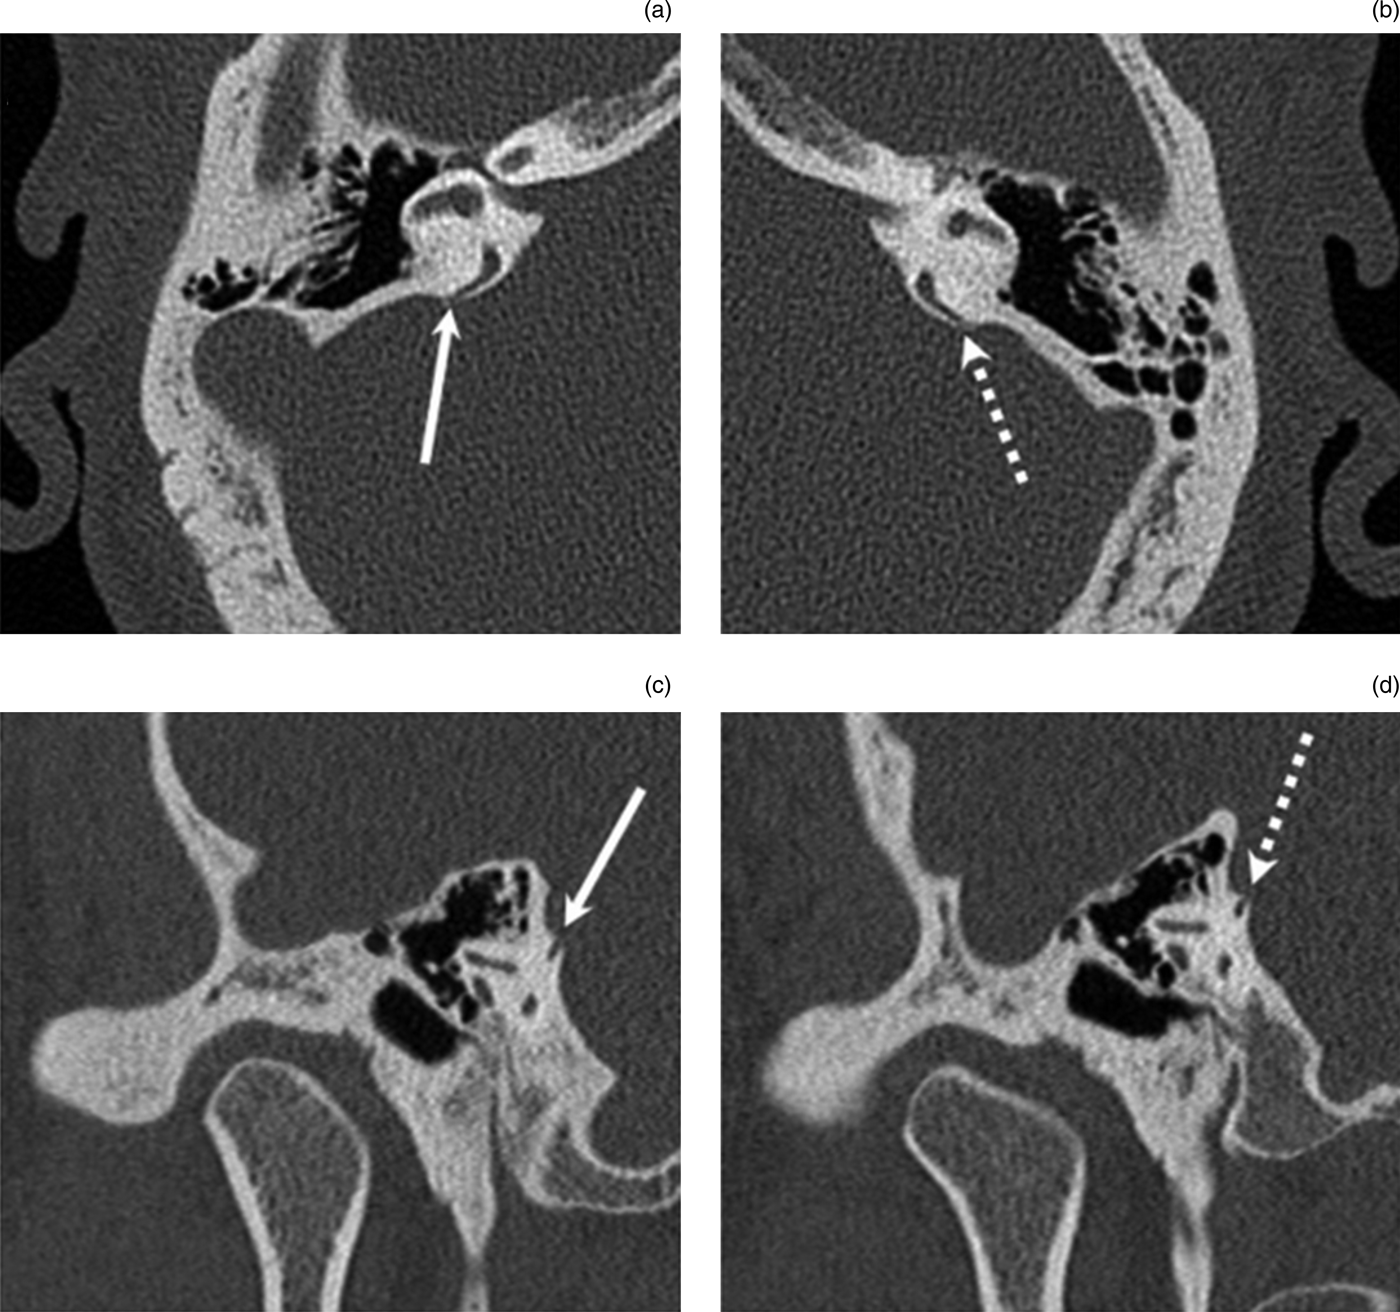
Magnetic resonance imaging performed five years prior to clinical presentation was normal. Temporal bone computed tomography (CT) in the axial and oblique planes revealed dehiscences of both the right superior semicircular canal (Figures 2a and 2c) and the right posterior semicircular canal (Figures 3a and 3c), of 2–3 mm. Interestingly, the superior dehiscence was not at the usual area, at the dome of the semicircular canal, but rather was located more posteriorly and adjacent to the common crus. The posterior defect was also adjacent to the common crus. A similar pattern was detected on the contralateral side (Figures 2b, 2d, 3b and 3d) but with smaller dehiscences (approximately 1 mm each). While the lateral tegmen was not low-lying, CT delineated an anterosuperiorly positioned sigmoid sinus and a high-riding jugular bulb on the right side.
Axial (a and b) and oblique Poschl (c and d) computed tomography images of the right (a and c) and left (b and d) temporal bones, demonstrating bilateral dehiscence of the superior semicircular canal (arrowheads in a and c; arrows in b and d) in close proximity to the common crus. Note also the anterior positioning of the groove for the right sigmoid sinus (a, asterisk) compared with the normal left side.
Axial (a and b) and oblique Poschl (c and d) computed tomography images of the right (a and c) and left (b and d) temporal bones, demonstrating bilateral dehiscence of the posterior semicircular canal (arrows in a and c; dashed arrows in b and d), also in close proximity to the common crus.
Motivated by his autophony and right-sided hyperacusis, the patient elected to undergo surgery. A transmastoid approach was selected to address the right-sided posterior and superior semicircular canal dehiscences, with intra-operative auditory brainstem response (ABR) testing and electrocochleography monitoring. To access the otic capsular structures, the aberrant sigmoid sinus required significant decompression and posterior mobilisation. After skeletonisation and blue-lining of the superior semicircular canal and the posterior semicircular canal, small dehiscences (2–3 mm each) of both canals were noted where the posterior fossa dura rested on exposed canal lumina. The lumina of the canals on either side of the dehiscences were exposed using micropicks, and temporalis fascia plugs were then gently advanced toward the ampullated and the common crus ends of each canal. Small bone chips were advanced behind the fascia plugs within the lumen of each canal, and bone paté was then placed over the area. Intra-operative ABR and electrocochleography waveforms were preserved throughout the procedure.
By one month post-operatively, the patient had experienced significant improvement in his right-sided hyperacusis, although he described persistent right ear fullness. He developed symptoms of right benign paroxysmal positional vertigo (BPPV) and had a positive right-sided Dix–Hallpike manoeuvre. An Epley manoeuvre on the right effectively treated his symptoms. Notably, his hyperacusis was completely resolved at three months post-operatively, and he resumed all choir-related activities. He experienced some residual imbalance worsened by moving his head up or down. This resolved by one year post-operatively after a course of vestibular rehabilitation. His right-sided ear fullness was also improving at that time. Followup at three years after surgery revealed partial recurrence of right pulsatile tinnitus, aural fullness and hyperacusis. These symptoms were not debilitating to the patient and were not progressive in severity.
Audiography demonstrated mild improvement in some of the patient's bone conduction thresholds on the right side, at one month and three month intervals. At one year post-operatively, his audiogram demonstrated a 10–30 dB improvement in air conduction thresholds in the operative ear (Figure 1), and his speech discrimination score was greater than 92 per cent, with normal tympanometry. His contralateral thresholds were unchanged, as was the high frequency, noise-induced configuration of hearing loss bilaterally. At three years post-operatively his pure tone thresholds and speech discrimination scores were unchanged compared to those on audiography at one year after surgery.
Discussion
We present a rare case of bilateral dehiscences of both the superior and posterior semicircular canals, in which the right-sided dehiscences were symptomatic.
The aetiology of superior semicircular canal dehiscence has been proposed as a combination of a developmental abnormality resulting in thin bone overlying the semicircular canal, together with disruption of this thin, bony layer by head trauma or gradual degeneration.Reference Minor, Cremer, Carey, Della Santina, Streubel and Weg2 Zhou et al.Reference Zhou, Gopen and Poe7 expanded upon this idea and proposed a congenital defect of the entire middle fossa floor as the likely aetiology for semicircular canal dehiscence syndrome. While our patient's previous head trauma could have contributed to his abnormal optokinetic and saccade test results and broad-based gait, the long interval between this event and the occurrence of his fistulous symptoms made the head trauma less likely to be a contributory factor in the development of his symptomatic dehiscences.
Our patient had an unusual presentation of semicircular canal dehiscence syndrome, with troublesome hyperacusis as his primary complaint. Patients with superior semicircular canal dehiscence often present with pressure- or sound-induced vertigo and nystagmus. These phenomena are due to the creation of a mobile third window into the inner ear as the result of the dehiscence, causing abnormal ampullofugal and ampullopetal endolymphic flow, which results in atypical activation or inhibition of the affected canals.Reference Minor, Solomon, Zinreich and Zee1, Reference Banerjee, Whyte and Atlas3 Posterior semicircular canal dehiscence has been shown to cause sound- and pressure-induced vertigo and disequilibrium, or no vestibular symptoms in some patients.Reference Gopen, Zhou, Poe, Kenna and Jones4–Reference Chien, Carey and Minor8 Our patient was not affected by any significant vestibular symptoms. However, his hyperacusis had significantly interfered with his singing activities and his social interactions with his young children, leading him to seek definitive management. Despite his somewhat unusual symptomatic presentation, he had low frequency hearing loss and abnormal vestibular evoked myogenic potential thresholds, which are known to be associated with superior semicircular canal dehiscence.Reference Chien, Carey and Minor8
The anatomy of dehiscences described in our case is unusual. In their original and subsequent reports, Minor and colleaguesReference Minor, Solomon, Zinreich and Zee1, Reference Minor9 described superior semicircular canal dehiscence occurring at the roof of the superior semicircular canal. However, there appears to be some variability in the location of the bony dehiscence in superior semicircular canal dehiscence cases.Reference Minor9, Reference Rajenderkumar, Farrell, Alles and Savy10 The location of posterior semicircular canal dehiscence also appears to be variable. Brantberg et al.Reference Brantberg, Bagger-Sjöbäck, Mathiesen, Witt and Pansell6 reported a case of posterior semicircular canal dehiscence sited close to the ampulla. In another radiological report, defects could be seen along either the caudal portion or the cephalic portion of the posterior semicircular canal.Reference Gopen, Zhou, Poe, Kenna and Jones4 In our report, the defects were found to be very close to the common crus. Interestingly, high-riding jugular bulbs have been noted in the majority of patients with posterior semicircular canal dehiscence,Reference Gopen, Zhou, Poe, Kenna and Jones4 as was observed in our patient.
The unusual anatomy dictated our choice of operative approach, as a middle fossa approach would not have provided adequate exposure for both canal dehiscences simultaneously. While the transmastoid approach was complicated by the anteriorly positioned sigmoid sinus, we were able to effectively mobilise this vessel posteriorly to provide adequate access for successful plugging of the involved canals. Doing so resulted in a marked improvement in the patient's primary symptom of hyperacusis, as well as a 10–30 dB improvement in his air conduction thresholds, without affecting his cochlear function. While he had partial recurrence of aural fullness, pulsatile tinnitus and hyperacusis in the operative ear on long-term follow up, the patient subjectively maintained meaningful benefit from the surgery and his hearing thresholds remained stable.
• Dehiscence of both superior and posterior semicircular canals can occur bilaterally, with atypical symptoms
• These dehiscences may occur close to the common crus
• Computed tomography and vestibular evoked myogenic potential testing are important pre-operatively
• A transmastoid approach can enable effective, simultaneous management
The post-operative development of BPPV-like symptoms and findings in our patient was very surprising, given that plugging of the posterior semicircular canal has been shown to effectively treat intractable BPPV.Reference Beyea, Agrawal and Parnes11 Possible explanations include cupulolithiasis or incomplete occlusion of the posterior canal. Regardless, a repositioning manoeuvre eliminated the observed nystagmus and resulted in resolution of the patient's associated positional symptoms.
Conclusion
Dehiscence of both the superior and the posterior semicircular canals, which can occur bilaterally, may present with a spectrum of atypical symptoms, in comparison with the more common superior semicircular canal dehiscence syndrome. Dehiscences of the superior and posterior semicircular canals may occur close to the common crus.
Computed tomographic imaging and vestibular evoked myogenic potential testing should be used as complementary investigations to clearly define the location and size of the canal dehiscences, and to identify pre-operatively any aberrant vascular or dural anatomy which may complicate surgical management.
A transmastoid approach can enable effective and simultaneous management of dehiscences of the posterior and superior semicircular canals.
Acknowledgements
This project was supported by the Clinical and Translational Science Award program, previously through a National Center for Research Resources grant (1UL1RR025011) and subsequently by National Center for Advancing Translational Sciences grants (9U54TR000021). The senior author (SPG) received support from grants NIH 1 R03 DC012432-01 and P30 HD003352.