Our target article proposed that addiction is a spectrum disorder, with the different aspects arising from misperformance (vulnerabilities, failure-modes) of the machinery of decision-making. The 25 commentaries are generally supportive and have provided several different viewpoints on our theory ranging from the molecular to the sociological. In this response, we address those additional viewpoints and show how our theory incorporates them.
We start with a review of the major issues raised in the commentaries (sect. R1) and then proceed with clarifications of several issues that were unclear in the target article (sect. R2). We then discuss revisions to the proposed framework for decision-making (sect. R3), particularly the incorporation of additional components such as Pavlovian action-selection mechanisms, and revisions to the proposed taxonomy of addiction (sect. R4), particularly the role of additional processes such as negative affect. From there, we turn to the question of predictions and falsifiability (sect. R5), to identifying specific additional vulnerabilities (sect. R6), and finally to implications for treatment, clinical assessment, and policy (sects. R7 and R8).
R1. Introduction: The parameter space of addiction
Theories of decision create an interacting parameter space of behavior, decision, and brain function, within which we can place terms such as addiction, compulsion, dysfunction, and illness. Our target article identifies addiction as arising from failures in the machinery of decision-making. Ahmed suggests that we have created an “addiction space” within which the different observations and theories of addiction can be placed.
The most contentious issue raised is whether our framework of decision-making and thus of addiction is complete and whether we have separated fragments that should have been merged (Bickel & Yi; Goudie, Field, & Cole [Goudie et al.]). We note that there is at least one additional component which needs to be factored into theories of addiction: Pavlovian conditioning and affect (Kiviniemi & Bevins, Ostlund & Balleine; see also Balleine Reference Balleine, Mowrer and Klein2001; Reference Balleine, Whishaw and Kolb2004; Dayan et al. Reference Dayan, Niv, Seymour and Daw2006). However (with the addition of this Pavlovian/affective component), our framework holds up very well to the potential counterexamples raised in the commentaries. (See, for example, our discussion of the effect of expectancies later in response to Wiers, Havermans, Deutsch, & Stacy [Wiers et al.])
The second contentious issue is the extent to which addiction is explicable as a single phenomenon or whether it is in truth a spectrum of disorders with separably identifiable etiologies. Le Moal suggests that our theory is just one more theory to add to a large list of potential theories (which he seems to reject). However, we would argue that our theory is a synthesis of many theories (including Le Moal's) and in doing so unifies a larger space than the other addiction theories. Hardcastle points out that our list is neither complete nor shorter than prior lists on addiction, and thus provides neither a necessary nor sufficient definition of addiction. Three important questions arise here: (1) Is it possible to shorten the list? (2) Does our taxonomy more directly reflect separable components? (3) Can our theory provide a framework within which to explain the phenomena within addiction? We would argue that our vulnerabilities reflect a priori failure-modes of the decision system and as such are more likely to reflect separable components. The extent to which our vulnerabilities reflect the actual mechanisms of addiction is going to require additional work in the clinical realm. As noted by several commentators (e.g., Ahmed, Bickel & Yi, Yin), our proposal is only the first step to identifying this process-space within which we can find the dysfunction that is addiction.
One issue raised by several commentators is the question of whether our “unified framework for addiction” is truly unified. Griffiths suggests that it is unified only at a biological level. Several commentators (Boden, Goudie et al., Griffiths, Lende) argue that addiction arises at a more sociological level. The sociological effects on addiction are very interesting, particularly from a policy perspective (MacCoun), but we suggest further on that any sociological effects must change the decision-making systems because, in the end, the addictive behavior (taking the drug, playing the game) is fundamentally an individual action. We argue that the theory we have proposed can incorporate social and ethnological levels as well, because it provides a parameter space within which to understand the social and ethnological effects on decision-making.
As we will discuss later, there are many unanswered questions that remain, both within our understanding of the machinery of decision-making itself as well as within the potential dysfunctions. Other decision failures can also be sited within this framework. For example, Andreou places the problem of procrastination into the framework of decision failures, identifying this also as a consequence of succumbing to a vulnerability within the system. Similar suggestions have been made that mental illness (such as schizophrenia, obsessive-compulsive disorder, and other problems) can be seen as failure-modes of neural functional machinery (Paulus Reference Paulus2007), which may explain the comorbidity often seen with addiction (Chambers).
R2. Clarifications
Several of the commentaries seem to have misunderstood claims made in the target article. Before responding to issues raised within the commentaries, we wish to clarify certain points of our theory.
R2.1. Our theory is looking at all stages of addiction
Several commentators have attempted to place our theory at a specific “stage” of the addiction process. For example, Le Moal suggests that we were looking at the “end-stage of addiction.” This was not our intention at all. The unified model of decision-making should be able to explain behavior, and thus, it should be able to explain not only all aspects of addictive use, but also non-addictive use. The vulnerabilities hypothesis says that addiction arises when drug use occurs because drug use is inappropriately driving decision-making. A similar case can be made for failure-modes arising from non-pharmacological consequences (such as in gambling or other behavioral addictions).
Because much behavior moves from expectancy-based, planning-capable systems ( ) to stimulus-response, sequence-based, habit-like systems (
 ), drug use will often proceed through the same stages that normal behaviors do (Everitt & Robbins Reference Everitt and Robbins2005). However, as noted in the target article, not all behaviors proceed through the same sequence. It is possible for some behaviors to remain controlled by flexible
 systems, and it is possible in some behaviors for the process to return to being controlled by the
 system after being controlled by the
 system. Our contention is that all components of the decision-making system have failure-modes, that these failure-modes will be clinically identifiable, and that successful treatment will require the identification of these failure-modes.
It is important to note that not all subjects will show all failure-modes. Our suggestion that addiction is a spectrum disorder implies that addiction can arise from any of the vulnerabilities (i.e., that it is an or process), and that any, some, or all of these failure-modes may be active within any specific subject. As noted by Ahmed, most of the previous theories of addiction have assumed that addiction arises from a loss of a cognitive, flexible, planning-capable ability to a habitual, compulsive, automatic system. Several commentators (e.g., Le Moal) have incorrectly assigned such a model to us. In fact, our model explicitly posits that both systems have potential failure-modes. Addicts can lose control due to a vulnerability in the planning system, to a vulnerability in the habit system, or to a vulnerability in their interaction. With the addition of a Pavlovian/affective system ([SO]  ; Berridge, Zhang, & Aldridge [Berridge et al.]; Kiviniemi & Bevins; Ostlund & Balleine; see further on in this response), there will be additional vulnerabilities in that system as well as in its interaction with the other systems (Balleine Reference Balleine, Mowrer and Klein2001; Reference Balleine, Whishaw and Kolb2004; Breland & Breland Reference Breland and Breland1961; Dayan et al. Reference Dayan, Niv, Seymour and Daw2006).
R2.2. Falling victim to a vulnerability does not imply that all decision making is faulty
Several commentators assume that falling victim to a failure-mode implies that a component is unavailable to decision-making. For example, Hart & Krauss suggest that because addicts can actually plan and make decisions, they must not have a problem with decision-making. We explicitly suggest that each decision, and each failure, will be caused by an interaction between drugs, the individual, and the experience. These failure-modes will be both partial and specific. By analogy, a patient with allergies has a failure of his immune system, but still can mount an appropriate immune response to a viral attack. Similarly, a drug addict who overvalues heroin can still plan, both how to get the heroin, and how to get to a clinic. It is in the contrasts of those plans that overvaluation becomes an issue.
R2.3. Drugs are economic objects and users are sensitive to cost
As first predicted by Becker (Reference Becker1976, Becker & Murphy Reference Becker and Murphy1988), drugs are economic objects and thus sensitive to price and cost. Although there is strong evidence that changes in drug costs lead to changes in drug use, drug use remains less elastic to cost than a rational theory would predict (MacCoun). Nevertheless, they do remain at least somewhat sensitive to cost (Becker et al. Reference Becker, Grossman and Murphy1994; Grossman & Chaloupka Reference Grossman and Chaloupka1998; Liu et al. Reference Liu, Liu, Hammit and Chou1999). Similarly, many experiments have shown that drug use in both animals (Carroll Reference Carroll1993; Carroll et al. Reference Carroll, Lac and Nygaard1989; Elsmore et al. Reference Elsmore, Fletcher, Conrad and Sodetz1980; Lenoir & Ahmed Reference Lenoir and Ahmed2007; Lenoir et al. Reference Lenoir, Serre, Cantin and Ahmed2007; Nader & Woolverton, Reference Nader and Woolverton1990; Reference Nader and Woolverton1991) and humans (Hart et al. Reference Hart, Haney, Foltin and Fischman2000; Hatsukami et al. Reference Hatsukami, Thompson, Pentel, Flygare and Carroll1994; Higgins et al. Reference Higgins, Alessi and Dantona2002; Reference Higgins, Heil and Lussier2004) is decreased with the provision of alternate options. Several commentaries incorrectly attribute to our theory the prediction that drug use would be entirely inelastic and that any evidence that drug users are sensitive to cost would disprove computational theories of drug addiction (e.g., Hart & Krauss).
Most current computational models (and most animal experiments) suggest that drug users should remain sensitive to costs: drug users become willing to pay very high cost for drugs, but if a drug user is given the option between high- and low-cost drugs, they will select the lower cost. For example, Figure 2 of Redish (Reference Redish2004) explicitly shows the modeled drug user (Vulnerability 7) being sensitive to cost. Thus, sin taxes remain an important policy issue and a potential means of attacking the drug problem (MacCoun). It is important to differentiate a drug user's ability to recognize costs and to select the lesser-cost drug from rationality.
Similarly, it very interesting how small (inconsequential) rewards (like $5 trinkets; Hart & Krauss) can serve as alternate rewards to reduce drug use more than simply increasing the cost of the drugs by $5. This implies that these vouchers and alternate rewards are accessing other mechanisms beyond cost increases. An important open question is to determine why these voucher systems work, and for whom. As we discuss later (see Treatments), our prediction is that these voucher systems are allowing the decision-making system to somehow get around a vulnerability. Which vulnerability is involved and how those trinkets allow a user to circumvent and accommodate that vulnerability remains an open question for future research.
R2.4. Addiction arises from misperformance of the decision-making machinery
We selected the term vulnerability (or failure-mode) from an analogy to engineering to reflect the concept of a machine doing the wrong thing because of an interaction with conditions that it was not evolved to handle. However, several commentators (e.g., Le Moal, Hart & Krauss) have taken the term to imply an intrinsic factor preceding any interaction with conditions. Some commentators (e.g., Neal & Wood) have taken this term to imply that all effects were due to pharmacological manipulations of the system. Other commentators (e.g., Hart & Krauss; Wiers et al.) have taken it to imply that a system misperforming because of a vulnerability entails a complete failure of the system involved. These are all misunderstandings of our terminology.
A “vulnerability” in our terminology is simply any mechanism by which the machine misperforms. This misperformance can be caused by pre-existing conditions, by pharmacological manipulations, by natural experiential sequences (e.g., gambling), or through an interaction of these conditions.
Note that a subject can still use a system that is misperforming because of a vulnerability within that system. Thus, a subject with a pre-existing strong planning system (Wiers et al.) may be more likely to use that planning system, whether correctly or incorrectly. In fact, the example given by Wiers et al. is exactly what our theory would predict: In users with strong planning systems, drug use is more likely to arise from overvaluation in those planning systems, whereas in users with weak planning systems, drug use is more likely to arise from overvaluation in the non-planning, habit system.
R3. A framework for understanding the machinery of decision-making
Several commentators ask whether this is a reasonable and correct taxonomy of decision-making (Wiers et al.), whether we have missed certain components (Berridge et al., Kiviniemi & Bevins, Le Moal, Ostlund & Balleine), and whether our theory depends on assumptions of rationality (Andreou, Hart & Krauss, Khalil, Lende, Neal & Wood). We address each of these issues in turn.
We wish to start by stating that our fundamental claim that addiction arises because of failures of decision-making and can be best understood and treated by identifying what those failure-modes are, does not actually depend on the specific framework of decision-making that we have identified. As noted by Yin, this framework is only the first step. Additional research will be needed to validate, extend, and correct the decision-making framework. The framework laid out in the target article is based on rational neuroeconomics because of its simplicity. We would argue that these other, more complex theories (e.g., prospect theory [Kahneman & Tversky Reference Kahneman and Tversky1979], or multiple memory theories [Schacter Reference Schacter2001, Schacter & Tulving Reference Schacter and Tulving1994]) would also have additional vulnerabilities (failure-modes) through which behavior could be driven incorrectly. Our theory is that addiction lies within those failure-modes. For example, recent work has suggested the existence of fictive learning signals (e.g., regret) (Bell Reference Bell1982; Lee Reference Lee2008; Lohrenz et al. Reference Lohrenz, McCabe, Camerer and Montague2007). Chiu et al. (Reference Chiu, Lohrenz and Montague2008) found that smokers' brains reflected those fictive signals correctly, but their behavior did not. This mismatch identifies a potential unidentified vulnerability whose mechanism needs to be understood.
R3.1. A role for affect and Pavlovian conditioning
In addition to the “planning”  and “habit”
 systems, the framework laid out in the target article identified a further condition (“observation”,
 ), which we identified as not entailing an action and thus as not part of the decision-making system. As noted by Ostlund & Balleine, this system is better described as a Pavlovian association ([SO]), which can drive actions through Pavlovian conditioning processes
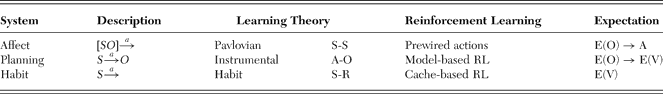
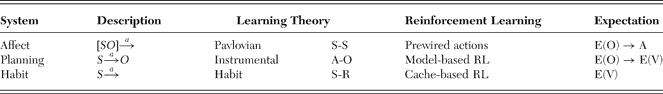
 . This could be phrased as an “evolutionary pre-wired response” to expected outcomes (Dayan et al. Reference Dayan, Niv, Seymour and Daw2006). As noted by Balleine (Reference Balleine, Mowrer and Klein2001; Reference Balleine, Whishaw and Kolb2004), this Pavlovian process proceeds through an affect-based system in which the outcome first produces an emotional affect, which then drives a pre-wired response (approach or avoid, fight or flight). The connection to affect suggests that this may be similar to the direct affect-action component posited by Kiviniemi & Bevins. Current computational models that examine actions produced through this system are limited (Balleine Reference Balleine, Mowrer and Klein2001; Reference Balleine, Whishaw and Kolb2004; Dayan et al. Reference Dayan, Niv, Seymour and Daw2006); nevertheless, several models have identified vulnerabilities in Pavlovian and Pavlovian-instrumental interactions that can lead to incorrect behavior (Balleine & Ostlund Reference Balleine and Ostlund2007; Breland & Breland Reference Breland and Breland1961; Dayan et al. Reference Dayan, Niv, Seymour and Daw2006).
R3.2. Dynamic motivational control
The issue of dynamic motivational control as raised by Berridge et al. has important implications for how the  system evaluates the expectation of value from the expectation of action. As noted by Berridge et al., cached-value or cached-action reinforcement learning systems (our
 system) cannot accommodate changes in value. However, decision-making systems based on expectancies of outcomes derived from searching through models of the world (our
 system) can theoretically change valuation on fast time-courses. Current planning system models (e.g., Daw et al. Reference Daw, Niv and Dayan2005; Niv Reference Niv2006; Niv et al. Reference Niv, Joel and Dayan2006b; Redish & Johnson Reference Redish and Johnson2007), and recent experimental results directly examining search and expectancies (Johnson & Redish Reference Johnson and Redish2007; Padoa-Schioppa & Assad Reference Padoa-Schioppa and Assad2006; Ramus et al. Reference Ramus, Davis, Donahue, Discenza and Waite2007; Schoenbaum et al. Reference Schoenbaum, Roesch and Stalnaker2006a), provide a first step towards this because these models calculate value on the fly through
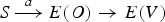 .
The extent to which value can actually be calculated on the fly is an interesting, open question. As noted in the commentary by Ostlund & Balleine, devaluation of outcome in instrumental learning (A-O,  paradigms requires experience with the outcome before the change in responding (Balleine Reference Balleine, Mowrer and Klein2001; Reference Balleine, Whishaw and Kolb2004). In contrast, Pavlovian paradigms can change immediately, without a prior interaction (Balleine Reference Balleine, Mowrer and Klein2001; Reference Balleine, Whishaw and Kolb2004). The experiments cited by Berridge et al. fit well within this distinction. These experiments imply an interaction between the homeostatic/allostatic vulnerabilities and the other vulnerabilities. The dynamic control of motivation will lie in that interaction (Niv et al. Reference Niv, Joel and Dayan2006b). But exactly how that dynamic control of motivation happens, computationally, is still unknown. Theoretically, the dynamic control of motivation is possible in both the Pavlovian
 and Instrumental (
 ) systems; however, current models have not explored how those expectations of value are calculated from the expectations of outcome. An important question remains whether dynamic controls of motivation are only influencing planning systems (as suggested by these models) or whether they can also influence habit systems as well. Several computational models of motivation in habit systems through changes in latency to action (Niv Reference Niv2006; Reference Niv2007; Niv et al. Reference Niv, Daw, Dayan, Weiss, Schölkopf and Platt2006a; Reference Niv, Joel and Dayan2006b; Reference Niv, Daw, Joel and Dayan2007) have been proposed. Although these models do not dynamically control goals (there is no expectation of outcome in
 ), changes in latency and reaction time can change distributions across goals under specific experiments (Niv Reference Niv2006; Niv et al. Reference Niv, Joel and Dayan2006b).
In a similar analysis, Sarnecki, Traynor, & Clune [Sarnecki et al.] suggest that dopamine can drive increased attention, and that attention can drive motivational control. We note that the temporal difference algorithms imply a shift in dopamine to cues predicting reward (Montague et al. Reference Montague, Dayan and Sejnowski1996; Schultz Reference Schultz1998; Sutton & Barto Reference Sutton and Barto1998) and drugs (Redish Reference Redish2004). These shifts occur in Pavlovian  , instrumental
 , and habit
 systems.
R3.3. New models of shifting systems
As noted earlier, new computational models based on reinforcement learning concepts (Sutton & Barto Reference Sutton and Barto1998) have addressed Pavlovian/affect systems (e.g., Dayan et al. Reference Dayan, Niv, Seymour and Daw2006); instrumental learning systems, based on search through models of the world (e.g., Daw et al. Reference Daw, Niv and Dayan2005; Johnson & Redish Reference Johnson and Redish2007; Niv et al. Reference Niv, Joel and Dayan2006b; Redish & Johnson Reference Redish and Johnson2007) or on added memory components (e.g., Zilli & Hasselmo Reference Zilli and Hasselmo2008); and habit learning systems (e.g., Daw Reference Daw2003; Doya Reference Doya2000b; Montague et al. Reference Montague, Dayan and Sejnowski1996; Redish Reference Redish2004; Suri Reference Suri2002). However, it is important to note that these models do not directly address the question of “What is a unified action?” as asked by Chambers (see also Chambers et al. Reference Chambers, Bickel and Potenza2007). These questions can be related to early computational models of decision-making at human scales, such as the early models of chunking (Graybiel Reference Graybiel1998; Newell Reference Newell1990).
R3.4. A new framework
Thus, we can re-describe our framework as consisting of three components: Pavlovian (in which actions are evolutionarily driven or “pre-wired” for a given outcome, even when associated with other stimuli:  ; instrumental (in which actions are decided upon through a deliberative search through future possibilities and their consequences:
 ); and habit (cached-action or cached-value systems, in which actions are associated with specific situations, and continued without consideration of the potential outcomes:
 ). (See Table R1.) Our theory posits that all three systems have potential failure-modes which can drive addictive behaviors and that interactions between failures in different systems can drive addictive behavior. For example, Neal & Wood note that habit failures can arise because of an interaction between normal learning mechanisms and faulty decision-making in the planning system.
Three components of the decision-making machine
R3.5. Faulty decision-making in normals
Several commentators (Andreou, Hart & Krauss, Khalil, Lende, Neal & Wood) noted that the simple neuroeconomic hypothesis of maximizing expected utility that we began our target article from has been known to be incorrect for many years. We do not deny that even normals show many non-simple (and non-rational) decision-making processes. For simplicity, we started our theorizing from the maximizing-value neuroeconomic model. We believe that these more complex theories will also have failure-modes.
We note, however, that our theory is, in fact, descriptive and not normative. For example, search is, by definition, incomplete, even in normals (see Vulnerability 5). Nothing in our model guarantees transitivity. Thus, our model does not actually fit the “rationality” definitions identified by Khalil. However, as noted in the target article, other errors exist as well (e.g., judgment errors [Kahneman & Tversky Reference Kahneman and Tversky1979], framing errors [Windmann et al. Reference Windmann, Kirsch, Mier, Stark, Walter, Gunturkun and Vaitl2006], and memory errors [Schacter 2001]). Our argument is that the better our understanding of the decision-making machine, the better our understanding of its potential failure-modes will be, which will lead to better abilities to identify and treat addiction.
R4. A taxonomy of addiction
One of the major claims of our article is that addiction is a spectrum disorder, consisting of many interacting subparts. Hardcastle suggests that health-care providers already view addiction as a multifaceted disorder. Certainly, the subset methodology within the DSM-IV-TR (American Psychiatric Association 2000) and ICD-10 (World Health Organization 1992) would suggest this. However, this view is not shared by all scientists or clinicians as can be seen in the Ross and Le Moal commentaries.
In particular, Hardcastle takes us to task for neither shortening the list nor being complete. If addiction is in truth a spectrum disorder, it may not be possible to shorten the list. Additionally, as noted by MacCoun, which behaviors constitute addictions depend on sociological definitions. Our hope is that by starting from failure-modes of the decision-making machine, we will approach a more parsimonious division of behavior which can improve the ability of clinicians to guide patients to treatment.
R4.1. Is there really one (hidden) unifying principle?
Several commentators suggest that there is really only one unifying principle. However, as noted in the target article, this is belied by the limited success of treatments across the general population (but strong success within subpopulations), by the multifaceted nature of addiction, and by the subset methodologies in the DSM-IV-TR (American Psychiatric Association 2000) and ICD-10 (World Health Organization 1992).
Ross suggests that the underlying principle may arise from timing errors within the dopamine system. However, animals without dopamine will still self-administer drugs (Rocha et al. Reference Rocha, Fumagalli, Gainetdinov, Jones, Ator, Giros, Miller and Caron1998; Volkow et al. Reference Volkow, Fowler and Wang2002), and timing theories of reinforcement do not fit all of the animal-learning literature. The combination of differences between reinforcement (delivery of unexpected reward) and disappointment (non-delivery of expected reward; see Redish et al. Reference Redish, Jensen, Johnson and Kurth-Nelson2007) and timing errors in dopamine is likely to be an important component of some addictions, particularly non-pharmacological addictions, such as gambling, video games, and Internet addictions. However, this combination cannot explain all addictions. It is unlikely to explain addictions with a high predictability of reward-delivery (such as heroin or cocaine). For many pharmacological substances, faster and more reliable delivery methods lead to higher addictive liability (e.g., smoking nicotine vs. nicotine gum vs. the nicotine patch [Henningfield & Keenan Reference Henningfield and Keenan1993], or crack vs. powder cocaine [Balster Reference Balster1973; Reference Balster, Clouet, Asghar and Brown1988; Gold Reference Gold, Lowinson, Ruiz, Millman and Langrod1997]). Nevertheless, Ross's hypothesized interaction is likely an important vulnerability in decision-making systems.
Le Moal suggests that entities should not be multiplied without necessity and accuses us of proposing “one more theory.” However, as noted by Stalnaker & Schoenbaum, many single-process theories have been suggested, and do not fit the data. We disagree with Le Moal's conclusion that all of the neurobiological theories of addiction agree on the network involved in addiction. While the anatomy itself is not in contention, many theorists disagree about the underlying neurophysiology of addiction (for example, compare the different description of the underlying neurophysiology of addiction in Everitt & Robbins Reference Everitt and Robbins2005, in Kalivas et al. Reference Kalivas, Peters and Knackstedt2006, and in Koob & Le Moal Reference Koob and Le Moal2006). Disagreements range through the importance of the role of withdrawal (Koob & Le Moal Reference Koob and Le Moal2006; Robinson & Berridge Reference Robinson and Berridge2003), the role of opioid signals (Laviolette et al. Reference Laviolette, Gallegos, Henriksen, van and Kooy2004), and the role of dorsal striatum (Everitt & Robbins Reference Everitt and Robbins2005). Even within his commentary, Le Moal notes both ventral striatum and prefrontal cortex as separate dysregulations. Although a strong claim of our theory is that there are many dysregulations, it is certainly possible (and likely!) that some processes are more essential than others. Nevertheless, the fundamental claim of our theory is that addiction is a spectrum disorder with multiple underlying etiologies.
R4.2. Can some of the vulnerabilities be merged or combined?
Just as our framework of the decision-making machine is only a first step, our taxonomy of addiction is also only a first step. Several commentators suggested merging some of the vulnerabilities. A final definition of what constitutes a failure-mode, the extent of those failure-modes, and the variability and interaction between them will require more work from both the basic science and the clinical sides.
Goudie et al. suggest merging Vulnerabilities 1 and 2 (the homeostatic and allostatic vulnerabilities). Although both vulnerabilities reflect changes in internal definitions of needs and targets, Koob and Le Moal (Reference Koob and Le Moal2006) make a strong case for separating the concepts of homeostasis and allostasis. Whether a single process can explain (and treat) them or whether they need to be treated separately will depend on future work directly addressing homeostasis and allostasis in the context of decision-making systems. Goudie et al. also suggest that both Vulnerabilities 3 and 4 are examples of positive reinforcement within the planning system. Yet Berridge and Robinson (Reference Berridge and Robinson2003) have shown differences between hedonic reward delivery and overvaluation, suggesting that they arise from different pharmacological processes, which would imply they will have different vulnerabilities to pharmacological manipulation. Similarly, Goudie et al. note that Vulnerabilities 4, 5, 7, and 10 are all examples of hyperlearning, but hyperlearning in planning systems will be very different from hyperlearning in habit systems. As an example of the complexity within this taxonomy, Bickel & Yi suggest merging Vulnerabilities 8 (Interactions between planning] and habit) and 9 (Temporal discounting). These can be seen as two kinds of impulsivity – an inability to inhibit a prepotent response in a go/no-go task (8) and over-fast temporal discounting (9). Yet, Goudie et al. and Lejuez & Potenza note that there are multiple kinds of impulsivity and cite data from Reynolds et al. (Reference Reynolds, Ortengren, Richards and de Wit2006) that there is no correlation between these two experiments. The real question that needs to be addressed is whether the vulnerabilities are clinically separable and clinically treatable as separate processes.
Several commentators noted that these vulnerabilities interact. Bickel & Yi note that sensitivity to price is affected by the availability of substitutes, implying that discounting can interact with homeostatic levels. Berridge et al.'s concept of dynamic motivational control implies a necessary interaction between homeostasis/allostasis and planning systems. Goudie et al. note that homeostasis and attention to cues interact. And Neal & Wood note that the balance between habit and planning is sensitive to normal processes such as stress. Finally, Coventry asks what would large errors in situation recognition (Vulnerability 6) do to small errors in the other vulnerabilities, such as the learning Vulnerabilities 3 to 7? These interactions are only just now beginning to be studied at a computational level (e.g., Daw et al. Reference Daw, Niv and Dayan2005; Dayan et al. Reference Dayan, Niv, Seymour and Daw2006; Niv et al. Reference Niv, Joel and Dayan2006b; Redish et al. Reference Redish, Jensen, Johnson and Kurth-Nelson2007).
R4.3. What about a role for other memory systems in addiction?
Several commentators suggested addiction components not included in the original decision-making taxonomy. In particular, four additional decision-making components were suggested, including negative components (Le Moal, Lende), affective (emotion) components (Kiviniemi & Bevins, Le Moal), Pavlovian components (Ostlund & Balleine), and semantic and working memory components (Wiers et al.).
R4.3.1. Negative components
One of the largest gaps in the theory laid out in our target article is the lack of an explicit role for negative components in the decision-making model. We acknowledge the importance of negative components in decision-making but note a gap in the current computational modeling of decision-making literature. Negative effects (punishments, aversive signals) are treated as negative rewards, and non-delivery of punishments (relief) is treated as positive rewards. Similarly, the non-delivery of positive rewards (disappointment) is treated as negative rewards. Extinction studies demonstrate that aversion is a very different process computationally from non-delivery of expected reward (Redish et al. Reference Redish, Jensen, Johnson and Kurth-Nelson2007).
Even if one follows the concept of aversion and reinforcement as parallel processes (with relief and disappointment as the non-delivery of expected punishments and rewards) (Daw et al. Reference Daw, Kakade and Dayan2002; Redish et al. Reference Redish, Jensen, Johnson and Kurth-Nelson2007), decision-making in the face of aversion is still not parallel (computationally) to reinforcement. With reinforcement, one thing draws an agent to it, other choices can be ignored (except in that they may provide potentially better choices). From a satisficing perspective (Simon Reference Simon1955), after observing a reward, one has information about a minimally successful choice. The potential for improvement must be balanced with the cost of exploration (Stephens & Krebs Reference Stephens and Krebs1987; Sutton & Barto Reference Sutton and Barto1998). In contrast, after a punishment, one only has information about what not to do. The question of what action should be taken still remains unanswered. This has led to a gap in the decision-making literature. We believe that this is an important missing component of the computational literature and that a computational model filling this gap will provide additional vulnerabilities, which will provide important components to our understanding of addiction.
R4.3.2. Emotion and affect – Pavlovian components
Both Le Moal and Kiviniemi & Bevins argue for an important component of affect in the vulnerabilities of addiction. Le Moal seems to attribute all addiction to errors of affect. But this belies the presence of robotic users (Sayette et al. Reference Sayette, Shiffman, Tiffany, Niaura, Martin and Shadel2000; Tiffany Reference Tiffany1990). It also belies addicts' own descriptions, which differentiate “craving” and “withdrawal” (Robinson & Berridge Reference Robinson and Berridge2003). We would suggest that affect must have a computational effect on the decision-making process, perhaps through an interaction between homeostatic and allostatic needs and the other vulnerabilities (Bickel & Yi, Berridge et al., Goudie et al.). Perhaps, emotion and affect are means by which expectancies are evaluated (E(O)→E(V), which would influence Vulnerability 4), or perhaps emotion and affect change the set of actions considered at any time (which would influence Vulnerability 5). Kiviniemi & Bevins suggest the presence of a third action system: 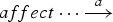 . We suspect that this may be related to the difference between Pavlovian and instrumental conditioning (Ostlund & Balleine; see also Dayan & Balleine Reference Dayan and Balleine2002 and Dayan et al. Reference Dayan, Niv, Seymour and Daw2006), and to the dynamic control of motivation (Berridge et al.). As discussed earlier, one can fold in a model of Pavlovian action selection based on affective implications of expected outcomes
 . The relation of these issues with homeostatic and allostatic changes has only just begun to be studied computationally (Dayan et al. Reference Dayan, Niv, Seymour and Daw2006; Niv et al. Reference Niv, Joel and Dayan2006b). The implications for addiction are well worth additional study.
R4.3.3. Semantic memory, working memory, episodic memory, and so on
Psychological theories of memory include many components beyond the simple “situation-recognition” component discussed in the target article. Recent computational models (e.g., Daw et al. Reference Daw, Niv and Dayan2005; Zilli & Hasselmo Reference Zilli and Hasselmo2008) have begun to explore how working and episodic memory can enable the mechanisms underlying search and planning systems ( ).
Our theory suggests that these memory systems will interact with the decision-making machinery to provide additional vulnerabilities. Taking the example cited by Wiers et al., subjects with poor working memory capacity are more likely to use automatic associations in drug use. In our interpretation, this would be due to a stronger automatic  system. In contrast, Wiers et al. also note that subjects with high working memory capacity are more sensitive to explicit expectancies. Given the likely relationship between working memory, expectancies, and the planning
 system (Redish & Johnson Reference Redish and Johnson2007; Zilli & Hasselmo Reference Zilli and Hasselmo2008; see discussion in target article), users with strong working memory are more likely to fall victim to vulnerabilities in the planning system, whereas users with poor working memory are more likely to fall victim to vulnerabilities in the habit system. This is exactly the major point of our theory: it should be possible to subdivide addictive populations based on neuropsychological tests (strength of working memory) and see differences in the mechanisms underlying their addictions (dependence on expectancies). We predict that these two groups will require different treatment regimens in order to break their addictions.
R5. Predictions and falsifiability
Stalnaker & Schoenbaum ask, How can this theory be tested? What falsifies it? Obviously, if a single, underlying cause of addiction is found (such as suggested by Ainslie, Le Moal, or Ross) or if all addicts pass through a single sequence (as suggested by Le Moal), then our multiple-vulnerabilities theory would be wrong. However, such a clear alternative is unlikely to be found. Instead, we need to identify specific predictions and consequences of our theory.
The key prediction of our theory is that addiction should consist of multiple dissociable, but potentially overlapping, syndromes. This implies that there should be multiple subgroups within addiction, and that each subgroup will need different treatment regimens. We suggest, furthermore, that these subgroups can be best defined by vulnerabilities or failure-modes of decision-making systems. While the specific taxonomy proposed in the target article is certainly incomplete, it can provide a direction with which to proceed in our understanding of addiction. In a sense, as noted by Ahmed, our theory suggests theories of decision-making provide a “space” within which addiction can reside. Each individual will have a different parameter subspace based on that individual's decision-making machinery, which will change the individual's susceptibility to potential addictions. As noted by Ahmed, this implies that there should be species, age, and developmental differences in addictions. We would note also that there should be genetic and experiential (sociological) differences as well.
Different species of animals have different cognitive and decision-making abilities. Although the ability of nonhuman animals to encode non-local information, to create expectancies of their future, and to plan based on those expectancies is still controversial (Buckner & Carroll Reference Buckner and Carroll2007; Johnson & Redish Reference Johnson and Redish2007; Johnson et al. Reference Johnson, van, Meer and Redish2007; Roberts et al. Reference Roberts, Feeney, Macpherson, Petter, McMillan and Musolino2008; Suddendorf & Busby Reference Suddendorf and Busby2003), it is clear that different species have different abilities. In particular, it is clear that different species will show different abilities within planning and habit systems and different balances between these systems, as well as different interactions between them. This means that the availability and likelihood of the available vulnerabilities will differ between species. This also means that a cross-species comparison of behavioral liability to addiction subtypes may be a fruitful avenue for future addiction research.
Ahmed notes that a similar distinction can be made across development. Adolescents and adults have very different addiction liabilities (Casey et al. Reference Casey, Jones and Hare2008; Chambers et al. Reference Chambers, Taylor and Potenza2003; Kelley et al. Reference Kelley, Schochet and Landry2004; Chambers' commentary). These changed behavioral and psychological decision-systems should change the addiction space and provide different vulnerabilities.
Similar arguments can be made as to genetic and structural differences. Each individual's addiction subspace is going to be strongly influenced by its genetic variability. For example, Frank et al. (Reference Frank, Moustafa, Haughey, Curran and Hutchison2007) have shown a triple dissociation with learning rates and three different dopamine-related polymorphisms. Our theory predicts that these effects on learning and decision-making should imply different susceptibilities to different addiction vulnerabilities identified in the target article, the commentaries, and this response.
Chambers suggests that mental illnesses known to change both brain function and decision-making systems could provide insights into these differences. These changed decision-making systems should, again, have different liabilities. This may explain the comorbidity seen between addiction and many mental illnesses.
This suggests a fascinating experimental paradigm in which lesions known to affect decision-making systems (e.g., hippocampus [HC], prefrontal cortex [PFC], different components of striatum) can be predicted to shift the addiction space and thus the availability and likelihood of vulnerabilities and the liability of different aspects of the addiction syndrome.
An additional falsifiable aspect of our theory is that each of the identified vulnerabilities entails a set of predictions. For example, the opiate theory of Redish and Johnson (Reference Redish and Johnson2007) predicts that dopamine will not be released from well-predicted opiate delivery (by analogy to food-reward; Schultz Reference Schultz1998).Footnote 1 If this prediction was found to be wrong, then the opiate explanation for Vulnerability 3 (mimicking reward) would be wrong. However, such a result would not demolish the entire theory. Vulnerability 7, as laid out in Redish (Reference Redish2004), is dependent on the validity of the temporal difference reinforcement learning theory (TDRL) explanation of dopamine signaling (Montague et al. Reference Montague, Dayan, Person and Sejnowski1995; Reference Montague, Dayan and Sejnowski1996; Schultz Reference Schultz1998). If the TDRL explanation for dopamine signaling is wrong (Berridge Reference Berridge2007), then Vulnerability 7 is wrong. But again, such a result would not demolish the multiple-vulnerabilities theory itself.
R5.1. A framework within which to search for other vulnerabilities
Scientific theories have many purposes beyond providing predictions to disprove. They also provide a framework within which to place and understand questions and answers (Ben-Ari Reference Ben-Ari2005; Mayr Reference Mayr1998). Our theory provides just such a framework for addiction. It says that addiction arises as failure-modes of decision-making. Our theory thus suggests a path for future work to (1) elucidate the decision-making system, and (2) look for failures within it. A recent very exciting example is that of Chiu et al. (Reference Chiu, Lohrenz and Montague2008) who found that smokers' brains reflect fictive learning signals, but do not respond to them. Chiu et al.'s work implies the presence of an as-yet-unspecified vulnerability in this disconnect that can be looked for and identified.
R6. Additional vulnerabilities
In the target article, we argue that there are vulnerabilities in the decision-making machinery of humans and animals, and we identified ten potential vulnerabilities. As explicitly noted in the target article, that list is not complete. Several of the commentators suggested additional vulnerabilities.
Vulnerability 11: Errors in expectations
Boden notes that in addition to errors in valuation, the planning system can also include errors in the actual outcome expectations. In a sense, these are errors in the calculation of the outcome to expect in the  relationship. In the computational language of model-based reinforcement learning paradigms (Daw et al. Reference Daw, Niv and Dayan2005; Niv et al. Reference Niv, Joel and Dayan2006b), it entails errors in the calculation of the probability distribution
 . It would have effects similar to Vulnerabilities 3 (Mimicking reward), 4 (Overvaluation in planning systems), and 5 (Errors in the search process). In particular, social expectations (Goudie et al., Griffiths, Hardcastle, Hart & Krauss, Kiviniemi & Bevins, Lende) can change expected outcomes and thus lead to incorrect expectations. Examples include alcohol expectancy theory (Goldman et al. Reference Goldman, Brown, Christiansen, Blaine and Leonard1987; Reference Goldman, Boca, Darkes, Leonard and Blane1999) in which expectations of consequences of drinking lead to increased or decreased drinking, particularly under conditions in which the planning (expectancy) system is more active (Wiers et al.). A similar issue can be identified in misapplication of probability of outcome and misunderstandings of statistics (Ainslie, Goudie et al., Ross).
Vulnerability 12: Errors in construction of past memory
As noted by Neal & Wood, errors in construction of past memory of success can change the expectation and evaluation of future consequences (Gilovich et al. Reference Gilovich, Griffin and Kahneman2002; Kahneman & Frederick Reference Kahneman, Frederick, Gilovich, Griffin and Kahneman2002; Schacter Reference Schacter2001).
Vulnerability 13: Timing errors
Differences between reinforcement and disappointment (Redish et al. Reference Redish, Jensen, Johnson and Kurth-Nelson2007) mean that multiple samples of unpredictable reinforcement scattered among unpredictable lack of delivery of expected reward will lead to excess reinforcement. As noted by Ross, either timing errors (Daw Reference Daw2003) or unpredictable timing (such as seen in video games, gambling, and Internet packet delivery) can lead to an inability for predicted δ signals to cancel out appropriately.
Vulnerability 14: Pavlovian and affective errors
As discussed earlier, our two-system theory ( vs.
 ) is incomplete and needs to incorporate a Pavlovian
 component based on evolutionary precompiled actions taken in response to affective responses to situation-outcome associations (Kiviniemi & Bevins, Ostlund & Balleine). This system and its interaction with the other systems will provide additional vulnerabilities that will need to be incorporated into the theory (Balleine Reference Balleine, Mowrer and Klein2001; Reference Balleine, Whishaw and Kolb2004; Breland & Breland Reference Breland and Breland1961; Dayan et al. Reference Dayan, Niv, Seymour and Daw2006).
Sarnecki et al. expand on one aspect of Vulnerability 10 (Learning rate modulators), which they call “cue fascination.” The concept is that cues become goals or targets in their own right (Ainslie). It should be noted that this is a key concept within many learning theories, including both Pavlovian conditioning (Dickinson Reference Dickinson1980; Mackintosh Reference Mackintosh1974) and temporal difference reinforcement learning theory (Montague et al. Reference Montague, Dayan and Sejnowski1996; Redish Reference Redish2004; Sutton & Barto Reference Sutton and Barto1998). Goudie et al. suggest that attentional biases interact with craving, so that craving can cause and be caused by excess attention to cues. The underlying etiology of craving is an open question that will require additional experiments in the context of decision-making (Niv et al. Reference Niv, Joel and Dayan2006b; Redish & Johnson Reference Redish and Johnson2007).
Vulnerability 15: Interactions with standard behavioral learning mechanisms
Continued use of drugs through one vulnerability can lead to learning through normal behavioral learning mechanisms, even if there is nothing explicitly failing about the other mechanisms. For example, Neal & Wood note that habits are generally hard to break – inhibition of a well-trained response is difficult and requires effort (Dickinson Reference Dickinson1980; Gray & McNaughton Reference Gray and McNaughton2000; Husain et al. Reference Husain, Parton, Hodgson, Mort and Rees2003; Isoda & Hikosaka Reference Isoda and Hikosaka2007; Iversen & Mishkin Reference Iversen and Mishkin1970; Sakagami et al. Reference Sakagami, Pan and Uttl2006). This means that continued drug use due to a planning vulnerability (e.g., Vulnerability 3: Mimicking reward, or Vulnerability 4: Overvaluation in the planning system) can lead to development of a habit through normal mechanisms. Intransitive preferences (Ainslie Reference Ainslie1992; Reference Ainslie2001; Rachlin Reference Rachlin2004), normal procrastination effects (Andreou Reference Andreou2005; O'Donoghue & Rabin Reference O'Donoghue and Rabin1999a), and switching costs of decision making (Wood & Neal Reference Wood and Neal2007), can lead to continued use once started (perhaps because of one vulnerability, e.g., Vulnerability 1: Homeostatic effects) despite a lack of additional failures of the decision-making system (Andreou, Neal & Wood).
Vulnerability 16: Implications of social issues
Some commentators (Boden, Griffiths, Lende) suggested components occurring at other than neurophysiological levels, for example, those arising from social issues. These commentators asked about the implication of levels of analysis, particularly raising social and ethnographic reasons for drug taking, seeking, and continued use. Our claim that addiction arises from errors in decision-making would imply that these social interactions would be reducible (perhaps through a complex mechanism) to changes in expectations, valuations, and action-selection.
Taking the example by Lende that some people use amphetamine to increase skills,Footnote 2 our argument is that this increased skill use is an expectation of the future  . Ignoring the potential downside of continued use can be seen as incorrectly calculating the expectation of the future (an error in
 , see above) or incorrectly evaluating that expectation (Vulnerability 4). The examples given by Hart & Krauss and Griffiths relating peer behavior and other psychosocial factors imply changes in expectations and evaluations. Boden explicitly suggests this, noting that social interaction can drive overvaluation (peer pressure, Vulnerability 4), that social context can stimulate memory retrieval and can increase recall (changing search parameters, Vulnerability 5), and that over-generalization (Vulnerability 6) can lead to a lack of appreciation of the dangers of moving from low-risk (gateway) drugs to high-risk drugs.
R7. Treatment and assessment
We end our response with a discussion of the implications of our theory for the clinical and policy realms.
From a clinical perspective, the main implication of our theory is that because each addict's problem will be due to a spectrum of vulnerabilities/failure-modes, each addict will require a treatment regimen guided towards those vulnerabilities. These implications can be contrasted with molecular theories (Yin; e.g., Nestler Reference Nestler2005) and other theories of unified causes for addiction (e.g., Le Moal), which would imply that there would exist a single magic bullet treatment for all addicts. Our theory suggests that such a magic bullet does not exist.
Several commentators have brought up the question of how the individualized treatment regimen suggested by our theory would work in practice (Goudie et al., Hardcastle). Hardcastle notes that many clinicians already individualize treatment. This is certainly true in practice, and we review several examples further on. However, we suggest that because the effects of these treatments on decision-making systems are not known, it has been difficult to steer addicts to appropriate treatments, or to determine how treatments might interact to provide a potential individualized treatment regimen. A similar discussion can be made as to policy, including the effect of taxes, criminal punishments, education, and interdiction (MacCoun). There are many treatments currently being used for addiction, including providing alternative rewards and vouchers (Higgins et al. Reference Higgins, Alessi and Dantona2002, Reference Higgins, Heil and Lussier2004), behavioral (Carroll et al. Reference Carroll, Kosten and Rounsaville2004), and social treatments (e.g., 12-step programs), as well as various pharmacological treatments (Grant et al. Reference Grant, Potenza, Hollander, Cunningham-Williams, Nurminen, Smits and Kallio2006; Hyman Reference Hyman2005; Meyer & Mirin Reference Meyer and Mirin1979; O'Brien et al. Reference O'Brien, Volpicelli and Volpicelli1996). In general, treatments work very well for subpopulations. Subpopulations within addicted groups have been found in alcoholism (Addolorato et al. Reference Addolorato, Leggio, Abenavoli and Gasbarrini2005; Crabbe Reference Crabbe2002; Nurnberger & Bierut Reference Nurnberger and Bierut2007; Stalnaker & Schoenbaum, Wiers et al.), in nicotine addiction (Irvin & Brandon Reference Irvin and Brandon2000; Irvin et al. Reference Irvin, Hendricks and Brandon2003), and in gambling (Grant et al. Reference Grant, Potenza, Hollander, Cunningham-Williams, Nurminen, Smits and Kallio2006; Sharpe Reference Sharpe2002; Coventry, Lejuez & Potenza, Griffiths).
Lejuez & Potenza note that there is more to treatment than correcting errors. This is an important insight and may lead to alternative methods that could enable addicts to behaviorally prevent relapse even without directly eliminating the active vulnerability. For example, there may be treatments that can change the balance between planning and habit systems as a means of decreasing the influence of one or the other (Bickel & Yi). Treatments will presumably move patients to new portions of the addiction-space. An important question then is: What are the trajectories of patients within treatment? Different treatments will move different subpopulations in different ways. It is even possible that some treatments will shift different subpopulations toward other, previously unrealized vulnerabilities.
We suggest that two important next steps in addiction research are:
1 To develop clinical tests that could differentiate subpopulations. For example, the differences in working memory noted by Wiers et al. could be used to steer different subpopulations of alcoholics to different treatments. As another example, the identification of subjective craving in gamblers allowed Grant et al. (Reference Grant, Potenza, Hollander, Cunningham-Williams, Nurminen, Smits and Kallio2006) to find significant success with Nalmefene in treating problem gambling. Our hope is that our theory provides a framework within which such clinical tests can be situated.
2 To identify the effects of known (or novel) treatments on the decision-making system, particularly on vulnerabilities within the decision-making system. For example, Hart & Krauss note the remarkable success of providing small alternate rewards (such as $5 vouchers) for abstinence. Raising drug prices by $5 would not lead to a similar success. So what is it about actually being forced to make a decision with an explicit alternate choice that helps some addicts maintain abstinence? Our hope is that our theory provides a framework within which to explain those treatments.
R8. Policy, framing, philosophical space
As noted by some commentators (Griffiths; MacCoun), the key question for addiction is that of framing and policy. Approximately a decade ago, addiction was reframed by Leshner (Reference Leshner1997) and others (e.g., O'Brien & McLellan Reference O'Brien and McLellan1996; O'Brien et al. Reference O'Brien, Volkow and Li2006) as a chronically relapsing, remitting disorder or disease. In doing so, these scientists moved addicts from sinners to be reviled to patients to be treated. Unfortunately, as also noted by MacCoun, the neuroscience complicates rather than simplifies the drug policy analysis.
But we believe the first question is actually: What is addiction? Like many definitions of addiction, we started from a definition of addiction as maladaptive decisions, but this is, of course, insufficient. There are many cases in which we celebrate choices made despite negative consequences. For example, we celebrate Martin Luther King going to jail for his beliefs. Or perhaps, even more specifically, we celebrate the middle-class whites who left their homes and comfort to march with Dr. King. It would be ludicrous to say that they were addicted to marching for civil rights for others. As another example, Osip Mandelstam continued to write poetry after he was thrown in the Soviet gulag. Do we really want to say that he was addicted to poetry?
In order to step away from this controversy, the DSM-IV-TR and ICD-10 do not use the word “addiction” and instead refer to “dependence.” This leads to a difficulty in defining non-pharmacological behaviors as addictive (e.g., gambling, shopping, sex, or Internet addictions) (Holden Reference Holden2001; Potenza Reference Potenza2006; Potenza et al. Reference Potenza, Kosten and Rounsaville2001; Griffiths). Even in the context of pharmacological addictions, current clinicians have begun arguing for a return to the term “addiction” (O'Brien et al. Reference O'Brien, Volkow and Li2006, Hart & Krauss).
As noted by Griffiths, addiction is a contextual and socially constructed term. It is dependent on the policy implications of the behavior and on the social disapproval of said behavior. But again, there are behaviors that are maladaptive, socially disapproved of, but not addictive.
One thing that is clear from the commentaries is that few people seem to agree on the core features of addiction. This is part of what makes addiction such a difficult and controversial issue. We believe that our vulnerabilities view may be able to unify some of the debate by asking how animals (including humans) make decisions and starting to examine the definition of addiction as failures in those decision-making systems.
ACKNOWLEDGMENTS
We would like to thank the anonymous reviewers who helped us improve our earlier drafts of the target article, as well as the many commentators who provided a lively discussion. This work was supported by a Career Development Award from the University of Minnesota TTURC (to A. David Redish, NIH NCI/NIDA P50 DA01333), and by a doctoral dissertation fellowship from the University of Minnesota Graduate School (to Adam Johnson).