INTRODUCTION
Overview
There is now firm evidence to link mental disorder and violence. Major mental disorder increases the risk of criminality (Hodgins, Reference Hodgins1992) and a diagnosis of schizophrenia carries an increased risk of violent and non-violent crime compared with the general population (Hodgins et al., Reference Hodgins, Mednick, Brennan, Schulsinger and Engberg1996). For example, Arsenault et al. (Reference Arsenault, Moffitt, Caspi, Taylor and Silva2000) found that people under 21 years of age with schizophrenia were over five times more likely to be violent than those without mental illness. People with serious psychiatric disorders are often themselves the target of bullying and violence (Estroff et al., Reference Estroff, Jeffrey and Swanson1998).
The comorbid use of alcohol and illicit drugs increases the risk of violence. The Epidemiologic Catchment Area Surveys indicated that people with schizophrenia had a fourfold increase in the risk of violence and whenever substance misuse was present the risk further elevated to more than six times the risk compared to persons with no diagnosis (Swanson et al., Reference Swanson, Holzer, Ganju and Jono1990). In the McArthur Violence Risk Assessment Study the rates of violence was 18% in subjects with mental disorder. This escalated to 31% when substance misuse was present and even further to 43% when personality disorder or adjustment disorder was present (Steadman et al., Reference Steadman, Mulvey, Monahan, ClarkRobbins, Appelbaum, Grisso, Roth and Silver1998).
Given the impact of substance misuse on violent behaviour in the psychiatric population it seems pertinent to identify and manage the problem. On general psychiatric wards nearly a quarter of patients who underwent urine drug screens tested positive (Ley et al., Reference Ley, Jeffery, Ruiz, McLaren and Gillespie2002), and there is evidence that illicit drugs are finding their way onto the wards (Phillips & Johnson, 2003; Dolan & Kirwan, Reference Dolan and Kirwan2001), e.g. via visitors or people's regular dealers (Phillips & Johnson, Reference Phillips and Johnson2003). In the efforts to combat violence the need for assessment of risk factors such as substance misuse, anti-social personality disorder and conduct disorder has been drawn sharply into focus (Hodgins & Müller-Isberner, Reference Hodgins and Müller-Isberner2004).
This paper presents an analysis of data from the fourth National Audit of Violence on inpatient psychiatric units (McGeorge et al., Reference McGeorge, Shinkwin and Hinchcliffe2008) specifically relating to drugs and alcohol use. The Royal College of Psychiatrists’ Research and Training Unit (CRTU), in particular the College Centre for Quality Improvement (CCQI), was tasked with coordinating the nationwide effort on behalf of the Healthcare Commission.
The previous audit for the Healthcare Commission was completed in 2005 (Healthcare Commission, 2005). The CRTU then audited 184 psychiatric wards against clinical practice guidelines and evaluated the opinions of both staff and patients. One of the major findings arising from this project was the frequent reported association between alcohol and drugs and inpatient violence (Chaplin et al., Reference Chaplin, McGeorge and Lelliot2006). Others have shown that the problem of violence in PICUs is a complicated one that has a variety of origins and that management of it can be problematic (Dawson et al., Reference Dawson, Kingsley and Pereira2005).
Aims
This study aims to determine: 1) the numbers of patients and nurses who are assaulted on PICUs and compare this with acute and forensic wards; 2) whether nurses or patients were more likely to report problems with alcohol or drugs; 3) whether there are differences between types of wards on nurses’ perception of the cause of problems and 4) whether drugs or alcohol are more likely the cause of problems. In addition, it will explore qualitatively the views of patients and visitors on the triggers of violence on the ward and the views of staff on particular problems and potential solutions.
METHOD
Sixty-nine English and Welsh National Health Service Trusts and independent sector providers enrolled and nominated three wards for the national audit programme. A total of 215 wards took part in the whole programme of which 76 were in the older adult sector (these were analysed in a separate paper and were therefore excluded from this report). This left 139 wards serving adults of working age, of which 27 were psychiatric intensive care units, 89 were acute adult wards and 17 were forensic wards (the remaining 6 were rehabilitation wards and are not discussed further).
Anonymous questionnaires were developed for staff and patients based on the clinical practice guidelines for the short term management of violence in inpatient psychiatric settings (National Institute for Clinical Excellence, 2005). Nurses and patients were asked regarding violent behaviour on this ward ‘Have you ever been physically assaulted’ although they were not asked to state a time frame for this. Physical assault was not defined, however they were asked about feeling threatened, made to feel unsafe and feeling upset or distressed by a patient's violent behaviour in other questions which are not reported here. In addition they were asked whether there ‘Is there ever any trouble on the ward because of patients getting drunk or taking illegal drugs’ and to identify triggers for violence. Anonymous postal questionnaires were distributed to nursing staff from the local project teams of each trust. Teams were advised to distribute questionnaires to the patients currently admitted to the wards using systems independent of staff, for example using advocates, or service user representatives. There were no repeat distributions of reminders.
The qualitative data were coded according to themes by authors IL and RC. Eleven feedback events were facilitated by staff from the quality improvement department of the Royal College of Psychiatrists’ Research Unit at the end of the audit, and attended by 52 teams in total. Subjects for discussion were chosen by the groups’ participants. Three were chosen from a list of six provided by the facilitators. This list arose from subjects discussed on previous National Audits of Violence. This paper reports on two discussion groups where the author IL transcribed notes and the 12 ward teams involved chose to debate alcohol and drug use and its impact on inpatient violence. Participants were aware that the contents of their discussion could be presented in the National Audit Report.
Chi-square analysis with one degree of freedom was used to analyse outcomes between groups. Content of the discussion groups was analysed independently according to themes by IL and RC.
RESULTS
From a total of 2671 responses, most questionnaires came from acute wards (1848, 69%), followed by PICUs (442, 17%) and forensic wards (381, 14%). Of these, nurse responses totalled 1690 (63%) and patient responses 981 (37%).
Experience of assault
Of nurse respondents working on acute wards, 489/1084 (45%) reported having been physically assaulted. Nurses working on PICUs (190/313, 61%) were significantly more likely to report assault than their colleagues working on acute wards (χ2 = 22.7, p < 0.0001), while nurses on forensic units (91/275, 33%) were significantly less likely to do so (χ2 = 12.9, p = 0.0003). Patients on PICUs were more likely to report physical assault (31/117, 25%) than their counterparts on acute wards (105/707, 15%; χ2 = 9.8, p = 0.0017) but not on forensic wards (24/97, 23%; χ2 = 0.08, p = 0.77).
Problems associated with alcohol and drug use
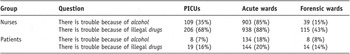
Across all wards, nurses were much more likely than patients to report overall problems with drugs (χ2 = 812.6, p < 0.0001) and alcohol (χ2 = 560.2, p < 0.0001). Table 1 shows more nurses than patients on all three types of ward perceiving that problems resulted from the use of drugs than alcohol. On acute wards significantly more nurses felt drugs, compared with alcohol were the cause of problems (χ2 = 4.7, p = 0.03). On forensic wards highly significantly more nurses thought drugs rather than alcohol were the cause of problems (χ2 = 52, p < 0.0001). This was also the case on PICUs (χ2 = 65, p < 0.0001). The numbers of patients were too small to permit statistical comparisons between the different types of units.
Alcohol and drug problems according to type of ward

Alcohol and drug use by type of ward
Table 1 shows that nurses on PICUs were less likely to consider alcohol to cause violence compared with acute ward nurses (χ2 = 310.1, p < 0.0001) but more likely than forensic ward nurses (χ2 = 31.5, p < 0.0001). Nurses on PICUs (68%) were also less likely to consider drugs caused violence than acute ward nurses (88%, χ2 = 74.1, p < 0.0001) but more likely than forensic ward nurses (43%, χ2 = 34.6, p < 0.0001).
Personal searches
Personal searches may restrict drug and alcohol use by preventing these substances from coming onto the wards. Searches were reportedly carried out by 58% of nurses on acute wards, 66% on PICUs and 72% on forensic wards. However, few nurses from the total sample who responded reported having received training in this: Compared with nurses on forensic wards (60%), nurses on PICUs (43%, χ2 = 12.18, p = 0.0005) and acute wards (34%, χ2 = 40.08, p = 0.0001) were much less likely to receive ongoing and regularly updated training.
Availability of substances to patients on leave
Permission for patients to leave the ward may result in increased availability of alcohol or drugs: this was reportedly available to 66% of patients on PICUs, 78% on acute wards and 89% on forensic wards.
Triggers for violence
Of the 981 patient respondents, 253 patients from acute wards, 54 patients from PICUs and 37 from forensic wards offered a free text response to the question: ‘Is there anything that ‘triggers’ severely challenging/violent behaviour?’. Of those who specified a trigger, 40/981 (4%) named drugs and an additional six patients specified withdrawal states.
On acute wards the six most common triggers for violence were reportedly: illness/personality factors of the patients (46 comments from a total of 751 respondents), neglect from staff (34), violence resulting from interaction between patients (28), boredom / lack of activity (27), drugs and alcohol (27 and an extra 3 mentioned withdrawal) and restriction (26). On PICUs, the most commonly reported triggers were: restriction (9 comments from a total of 124 respondents), violence resulting from interaction between patients (8), smoking (8), illness (6), staff provocation (6) and privacy (6). On forensic wards the triggers were: other patients (14 comments from a total of 106 respondents), environmental (8 comments including dirty crockery, loud noise), restriction (6) and illness / personality factors (6).
Qualitative data from the feedback events
Discussion initially centred on substance use screening, which was largely considered negative as the outcome of a positive screen led to progressive loss of a patient's leave or discharge signifying a therapeutic failure. Other staff highlighted that patients were not given enough time to tell their side of the story when they returned a positive screen to discuss the antecedents of substance use. Staff also reported a perception that little was generally done to explore the consequences of patients using drugs on the ward. In some units staff had stopped screening procedures as a result of these experiences. They experienced the issue of screening as a testing time for the trust patients have in them and their potential punitive role when patients are caught using and thereby risking the quality of the therapeutic relationship.
These negative perceptions about the role of screening were further illustrated by reports that other colleagues having their own views on substance use for example not disapproving of occasional cannabis use by an inpatient as long as it was done away from others. In addition to staff attitudes toward substance use the practicalities of dealing with it were also challenging with group members remarking on the difficulty of arranging for police drug sniffer dogs to come to their unit.
The discussion then moved to potential solutions being suggested. Some of the participants felt there should be a dedicated ‘lapse review’ to identify high risk situations for substance use and attempts to avert it. A participant raised the point that very little was being done to investigate the extent of craving in patients. It was suspected that an intervention aimed at this early stage of relapse could have bigger impact compared to a later stage. Although motivational interviewing techniques were considered to be a potentially helpful tool, staff did not receive formal training to administer it.
Further initiatives suggested by the discussion groups included ‘friendly inter-ward or inter-wing competitions’ that could draw patients together. Strategies suggested included rewarding the longest time without use and rota for displaying posters or information sheets to raise awareness on substance misuse and related topics such as infections, complications of use and sexual dysfunction.
Participants identified a need for training on substance misuse which could be as simple as improving basic awareness of the problem. An introductory tutorial and an ongoing programme of training including brief motivational interviewing skills were strongly recommended.
DISCUSSION
Main findings
Nursing staff on PICUs are more likely to report having been physically assaulted compared with nurses on both acute adult and forensic wards. Patients were significantly more likely to report assault on PICUs compared with patients on acute wards, but not significantly more so than patients on forensic wards. Across all types of ward, nursing staff were more likely than patients to report drugs and alcohol as the cause of violence. Fewer nurses reported violence due to drugs and alcohol on PICUs compared to acute adult wards. On PICUs and forensic wards nurses believed that drugs were more likely than alcohol to be the cause of violence. Many nurses on PICUs carried out personal searches but a minority had received training in this.
From the free-text responses it emerged that drugs and alcohol (including withdrawal states) was one of the top six triggers for violence across all three types of ward. Further qualitative data from the feedback events revealed that participants believed screening for drug and alcohol use was important but that they were reluctant to employ such measures because of practical implications and adverse outcomes for the patient. Participants proposed educational initiatives and substance misuse training as interventions that could address the problem of substance use on psychiatric wards.
Comparison with other studies
Illicit drug and alcohol use has been considered by staff to be a major problem on acute wards and an important contextual determinant of risk (Quirk et al., Reference Quirk, Lelliot and Seale2004). The association of drug and alcohol misuse in individuals with mental health problems and its relevance in violence has been demonstrated (Swanson et al., Reference Swanson, Swartz, Van Dorn, Elbogen, Wagner, Rosenheck, Stroup, McEvoy and Lieberman2006), but the use of substances in the psychiatric intensive care population has its own dangers and implications (Beer, Reference Beer2007). Even in difficult to engage populations such as the subjects of the PAN-London Assertive Outreach Study (Priebe et al., 2003), a consistent finding is that more individuals with mental illness misuse or are dependent on illicit drugs than alcohol. Up to 20% of this sample misused or were dependent on drugs compared to 16% for alcohol. This is a significant finding if it is kept in mind that more than 50% were admitted compulsorily in the last two years prior to the project and during the same period they had spent an average of 44 days in hospital (Priebe et al., Reference Priebe, Fakhoury, Watts, Bebbington, Burns, Johnson, Muijen, Ryrie, White and Wright2003).
Psychiatric treatment facilities were once described as ‘closed’ institutions because the patients within them were cut off from the outside world (see for example Goffman, Reference Goffman1961). Others have argued that today's acute wards are, in contrast, better understood as ‘permeable institutions’ (Quirk et al., Reference Quirk, Lelliott and Seale2006) because of their greater open-ness to the outside world, as manifest in things such as a ward's location within the patient's community rather than out of town, patients frequently leaving and returning to the ward, the use of mobile telephones and the receipt of many visitors. The many obvious benefits of permeability, including the reduced risk of institutionalism, is balanced by the potential for negative consequences, such as the increase in illicit drug use due to the comparative ease by which substances can get onto the wards (Quirk et al., Reference Quirk, Lelliott and Seale2006).
In the present study, acute wards, with high rates of violence relating from alcohol and drugs linked with high numbers of patients receiving leave, represent a comparatively ‘permeable’ environment. The even higher number of patients receiving leave on forensic wards was not associated with high rate of substance use related violence; we speculate that this is probably due to patients’ on leave being escorted by nursing staff (this was not specifically enquired about in the study). Forensic wards can be understood as representing a comparatively closed, traditional type of ward, while PICUs – with rates of substance-related violence midway between acute and forensic wards – can be considered to have intermediate permeability compared with acute and forensic wards.
The finding that drugs were perceived to cause more problems than alcohol on PICUs and forensic wards, but with the difference less marked on acute wards, may also be understood in terms of the concept of ‘permeability’. It may be easier to conceal alcohol use in a less secure environment, whereas on PICUs and forensic wards illicit drugs may be harder to detect. The searching of patients may also be considered a practice in line with the openness of a ward, with it occurring less (and staff being trained less) on more open wards. Paradoxically, searching seems more necessary on acute wards and PICUs considering the higher rates of alcohol and especially drug related violence.
However, restriction on patients or staff provocation may result from the efforts of staff to limit dug and alcohol use, for example by the use of searches. Hence drug and alcohol use and attempts by staff to deal with it may both be potential triggers to violence (Mellesdal, Reference Mellesdal2003).
Strengths and limitations
The data under discussion were derived from an extensive nationwide audit and thus reflect large numbers of respondents from multiple centres, but response bias may operate as NHS trusts were voluntarily assigning their units to take part. There was no randomisation process involved when trusts selected wards to complete the questionnaires and a response rate could not be calculated given the method employed in their distribution.
CONCLUSION
Being a victim of violence is a common experience for staff working on PICUs and appears to be a higher risk than for those working on acute or forensic wards. It is often, in the opinion of nurses and patients, associated with alcohol and drug use amongst the patients. Improvements need to be made to staff training on the reasons people with mental illness use substances. Also those working in PICUs need specific training in performing personal searches. However the efforts of staff to reduce the use of substances on the ward through this measure may be an important factor in the escalation of violence when it is perceived as provocation or harassment.
Potential factors that could perpetuate the use of alcohol and drugs on such a unit are staff attitudes toward screening and substance misuse, the ‘permeability’ of PICUs and insufficient time for staff to discuss antecedents to use. Psychiatric intensive care units are under pressure to deal with the demand to treat patients who have acute and often temporary high levels of disturbance and cope with the difficulties of a rapid patient turnover. This paper suggests that initial efforts to reduce substance misuse related violence could focus on drugs rather than alcohol.
Acknowledgements
We would like to thank Maureen McGeorge, Graham Hinchcliffe and Leanne Shinkwin without whom this work would not have been possible.