Introduction
Following tympanomastoid surgery, it is essential to create a large external auditory meatus in order to ensure a well-aerated, non-discharging cavity. An adequately sized meatus promotes a dry ear by allowing ventilation of an open cavity and facilitating the natural outward migration of squamous epithelium. It also facilitates easier post-operative access for cleaning the cavity in the out-patient clinic. Following mastoid surgery, the bony cavity extends as high as the tegmen tympani, but the meatoplasty is usually created lower than this, and migrates lower still with time.
Various meatoplasty techniques have been described.Reference Raut and Rutka1–Reference Ali10 Most involve the creation of concho-meatal skin flaps and the debulking of soft tissue with cartilage excision. The disadvantage of many of these techniques is that they widen the meatus in its posterior and inferior parts, rather than superiorly where the attic has been opened. One is often looking up into the cavity, and access and cleaning can be challenging and uncomfortable for patients. Many old mastoid cavities need cleaning by laterally flexing the patient's neck to look up into the cavity.
Another issue is the inferior and anterior migration of the pinna in relation to the bony cavity, as a result of surgical disruption of the ligaments and muscles supporting the outer ear.
The pinna is attached to the skull by multiple ligaments and muscles. There are two main ligaments: the anterior and posterior ligament. The anterior ligament extends from the tragus and spina helicis to the root of the zygomatic process of the temporal bone. The posterior ligament passes from the posterior surface of the concha to the outer surface of the mastoid process. Attached to the auricular perichondrium are three extrinsic auricular muscles radiating out to insert into the epicranial aponeurosis.
Inferior and anterior migration of the ear can result from surgical disruption of these elements, particularly the suspensory ligaments of the ear. AliReference Ali10 described multiple factors associated with inferior migration of the pinna following ear surgery. These comprise: detachment of ligamentous support of the cartilaginous canal; loss of periosteal continuity; loss of ear canal continuity; drilling of the posterior bony canal; partial excision of ear cartilage; post-operative oedema; poor head bandage placement; and contraction of scar tissue and auricular cartilage.
The present paper presents a new, previously unpublished technique of helix advancement meatoplasty, which overcomes the problems of inferior positioning of the meatus and inferior migration of the pinna following tympanomastoid surgery. It allows the meatoplasty to be created at the level of the tegmen tympani, and to remain there.
Indications
Helix advancement meatoplasty was originally developed for ear surgery camps in developing countries, where large, dependable meatoplasties are of critical importance as patient follow up can be poor.
The authors do not suggest that this technique is necessary for every tympanomastoid procedure, but it is particularly useful in cases of revision mastoid surgery, keratitis obturans, refractory or chronically discharging mastoid cavities, and revision canaloplasty. The technique has also proved very useful in primary mastoidectomy cases in which the cavity formation is higher than normal, and in cases where there is likely to be further growth of the pinna.
Surgical technique
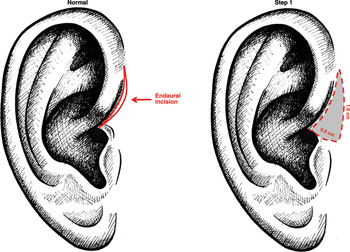
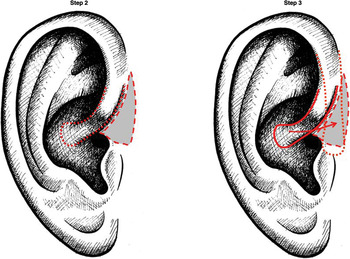
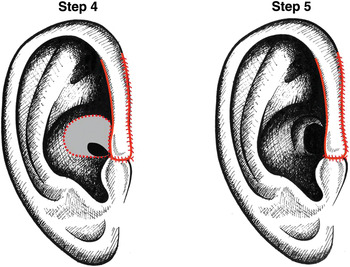
After completion of the mastoidectomy or canaloplasty, the following steps are performed (Figures 1 to 3).
An inferiorly based, triangular piece of skin and soft tissue measuring approximately 0.8 × 1.6 cm is excised anterior to the root of the helix (step 1), thus ensuring that skin overlying the superior part of the tragus is also excised.

The helix is released from the superior conchal bowl and the root of the helix is dissected from the surrounding soft tissues (step 2); it is then rotated anteriorly into the defect, and sutured to the tragus using 4/0 vicryl (step 3).

A superior ellipse of conchal bowl and scaphoid fossa cartilage is excised (step 4) (this is higher than in the standard excision, which usually involves the conchal bowl only). The skin of the concho-meatal flap is placed into the mastoid cavity (step 5).

Firstly, an inferiorly based, triangular piece of skin and soft tissue is excised anterior to the root of the helix, measuring approximately 0.8 × 1.6 cm. Skin overlying the superior part of the tragus is also excised.
The helix is then released from the superior conchal bowl (it inserts into the concha, dividing it into the scaphoid fossa above and the conchal bowl below).
Next, the root of the helix is dissected from the surrounding soft tissues and rotated anteriorly into the defect and sutured to the tragus using 4/0 vicryl.
A superior ellipse of conchal bowl and scaphoid fossa cartilage is then excised. (This is higher than the standard excision, which usually involves mainly the conchal bowl.)
Following this, the skin of the concho-meatal flap is placed into the mastoid cavity.
Finally, the cavity is packed with ribbon gauze soaked in bismuth iodide paraffin paste. This is left in place for up to three weeks.
Advantages
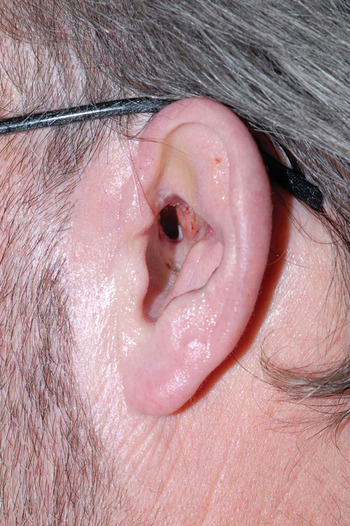
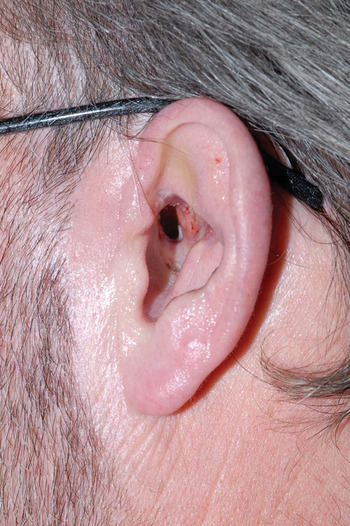
Helix advancement meatoplasty prevents inferior meatal migration by supporting the helix on the tragus. This, together with the higher excision of the scaphoid fossa and the conchal bowl, enables a direct view into the mastoid cavity (Figure 4), facilitating easier aural toilet and superior cavity aeration.
Post-operative photograph showing a direct view into the mastoid cavity. Very few patients are concerned with the cosmetic appearance.
Limitations
Patients may report some dissatisfaction with the cosmetic appearance of the pinna following the described procedure. However, this is also seen with other wide meatoplasties.Reference Ali10
Conclusion
The described technique of helix advancement meatoplasty is a predictable and reliable method of creating a wide, well-placed meatoplasty and overcoming later inferior migration of the meatus.