Introduction
Adenoid cystic carcinoma represents 3 per cent of all neoplasms of the head and neck, and it is the most common malignant tumour of the submandibular and minor salivary glands.Reference Bradley1 Local and distant recurrence is common in this patient population, regardless of treatment modality.
Well designed, randomised trials are made difficult by small numbers and heterogeneous tumour subsites requiring long-term follow up. Consequently, information about appropriate management is limited to retrospective reports from small series and personal reflections from experienced surgical oncologists. Controversy exists, therefore, about whether patients should undergo more radical treatment with higher morbidity for the sake of a small or dubious increased long-term cure rate, or whether less morbid treatment with a higher chance of short-term tumour morbidity would be preferable.
This study compared the outcomes of patients whose adenoid cystic carcinoma of the head or neck was treated by surgery plus post-operative radiotherapy, or by surgery alone or radiation alone. The patient cohort studied represented individuals treated over the last 40 years at the University of Iowa Hospitals and Clinics. Outcomes of interest include these patients' recurrence and survival rates as well as their health-related quality of life, when available.
Methods
Cases were accessed using the search terms ‘adenoid cystic’ and ‘cylindroma’ in the University of Iowa SNOMED database, which covers pathology specimens examined between August 1966 and August 2007. Charts were retrospectively reviewed and follow-up data were taken from the University of Iowa Cancer Registry. A subset were prospectively accrued and studied through the University of Iowa's health-related quality of life ‘Outcomes Assessment Project’. Patients were excluded if they had adenoid cystic carcinoma of the skin, lacrimal gland, or non-head and neck subsites.
The following parameters were analysed in all cases: demographics, extent of resection, histopathological assessment of margins, histological subtype, perineural invasion, primary treatment, recurrence, subsequent treatment and observed survival rates. Health-related quality of life was measured using the Head and Neck Cancer Inventory, a well validated instrument which measures eating, speech, aesthetics and social disruption.Reference Funk, Karnell, Christensen, Moran and Ricks2 Scores are reported on a scale of zero to 100, with lower scores representing worse functioning. Differences between scores can be compared with previously published small, intermediate, and large clinically important differences for each of these domains, in order to determine clinical significance.Reference Funk, Karnell, Smith and Christensen3
Tumour-node-metastasis (TNM) classification and stage were assigned based on the sixth edition of the American Joint Committee on Cancer (AJCC) staging manual. Retrospective re-staging was done by chart review, which included documentation of clinical examination findings, pathology reports, operative reports and imaging reports. For the purpose of analysis, T4A and T4B tumours were grouped together as T4.
The treatment philosophy during the study period was to offer surgery when the primary lesion was deemed resectable. Prior to approximately 1990, post-operative radiotherapy was used for involved margins or unresectable local disease. After 1990, radiotherapy was routinely offered after surgery. Radiotherapy alone was used if the primary was considered unresectable, or if the patient refused surgery or was considered medically unfit for surgery.
Patients undergoing radiotherapy received continuous course megavoltage photons using once-daily fractionation. Up until approximately 1999, patients were generally treated with a wedge pair technique or mixed photon-electron fields if ipsilateral neck nodes and primary site were treated. Opposed lateral fields were generally used for those with bilateral neck disease. After 1999, intensity modulation became routinely utilised for head and neck cancers, and target-based prescriptions were written. Known microscopically positive disease received 66 Gy in a post-operative setting, or 70 Gy if known gross residual disease was present. High risk areas received 60 Gy, while lower risk areas received doses limited to 50 Gy.
Treatment of the neck varied by primary physician and primary site. For example, tumours of the submandibular gland received concurrent neck dissection as well as treatment of lower nodes in radiation fields. Various chemotherapy agents were offered for symptomatic metastatic disease.
Analysis was performed to address the following questions. Was surgery alone or surgery plus post-operative radiotherapy associated with better local control, survival or health-related quality of life, compared with radiotherapy alone? Was surgery with or without radiotherapy for local recurrence associated with better local control or survival, compared with radiotherapy alone or no treatment? And finally, what impact did various distant metastases from adenoid cystic carcinoma have on survival, and how did chemotherapy affect survival and health-related quality of life?
Statistical analysis was performed using the Statistical Package for the Social Sciences version 14.0 software (SPSS Inc, Chicago, Illinois, USA). Significant associations were determined using a 2 × 2 Fisher's exact chi-square test. Actuarial survival analyses were used to calculate observed survival rates (with the end point being death from all causes), and Wilcoxon tests were used to identify significant differences in these observed survival rates.
Results
Of the 183 patients with previously untreated adenoid cystic carcinoma of the head and neck who were treated at the University of Iowa Hospitals and Clinics between January 1966 and June 2007, 114 (62.3 per cent) were female and 69 (37.7 per cent) male. Their mean age was 52.8 years (range nine to 93 years).
The mean duration of follow up was 9.0 years (range 0.5–40.8 years). Of the 183 patients, sufficient survival data was lacking for eight, recurrence status was unknown for three, and recurrence date was unknown for six cases with known recurrence.
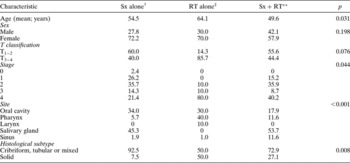
Patients receiving radiotherapy alone were more likely to have oropharyngeal or hypopharyngeal primaries and stage four disease (Table I). Patients receiving surgery alone had similar staging and subsites compared with those receiving surgery plus post-operative radiotherapy.
Characteristics of patients with adenoid cystic Ca of head and neck* receiving surgery alone, RT alone or surgery plus RT

Data are shown as percentages unless indicated otherwise.
* n = 159; †n = 54; ‡n = 10; **n = 95. Ca = carcinoma; Sx = surgery; RT = radiotherapy
Thirteen patients received intensity-modulated radiotherapy. The median dose was 62.0 Gy (range 15 to 72 Gy) for post-operative radiotherapy (n = 87) and 66.0 Gy (range 58 to 70 Gy) for radiotherapy used as a sole modality (n = 10).
Three patients included in the post-operative radiotherapy group received less than the typical minimum recommended dose of 50 Gy. One patient with a parotid tumour received a 15 Gy electron beam dose in five fractions; this patient had a local recurrence 11 years after initial treatment and was salvaged with surgery alone. Another patient with a parotid tumour received a single fraction, stereotactic, radiosurgery dose of 15 Gy and had no evidence of recurrence four years after completing treatment. A third patient, with a hard palate primary tumour, died of a myocardial infarction during the radiotherapy course, after receiving 40 Gy of a planned 66 Gy.
Survival
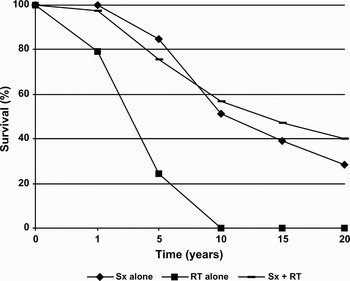
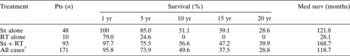
The observed survival for all patients was 73.9 per cent at five years and 49.6 per cent at 10 years (Figure 1 and Table II). Survival rates were worse following treatment with radiotherapy alone, compared with surgery alone (p = 0.002) and surgery plus post-operative radiotherapy (p = 0.001). Survival following treatment with surgery alone did not differ significantly from that following surgery plus post-operative radiotherapy (p = 0.795).
Survival by treatment type for patients with adenoid cystic carcinoma of the head and neck (n = 151). Sx = surgery; RT = radiotherapy

Survival of patients with adenoid cystic Ca of head and neck*, by treatment type

Survival rates for the three treatment groups differed significantly (p = 0.003). Survival for the radiotherapy (RT) alone group was significantly worse than that for surgery (Sx) alone (p = 0.002) and Sx + RT (p = 0.001) (pairwise comparisons). Survival for the two surgical groups (Sx alone vs Sx + RT) did not differ significantly (p = 0.795).
* n = 151. †Represents all cases with known survival status, including those with no treatment or unknown treatment. Ca = carcinoma; pts = patients; yr = year; med surv = median survival
Local control
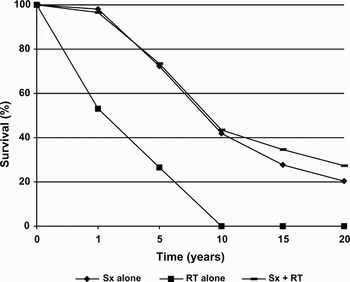
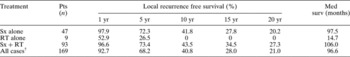
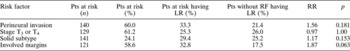
Local recurrence free survival for all cases was 68.2 per cent at five years and 40.8 per cent at 10 years (Figure 2 and Table III). When broken down by treatment type, local recurrence free survival rates were significantly lower for radiotherapy alone compared with surgery alone (p = 0.004) and surgery plus post-operative radiotherapy (p = 0.001). Local recurrence free survival rates did not differ significantly following treatment with surgery alone, compared with surgery plus post-operative radiotherapy (p = 0.900). No risk factor significantly predicted local recurrence and, importantly, no risk factor was sensitive in predicting local recurrence (Table IV).
Local recurrence free survival by treatment type, for patients with adenoid cystic carcinoma of the head and neck (n = 169). Sx = surgery; RT = radiotherapy

Local recurrence free survival of patients with adenoid cystic Ca of head and neck*, by treatment type

Survival rates for the three treatment groups differed significantly (p = 0.004). Survival for the radiotherapy (RT) alone group were significantly worse than that for the surgery (Sx) alone (p = 0.004) and Sx + RT (p = 0.001) groups (pairwise comparisons). Survival for the two surgical groups (Sx alone vs Sx + RT) did not differ significantly (p = 0.900).
* n = 169. †Represents all cases with known recurrence status, including those with no treatment or unknown treatment. Ca = carcinoma; pts = patients; yr = year; med surv = median survival
Incidence and relative risk of risk factors for local recurrence, in patients with adenoid cystic Ca of head and neck

Ca = carcinoma; RF = risk factor; pts = patients; LR = local recurrence; RR = relative risk
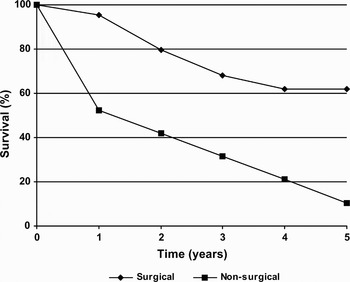
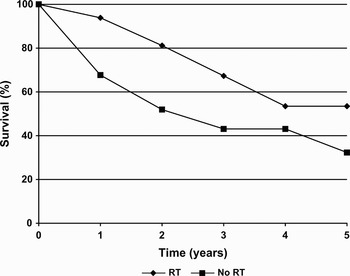
Patients who had local recurrences and who received salvage surgical treatment lived significantly longer than those who did not receive salvage surgical treatment (p = 0.006) (Figure 3 and Table V). There was a non-significant trend favouring survival for those patients having a local recurrence and subsequently receiving radiotherapy, compared with those not receiving radiotherapy for local recurrence (p = 0.139) (Figure 4 and Table VI).
Survival by type of treatment for recurrence (surgical vs non-surgical or none), for patients with adenoid cystic carcinoma of the head and neck developing local recurrence (n = 34).

Survival by type of treatment for recurrence (radiotherapy (RT) with or without surgery vs no RT or no treatment), for patients with adenoid cystic carcinoma of the head and neck developing local recurrence (n = 34).

Survival of patients with adenoid cystic Ca of head and neck developing local recurrence*, by type of treatment for recurrence

Survival was significantly better in the surgical (Sx) group compared with the group receiving non-Sx or no treatment (p = 0.006).
* n = 34. Ca = carcinoma; pts = patients; yr = year; med surv = median survival
Survival of patients with adenoid cystic Ca of head and neck developing local recurrence*, by type of treatment for recurrence

Survival did not differ significantly, comparing the radiotherapy (RT) group and the group receiving no RT or no treatment (p=0.139).
* n = 34. Ca = carcinoma; pts = patients; yr = year; med surv = median survival
Neck control
Of the 183 patients, 146 had known nodal status at presentation and 127 had known nodal status at last follow up. Six of the 127 patients (4.7 per cent) who were N0 at presentation subsequently developed a regional recurrence, at a mean interval of 75.7 months (range eight to 193 months) after diagnosis. Twelve of the 146 patients (8.2 per cent) with known nodal status at diagnosis had involved cervical lymph nodes at presentation. Of those patients with involved lymph nodes at presentation, three (25.0 per cent) later had recurrence in cervical lymph nodes despite radiotherapy (two patients) or surgery plus radiotherapy (one patient).
Distant metastases
Of the 183 patients, 58 (31.7 per cent) were identified as having distant metastases at last follow up (21 patients) or death (37 patients). The mean interval between diagnosis and death for the 37 patients who died was 34.8 months (range zero to 272 months).
The number of patients who died with known distant metastatic disease, and their mean survival duration, were as follows (in order of site of metastasis): lung, 30 patients, 30.7 months (range zero to 123 months); bone, eight patients, 57.2 months (range five to 272 months); brain, four patients, 9.2 months (range zero to 24 months); and liver, two patients, 13 months (range eight to 18 months). Note that patients may have metastases to more than one distant site.
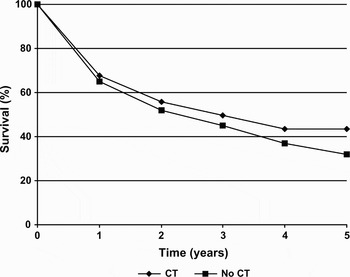
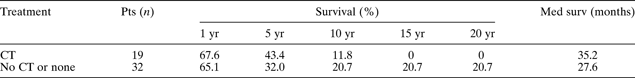
Chemotherapy was used as the sole agent in the management of the majority of patients with symptomatic distant metastases. The chemotherapeutic agents used were varied: adriamycin, cisplatin, carboplatin, 5-fluorouracil, methotrexate, bacille Calmette-Guerin (BCG), Taxol®, docetaxel, Gleevec®, vincristine and lapatinib (this latter in a trial). The survival rates for patients with distant metastases were similar, comparing those receiving and not receiving chemotherapy (p = 0.747) (Figure 5 and Table VII).
Survival by type of treatment for recurrence (chemotherapy (CT) vs no CT), for patients with adenoid cystic carcinoma of the head and neck developing distant recurrence (n = 51).

Survival of patients with adenoid cystic Ca of head and neck developing distant recurrence*, by type of treatment for recurrence
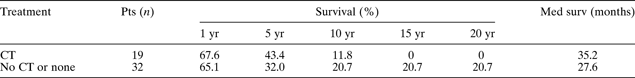
Survival did not differ significantly, comparing the chemotherapy (CT) group and the group receiving no CT or no treatment (p = 0.747).
* n = 51. Ca = carcinoma; pts = patients; yr = year; med surv = median survival
Health-related quality of life
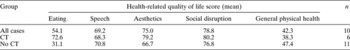
Twenty-eight of the 183 patients in our study cohort provided health-related quality of life information as part of a separate, longitudinal outcomes project. Of these 28, 13 developed distant metastases, although only 10 provided self-reported outcomes data after this recurrence. Of these 10 patients, six received chemotherapy and had higher eating scores than the remaining four who did not receive chemotherapy, with the magnitude of the difference being large and clinically significant. These same six patients also had higher aesthetic scores, compared with the same four patients, with the difference being of intermediate magnitude. A large detrimental effect was observed in respondents' general physical health following chemotherapy distant recurrence (Table VIII). Respondents suffering recurrence and receiving chemotherapy showed a trend toward slower deterioration in aesthetic and eating scores (although no improvement) and toward faster decline in general physical health, compared with respondents with recurrence who did not receive chemotherapy (however, these latter also declined over time due to distant metastatic disease).
Health-related quality of life scores after recurrence, for patients with adenoid cystic Ca of head and neck developing distant recurrence*

* n = 10. Ca = carcinoma; CT = chemotherapy
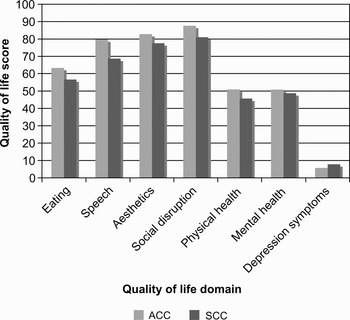
Patients with adenoid cystic carcinoma who provided health-related quality of life scores one year after diagnosis (n = 20) demonstrated significantly better mean health-related quality of life scores for eating, speech, aesthetics, social disruption and overall physical health, compared with patients with squamous cell carcinoma (n = 605) (Figure 6).
Comparison of health-related quality of life scores for patients with adenoid cystic carcinoma (ACC; n = 20) and with squamous cell carcinoma (SCC; n = 605), 12 months after diagnosis.

Discussion
Adenoid cystic carcinoma is characterised by a high rate of late local failure and distant metastases. In this series of 183 patients, the overall five- and 10-year local recurrence free survival rates were 68.2 and 40.8 per cent, respectively. These rates are similar to the findings of Conley and Casler, who reviewed 406 patients of the head and neck with adenoid cystic carcinoma and found only 30 per cent to be free of disease at 10 years, 36 per cent having died of their disease.Reference Conley and Casler4 The observed survival in this series was 73.9 per cent at five years, 49.6 per cent at 10 years, 37.5 per cent at 15 years and 28.8 per cent at 20 years. These rates demonstrate that long-term follow up is required when estimating local control and survival rates.
Based on the current, limited evidence, most authors advocate surgery and routine post-operative radiotherapy for adenoid cystic carcinoma of the head and neck. In the present study, radiotherapy alone was associated with significantly worse local control (p = 0.004) and survival (p = 0.003), compared with surgery and surgery plus post-operative radiotherapy. There was no observed improvement in local control with post-operative radiotherapy, compared with surgery alone; however, a selection bias was evident.
Patients with parotid and submandibular gland primaries, representing 45 per cent of the subjects in this series, have been shown to do well with surgery and post-operative radiotherapy. Gurney et al. reviewed 33 patients with major salivary gland adenoid cystic carcinoma and showed local control rates at five and 10 years to be 94 and 73 per cent, respectively.Reference Gurney, Eisele, Weinberg, Shin and Lee5 Other subsites represented over 50 per cent in this series; these tended to be less amenable to complete surgical resection without significant morbidity, and had a substantial local failure rate. Prokopakis et al. showed a 59 per cent local recurrence rate after a mean follow up of 52 months (minimum 24 months) for all subsites, using surgery and post-operative radiotherapy in 83 per cent of their cases.Reference Prokopakis, Snyderman, Hanna, Carrau, Johnson and D'Amico6
Mendenhall et al. supported the use of surgery with or without post-operative radiotherapy where possible; in their study of 101 cases of adenoid cystic carcinoma, local control following radiation alone was inferior to that following surgery plus post-operative radiation.Reference Mendenhall, Morris, Amdur, Werning, Hinderman and Villaret7 These authors' five- and 10-year local control rates were respectively 56 and 43 per cent for radiation alone, compared with 94 and 91 per cent for surgery plus radiotherapy. However, Mendenhall and colleagues' local control rates for surgery plus post-operative radiotherapy were substantially higher than those of most published series. Mendenhall et al. observed a non-significant trend towards improved survival following surgery plus post-operative radiotherapy, compared with radiotherapy alone. Our study, with almost twice as many patients, did find that surgery and surgery plus post-operative radiotherapy were associated with better survival, compared with radiotherapy alone (p = 0.003). However, selection bias is an inherent problem in each of these institutional experiences.
The current series showed no clear benefit, in terms of local control (p = 0.90) or survival (p = 0.795), from the addition of post-operative radiotherapy, compared with surgery alone. Although the surgery alone and surgery plus post-operative radiotherapy groups appeared similar with respect to stage and primary site, radiotherapy was selectively used in patients with a worse prognosis (i.e. positive margins after resection or advanced T stage at presentation). Surgery plus post-operative radiotherapy seems to be associated with local control and survival rates comparable to those of patients with more favourable tumours treated with surgery alone. Patients receiving surgery plus post-operative radiotherapy showed a non-significant trend towards improved local control and survival beyond 10 years, compared with patients receiving surgery alone. The lack of significance may reflect the smaller numbers in the subgroups, or the wide variability in time to local recurrence or death which characterises adenoid cystic carcinoma.
The decision whether to use selective post-operative radiotherapy, as in squamous cell carcinoma, is made particularly difficult by the inability to predict which patients will experience a recurrence. Prokopakis et al. showed that the most important predictive factors for recurrence were site (which limits both radiation fields and surgical extent) and pathological negative margins.Reference Prokopakis, Snyderman, Hanna, Carrau, Johnson and D'Amico6 Although no single factor was significant in predicting local recurrence in the current series, margin status showed some association (p = 0.063). Given that even early stage tumours with clear resection margins frequently develop local recurrence, and that many patients have a long life expectancy, routine radiotherapy should be offered.
Conley and Casler describe adenoid cystic carcinoma as ‘radiosensitive but not radiocurable’.Reference Conley and Casler4 Hosokawa et al. showed the utility of radiation alone for local palliation; however, as in the current series, most patients eventually developed local recurrence.Reference Hosokawa, Ohmori, Kaneko, Yamasaki, Ahmed and Arimoto8 Given the long survival times (on average nearly three years), even with distant metastases, and the wide variation in survival with distant metastases (one patient survived 20 years), radiotherapy alone remains an important modality for patients with unresectable tumours. Van der Wal et al. showed the mean survival time from detection of metastases to be 32.3 months for lung lesions and 20.6 months for other sites.Reference Van der Wal, Becking, Snow and van der Waal9 However, Sung et al. found an even longer survival (a mean of 54 months) when isolated lung lesions were detected.Reference Sung, Kim, Kim, Min, Seong and Roh10
• Adenoid cystic carcinoma represents 3 per cent of head and neck neoplasms and has a propensity to late local and distant recurrence
• In this series, surgery plus post-operative radiotherapy did not improve local control compared with surgery alone, but a selection bias was evident. Radiotherapy alone did have a role in unresectable tumours, although surgical debulking appeared to assist with palliation
• The use of surgery to treat resectable local recurrence was associated with improved survival
• The chemotherapy regimens used did not improve survival in patients with distant disease, but provided a small benefit in eating and aesthetic quality of life, albeit at the expense of overall physical health
Adenoid cystic carcinomas tend to show perineural invasion and slow, infiltrative growth. Consequently, even recurrent disease often produces few functional problems, as evidenced by the superior 12-month health-related quality of life scores for patients with adenoid cystic carcinoma compared with squamous cell carcinoma. Extrapolating from this, debulking surgery plus post-operative radiotherapy may provide superior palliation compared with radiotherapy alone. Gormley et al. reported that six of 16 patients with gross intracranial extension of tumour had no evidence of disease 72 months after receiving debulking surgery and post-operative radiotherapy.Reference Gormley, Sekhar, Wright, Olding, Janecka and Synderman11 Pommier et al. reviewed 23 patients with sinonasal tumours, 53 per cent of whom underwent significant surgical debulking followed by radiation, while the remainder were treated with proton and photon radiotherapy alone; local control at five years was 93 per cent.Reference Pommier, Liebsch, Deshcler, Lin, McIntyre and Barber12
In the current series, treatment of local recurrence was associated with significantly increased survival, compared with no treatment (p = 0.004). However, patients not receiving treatment would be expected to have worse outcomes due to unresectable disease or poor premorbid condition. Again, surgery seems to be an effective treatment, even for local recurrence (p = 0.006), although radiotherapy did show a non-significant trend toward better outcomes (p = 0.139). This finding may support the theory of radioresistance of adenoid cystic carcinoma, and the trend towards using surgery in more favourable cases.
Chemotherapy for symptomatic distant metastases is not associated with improved survival.Reference Kaplan, Johns and Cantrell13 Patients offered chemotherapy are more likely to be higher functioning, with a better expected survival. Consequently, the lack of survival improvement suggests that contemporary chemotherapy regimens offer little if any survival benefit. However, patients receiving chemotherapy did report better eating and aesthetic scores and worse physical health scores, compared with patients not receiving chemotherapy. Interpretation of this analysis is difficult, however, due to the wide range of chemotherapeutic agents used.
Conclusion
Patients with adenoid cystic carcinoma have a propensity to develop local and distant recurrence, even when presenting with early stage disease, and even as much as 20 years after diagnosis. In the current series, surgery with or without radiotherapy was associated with improved local control and survival, compared with radiotherapy alone. Surgery plus post-operative radiotherapy did not improve local control compared with surgery alone; however, a selection bias was evident. Radiotherapy alone did have a role in the treatment of unresectable tumours, although surgical debulking appeared to assist with palliation. Determining the selective use of post-operative radiotherapy is made difficult by the lack of factors identified as predicting local recurrence. Surgery used to treat resectable local recurrence was associated with improved survival. The chemotherapy regimens used did not improve survival in patients with distant disease, but did provide a small benefit in eating and aesthetic quality of life, albeit at the expense of overall physical health.