INTRODUCTION
Nearly 56 million people die worldwide each year (World Health Organization, 2015). Many more are bereaved, as four people on average grieve each death (Parliamentary Committee on Palliative and Compassionate Care, 2011). Although most bereaved people recover over time, from 2 to 20% experience extremely severe and often prolonged or even permanent grief (Holland et al., Reference Holland, Currier and Gallagher-Thompson2009; He et al., Reference He, Tang and Yu2014; Middleton et al., Reference Middleton, Burnett and Raphael1996; Zhang et al., Reference Zhang, El-Jawahri and Prigerson2006). Bereavement grief is therefore not only a common experience but often a highly impactful one. In some cases, grief leads to physical and/or psychological illnesses and early death, with antidepressants, antipsychotics, hypnotics, and sedatives often ordered to try and help people recover from or live with their grief (Shah et al., Reference Shah, Carey and Harris2013). Other more common ways of helping people who experience grief range from the informal support provided by friends and family members to structured bereavement services.
A recent bereavement services mapping exercise for a Canadian province revealed a growing number and increasing variety of structured bereavement services, with most of these services designed and provided by freestanding hospices, private organizations, and well-meaning individuals (Wilson & Playfair, Reference Wilson and Playfair2016). This mapping exercise also revealed much organizational interest in the provision of effective bereavement services, with service or program evaluations routinely conducted by most organizational and individual providers for quality assurance or improvement purposes. Clearly, there are many different types of bereavement services available, but there is little information or evidence to reveal which services or service is more effective than the others (Roberts & McGilloway, Reference Roberts and McGilloway2011; Schut & Stroebe, Reference Schut and Stroebe2011). Given the potential for some people to have complicated grief, a chronic debilitating condition that needs to be diagnosed and treated (Shear et al., Reference Shear, Simon and Wall2011), and for some to suffer from illnesses and premature death, effective bereavement services are essential. It is also important to ensure that no harm or harmful side effects exist in relation to bereavement services for recipients and providers (Schut & Stroebe, Reference Schut and Stroebe2011).
The objectives of this scoping research literature review were to locate and assess researched bereavement service outcomes to determine the state of bereavement services evaluation, to catalogue bereavement service types, and to identify which bereavement service or services, if any, demonstrate clear evidence of effectiveness. This review was undertaken to enhance evidence-based practice (Zhang et al., Reference Zhang, El-Jawahri and Prigerson2006), a compelling requirement for bereavement services. The following is a report of our project and its findings, with evidence and evidence gaps highlighted.
METHODS
As indicated, a scoping literature review was done in the interest of conducting a comprehensive exploration to create knowledge associated with bereavement services and their outcomes (Whittemore & Knafl, Reference Whittemore and Knafl2005). Scoping reviews are designed to collect and organize information, and to ultimately develop an understanding of the existing evidence base (Armstrong et al., Reference Armstrong, Hall and Doyle2011). Arksey and O'Malley (Reference Arksey and O'Malley2005) indicate that scoping reviews “map” the existing literature in a field of interest. Moreover, they highlight two main differences between systematic literature reviews and scoping reviews: (1) systematic reviews focus on well-defined questions as compared to scoping reviews, which focus on broad topics; and (2) systematic reviews aim to provide answers to specific questions through the use of a narrow range of quality-confirmed studies, as compared to scoping reviews, where a much broader literature base is assessed (Arksey & O'Malley, Reference Arksey and O'Malley2005). To this end, a university librarian was consulted to determine which library databases and MESH and/or keywords would identify published qualitative, quantitative, and mixed-methods research reports that focus on bereavement service outcomes. The goal was to find and assess all published English-language research reports in peer-reviewed journals over the past decade (2005–2015) to identify which types of structured or formal bereavement services and service outcomes have been studied, and to determine if any specific type or types show clear and convincing evidence of effectiveness. Our review also gathered baseline information on each bereavement service: (1) when or at which point a service was to be initiated during the grief process; (2) the duration of the service; and (3) who was intended to receive this service. The evaluation methods were also identified, as these methods could impact the findings.
As outlined in the Appendix, Embase, PubMed, and Medline (via Ovid) were identified as the most critically important library databases in which to search for relevant published research reports, as these are widely utilized by healthcare and social-service professionals. The search terms were “bereave* OR grief,” “program*” combined with “service*,” and “evaluation OR assessment.” The inclusion criteria were English language, had an abstract, published in a peer-reviewed journal during the previous decade, was a research study with information provided on the methods used to gather and analyze data, and focused in whole or in part on the outcomes or impact for bereaved persons using one or more formal bereavement services. CINAHL was similarly searched after a second librarian was consulted. The search criteria excluded all non-research reports, and those research reports focused on the development of bereavement services, the impact of bereavement support from family and friends, and the impact of services designed to reduce bereavement reactions among healthcare workers. Other reviews were also excluded. Only one was found, which focused on hospital-based bereavement services following the death of a child (Donovan et al., Reference Donovan, Wakefield and Russell2015). The reference list in that paper and those in all the selected papers were read to identify additional potential articles for review.
All potentially relevant articles for review were first assessed by way of a title and abstract review for relevance, which greatly reduced the number. Following this, a reading of all retained full articles was done, with this again reducing the number considerably to 38 papers that met our inclusion criteria. After these publications were read and reread, and the findings discussed by the research team, it was decided that none would be eliminated—despite various concerns over the research methodological quality of many articles. Often, a lack of detail about study design and/or findings was present. As such, all research articles published during the previous decade in peer-reviewed journals referenced in key library databases on the topic of bereavement service outcomes were assessed.
RESULTS
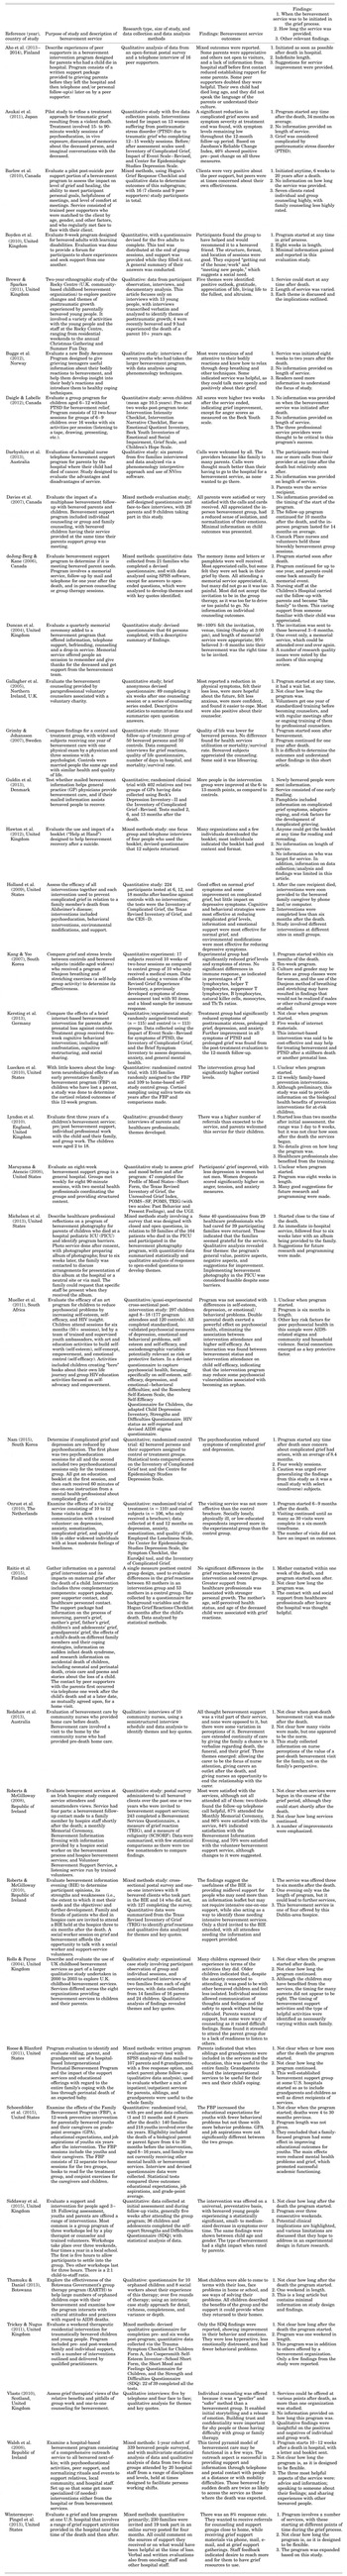
Table 1 contains information on each of the 38 articles; including: (1) author(s), year published, and country where the study was conducted; (2) purpose of the study and a description of the bereavement service; (3) type of study (i.e., mixed methods, qualitative, or quantitative), size of the study, what data were collected and how, and data analysis methods; (4) service outcome findings; and (5) information on other potentially relevant factors, such as when or at which point in the grief process the bereavement service was initiated, who was to receive the service, and the duration of the service.
Literature review findings

The collective findings from this review are outlined below. Chief among these is the finding that a wide variety of bereavement service outcomes were of interest to the researchers, with most studies seeking evaluative information on more than one outcome. Nearly half (n = 16) of the studies, however, were unclear about the outcome or outcomes of interest, including most qualitative studies, as they typically sought (as is expected of qualitative research) to gain an understanding of what participants had received from the bereavement service. For those articles with a defined outcome—10 studies focused on the bereaved person's level of grief, 6 on their stress or distress level, 6 on their grief/bereavement knowledge or educational level, 6 on their level of depression, and 5 on somatization or physical symptoms—many other outcomes were also researched.
Most studies focused on short-term or immediate outcomes, as determined through measurements taken soon after the bereavement service had ended. Some studies included pre- and post-intervention testing, with three conducted as late as 6 or 10 years following the death or conclusion of the bereavement service. A wide range of compassionate and practical services was evaluated, although three basic types were apparent to the literature review team: (1) crisis intervention services to provide immediate assistance to help people through the initial phase of grief; (2) ongoing services provided during a grief process, with these designed to speed or increase recovery; and (3) services designed to identify people who need professional treatment and/or long-term support to prevent or address complicated grief.
Outcomes data were gathered through the use of many different tools. Among these, a self-designed questionnaire or survey was the most common (n = 18), followed by interviews (n = 15), the Inventory of Complicated Grief (n = 6), the Center for Epidemiology Depression Scale (n = 3), the Impact of Event Scale (n = 2), the Texas Revised Inventory of Grief (n = 2), and other single-use measures. The majority of studies were quantitative (n = 18), followed by qualitative (n = 11), and mixed methods (n = 9). More studies were conducted in the United Kingdom (i.e., England, Northern Ireland, Scotland, and Wales; n = 10) than in the United States (n = 7), Canada (n = 4), the Republic of Ireland (n = 3), Australia (n = 2), Finland (n = 2), South Korea (n = 2), and eight other countries with one study for each.
The services provided by healthcare or social-service professionals were most often evaluated (n = 27), as compared to those provided by peer volunteers (n = 5) or by professionals and volunteers working together or in conjunction (n = 5). One article did not specify if the evaluated service was provided by paid professionals or peer volunteers. The bereavement services also varied considerably, as did the target population for these services. Most commonly, a group of services was evaluated (n = 17), followed by group therapy (n = 6), individual counseling (n = 5), written information (n = 2), and other less common services such as phototherapy. Most often, the services offered and evaluated were available to any bereaved person (n = 12), although many were oriented to specific types of people, including parents who had lost a child (n = 8), children who had lost a parent or sibling (n = 11), widows or widowers (n = 4), and others such as grandparents or adults with learning disabilities.
DISCUSSION
With 38 bereavement service evaluation studies conducted during the previous decade in many different countries, worldwide interest in providing effective bereavement services is evident. The services examined varied considerably in terms of type, duration, target audience, and many other factors. This diversity reflects the widely varying reasons for grief (i.e., deaths of younger vs. older persons, sudden vs. expected deaths, quick vs. lingering deaths, etc.) and the wide range of bereaved people who may benefit from help (i.e., young and old, previous grief experiences or not, limited or strong social support systems, rural or urban living, can access the internet or not, etc.). However, the assessed services typically provided emotional support to the individual and family or educational information in print or verbal forms to enhance knowledge about grief.
The outcome or outcomes investigated also varied widely, although half of the studies did not research a priori outcomes. Despite this, all but one research study (a visiting service for widows/widowers that was evaluated by Onrust et al. [2010]) indicated that the studied service or services had value. Some evidence was subjective, however, such as whether the service recipient had liked the service or had felt it was beneficial. However, such subjective viewpoints can comprise a valid and critically important outcome when assessed through rigorous qualitative or quantitative research methods. Other evidence was oriented to one specific outcome or a few specific outcomes—most often grief level and stress level. With such diversity in services examined, and with little confirming evidence of effectiveness for any specific service or group of services, it cannot be said that any type demonstrated clear or irrefutable evidence of effectiveness. Until future high-quality research studies have repeatedly revealed evidence of service effectiveness, it is possible to consider that the positive outcomes of bereavement services may be essentially related to bereaved people receiving helpful educational information and emotional support from organizations and other people who are prepared to help. These two primary purposes require research to validate their relevance. For instance, it is possible that educational information is helpful for only some people, and it is also possible that educational information is not really helpful at all with respect to reducing grief. Research is also needed to determine if there are other primary purposes for bereavement services.
Future studies are also indicated to validate the effectiveness of existing bereavement services—research that will hopefully avoid additional research issues. Many evaluation studies were conducted by the people who provided the bereavement service(s). Objectivity may have suffered as a result, and with the added concern that most studies appeared to be done by people with no expertise in evaluation research. The need for sound evaluations was identified by Rolls and Penny (Reference Rolls and Penny2011), who conducted a mapping exercise of U.K. childhood bereavement services evaluation and found the following:
Child bereavement services were struggling with a considerable burden of demand for [evaluation] information from a range of users. … The most common forms of evaluation were post-intervention user satisfaction surveys of core interventions, using self-completion questionnaires. However, collection of basic data was limited and patchy, and evaluations of outcomes and organizational processes and reporting on the findings were less common. (p. 43)
Future evaluations should involve researchers with expertise in evaluation research, preferably through research/practice partnerships, as these are optimal since they retain the service knowledge and insights of service providers. Another advantage is that evaluation researchers are likely to have external research funding—funding that would reduce the current demands on bereavement organizations to provide human and other resources for service evaluations.
In keeping with Rolls and Penny's (Reference Rolls and Penny2011) report, we also found that self-designed questionnaires were most commonly used in the 38 reviewed studies to elicit evaluative information from service users. It is understandable that self-designed questionnaires are purposed to gather information, as they can be quickly developed, are easy to use, and can be tailored to the specific service and the interests of the evaluator(s). Established measurement tools are encouraged in future studies, as many well-developed tools are now available. These tools were already in use at the time of some of the reviewed studies, although some of these tools only focus on one distinct outcome—such as grief, depression, or stress. Future evaluations should include multiple tools or tools with a broader focus, as bereavement grief can impact physical, mental, and psychosocial health.
Another issue is that many of the evaluations focused on the immediate impact of a service, with only a few focused on outcomes measured as late as 1 to 10 years following the death or the end of the bereavement service. Multiyear follow-up in longitudinal or time-series studies is indicated, as the impact of grief can be lifelong (Zhang et al., Reference Zhang, El-Jawahri and Prigerson2006). These suggestions address the concern of Schut and Stroebe (Reference Schut and Stroebe2011) that “without sound evaluation, not only is it not known whether the [bereavement] intervention is effective, but also whether it has harmful side effects” (p. 6). However, it must be emphasized that none of the reviewed studies found or reported harmful side effects for recipients or providers.
Another concern is finding such diverse bereavement services. As indicated, the articles revealed a wide range of compassionate and practical services, but with three different types apparent. Some services were oriented toward crisis intervention, as they provide immediate assistance to help people through the initial phase of grief, and these services are often provided at the time of death or shortly thereafter by attending nurses or other direct-care providers, bereavement or palliative care specialists, and psychologists or social workers working in hospitals or nursing homes. Other services are provided later on during the grieving process, with these designed to hasten or increase recovery. These services and their providers vary considerably. The third service type was designed to identify people who need professional treatment and/or long-term support to prevent or address complicated grief. These identification services are often a component of the two other types, as crisis intervention and follow-up service providers would have an obligation to identify any people in danger of harming themselves or at risk of complicated grief. All three types of services are important, and future evaluations will hopefully focus on each specific type. Comparisons of existing services for each type would be highly beneficial for determining if one service is more effective than the others.
IMPLICATIONS AND RECOMMENDATIONS
Despite much interest among the providers of bereavement services to ensure helpful and appropriate services, this literature review did not identify any one bereavement service as being more efficacious than any of the others. The state of science in relation to bereavement service evaluation was determined to be in the beginning stages, but with development and refinement indicated as being on the way.
Given these two conclusions, we will provide suggestions to direct future research, bereavement service development, and health/social policy. One recommendation is in keeping with Rolls and Penny's (Reference Rolls and Penny2011) advice to have a set of common evaluation tools that could be used by bereavement researchers. Given the broad-based impact of grief, there is a need to develop and validate comprehensive bereavement service evaluation tools. It is therefore necessary to determine which service outcomes are of primary concern. There are many possible outcomes—the ones of interest to the researchers who undertook the reviewed evaluation studies and additional ones that may not yet have been identified as important by bereaved persons or bereavement service providers. To this end, it is recommended that researchers who are versed in evaluation research work with bereavement service providers and bereaved persons to advance the measurement of bereavement service outcomes. This work will help validate or refine bereavement services and will likely also demonstrate where service expansion is indicated, with the ultimate aim of effectively helping more bereaved persons who are suffering as a result of the death of a loved one.
ACKNOWLEDGMENTS
The first author appreciates the student volunteers and other coauthors for their careful and diligent work. All the authors would like to thank the researchers who conducted the reviewed studies and all the bereavement service planners and providers for their efforts in helping those among us who are bereaved.
APPENDIX
Search Strategy and Findings
Embase, PubMed, and Medline:
-
■ bereave* OR grief = 13,186 articles
-
■ program* OR service* = 2,340 articles
-
■ evaluation OR assessment OR effective* = 584 articles
Titles and abstracts screened after limits applied = 136 articles
Articles appearing to meet criteria for review = 20 articles
CINAHL:
-
■ bereave* OR grief = 11,833 articles
-
■ program* OR service* = 6,928 articles
-
■ evaluation OR assessment OR effective* = 301 articles
Titles and abstracts screened after limits applied = 165 articles
Articles appearing to meet criteria for review = 55 articles
After removing duplicates, and finding two additional articles through searching the reference lists of the selected articles, a total of 38 articles met all inclusion criteria and were reviewed.