The Spanish National Health Service (SNHS) is a decentralized public health insurance system with universal coverage which provides free health care to every resident in all the seventeen Spanish regions or autonomous communities. The SNHS is managed at a regional level, and fully financed by national insurance contributions and taxes, although some regional governments add local taxes to provide additional funding. Like many other countries, Spain has implemented several mechanisms to promote the introduction and diffusion of health technologies of proven value and alter those which do not provide additional benefits and/or are non–cost-effective. Health technology assessment (HTA) has been one of these mechanisms since 1984, when a National Advisory Board on High Technology was created. Later, since the early 1990s, and which can be explained by the decentralized character of the SNHS, some regional HTA units were developed in Catalonia and the Basque Country, followed by an HTA agency at National Level and in some other regions such as Andalucía, Canary Islands, Galicia, Madrid, and Aragón. This process led to a status of maturity of HTA in Spain, which, nevertheless, faced a series of challenges: improving coordination at national level; improving implementation of recommendations among decision makers at regional levels; and to have an adequate and stable funding (Reference Sampietro-Colom, Asua, Briones and Gol1). The objectives of this study are to report and update the normative and organizational state of HTA in Spain; describing noteworthy advances witnessed during the past 10 years; reflecting on the drivers, as well as discussing existing challenges.
Background: Timeline/Chronology, Members, and Initial Objectives
The Spanish Network for Health Technology Assessment and Services of the National Health System (Red Española de Agencias de Evaluación de Tecnologías Sanitarias y Prestaciones del Sistema Nacional de Salud [RedETS]) was officially created in February 2012 to respond to the impact of the recent “great recession” in Spain (2008–16) linked to the world-wide financial crisis in 2007 (2). However, earlier, the Quality Plan of the Spanish National Health System, prepared by the Ministry of Health (MoH) in 2006, had already included the commitment of developing a specific strategy on HTA to support decision making across the National Health System (NHS) both at state and regional levels (3). This earlier national strategy brought together all public HTA organizations working at national and regional levels as an informal (not officially created) HTA network with a clear focus on nondrug health technologies assessment.
The Spanish Agency of Medicines and Sanitary Products (AEMPS) is the administrative body responsible for assessing pharmacological technologies. From 2006 until now, the state level activity of the Spanish HTA Network has been funded by the MoH, extending the available financial support provided for every HTA agency by their corresponding Regional Governments to support local HTA needs. The overall funding provided for RedETS by the MoH is annually approved and distributed among the participant agencies by the Interterritorial Council of the National Health System, according to existing criteria based on workload considerations. From 2006 to 2012, all technical and logistic issues in HTA collaboration at national level were coordinated by the Agencia de Evaluación de Tecnologías Sanitarias del Instituto de Salud Carlos III (AETS-isciii) by means of collaboration agreements with the following HTA public organizations from autonomous communities: Agència de Qualitat i Avaluació Sanitàries de Catalunya (AQuAS); Servicio de Evaluación de Tecnologías Sanitarias del País Vasco (Osteba); Agencia Andaluza de Evaluación de Tecnologías Sanitarias (AETSA); Servicio de Evaluación del Servicio Canario de la Salud (SESCS); la Unidade de Asesoramento Científico-técnico avalia-t; la Unidad de Evaluación de Tecnologías Sanitarias de la Comunidad de Madrid (UETS); y el Instituto Aragonés de Ciencias de la Salud (IACS).
During this initial period, the progressive development of the Spanish HTA network targeted, as main objectives, the setting-up and sharing of common procedures, methodological guidelines and instruments as basic requirements for effective cooperation and mutual recognition of the scientific and technical production in HTA. At the same time, several other horizontal actions were funded by the MoH to extend and improve the evaluative culture into the Spanish NHS, including competitive calls to fund evaluative research on HTA; specific teaching/training activities related to HTA and evidence based clinical/managerial decision making; and the creation of the Spanish Program Guia-Salud to develop and update Clinical Practice Guidelines (www.guiasalud.es). Over this first stage of development, the Spanish HTA network prepared many annual HTA reports, methodological guidance on HTA and Clinical Practice Guidelines (CPG).
All this production was published both in print and electronically and extensively disseminated among the Spanish Regional Health Authorities (17 autonomous communities and 2 autonomous cities) and their corresponding networks of hospitals and primary care centers to inform decision making at macro, meso and micro levels. This period coincided with the birth and initial development of the European Network for Health Technology Assessment (EUnetHTA), where the participation of the Spanish HTA agencies allowed a progressive conceptual, methodological and instrumental convergence, in addition to reducing duplication of work at European level.
Official Creation of RedETS and Structure
After the official foundation of RedETS in 2012 (4), its activity has been much more focused on informing about the revision of the Benefit Portfolio of the Spanish NHS, including either decisions on funding/approval of new cost-effective nonpharmacological health technologies (NPHT) or the exclusion (disinvestment) of obsolete and/or non–cost-effective but previously included NPHT. RedETS also inform on decisions on potential changes of indications or usage conditions of NPTH.
RedETS is formed by AETS-isciii, AQUAS, OSTEBA, AETSA, SESCS, Avalía-t, UETS, and IACS; and its main structural figures for internal coordination are the Plenary Board and its Permanent Commission, the Presidency, and the Technical Secretariat.
The Plenary Board is formed by the heads of all HTA agencies in Spain and the Directorate-General for Public Health, Quality and Innovation, and the Directorate-General for the NHS Portfolio of Services and Pharmacy in the MoH. The Sub-directorate-General for NHS Portfolio of Services and Compensation Funds in the MoH assumes the role of the Technical Secretariat.
The Permanent Commission is formed by the Presidency and the Vice Presidency of REDETS and the Directorate-General for the NHS Portfolio of Services and Pharmacy. This Permanent Commission supervises the adherence to the agreements and plans adopted by the Plenary Board; and proposes the creation of specific working groups; in addition to adopting urgent decisions that cannot be submitted to the Plenary Board in time.
The Presidency is rotated annually among the heads of the HTA agencies in RedETS. The main responsibilities of the RedETS Presidency are accepting RedETS representation; convening the board meetings (Plenary or Permanent Commission) and setting their corresponding agenda. The Technical Secretariat is responsible for coordinating the development of the Annual HTA Plan for its later consideration and approval by the Interterritorial Council of the National Health System; setting the functioning regulation for the Plenary Board of RedETS; managing the RedETS website (www.redets.mscbs.gob.es), and the dissemination of all RedETS outputs.
RedETS Production for Different Stakeholders in the NHS
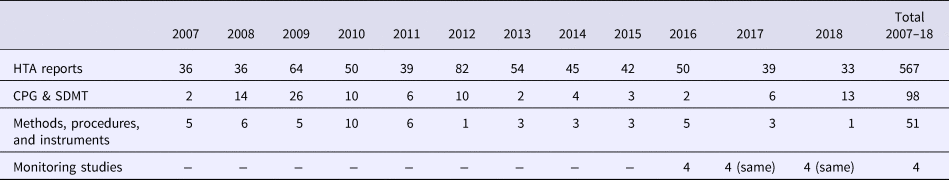
As Table 1 shows, the outputs delivered by RedETS have increasingly diversified from the initial production of HTA reports and CPG, to the subsequent preparation of methodological guidance reports, relative effectiveness assessments, tools to support shared decision making between patients and healthcare professionals (SDMT), and monitoring studies. Even though the selection and prioritization of topics for HTA depend on health authorities at national and regional levels, all outputs are aimed at supporting decision making for most actors in the SNHS, including health policy decision makers, managers, healthcare professionals, patients, and caregivers.
Main Outputs Delivered by RedETS along 2007–18

The main and more common outputs are the full HTA reports containing conclusions and recommendations based on comparative effectiveness, safety, and cost-effectiveness as well as on budget, organizational, social, and ethical impacts. These reports are commonly used by the Directorate-General for the NHS Portfolio of Services and Pharmacy of the MoH to decide, together with the Regional Health Authorities, on coverage and public funding of health technologies for specific indications and patient groups at a national level. The information on organizational and economic impact also helps regional health policy decision makers and managers in their regional adoption and organizational decisions. Full HTA reports are usually delivered by RedETS in a time frame of 12 months.
The relative effectiveness assessment (REA) containing comparative information on effectiveness and safety, delivered in a maximum time frame of 6–8 months, are also of great value for health policy makers and managers, as well as for healthcare professionals, in most circumstances. Continuous updating of the EUnetHTA POP database (https://www.eunethta.eu/pop-database/) and early dissemination of EUnetHTA REA reports, help to avoid the duplication of work, allowing specific adaptations to the Spanish organizational and economic context.
The early and timely identification of new and emergent health technologies is followed by the completion of short files containing the minimal information required for the later prioritization process. Short REA reports are prepared for prioritized new/emergent technologies in a time frame of 2–4 months.
The CPG Program in the Spanish NHS has the aim of “Promoting the preparation, adaptation and/or updating of CPGs based on the best scientific evidence available with a homogeneous and verified methodology”. The development of a CPG usually requires around 24 months while its update requires 8–18 months. In addition to CPGs, this programme also prepares “other evidence-based products” (OPBE), such as protocols and information for patients and careers by means of the patient versions of CPGs or by the development of tools to support SDMT. While the patients' version of the CPGs requires a maximum of 2–3 months; both, protocol development and the whole process of developing and validating an SDMT usually entails 12 months.
RedETS has been producing methodological, instrumental and procedural reports since 2006 to ease the progressive convergence and mutual recognition of the HTA work/reports among its members. These types of reports tend to be cooperative, mainly for internal use and are not subject to specific deadlines.
Supervised studies (SS) (5) and monitoring studies (MS) (6) use observational designs to reduce uncertainty and support health policy decision making on public funding, at different stages of the postlaunch phase, when evidence is limited. Both, SS and MS, are promoted by the MoH to assess health technologies of high healthcare need or relevance for the NHS, with the aim of providing real world information on effectiveness, and economic or organizational impacts. SS and MS are coordinated and monitored by one of the Spanish HTA agencies belonging to RedETS, by means of a predefined and agreed upon protocol, in a limited number of healthcare settings (predefined by regional health authorities), with a follow-up period of 1–2 years. While SS are applied to health technologies before their inclusion in the Benefit Portfolio of the Spanish NHS, MS corresponds to technologies already included in the Benefit Portfolio of the Spanish NHS to assess specific conditions of use or effects in certain target population groups.
Finally, according to international HTA dynamics and with the aim of making the HTA process more valuable and efficient, some initial experiences of early scientific advice to the medical devices industry have been performed by RedETS in Spain, following the EUnetHTA recommendations (https://www.eunethta.eu/services/early-dialogues/).
Relationships between RedETS and the Spanish Portfolio of Health Benefits
From its official introduction in 2012, RedETS has been involved in most activities driven by the Directorate-General for NHS Portfolio of Services and Pharmacy of the MoH, to review the technologies included in the Benefit Portfolio of the Spanish NHS. To this end, RedETS has a seat in every expert working group organized by the Directorate-General for NHS Portfolio of Services and Pharmacy, together with designated experts from Scientific Societies, representatives from the MoH and the Spanish Agency of Medicines and Sanitary Products (AEMPS). When the reports provided by RedETS to scientifically support this workflow do not solve specific uncertainty areas, the Directorate-General for NHS Portfolio of Services and Pharmacy activates either MS or SS, depending on the previous inclusion or not of the technology under scrutiny in the Benefit Portfolio, to obtain additional evidence for decision making.
To better assist the HTA needs of all Regional Health Authorities, a new Standing Working Group (SWG-HTA) was formed in 2017 by the Directorate-General for NHS Portfolio of Services and Pharmacy to support the activity of RedETS, which was composed of strategic representatives from every regional health service. The SWG-HTA was created to support and improve HTA activities into the Spanish-NHS by managing and assuming regional responsibilities in detecting and setting priorities among health technologies eligible for assessment; providing RedETS with regional data needed for specific HTA reports; taking part in the reviewing processes either of the protocols and/or preliminary reports; and helping in the dissemination and implementation of all outputs delivered by RedETS.
Participation and Transparency in the RedETS Annual Work Program
The annual work plan of RedETS includes different products, with the main ones being: assessments arising from HTA needs of the Regional Health Services; specific assessment needs of the Directorate-General for NHS Portfolio of Services and Pharmacy (MoH); early identification of new/emergent technologies; CPGs and OPBE development or updating; coordination of additional evidence generation studies (SS/MS); and methodological developments for quality improvement and internal and external convergence in the context of the EUnetHTA Joint Action-3 as well as other international and dissemination activities.
The HTA assessments requested by the different Regional Health Services are, by far, the biggest component of the annual working plan: up to four to 5five full reports for each agency in RedETS. These regional assessment needs are identified according to a specific process, executed every year, by the end of summer, by an invitation from the Directorate-General for NHS Portfolio of Services and Pharmacy. Regional Health Authorities are responsible for collecting and compiling the requests received from their respective healthcare systems, which should be submitted by means of a predefined submission form that provides supportive information on the technology. Once compiled and filtered to exclude those that are not potentially relevant, topics are prioritized by a Commission integrated by representatives from all the regions. This prioritization process is carried out with the use of the PRITEC tool (Reference Varela-Lema, Atienza-Merino and López-Garcia7). This is an automatic web tool allowing the ranking of the different technologies based on the score given by the evaluators to a set of previously weighted criteria, distributed by domains. A final list of ranked technologies is delivered to the Spanish MoH as part of this process (Reference Lema L, Rozas MC and Yerro I8).
While patient participation in CPG development has a long and clear international and national history, participation in specific HTA activities are less well developed. RedETS defined a patient participation framework for HTA activities in 2016, envisaging participation in almost every step in the HTA process (Reference Toledo-Chávarri, Perestelo-Pérez and Álvarez-Pérez9), including the identification and prioritization of topics for assessment; defining the scope and objectives of the HTA report; suggesting health relevant outcomes for patients; providing additional contextual experiential knowledge about either the health problem or the technology assessed; helping in developing the simplified patient version of the reports and contributing to a wider dissemination among affected patients and their caregivers. Similarly, a standardized and transparent procedure for industry participation in HTA is currently under development by RedETS.
Additionally, in 2017 RedETS developed a procedural framework to guide good practices and quality assurance in the network (Reference Palenzuela C, Peláez S, López T and López R10). This framework grouped the standards in 12 quality criteria, structured in four dimensions (Responsibility, Clients and Stakeholders, Production Process, and Resources). Furthermore, a first impact assessment of RedETS activities is awaiting publication in the near future.
International Collaboration of RedETS
RedETS participates in different international networks and societies. This broad cooperation in HTA warrants multidirectional exchange of reports and information, also allowing benchmarking procedures to improve assessment activities. Most of the Spanish HTA agencies are members of the International Network of HTA agencies (INAHTA) and are actively participating in the EUnetHTA, as well as in the international scientific society HTA-i and its Interest Groups. RedETS is also committed to the early identification and assessment of technologies promoted by EuroScan activities. Some member agencies have also been collaborating with REDETSA, the regional network of agencies of the Americas; with the Guidelines International Network G-I-N, and the Cochrane Collaboration and/or WHO. Most of the Spanish regional agencies included in RedETS also participate in research activities, as members of national and international research networks and internationally funded research projects (Reference Granados, Sampietro-Colom, Asua, Conde and Vázquez-Albertino11).
Upcoming Challenges for RedETS
Despite current success of RedETS as a national networking organization in HTA committed to sharing, collaborating, and converging, at a European level, with the aims of EUnetHTA, the near future will bring the following challenges (12):
• Contributing to the expansion of the evaluative and transparency culture across the different decision-making levels in the Spanish-NHS, due to observed deviations in health policy decisions at regional level.
• Reinforcing HTA on disinvestment and its impact assessment given that most current RedETS efforts are addressed toward the assessment of new/emerging technologies.
• Promoting a wider use of the early warning systems to detect new and emerging health technologies to provide timely information to support decisions regarding the updating of the Benefit Portfolio of the Spanish-NHS. At present, not all RedETS members are fully engaged in this activity.
• Methods development and consensus for multicomponent and eHealth-based technologies to better afford the growing development and delivery of these types of technologies.
• Solving structural and normative regional barriers and training researchers to increase the use and validity of existing real-world data in HTA activities.
• Ensuring the required funding to extend the use of evidence generation studies to inform coverage decision making, providing real-world data information enriched with patient experiences from different regions.
• Increasing the resources needed to warrant the production and updating of tools to support clinical and shared decision making, linked to more effective implementation procedures. Currently, structural differences in the information systems supporting the electronic clinical records among regions hinder advance.
• Expanding patient involvement (PI) in HTA and assessing its results. The current availability of limited resources to support these activities, forced us to plan a progressive implementation of PI activities with increasing complexity in a growing number of HTA reports.
• Industry implication in HTA should be guided by clear objectives and transparent procedures, with special interest in promoting early dialogs among industry, regulatory authorities and health technology assessors to provide scientific advice. The limited background in transparent and effective cooperation among HTA bodies and the industry will require a specific framework and timeframe.
• Improving dissemination of all RedETS outputs and measuring their short-term decisional impact at regional and national levels. More active dissemination processes might be required to improve uptake of RedETS outputs, especially in regions without HTA organizations.
• Extending and strengthening cooperation with other national and regional evaluative organizations in the Spanish-NHS, such as the AEMPS or other regional bodies assessing medications.
• Strengthening effective and efficient cooperation with all European HTA agencies through EUnetHTA and with the HTA Network in the European Commission.
• Improving recruitment, training, and retention of young multidisciplinary researchers engaged in HTA in Spain.
As a brief conclusion, the development of RedETS took advantage of the decentralized, political and administrative, organization in Spain, favored by the early development and consolidation of several regional HTA organizations in addition to a state level HTA agency. This bottom-up process of building an HTA network exploited all previously existing resources, knowledge and diversity of backgrounds, experience, and prestige; requiring a new and sustained political and economic commitment at national level, in addition to a substantial coordinating effort to successfully develop and share an early common vision, procedures, methods, and outputs under the premise of mutual recognition. Previous periodic collaborative encounters among HTA agencies driven by the AETS-isciii, strengthened by the parallel participation in the process of the EUnetHTA development at European level, together with a long-standing cooperation in national health services research networks might also have contributed to the success of RedETS. The availability of a specific procedure to identify and set HTA priorities, with the participation of all regional health authorities, has also contributed to improve the usefulness and acceptability of RedETS.
Conflicts of interest
The authors declare that they have no conflicts of interest.