Introduction
In bilingual individuals, the first (L1) and the second (L2) language have been shown by behavioral and neurophysiological data to share partly overlapping brain representations (Chee, Tan & Thiel, Reference Chee, Tan and Thiel1999; Illes, Francis, Desmond, Gabrieli, Glover, Poldrack, Lee & Wagner, Reference Illes, Francis, Desmond, Gabrieli, Glover, Poldrack, Lee and Wagner1999; Kim, Relkin, Lee & Hirsch, Reference Kim, Relkin, Lee and Hirsch1997; Perani & Cappa, Reference Perani, Cappa, Denes and Pizzamiglio1998), with the degree of overlap of each language depending on the age of acquisition (Kim et al., Reference Kim, Relkin, Lee and Hirsch1997), immersion and proficiency (Abutalebi, Reference Abutalebi2008; Perani & Abutalebi, Reference Perani and Abutalebi2005). Neuroimaging studies of language organization in bilinguals suggest that the earlier the age of acquisition and the higher the proficiency in the second language, the larger will be the overlap of the brain representations of L1 and L2 in various aspects of comprehension and production (Chee, Hon, Lee & Soon, Reference Chee, Hon, Lee and Soon2001; Hernandez, Martinez & Kohnert, Reference Hernandez, Martinez and Kohnert2000; Klein, Milner, Zatorre, Meyer & Evans, Reference Klein, Milner, Zatorre, Meyer and Evans1995; Klein, Zatorre, Milner, Meyer & Evans, Reference Klein, Zatorre, Milner, Meyer and Evans1994; Perani, Paulesu, Galles, Dupoux, Dehaene, Bettinardi, Cappa, Fazio & Mehler, Reference Perani, Paulesu, Galles, Dupoux, Dehaene, Bettinardi, Cappa, Fazio and Mehler1998). The brain regions supporting both L1 and L2 include the left and, occasionally, the bilateral frontal and temporal areas (Abutalebi & Green, Reference Abutalebi and Green2007; Fabbro, 2001b).
This overlap of L1 and L2 representations is supported by studies of post-stroke aphasia in bilinguals. Patients often display parallel modes of impairment and recovery in their first and second language (Fabbro, 2001a; Tschirren, Laganaro, Michel, Martory, Di Pietro, Abutalebi & Annoni, Reference Tschirren, Laganaro, Michel, Martory, Di Pietro, Abutalebi and Annoni2011). However, some biographical factors may affect the level of overlap and functioning of L1 and L2. For example, L2 semantic processing can be affected by the level of proficiency in L2, and syntactic processing seems to depend on the age of second-language acquisition (Wartenburger, Heekeren, Abutalebi, Cappa, Villringer & Perani, Reference Wartenburger, Heekeren, Abutalebi, Cappa, Villringer and Perani2003; Weber-Fox & Neville, Reference Weber-Fox and Neville1996). These findings support the idea that, while grammatical processing of a late second language relies on explicit processing, the processing of the first language's grammar relies on implicit processing (Ullman, Reference Ullman2001).
Studying the elderly and populations with neurodegenerative disease may also allow the testing of predictions on these language models. Normal aging seems to affect both languages equally (Juncos-Rabadan & Inglesias, Reference Juncos-Rabadan and Inglesias1994). In DAT, different patterns of language impairment have been found, however, the dominant trend suggests that neurodegenerative diseases impact more on the non-dominant language. According to the above-mentioned neuropsychological theories, it has been proposed that cortical dementia, such as dementia of the Alzheimer type or progressive aphasia, would more importantly impair explicit semantic and syntactic L2 processing (Paradis, Reference Paradis, Stemmer and Whitaker2008), while implicit L1 processing predominantly involving the basal ganglia would be spared (Zanini, Angeli & Tavano, Reference Zanini, Angeli and Tavano2011). Further evidence for different neural networks for L1 and L2 processing come from studies showing that late bilinguals do not achieve native-like competence in L2 syntax (Long, Reference Long1990). Studies of epileptic patients showing that brain stimulation can impair specifically one language also suggest that some cortical areas may be more bound to one than the other language (e.g. Giussani, Roux, Lubrano, Gaini & Bello, Reference Giussani, Roux, Lubrano, Gaini and Bello2007).
However, more recent studies better controlled for biography of bilingualism have failed to show such differential impairment of L1 and L2 (Costa, Calabria, Marne, Hernández, Juncadella, Gascón-Bayarri, Lleó, Ortiz-Gil, Ugas, Blesa & Reñé, Reference Costa, Calabria, Marne, Hernández, Juncadella, Gascón-Bayarri, Lleó, Ortiz-Gil, Ugas, Blesa and Reñé2012). Costa and colleagues suggest that the “neural substrates of the lexico-semantic representations are largely shared (at least at the macroscopic level) between the two languages” (ibid., p.749). Support for a shared bilingual neural substrate also comes from stroke studies (Tschirren et al., Reference Tschirren, Laganaro, Michel, Martory, Di Pietro, Abutalebi and Annoni2011), as well as experimental priming studies observing shared lexicons (Dijkstra, Reference Dijkstra, Kroll and de Groot2005) and syntax (Hartsuiker, Pickering & Veltkamp, Reference Hartsuiker, Pickering and Veltkamp2004; Kantola & van Gompel, Reference Kantola and van Gompel2011).
DAT is a neurodegenerative disease evolving in dementia syndromes and is characterized by a progressive decline of episodic and working memory, followed by language deficits (Faber-Langendoen, Morris, Knesevich, LaBarge, Miller & Berg, Reference Faber-Langendoen, Morris, Knesevich, LaBarge, Miller and Berg1988). Language deficits in DAT have been the focus of numerous studies, but how DAT affects both languages of bilinguals, and in particular late bilinguals, has so far not been investigated systematically.
In monolinguals, one of the first symptoms of linguistic decline related to DAT are word-retrieval difficulties (Cardebat, Demonet, Puel, Agniel, Viallard & Celsis, Reference Cardebat, Demonet, Puel, Agniel, Viallard and Celsis1998; Gomez & White, Reference Gomez and White2006). Later, DAT patients typically exhibit deficits at the level of oral production, semantic dissociations (Ulatowska, Allard, Donnell, Bristow, Haynes, Flower & North, Reference Ulatowska, Allard, Donnell, Bristow, Haynes, Flower and North1988) and both quantitative and qualitative discourse impoverishment (Heller, Dobbs & Rule, Reference Heller, Dobbs and Rule1992). As the disease progresses, DAT affects written production and comprehension (Cardebat et al., Reference Cardebat, Demonet, Puel, Agniel, Viallard and Celsis1998).
However, language impairments in monolinguals with DAT remain heterogeneous, and their temporal dynamics show a high degree of variability. Language deficits may be manifest at the onset of DAT, or appear later as the disease develops (Cummings, Benson, Hill & Read, Reference Cummings, Benson, Hill and Read1985). Neuropathologically, DAT manifests at the levels of several language-related brain areas. In the initial stage of the disease, neurofibrillar degeneration occurs within all polymodal cortical regions, including the superior temporal cortex, the frontal pole and the parietal cortex. Typically, the degeneration then further extends to the subcortical nuclei (Delacourte, Reference Delacourte2000).
Collectively, previous evidence concerning the organization of language in bilinguals and brain lesion patterns in DAT patients suggests that global L1 and L2 deficits should manifest in late, proficient bilingual DAT patients. To our knowledge, whether language deficits in bilinguals with DAT will manifest similarly in each language remains unknown, as this has rarely been tested systematically. Indeed, previous studies of language in bilingual patients with DAT focused on the analysis of a single language function or theme (e.g. Fama, Sullivan, Shear, Stein, Yesavage, Tinklenberg & Pfefferbaum, Reference Fama, Sullivan, Shear, Stein, Yesavage, Tinklenberg and Pfefferbaum2000). For instance, Salvatierra, Rosselli, Acevedo and Duara (Reference Salvatierra, Rosselli, Acevedo and Duara2007) investigated semantic and phonemic fluency in bilinguals with DAT and showed that while healthy participants produced more words in the semantic than the phonemic condition, the DAT patients’ performances were the same in both tasks, in both languages. The authors interpreted this finding in terms of a general deficit in semantic processing which only indirectly impairs semantic fluency.
Further, some case studies on the impact of bilingualism on language functions in dementia patients focused on discursive and conversation analyses. Hyltenstam and Stroud (Reference Hyltenstam, Stroud, Hyltenstam and Obler1989) showed that bilinguals with DAT have difficulty in selecting the appropriate language during daily conversations. More recent studies, which have focused more specifically on L1 and L2 impairment in DAT, suggest a parallel progressive impairment of L1 and L2 for early bilinguals (Gómez-Ruiz, Aguilar-Alonso & Espasa, Reference Gómez-Ruiz, Aguilar-Alonso and Espasa2012), and for naming capacities in more distant languages, such as English and Spanish (Gollan, Salmon, Montoya & da Pena, Reference Gollan, Salmon, Montoya and da Pena2010). However, this last study considered L2 as the less proficient language and did not look at the age of acquisition.
In the current study, we used a mixed design to compare language production performance in the first and second languages of bilinguals with DAT to healthy participants matched by age and bilingualism at the level of proficiency, age of acquisition and immersion. We focused on several tasks including semantic, lexical and grammatical aspects, as well as automatisms and transcoding.
Materials and methods
The study was approved by the local Ethics Committee of Fribourg and Geneva, Switzerland, and all participants provided written informed consent in accordance with the Declaration of Helsinki.
Participants
Inclusion criteria for patients were: (i) a diagnosis of DAT (probable or possible Alzheimer's disease) according to good clinical practice; (ii) a Mini-Mental State Examination (MMSE; Gollan et al., Reference Gollan, Salmon, Montoya and da Pena2010) ≤ 25 and ≥ 10; and (iii) a Clinical Dementia Rating (CDR) of 1 or 2 (Morris, Reference Morris1993).
Exclusion criteria were: (i) unaided sensory disorders; (ii) history of stroke, vascular dementia, Parkinson's disease, psychiatric disorders, major illness (e.g. cancer) and any other neurological disorders; (iii) a score > 7 on the Hachinski scale (Hachinski, Oveisgharan, Romney & Shankle, Reference Hachinski, Oveisgharan, Romney and Shankle2012); (iv) extrapyramidal rigidity of the upper limbs with a score > 2, based on item 22 of the Unified Parkinson's Disease Rating Scale (UPDRS) motor score (Movement Disorder Society Task Force on Rating Scales for PD, 2003); and (v) widespread deep white-matter hyper-intense lesions and/or extensive, irregular periventricular hyper-intense lesions, and/or micro-haemorrhage.
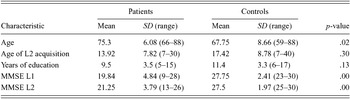
The inclusion criterion for the control subjects was an MMSE > 25. Exclusion criteria were a history of neurological, medical or psychiatric disorders and abnormal neurological examinations. The control population was matched to the patients by age, education level and age of acquisition of L2 (see Table 1).
Demographic characteristics of the Patient Group (n = 13) and the Control Group (n = 12).

SD: standard deviation; MMSE: Mini-Mental State Evaluation; L1: first language; L2: second language. p-value: uncorrected independent sample t-tests, p-value refers to difference between controls and patients.
For both groups, bilingualism-related inclusion criteria were: (i) French as a second language (L2) with late acquisition (> 7 years); (ii) immersion in L2 French > 20 years; (iii) mother tongue (L1) German, Spanish or Italian. The total score for L2 proficiency (speech comprehension, writing and reading) was 75.9 ± 4.6% for the patients and 75.4 ± 3.6% for the controls (t = 0.09; p = .92). Moreover, a previous medical history of language/speech difficulties (e.g. developmental dyslexia) was an exclusion criterion for both groups.
Patients
The patients were recruited from the neurology departments at the hospitals of Fribourg, Lausanne and Geneva and underwent a complete neuropsychological assessment. Out of 20 screened bilingual patients, 13 right-handed bilingual patients with dementia were included in the study (seven females). All the patients had French as L2. Three patients had Italian, two had Spanish and eight had German as L1. Their dementia was diagnosed by an experienced neurologist, trained on the basis of clinical criteria for dementia as defined by CDR > 0.5 (Morris, Ernesto, Schafer, Coats, Leon & Sano, Reference Morris, Ernesto, Schafer, Coats, Leon, Sano, Thal and Woodbury1997), the diagnosis of possible or probable DAT according to NINCDS-ADRDA (McKhann, Drachman, Folstein, Katzman, Price & Stadlan, Reference McKhann, Drachman, Folstein, Katzman, Price and Stadlan1984) and the Swiss Consensus for Dementia Diagnosis (Monsch, Hermelink, Kressig, Fish, Grob, Hiltbrunner, Martensson, Rüegger-Frey & von Gunten, Reference Monsch, Hermelink, Kressig, Fisch, Grob, Hiltbrunner, Martensson, Rüegger-Frey and von Gunten2008). Eleven patients had probable DAT and two possible DAT. See Table 1 for detailed demographic information.
Controls
Twelve right-handed healthy participants (five females) were included as a control group. All participants had French as L2. Three had Italian, two had Spanish and seven had German as L1 (Table 1).
Procedure
The tests were conducted in two sessions with an interval of one to ten days between each session. One session was in French (L2) and the other in the participant's native language (L1: Italian, Spanish, or German). The order of the L1 and L2 sessions and of the tests within each session was counterbalanced across participants.
Materials
Evaluation of bilingualism
Proficiency and immersion in L2 were assessed using internally-developed questionnaires consisting of a visual analogue scale, which were scored by the examiner based on the patient's answers and validated by the family. The questionnaires evaluated L2 proficiency at the level of oral and written expression, oral comprehension and reading in L2 French, levels of exposure to and use of L1 and L2 as a percentage frequency of the languages used in childhood and languages currently used in learning and spoken within the family (Tschirren et al., Reference Tschirren, Laganaro, Michel, Martory, Di Pietro, Abutalebi and Annoni2011).
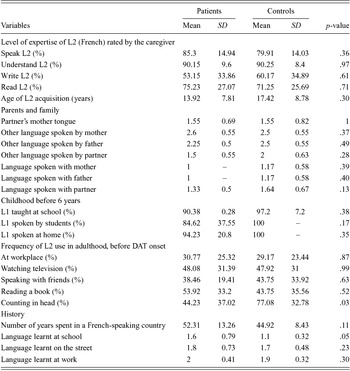
The patient group matched the control group in all the criteria evaluating the level of bilingualism. Table 2 presents the mean values, standard deviations and ranges for these variables for each population and the statistical assessment of the degree of matching between the two groups.
Comparison between Patients and Controls on variables influencing bilingualism.

SD: standard deviation; L2: second language; Partner's mother tongue: 1 = German, 2 = French, 3 = other; p-value: uncorrected independent sample t-tests, p-value refers to difference between controls and patients.
Evaluation of oral language
Comprehension and expression of oral language were assessed in both L1 and L2 using the following tests:
From the Boston Diagnostic Aphasia Evaluation (BDAE; Mazeaux, Orgogozo, Goodglass & Kaplan, Reference Mazeaux, Orgogozo, Goodglass and Kaplan1983; Naeser & Hayward, Reference Naeser and Hayward1978), the following subtests were selected: (i) Verbal discrimination: associating images of six objects, six actions, six shapes, six symbols, six colours and six figures to orally pronounced words; (ii) Order execution: performing an oral command; (iii) Oral naming: naming of six objects, six actions, two shapes, six symbols, six colours, six figures and three body parts; (iv) Performance in automatic language (Counting): counting aloud to 21.
From the Bilingual Aphasia Test (BAT; Paradis, Reference Paradis2011), the following subtests were selected: (i) Syntactic comprehension: selecting the image that corresponds to the orally-presented sentence; (ii) Repetition of words and non-words: a lexical decision task is associated with each word, the patient repeats an orally-presented word, and then has to say whether the word exists or not; (iii) Repetition of sentences: repeating orally presented sentences.
Finally, for verbal fluency, the Isaacs Set Test (Isaacs & Kennie, Reference Isaacs and Kennie1973) was used. The patient was asked to produce as many nouns as possible from four semantic categories (colours, towns, animals and fruits) which alternated every 15 seconds.
The choice of the BDAE and the BAT were based on the fact that these tests have been validated in French and German, which were the main languages of our groups. The tests in each language were performed on two different days with an interval of 1 to 10 days. The evaluator was different for each language and was always a native speaker of the language of interest, except in the case of a Spanish–French patient, whose examiner was a highly proficient bilingual in both Spanish and French.
Statistical analysis
Bilingual competence and demographic factors were compared between the patients and the healthy controls using uncorrected independent sample t-tests.
Language performance between the patients and the healthy controls was analysed using a 2 × 2 mixed analysis of variance (ANOVA) design, with Language (L1; L2) as within-subject factor and Group (controls; patients) as between-subject factor. Correction for multiple tests was achieved using the Bonferroni method. All data analyses were performed using SPSS (version 19; SPSS Inc.).
Results
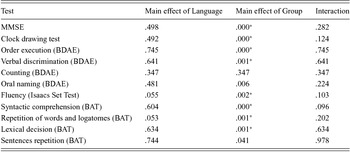
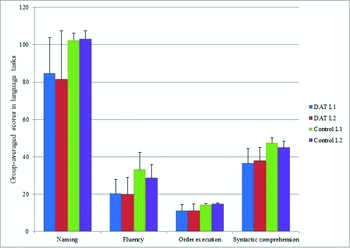
All results are summarized in Table 3 (see also Figure 1). We only report the essentials here. As was expected from the inclusion criteria, the groups differed significantly in their MMSE scores (p < .000). The Language × Group ANOVA revealed a significant (p < .005) main effect of Group for all the tests (all p-values < .004; see Table 3), except for Counting (p = .347), Oral naming (p = .006) and Sentence repetition (p = .041). There was no main effect of Language and no interaction (all p-values are reported in Table 3).
p-values of the effects obtained in the different language test scores.

Note: Correction for multiple tests was achieved using the Bonferroni method (11 tests, alpha set to .005). The significant values are marked with an *.
Group-averaged scores in two expressive language tasks (BDAE Oral naming task – here scores are divided by two for graphic purposes – and Isaacs Set Test (Verbal fluency task)), and in two receptive language tasks (BDAE Order execution and BAT Syntactic comprehension task) in the first (L1) and second (L2) language. DAT patients performed worse than the controls in Fluency, Order execution and Syntactic comprehension tasks. No differences were found between languages, and there were no Language × Group interactions (see text for details).

Discussion
To identify the impact of DAT on both languages of the bilinguals, we assessed language comprehension and oral production in a group of 13 DAT patients and 12 matched controls using 2 × 2 mixed designs with First Language (L1) and Second Language (L2) as within-subject factor and Group (DAT patients and controls) as between-subject factor. For all tests except Sentence repetition, Oral naming and Counting, there were main effects of the factor Group, driven by the poorer performance of the DAT patients compared to the controls. There were no main effects of Language, and, critically, we did not find evidence of interaction between the factors Group and Language, suggesting that DAT impaired L1 and L2 similarly.
Main effect of Group
As expected, the main effects of Group revealed that the DAT patients performed less well than the control group in terms of language, despite having the same biography of bilingualism.
The DAT patients performed worse in all language tests except Counting, Oral naming and Sentence repetition. This result corroborates previous findings that linguistic automatisms are preserved in the early stages of DAT (Gomez & White, Reference Gomez and White2006). The tests employed for both languages in the DAT group are those involving the lexico-semantic system (for instance, complex comprehension (Order execution) or verbal fluency) because these abilities are impaired very early on in the course of DAT (Ullman, Reference Ullman2004). In contrast, other tasks in our neuropsychological battery involved aspects such as automatic counting and repetitions, which rely on automatic mechanisms and subcortical brain regions usually spared in early DAT (Arroyo-Anllo, Bellouard, Ingrand & Gil, Reference Arroyo-Anllo, Bellouard, Ingrand and Gil2011).
No main effect of Language
We did not find any main effect of Language, confirming that language performance was similar in both L1 and L2 in our sample. The global rating of L2 proficiency in the DAT patients provided by their families, and the self-ratings by the controls in oral comprehension and oral expression were higher or equal to 80% of the proficiency in L1. The study of populations with comparable L1 and L2 proficiency was important to the present study because most of our language tasks focused on oral language and were thus strongly influenced by the proficiency of the participants. In our sample, the high proficiency of elderly people in both L1 and L2 is in line with previous evidence for a limited impact of aging on L2. Schrauf (Reference Schrauf2009), for example, demonstrated that in elderly immigrants, L2 is well preserved in healthy subjects, particularly in those that have children and are well integrated into their L2 community.
There was no main effect of Language for the Syntactic comprehension tasks of the BAT, corroborating that aspects of language acquired late are well preserved in late bilingual immigrants as those included in the current study (Schrauf, Reference Schrauf2009).
It should be noted that a marginally significant effect of Language was found in fluency (Isaacs Set Test) and the repetition of words and logatomes (BAT). Marginal uncorrected effects in the repetition tests call for further studies with larger groups and patients with more advanced DAT, to test for preservation of L1 phonological processing. Phonological processes are generally found to be less impaired in DAT (Bayles, Tomoeda & Trosset, Reference Bayles, Tomoeda and Trosset1992; Glosser & Deser, Reference Glosser and Deser1991; Nebes, Reference Nebes, Craik and Salthouse1992). Glosser and colleagues (1997) report that for word and non-word repetition, monolingual DAT patients show worse performance than controls. The results of the patients were not correlated with the severity of DAT. The patients produced the same types of errors as the controls and repeated words better than non-words. The authors conclude that the DAT patients use the same phonologic system for the repetition of the two types of stimuli, i.e. independently of their meaning. In the present study, the slight main effect of language at the level of the Repetition task may be linked to better preservation of phonological capacities in L1.
No Language × Group interaction
The main result of the present study is the absence of an interaction between the factors Group and Language in any of the language tasks. This pattern of results supports the argument that degenerative processes in DAT impact equally on L1 and L2 and that L1 is not specifically spared in DAT.
This pattern corroborates previous literature on the effect of DAT on language and on the organization of language in the bilingual brain. Thus, current evidence suggests that the cortical representations of L1 and L2 overlap at the level of the aspects impaired by DAT, and therefore DAT should provoke the same deficits in L1 and L2.
Indeed, the convergence hypothesis of language representation in bilinguals (Abutalebi & Green, Reference Abutalebi and Green2007) posits an overlap of L1 and L2 representations for semantico-lexical aspects including, for example, naming (Hernandez, Dapretto, Mazziotta & Bookheimer, Reference Hernandez, Dapretto, Mazziotta and Bookheimer2001) or semantic judgment (Illes et al., Reference Illes, Francis, Desmond, Gabrieli, Glover, Poldrack, Lee and Wagner1999). The specific characteristics of our patient group (late bilinguals) allowed us to test Ullman's hypothesis differentiating between implicit and explicit syntactic/grammatical learning. Generally, early L1 would be subserved by fronto-subcortical loops involving left frontal and basal ganglia structures, while explicit processing associated to L2 would be associated with bilateral temporal (particularly lateral) lobes structures (Ullman, Reference Ullman2001).
Greater syntactic impairments in L1 than L2 in bilingual Parkinson's disease patients have been proposed as evidence for this theory (Zanini, Tavano, Vorano, Schiavo, Gigli, Aglioti & Fabbro, Reference Zanini, Tavano, Vorano, Schiavo, Gigli, Aglioti and Fabbro2004). Basal ganglia are not early targets of either Alzheimer's disease or normal aging, in contrast with temporal lobe atrophy in DAT. Temporal lobe atrophy would predict an interaction in syntactic performance, due to stronger impairment of L2, which is not the case here. Thus our data do not support divergent syntactic representation for L1 and L2.
To summarize, our data support the convergent representation, but marginal Language effects in repetition and verbal fluency raise the question of some cortical specialization. Larger studies which include L2 proficiency as covariate may help to answer this point. Furthermore, while L2 requires supplementary cognitive resources when its proficiency is lower than L1, the convergence of brain representations for L1 and L2 increases with L2 proficiency (Abutalebi, Reference Abutalebi2008; Stein, Federspiel, Koenig, Wirth, Lehmann, Wiest, Strik, Brandeis & Dierks, Reference Stein, Federspiel, Koenig, Wirth, Lehmann, Wiest, Strik, Brandeis and Dierks2009; Wartenburger et al., Reference Wartenburger, Heekeren, Abutalebi, Cappa, Villringer and Perani2003).
Perani et al. (Reference Perani, Paulesu, Galles, Dupoux, Dehaene, Bettinardi, Cappa, Fazio and Mehler1998) tested in a PET study whether the age of acquisition or the proficiency determined the degree of convergence of the brain region involved in processing L1 and L2. Their population were Italian–English highly proficient bilinguals with late age of acquisition (> 10 years) and a group of Spanish–Catalan bilinguals with early age of acquisition (< 4 years). The late acquisition group listened to stories in Italian, English and Japanese (an unfamiliar language), while the early acquisition group listened to stories in L1 and L2. The authors showed that even if the age of acquisition was late, oral comprehension involved the same areas in L1 as in L2, if L2 was highly proficient.
We hypothesize that the two languages of our patients were similarly affected by DAT as those of the controls were affected by normal aging because there was no difference between the groups in L2 proficiency or in age of L2 acquisition. Our results suggest that late bilinguals living in a French-speaking environment reach a high level of immersion and proficiency in L2, which is maintained during aging and even neurodegenerative disorders. Our patients arrived in French-speaking Switzerland and began to learn their second language between the ages of 7–30 years of age. They have been living in their second country for 50 years, have developed their social skills in L2, and use their second language for a large part of their activities (watching television, reading books, even mental arithmetic), suggesting that their L2 actually has become their preferred way of communicating. Another possible reason is that the region where the patients live is partly bilingual, thus promoting the preservation of both languages. Thus, 12 out of the 13 patients live in Fribourg, a strongly French–German bilingual environment, and one in Geneva, a predominantly French-speaking region.
Costa et al. (Reference Costa, Calabria, Marne, Hernández, Juncadella, Gascón-Bayarri, Lleó, Ortiz-Gil, Ugas, Blesa and Reñé2012) and Gómez-Ruiz, Aguilar-Alonso and Espasa (Reference Gómez-Ruiz, Aguilar-Alonso and Espasa2012) studied early bilinguals whose languages were linguistically very close. They found a difference only in spontaneous speech, where DAT patients produced more words and sentences in Catalan. In the BAT subtests that they used, only the Verbal fluency subtest showed slightly higher mean performances in Spanish (mean = 19.9) than in Catalan (mean = 13.6). Thus, in their population, L2 was slightly better preserved than L1 in verbal fluency tasks, a result which supports the role of social immersion in language preservation. We selected participants from various mother tongue languages (Italian, German and Spanish). The linguistic families of these languages differ, thus enabling us to be sure that the lack of Group × Language interaction did not arise from the fact that our patients and controls spoke specific types of languages.
Our data do not support the declarative/procedural theoretical model proposed by Paradis (Reference Paradis, Stemmer and Whitaker2008), i.e. that in the L1, grammatical knowledge depends mostly on procedural memory processes supported by the left fronto/basal-ganglia structures (Ullman, Reference Ullman2001; Ullman, Reference Ullman2004). In this model, the L2 of late bilinguals relies on more explicit knowledge, which is mostly supported by the cortical area. Consequently, cortical degeneration diseases, such as DAT, should lead to decreased L2 performances in syntactical scores. In our DAT group (and in Gomez-Ruiz's group of patients), performances in syntactic tasks did not differ between L1 and L2.
The lack of difference in the impact of DAT on L1 and L2 is also in line with previous data on stroke-induced language impairment in bilinguals, which show that lesions impair L1 and L2 similarly (Tschirren et al., Reference Tschirren, Laganaro, Michel, Martory, Di Pietro, Abutalebi and Annoni2011). A meta-analysis by Paradis (Reference Paradis1995) also showed that L1 and L2 improve to a similar extent and concurrently in 61% of patients during post-lesion recovery. To further support the argument that brain damage similarly affects L1 and L2, growing evidence indicates that after brain lesions there is active transfer from one language to the other, which was observed in about half of the stroke patients who received monolingual speech therapy (Faroqi-Shah, Frymark, Mullen & Wang, Reference Faroqi-Shah, Frymark, Mullen and Wang2010). Moreover, such transfer seems more effective if the languages have more structural similarities, as in the current study (Goral, Levy & Kastl, Reference Goral, Levy and Kastl2010).
An important limitation of the present study is that our interpretations are based on negative results (i.e. a lack of Group × Language interaction). Negative results should be interpreted with caution since a finding of no interaction does not provide definitive evidence that there are no interactions. This issue is particularly relevant in the current study since we have limited statistical power and thus the probability of type II errors is increased (Moher, Dulberg & Wells, Reference Moher, Dulberg and Wells1994). Post-hoc power analyses were conducted using G*Power 3.1.5 (Faul, Erdfelder, Buchner & Lang, Reference Faul, Erdfelder, Buchner and Lang2009) to compute the number of patients needed per group to reach a significant p-value (p < .05), with an effect size of 0.8 when comparing the mean of the two groups using an independent sample t-test. The results indicate that, to reach a power of 0.8, each group should be of 26 participants. Further studies with larger sample sizes are thus required to confirm our finding that DAT affects L1 and L2 similarly in bilinguals.
The tendency for a Language × Group interaction for the Syntactic comprehension task should be further explored in patients with more severe DAT than that in our group. Previous studies comparing semantic and syntactic performance between monolingual DAT to controls showed no difference at the level of syntactic processing, suggesting that the structural language of DAT patients remained rich (Kave & Levy, Reference Kave and Levy2003; Lai, Pai & Lin, Reference Lai, Pai and Lin2009). In contrast, at the semantic level, DAT patients produced a less informative discourse and more semantic errors than the controls.
The marginally significant effect of Language in the Isaacs Set Test with better scores in L1 than L2 may result from the fact that in verbal fluency tasks, bilingual individuals produce more intrusion errors in their non-dominant language. This tendency may not be present in other tasks, for example naming, because they are less sensitive to interference (Gollan, Montoya, Cera & Sandoval, Reference Gollan, Montoya, Cera and Sandoval2008; Gollan, Montoya, Fennema-Notestine & Morris, Reference Gollan, Montoya, Fennema-Notestine and Morris2005). Alternatively such results may be consistent with the hypothesis suggested by Costa (2012, p. 749) for a “largely–but not totally” shared network between the two languages, with a larger implication of subcortical structures for L1 being less sensitive both to aging (Joanette, Ali-Cherif, Delpuech, Habib, Pellissier & Poncet, Reference Joanette, Ali-Cherif, Delpuech, Habib, Pellissier and Poncet1983) and cortical degeneration (Zanini et al., Reference Zanini, Angeli and Tavano2011). Prestia, Baglieri, Pievani, Bonetti, Rasser, Thompson and Frisoni (Reference Prestia, Baglieri, Pievani, Bonetti, Rasser, Thompson, Marino, Bramanti and Frisoni2013) showed that aging impacted on the cortex of healthy individuals at the level of fronto-temporo-parietal regions. This hypothesis should be explored with larger studies.
In addition, the use of questionnaires to rate premorbid proficiency in patients and current proficiency in controls may also be a limiting factor in the present study, since the patients’ families may have misjudged the true level of patients’ premorbid L2 proficiency. There is, however, no other possible way to evaluate the patients’ previous language knowledge (except through access to previous language examinations, which is very rare). Moreover, a number of studies have demonstrated the validity of this questionnaire in assessing language proficiency (e.g. Schrauf, Reference Schrauf2009), and have shown that self-ratings correlate with objective measures of proficiency in highly proficient subjects (Marian, Blumenfeld & Kaushanskaya, Reference Marian, Blumenfeld and Kaushanskaya2007).
The mean MMSE of our patients group were respectively 19.8 for L1 and 21.2 for L2. Moreover, we restricted our DAT group to MMSEs higher than 10. Because of this exclusion criterion, the patient group was in the mild to moderate severity range of DAT, and our data must be interpreted for this group. We cannot rule out that Group × Language interactions may appear in more severe DAT cases. However, in a recent study of 71 Catalan--Spanish bilinguals, the severity of the dementia as measured by the MMSE could not explain the differences in the performances between L1 and L2 (Costa et al., Reference Costa, Calabria, Marne, Hernández, Juncadella, Gascón-Bayarri, Lleó, Ortiz-Gil, Ugas, Blesa and Reñé2012), which suggests that this issue is not necessarily critical.
Another limitation of the present study is the difference in age between our two populations (patients: mean age = 75.3 years; controls: mean age = 67.7 years), which may have confounded differences related to the presence of DAT and may explain some of the main effects of Group in the language tests. The decrease in language performance in normal aging is moderate and generally manifests after 70 years of age. Most probably, the main effect of Group in tasks with high attentional demand (Oral naming, Isaacs Set Test and Syntactic comprehension) may be accounted for by the difference in age (Eustache, Reference Eustache, Eustache and Lechevalier1993). However, we did not find a significant main effect of Group for Oral naming, suggesting that the age difference cannot be advanced as the only cause of the between-group differences we have found. This finding calls for further studies with perfectly age-matched populations.
In addition to the effect of normal aging on language, another problem related to age differences between patients and controls is the putative modification of language control with age, which may affect L1 or L2 production indirectly. However, recent findings suggest that age-related inhibition decline concerns mostly balanced bilinguals and late bilinguals to a lesser degree (Goral, Campanelli & Spiro, published online April 4, Reference Goral, Campanelli and Spiro2013). We would also note that our primary interest was the interaction between the two factors Group and Language, not the main effect of the groups. In this regard, the difference in age most likely impacted similarly on L1 and L2 and thus did not influence the interaction.
In addition to assessing language performance, future study should focus on language control, a key aspect in language impairment and recovery in neurologically impaired bilingual patients. We did not assess language control in the present study because the DAT population showed a high degree of fatigability, and we thus had to choose a limited number of tests of interest among all possibilities. Language control has indeed been advanced as a potential factor influencing whether and how L1 and L2 recover after stroke (e.g. Abutalebi, Della Rosa, Tettamanti, Green & Cappa, Reference Abutalebi, Della Rosa, Tettamanti, Green and Cappa2009). Such mechanisms may also influence language performance in bilingual DAT populations.
Our results also provide insights into whether language assessment in dementia cases should be conducted in L1 or L2 in bilingual individuals (Faroqi-Shah et al., Reference Faroqi-Shah, Frymark, Mullen and Wang2010; Gollan et al., Reference Gollan, Salmon, Montoya and da Pena2010). On the basis of our results, it would appear that at present there is no reason to choose one language over the other for the purposes of neuropsychological assessment of DAT.