CHD represent a broad spectrum of disease, which spans from minor subclinical anomalies to severe defects that are incompatible with life. The incidence of CHD is known to vary across geographical regions and over time. From the 1930s through to the 1990s, a substantial increase in CHD prevalence was observed. Interestingly, the increase over time was not constant (per unit time) but rather S-shaped; that is it increased from 1930 to 1960 (0.6 to 5.3 per 10,000), followed by a plateau phase, and a new sharp increase from the late 1970s until the mid 1990s where it stabilised around 9.1 per 10,000.Reference van der Linde 1 Routine use of echocardiography has been shown to increase the detection of minor anomalies,Reference Reller 2 and it is generally agreed upon that some of the increased CHD prevalence may well reflect advances in diagnostics rather than true changes in prevalence.Reference van der Linde 1 , Reference Oyen 3 Concurrently, surgical and pharmacological therapies have substantially reduced fatality among children with CHD.Reference Mandalenakis 4 , 5 Furthermore, deaths from CHD have shifted away from infants and towards adults, with an increasing age at death.Reference Khairy 6 The reduced fatality rate from CHD has been brought along by more specialised care for both surgical and non-surgical admissions, 5 but the hospitalisation rate for paediatric chronic heart failure has remained stable.Reference Rossano 7 Although massive improvements in management of chronic heart failure in adults have been achieved,Reference Sacks, Jarcho and Curfman 8 data on optimal management of paediatric chronic heart failure are lagging. This has prompted some authors to suggest that there is a state of “nihilism” regarding paediatric chronic heart failure therapy such that treatment known to be effective in adults is withheld to children.Reference Schranz and Voelkel 9 To our knowledge, no study has addressed prescription of cardiovascular drugs to children, except in children admitted with acute decompensated heart failure.Reference Moffett and Price 10 Owing to a paucity of data on prescription of cardiovascular drugs to children, it is, in our opinion, difficult to argue a case of either under- or over-treatment.
We sought to examine trends in prescription of cardiovascular drugs to children in two Nordic countries and correlate this with the prevalence of CHD over an 18-year period.
Methods
Data were included in Norway from 1 January, 2004 to 31 December, 2016 and in Denmark from 1 January, 1999 to 31 December, 2016. We retrieved data on the use of cardiovascular drugs according to the Anatomical Therapeutic Chemical classification system from a publicly accessible database in NorwayReference Berg, Fenne and Furu 11 and Denmark. 12 The registers include drug sale from pharmacies in defined daily doses. Defined daily dose is a World Health Organization-defined statistical measure of drug consumption. It represents the assumed average maintenance dose required by an adult taking the drug for its primary medical indication. We compiled data on the sale and use of the cardiovascular drug (Anatomical Therapeutic Chemical code: C03–C09) in defined daily doses. Data on cardiovascular drugs were divided into the following categories: C01A, cardiac glycosides (Digoxin); C01B, anti-arrhythmic drugs (Class I, III, IV); C03C and C03DA, diuretics; C07, beta blockers; C08D, selective calcium-channel blockers; C09, drugs affecting the renin–angiotensin system. Total sale of cardiovascular drugs was defined as follows: the total amount of defined daily doses sold by Norwegian and Danish pharmacies in the period. The sale therefore reflects prescription from both outpatient clinics at hospitals and from general practitioners. It does not include data on drugs used while the patients were admitted to hospital.Reference Schmidt 13 When extracting data from the Norwegian and Danish databases, we noted a slight discrepancy between the total defined daily doses prescribed of a given Anatomical Therapeutic Chemical code Fourth-level class of drugs (e.g. beta blockers) and the number we found by adding all Anatomical Therapeutic Chemical code Fifth-level drugs (e.g. metoprolol, atenolol etc.) in that class together. In all these instances, we have used the summed value for the Fifth level to account for the total Fourth-level prescriptions. All original data extracts are provided in the supplement along with detailed data analysis (Supplementary material S1).
All CHD prevalence data from Norway and Odense (Denmark) were accessed through the European Surveillance of Congenital Anomalies website 14 Both the Norway and Odense registry covers geographical defined areas and are thus not hospital based. Total annual number of births were accessed from Statistics Norway 15 and Statistics Denmark. 16
CHD: all ICD-10 diagnosis Q20–Q26
Patent arterial duct (Q250) and patent foramen ovale (DQ211) were excluded if gestational age was<37 weeks.
Severe CHD
Severe CHD was defined as all cases of common arterial truncus (Q200), transposition of great vessels (Q203), single ventricle (Q204), atrioventricular septal defect (Q212), Tetralogy of Fallot (Q213), pulmonary valve atresia (Q220), tricuspid atresia or stenosis (Q224), Ebstein’s anomaly (Q225), hypoplastic right heart (Q226), aortic valve atresia or stenosis (Q230), hypoplastic left heart (Q234), coarctation of aorta (Q251), and total anomalous pulmonary vein return (Q262).
Calculation of prevalence rates
The total prevalence rate (TPR) was calculated as:
 $${\rm TPR}\,{\equals}\,{\rm No}.\,{\rm cases}\,\left( {{\rm LB}\:{\plus}\:{\rm FD}\:\:{\plus}\:{\rm IA}} \right)\,/\,{\rm No}.\,{\rm Births}\,\left( {{\rm live}\,{\rm and}\,{\rm still}} \right)$$
where cases are the cases of congenital anomaly in population; LB the live born; FD the fetal deaths from 20 weeks gestation; IA the induced abortion or termination of pregnancy after prenatal diagnosis, at any gestational age; Birth (live and still) the all live and stillbirths in the population as declared on official birth registrations. Please note that, for Norway, data are available in the time period from 1 January, 1999 to 31 December, 2012 and in Denmark from 1 January, 1999 to 31 December, 2014.
Statistical analysis
Change in prevalence over time was analysed with a chi-square test for heterogeneity, divided into the trend component – “χ2 test for trend” and the non-linear component – “χ2 test for non-linear change”. Changes in defined daily doses over time were analysed using linear regression. For all statistical tests, differences were considered significant at p<0.05, but in order to correct for multiple testing a post-hoc Bonferroni was performed, which gave a new critical α of 0.04; i.e. only p-values below this α were considered significant. Calculations were performed using GraphPad Prism (GraphPad Software, San Diego, California, United States of America).
Results
Prescription of cardiovascular drugs
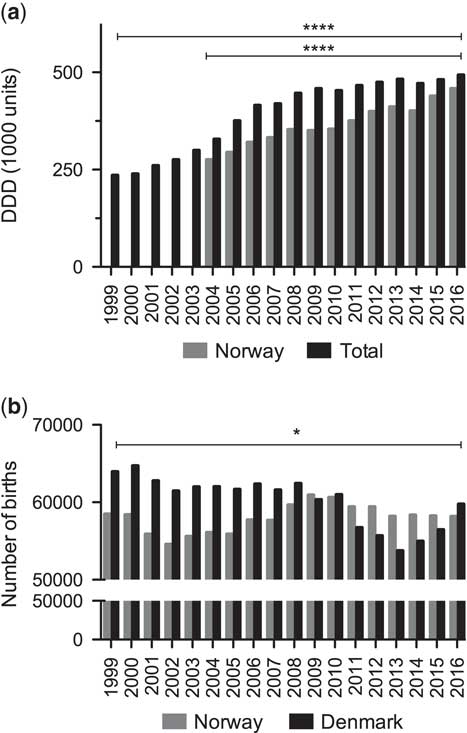
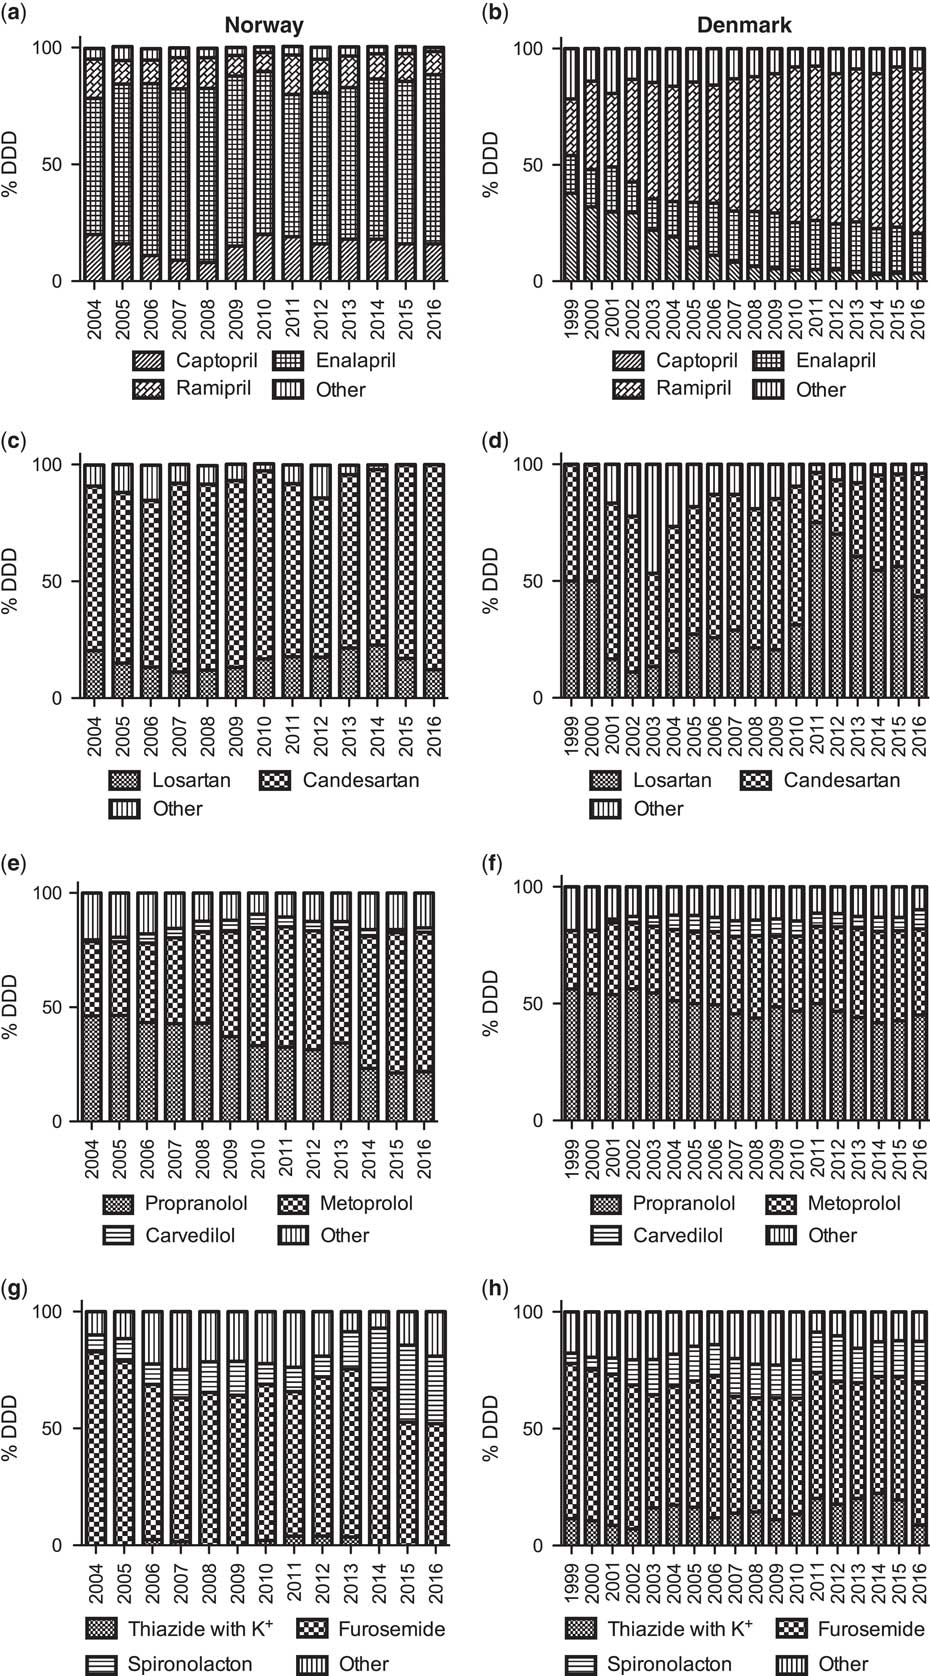
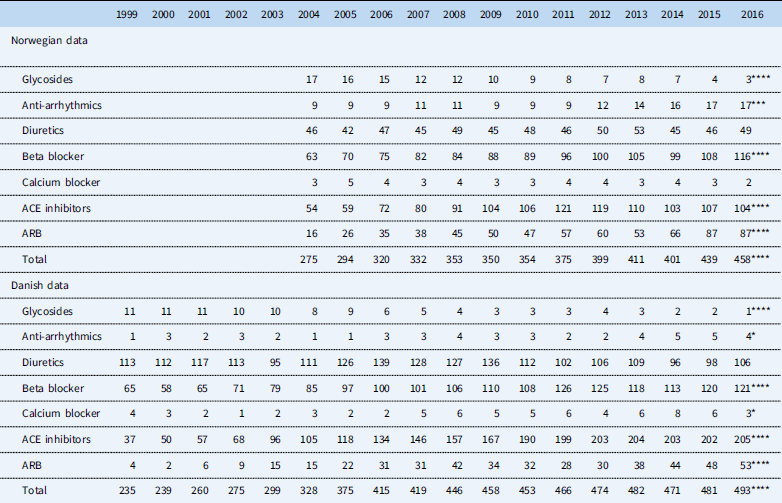
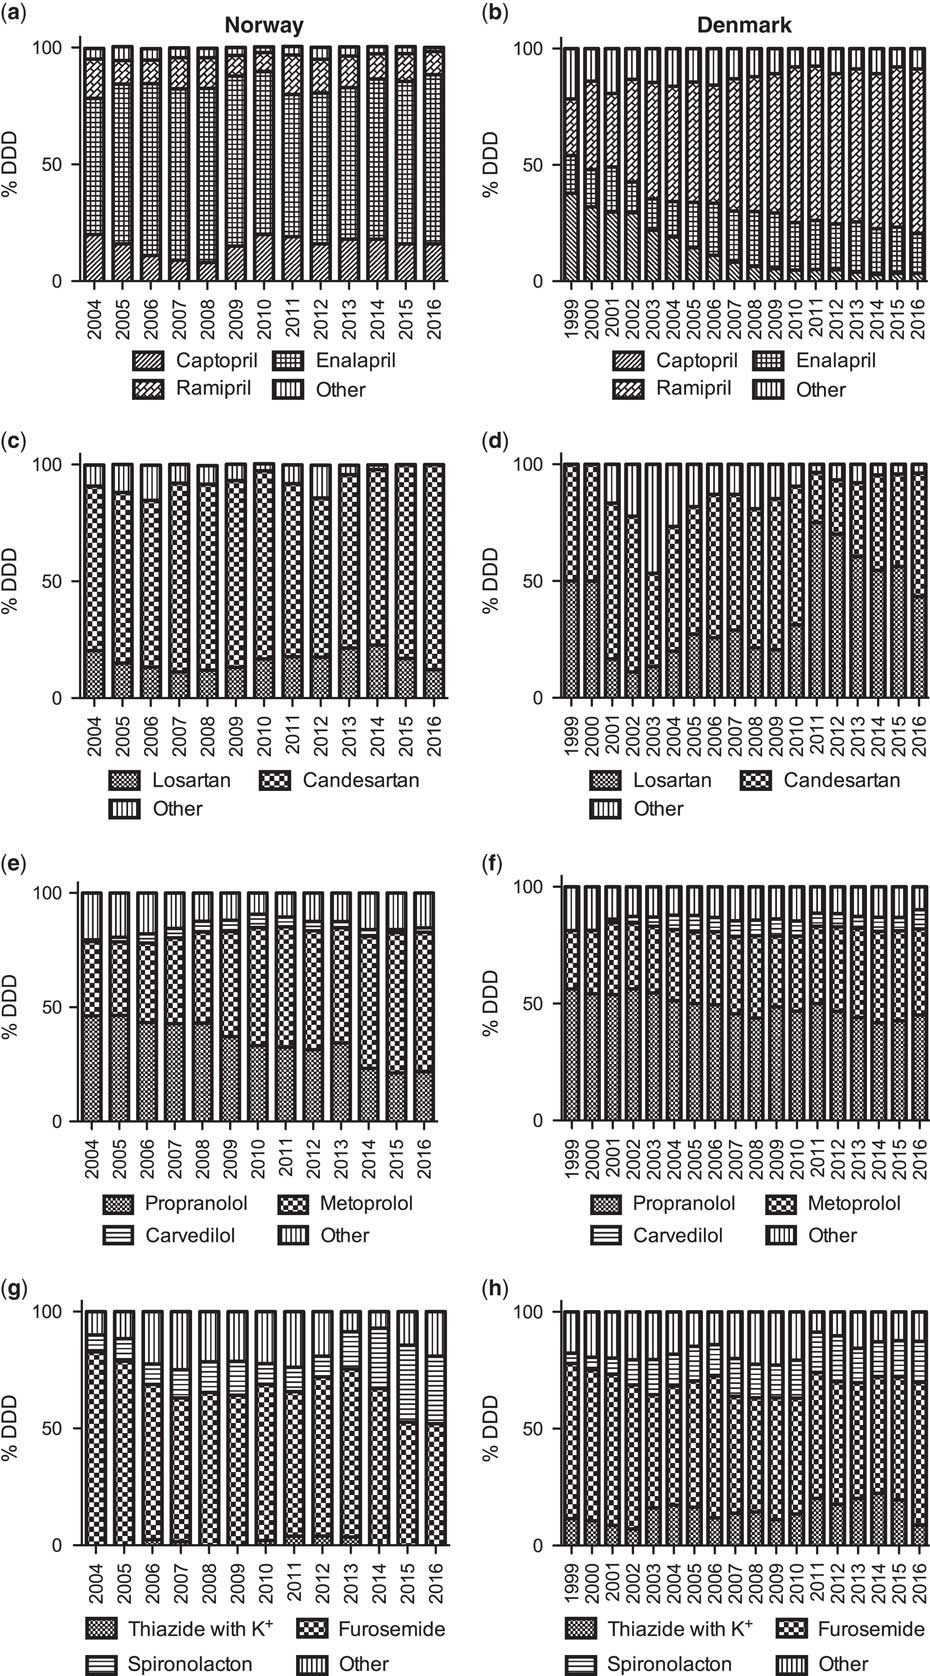
During the period, in both Norway and Denmark, the prescription of cardiovascular drugs to children and adolescents increased significantly – by 67% in Norway, that is 275–458 defined daily doses, p<0.0001, and by 110% in Denmark, that is 235–493 defined daily doses, p<0.0001, Fig 1. In both nations the trends in prescribed medication were similar. The specified prescription of drugs in both Denmark and Norway is shown in Table 1. Angiotensin-converting enzyme inhibitor therapy increased by 52% in Norway (p<0.0001) and by 454% (p<0.0001) in Denmark. Enalapril was predominantly favoured in Norway, whereas in Denmark it was ramipril (Fig 2a and b). Angiotensin II receptor blocker prescription increased by 444% (p<0.0001) in Norway and 1225% (p<0.0001) in Denmark. In Norway, candesartan accounted for more than 85% of prescriptions, whereas in Denmark prescriptions were approximately equally divided among candesartan and losartan: 44 and 53%, respectively, Fig 2c and d. Beta-blocker therapy increased by 86% (both, p<0.0001) in both countries. More than 70% of beta blockers used were either metoprolol or propranolol (Fig 2e–f). Prescription of anti-arrhythmic drugs increased by 100% (p<0.0005) in Norway and 300% (p<0.0001) in Denmark, whereas calcium-channel blockers remained constant in Norway and decreased by 33% (p=0.004) in Denmark. The only class of drugs to be reduced in both countries were cardiac glycosides – that is by 399% in Norway (p<0.0001) and by 1000% in Denmark (p<0.0001). There were no statistically significant changes in prescription of diuretics in either Norway or Denmark. In both countries, furosemide and, to a less extent, spironolactone were most often prescribed (Fig 2g–h).
(a) Yearly prescription of all cardiovascular drugs to children (ages 0–19) in daily defined doses (DDD) for both Norway and Denmark. The observed increase in total prescription is statistically significant in both countries (****p<0.0001). (b) Total annual number of births that occurred from 1999 to 2016. No significant change occurred in Norway, while the number of births decline by 6% in Denmark during the study period (*p<0.0001).

Overview of which ATC fifth level drugs were used for each pharmacological fourth level class of drugs in the study period for both Norway and Denmark. All values are in defined daily dosages (DDD). (a and b) Prescription of angiotensin-converting-enzyme inhibitors in both countries, note how enalapril was the most favoured. For Norway the category “Other” includes: lisinopril, perindopril, fosinopril, trandolapril, etc. For the Danish data the category “Other” includes: lisinopril, perindopril, quinapril, benazepin, etc. (c and d) Prescription data of angiotensin II receptor blockers, in Norway candesartan was almost exclusively prescribed whereas in Denmark both losartan and candesartan was used. For Norway the category “Other” includes: eprosartan, valsartan, irbesartan, telmisartan, etc. (e and f) Prescription of beta-blockers; propranolol (non-cardioselective β1- and β2-adrenergic blocker) and metoprolol (β1 selective blockers) were almost exclusively prescribed. For Norway the category “Other” includes: alprenolol, oxprenolol, pindolol, timolol, etc. For the Danish data the category “Other” includes: alprenolol, oxprenolol, pindolol, timolol, etc. (g and h) Diuretics prescribed in both countries. Furosemide was the most widely prescribed diuretic. Thiazide with K+ refers to bendroflumethiazide with potassium. For Norway the category “Other” includes: bendroflumethiazide, hydrochlorothiazide, trichlormethiazide, chlortalidone, etc. For the Danish data the category “Other” includes: bendroflumethiazide, hydroflumethiazide, hydrochlorothiazide, chlorothiazide, etc. For further details please see supplementary material S1.
Shown is the yearly total prescription of cardiovascular drugs to children (ages 0–19) from 1999 to 2016 in defined daily doses.

ACE=angiotensin-converting enzyme; ARB=angiotensin receptor blockers
Norwegian prescription data before 2004 are not available Statistically significant changes during the study period: *p<0.05, **p<0.005, **p<0.0005, ****p<0.0001
Live births
In Norway, the total number of live births remained stable around 58,000 in the study period. In Denmark, a slight decline occurred, from 63,943 in 1999 to 59,739 in 2016 (p<0.0001), corresponding to a 6% reduction in birth rate (Fig 1).
Prevalence of CHD
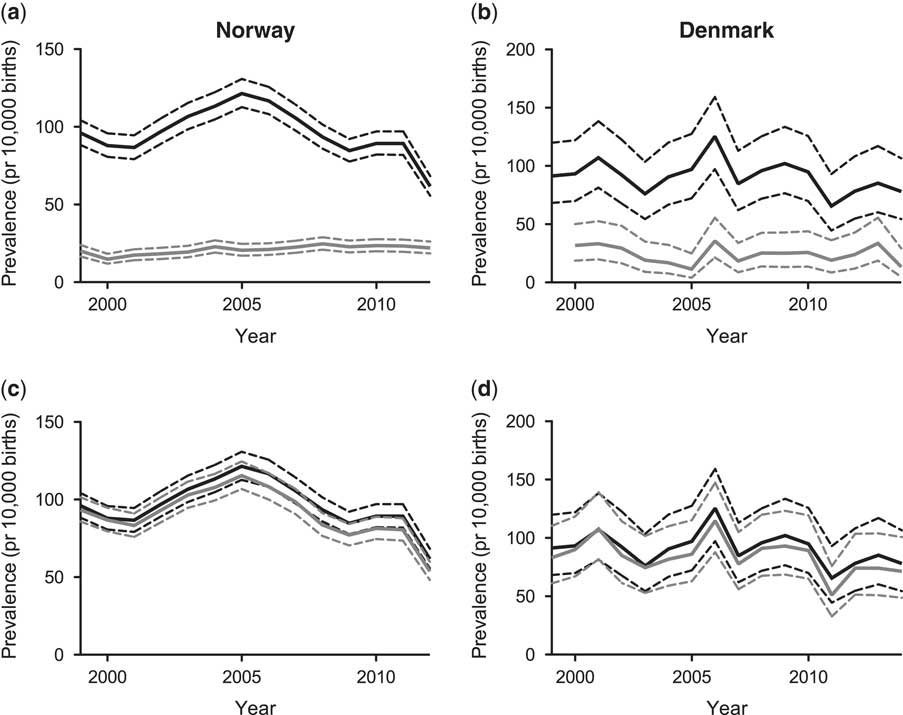
In Norway, the total prevalence of CHD was 96 per 10,000 births (95% confidence interval: 104–88) in 1999 and 62 per 10,000 births (95% confidence interval: 68–56) in 2012; these change were not statistically significant. The total prevalence in Denmark in 1999 was 120 per 10,000 births (95% confidence interval: 120–68) and 71 per 10,000 births (95% confidence interval: 101–49) in 2014. The live-birth prevalence of CHD was not notably different from the total CHD prevalence in the study period for both Norway and Denmark (Fig 3).
Total and live birth prevalence of CHD and severe CHD in both Norway (from 1 January 1999 to 31 December 2012) and Denmark (from 1 January 1999 to 31 December 2014). (a) The total prevalence (black) and prevalence of severe CHD (grey) in Norway. Although the prevalence of total CHD fluctuates, none of the observed changes over time are significant. (b) The total prevalence (black) and prevalence of severe CHD (grey) in Denmark. Due to the smaller number of births registered in the Danish registry the confidential intervals are notably wider than those from the Norwegian registry. (c) The total (black) and live birth prevalence (grey) of all CHD in Norway. Note that although the live birth prevalence is lower than the total prevalence throughout the study period there is only a marginal difference, which is not significant. (d) The total (black) and live birth prevalence (grey) of CHD in Denmark. As for Norway there is only a marginal not significant difference between these two. Dotted lines represent 95% confidence intervals.

Prevalence of severe CHD
In Norway, the prevalence was 20 per 10,000 births (95% confidence interval: 24–17) in 1999 and did not change significantly until 2012 – 22 per. 10,000 births (95% confidence interval: 26–19). In Denmark, the total prevalence in 1999 was 32 per 10,000 births (95% confidence interval: 50–19) and 9 per. 10,000 births (95% confidence interval: 23–3) in 2014; this change was not significant (Fig 3).
Discussion
From 1999 to 2016, the prescription of cardiovascular drugs to children roughly doubled, predominantly owing to increased prescription of beta blockers and angiotensin-converting-enzyme inhibitors/angiotensin II receptor blockers, whereas CHD prevalence and birth rates remained constant or declined in both countries.
Currently, there are well-established guidelines for the treatment of heart failure in adults, but no equivalent consensus for children exists.Reference Kirk 17 The most striking changes in prescription pattern in the two countries were the increased use of beta blockers and angiotensin-converting-enzyme inhibitors/angiotensin II receptor blockers. The prescription of beta blockers increased throughout the study period despite the fact that one of the few available randomized controlled trials (RCTs) on paediatric chronic heart failure (CHF) patients found that the beta-blocker carvedilol “did not significantly improve clinical heart failure outcomes in children and adolescents with symptomatic systolic heart failure”. 18 This is in contrast to the COMET trial, which suggested a survival benefit of carvedilol as compared with metoprolol in adults with chronic heart failure.Reference Poole-Wilson 19 However, there are a few caveats with regard to the study by Shaddy et al. that are worth mentioning. First, as pointed out by the authors, owing to low event rates of the composite end point, the trial may have been underpowered. Second, down-regulation of β2-receptors in children with heart failureReference Miyamoto 20 might favour β1-selective blockers, such as metoprolol and bisoprolol, compared with carvedilol, which blocks both β1- and β2-adrenergic receptors, and α1-adrenergic receptors.Reference Rupp and Jux 21 We show that the β1-selective blocker metoprolol is one of the two most frequently prescribed beta blockers, the other being the non-cardioselective β1- and β2-adrenergic propranolol. It should be emphasised that the prescription databases do not contain information regarding drug indication; it is therefore possible that propranolol was prescribed for other conditions – i.e. infantile haemangioma and so on. Although no conclusive studies have been performed, beta blockers continue to be recommended as standard therapy in children.Reference Rupp and Jux 21 The studies supporting the current guideline recommendationReference Kirk 17 of angiontension-converting-enzyme inhibitors are either observationalReference Lewis and Chabot 22 or based on RCTs performed in children with Duchenne muscle dystrophi – a condition known to cause heart failure over time owing to the absence of dystrophin.Reference Duboc 23 Thus, the standard use of angiotensin-converting enzyme inhibitors is mainly based on experience from clinical trials in adults, which are not necessarily representative for the paediatric population. In both countries, the use of glycosides decreased significantly, a decline that began before the publication of a randomised controlled trial showing no benefit of digoxin to children with chronic heart failure owing to intracardiac left-to-right shunts.Reference Elkiran 24 The use of diuretics remained constant in both nations, although this has been recommended by some authors for the management of paediatric CHF.Reference Masarone 25 A classic axiom of paediatrics is that children are not small adults,Reference Gillis and Loughlan 26 but from the above discussion it would appear that we are treating them as such with regard to chronic heart failure. The paucity of valid paediatric chronic heart failure trials essentially forces clinicians to choose between pathways: either withhold drugs for children with chronic heart failure – drugs documented beyond reasonable doubt for adults – or extrapolate data from adult chronic heart failure trials to children and treat according to these, thus violating that old axiom. Our data would seem to suggest that more clinicians are opting for the latter option.
It is interesting to note that there was no significant difference in the total and live-birth prevalence of CHD in the study, suggesting that foetal diagnosis of CHD seldom leads to termination of pregnancy in these populations. A change in CHD prevalence could therefore not in itself account for the observed changes in prescription rates likely reflecting an increased prescription per patient, rather than more patients receiving a constant amount of drugs. In both Norway and Denmark, there was a tendency towards a decline in CHD prevalence in the last year for which data are available; missing data probably cause this – that is all cases for the final year have not been reported to the database yet.
An important limitation of this study is that the databases do not allow identification of prescription on the level of the individual patient. It is therefore not possible to asses exactly which diagnosis is driving the increased use of cardiovascular drugs.
In conclusion, the prescription of cardiovascular drugs to children has doubled, particularly beta blockers and angiotensin-converting-enzyme inhibitors/angiotensin II receptor blockers, whereas CHD prevalence has remained constant, suggesting that the increased use of cardiovascular drugs reflected increased prescription per patient, rather than more patients receiving a constant amount of drugs. Further studies are needed to determine whether this affects patient morbidity and mortality.
Supplementary material
To view supplementary material for this article, please visit https://doi.org/10.1017/S1047951118000951
Acknowledgements
None.
Financial Support
This research received no specific grant from any funding agency or from commercial or not-for-profit sectors.
Conflicts of Interest
None.
Ethical standards
The study was conducted in full compliance with the Declaration of Helsinki (https://www.wma.net/wp-content/uploads/2016/11/DoH-Oct2008.pdf).