Nowadays, congenital heart diseases are regularly repaired in neonate patients. Right ventricular outflow tract can be repaired in newborns for congenital cardiac malformations and, in Ross procedureReference Ross 1 , the pulmonary valve used as autograft has to be replaced. Following the first description of a right ventricular outflow tract reconstruction with a pulmonary homograft by Ross and Somerville in 1966,Reference Ross and Somerville 2 this technique has spread, particularly after the 1980s, with the routine use of cryopreservation techniques. The increasing demand in neonates unfortunately has led to a shortage of pulmonary homograft. The lack of availability and the durability of homografts in younger patientsReference Bando, Danielson, Schaff, Mair, Julsrud and Puga 3 , Reference Tweddell, Pelech and Frommelt 4 supported the search for alternative conduits. The failure of early homografts can be observed, mainly due to early calcifications and shrinking.Reference Wells, Arroyo, Bremner, Wood and Starnes 5 For these reasons, numerous alternative valved conduits have been introduced. However, until now, substitutes are far from being considered ideal, particularly in neonates. As an alternative, Medtronic (Minneapolis, Minnesota, United States of America) introduced in 1999 the Contegra® conduit for right ventricular outflow tract reconstruction. Contegra is a bovine jugular vein conduit with a natural integrated triple-leaflet valve. The initial experience with Contegra was promising,Reference Bové, Demanet and Wauthy 6 – Reference Brown, Ruzmetov, Rodefeld, Vijay and Darragh 8 but early contradictory reports rapidly tempered the optimism.Reference Bautista-Hernandez, Kaza, Benavidez and Pigula 9 – Reference Meyns, Van Garsse and Boshoff 11 In fact, conflicting evidence exists about the performances of this conduit, particularly when considering young patients and small-sized conduits.Reference Gist, Mitchell, Jaggers, Campbell, Yu and Landeck II 12 Even if first experiences with Contegra ranked them at the level of pulmonary homograft,Reference Bové, Demanet and Wauthy 6 – Reference Brown, Ruzmetov, Rodefeld, Vijay and Darragh 8 some concerns rapidly appeared: aneurism development,Reference Bautista-Hernandez, Kaza, Benavidez and Pigula 9 supravalvular stenosis, acute thrombosis in small infants,Reference Tiete, Sachweh, Roemer, Kozlik-Feldmann, Reichart and Daebritz 13 and early conduit insufficiency notably in small diametersReference Gist, Mitchell, Jaggers, Campbell, Yu and Landeck II 12 (12–14 mm). The comparisons of pulmonary homograft and Contegra conduit are available in literature, but none investigated exclusively a heterogeneous population of newborn patients. The purpose of this study was to compare the performances of small-sized Contegra and pulmonary homograft in this challenging patient population.
Patients and methods
This study was approved by our local ethic board (reference CEH 22/16) and, due to the retrospective nature of the study, patient consent was waived. Between 1992 and 2014, all newborns who had right ventricular outflow tract reconstruction using either pulmonary homograft or Contegra conduits at the Hôpital Universitaire des Enfants Reine Fabiola were identified and considered. Pre-operative medical records were reviewed: basic demographic data, past medical history, and echocardiographic data collected before surgery. Nakata Index was calculated for each patient to assess if there was a correlation between the indexed surface area of pulmonary arteries and degradation of the conduit. We considered Nakata Index as easy to manage over the threshold of 170 mm²/m².
All patients were operated with conventional cardiopulmonary bypass and moderate (28–32°C) or profound (<28°) hypothermia if circulatory arrest was needed. Myocardial protection was assured by cold crystalline cardioplegia. Contegra or pulmonary homograft was used based on the pulmonary homograft availability in the required sized. In the Contegra group, proximal anastomosis was completed without the addition of other prosthetic material, while in the pulmonary homograft group, an autologous pericardial tanned patch with glutaraldehyde was used. Great care was always taken to place the valve as close as possible to the pulmonary bifurcation and the conduit as far as possible from the midline. Pulmonary arteriotomy was prolonged on the left pulmonary artery if needed to allow a non-restrictive distal suture. In three cases, the pulmonary homograft was undersized with bicuspidalisation technique as described previously.Reference Bové, Demanet and Wauthy 6 Conduit size was expressed as the operative final measured diameter after bicuspidalisation if realised. Cryopreserved valved conduits were obtained from the European Homograft Bank in Brussels, Belgium. In the Contegra group, a protocol of glutaraldehyde washing-out was applied respecting manufacturer’s guidelines. In the pulmonary homograft group, the conduits were thawed out and antibiotic-rinsed according to the European Homograft Bank guidelines. Operative, post-operative, and follow-up data were considered. All Contegra patients received low-molecular-weight heparin under the skin during 2 months after the operation, while pulmonary homograft patients received antiplatelet alone. Our actual protocol was to provide an antiXa activity of 0.2–0.4 UI/ml.
z-Score was considered to assess mismatch between conduit size and ideal pulmonary valve size. The patient’s normal expected pulmonary valve size was compared to the implanted valve size. The z-value for the conduit size was then determined.Reference Zilberman, Khoury and Kimball 14 z-Score was considered ideal between +1 and +3.Reference Fiore, Ruzmetov and Huynh 15 , Reference Sierra, Christenson, Lahlaidi, Beghetti and Kalangos 16 When z-score was higher than +3, we considered the conduit excessively oversized.
Morbidity included the incidence of delayed chest closure, the occurrence of atrioventricular block, a low post-operative cardiac output needing prolonged (>72 hours) inotropic support, and extracorporeal membrane oxygenation requirement. Early function of conduits was evaluated by transthoracic 2D echocardiogram during post-operative hospitalisation. Regurgitation was considered severe when graded 3/4 to 4/4. Gradient trough of the conduit was considered significant if it was >15 mmHg and moderate if <15 mmHg. The localisation of gradient was considered either proximal or on the distal anastomosis.
Late echocardiographic assessment was obtained for all patients: we considered the last echo before re-operation if a re-operation was needed and the last echo of follow-up if patients didn’t require re-operation at the time of this study at complete follow-up. In late echo we adopted the same criteria for insufficiency, but gradient was considered significant if >50 mmHg, moderate if between 50 and 15 mmHg, and negligible if <15 mmHg. Conduit failure was defined as the need to be replaced. Early re-operation was defined as the need for replacement during the first 24 months of follow-up. Indications for replacement were severe stenosis or regurgitation associated with degradation in functional status, right ventricular enlargement, or arrhythmias. Transcatheter valve replacement was considered as conduit replacement. Catheter intervention on pulmonary artery branches for narrowing not involving distal anastomosis was not considered as conduit failure.
Statistical analysis
Patients’ follow-up data were collected retrospectively, verified and encoded in a database. Computed statistical analysis was performed using SPSS software (SPSS Inc., version 22.0). Continuous variables were expressed as means ± standard deviation if the variable was Gaussian, or as median (interquartile space) if the variable was not Gaussian. The normality of variables was verified with the Wilk-Shapiro test. Discrete variables were expressed as percentage or total number. For continuous variables, t-test was used to compare the two groups if the variable was Gaussian. Non-Gaussian variables were compared with Wilcoxon–Mann–Whitney test. Discrete variables were compared with chi-square test or Fischer exact test. Freedom from event (death or reintervention) was calculated using Kaplan-Meier curves. Inter-group comparisons were conducted using the log-rank test. When appropriate, multivariable analysis (logistic regression) was performed.
Results
Patients’ characteristics
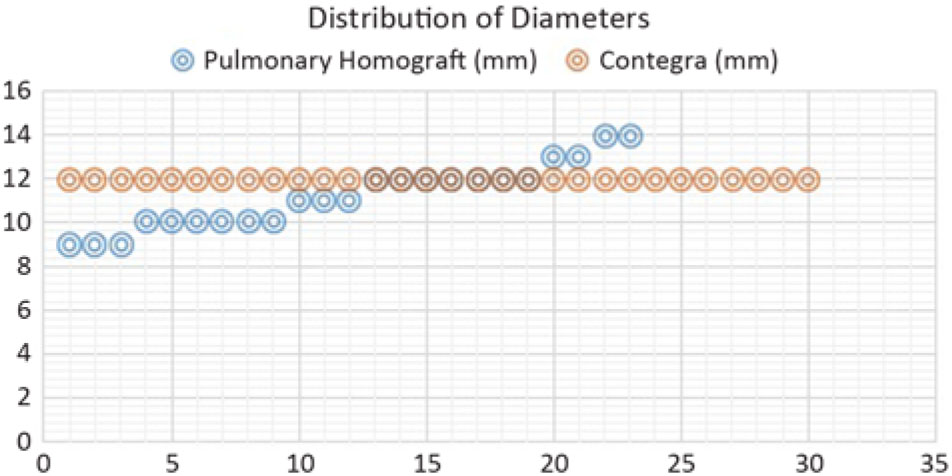
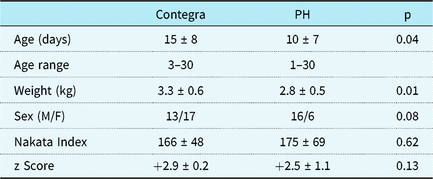
There were 53 right ventricular outflow tract reconstructions in newborns in our institution during the considered period; 30 received a Contegra conduit and 23 a pulmonary homograft, depending on homograft availability. In this study, only Contegra 12 mm and 9–14 mm pulmonary homograft were used. There were fewer pulmonary homografts in the recent years and more Contegra because of shortage of small-sized pulmonary homograft stock. Demographic data are summarised in Table 1. There were 14 (47%) and 9 (39%) patients, respectively, for Contegra and pulmonary homograft groups presenting a low Nakata Index (<170 mm²/m2; p = 0.30). Excessively oversized conduit (z-score up to 3) was observed in 11 (37%) Contegra patients and in 10 (43%) pulmonary homograft patients. Comparing pulmonary homograft diameter with that of Contegra, there was a significant difference between the two groups (Fig 1; p = 0.01), but it is important to mention that there was no difference in z-score between the two groups, and in our study there was no correlation between diameter and conduit survival.
Distribution of diameters.

Demographics

F = female; M = male; PH = pulmonary homograft.
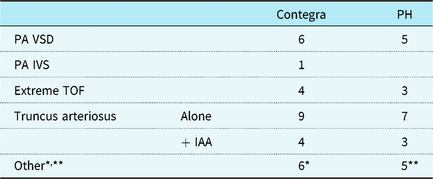
Indications for right ventricular outflow tract reconstruction in these patients are listed in Table 2. No patient has had previous cardiac surgery. Other indications included six patients in the Contegra group (one right ventricular outflow tract replacement for absent pulmonary valve and five Ross procedures), and five patients in the pulmonary homograft group (one right ventricular outflow tract replacement for absent pulmonary valve, one Ross procedure, and three Rastelli procedures). Seven patients required circulatory arrest during surgery to repair an interrupted aortic arch (three Contegra and two pulmonary homograft patients).
Indications for reconstruction

IAA = interrupted aortic arch; IVS = intact ventricular septum; PA = pulmonary atresia; PH = pulmonary homograft; TOF = tetralogy of Fallot; VSD = ventricular septal defect
* One right ventricular outflow tract replacement for absent pulmonary valve and five Ross procedures.
** One right ventricular outflow tract replacement for absent pulmonary valve, one Ross procedure, and three Rastelli procedures.
In-hospital outcome
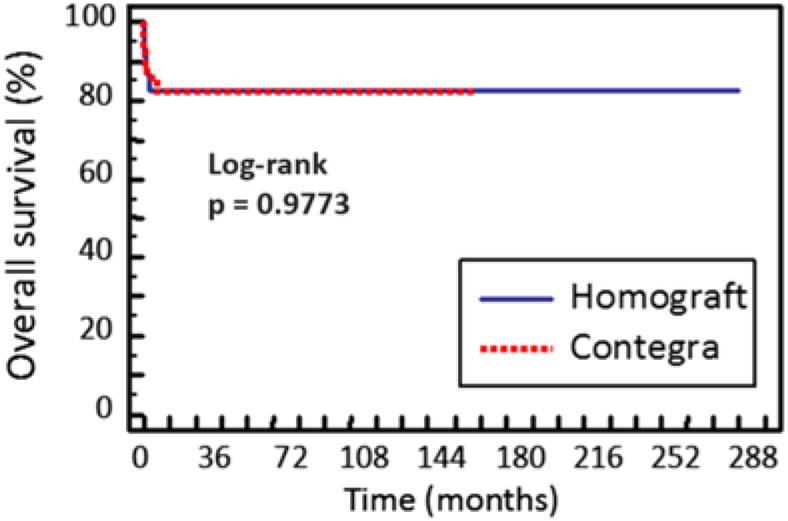
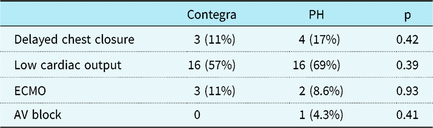
Overall mortality in this series was 16.6% in Contegra versus 17.4% in pulmonary homograft group (p = 0.98 log-rank) (Fig 2). All the deaths were observed during post-operative hospitalisation (within 6 months after intervention). Morbidity indices, early, and late outcomes of the conduits are listed in Table 3 and are comparable between the two groups. Echocardiographic assessment was carried out during the early post-operative period and late follow-up. Some degree of regurgitation was observed in 19 (63%) and 17 cases (73%), respectively, in Contegra and pulmonary homograft groups (p = 0.83).
Actuarial Kaplan–Meier curve for the overall survival of pulmonary homograft (continuous blue line) compared with Contegra (interrupted red line).

Perioperative complications

AV = atrioventricular; ECMO = extracorporeal membrane oxygenation; PH = pulmonary homograft.
Follow-up
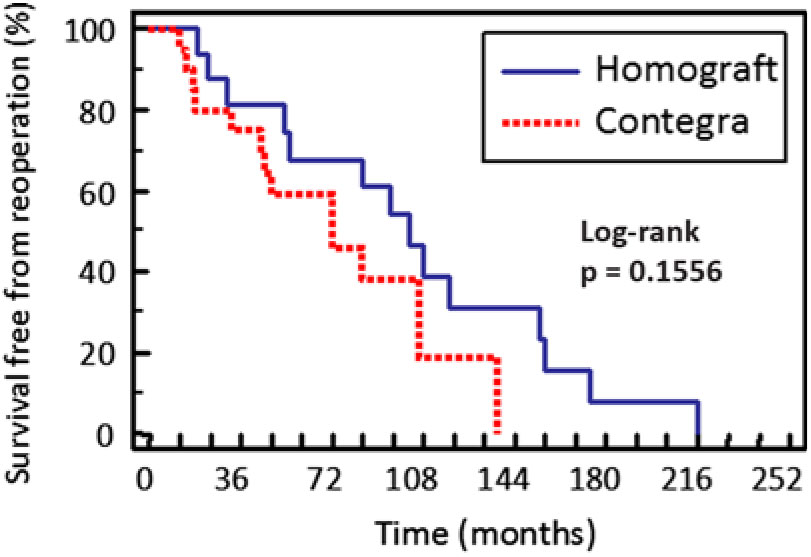
Mean follow-up for this study was 121 ± 74 months. There were no deaths after discharge. Two patients in the Contegra group were lost to follow-up, and the remaining 51 patients have a complete follow-up to date. Two patients in Contegra and none in pulmonary homograft groups needed pulmonary artery branch stenting post-operatively. Survival free from re-operation is illustrated as a Kaplan-Meier curve in Figure 3 and shows that there was no statistically significant difference between the two groups (p = 0.15 log-rank). Within the first 24 months after the initial surgery, we observed early conduit failure leading to early re-operation in four (13%) Contegra patients and in three (14%) pulmonary homograft patients (p = 0.68). The presence of severe early regurgitation was not associated (p = 0.66) with the need of an early re-operation (during the first 24 months of follow-up). The presence of a severe early gradient did not increase the rate of early re-operations (during the first 24 months of follow-up). Contradictorily, multivariable analysis showed a significant association between the presence of an early severe gradient and survival free from re-operation in this series (p = 0.02).
Actuarial Kaplan–Meier curve for survival free from re-operation of pulmonary homograft (blue line) compared with Contegra (red line).

Reasons for failure in the Contegra group were two distal stenoses (14 and 17 months post-operatively), one proximal stenoses (18 months postoperatively), and one pulmonary artery bifurcation stenoses with Contegra regurgitation (12 months postoperatively). In Contegra group the presence of an early conduit dysfunction in terms of severe gradient was associated with an earlier conduit failure compared with the pulmonary homograft group (p = 0.02). We observed three cases of Contegra valve thrombosis and none in the pulmonary homograft group (p = 0.11) without the need for early re-operation (and no case of proximal dilatation).
In the pulmonary homograft group, one patient needed re-operation at 2 months for early dilatation and two patients for early calcification and shrinking (19 months and 23 months postoperatively, respectively). In the pulmonary homograft group, 22%, versus 0% of Contegra patients, needing re-operation had severe regurgitation as principal conduit failure criteria.
Considering patients with persistent pulmonary arterial hypertension, there was no significant reduction in freedom from re-operation time in this subgroup of patients (p = 0.17), and low Nakata Index was not associated with increased probability of early (p = 0.72) or late (p = 0.66) re-operation. We did not find any association between excessive oversizing and early (p = 0.82) or late (p = 0.91) conduit failure.
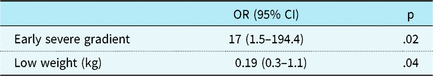
In our study, multivariable analysis showed only weight and early severe gradient as factors strongly associated with anticipated conduit failure (Table 4).
Multivariable analysis

CI = confidence interval; OR = odds ratio.
Discussion
In newborns, the Ross procedureReference Ross 1 and congenital heart diseases affecting the right ventricular outflow tract are the main indications for pulmonary homograft or artificial conduit implantation. Most surgeons consider that pulmonary homograft is the first choice in this indication. Unfortunately, increasing demand and reduced availability secondary to left ventricular hypoplasia treatment may lead to homograft shortage for newborns. Other surgeons think that pulmonary homograft has shown some weaknesses, particularly in infants. Different modes of degradations may be observed in pulmonary homograft as well as early calcification, shrinking, degeneration, and late incompetency secondary to valve destruction.Reference Bando, Danielson, Schaff, Mair, Julsrud and Puga 3 – Reference Wells, Arroyo, Bremner, Wood and Starnes 5 The risk factors for homograft failure include smaller homograft diameter, younger age of the patient, as well as low weight.Reference Tweddell, Pelech and Frommelt 4 , Reference Wells, Arroyo, Bremner, Wood and Starnes 5 The hypothesis for chronic degradation is that cryopreservation does not eliminate antigenic expression in pulmonary homograft, resulting in humoral and cell-mediated response with a significant impact on graft function and durability,Reference Shaddy, Hunter and Osborn 17 – Reference Hoekstra, Wityliet and Knoop 20 particularly if pulmonary homografts are not ABO-matched.Reference Baskett, Nanton, Warren and Ross 21 In our country, pulmonary homografts are never ABO-matched.
Nowadays, the data on Contegra outcomes are consistent, including comparisons with blood-compatible pulmonary homografts. Some data suggest that Contegra has similar performances as homografts in children <5 years.Reference Sierra, Christenson, Lahlaidi, Beghetti and Kalangos 16 , Reference Christenson, Sierra, Colina Manzano, Jolou, Beghetti and Kalangos 22
Technical considerations may influence the surgeons’ preference. Pulmonary homograft implantation requires prosthetic or pericardial patches to connect the valved conduit to the right ventricle. All these factors lead us to consider homografts as imperfect substitutes in neonates. As an alternative to homografts, Contegra was introduced in 1999 for right ventricular outflow tract reconstructions. We have been using unsupported Contegra conduits since they were made available in our country. Contegra is a bovine jugular vein conduit with a naturally integrated triple-leaflet valve. It has the advantage of shelf availability in different diameter sizes from 12 to 22 mm. It is usually treated with glutaraldehyde, thus considerably reducing the antigenic load and reaction.Reference Fiore, Brown and Turrentine 23 Contegra are also easy to handleReference Boethig, Thies, Hecker and Breymann 24 after protocoled elimination of the glutaraldehyde remnant. Technically, there is no need for additional prosthetic material to complete the proximal anastomosis. We made several improvements to the management of these conduits. Contegra’s ducts are treated with glutaraldehyde and therefore no longer contain living cells. They must first be colonised by endothelial cells. Based on published research,Reference Goh, Wong, Farhatnia, Tan and Seifalian 25 we tried to promote endothelialisation of the conduit. We aimed to reduce thrombogenesis (potential cause of acute thrombosis) and intimal hyperplasia that may lead to intravascular peal formation. Endothelial progenitor cells arising from the blood may adhere to the intravascular surface of the conduit and grow and differentiate into mature endothelial cells.Reference Goh, Wong, Farhatnia, Tan and Seifalian 25 During the window period between implantation and presence of a fully operational endothelium, anticoagulation may prevent acute thrombosis and promote endothelialisation.Reference Goh, Wong, Farhatnia, Tan and Seifalian 25 Firstly, all the patients are anticoagulated for 2 months after Contegra implantation. Secondly, we realise rigorous everting vascular sutures when using Contegra to avoid exposure of the external structure of the conduit with intravascular compartment that could lead to the classical distal stenosis observed in Contegra.Reference Meyns, Van Garsse and Boshoff 11 These precautions may explain the lower incidence of distal stenosis on the suture line secondary to peal-growing and acute conduit thrombosis. However, despite our policy of anticoagulation, we observed three cases of early Contegra cusp thrombosis without the need for early re-operation but none in the pulmonary homograft group (p = 0.11). When thrombosis occurred it was always the cause of some degree of regurgitation because of cusp localisation. Despite this, no significative hemodynamic change occurred and thrombosis was ruled out on routine post-operative ultrasounds. It has to be noted that in one of these cases, anticoagulation therapy was prematurely discontinued. An improved use of this conduit has led to apparent favourable late outcome.Reference Sierra, Christenson, Lahlaidi, Beghetti and Kalangos 16 , Reference Fiore, Brown and Turrentine 23 , Reference Boethig, Thies, Hecker and Breymann 24 , Reference Rastan, Walther and Daehnert 26 , Reference Breymann, Blanz and Wojtalik 27 However, questions remain. The risk factors for adverse events are young age (<1 year), small conduit size, small pulmonary arteries, inadequate glutaraldehyde removal, kinking of excessive conduit length, distortion by the ascending aorta from rightward implantation on the pulmonary artery, and improper suturing leading to anastomotic stenosis.Reference Fiore, Brown and Turrentine 23 , Reference Rastan, Walther and Daehnert 26 Besides these, studiesReference Gist, Mitchell, Jaggers, Campbell, Yu and Landeck II 12 , Reference Fiore, Brown and Turrentine 23 , Reference Rastan, Walther and Daehnert 26 have observed a high incidence of severe Contegra insufficiency especially in younger patients, smaller conduits (12–14 mm), truncus arteriosus, pulmonary artery branch obstruction, and elevated pulmonary vascular resistance. For all these reasons, caution is required concerning long-term evolution of small conduits and younger patients.Reference Fiore, Brown and Turrentine 23 A relevant comparison of different conduits is difficult due to a limited number of patients, wide range of patients’ ages and body weights, different congenital heart defects considered, and heterogeneity in the homograft considered (pulmonary versus aortic).
Experiences with small conduits have been reported, comparing Contegra 12–14 mm with homografts in the pulmonary position.Reference Sinzobahamvya, Asfour and Boscheinen 28 The durability of both conduits seems to be similar after a mean follow-up of 22 months, but homografts in this series included pulmonary and aortic homografts. The last ones have been previously reported as a risk factor for early degenerationReference Boethig, Goerler and Westhoff-Bleck 29 and may negatively influence the prognosis of homografts in this report. Moreover, the mean age at implantation was 198 days for the Contegra group and 89 days for the pulmonary homograft group, far from the neonate context. Fiore et al. compared pulmonary homografts (10–15 mm) with Contegra (12–14 mm) in children under the age of 2 years and showed superior performances at 5 and 10 years with Contegra. Nevertheless, low weight is an independent risk factor when considering survival free from re-operation either for Contegra or pulmonary homograft. One study noted that allografts of diameters <15 mm exhibited no advantage over xenografts.Reference Boethig, Goerler and Westhoff-Bleck 29
Because of the existence of such conflicting evidence regarding Contegra, we focused our study on newborns only.
In 2008, Hickey et al.Reference Hickey, McCrindle and Blackstone 30 compared the fate of Contegra and allografts in the repair of truncus arteriosus in newborns. Interestingly, they found that even if Contegra 12 mm has been the only diameter small enough for newborns, it consistently matched the ideal z-score (between +1 and +3). In our experience, regurgitation tended to progress more rapidly in homografts, and the Contegra valve seemed to keep a better competence in late echo follow-up than pulmonary homograft valve. This was also observed by Hickey and colleagues. The conclusion of their paper was that truncus arteriosus repair could be achieved with Contegra and homografts with comparable results. They suggested that it could be the same for other indications. We found similar performances in our series, which is the first one to compare the outcomes of these conduits focusing only on newborns with heterogeneous indications.
In our experience we observed no significant differences in overall survival and in survival free from re-operation when Contegra was used for right ventricular outflow tract reconstruction compared with pulmonary homograft (Fig 1). Early severe gradient was associated with anticipated conduit failure in the two groups. Moreover, in the Contegra group the presence of an early conduit dysfunction in terms of severe gradient was associated with an earlier conduit failure compared with the pulmonary homograft group. Instead, early dysfunction in terms of regurgitation did not correlate with an early (within the first 24 months after implantation) conduit failure. Late echography showed regurgitation in 17 (60%) bovine jugular vein conduit and 19 (82%) pulmonary homograft patients, respectively (p = 0.07), and severe regurgitation in four (14%) versus nine (39%) patients, respectively (p = 0.06). Regurgitation was the main criterion for replacement in 22% of pulmonary homograft patients versus none in the Contegra group. Nonetheless, another neonatal experience reported by Sinzobahamvya et al. compared homografts (pulmonary and aortic) and Contegra in the setting of truncus arteriosus repair.Reference Sinzobahamvya, Boscheinen and Blaschczok 31 They observed a higher durability of the homografts (most favourable graft being aortic homograft) compared with Contegra. These different results may be partially explained by the small number of Contegra (n = 8) and the utilisation of aortic homografts (n = 14) in the Sinzobahamvya et al. report. Also, we considered a heterogeneous population compared to this report even if there was a considerable number of truncus arteriosus (46.4% of Contegra and 43.5% of pulmonary homograft indications, respectively). Rastan et al. observed that elevated right ventricular pressure is a risk factor for re-operations.Reference Rastan, Walther and Daehnert 26 In our series, in one patient we needed to replace a 9-mm pulmonary homograft 2 months post-operatively because of proximal dilatation probably linked to excessive right ventricular pressure (pulmonary hypertension or residual ventricular septal defects). Our population presented a mean Nakata Index of 170 ± 58 mm²/m² and the same range in both groups. We considered a comfortable situation when Nakata Index was ≥170, and we observed no association between low Nakata Index (<170 mm²/m²) and anticipated conduit failure in the two groups. It is important to mention that stenting and balloon angioplasty was performed to treat pulmonary artery branch stenoses in two cases in the Contegra group; nevertheless, no difference could be demonstrated between the two groups.
We may assume that the durability of small conduits could be considered a less critical issue when implanted in very young patients because they will overgrow their conduit before degeneration occurs. This consideration is subject to debate,Reference Wells, Arroyo, Bremner, Wood and Starnes 5 but frequently oversizing is applied to postpone mismatch. Excellent results of Contegra conduits were reported with moderate oversize (z-score approximately 2).Reference Fiore, Ruzmetov and Huynh 15 , Reference Sierra, Christenson, Lahlaidi, Beghetti and Kalangos 16 We applied the same policy in neonates, but with regard to their low weight and available sizes of Contegra and pulmonary homograft, the final observed z-score was generally between 2 and 3. In our series this excessive oversizing was not associated with an earlier conduit dysfunction or failure in these patients compared with the ideal z-score group, and also other authors considered an ideal z-score between 1 and 3.Reference Hickey, McCrindle and Blackstone 30
Recent reports state that Contegra is associated with a considerable increase in late endocarditis.Reference Ugaki, Rutledge, Al Aklabi, Ross, Adatia and Rebekya 32 , Reference Mery, Guzmán-Pruneda and De León 33 Even if conduit susceptibility to infection has been advocated, it has to be noted that other factors could play a role, such as longer durability and widespread use of these conduits, thrombus formation in patients with distal obstruction, and valve degeneration.Reference Bahaaldin 34 Moreover, these are more and more used in smaller children who are more susceptible to delayed chest closure, longer hospitalisation, longer invasive monitoring,Reference Bahaaldin 34 and possibly larger use of extracorporeal membrane oxygenation for low cardiac output. We previously reported a rare Q-fever endocarditis on Contegra, but we observed no endocarditis in this series with newborns.
Conclusions
The performances of Contegra 12 mm and small-sized pulmonary homografts in newborns are quite comparable in terms of early failure, morbidity, and durability. Between 5 and 10 years after implantation, a great majority of these conduits have to be replaced without significant differences in survival free from re-operation between the two groups. Although this is a small-sample retrospective study, it is the first focusing only on “all-comers” newborns. We consider Contegra a valuable alternative to pulmonary homograft in newborns.
Acknowledgements
None.
Financial Support
This research received no specific grant from any funding agency, commercial or not-for-profit sectors.
Conflicts of Interest
None.
Ethical Standards
The authors assert that all procedures contributing to this work complied with the ethical standards of the relevant national guidelines on human experimentation (Belgium) and with the Helsinki Declaration of 1975, as revised in 2008, and has been approved by the institutional committees (Comité d’Ethique de l’Hôpital Universitaire des Enfants Reine Fabiola, Brussels, Belgium; reference CEH 22/16).