Introduction
Carcinoma of gallbladder is a rare malignancy in the United StatesReference Jemal, Siegel, Xu and Ward1 and does not feature in the top ten leading cancer sites; however, the incidence varies worldwide, with high incidence reported in Indian, Japanese, Korean and South American populations.Reference Randi, Franceschi and La Vecchia2–4 In India, this malignancy features in the top five cancer sites as per data collected from population-based cancer registries.5 Complete surgical resection is the most effective treatment wherever possible, with patients undergoing microscopically complete resection having the best outcome, although only 5–35% patients are diagnosed at an operable stage.Reference Mahe, Stampfli, Romestaing, Salerno and Gerard6 Survival ranges from 33% to 100% for Stage 0–1 to as low as 5% for the higher stages.Reference Kresl, Schild and Henning7–Reference Arnaud, Casa and Georgeac15 Chemo-irradiation with 5-fluro-uracil-based regimens has been used in adjuvant setting to improve local control. The results from published reports are not conclusive but show a trend towards better survival in the subset of patients who undergo adjuvant chemo-irradiation after complete resection.Reference Kresl, Schild and Henning7, Reference Houry, Schlienger, Huguier, Lacaine, Penne and Laugier16–Reference Kim, Kim, Bang, Heo and Ha23 Delivering radiation therapy to the intended target for this disease is always challenging, with dose-limiting critical structures around the treatment volumesReference Halperin, Perez and Brady24 like rest of the liver, kidneys and bowel. The target volume for radiation therapy includes tumour bed and regional lymph nodes (porta -hepatis, coeliac and pancreaticoduodenal groups).Reference Kresl, Schild and Henning7, Reference Czito, Hurwitz, Clough, Tyler, Morse and Clary25 The desirable dose is 45–54 Gy in 25–30 fractions to the target volume. Recently, intensity-modulated radiation therapy (IMRT) has been used as a tool to achieve conformal dose distributions while respecting normal tissue tolerances for abdominal malignancies.Reference Wieland, Dobler and Mai26–Reference Ben-Josef, Shields and Vaishampayan29 Image-guided radiation therapy (IGRT) enhances the utility of IMRT through accurate beam placement verification and hence allows assessment of the target on a regular basis in actual treatment position, allowing for correction of day-to-day positional variations and therefore reducing the daily set-up errors. Using IGRT therefore is valuable in reducing planning target volume (PTV) margins.Reference Fuller, Thomas and Wong27, Reference Fuss, Salter and Cavanaugh30 Recently, a few reports have discussed the process of IGRT for upper abdominal malignancies. They have described the use and accuracy of the modalities of ultrasound, cone-beam computerised tomography (CBCT) and kilovoltage beam portals (kVps).Reference Fuller, Thomas and Wong27, Reference Fuss, Salter and Cavanaugh30–Reference Perkins, Fox, Elder, Kooby, Staley and Landry32 We undertook a study of set-up variations/shifts in three patients treated with IMRT using kilovoltage CBCT and paired kVps, and 32 off-line reviews were analysed for margins because of set-up errors.
Materials and methods
For our study, we retrospectively analysed three consecutive patients with carcinoma of gallbladder who underwent post-operative adjuvant chemo-irradiation at our department by IGRT on Clinac iX (Varian Medical Systems Inc., Palo Alto, CA, USA) after microscopically complete surgery. Only those patients who were immobilised in the following manner were included in this study. All patients were placed in the supine position using all-in-one solution (The AIO Solution®; Orfit Industries, Wijnegem, Belgium). An all-in-one board with a blue cushion set with extension and armrest as suited to the patient were used. Along with the above, either a knee rest or a vaccusion was used, both of which were duly indexed to the all-in-one board and cushion. The vaccusion was made only for lower limbs, starting just above the knee and below up to the ankles. The head was rested on the head rest for adequate comfort. Over this, a four-clamp thermoplastic orfit cast (Orfit Industries) was used. Half an hour before their planning computed tomographic (CT) scan, the patients were told to consume 200 ml of water. This was done to improve the visibility of the duodenum. Planning CT scans were acquired in the spiral mode at an interval of 3 mm with intravenous non-ionic contrast. Planning was done using Eclipse planning system (Varian Medical Systems Inc). The clinical target volume included the tumour bed and regional lymph nodes (porta hepatis, coeliac and pancreaticoduodenal lymph nodes). An extra margin of 1·5 cm in the longitudinal direction and 1 cm in the lateral and vertical directions were given to account for daily set-up errors. All patients were planned with IMRT. The dose prescribed was 45 Gy in 1·8 Gy fractions. Set-up verification of position was done using regular CBCTs and kVps. On an average, each patient underwent two imaging studies with CBCT or kVps every week. All these images were reviewed off-line retrospectively, and matching was done according to bony landmarks and surrogates as discussed below to determine set-up errors for each of these sessions All the shifts were tabulated in each direction for all 32 sessions, and the mean shifts (m) and standard deviation (SD) were calculated. The mean shift in each direction for each patient was calculated separately. The mean of these means (M) was calculated to arrive at the systematic error in each direction and its standard deviation (Σ) was calculated. The root means square (RMS) (σ) of standard deviation (SD) was calculated for each direction to arrive at the group mean of standard deviations.Reference Van Herk33 The PTV margins were calculated using the formula proposed by Stroom et al.Reference Van Herk33, Reference Stroom, de Boer, Huizenga and Visser34 as two times the total of SD of systemic errors plus 0·7 times the total SD of random errors to ensure that on an average 99% of the target volume receives 95% of the prescribed dose or more.
Method used to perform matching in CBCT scans (use of surrogates)
The Offline Review tool (Varian Medical Systems Inc.) was used to record all errors after matching or co-registration of CBCT or kVps with planning CT scans and digitally reconstructed radiographs, respectively. The process of matching the CBCT images with planning CT scans was done in the following manner: the images acquired during CBCT and the images available from the planning CT scan were first matched using automatic matching tool. The manual matching process was then started. The first correction was attempted in the longitudinal (craniocaudal) direction. The head of the 12th rib and the coeliac trunk were used as surrogates for correction in longitudinal direction. The head of the 12th rib was matched to begin with. The head of the 12th rib can be easily localised by scrolling down on planning CT images and stopping at the point where no more ribs are sprouting out of the vertebrae; similar scrolling can be done on CBCT images and the 12th rib is visually examined to be in the same slice (hence longitudinally correct) (Figure 1). Matching and co-registration in the lateral and vertical directions was also done in the same section. After this, the coeliac trunk was located, first on the planning CT scan and then on CBCT scan, and matched (Figure 2). After the above step, the images were scrolled throughout to appreciate any lateral and vertical shifts. The corrections were done as felt using mainly vertebral bodies as surrogates and rechecked in all sections with a quick scroll for overall correctness. The kVps were matched manually using bony landmarks. Again, first, longitudinal correction was done (in the craniocaudal direction) and then lateral and vertical corrections. Adequate windowing was used during matching as it was realised that both anteroposterior and lateral films require separate window level settings for proper evaluation.
A screen shot from an off-line match® showing the head of the 12th rib (arrowhead) being matched in a cone-beam computed tomography (CBCT) image. Note that the image acquired using CBCT is grainy.

A screen shot from an off-line match®. Note that the coeliac trunk is easily seen in the cone-beam computed tomography scan image once seen on a planning computerised tomography image.

Results
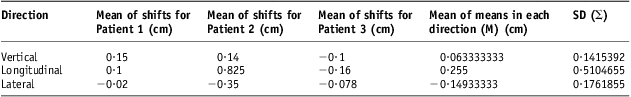
All the shifts were tabulated in each direction for all 32 sessions. There were a total of 32 readings of which 21 were CBCTs and 11 were kVps. The mean shifts in each direction for each patient were calculated separately. The mean of these means (M) was calculated to arrive at the systematic error in each direction, and its standard deviation (Σ) was calculated in Table 1. The mean shift (M) in the vertical direction was 0·06 cm, in the longitudinal direction was 0·25 cm and in the lateral direction was −0·14 cm. The associated standard deviation was calculated (Σ) (Table 1). Using the above calculations, the resultant PTV margins were calculated in each direction as given in Table 2.
Table shows the mean of random daily shifts for each patient
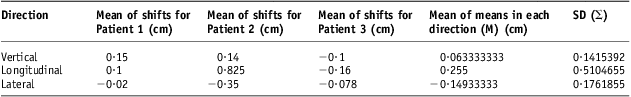
Notes: The mean of these means is calculated to obtain the group systematic mean (M). The SD is calculated for the purpose of obtaining PTV margins.
Abbreviations: SD, standard deviation; PTV, planning target volume.
Calculated PTV margins in each direction using formula by Stroom et al.

Abbreviation: PTV, planning target volume.
Discussion
Decreasing margins of set-up errors complements practice of modern radiation oncology techniques such as 3DCRT and IMRT. This is due to the fact that the target coverage and conformity are improving with the use of these conformal techniques, and therefore by decreasing margins there is a possibility of improving tolerance because of a consequent decrease of side effects of radiation therapy.Reference Halperin, Perez and Brady35 Concurrent chemo-irradiation is the standard of care in post-operative adjuvant setting for upper abdominal malignancies,36, 37 and therefore improving tolerance to radiation therapy becomes important. The reported incidence of toxicities is to the tune of 30–50%;Reference Gold, Miller and Haddock38 this is likely to worsen with concurrent chemotherapy, and hence any decrease in margins is of value in decreasing morbidity. The survival rates associated with upper abdominal malignancies are improving;37, Reference Czito, Anscher and Willett39 therefore, tolerance to therapy and long-term effects are becoming more and more important in practice. IGRT practice helps us to visualise the target daily and correct the errors; this helps us monitor the errors more closely and keep the margins for set-up errors low. Recently, many papers have discussed the accuracy of ultrasound for IGRT and have reported good results.Reference Fuller, Thomas and Wong27, Reference Fuss, Salter and Cavanaugh30, Reference Boda-Heggemann, Mennemeyer and Wertz31 What we present here are results of our observed shifts, our use of immobilisation systems and proposed surrogates for matching soft tissues using CBCT scans for IGRT. In our short experience, we realised that longitudinal correction should be done first followed by matching in the lateral and vertical directions. This is because of the fact that maximum shifts are seen in the longitudinal direction; hence, if matching would be performed first in other directions, it would probably have to be redone after longitudinal correction.
This study was performed to analyse the set-up errors, and for this purpose the 12th rib and the coeliac trunk were found to be particularly useful surrogates apart from the vertebral bodies. The 12th rib is easy to localise and was found to be relatively stable despite respiratory movements. This marker becomes more relevant in the light of the fact that the target is mostly retroperitoneal in location. These surrogates were chosen because the available CBCT images around the isocentre for treatment of carcinoma of gallbladder were difficult to analyse for longitudinal shifts because of the relative absence of specific bony landmarks in that area. This was because the maximum length of acquisition of the CBCT scan is 16 cm. The vertebral bodies being similar in anatomy were not very reliable. Therefore, the relatively stable and relevant landmarks of 12th rib and coeliac trunk were used. To localise the 12th rib, we scrolled down the planning CT images till the time the ribs stop sprouting from the vertebrae; the 12th rib is very small as compared with other ribs and is easily identifiable (Figure 1). The same activity is repeated in CBCT images and the images are matched visually so that the head of the 12th rib is in the same slice. To localise the coeliac trunk for matching with CBCT, we found that locating the coeliac trunk first on the planning CT scan was helpful because the images in the planning CT scan are better in resolution so that the operator can have a mental picture of what to look for in the CBCT images. The coeliac trunk was located by scrolling down on the CT images and the first large vessel that sprouts out from the aorta is the coeliac trunk (Figure 2). As described for the 12th rib, the coeliac trunk is visually examined to be in the same slice, hence verifying them for correctness in longitudinal direction. For correction in the lateral and vertical directions, vertebral bodies and spinal canal were found to be useful. The clips left in the operated bed created artefacts in the CBCT images and are always mobile with respiration, and hence were not found to be a reliable surrogate for matching in any direction. A similar observation has been published in a report by Perkins et al.,Reference Perkins, Fox, Elder, Kooby, Staley and Landry32 in which the use of kVps for upper abdominal malignancies is discussed. We matched the paired kV portal images (kVps) first longitudinally and then laterally in the AP image followed by correction in the vertical direction in the lateral image. We realised that both anteroposterior and lateral films require separate window level settings for proper evaluation, and thus care was taken to change windowing during matching. The automatic matching tool was not found useful for matching kVps.
Other authors have also described the use of surrogates in upper abdominal malignancies. The structures used along with BAT device (B-mode Acquisition and targeting device, Nomos, Cranberry Township, PA, USA) are liver outline, coeliac, mesenteric portal and other abdominal vessels, and pancreas.Reference Fuller, Thomas and Wong27 Bony structures are used for matching when working on paired kV portals.Reference Perkins, Fox, Elder, Kooby, Staley and Landry32 Heggeman et al.Reference Boda-Heggemann, Mennemeyer and Wertz31 in their report have discussed the use of CBCT for IGRT in upper abdominal malignancies; they have used CBCTs to correct their images obtained using BAT. The translational corrections in patients showing good sonographic quality ranged between 0·1 and 0·93 mm in all directions, and in those with satisfactory quality ranged between 0·64 and 1·76 mm in all directions. They have considered images obtained by CBCT as final.Reference Boda-Heggemann, Mennemeyer and Wertz31
The process of IGRT using CBCT or kVps was found to be quite simple and less time-consuming. On an average, CBCT acquisition takes 1 minute and matching takes another 1 or 2 minutes. The CBCT/kVps were obtained by the technologist in our department, and the radiation oncologist was called to the console for online corrections during the course of acquisition. IGRT using CBCT does not require any patient selection or understanding the patients for individual anatomy; the learning curve for CBCT matching is also very steep. One more advantage of CBCT/kVps-based IGRT is that the images and matching can be audited using off-line review. CBCT images, however, are of lower resolution than regular CT images. To practice CBCT-based IGRT, the operator has to get used to identifying and matching surrogates.
These results show that our mean error in each direction was within 3 mm and the associated standard deviation was within 5·1 mm, with errors in longitudinal directions being the maximum. The PTV margins hence calculated are summarised in Table 2. As commonly expected, PTV margins in the longitudinal direction are more than the other directions. The summary of results reported by other authors using paired kV portals,Reference Perkins, Fox, Elder, Kooby, Staley and Landry32 BAT localisation systemReference Fuller, Thomas and Wong27, Reference Fuss, Salter and Cavanaugh30, Reference Boda-Heggemann, Mennemeyer and Wertz31 can be seen in Table 3. As it can be seen, the results reported previously are neither consistent with each other nor with our results. The number of publications specifically addressing the issues of CBCT-based IGRT in upper abdominal tumours is limited because the experience is still growing.
Summary of reported shifts + SD in published reports

Note: Our results have been reported in mm for comparison with other reports
Abbreviation: SD, standard deviation.
It is also worthwhile to discuss the immobilisation system that was used for our patients. We used an all-in-one board along with blue cushions with extensions and armrest as suited to the patient. Along with the above, either a duly indexed knee support or a vaccusion was used (Figure 3). Very few reports have discussed immobilisation systems for upper abdominal malignancies. We found our system to be quite useful in terms of patient comfort and reproducibility. Table 4 summarises the maximum and minimum shifts seen in our data; shifts >0·5 cm are also tabulated. We found that with our immobilisation technique shifts of >0·5 cm were seen in 35% of observations in longitudinal directions and only 0% and 9% in vertical and lateral directions, respectively. The report by Perkins et al.Reference Perkins, Fox, Elder, Kooby, Staley and Landry32 discusses the same and they found the shifts to be >0·5 cm in 27·5%, 24·6% and 29·7% in the longitudinal, vertical and lateral directions, respectively.
Set-up photo of a patient. The all-in-one board is used along with a TA sponge with armrest and hand grip. The knee rest is duly indexed. Over this, a thermoplastic cast is made.

The maximum and minimum shifts seen in our data along with the number of instances when shifts are >0·5 cm

For these reported patients treated, we had kept a margin of 1·5 cm in the longitudinal direction and a margin of 1 cm in both lateral and vertical directions. The margin of error calculated thus is well within these limits.
One shortfall of these data is the low number of patients reported; the number although low gives us information regarding 32 sessions, which can be of guidance to begin with. This study helps us understand the set-up errors associated with our method of immobilisation in a group of patients receiving similar treatment. Although these data encourage us to reduce margins for set-up errors, we shall continue to monitor the day-to-day errors with CBCT. We can see in our data that even with the same immobilisation system used consistently in all patients the resultant errors are different for each. This points towards the limitation of immobilisation systems in keeping the error within predictable limits. This highlights the importance and need for image guidance in delivering conformal radiation therapy. This study has helped us establish an IGRT process at our department with a consistent use of surrogates. As discussed above, because of a limited span of 16 cm around the isocentre for CBCT scanner, the acquired images have few bony landmarks. This study helps us propose useful surrogates. We feel inspired to perform a similar study with more number of patients to deliver more reliable results.
Future directions
The information and data about margins need to be addressed especially in terms of the immobilisation system used. The workflow of IGRT needs to be more and more streamlined to make the methodology and results more objective. This might be possible by undertaking studies on a larger number of patients, which are prospective in nature. Such mature data shall help formulate guidelines in the future.
Conclusions
IGRT for carcinoma of gallbladder can be done using CBCT and kVps in a reliable way. The surrogates used must be reliable and relevant to the target volume. The margin of errors on a daily basis, which incorporate components of both random and systematic errors, can be kept low when good immobilisation systems are used. More and more experience is needed both in terms of day-to-day understanding of IGRT processes and specifically designed research work to further understand the nuances of IGRT.
Acknowledgements
No financial aid was received in any form to carry out this study.
Conflict of interest
Do not exist.